Нисък резултат за ензима GAA поражда съмнение за болест на Помпе, но само скринингът не може да я потвърди. Повторното изследване в подходяща проба и генетичният анализ на GAA помагат да се разграничат истинският дефицит, носителството и псевдодефицитът.

Основни изводи
- Ниска активност на ензима GAA е сигнал за последващо изследване, а не диагноза; 1 отклонение в изсушена кръвна капка изисква потвърждение под ръководството на специалист.
- Референтни стойности зависят от пробата и метода; nmol/h/mL не могат да се сравняват директно с nmol/h/mg протеин.
- Остатъчната ензимна активност често е под 1% при класическата инфантилна болест на Помпе, но тази стойност не е универсален праг за скрининг.
- Псевдодефицитът може да понижи лабораторно измерената активност на GAA, без да причинява болест на Помпе; повторението със същия метод може отново да даде нисък резултат.
- Изследването на гена GAA търси болестотворни варианти, засягащи и двете копия на гена; 2 варианта трябва да бъдат интерпретирани с оглед на класификацията и фазата.
- Варианти с неясно значение не установяват болест на Помпе; 1 или 2 варианта с неясно клинично значение изискват допълнителни доказателства.
- Риск за семейството е 25% за засегнато дете при всяка бременност, когато и двамата родители носят причиняващ заболяването вариант на GAA.
- Спешна оценка е необходима за кърмаче с ниска активност на GAA и затруднено хранене, изразена слабост или съмнение за засягане на сърцето; не чакайте рутинно повторно изследване.
Какво всъщност означава нисък резултат за ензима GAA?
A Изследване за болест на Помпе показващ ниска активност на GAA означава, че лабораторията е измерила намалена функция на киселата алфа-глюкозидаза при условията на своя анализ. Това не доказва болест на Помпе: 1 нисък резултат от скрининга може да се дължи на истински дефицит, псевдодефицит, припокриване със стойностите при носителство или проблем с пробата.
Активността на GAA измерва функцията на ензима, а не просто количеството наличен ензимен протеин. Първите 3 неща, които трябва да проверите, са видът на пробата, мерните единици и диагностичният праг на лабораторията; резултат, описан като нисък без тези подробности, не може да бъде надеждно интерпретиран спрямо стойност, намерена онлайн.
Причината за изследването променя значението на положителния скринингов резултат. Новородено, установено чрез популационен скрининг, и 45-годишен човек с прогресираща слабост в областта на тазобедрените стави имат различна изходна вероятност за болест на Помпе, дори ако отчетените им стойности на ензима съвпадат; затова симптомите и прегледът трябва да се разглеждат заедно с лабораторния резултат.
Положителен скринингов резултат не означава потвърдена болест. Ако 2 лаборатории използват различни субстрати или методи за подготовка на пробите, числените им резултати може да се разминават, без нито една лаборатория да е допуснала грешка; попитайте дали следващият преглед е за ново скринингово измерване или за действително потвърдителен ензимен анализ.
Кантести е един AI кръвен анализатор което може да помогне при подреждането на резултатите за GAA заедно с рутинните лабораторни находки, но не може да установи диагноза болест на Помпе въз основа на 1 стойност, отбелязана като отклонение. Нашата информация за компанията обяснява организацията на услугата; при съмнение за наследствен ензимен дефицит все пак е необходим специалист по метаболитни или нервно-мускулни заболявания.
Защо дефицитът на GAA причинява проблеми с мускулите и сърцето?
Болестта на Помпе се дължи на дефицит на лизозомна кисела алфа-глюкозидаза, ензим, който разгражда гликогена в клетъчните отделения за рециклиране. GAA действа върху глюкозните връзки алфа-1,4 и алфа-1,6; недостатъчната активност води до натрупване на гликоген, особено в скелетните и сърдечния мускул.
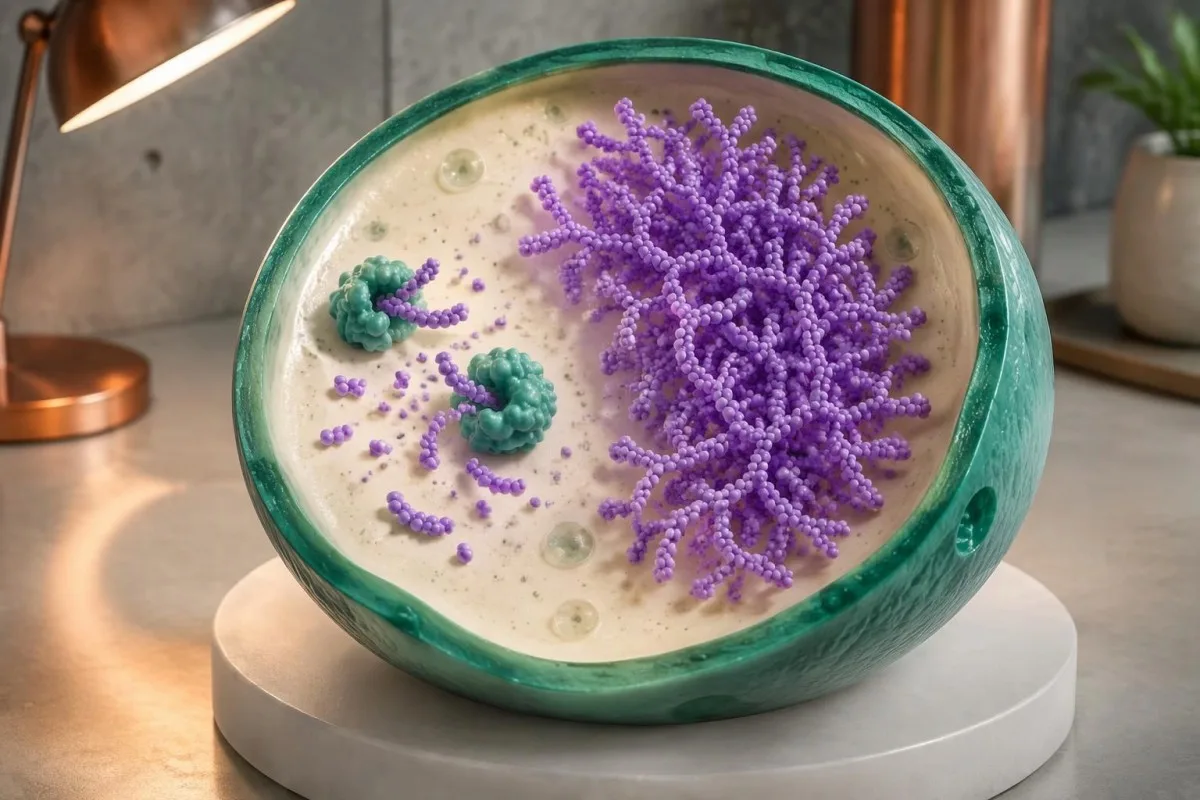
При класическата инфантилна форма на болестта на Помпе активността на GAA в диагностични тъканни анализи често е под 1% от нормалната. При късно проявяващата се форма може да се запази по-висока активност, понякога приблизително 2–40% при определени анализи; тези описателни диапазони се припокриват с ограниченията на анализите и не бива да заместват валидираната диагностична интерпретация на лабораторията.
Насоките на Kishnani et al. от 2006 г. в Genetics in Medicine описват връзката между дефицита на GAA, натрупването на гликоген и мултисистемната оценка. Клиничното разграничаване не се свежда само до това дали активността е под 1%: възрастта при проява, сърдечните находки и функцията на дихателните мускули също помагат за определяне на формата и спешността на заболяването.
Рутинното изследване на глюкозата не измерва разграждането на гликогена в лизозомите. Например, възрастен в хипотетичен случай може да има глюкоза на гладно 92 mg/dL и същевременно наследствено заболяване с натрупване на гликоген в мускулите; нормалната глюкоза не доказва, че гликогенът в мускулните лизозоми се разгражда нормално.
Другите лизозомни заболявания засягат различни ензими и гени, затова техните прагове не могат да се прилагат при изследване за болест на Помпе. Нашето обяснение на потвърждаването на ензимния дефицит при болест на Gaucher илюстрира по-общия работен процес от ензимното изследване до генетичния анализ и показва защо ензимният анализ за едно заболяване не може да замести този за друго.
Има ли референтни стойности за активността на ензима GAA?
There is no single universal normal range for GAA enzyme activity. Dried blood spots, leukocytes and cultured fibroblasts use different preparations and reporting units; a number expressed in nmol/h/mL cannot be directly compared with a result expressed in nmol/h/mg protein.

A screening cutoff separates samples needing follow-up from samples passing that screen. It does not necessarily separate affected people from unaffected people with complete accuracy; laboratories may use different fluorometric or tandem mass spectrometry methods, and 2 screening programs may therefore select different recall thresholds.
For a clearly hypothetical example, suppose a laboratory uses a DBS screening cutoff of 1.5 nmol/h/mL and reports 0.7 nmol/h/mL. The result is below that invented laboratory threshold, but dividing 0.7 by 1.5 gives 47% of the cutoff—not 47% of normal enzyme activity and not a severity score.
The lower limit of detection is different from the clinical cutoff. A report reading less than 0.1 in its stated units may mean the method cannot quantify lower activity reliably; it does not prove absolute absence of enzyme, and repeating measurements close to that analytical floor may produce proportionally large variation.
Screening performance also depends on prevalence. In a hypothetical group with 10 true-positive and 100 false-positive results, only about 9% of positive screens represent disease; those invented counts are not Pompe screening statistics, but explain why качествени спрямо количествени резултати require different interpretation.
| Ниво | Диапазон | Какво означава |
|---|---|---|
| Passes hypothetical screen | ≥1.5 nmol/h/mL | Illustrative DBS cutoff only; not a universal normal range and not an absolute exclusion in a symptomatic person. |
| Below hypothetical cutoff | <1.5 nmol/h/mL | Illustrative follow-up threshold only; true deficiency, pseudodeficiency and specimen effects still need separation. |
Защо изследването на GAA се повтаря в друг вид проба?
Repeat GAA testing checks whether low activity is reproducible and whether specimen quality or assay interference explains it. Confirmation usually moves beyond 1 screening card to a fresh, appropriately handled specimen, often with GAA measurement in leukocytes or another specialist-selected cell preparation.

Heat, humidity and inadequate drying can reduce enzyme activity in a dried blood spot. A low result after 2 days of poorly controlled transport may deserve a fresh collection, but transport history cannot be used to dismiss a result automatically; the laboratory should assess card quality and its stability requirements.
Acarbose is used in some GAA assay methods to suppress interfering maltase-glucoamylase activity. That interference can make measured activity appear higher and potentially obscure deficiency; checking how a laboratory isolates GAA activity can therefore matter more than obtaining a second number with the same unresolved methodological limitation.
Two low DBS results still do not automatically confirm Pompe disease. Pseudodeficiency can reproduce across repeated measurements, including some confirmatory methods; when enzyme and genetic findings disagree, a specialist laboratory may recommend cultured fibroblast testing or additional molecular investigation rather than simply ordering a third screening card.
Give the laboratory the dates of collection, recent transfusions or transplantation, and any enzyme replacement treatment already received. Our guide to интерференция, свързана с качеството на пробата explains the general distinction between biological findings and specimen problems; GAA testing has its own handling rules, so do not import another test's redraw interval.
По какво псевдодефицитът на GAA се различава от болестта на Помпе?
GAA pseudodeficiency means an inherited variant lowers measured enzyme activity without causing the glycogen-storage disorder Pompe disease. Two commonly discussed variants are c.1726G>A, p.Gly576Ser, and c.2065G>A, p.Glu689Lys; their interpretation depends on the complete genotype and the assay used.
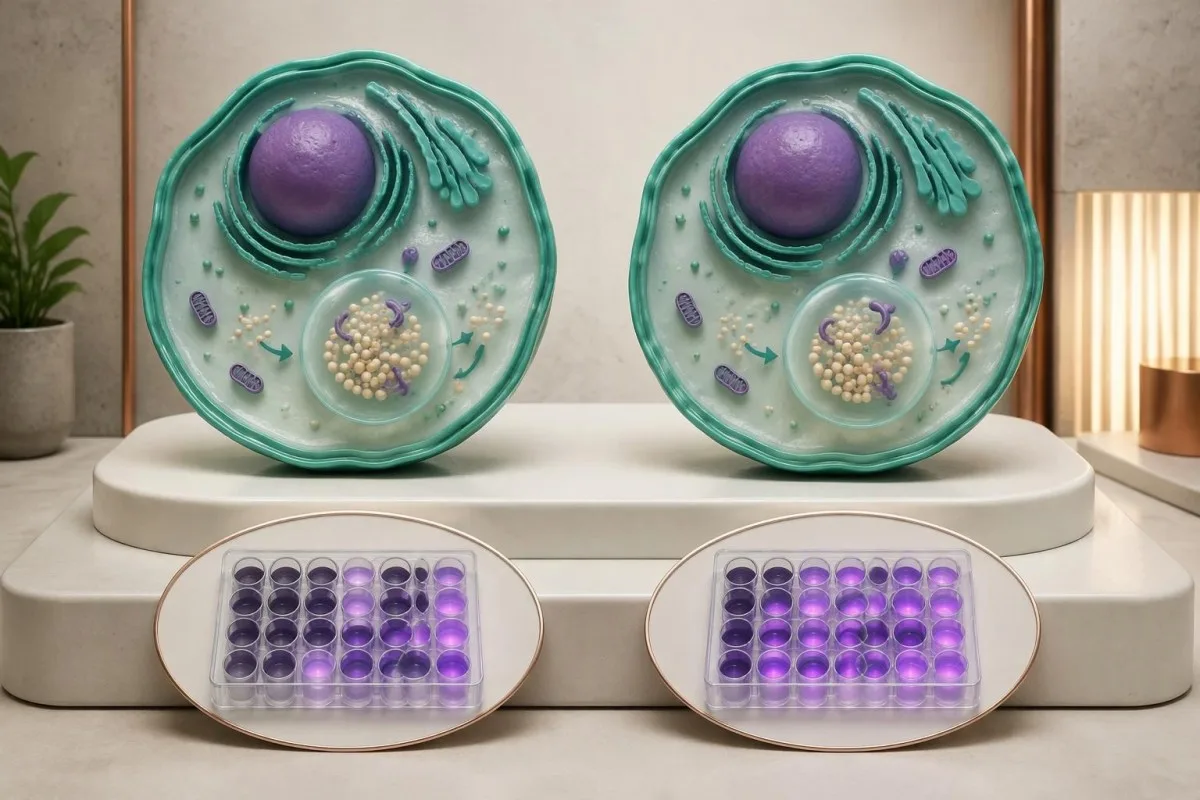
Pseudodeficiency is a biochemical testing issue, not an early stage of Pompe disease. A person with only pseudodeficiency variants does not need Pompe treatment because of 1 low activity result; the specialist must first verify that disease-causing variants or another explanation have not been missed.
The p.Gly576Ser and p.Glu689Lys variants are often found together on 1 gene copy and are particularly relevant in some East Asian ancestry populations. Ancestry changes how often laboratories encounter this pattern, but cannot establish or exclude pseudodeficiency in an individual; people from other backgrounds can carry these variants too.
Pseudodeficiency can remain low on repeat enzyme testing. The practical distinction is whether the complete biochemical and genetic evidence supports disease-causing GAA deficiency, not whether a second result falls below an arbitrary percentage; specialists may compare different assay substrates or cell preparations when the pattern remains ambiguous.
Pseudodeficiency variants can also coexist with a disease-causing variant, making a short report misleading if it lists everything under mutations. Our Fabry enzyme and genetics guide shows another situation where enzyme results need genetic context, although Fabry's X-linked inheritance differs from Pompe's 2-copy recessive mechanism.
Какво трябва да търси изследването на гена GAA?
GAA gene testing investigates whether disease-causing variants affect both copies of the GAA gene. Pompe disease is autosomal recessive, and the GAA gene is located on chromosome 17; interpretation requires variant classification, adequate test coverage and, when needed, confirmation that variants affect opposite gene copies.
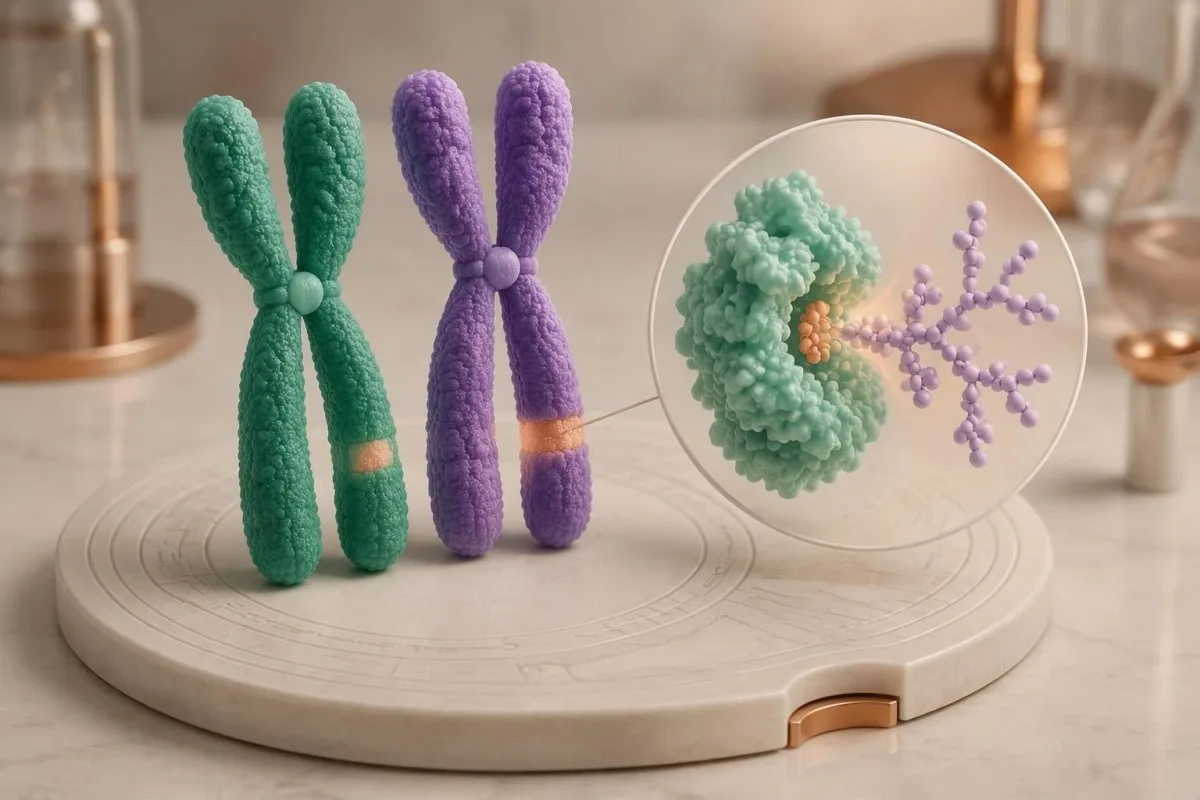
Two pathogenic or likely pathogenic GAA variants in trans support molecular confirmation of Pompe disease. In trans means the variants affect opposite gene copies; 2 variants in cis affect the same copy and do not, by themselves, demonstrate a recessive disease genotype.
Standard sequencing detects many small substitutions and insertions or deletions, but does not answer every possible genetic question. If only 1 disease-causing variant is found despite convincing enzyme deficiency, ask whether deletion/duplication analysis was included and whether poorly covered or deep intronic regions require further investigation.
A common later-onset-associated GAA variant is c.-32-13T>G, which affects splicing. Finding this variant on 1 copy does not diagnose Pompe disease, and finding it with another disease-causing variant does not precisely predict the age symptoms will begin; residual splicing and other biological factors influence presentation.
Parental testing can help establish phase when a laboratory detects 2 different variants but cannot determine their arrangement. Our guide to inherited disease genetic reports explains why inheritance and family testing matter, while the actual gene coverage and diagnostic criteria must remain specific to GAA.
Как трябва да се тълкуват патогенните, несигурните и отрицателните резултати?
A pathogenic result, a variant of uncertain significance and a negative result have different diagnostic meanings. Genetic laboratories commonly use 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign and benign; a VUS is not equivalent to a disease-causing GAA variant.

Richards et al.'s 2015 ACMG/AMP consensus established the widely used 5-category sequence-variant framework and states that a VUS should not guide clinical decision-making as though pathogenic. For Pompe evaluation, low enzyme activity can contribute evidence, but its value depends on whether pseudodeficiency and assay limitations have been addressed.
One pathogenic variant plus 1 VUS is an unresolved combination, not automatic confirmation or exclusion. Depending on the enzyme and clinical findings, specialists may investigate family segregation, RNA effects or variant-specific functional evidence; a diagnostic enzyme result may support disease even while the second molecular finding remains incompletely characterized.
A negative sequencing report means the test found no reportable variants within its scope. It does not prove that every GAA-related mechanism was examined; 1 negative limited test may warrant expanded testing when properly performed enzyme studies and the clinical pattern remain strongly suggestive.
Кантести е един Платформа за кръвни изследвания тълкуване с AI that can help separate a report's 5 classification terms from its numerical enzyme findings, without adjudicating an uncertain genotype. Our технически и клинични стандарти describe interpretation boundaries; our uncertain gene-result explanation provides a related example of why variants and diagnoses are not interchangeable.
Означава ли един вариант на GAA носителство или заболяване?
One confirmed disease-causing GAA variant usually indicates carrier status if a second disease-causing variant and diagnostic enzyme deficiency are absent. Carriers do not typically develop Pompe disease; when both parents are carriers, each pregnancy has a 25% affected, 50% carrier and 25% non-carrier probability.

Carrier enzyme values can overlap with values in unaffected people. GAA activity is therefore not a reliable standalone carrier test, and a carrier's activity should not be assumed to equal exactly 50% of a laboratory's normal mean; targeted genetic testing is generally more informative when a familial variant is known.
The 25% affected-child probability applies independently to each pregnancy when both parents carry disease-causing variants capable of producing Pompe disease together. Having 1 unaffected child does not reduce the next pregnancy's Mendelian probability, and pseudodeficiency variants should not be substituted for pathogenic variants in that calculation.
Family testing is most useful after the affected person's variants are clarified. If a symptomatic adult has only 1 identified pathogenic variant, relatives should not be reassured that the entire family question is settled until the specialist considers whether the second variant was missed by the original assay.
For a hypothetical couple, one partner carrying a pathogenic GAA variant and the other carrying only a pseudodeficiency variant does not create the same 25% Pompe risk as 2 pathogenic-variant carriers. Our carrier screening limitations guide explains why a report's coverage and residual risk deserve discussion before reproductive decisions.
Кои други лабораторни резултати подкрепят оценката за болест на Помпе?
Creatine kinase, AST, ALT and urinary glucose tetrasaccharide can support Pompe evaluation, but none confirms the diagnosis alone. Urinary glucose tetrasaccharide may be reported as Glc4 or within a Hex4 assay; these 2 report terms require method-specific interpretation rather than assumption that every laboratory measures exactly the same thing.
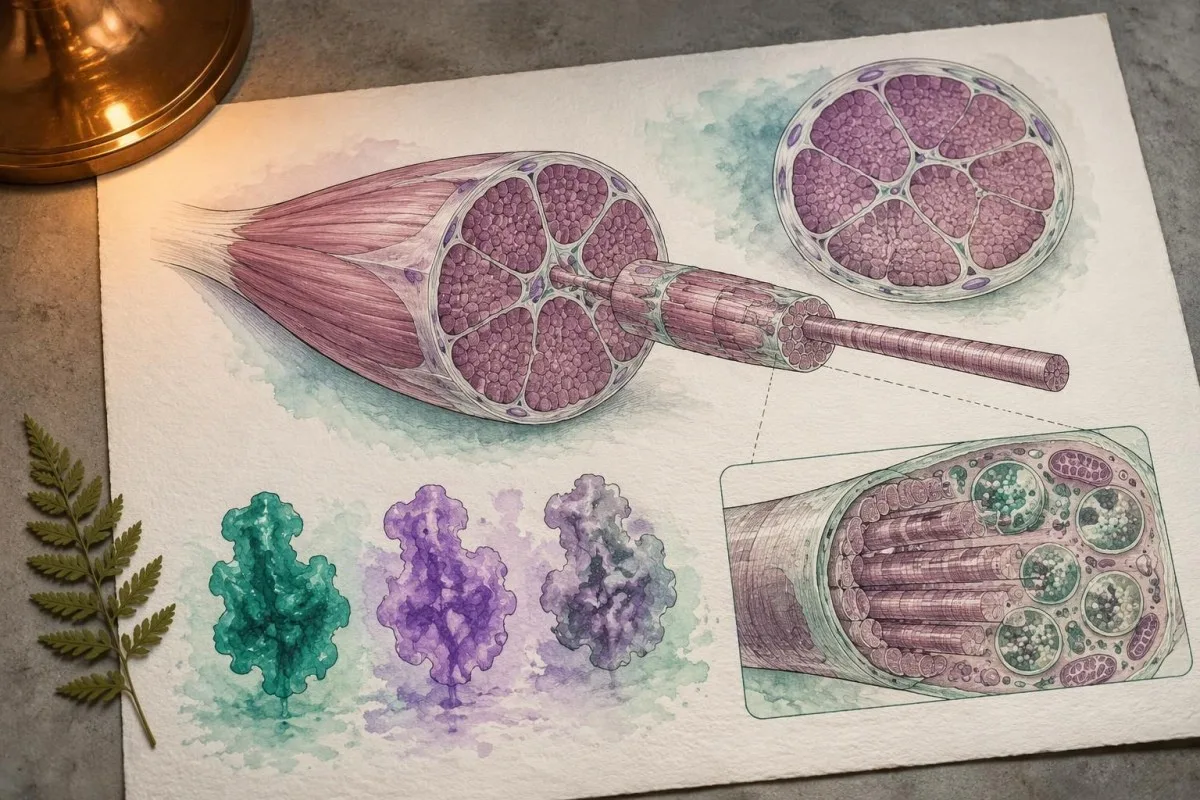
Normal CK does not exclude later-onset Pompe disease. In a hypothetical adult with progressive difficulty rising from a chair, CK of 140 U/L may fall within that laboratory's interval despite clinically meaningful weakness; the combination of symptoms and low confirmed GAA activity matters more than a reassuring CK flag.
AST and ALT can rise because of muscle involvement, not only liver disease. A hypothetical AST of 86 U/L with elevated CK and muscle weakness deserves a muscle-aware assessment; our aldolase and muscle marker guide explains why additional muscle enzymes may help characterize the pattern without identifying its cause.
Urinary Glc4 is a supportive glycogen-related biomarker, not a Pompe-specific diagnostic test. Reference limits vary with age and method, and elevation can occur in other circumstances; 1 elevated result should be interpreted alongside enzyme findings, genetics and the laboratory's creatinine-normalized units.
A falling CK or Glc4 after treatment does not automatically prove that strength or breathing has improved by the same percentage. Our discussion of AST interpretation beyond liver disease illustrates why 2 related markers can move together while still answering different questions about tissue injury and function.
Защо се оценява дишането при отклонение в теста за Помпе?
Pompe disease can weaken the diaphragm and other respiratory muscles, sometimes before obvious walking difficulty. Assessment may include seated and supine forced vital capacity, respiratory muscle pressures and sleep-related testing; a daytime oxygen saturation of 97% does not rule out overnight hypoventilation.
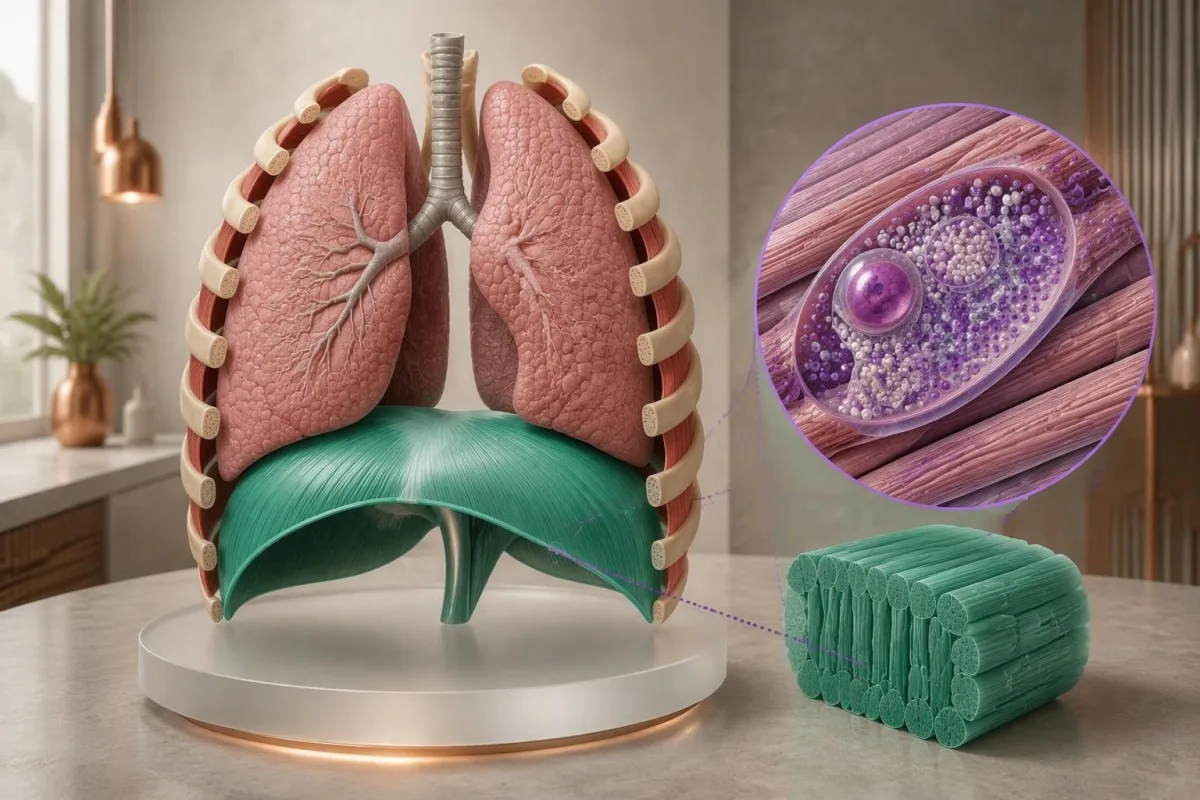
A position-related fall in vital capacity can suggest diaphragm weakness. For example, a hypothetical seated FVC of 3.0 L and supine FVC of 2.4 L represents a 20% decline; the specialist interprets that difference with technique, predicted values and symptoms, rather than treating it as a Pompe-specific cutoff.
Morning headaches, unrefreshing sleep and difficulty breathing when lying flat can justify evaluation for sleep-related hypoventilation. These symptoms do not identify Pompe disease on their own; our наръчник за тестване на задух explains why laboratory results cannot replace respiratory examination and physiological testing.
Arterial carbon dioxide is normally about 35–45 mmHg in adults, with context-dependent variation. A value above 45 mmHg indicates hypercapnia, but its urgency depends on pH, symptoms and the clinical setting; our blood gas interpretation guide explains why oxygen and carbon dioxide answer different questions.
Severe breathlessness, confusion, blue coloration or rapidly worsening weakness warrants emergency care, not an online interpretation session. A confirmed molecular result affecting 2 GAA copies does not measure current respiratory safety; clinicians need direct functional assessment to decide whether ventilation support or urgent monitoring is necessary.
Какво следва след положителен скрининг за болест на Помпе при новородено?
A positive newborn Pompe screen requires prompt specialist assessment, confirmatory enzyme testing and genetic evaluation. It does not mean every infant has Pompe disease; the immediate task is to distinguish pseudodeficiency or carrier findings from infantile disease and a later-onset-associated genotype affecting both GAA copies.

Burton et al.'s 2017 Pediatrics newborn-screening algorithms describe an initial evaluation integrating GAA confirmation, molecular testing and clinical assessment. If an infant has feeding difficulty, marked hypotonia or suspected cardiomyopathy, do not wait 2 weeks for a routine repeat appointment; the screening team should arrange urgent metabolic and cardiac evaluation.
Classic infantile Pompe disease commonly involves hypertrophic cardiomyopathy. A newborn's echocardiogram and electrocardiogram help assess risk that cannot be estimated from 1 enzyme number; absence of obvious heart symptoms at home does not replace the specialist examination after an abnormal screen.
CRIM status concerns whether cross-reactive GAA protein is present and helps specialists plan immune-risk management around enzyme replacement therapy. Less than 1% enzyme activity does not by itself establish CRIM-negative status, because an inactive protein may still be present; this is a protein-expression question, not just an activity threshold.
Later-onset-associated findings in a newborn require a monitoring plan, not an invented age-of-onset prediction. Even 2 classified disease-causing variants may not reveal when symptoms will emerge; our насоки за безопасност при използване на ИИ в педиатрията explains why pediatric results require age-specific context and clinician-led decisions.
Как специалистите изясняват противоречиви резултати от изследвания при възрастни?
Conflicting adult Pompe results are resolved by checking specimen quality, confirmatory enzyme methods, variant classification and clinical fit. One low screen plus 1 genetic finding rarely tells the whole story; specialists investigate whether the apparent conflict comes from pseudodeficiency, an incomplete molecular test or another cause of weakness.

Consider a hypothetical 52-year-old with mild fatigue, low DBS GAA activity and only the 2 commonly discussed pseudodeficiency variants. If specialist testing supports pseudodeficiency and no disease-causing genotype, the low screen does not explain the fatigue; other causes should be assessed rather than attaching a Pompe label to an incidental biochemical finding.
A second hypothetical adult has progressive hip weakness, a 20% positional FVC decline, confirmed cellular GAA deficiency and 2 pathogenic variants in trans. Together, those findings support Pompe disease; a normal routine glucose or modest CK result would not outweigh the converging biochemical, genetic and functional evidence.
Convincing enzyme deficiency with only 1 identified pathogenic variant deserves further investigation. The appropriate next step may be deletion/duplication analysis, RNA studies or another specialist assay—not automatically calling the person a carrier; the investigation should also check whether non-Pompe neuromuscular conditions better explain the examination.
Variant-related disease monitoring is not the same as predicting a person's future from their DNA. Our inherited neuromuscular risk guide offers a related family-testing perspective, but 2 conditions can differ substantially in inheritance, penetrance and treatment triggers.
Какво трябва да носите на прегледа при специалист по болестта на Помпе?
Bring the complete enzyme report, complete genetic report and a dated symptom history to a Pompe specialist appointment. Three report details are especially useful: specimen type, assay units and variant classification; screenshots showing only a red flag or the word mutation can omit information that changes the interpretation.

Ask whether confirmatory testing has already been completed and whether the laboratory measured GAA specifically in an appropriate cell preparation. If 2 variants were found, ask whether they are in trans; if only 1 was found, ask what variant types and regions the test could detect.
Do not try to raise GAA activity with supplements or diet before confirmation. No vitamin or food corrects inherited pathogenic variants affecting both GAA copies; nutrition may support general care after diagnosis, but cannot substitute for enzyme confirmation or specialist treatment planning.
Кантести е един Инструмент за анализ на кръвни изследвания с AI that can help organize report terminology and associated laboratory trends, not decide whether 2 uncertain variants establish Pompe disease. Our наръчник за проверка на източника на резултатите explains why the original document remains the reference when an automated explanation and a specialist interpretation differ.
Genetic documents can contain information relevant to relatives as well as the tested person. Before sharing 1 family member's report, check consent and remove unnecessary identifiers; Kantesti's информация за поверителността и данните describes our handling approach, while sharing results with relatives should follow a genetic counselor's guidance.
Научни публикации и ограничения при тълкуването на изследванията за болест на Помпе
Pompe test interpretation rests on disease-specific enzyme, genetic and clinical evidence—not on general laboratory publications or an AI explanation. Kantesti includes 3 directly relevant external sources below and 2 separate educational publications; the iron and coagulation publications are not evidence for diagnosing Pompe disease.
The 2006 Kishnani guideline provides disease-specific diagnostic and management context, while the 2017 Burton newborn-screening paper addresses confirmation after population screening. Their recommendations should be applied with the specialist laboratory's validated methods; neither supplies 1 universally transferable DBS enzyme cutoff for every instrument and population.
Richards et al.'s 2015 ACMG/AMP publication explains the 5-category variant framework used to distinguish pathogenic findings from uncertainty. Classification can change when new evidence becomes available, so ask the genetics service whether an unresolved result has a reanalysis pathway rather than assuming every VUS will eventually become pathogenic.
Нашият образователен ресурс публикация за изследванията на желязото addresses a different laboratory domain. The separate публикация за изследване на коагулацията also covers unrelated markers; their 2 DOI records are provided for publication transparency, not as supporting citations for GAA deficiency or pseudodeficiency.
На Kantesti стандарти за медицинско съдържание distinguish patient education from diagnosis and treatment instructions. The practical endpoint is a documented interpretation of 3 evidence streams—enzyme testing, genetic analysis and clinical assessment—with urgent care taking priority whenever infantile disease or respiratory compromise is suspected.
Често задавани въпроси
Означава ли ниската активност на ензима GAA винаги болест на Помпе?
0 Ниската активност на ензима GAA не означава непременно болест на Помпе. Един отклонен резултат от скринингово изследване може да отразява истински дефицит, псевдодефицит, разграждане на пробата или стойности на активността, припокриващи се с тези при носителство. Потвърждението изисква интерпретация от специалист на подходящ ензимен анализ, генетични находки за GAA и клиничния контекст. Повтарянето само на същия скринингов анализ може да възпроизведе псевдодефицита, вместо да разреши неяснотата му.
Какво е нормалното ниво на ензима GAA?
There is no universal normal GAA enzyme level because specimen preparation, assay substrate and reporting units differ between laboratories. A value in nmol/h/mL cannot be directly compared with a value in nmol/h/mg protein. Classic infantile Pompe disease often has less than 1% of normal activity in diagnostic tissue assays, but this is not a universal newborn-screening cutoff. Use the reference information printed on the original report and the specialist laboratory's interpretation.
Възможно ли е два ниски резултата от изследване на GAA все пак да са псевдодефицит?
Два ниски резултата от изследването на GAA все пак могат да отразяват псевдодефицит, особено когато се използват същите или сходни методи за изследване. Вариантите на псевдодефицит намаляват измерената активност, без сами по себе си да причиняват гликогеноза на Помпе. Специалистите разграничават този модел, като вземат предвид пълния генотип на GAA, характеристиките на изследването и, когато е необходимо, друга клетъчна проба или функционално изследване. Следователно два повтарящи се ниски резултата не са равнозначни на две независими потвърждения на заболяването.
Потвърждават ли два варианта в гена GAA болестта на Помпе?
0 Два варианта в GAA не потвърждават автоматично болестта на Помпе. Два патогенни или вероятно патогенни варианта в транс, засягащи противоположните копия на гена, подкрепят молекулярното потвърждение, докато два варианта в цис засягат само едно копие. Вариантите с неясно клинично значение и вариантите на псевдодефицит не могат да се приемат за установени причиняващи заболяването находки. Ензимните и клиничните данни остават особено полезни, когато класификацията или фазата не са изяснени.
Може ли нормалното ниво на CK да изключи болестта на Помпе с късно начало?
Normal CK cannot rule out late-onset Pompe disease. A hypothetical CK of 140 U/L may fall within a laboratory's reference interval despite progressive proximal weakness or diaphragm involvement. CK measures muscle injury-related enzyme release, not lysosomal GAA function. Persistent compatible symptoms deserve specialist assessment even when routine muscle markers are reassuring.
Колко спешен е положителният тест за болест на Помпе при новородено?
0 Един положителен скринингов тест за болест на Помпе при новородено изисква незабавен контакт с екипа по скрининг или метаболитни заболявания, а кърмаче със затруднено хранене, изразена хипотония или съмнение за сърдечно засягане се нуждае от спешна оценка. Една положителна скринингова карта не потвърждава диагнозата, но при съмнение за класическата инфантилна форма на заболяването не бива да се чака рутинен преглед след няколко седмици. Специалистите организират потвърдително ензимно изследване, генетична оценка и кардиологично изследване, често паралелно. Тежките затруднения в дишането или намалената реактивност налагат спешна медицинска помощ.
Какъв е рискът за децата, ако и двамата родители са носители на болестта на Помпе?
Ако и двамата родители носят болестотворни варианти на GAA, при всяка бременност има вероятност от 25% за дете със заболяването, вероятност от 50% за дете носител и вероятност от 25% за дете, което не наследява нито един от фамилните варианти. Тези вероятности важат независимо за всяка бременност. Вариантите, причиняващи псевдодефицит, не са взаимозаменяеми с патогенните варианти при това изчисление. Генетичното консултиране помага за потвърждаване на резултатите при родителите и за разясняване на възможностите за изследване.
Получете обяснение на резултатите от кръвните си изследвания
Качете лабораторния си доклад и AI на Kantesti ще обясни всеки биомаркер на разбираем език за секунди. Използва се от над 2 милиона души по света.
Референции
- Klein, T., Mitchell, S., & Weber, H. (2026). Ръководство за изследвания на желязото: TIBC, насищане на желязото и железосвързващ капацитет. Медицински изследвания с Kantesti AI. ДОИ
- Klein, T., Mitchell, S., & Weber, H. (2026). Референтни стойности за aPTT: ръководство за D-димер и протеин C при кръвосъсирването. Медицински изследвания с Kantesti AI. ДОИ
- Kishnani PS et al. (2006). Pompe disease diagnosis and management guideline. Genetics in Medicine. ДОИ PubMed
- Burton BK et al. (2017). The Initial Evaluation of Patients After Positive Newborn Screening: Recommended Algorithms Leading to a Confirmed Diagnosis of Pompe Disease. Pediatrics. ДОИ
- Richards S et al. (2015). Стандарти и насоки за интерпретация на варианти в последователността: съвместна консенсусна препоръка на Американския колеж по медицинска генетика и геномика и Асоциацията за молекулярна патология. Genetics in Medicine. ДОИ PubMed
- 2 милиона+Анализирани тестове
- 127+Държави
- 100+Езици
За медицинския екип


Сигнали за доверие E-E-A-T
Опит
Медицински преглед, воден от лекар, на работните процеси за интерпретация на лабораторни резултати.
Експертиза
Фокус в лабораторната медицина върху това как се държат биомаркерите в клиничен контекст.
Авторитетност
Медицинска рецензия от д-р Thomas Klein, с принос от д-р Sarah Mitchell и проф. д-р Hans Weber.
Надеждност
Интерпретация, основана на доказателства, с ясни последващи стъпки за намаляване на тревогата.






Медицински отказ от отговорност
Тази статия е само с образователна цел и не представлява медицински съвет. Винаги се консултирайте с квалифициран медицински специалист за решения относно диагностика и лечение.
Публикувано · Свържете се с редакционния екип
Издава се от Kantesti Ltd, регистрирана в Англия и Уелс, дружество №. 17090423, Лондон, Обединено кралство.
