GAA 효소 결과가 낮으면 폼페병이 의심되지만, 선별검사만으로는 확진할 수 없습니다. 적절한 검체로 검사를 반복하고 GAA 유전자 분석을 시행하면 실제 결핍, 보인자 상태 및 가성결핍을 구분하는 데 도움이 됩니다.

핵심 요점
- 낮은 GAA 효소 활성 은 후속 검사가 필요하다는 신호이지 진단이 아닙니다. 비정상 건조혈액반점 검사 결과가 나오면 전문의의 지시에 따른 확인 검사가 필요합니다.
- 참고 범위 은 검체와 분석법에 따라 다릅니다. nmol/h/mL은 nmol/h/mg protein과 직접 비교할 수 없습니다.
- 잔여 효소 활성 은 영아형 폼페병의 전형적인 경우 흔히 1% 미만이지만, 이 수치는 보편적인 선별검사 기준값이 아닙니다.
- 가성결핍 은 폼페병을 일으키지 않으면서 검사실 GAA 활성을 낮출 수 있습니다. 같은 분석법으로 검사를 반복하면 낮은 결과가 다시 나올 수 있습니다.
- GAA 유전자 검사 는 두 유전자 사본 모두에 영향을 미치는 질병 유발 변이를 찾습니다. 변이 2개는 분류 및 위상 해석이 필요합니다.
- 불확실한 변이 폼페이병을 확진하지 않습니다. 불확실한 의미의 변이가 1개 또는 2개 있으면 추가 근거가 필요합니다.
- 가족 위험도 양쪽 부모 모두 질병을 유발하는 GAA 변이를 보유한 경우, 매 임신마다 영향을 받은 아이가 태어날 위험은 25%입니다.
- 긴급 평가 GAA 수치가 낮고 수유 곤란, 뚜렷한 근력 저하 또는 심장 침범 의심이 있는 영아에게 필요합니다. 정기 재검사를 기다리지 마십시오.
GAA 효소 결과가 낮다는 것은 실제로 무엇을 의미하나요?
A 폼페이병 검사 낮은 GAA 활성을 보인다는 것은 검사실의 분석 조건에서 산성 알파-글루코시다아제 기능이 감소한 것으로 측정되었다는 뜻입니다. 이것만으로 폼페이병이 입증되지는 않습니다. 선별검사 결과가 낮게 나온 것은 실제 결핍, 위결핍, 보인자와 관련된 결과 중복 또는 검체 문제 때문일 수 있습니다.
GAA 활성은 효소 단백질의 양만이 아니라 효소 기능을 측정합니다. 먼저 확인할 세 가지 사항은 검체 종류, 측정 단위, 검사실의 판정 기준치입니다. 이러한 세부 정보 없이 낮다고만 기술된 결과는 온라인에서 찾은 수치와 신뢰성 있게 비교해 해석할 수 없습니다.
검사 이유에 따라 양성 선별검사의 의미가 달라집니다. 인구 선별검사에서 발견된 신생아와 진행성 고관절 근력 저하가 있는 45세 성인은 보고된 효소 수치가 같더라도 폼페이병의 사전 확률이 다릅니다. 따라서 증상과 진찰 소견을 검사실 결과와 함께 살펴봐야 합니다.
선별검사 양성은 질병 양성과 같은 의미가 아닙니다. 두 검사실이 서로 다른 기질이나 검체 전처리 방법을 사용하면 어느 쪽도 오류가 없는데 수치가 다르게 나올 수 있습니다. 다음 진료가 또 다른 선별검사를 위한 것인지, 실제 확진용 효소 검사인지 문의하십시오.
칸테스티는 AI 혈액검사 분석기 GAA 보고서를 일반적인 검사실 소견과 함께 정리하는 데 도움이 될 수 있지만, 표시된 수치 1개만으로 폼페이병을 확진할 수는 없습니다. 당사의 회사 정보는 더 넓은 의료 AI 사명, 인증, 제품 범위를 설명합니다. 실질적인 약속은 간단합니다. 빠른 해석도 여전히 신중한 해석이어야 합니다. 서비스의 운영 체계를 설명하지만, 유전성 효소 결핍이 의심되는 경우에는 여전히 대사 또는 신경근육 전문의의 진료가 필요합니다.
GAA 결핍은 왜 근육과 심장에 문제를 일으키나요?
폼페이병은 리소좀 산성 알파-글루코시다아제의 결핍으로 발생합니다, . 이 효소는 세포 내 재활용 구획에서 글리코겐을 분해합니다. GAA는 알파-1,4 및 알파-1,6 포도당 결합에 작용합니다. 활성이 부족하면 글리코겐이 축적되며, 특히 골격근과 심장근에 축적됩니다.
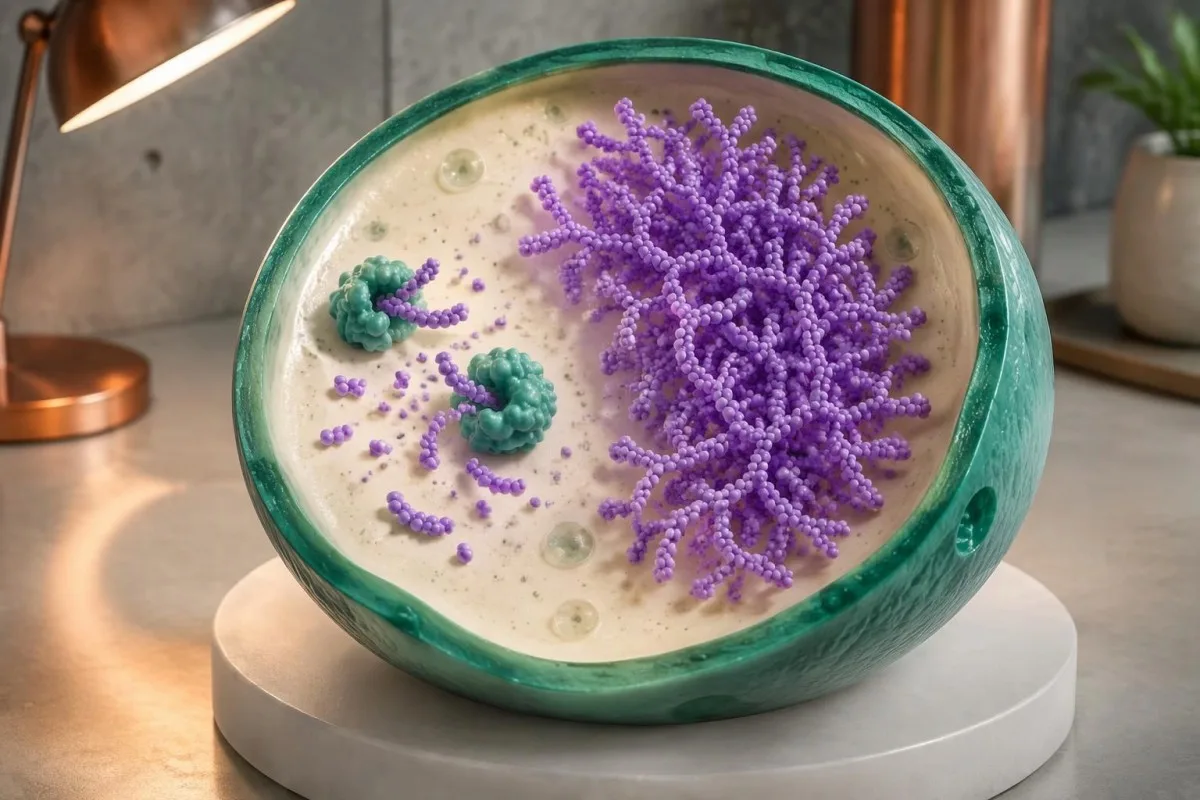
전형적인 영아형 폼페이병은 진단용 조직 검사에서 정상 GAA 활성의 1% 미만인 경우가 많습니다. 후기 발병형 질환은 활성이 더 많이 남아 있을 수 있으며, 특정 검사에서는 약 2–40%인 경우도 있습니다. 이러한 설명적 범위는 검사법의 한계와 중복되므로 검사실에서 검증한 진단적 해석을 대신해서는 안 됩니다.
Kishnani 외 연구진의 2006년 Genetics in Medicine 가이드라인은 GAA 결핍, 글리코겐 축적, 다기관 평가 사이의 연관성을 설명합니다. 임상적 구분은 활성이 1% 미만인지 여부만으로 결정되지 않습니다. 발병 연령, 심장 소견, 호흡근 기능도 질환의 유형과 긴급성을 판단하는 데 도움이 됩니다.
일반적인 포도당 검사 결과는 리소좀의 글리코겐 제거 능력을 측정하지 않습니다. 예를 들어, 가상의 성인은 공복 혈당이 92 mg/dL이더라도 유전성 근육 글리코겐 축적 질환이 있을 수 있습니다. 혈당이 정상이라고 해서 근육 리소좀 내부의 글리코겐이 정상적으로 처리된다는 뜻은 아닙니다.
다른 리소좀 질환은 관련 효소와 유전자가 다르므로, 그 질환의 기준치를 폼페이병 검사에 적용할 수 없습니다. 당사의 설명은 고셔병 효소 확진 효소 검사에서 유전학 검사로 이어지는 전반적인 절차를 보여 주는 동시에, 한 질환의 효소 분석법이 다른 질환의 검사법을 대신할 수 없는 이유를 설명합니다.
GAA 효소 활성의 정상 범위가 있나요?
There is no single universal normal range for GAA enzyme activity. Dried blood spots, leukocytes and cultured fibroblasts use different preparations and reporting units; a number expressed in nmol/h/mL cannot be directly compared with a result expressed in nmol/h/mg protein.

A screening cutoff separates samples needing follow-up from samples passing that screen. It does not necessarily separate affected people from unaffected people with complete accuracy; laboratories may use different fluorometric or tandem mass spectrometry methods, and 2 screening programs may therefore select different recall thresholds.
For a clearly hypothetical example, suppose a laboratory uses a DBS screening cutoff of 1.5 nmol/h/mL and reports 0.7 nmol/h/mL. The result is below that invented laboratory threshold, but dividing 0.7 by 1.5 gives 47% of the cutoff—not 47% of normal enzyme activity and not a severity score.
The lower limit of detection is different from the clinical cutoff. A report reading less than 0.1 in its stated units may mean the method cannot quantify lower activity reliably; it does not prove absolute absence of enzyme, and repeating measurements close to that analytical floor may produce proportionally large variation.
Screening performance also depends on prevalence. In a hypothetical group with 10 true-positive and 100 false-positive results, only about 9% of positive screens represent disease; those invented counts are not Pompe screening statistics, but explain why 정성 대 정량 결과 require different interpretation.
| 수준 | 범위 | 의미 |
|---|---|---|
| Passes hypothetical screen | ≥1.5 nmol/h/mL | Illustrative DBS cutoff only; not a universal normal range and not an absolute exclusion in a symptomatic person. |
| Below hypothetical cutoff | <1.5 nmol/h/mL | Illustrative follow-up threshold only; true deficiency, pseudodeficiency and specimen effects still need separation. |
다른 검체로 GAA 검사를 반복하는 이유는 무엇인가요?
Repeat GAA testing checks whether low activity is reproducible and whether specimen quality or assay interference explains it. Confirmation usually moves beyond 1 screening card to a fresh, appropriately handled specimen, often with GAA measurement in leukocytes or another specialist-selected cell preparation.

Heat, humidity and inadequate drying can reduce enzyme activity in a dried blood spot. A low result after 2 days of poorly controlled transport may deserve a fresh collection, but transport history cannot be used to dismiss a result automatically; the laboratory should assess card quality and its stability requirements.
Acarbose is used in some GAA assay methods to suppress interfering maltase-glucoamylase activity. That interference can make measured activity appear higher and potentially obscure deficiency; checking how a laboratory isolates GAA activity can therefore matter more than obtaining a second number with the same unresolved methodological limitation.
Two low DBS results still do not automatically confirm Pompe disease. Pseudodeficiency can reproduce across repeated measurements, including some confirmatory methods; when enzyme and genetic findings disagree, a specialist laboratory may recommend cultured fibroblast testing or additional molecular investigation rather than simply ordering a third screening card.
Give the laboratory the dates of collection, recent transfusions or transplantation, and any enzyme replacement treatment already received. Our guide to 품질 간섭에 관한 안내서에서는 explains the general distinction between biological findings and specimen problems; GAA testing has its own handling rules, so do not import another test's redraw interval.
GAA 가성결핍은 폼페병과 어떻게 다른가요?
GAA pseudodeficiency means an inherited variant lowers measured enzyme activity without causing the glycogen-storage disorder Pompe disease. Two commonly discussed variants are c.1726G>A, p.Gly576Ser, and c.2065G>A, p.Glu689Lys; their interpretation depends on the complete genotype and the assay used.
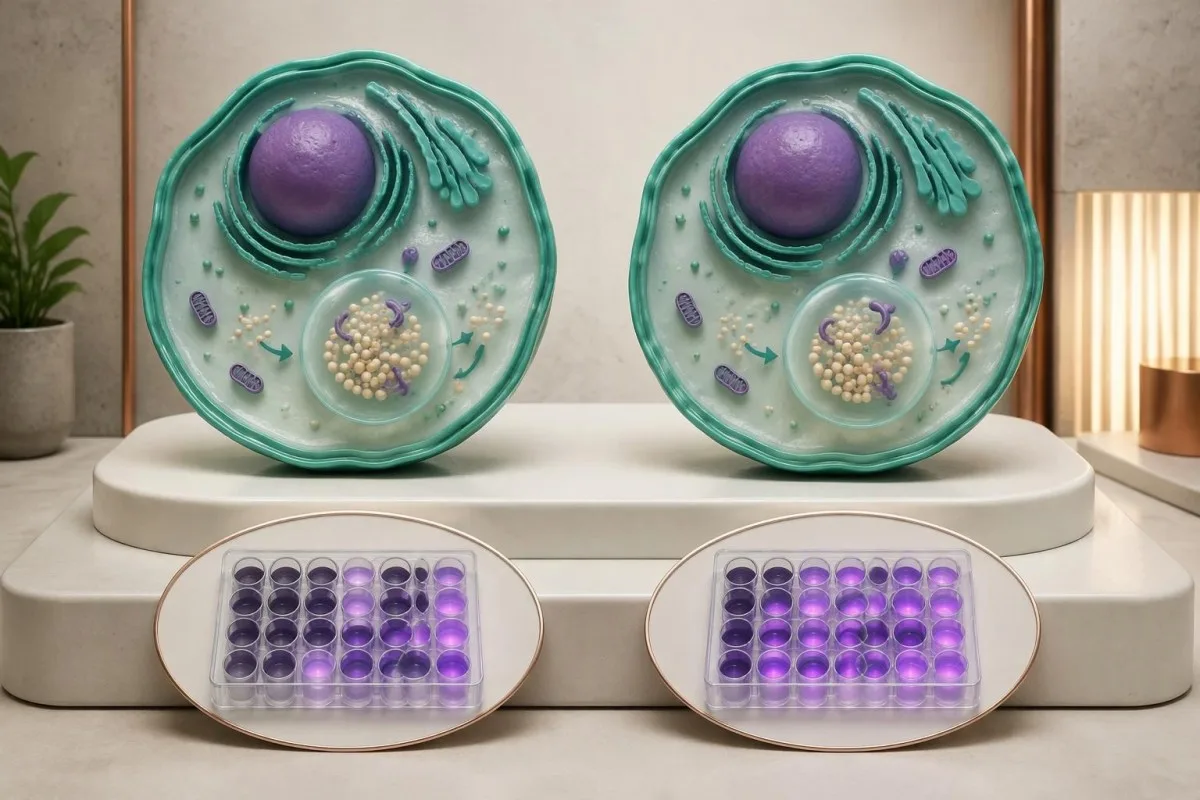
Pseudodeficiency is a biochemical testing issue, not an early stage of Pompe disease. A person with only pseudodeficiency variants does not need Pompe treatment because of 1 low activity result; the specialist must first verify that disease-causing variants or another explanation have not been missed.
The p.Gly576Ser and p.Glu689Lys variants are often found together on 1 gene copy and are particularly relevant in some East Asian ancestry populations. Ancestry changes how often laboratories encounter this pattern, but cannot establish or exclude pseudodeficiency in an individual; people from other backgrounds can carry these variants too.
Pseudodeficiency can remain low on repeat enzyme testing. The practical distinction is whether the complete biochemical and genetic evidence supports disease-causing GAA deficiency, not whether a second result falls below an arbitrary percentage; specialists may compare different assay substrates or cell preparations when the pattern remains ambiguous.
Pseudodeficiency variants can also coexist with a disease-causing variant, making a short report misleading if it lists everything under mutations. Our Fabry enzyme and genetics guide shows another situation where enzyme results need genetic context, although Fabry's X-linked inheritance differs from Pompe's 2-copy recessive mechanism.
GAA 유전자 검사에서는 무엇을 확인해야 하나요?
GAA gene testing investigates whether disease-causing variants affect both copies of the GAA gene. Pompe disease is autosomal recessive, and the GAA gene is located on chromosome 17; interpretation requires variant classification, adequate test coverage and, when needed, confirmation that variants affect opposite gene copies.
Two pathogenic or likely pathogenic GAA variants in trans support molecular confirmation of Pompe disease. In trans means the variants affect opposite gene copies; 2 variants in cis affect the same copy and do not, by themselves, demonstrate a recessive disease genotype.
Standard sequencing detects many small substitutions and insertions or deletions, but does not answer every possible genetic question. If only 1 disease-causing variant is found despite convincing enzyme deficiency, ask whether deletion/duplication analysis was included and whether poorly covered or deep intronic regions require further investigation.
A common later-onset-associated GAA variant is c.-32-13T>G, which affects splicing. Finding this variant on 1 copy does not diagnose Pompe disease, and finding it with another disease-causing variant does not precisely predict the age symptoms will begin; residual splicing and other biological factors influence presentation.
Parental testing can help establish phase when a laboratory detects 2 different variants but cannot determine their arrangement. Our guide to inherited disease genetic reports explains why inheritance and family testing matter, while the actual gene coverage and diagnostic criteria must remain specific to GAA.
병원성, 불확실성 및 음성 결과를 어떻게 해석해야 하나요?
A pathogenic result, a variant of uncertain significance and a negative result have different diagnostic meanings. Genetic laboratories commonly use 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign and benign; a VUS is not equivalent to a disease-causing GAA variant.

Richards et al.'s 2015 ACMG/AMP consensus established the widely used 5-category sequence-variant framework and states that a VUS should not guide clinical decision-making as though pathogenic. For Pompe evaluation, low enzyme activity can contribute evidence, but its value depends on whether pseudodeficiency and assay limitations have been addressed.
One pathogenic variant plus 1 VUS is an unresolved combination, not automatic confirmation or exclusion. Depending on the enzyme and clinical findings, specialists may investigate family segregation, RNA effects or variant-specific functional evidence; a diagnostic enzyme result may support disease even while the second molecular finding remains incompletely characterized.
A negative sequencing report means the test found no reportable variants within its scope. It does not prove that every GAA-related mechanism was examined; 1 negative limited test may warrant expanded testing when properly performed enzyme studies and the clinical pattern remain strongly suggestive.
칸테스티는 AI 혈액검사 결과 해석 플랫폼 that can help separate a report's 5 classification terms from its numerical enzyme findings, without adjudicating an uncertain genotype. Our 기술 및 임상 표준 describe interpretation boundaries; our uncertain gene-result explanation provides a related example of why variants and diagnoses are not interchangeable.
GAA 변이가 하나 있으면 보인자 상태인가요, 아니면 질병이 있나요?
One confirmed disease-causing GAA variant usually indicates carrier status if a second disease-causing variant and diagnostic enzyme deficiency are absent. Carriers do not typically develop Pompe disease; when both parents are carriers, each pregnancy has a 25% affected, 50% carrier and 25% non-carrier probability.

Carrier enzyme values can overlap with values in unaffected people. GAA activity is therefore not a reliable standalone carrier test, and a carrier's activity should not be assumed to equal exactly 50% of a laboratory's normal mean; targeted genetic testing is generally more informative when a familial variant is known.
The 25% affected-child probability applies independently to each pregnancy when both parents carry disease-causing variants capable of producing Pompe disease together. Having 1 unaffected child does not reduce the next pregnancy's Mendelian probability, and pseudodeficiency variants should not be substituted for pathogenic variants in that calculation.
Family testing is most useful after the affected person's variants are clarified. If a symptomatic adult has only 1 identified pathogenic variant, relatives should not be reassured that the entire family question is settled until the specialist considers whether the second variant was missed by the original assay.
For a hypothetical couple, one partner carrying a pathogenic GAA variant and the other carrying only a pseudodeficiency variant does not create the same 25% Pompe risk as 2 pathogenic-variant carriers. Our carrier screening limitations guide explains why a report's coverage and residual risk deserve discussion before reproductive decisions.
폼페병 평가를 뒷받침하는 다른 검사실 결과에는 어떤 것이 있나요?
Creatine kinase, AST, ALT and urinary glucose tetrasaccharide can support Pompe evaluation, but none confirms the diagnosis alone. Urinary glucose tetrasaccharide may be reported as Glc4 or within a Hex4 assay; these 2 report terms require method-specific interpretation rather than assumption that every laboratory measures exactly the same thing.
Normal CK does not exclude later-onset Pompe disease. In a hypothetical adult with progressive difficulty rising from a chair, CK of 140 U/L may fall within that laboratory's interval despite clinically meaningful weakness; the combination of symptoms and low confirmed GAA activity matters more than a reassuring CK flag.
AST and ALT can rise because of muscle involvement, not only liver disease. A hypothetical AST of 86 U/L with elevated CK and muscle weakness deserves a muscle-aware assessment; our aldolase and muscle marker guide explains why additional muscle enzymes may help characterize the pattern without identifying its cause.
Urinary Glc4 is a supportive glycogen-related biomarker, not a Pompe-specific diagnostic test. Reference limits vary with age and method, and elevation can occur in other circumstances; 1 elevated result should be interpreted alongside enzyme findings, genetics and the laboratory's creatinine-normalized units.
A falling CK or Glc4 after treatment does not automatically prove that strength or breathing has improved by the same percentage. Our discussion of AST interpretation beyond liver disease illustrates why 2 related markers can move together while still answering different questions about tissue injury and function.
폼페병 검사 결과가 비정상일 때 호흡을 평가하는 이유는 무엇인가요?
Pompe disease can weaken the diaphragm and other respiratory muscles, sometimes before obvious walking difficulty. Assessment may include seated and supine forced vital capacity, respiratory muscle pressures and sleep-related testing; a daytime oxygen saturation of 97% does not rule out overnight hypoventilation.
A position-related fall in vital capacity can suggest diaphragm weakness. For example, a hypothetical seated FVC of 3.0 L and supine FVC of 2.4 L represents a 20% decline; the specialist interprets that difference with technique, predicted values and symptoms, rather than treating it as a Pompe-specific cutoff.
Morning headaches, unrefreshing sleep and difficulty breathing when lying flat can justify evaluation for sleep-related hypoventilation. These symptoms do not identify Pompe disease on their own; our 호흡 곤란 검사 안내서 explains why laboratory results cannot replace respiratory examination and physiological testing.
Arterial carbon dioxide is normally about 35–45 mmHg in adults, with context-dependent variation. A value above 45 mmHg indicates hypercapnia, but its urgency depends on pH, symptoms and the clinical setting; our blood gas interpretation guide explains why oxygen and carbon dioxide answer different questions.
Severe breathlessness, confusion, blue coloration or rapidly worsening weakness warrants emergency care, not an online interpretation session. A confirmed molecular result affecting 2 GAA copies does not measure current respiratory safety; clinicians need direct functional assessment to decide whether ventilation support or urgent monitoring is necessary.
신생아 폼페병 선별검사 양성 후에는 어떤 일이 진행되나요?
A positive newborn Pompe screen requires prompt specialist assessment, confirmatory enzyme testing and genetic evaluation. It does not mean every infant has Pompe disease; the immediate task is to distinguish pseudodeficiency or carrier findings from infantile disease and a later-onset-associated genotype affecting both GAA copies.

Burton et al.'s 2017 Pediatrics newborn-screening algorithms describe an initial evaluation integrating GAA confirmation, molecular testing and clinical assessment. If an infant has feeding difficulty, marked hypotonia or suspected cardiomyopathy, do not wait 2 weeks for a routine repeat appointment; the screening team should arrange urgent metabolic and cardiac evaluation.
Classic infantile Pompe disease commonly involves hypertrophic cardiomyopathy. A newborn's echocardiogram and electrocardiogram help assess risk that cannot be estimated from 1 enzyme number; absence of obvious heart symptoms at home does not replace the specialist examination after an abnormal screen.
CRIM status concerns whether cross-reactive GAA protein is present and helps specialists plan immune-risk management around enzyme replacement therapy. Less than 1% enzyme activity does not by itself establish CRIM-negative status, because an inactive protein may still be present; this is a protein-expression question, not just an activity threshold.
Later-onset-associated findings in a newborn require a monitoring plan, not an invented age-of-onset prediction. Even 2 classified disease-causing variants may not reveal when symptoms will emerge; our 소아 AI 안전 지침 explains why pediatric results require age-specific context and clinician-led decisions.
전문의는 성인의 검사 결과가 서로 일치하지 않을 때 어떻게 판단하나요?
Conflicting adult Pompe results are resolved by checking specimen quality, confirmatory enzyme methods, variant classification and clinical fit. One low screen plus 1 genetic finding rarely tells the whole story; specialists investigate whether the apparent conflict comes from pseudodeficiency, an incomplete molecular test or another cause of weakness.

Consider a hypothetical 52-year-old with mild fatigue, low DBS GAA activity and only the 2 commonly discussed pseudodeficiency variants. If specialist testing supports pseudodeficiency and no disease-causing genotype, the low screen does not explain the fatigue; other causes should be assessed rather than attaching a Pompe label to an incidental biochemical finding.
A second hypothetical adult has progressive hip weakness, a 20% positional FVC decline, confirmed cellular GAA deficiency and 2 pathogenic variants in trans. Together, those findings support Pompe disease; a normal routine glucose or modest CK result would not outweigh the converging biochemical, genetic and functional evidence.
Convincing enzyme deficiency with only 1 identified pathogenic variant deserves further investigation. The appropriate next step may be deletion/duplication analysis, RNA studies or another specialist assay—not automatically calling the person a carrier; the investigation should also check whether non-Pompe neuromuscular conditions better explain the examination.
Variant-related disease monitoring is not the same as predicting a person's future from their DNA. Our inherited neuromuscular risk guide offers a related family-testing perspective, but 2 conditions can differ substantially in inheritance, penetrance and treatment triggers.
폼페병 전문의 진료에 무엇을 가져가야 하나요?
Bring the complete enzyme report, complete genetic report and a dated symptom history to a Pompe specialist appointment. Three report details are especially useful: specimen type, assay units and variant classification; screenshots showing only a red flag or the word mutation can omit information that changes the interpretation.

Ask whether confirmatory testing has already been completed and whether the laboratory measured GAA specifically in an appropriate cell preparation. If 2 variants were found, ask whether they are in trans; if only 1 was found, ask what variant types and regions the test could detect.
Do not try to raise GAA activity with supplements or diet before confirmation. No vitamin or food corrects inherited pathogenic variants affecting both GAA copies; nutrition may support general care after diagnosis, but cannot substitute for enzyme confirmation or specialist treatment planning.
칸테스티는 AI 기반 혈액검사 분석 도구 that can help organize report terminology and associated laboratory trends, not decide whether 2 uncertain variants establish Pompe disease. Our 보고서 출처 확인 안내 explains why the original document remains the reference when an automated explanation and a specialist interpretation differ.
Genetic documents can contain information relevant to relatives as well as the tested person. Before sharing 1 family member's report, check consent and remove unnecessary identifiers; Kantesti's 개인정보 및 데이터 관련 정보를 확인하고 describes our handling approach, while sharing results with relatives should follow a genetic counselor's guidance.
폼페병 검사 해석 관련 연구 논문 및 한계
Pompe test interpretation rests on disease-specific enzyme, genetic and clinical evidence—not on general laboratory publications or an AI explanation. Kantesti includes 3 directly relevant external sources below and 2 separate educational publications; the iron and coagulation publications are not evidence for diagnosing Pompe disease.
The 2006 Kishnani guideline provides disease-specific diagnostic and management context, while the 2017 Burton newborn-screening paper addresses confirmation after population screening. Their recommendations should be applied with the specialist laboratory's validated methods; neither supplies 1 universally transferable DBS enzyme cutoff for every instrument and population.
Richards et al.'s 2015 ACMG/AMP publication explains the 5-category variant framework used to distinguish pathogenic findings from uncertainty. Classification can change when new evidence becomes available, so ask the genetics service whether an unresolved result has a reanalysis pathway rather than assuming every VUS will eventually become pathogenic.
당사의 교육 자료는 철(iron) 검사 연구 addresses a different laboratory domain. The separate 응고 검사 논문 also covers unrelated markers; their 2 DOI records are provided for publication transparency, not as supporting citations for GAA deficiency or pseudodeficiency.
Kantesti의 의료 콘텐츠 표준 distinguish patient education from diagnosis and treatment instructions. The practical endpoint is a documented interpretation of 3 evidence streams—enzyme testing, genetic analysis and clinical assessment—with urgent care taking priority whenever infantile disease or respiratory compromise is suspected.
자주 묻는 질문
낮은 GAA 효소 활성은 항상 폼페병을 의미하나요?
낮은 GAA 효소 활성도가 항상 폼페병을 의미하는 것은 아닙니다. 비정상 선별검사 결과는 실제 결핍, 가성결핍, 검체 분해 또는 보인자 관련 활성도와의 중복을 반영할 수 있습니다. 확진을 위해서는 적절한 효소 분석법, GAA 유전자 검사 결과 및 임상적 맥락에 대한 전문의의 해석이 필요합니다. 동일한 선별검사만 반복하면 문제를 해결하기보다 가성결핍이 다시 나타날 수 있습니다.
정상적인 GAA 효소 수치는 얼마인가요?
There is no universal normal GAA enzyme level because specimen preparation, assay substrate and reporting units differ between laboratories. A value in nmol/h/mL cannot be directly compared with a value in nmol/h/mg protein. Classic infantile Pompe disease often has less than 1% of normal activity in diagnostic tissue assays, but this is not a universal newborn-screening cutoff. Use the reference information printed on the original report and the specialist laboratory's interpretation.
GAA 검사 결과가 두 번 모두 낮아도 여전히 가성 결핍일 수 있나요?
GAA 검사 결과가 두 차례 낮더라도, 특히 동일하거나 유사한 검사 방법을 사용한 경우에는 여전히 위결핍을 반영할 수 있습니다. 위결핍 변이는 자체적으로 폼페병(글리코겐 축적 질환)을 일으키지 않으면서 측정된 효소 활성을 낮춥니다. 전문가는 전체 GAA 유전자형과 검사 특성을 확인하고, 필요한 경우 다른 세포 준비물이나 기능 검사를 통해 이러한 양상을 구별합니다. 따라서 반복 측정에서 두 번 낮게 나온 수치가 질병을 독립적으로 두 차례 확인한 것과 동등한 것은 아닙니다.
두 가지 GAA 유전자 변이가 폼페병을 확진하나요?
두 GAA 변이가 있다고 해서 폼페병이 자동으로 확진되는 것은 아닙니다. 서로 반대쪽 유전자 사본에 위치한 병원성 또는 병원성 가능성이 높은 변이 두 개는 분자적 확진을 뒷받침하지만, 동일한 유전자 사본에 위치한 변이 두 개는 한 사본에만 영향을 미칩니다. 임상적 의미 불확실 변이와 위결핍 변이는 확립된 질병 유발 소견으로 간주할 수 없습니다. 변이 분류 또는 위상이 확인되지 않은 경우 효소 및 임상적 근거가 특히 유용합니다.
정상 CK 수치로 후기 발병형 폼페병을 배제할 수 있나요?
Normal CK cannot rule out late-onset Pompe disease. A hypothetical CK of 140 U/L may fall within a laboratory's reference interval despite progressive proximal weakness or diaphragm involvement. CK measures muscle injury-related enzyme release, not lysosomal GAA function. Persistent compatible symptoms deserve specialist assessment even when routine muscle markers are reassuring.
신생아 폼페병 검사에서 양성 결과가 나오면 얼마나 긴급한가요?
신생아 폼페병 검사에서 양성이 나오면 선별검사팀 또는 대사질환팀에 즉시 연락해야 하며, 수유 곤란, 현저한 근긴장 저하 또는 심장 침범이 의심되는 영아는 긴급 평가를 받아야 합니다. 선별검사 카드 한 건의 양성 결과만으로 진단이 확정되는 것은 아니지만, 전형적인 영아형 질환이 의심되면 몇 주 뒤의 정기 진료까지 기다려서는 안 됩니다. 전문의들은 확진을 위한 효소 검사, 유전학적 평가 및 심장 평가를 준비하며, 이들 검사는 흔히 동시에 진행됩니다. 심한 호흡 곤란이나 반응 저하는 응급 진료가 필요합니다.
부모 모두 폼페병 보인자라면 자녀에게 위험은 얼마나 되나요?
0 각 부모가 모두 질병 유발 GAA 변이를 보유한 경우, 임신할 때마다 질환이 있는 아이가 태어날 확률은 25%, 보인자 아이가 태어날 확률은 50%, 가족성 변이를 어느 것도 물려받지 않는 아이가 태어날 확률은 25%입니다. 이러한 확률은 모든 임신에 독립적으로 적용됩니다. 이 계산에서 유사결핍 변이는 병원성 변이와 같은 것으로 간주할 수 없습니다. 유전 상담은 부모의 검사 결과를 확인하고 검사 선택지를 설명하는 데 도움이 됩니다.
혈액검사 결과 보는법
검사실 보고서를 업로드하면 Kantesti의 AI가 몇 초 안에 각 바이오마커를 쉬운 말로 설명합니다. 전 세계 200만 명 이상이 사용하고 있습니다.
참고 자료
- Klein, T., Mitchell, S., & Weber, H. (2026). 철 검사 안내: TIBC, 철 포화도 및 결합능. Kantesti AI 의학 연구. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT 정상 범위: D-Dimer, Protein C 혈액 응고 안내서. Kantesti AI 의학 연구. DOI
- Kishnani PS et al. (2006). Pompe disease diagnosis and management guideline. 의학 유전학. DOI 퍼브메드
- Burton BK et al. (2017). The Initial Evaluation of Patients After Positive Newborn Screening: Recommended Algorithms Leading to a Confirmed Diagnosis of Pompe Disease. Pediatrics. DOI
- Richards S 외 (2015). 염기서열 변이 해석을 위한 표준 및 지침: 미국의학유전학·유전체학회와 분자병리학회의 공동 합의 권고. 의학 유전학. DOI 퍼브메드
- 200만+분석한 검사
- 127+국가
- 100+언어
의료진 소개


E-E-A-T 신뢰 신호
경험
의사가 주도하는 검사 해석 워크플로 임상 검토.
전문적 지식
임상 맥락에서 바이오마커가 어떻게 거동하는지에 대한 검사실 의학 중심.
권위
Thomas Klein 박사의 의학적 검토를 거쳤으며, Sarah Mitchell 박사와 Hans Weber 교수의 기여가 있었습니다.
신뢰성
경고를 줄이기 위한 명확한 후속 경로가 포함된 근거 기반 해석.






의학적 면책 조항
이 글은 교육 목적만을 위한 것이며 의학적 조언을 구성하지 않습니다. 진단 및 치료 결정에는 항상 자격을 갖춘 의료 전문가와 상담하세요.
게시됨 · 편집팀에 문의
Kantesti Ltd 발행, 잉글랜드 및 웨일스에 등록된 회사, 회사 번호. 17090423, 런던, 영국.
