
Three tests answer different questions: enzyme function, substrate accumulation, and inherited cause. A reassuring enzyme result can still miss Fabry disease in women.

Key takeaways
- Fabry disease test interpretation combines alpha-galactosidase A activity, lyso-Gb3, and GLA genetic findings; no single screening number answers every diagnostic question.
- Alpha-galactosidase A activity is typically below 1% of mean normal activity in males with classic Fabry disease, although later-onset forms can retain more activity.
- Women with Fabry disease can have normal enzyme activity because different cells express different X chromosomes; normal enzyme activity does not exclude the diagnosis.
- Lyso-Gb3 supports evidence of substrate accumulation, but normal concentrations do not exclude Fabry disease, particularly in women and some later-onset presentations.
- GLA gene testing reports one of 5 standard variant classifications; pathogenic and likely pathogenic findings have a different meaning from a variant of uncertain significance.
- A GLA VUS does not confirm Fabry disease and should not, by itself, determine disease-specific treatment or label relatives as affected.
- Family inheritance is X-linked: a heterozygous mother has a 50% chance of transmitting her GLA variant in each pregnancy.
- Kidney monitoring should include urine albumin-to-creatinine ratio as well as eGFR; albuminuria can appear while eGFR remains above 90 mL/min/1.73 m².
How does a Fabry disease test establish the diagnosis?
A Fabry disease test combines alpha-galactosidase A activity, lyso-Gb3, and GLA genetic testing to assess enzyme function, substrate accumulation, and inherited cause. Normal enzyme activity can miss Fabry disease in women, and a GLA variant of uncertain significance does not confirm diagnosis.

Fabry disease results from disease-causing changes in the GLA gene, which reduce the function of the lysosomal enzyme alpha-galactosidase A and permit accumulation of globotriaosylceramide, also called Gb3. These 3 diagnostic layers are connected but not interchangeable: a genetic finding identifies a potential cause, whereas an enzyme assay measures function in the particular specimen tested.
The starting test depends partly on sex chromosome biology and family history, rather than symptoms alone. In a male with suspected Fabry disease, clinicians commonly assess enzyme activity and confirm the molecular cause; in a woman or anyone with a known familial variant, GLA testing should not be withheld because 1 enzyme result is normal.
Kantesti is an AI blood test analyzer that can help explain the reported values and units across these 3 test types, without replacing specialist diagnosis or genetic variant classification. Our 회사 소개 explains the organization behind the service; clinical genetics or a metabolic disease team should resolve discordant findings before they become a lifelong diagnostic label.
What does low alpha-galactosidase A activity mean?
낮은 alpha-galactosidase A activity indicates reduced enzyme function in the tested specimen, but interpretation requires the specimen type and laboratory method. Males with classic Fabry disease typically have less than 1% of mean normal activity; later-onset disease can retain measurable activity.

An alpha-galactosidase A test measures catalytic activity, not simply the amount of enzyme protein present. Leukocyte activity may be reported in nmol/h/mg protein, plasma activity in nmol/h/mL, and dried-spot activity in µmol/L/h; these 3 formats cannot be compared numerically without method-specific information, even when every report uses the same enzyme name.
For a clearly hypothetical example, suppose a laboratory's mean normal leukocyte activity is 50 nmol/h/mg protein and a man's result is 0.25 nmol/h/mg protein. His activity is 0.5% of that laboratory's mean normal value, a markedly deficient result that warrants confirmatory investigation—not a reference interval readers should apply to their own report.
A mildly reduced result deserves a different response from near-absent activity: review specimen integrity, repeat in an appropriate confirmatory specimen, and examine GLA findings. Our explanation of enzyme activity versus quantity illustrates that distinction in another condition, although its numerical thresholds do not apply to Fabry testing; 1 low screening result is not a treatment decision.
Why can women have Fabry disease with normal enzyme activity?
Women with a disease-causing GLA variant can have normal alpha-galactosidase A activity because X-chromosome inactivation creates a mixture of cells with different enzyme production. A woman typically has 2 X chromosomes, and an average blood result does not reveal which chromosome is active in every affected tissue.
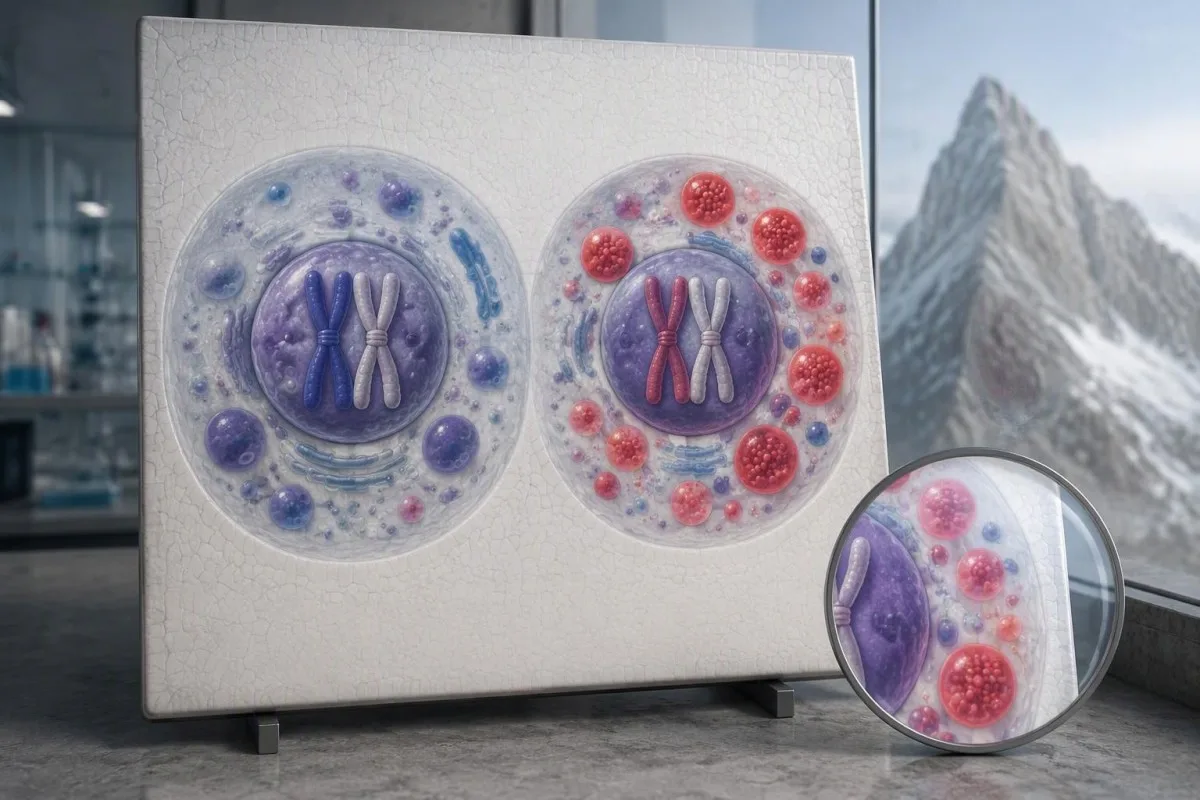
X-chromosome inactivation differs between cells and can differ between tissues. A blood sample may contain enough cells producing functional enzyme to yield a normal laboratory result, while kidney or cardiac cells have a less favorable expression pattern; 1 normal enzyme measurement therefore cannot reliably exclude Fabry disease in a heterozygous woman.
An apparently unaffected woman is not automatically an unaffected carrier: some women develop substantial cardiac, kidney, or neurologic disease, while others remain mildly affected. The limits of X-linked enzyme screening also arise in G6PD deficiency, but G6PD-specific retesting rules and red-cell effects must not be transferred to the GLA test.
가상의 38-year-old woman whose father has a confirmed pathogenic GLA variant: her enzyme activity and lyso-Gb3 both fall within their laboratory ranges. She still needs testing for that exact familial variant, because an affected father transmits his X chromosome to all biological daughters; a negative biochemical screen does not undo that inheritance pattern.
What does the lyso-Gb3 test add to enzyme testing?
그만큼 lyso-Gb3 test measures a deacylated derivative of Gb3 that often increases in Fabry disease, providing biochemical evidence of substrate accumulation. Laboratories may report results in ng/mL 또는 nmol/L; an elevated result supports investigation, but a normal result does not exclude Fabry disease.

Lyso-Gb3 concentrations tend to be higher in untreated males with classic Fabry disease than in many women or later-onset cases. Aerts et al., in their 2008 PNAS paper, established elevated globotriaosylsphingosine as a characteristic Fabry finding; the study does not justify turning 1 universal concentration into a diagnostic rule for every patient, assay, or phenotype.
A hypothetical laboratory might use 1.8 ng/mL as its upper reference limit, making 9.0 ng/mL five times that limit. Kantesti AI can help explain that relationship, but we would not compare it directly with a different laboratory's nmol/L report without checking the analyte and method; our guide to 범위를 벗어난 검사 경고 explains why a flag is not itself a diagnosis.
A normal lyso-Gb3 result can occur in genetically confirmed Fabry disease, particularly in women and some later-onset presentations. Repeated testing is most interpretable when the same assay measures the same analyte: a change from 2.0 to 1.6 ng/mL may reflect biological or analytical variation, treatment, or both—not necessarily a meaningful change in organ health.
| Level | Range | What it means |
|---|---|---|
| Within the hypothetical laboratory limit | ≤1.8 ng/mL | Illustrative only: no biochemical elevation by this invented laboratory's rule; Fabry disease is not excluded. |
| Above the hypothetical laboratory limit | >1.8 ng/mL | Illustrative only: review GLA classification, enzyme activity, phenotype, and specimen information. |
| 계산 예시 | 9.0 ng/mL | Five times the hypothetical upper limit; this is not a validated severity category or treatment threshold. |
How should you read GLA gene testing results?
GLA gene testing looks for variants that can alter alpha-galactosidase A function and reports their clinical classification. The GLA gene has 7 exons, but the meaning of a detected change depends on evidence of pathogenicity—not simply on whether sequencing found a difference.

Genetic laboratories commonly use 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign, and benign. A pathogenic or likely pathogenic GLA finding can establish a molecular diagnosis in the appropriate clinical-genetic context, including in a woman with normal enzyme activity; it does not automatically prove that every symptom or organ abnormality is caused by Fabry disease.
The report should identify the exact variant, transcript, classification, and test coverage, because 2 reports saying 'GLA positive' may mean very different things. The distinction between a genetic finding and a disease diagnosis also appears in our guide to interpreting inherited disease variants, although MEFV inheritance and diagnostic criteria differ from Fabry disease.
A negative result is only as broad as the assay: routine sequencing, deletion/duplication analysis, and targeted testing answer different questions. If a relative's precise GLA variant is known, targeted familial testing usually provides a direct answer; if strong biochemical evidence remains after 1 negative sequencing report, a specialist may review coverage, structural changes, or less routinely captured variants.
Why does a GLA VUS not confirm Fabry disease?
A GLA variant of uncertain significance, or VUS, means that available evidence cannot establish whether the variant causes disease. A VUS is 1 of 5 standard classifications, and it must not be treated as a positive Fabry diagnosis or an automatic indication for disease-specific therapy.

The ACMG/AMP sequence-variant framework states that a VUS should not be used in clinical decision-making (Richards et al., 2015). For Fabry disease, 3 useful evidence streams are biochemical findings, a compatible clinical phenotype, and genetic evidence such as segregation or validated functional studies; none should be cherry-picked merely because the variant appears in a disease-associated gene.
Family testing can sometimes help reclassify a VUS, but detecting the same uncertain variant in 2 relatives is not automatically proof of causation. Age-dependent disease, variable expression in women, and common alternative explanations for kidney or cardiac findings complicate segregation analysis; our discussion of genetic findings without overdiagnosis addresses the broader mistake of equating a DNA difference with disease.
For example, a hypothetical 55-year-old man with hypertension, mildly thickened ventricular walls, normal leukocyte enzyme activity, normal lyso-Gb3, and a GLA VUS has an unresolved genetic finding—not confirmed Fabry cardiomyopathy. He still deserves evaluation of his heart findings, while genetics reviews variant evidence and possible reclassification; uncertainty should prompt a plan, not either dismissal or premature treatment.
What if enzyme, lyso-Gb3, and GLA results disagree?
Discordant Fabry results require specialist reconciliation rather than a majority vote between tests. The 3 tests measure different biological layers, so normal biomarkers with a pathogenic GLA variant, or low enzyme activity with uncertain genetics, lead to different diagnostic pathways.
가상의 29-year-old man has profoundly deficient leukocyte enzyme activity, clearly elevated lyso-Gb3, and a pathogenic GLA variant: these findings align strongly with Fabry disease. The next question is organ involvement and care planning, not whether a normal creatinine or absence of childhood pain can overturn 3 concordant disease-specific findings.
A different hypothetical 46-year-old woman has a pathogenic GLA variant, normal enzyme activity, and normal lyso-Gb3; that pattern does not erase her molecular diagnosis. Disease burden requires separate assessment, just as the combination of a protein measurement and genotype can be informative in 알파-1 항트립신 검사를, although that disorder has different biology and thresholds.
Kantesti is an AI lab test interpretation service that can help organize these 3 reported evidence streams without independently reclassifying a GLA variant. Our 임상 해석 기준 provide context for that boundary; suspected pseudodeficiency, assay interference, or a conflicting laboratory classification requires review by the testing laboratory and a Fabry-experienced specialist.
Can sample handling cause an abnormal Fabry screen?
Sample handling can affect alpha-galactosidase A activity, particularly in dried-spot screening, so an unexpectedly low result may need confirmation in a fresh specimen. At least 2 questions should be checked before interpretation: was the specimen acceptable, and was the method intended for screening or diagnosis?

Dried-spot enzyme results can be influenced by inadequate application, drying, heat, moisture, and specimen composition. A repeat fresh leukocyte assay may be more informative than repeating the same compromised card, especially when more than 1 lysosomal enzyme appears unexpectedly low; the laboratory can explain whether internal quality checks suggest a generalized specimen problem.
Most Fabry-specific enzyme and genetic tests do not inherently require an 8–12시간 금식, but follow the collection laboratory's instructions when other tests are ordered alongside them. Our first laboratory visit preparation guide helps distinguish general preparation from assay-specific requirements; do not stop prescribed treatment simply to obtain a supposedly cleaner baseline.
Tell the laboratory about Fabry-specific treatment, recent transfusion, or hematopoietic transplantation because these circumstances can complicate enzyme or DNA interpretation. A hypothetical result that changes from 0.4 to 6.0 activity units after recollection needs method and specimen review before being called biological recovery; our guide to sample-quality interference explains why laboratories sometimes recommend a redraw.
Which symptoms and family clues justify Fabry testing?
Fabry testing is most useful when characteristic symptoms, unexplained organ findings, or a confirmed family diagnosis raise suspicion. Childhood heat-triggered burning extremity pain, reduced sweating, corneal changes, or otherwise unexplained kidney or cardiac disease can justify evaluation; 1 nonspecific symptom alone rarely identifies the cause.
Fabry-related pain often reflects small-fiber involvement, so routine nerve-conduction studies can be normal despite genuine symptoms. In a hypothetical 24세 with recurrent heat-triggered burning feet and reduced sweating, the pattern merits targeted history and examination; our guide to laboratory clues for unexplained pain also describes alternatives that should not be overlooked.
Cornea verticillata and clusters of angiokeratomas can increase suspicion, but neither should be interpreted outside its clinical context. For example, 2 medications—amiodarone and hydroxychloroquine—can produce corneal changes resembling a Fabry clue, while many skin marks are unrelated; an ophthalmologist or dermatologist can characterize the finding before it becomes genetic evidence.
Later-onset Fabry disease can present without the classic childhood symptom cluster, making unexplained ventricular thickening, proteinuria, or a suggestive pedigree more useful than a childhood checklist. A hypothetical 61세 with isolated cardiac disease needs consideration of common causes and other infiltrative or inherited conditions; blanket Fabry screening for every episode of fatigue or tingling creates more uncertainty than clarity.
Which kidney tests matter alongside Fabry results?
Kidney assessment in Fabry disease should include urine albumin-to-creatinine ratio, creatinine-based eGFR, and clinical context. 알부민-크레아티닌 비율이 30–300 mg/g, 약 3–30 mg/mmol, indicates moderately increased albuminuria; a normal eGFR does not exclude early kidney involvement.
A hypothetical person with confirmed Fabry disease has an eGFR of 98 mL/min/1.73 m² but repeated urine ACR values of 75 mg/g. Filtration is preserved, yet albumin leakage warrants assessment; our urine ACR preparation guide explains how exercise, urinary illness, and collection timing can distort a single measurement.
Creatinine can underestimate kidney impairment in someone with low muscle mass, and cystatin C may improve assessment when creatinine-based estimates appear implausible. At Kantesti, we encourage reading eGFR together with urine findings rather than reassuring someone from 1 creatinine result; our guide to 크레아티닌을 넘어서는 시스타틴 C explains the benefits and non-kidney influences of that additional marker.
Kidney impairment must not automatically be attributed to a GLA VUS, even when the patient has proteinuria. If a specialist recommends tissue examination to clarify unexplained kidney disease, lamellated inclusions require expert interpretation because some medications can cause similar phospholipidosis; our BUN 및 크레아티닌 가이드를 참고하세요. explains why a ratio alone cannot identify the cause of 1 abnormal kidney profile.
How do heart and neurologic findings affect interpretation?
Cardiac and neurologic findings help assess Fabry disease involvement, but they do not independently prove a GLA variant is pathogenic. Unexplained ventricular thickening, rhythm abnormalities, or stroke can support investigation; 1 elevated cardiac biomarker is neither specific to Fabry disease nor sufficient for genetic diagnosis.
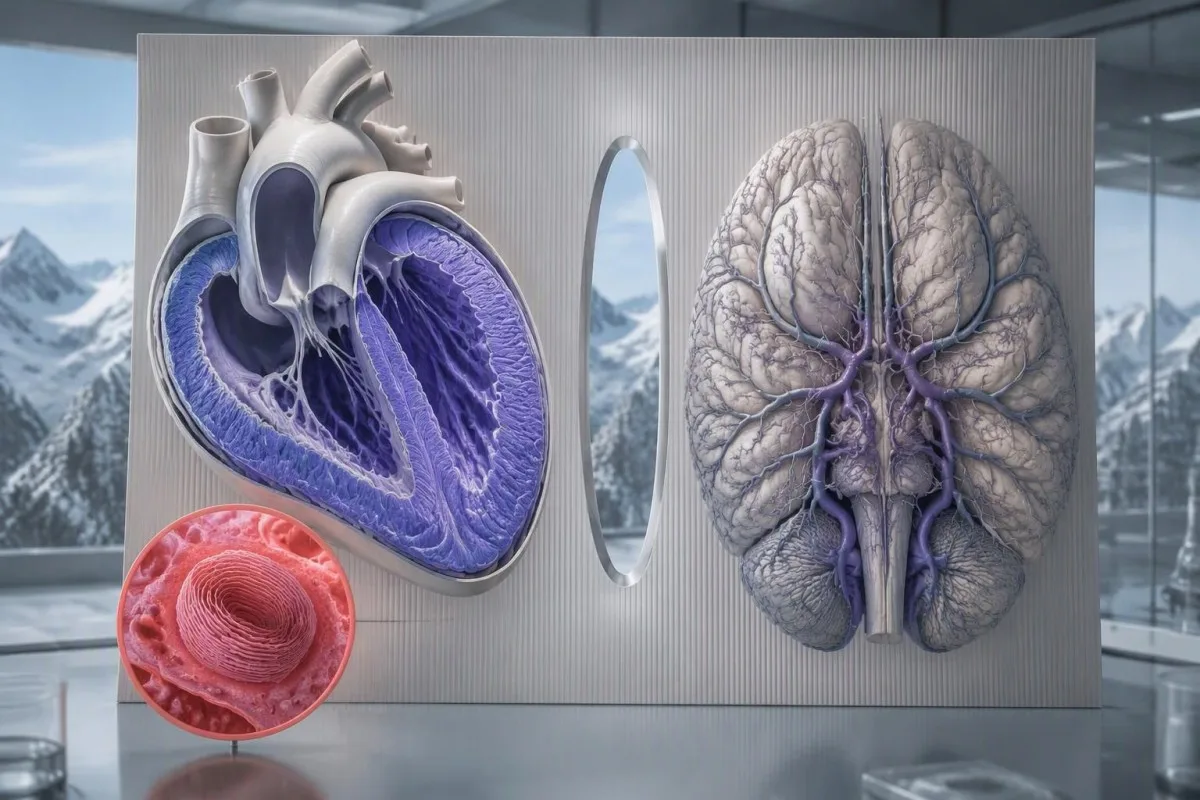
Fabry cardiac evaluation commonly combines electrocardiography, echocardiography, rhythm assessment, and cardiac MRI when appropriate, rather than relying on a single laboratory panel. The 2020 expert consensus on cardiovascular Fabry manifestations describes this multimodal approach (Linhart et al., 2020); 2 useful MRI clues—altered native T1 and characteristic fibrosis distribution—still require interpretation alongside other cardiac diagnoses.
NT-proBNP can rise with cardiac wall stress, but age, atrial fibrillation, and kidney function also influence its concentration. A hypothetical patient with NT-proBNP of 600 pg/mL needs clinical assessment, not a Fabry-specific label; our guide to NT-proBNP causes and cutoffs explains why symptom context and renal function change the meaning of the same number.
Sudden facial weakness, speech difficulty, or new one-sided weakness requires emergency assessment, regardless of pending GLA results or a previous reassuring enzyme test. Family history may shape longer-term prevention, as discussed in family stroke risk assessment, but waiting 1시간 for a genetic explanation is the wrong response to new stroke symptoms; chest pain, collapse, or severe breathlessness also needs urgent care.
Who in the family needs GLA testing?
Cascade testing should focus on the exact familial pathogenic or likely pathogenic GLA variant, supported by genetic counseling. A heterozygous mother has a 50% transmission chance in each pregnancy; an affected father transmits his variant to all biological daughters and none of his biological sons.
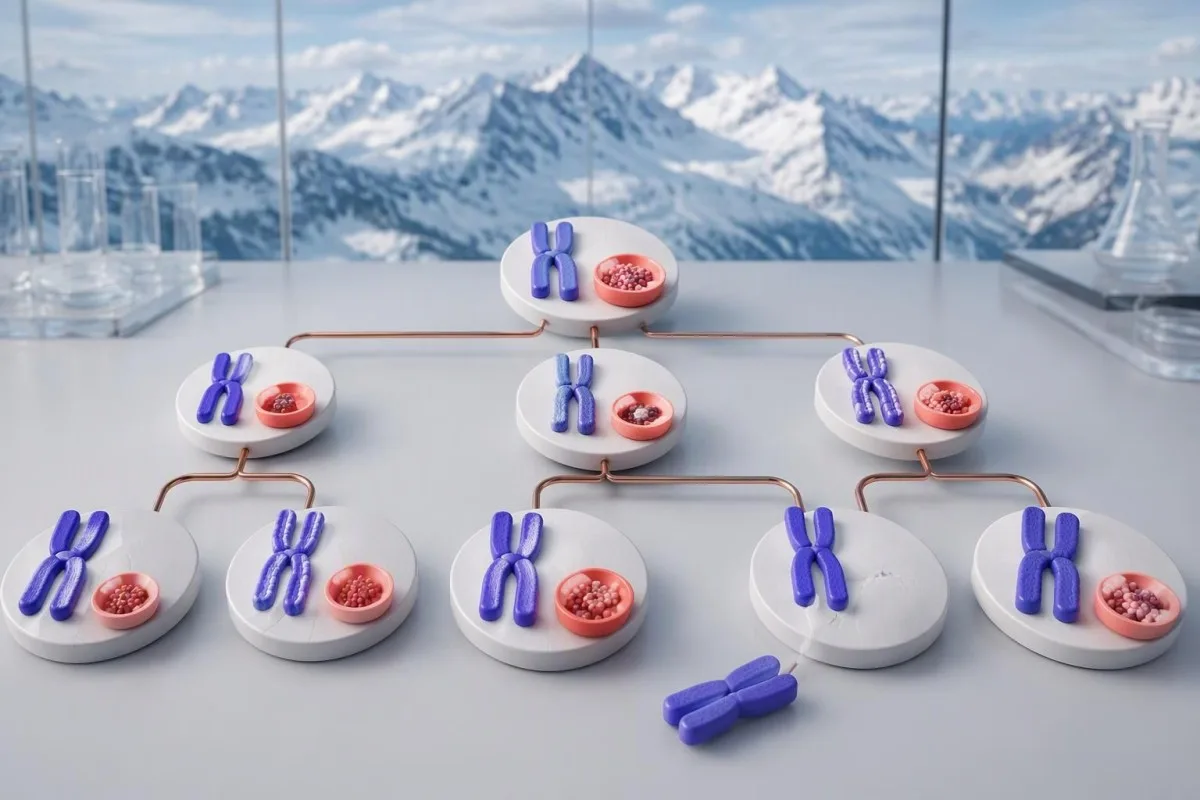
The 50% transmission probability applies independently to each pregnancy, not as a guarantee that half of the children in a particular family will inherit the variant. A daughter who inherits a pathogenic GLA variant may have normal enzyme activity and still need disease-specific assessment; a son's degree of enzyme deficiency and phenotype can differ from a female relative's presentation.
Family testing must distinguish a confirmed disease-causing variant from a VUS found in 1 relative. Testing selected relatives for a VUS may support laboratory reclassification, but it should not be presented as predictive testing for confirmed Fabry disease; our guide to X-linked genetic counseling questions illustrates why the exact condition and assay matter, since FMR1 repeat testing is not a substitute for GLA analysis.
Testing children requires discussion of potential childhood manifestations, benefits of surveillance, consent, and local genetics practice—not an automatic rule to defer until 18 years of age. Reproductive options may include targeted prenatal testing or preimplantation testing when a familial disease-causing variant is established; a genetics team should explain limitations and avoid turning uncertain variant evidence into a reproductive diagnosis.
Do Fabry test results determine treatment or response?
Fabry treatment decisions depend on a confirmed diagnosis, organ involvement, clinical trajectory, and treatment eligibility—not a lyso-Gb3 cutoff alone. Many enzyme replacement regimens are administered every 2주; oral chaperone eligibility requires a disease-causing GLA variant with demonstrated amenability and other appropriate clinical criteria.
Migalastat amenability and GLA pathogenicity are different questions. A variant can respond in an in-vitro amenability assay without sufficient evidence that it causes Fabry disease, so neither an 'amenable' label nor 1 uncertain genetic result should bypass diagnostic review; specialist prescribing also considers renal function, age eligibility, and the applicable product information.
Lyso-Gb3 often falls with effective Fabry-specific therapy, but biomarker improvement does not prove that established kidney scarring or cardiac fibrosis has reversed. If a hypothetical concentration falls from 40 to 10 ng/mL, that is a 75% reduction; Kantesti AI can help explain the arithmetic while keeping symptoms, eGFR, urine ACR, rhythm findings, and imaging separate from the biomarker trend.
Serial results should be compared using consistent assay methods and documented treatment timing. 변화가 2.1 to 1.9 ng/mL may be much less informative than a sustained multi-visit pattern, and persistent symptoms deserve evaluation even when lyso-Gb3 improves; our guide to 검사 간 의미 있는 변화 explains why small numerical shifts should not trigger unsupervised treatment changes.
AI interpretation limits and related research publications
AI can explain a Fabry laboratory report, but it cannot independently confirm Fabry disease, reclassify a GLA VUS, or prescribe disease-specific therapy. Keep the original reports for all 3 diagnostic layers, including specimen details, units, genetic classification, and the laboratory's interpretive comments.

Kantesti is an AI-powered blood test analysis tool that can help organize reported results and questions for a specialist appointment, while a genetic laboratory remains responsible for its variant classification. Before sharing 1 identifiable genetic report, 저희의 개인정보 및 데이터 관련 정보를 확인하고; genetic results can reveal information about relatives as well as the person whose sample was tested.
그만큼 2 DOI-linked publications below concern RDW interpretation and the BUN/creatinine ratio, not clinical validation of a Fabry diagnostic algorithm. Our RDW interpretation publication may help explain accompanying hematology results, but RDW cannot confirm or exclude Fabry disease; a DOI identifies a deposited publication and does not, by itself, establish peer review or diagnostic accuracy.
우리의 의료 콘텐츠 표준 describe how educational content should separate established facts from uncertainty. When using Kantesti to prepare for care, ask 3가지 실용적인 질문: does the GLA classification establish a molecular diagnosis, do the biochemical results support it, and what organ monitoring is needed; these answers are more useful than asking whether an AI has declared the report simply positive or negative.
자주 묻는 질문
파브리병을 진단하는 가장 정확한 검사는 무엇인가요?
파브리병 진단에는 보편적으로 충분한 단일 선별검사 대신 알파-갈락토시다아제 A 활성도, lyso-Gb3 및 GLA 유전자 검사에서 얻은 상호보완적 근거를 사용합니다. 전형적인 질환이 있는 남성의 효소 활성도는 일반적으로 평균 정상 활성도의 1% 미만이며, 유전자 검사로 분자적 원인을 확인합니다. 여성에서는 효소 활성도가 정상일 수 있으므로 GLA 검사가 특히 중요합니다. 병원성 또는 병원성 가능성이 높은 소견은 임상적 의미가 불확실한 변이와 진단적 의미가 다릅니다.
여성은 효소 검사 결과가 정상이어도 파브리병에 걸릴 수 있나요?
여성은 알파-갈락토시다아제 A 활성이 정상이어도 파브리병이 있을 수 있습니다. 여성은 일반적으로 X 염색체를 2개 가지고 있으며, X 염색체 비활성화로 인해 기능성 효소를 서로 다른 양으로 생성하는 세포들이 혼재하게 됩니다. 혈액의 효소 활성은 모든 신장 세포나 심장 세포의 효소 기능을 신뢰성 있게 반영하지 않습니다. 의심스러운 가족력이나 임상 양상이 있다면 효소 검사 결과가 정상 범위에 있더라도 GLA 유전자 평가가 필요합니다.
정상적인 lyso-Gb3 수치는 얼마인가요?
A normal lyso-Gb3 result is defined by the testing laboratory's assay-specific reference interval, not a universal Fabry cutoff. For illustration only, a hypothetical laboratory using an upper limit of 1.8 ng/mL would classify 9.0 ng/mL as five times that limit. Those figures must not be substituted for your laboratory's range or compared directly with a different-unit result. Normal lyso-Gb3 does not exclude Fabry disease, particularly in women and some later-onset cases.
GLA 불확실성 변이(VUS)가 있다는 것은 파브리병에 걸렸다는 뜻인가요?
불확실성 변이(GUS)로 분류된 GLA 변이는 파브리병을 확진하지 않습니다. VUS는 표준 유전 변이 분류 5가지 중 하나이며, 현재 이용 가능한 근거만으로는 해당 변이가 질병을 유발하는지 판단할 수 없다는 뜻입니다. 전문의는 효소 활성, lyso-Gb3, 임상 소견, 가족 내 분리 양상 및 검증된 기능적 근거를 검토할 수 있습니다. VUS만을 근거로 질병 특이적 치료를 시행하거나 친척에게 질병이 있을 것으로 예측해 표기해서는 안 됩니다.
정상 크레아티닌 수치로 파브리병 신장 질환을 배제할 수 있나요?
정상 크레아티닌 수치라고 해서 파브리병의 초기 신장 침범을 배제할 수는 없습니다. eGFR이 90 mL/min/1.73 m²를 초과하는 동안에도 소변 알부민-크레아티닌 비율이 비정상으로 나타날 수 있습니다. ACR 30–300 mg/g(약 3–30 mg/mmol)은 중등도 알부민뇨를 나타내며, 반복 검사와 임상적 맥락을 고려해 해석해야 합니다. GLA VUS가 있는 사람에게 단백뇨가 나타나더라도 다른 신장 원인에 대한 조사가 필요합니다.
파브리병 진단 후 친척들도 검사를 받아야 하나요?
Relatives should be offered genetic counseling and targeted testing when a familial pathogenic or likely pathogenic GLA variant is established. A heterozygous mother has a 50% chance of transmitting the variant in each pregnancy. An affected father transmits his variant to all biological daughters and none of his biological sons. Testing relatives for a VUS may help resolve uncertainty, but it is not equivalent to predictive testing for confirmed Fabry disease.
Do I need to fast before a Fabry disease test?
Fabry-specific enzyme and GLA genetic tests generally do not inherently require an 8–12-hour fast. Follow the collecting laboratory's instructions because lyso-Gb3 protocols or other tests ordered at the same visit may have additional requirements. Tell the laboratory about Fabry treatment, recent transfusion, or hematopoietic transplantation when relevant. Do not stop prescribed medication or disease-specific treatment solely to prepare for testing without clinical advice.
Get your blood test results explained
Upload your lab report and Kantesti's AI explains each biomarker in plain language within seconds. Used by more than 2 million people worldwide.
참고 자료
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW Blood Test: Complete Guide to RDW-CV, MCV & MCHC. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). BUN/크레아티닌 비율 설명: 신장 기능 검사 가이드. Kantesti AI Medical Research. DOI
- Aerts JM et al. (2008). Elevated globotriaosylsphingosine is a hallmark of Fabry disease. Proceedings of the National Academy of Sciences of the United States of America. DOI 퍼브메드
- Richards S et al. (2015). Standards and guidelines for the interpretation of sequence variants: a joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genetics in Medicine. DOI 퍼브메드
- Linhart A et al. (2020). An expert consensus document on the management of cardiovascular manifestations of Fabry disease. European Journal of Heart Failure.
- 200만+Tests analysed
- 127+국가
- 100+언어
About the medical team


E-E-A-T 신뢰 신호
경험
의사가 주도하는 검사 해석 워크플로 임상 검토.
전문적 지식
임상 맥락에서 바이오마커가 어떻게 거동하는지에 대한 검사실 의학 중심.
권위
Medically reviewed by Dr. Thomas Klein, with contributions from Dr. Sarah Mitchell and Prof. Dr. Hans Weber.
신뢰성
경고를 줄이기 위한 명확한 후속 경로가 포함된 근거 기반 해석.






Medical disclaimer
이 글은 교육 목적만을 위한 것이며 의학적 조언을 구성하지 않습니다. 진단 및 치료 결정에는 항상 자격을 갖춘 의료 전문가와 상담하세요.
게시됨 · Contact the editorial team
Published by Kantesti Ltd, registered in England & Wales, company no. 17090423, London, United Kingdom.
