A low GAA enzyme result raises suspicion for Pompe disease, but screening alone cannot confirm it. Repeat testing in an appropriate specimen and GAA genetic analysis help distinguish true deficiency, carrier status and pseudodeficiency.

Galvenie secinājumi
- Low GAA enzyme activity is a follow-up signal, not a diagnosis; 1 abnormal dried blood spot needs specialist-directed confirmation.
- Atsauces diapazoni depend on the specimen and assay; nmol/h/mL cannot be compared directly with nmol/h/mg protein.
- Residual enzyme activity is often below 1% in classic infantile Pompe disease, but that figure is not a universal screening cutoff.
- Pseudodeficiency can lower laboratory GAA activity without causing Pompe disease; repeating the same assay may reproduce the low result.
- GAA gene testing looks for disease-causing variants affecting both gene copies; 2 variants must be interpreted for classification and phase.
- Neskaidri varianti do not establish Pompe disease; 1 or 2 variants of uncertain significance require additional evidence.
- Family risk is 25% for an affected child in each pregnancy when both parents carry a disease-causing GAA variant.
- Steidzams izvērtējums is needed for an infant with low GAA plus feeding difficulty, marked weakness or suspected heart involvement; do not wait for a routine retest.
What does a low GAA enzyme result actually mean?
A Pompe disease test showing low GAA activity means the laboratory measured reduced acid alpha-glucosidase function under its assay conditions. It does not prove Pompe disease: 1 low screening result can reflect true deficiency, pseudodeficiency, carrier-related overlap or a specimen problem.
GAA activity measures enzyme function, not simply how much enzyme protein is present. The first 3 details to check are specimen type, measurement units and the laboratory's decision limit; a result described as low without these details cannot be interpreted reliably against a number found online.
The reason for testing changes the meaning of a positive screen. A newborn identified through population screening and a 45-year-old with progressive hip weakness have different starting probabilities of Pompe disease, even if their reported enzyme values match; symptoms and examination therefore belong beside the laboratory result.
Screen-positive is not the same as disease-positive. If 2 laboratories use different substrates or specimen preparations, their numerical results may disagree without either laboratory making an error; ask whether the next appointment is for another screening measurement or a genuinely confirmatory enzyme assay.
Kantesti ir AI asins analīžu analizators that can help organize a GAA report alongside routine laboratory findings, but cannot establish a Pompe disease diagnosis from 1 flagged value. Our uzņēmuma informācija explains the organization behind the service; suspected inherited enzyme deficiency still requires a metabolic or neuromuscular specialist.
Why does GAA deficiency cause muscle and heart problems?
Pompe disease results from deficient lysosomal acid alpha-glucosidase, an enzyme that breaks down glycogen inside cellular recycling compartments. GAA acts on both alpha-1,4 and alpha-1,6 glucose linkages; inadequate activity allows glycogen to accumulate, particularly in skeletal and cardiac muscle.
Classic infantile Pompe disease often has less than 1% of normal GAA activity in diagnostic tissue assays. Later-onset disease can retain more activity, sometimes approximately 2–40% in particular assays; these descriptive ranges overlap with assay limitations and must not replace a laboratory's validated diagnostic interpretation.
Kishnani et al.'s 2006 Genetics in Medicine guideline describes the connection between GAA deficiency, glycogen storage and multisystem assessment. The clinical distinction is not just whether activity is below 1%: age at presentation, heart findings and respiratory muscle function also help determine the form and urgency of disease.
A routine glucose result does not measure lysosomal glycogen clearance. For example, a hypothetical adult can have fasting glucose of 92 mg/dL while having an inherited muscle glycogen-storage disorder; normal glucose does not demonstrate that glycogen inside muscle lysosomes is being processed normally.
Other lysosomal disorders involve different enzymes and genes, so their thresholds cannot be borrowed for Pompe testing. Our explanation of Gaucher enzyme confirmation illustrates the broader enzyme-to-genetics workflow, while showing why 1 disease's enzyme assay cannot substitute for another's.
Is there a normal range for GAA enzyme activity?
There is no single universal normal range for GAA enzyme activity. Dried blood spots, leukocytes and cultured fibroblasts use different preparations and reporting units; a number expressed in nmol/h/mL cannot be directly compared with a result expressed in nmol/h/mg protein.

A screening cutoff separates samples needing follow-up from samples passing that screen. It does not necessarily separate affected people from unaffected people with complete accuracy; laboratories may use different fluorometric or tandem mass spectrometry methods, and 2 screening programs may therefore select different recall thresholds.
For a clearly hypothetical example, suppose a laboratory uses a DBS screening cutoff of 1.5 nmol/h/mL and reports 0.7 nmol/h/mL. The result is below that invented laboratory threshold, but dividing 0.7 by 1.5 gives 47% of the cutoff—not 47% of normal enzyme activity and not a severity score.
The lower limit of detection is different from the clinical cutoff. A report reading less than 0.1 in its stated units may mean the method cannot quantify lower activity reliably; it does not prove absolute absence of enzyme, and repeating measurements close to that analytical floor may produce proportionally large variation.
Screening performance also depends on prevalence. In a hypothetical group with 10 true-positive and 100 false-positive results, only about 9% of positive screens represent disease; those invented counts are not Pompe screening statistics, but explain why kvalitatīvi pret kvantitatīviem rezultātiem require different interpretation.
| Līmenis | Diapazons | Ko tas nozīmē |
|---|---|---|
| Passes hypothetical screen | ≥1.5 nmol/h/mL | Illustrative DBS cutoff only; not a universal normal range and not an absolute exclusion in a symptomatic person. |
| Below hypothetical cutoff | <1.5 nmol/h/mL | Illustrative follow-up threshold only; true deficiency, pseudodeficiency and specimen effects still need separation. |
Why repeat GAA testing in a different specimen?
Repeat GAA testing checks whether low activity is reproducible and whether specimen quality or assay interference explains it. Confirmation usually moves beyond 1 screening card to a fresh, appropriately handled specimen, often with GAA measurement in leukocytes or another specialist-selected cell preparation.

Heat, humidity and inadequate drying can reduce enzyme activity in a dried blood spot. A low result after 2 days of poorly controlled transport may deserve a fresh collection, but transport history cannot be used to dismiss a result automatically; the laboratory should assess card quality and its stability requirements.
Acarbose is used in some GAA assay methods to suppress interfering maltase-glucoamylase activity. That interference can make measured activity appear higher and potentially obscure deficiency; checking how a laboratory isolates GAA activity can therefore matter more than obtaining a second number with the same unresolved methodological limitation.
Two low DBS results still do not automatically confirm Pompe disease. Pseudodeficiency can reproduce across repeated measurements, including some confirmatory methods; when enzyme and genetic findings disagree, a specialist laboratory may recommend cultured fibroblast testing or additional molecular investigation rather than simply ordering a third screening card.
Give the laboratory the dates of collection, recent transfusions or transplantation, and any enzyme replacement treatment already received. Our guide to parauga kvalitātes traucējošajiem faktoriem explains the general distinction between biological findings and specimen problems; GAA testing has its own handling rules, so do not import another test's redraw interval.
How does GAA pseudodeficiency differ from Pompe disease?
GAA pseudodeficiency means an inherited variant lowers measured enzyme activity without causing the glycogen-storage disorder Pompe disease. Two commonly discussed variants are c.1726G>A, p.Gly576Ser, and c.2065G>A, p.Glu689Lys; their interpretation depends on the complete genotype and the assay used.
Pseudodeficiency is a biochemical testing issue, not an early stage of Pompe disease. A person with only pseudodeficiency variants does not need Pompe treatment because of 1 low activity result; the specialist must first verify that disease-causing variants or another explanation have not been missed.
The p.Gly576Ser and p.Glu689Lys variants are often found together on 1 gene copy and are particularly relevant in some East Asian ancestry populations. Ancestry changes how often laboratories encounter this pattern, but cannot establish or exclude pseudodeficiency in an individual; people from other backgrounds can carry these variants too.
Pseudodeficiency can remain low on repeat enzyme testing. The practical distinction is whether the complete biochemical and genetic evidence supports disease-causing GAA deficiency, not whether a second result falls below an arbitrary percentage; specialists may compare different assay substrates or cell preparations when the pattern remains ambiguous.
Pseudodeficiency variants can also coexist with a disease-causing variant, making a short report misleading if it lists everything under mutations. Our Fabry enzyme and genetics guide shows another situation where enzyme results need genetic context, although Fabry's X-linked inheritance differs from Pompe's 2-copy recessive mechanism.
What should GAA gene testing look for?
GAA gene testing investigates whether disease-causing variants affect both copies of the GAA gene. Pompe disease is autosomal recessive, and the GAA gene is located on chromosome 17; interpretation requires variant classification, adequate test coverage and, when needed, confirmation that variants affect opposite gene copies.
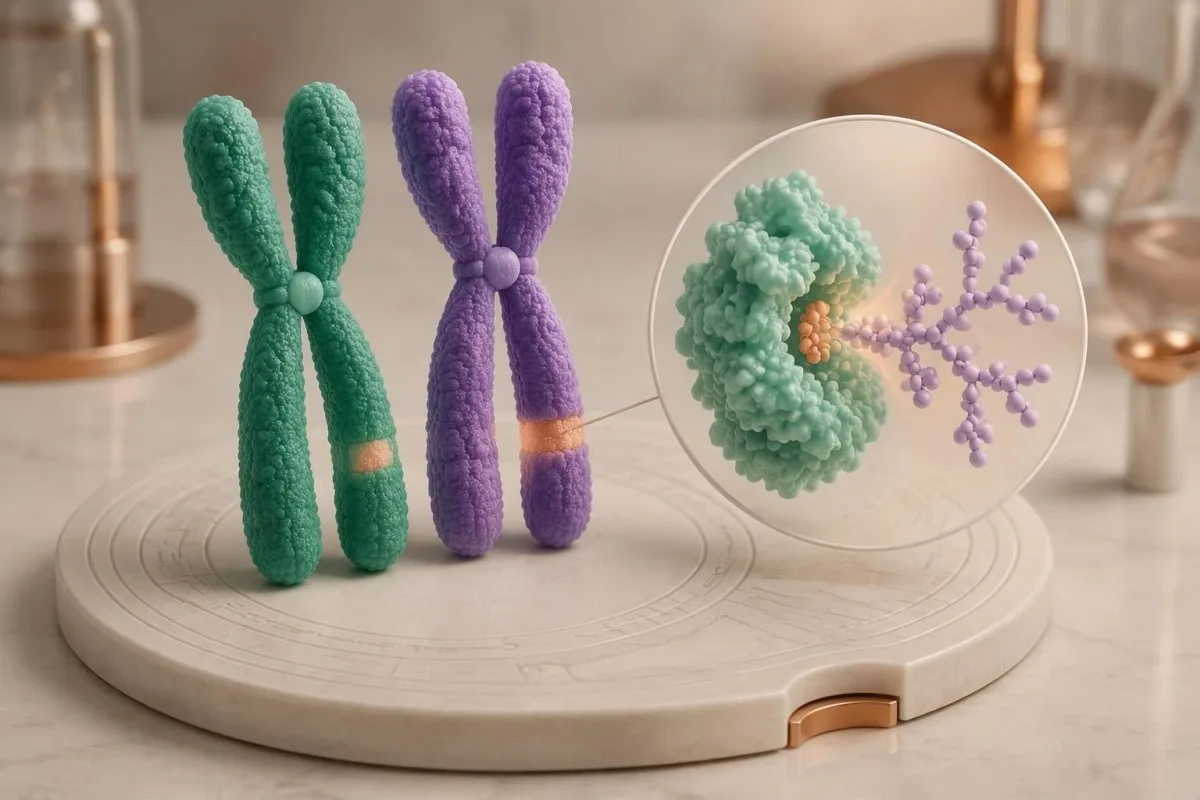
Two pathogenic or likely pathogenic GAA variants in trans support molecular confirmation of Pompe disease. In trans means the variants affect opposite gene copies; 2 variants in cis affect the same copy and do not, by themselves, demonstrate a recessive disease genotype.
Standard sequencing detects many small substitutions and insertions or deletions, but does not answer every possible genetic question. If only 1 disease-causing variant is found despite convincing enzyme deficiency, ask whether deletion/duplication analysis was included and whether poorly covered or deep intronic regions require further investigation.
A common later-onset-associated GAA variant is c.-32-13T>G, which affects splicing. Finding this variant on 1 copy does not diagnose Pompe disease, and finding it with another disease-causing variant does not precisely predict the age symptoms will begin; residual splicing and other biological factors influence presentation.
Parental testing can help establish phase when a laboratory detects 2 different variants but cannot determine their arrangement. Our guide to inherited disease genetic reports explains why inheritance and family testing matter, while the actual gene coverage and diagnostic criteria must remain specific to GAA.
How should pathogenic, uncertain and negative results be read?
A pathogenic result, a variant of uncertain significance and a negative result have different diagnostic meanings. Genetic laboratories commonly use 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign and benign; a VUS is not equivalent to a disease-causing GAA variant.

Richards et al.'s 2015 ACMG/AMP consensus established the widely used 5-category sequence-variant framework and states that a VUS should not guide clinical decision-making as though pathogenic. For Pompe evaluation, low enzyme activity can contribute evidence, but its value depends on whether pseudodeficiency and assay limitations have been addressed.
One pathogenic variant plus 1 VUS is an unresolved combination, not automatic confirmation or exclusion. Depending on the enzyme and clinical findings, specialists may investigate family segregation, RNA effects or variant-specific functional evidence; a diagnostic enzyme result may support disease even while the second molecular finding remains incompletely characterized.
A negative sequencing report means the test found no reportable variants within its scope. It does not prove that every GAA-related mechanism was examined; 1 negative limited test may warrant expanded testing when properly performed enzyme studies and the clinical pattern remain strongly suggestive.
Kantesti ir AI asins analīžu rezultātu platforma that can help separate a report's 5 classification terms from its numerical enzyme findings, without adjudicating an uncertain genotype. Our tehniskie un klīniskie standarti describe interpretation boundaries; our uncertain gene-result explanation provides a related example of why variants and diagnoses are not interchangeable.
Does one GAA variant mean carrier status or disease?
One confirmed disease-causing GAA variant usually indicates carrier status if a second disease-causing variant and diagnostic enzyme deficiency are absent. Carriers do not typically develop Pompe disease; when both parents are carriers, each pregnancy has a 25% affected, 50% carrier and 25% non-carrier probability.

Carrier enzyme values can overlap with values in unaffected people. GAA activity is therefore not a reliable standalone carrier test, and a carrier's activity should not be assumed to equal exactly 50% of a laboratory's normal mean; targeted genetic testing is generally more informative when a familial variant is known.
The 25% affected-child probability applies independently to each pregnancy when both parents carry disease-causing variants capable of producing Pompe disease together. Having 1 unaffected child does not reduce the next pregnancy's Mendelian probability, and pseudodeficiency variants should not be substituted for pathogenic variants in that calculation.
Family testing is most useful after the affected person's variants are clarified. If a symptomatic adult has only 1 identified pathogenic variant, relatives should not be reassured that the entire family question is settled until the specialist considers whether the second variant was missed by the original assay.
For a hypothetical couple, one partner carrying a pathogenic GAA variant and the other carrying only a pseudodeficiency variant does not create the same 25% Pompe risk as 2 pathogenic-variant carriers. Our carrier screening limitations guide explains why a report's coverage and residual risk deserve discussion before reproductive decisions.
Which other laboratory results support Pompe evaluation?
Creatine kinase, AST, ALT and urinary glucose tetrasaccharide can support Pompe evaluation, but none confirms the diagnosis alone. Urinary glucose tetrasaccharide may be reported as Glc4 or within a Hex4 assay; these 2 report terms require method-specific interpretation rather than assumption that every laboratory measures exactly the same thing.
Normal CK does not exclude later-onset Pompe disease. In a hypothetical adult with progressive difficulty rising from a chair, CK of 140 U/L may fall within that laboratory's interval despite clinically meaningful weakness; the combination of symptoms and low confirmed GAA activity matters more than a reassuring CK flag.
AST and ALT can rise because of muscle involvement, not only liver disease. A hypothetical AST of 86 U/L with elevated CK and muscle weakness deserves a muscle-aware assessment; our aldolase and muscle marker guide explains why additional muscle enzymes may help characterize the pattern without identifying its cause.
Urinary Glc4 is a supportive glycogen-related biomarker, not a Pompe-specific diagnostic test. Reference limits vary with age and method, and elevation can occur in other circumstances; 1 elevated result should be interpreted alongside enzyme findings, genetics and the laboratory's creatinine-normalized units.
A falling CK or Glc4 after treatment does not automatically prove that strength or breathing has improved by the same percentage. Our discussion of AST interpretation beyond liver disease illustrates why 2 related markers can move together while still answering different questions about tissue injury and function.
Why assess breathing when a Pompe test is abnormal?
Pompe disease can weaken the diaphragm and other respiratory muscles, sometimes before obvious walking difficulty. Assessment may include seated and supine forced vital capacity, respiratory muscle pressures and sleep-related testing; a daytime oxygen saturation of 97% does not rule out overnight hypoventilation.
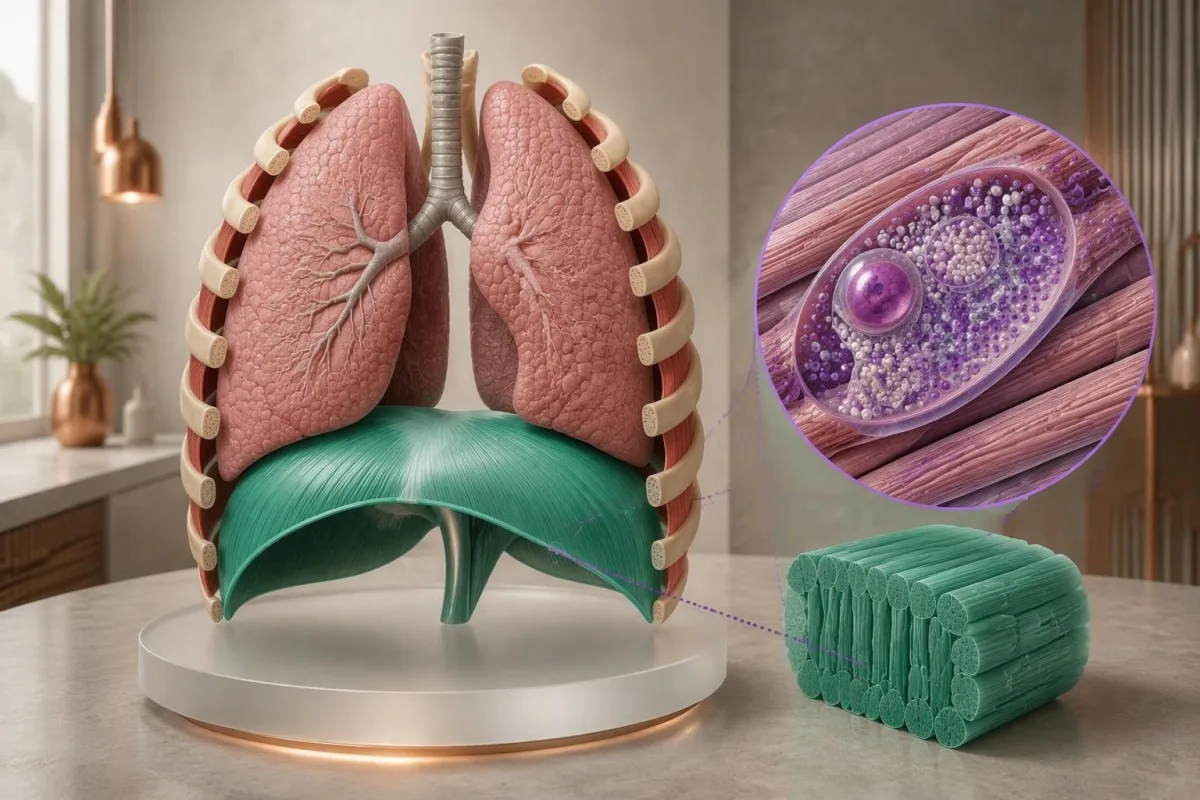
A position-related fall in vital capacity can suggest diaphragm weakness. For example, a hypothetical seated FVC of 3.0 L and supine FVC of 2.4 L represents a 20% decline; the specialist interprets that difference with technique, predicted values and symptoms, rather than treating it as a Pompe-specific cutoff.
Morning headaches, unrefreshing sleep and difficulty breathing when lying flat can justify evaluation for sleep-related hypoventilation. These symptoms do not identify Pompe disease on their own; our elpas trūkuma testēšanas rokasgrāmata explains why laboratory results cannot replace respiratory examination and physiological testing.
Arterial carbon dioxide is normally about 35–45 mmHg in adults, with context-dependent variation. A value above 45 mmHg indicates hypercapnia, but its urgency depends on pH, symptoms and the clinical setting; our blood gas interpretation guide explains why oxygen and carbon dioxide answer different questions.
Severe breathlessness, confusion, blue coloration or rapidly worsening weakness warrants emergency care, not an online interpretation session. A confirmed molecular result affecting 2 GAA copies does not measure current respiratory safety; clinicians need direct functional assessment to decide whether ventilation support or urgent monitoring is necessary.
What happens after a positive newborn Pompe screen?
A positive newborn Pompe screen requires prompt specialist assessment, confirmatory enzyme testing and genetic evaluation. It does not mean every infant has Pompe disease; the immediate task is to distinguish pseudodeficiency or carrier findings from infantile disease and a later-onset-associated genotype affecting both GAA copies.

Burton et al.'s 2017 Pediatrics newborn-screening algorithms describe an initial evaluation integrating GAA confirmation, molecular testing and clinical assessment. If an infant has feeding difficulty, marked hypotonia or suspected cardiomyopathy, do not wait 2 weeks for a routine repeat appointment; the screening team should arrange urgent metabolic and cardiac evaluation.
Classic infantile Pompe disease commonly involves hypertrophic cardiomyopathy. A newborn's echocardiogram and electrocardiogram help assess risk that cannot be estimated from 1 enzyme number; absence of obvious heart symptoms at home does not replace the specialist examination after an abnormal screen.
CRIM status concerns whether cross-reactive GAA protein is present and helps specialists plan immune-risk management around enzyme replacement therapy. Less than 1% enzyme activity does not by itself establish CRIM-negative status, because an inactive protein may still be present; this is a protein-expression question, not just an activity threshold.
Later-onset-associated findings in a newborn require a monitoring plan, not an invented age-of-onset prediction. Even 2 classified disease-causing variants may not reveal when symptoms will emerge; our pediatriskās AI drošības vadlīnijas explains why pediatric results require age-specific context and clinician-led decisions.
How do specialists resolve conflicting adult test results?
Conflicting adult Pompe results are resolved by checking specimen quality, confirmatory enzyme methods, variant classification and clinical fit. One low screen plus 1 genetic finding rarely tells the whole story; specialists investigate whether the apparent conflict comes from pseudodeficiency, an incomplete molecular test or another cause of weakness.

Consider a hypothetical 52-year-old with mild fatigue, low DBS GAA activity and only the 2 commonly discussed pseudodeficiency variants. If specialist testing supports pseudodeficiency and no disease-causing genotype, the low screen does not explain the fatigue; other causes should be assessed rather than attaching a Pompe label to an incidental biochemical finding.
A second hypothetical adult has progressive hip weakness, a 20% positional FVC decline, confirmed cellular GAA deficiency and 2 pathogenic variants in trans. Together, those findings support Pompe disease; a normal routine glucose or modest CK result would not outweigh the converging biochemical, genetic and functional evidence.
Convincing enzyme deficiency with only 1 identified pathogenic variant deserves further investigation. The appropriate next step may be deletion/duplication analysis, RNA studies or another specialist assay—not automatically calling the person a carrier; the investigation should also check whether non-Pompe neuromuscular conditions better explain the examination.
Variant-related disease monitoring is not the same as predicting a person's future from their DNA. Our inherited neuromuscular risk guide offers a related family-testing perspective, but 2 conditions can differ substantially in inheritance, penetrance and treatment triggers.
What should you bring to your Pompe specialist appointment?
Bring the complete enzyme report, complete genetic report and a dated symptom history to a Pompe specialist appointment. Three report details are especially useful: specimen type, assay units and variant classification; screenshots showing only a red flag or the word mutation can omit information that changes the interpretation.

Ask whether confirmatory testing has already been completed and whether the laboratory measured GAA specifically in an appropriate cell preparation. If 2 variants were found, ask whether they are in trans; if only 1 was found, ask what variant types and regions the test could detect.
Do not try to raise GAA activity with supplements or diet before confirmation. No vitamin or food corrects inherited pathogenic variants affecting both GAA copies; nutrition may support general care after diagnosis, but cannot substitute for enzyme confirmation or specialist treatment planning.
Kantesti ir ar AI balstīts asins analīzes rīks that can help organize report terminology and associated laboratory trends, not decide whether 2 uncertain variants establish Pompe disease. Our ceļvedis pārskatu avotu pārbaudei explains why the original document remains the reference when an automated explanation and a specialist interpretation differ.
Genetic documents can contain information relevant to relatives as well as the tested person. Before sharing 1 family member's report, check consent and remove unnecessary identifiers; Kantesti's informāciju par privātumu un datiem describes our handling approach, while sharing results with relatives should follow a genetic counselor's guidance.
Research publications and limits of Pompe test interpretation
Pompe test interpretation rests on disease-specific enzyme, genetic and clinical evidence—not on general laboratory publications or an AI explanation. Kantesti includes 3 directly relevant external sources below and 2 separate educational publications; the iron and coagulation publications are not evidence for diagnosing Pompe disease.
The 2006 Kishnani guideline provides disease-specific diagnostic and management context, while the 2017 Burton newborn-screening paper addresses confirmation after population screening. Their recommendations should be applied with the specialist laboratory's validated methods; neither supplies 1 universally transferable DBS enzyme cutoff for every instrument and population.
Richards et al.'s 2015 ACMG/AMP publication explains the 5-category variant framework used to distinguish pathogenic findings from uncertainty. Classification can change when new evidence becomes available, so ask the genetics service whether an unresolved result has a reanalysis pathway rather than assuming every VUS will eventually become pathogenic.
Mūsu izglītojošais dzelzs izpētes publikācija addresses a different laboratory domain. The separate publikācijā par asins recēšanas analīzēm also covers unrelated markers; their 2 DOI records are provided for publication transparency, not as supporting citations for GAA deficiency or pseudodeficiency.
Kantesti medicīniskā satura standarti distinguish patient education from diagnosis and treatment instructions. The practical endpoint is a documented interpretation of 3 evidence streams—enzyme testing, genetic analysis and clinical assessment—with urgent care taking priority whenever infantile disease or respiratory compromise is suspected.
Bieži uzdotie jautājumi
Vai zema GAA enzīma aktivitāte vienmēr nozīmē Pompes slimību?
Zema GAA enzīma aktivitāte ne vienmēr nozīmē Pompes slimību. Viens patoloģisks skrīninga rezultāts var liecināt par īstu deficītu, pseidodeficītu, parauga noārdīšanos vai aktivitātes pārklāšanos ar nesēja aktivitāti. Apstiprināšanai nepieciešama speciālista interpretācija, ņemot vērā atbilstoša enzīma testa rezultātus, GAA ģenētiskos atradumus un klīnisko kontekstu. Atkārtojot tikai to pašu skrīninga testu, pseidodeficīts var tikt konstatēts atkārtoti, nevis novērsta neskaidrība.
Kāds ir normāls GAA enzīma līmenis?
There is no universal normal GAA enzyme level because specimen preparation, assay substrate and reporting units differ between laboratories. A value in nmol/h/mL cannot be directly compared with a value in nmol/h/mg protein. Classic infantile Pompe disease often has less than 1% of normal activity in diagnostic tissue assays, but this is not a universal newborn-screening cutoff. Use the reference information printed on the original report and the specialist laboratory's interpretation.
Vai divi zemi GAA testu rezultāti joprojām var liecināt par pseidodeficītu?
Divi zemi GAA testa rezultāti joprojām var liecināt par pseidodeficītu, īpaši tad, ja tiek izmantotas vienas un tās pašas vai līdzīgi ietekmētas analīzes metodes. Pseidodeficīta varianti samazina izmērīto aktivitāti, paši par sevi neizraisot Pompe glikogēna uzkrāšanās slimību. Speciālisti šo ainu atšķir, izvērtējot pilnu GAA genotipu, analīžu metožu raksturlielumus un, ja nepieciešams, citu šūnu preparātu vai funkcionālu izmeklējumu. Tāpēc divi atkārtoti zemi rādītāji nav līdzvērtīgi diviem neatkarīgiem slimības apstiprinājumiem.
0 Vai divi GAA gēna varianti apstiprina Pompes slimību?
Divi GAA varianti automātiski neapstiprina Pompes slimību. Divi patogēni vai, visticamāk, patogēni varianti trans pozīcijā, kas skar pretējas gēna kopijas, apstiprina diagnozi molekulārā līmenī, savukārt divi varianti cis pozīcijā skar tikai vienu kopiju. Neskaidras nozīmes variantus un pseidodeficīta variantus nevar uzskatīt par pierādītiem slimību izraisošiem atradumiem. Enzīma un klīniskie dati joprojām ir īpaši noderīgi, ja klasifikācija vai fāze nav noskaidrota.
Vai normāls CK līmenis var izslēgt vēlīni sākušos Pompe slimību?
Normal CK cannot rule out late-onset Pompe disease. A hypothetical CK of 140 U/L may fall within a laboratory's reference interval despite progressive proximal weakness or diaphragm involvement. CK measures muscle injury-related enzyme release, not lysosomal GAA function. Persistent compatible symptoms deserve specialist assessment even when routine muscle markers are reassuring.
How urgent is a positive newborn Pompe disease test?
A positive newborn Pompe disease test needs prompt contact with the screening or metabolic team, and an infant with feeding difficulty, marked hypotonia or suspected heart involvement needs urgent assessment. One positive screening card does not confirm the diagnosis, but suspected classic infantile disease should not wait for a routine appointment several weeks later. Specialists arrange confirmatory enzyme testing, genetic evaluation and cardiac assessment, often in parallel. Severe breathing difficulty or reduced responsiveness requires emergency care.
What is the risk to children if both parents are Pompe carriers?
If both parents carry disease-causing GAA variants, each pregnancy has a 25% probability of an affected child, a 50% probability of a carrier child and a 25% probability of a child inheriting neither familial variant. These probabilities apply independently to every pregnancy. Pseudodeficiency variants are not interchangeable with pathogenic variants in this calculation. Genetic counseling helps confirm the parental findings and explain testing options.
Uzziniet, kā lasīt asins analīžu rezultātus
Augšupielādējiet laboratorijas pārskatu, un Kantesti mākslīgais intelekts dažu sekunžu laikā vienkāršā valodā izskaidros katru biomarķieri. To izmanto vairāk nekā 2 miljoni cilvēku visā pasaulē.
Atsauces
- Klein, T., Mitchell, S., & Weber, H. (2026). Dzelzs izmeklējumu ceļvedis: TIBC, dzelzs piesātinājums un saistīšanas spēja. Kantesti mākslīgā intelekta medicīniskie pētījumi. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT normālais diapazons: D-dimēra un C proteīna rokasgrāmata par asins recēšanu. Kantesti mākslīgā intelekta medicīniskie pētījumi. DOI
- Kishnani PS et al. (2006). Pompe disease diagnosis and management guideline. Medicīniskā ģenētika. DOI PubMed
- Burton BK et al. (2017). The Initial Evaluation of Patients After Positive Newborn Screening: Recommended Algorithms Leading to a Confirmed Diagnosis of Pompe Disease. Pediatrics. DOI
- Richards S et al. (2015). Standarti un vadlīnijas sekvenču variantu interpretācijai: Amerikas Medicīniskās ģenētikas un genomikas koledžas un Molekulārās patoloģijas asociācijas kopīgs konsensa ieteikums. Medicīniskā ģenētika. DOI PubMed
- 2M+Analizētie testi
- 127+Valstis
- 100+Valodas
Par medicīnas komandu


E-E-A-T uzticēšanās signāli
Pieredze
Ārstu vadīta klīniskā laboratorijas interpretācijas darbplūsmu pārskatīšana.
Ekspertīze
Laboratorijas medicīnas fokuss uz to, kā biomarķieri uzvedas klīniskā kontekstā.
Autoritāte
Medicīniski recenzējis Dr. Thomas Klein, piedaloties Dr. Sarah Mitchell un Prof. Dr. Hans Weber.
Uzticamība
Uz pierādījumiem balstīta interpretācija ar skaidriem turpmākās rīcības ceļiem, lai mazinātu trauksmi.






Medicīniskā atruna
Šis raksts ir paredzēts tikai izglītojošiem nolūkiem un nav medicīnisks padoms. Vienmēr konsultējieties ar kvalificētu veselības aprūpes speciālistu, lai pieņemtu lēmumus par diagnostiku un ārstēšanu.
Publicēts · Sazinieties ar redakcijas komandu
Publicējis Kantesti Ltd, reģistrēts Anglijā un Velsā, uzņēmuma reģistrācijas Nr. 17090423, Londona, Apvienotā Karaliste.
