
Una benda reactiva indica una ligason dels anticòrs, pas un diagnostic. L'algoritme complet de testatge, l'istòria d'exposicion e la cronologia dels simptòmas determinan se aquela trobalha sosten una malautiá de Lyme.

Punts essencials
- Las bendas individualas establisson pas una malautiá de Lyme; quitament una benda relativament especifica deu èsser interpretada dins un algoritme de testatge validat en dos nivèls.
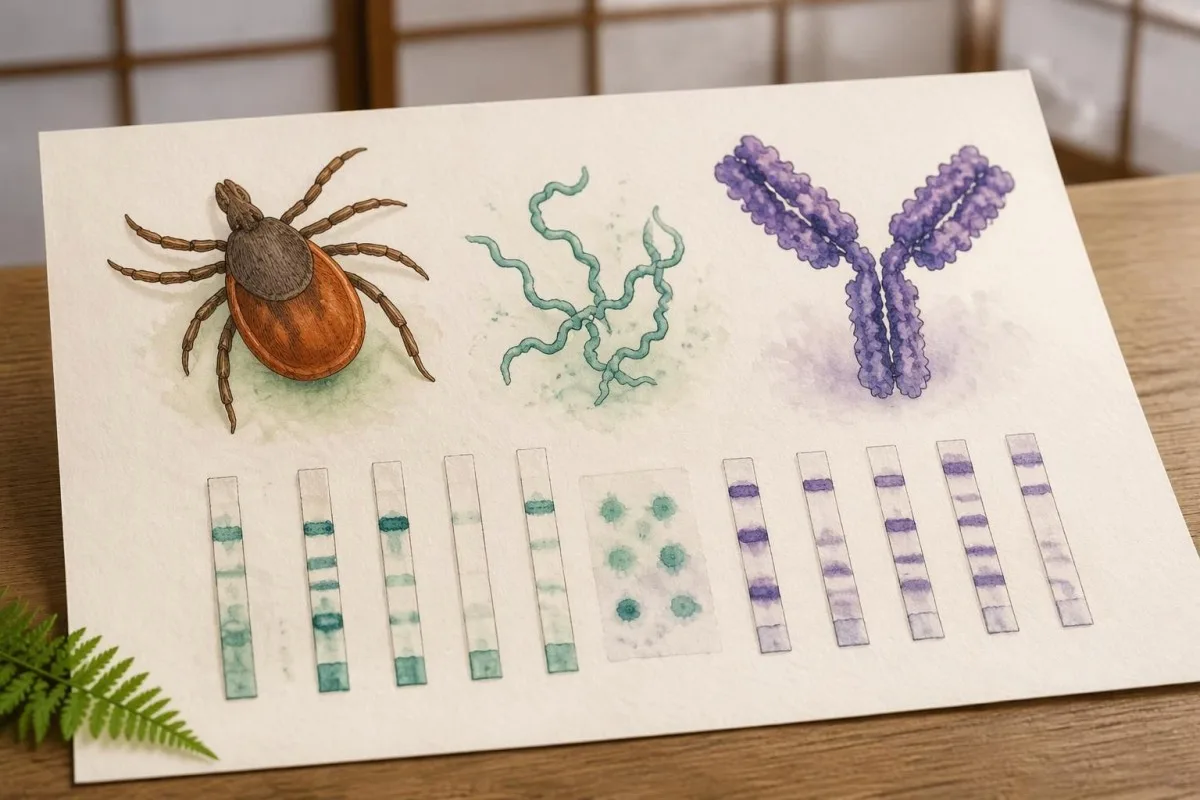
- Critèris tradicionals IgM requerisson almens 2 de las 3 bendas designadas: aproximativament 23–25, 39 e 41 kDa.
- Critèris tradicionals IgG requerisson almens 5 de las 10 bendas designadas: 18, 23, 28, 30, 39, 41, 45, 58, 66 e 93 kDa.
- La règla dels 30 jorns significa que l'IgM isolada deu pas sosténer un diagnostic de Lyme quand los simptòmas dure mai de 30 jorns.
- Un resultat global negatiu pòt coexistir amb de bendas reactivas, perque lo laboratòri avalora un perfil validat, pas se cap de benda apareis.
- Testatge modificat en dos nivèls utiliza 2 immunoanalisis enzimatics sequencials al luòc d’un immunoblot; pòt pas provesir cap de lista de bendas.
- Testing preliminar pòt èsser negatiu abans que los anticòrs se desvolopen; una erupcion tipica d’eritema migrant dins un contèxt d’exposicion apropriada se diagnostica clinicament.
- Anticòrs persistents pòt demorar detectable pendent d’annadas aprèp lo tractament e pòt pas establir una infeccion en cors ni mesurar la garison.
Que significa realament una benda positiva al Western blot de Lyme?
A benda positiva de l’immunoblot de Lyme significa que d’anticòrs se son ligats a un antigen del tèst; aquò establís pas independentament la malautiá de Lyme. Dins lo testatge tradicional dels Estats Units en dos nivèls, IgM exigís 2 de las 3 bendas designadas durant los primièrs 30 jorns dels simptòmas, mentre que IgG n’exigís 5 de 10; lo testatge modificat utiliza 2 immunoanalisis en plaça.

Lo resultat global combina lo tèst de cribratge del primièr nivèl amb lo resultat aproprià del segond nivèl, puslèu que de tractar cada benda visibla coma un diagnostic separat. Un rapòrt que mòstra 1 benda reactiva pòt doncas indicar corrèctament un resultat negatiu, e quitament un resultat positiu complet dels anticòrs deu èsser avalorat en foncion de l’exposicion, dels signes compatibles e d’una malautiá de Lyme anteriora.
L’identitat de la benda respond a una question precisa: quin antigen a atrach la ligason d’anticòrs dins las condicions d’aqueste tèst? Respond pas a las 3 questions que preocupan generalament los pacients—se l’infeccion es presenta ara, se explica lors simptòmas o se cal prendre d’antibiotics; nòstre guida sus resultats d'anticòs positius destria aquestes aspèctes.
Kantesti es un Analizador de tèst de sang d'IA que pòt ajudar a explicar perqué un rapòrt de Lyme conten de bendas reactivas mas una interpretacion negativa en 2 nivèls. Consideram l’interpretacion finala del laboratòri, lo metòde de l’assaig e la durada dels simptòmas coma un contèxt essencial—pas coma de detalhs que se pòdon passar per naut en comptant las linhas mesas en evidéncia dins un rapòrt telecargat.
Cossí lo testatge tradicional de Lyme en dos nivèls determina lo resultat
Testatge estandard en dos nivèls comença amb un immunoanalisi enzimatic, o de còps un tèst d’immunofluorescéncia, e passa a un immunoblot quand lo primièr tèst es positiu o equivòc. Las 2 etapas foncionan amassa; un resultat positiu del cribratge sol es pas un resultat confirmat positiu de serologia per Lyme.

A tèst positiu o equivòc del primièr nivèl seguit d’immunoblots apropriats negatius s’interprèta coma negatiu segon l’algoritme estandard. Lo cribratge inicial capta deliberadament mai de responsas possiblas, mentre que lo segond nivèl filtra la reactivitat non especifica; Moore et al. an descrich aqueste equilibri e sas errors d’interpretacion frequentas dins Emerging Infectious Diseases en 2016.
Un indici de 1.4 dins un tèst de cribratge es pas equivalent a 1.4 dins un autre, perque la composicion antigenica e los lindals dels fabricants diferisson. Parièrament, un resultat de cribratge equivòc es una instruccion per completar l’algoritme—pas un diagnostic a mièg camin entre infeccion e abséncia d’infeccion; resultats qualitatius contra quantitatius explica perqué los formats dels rapòrts comptan.
Demandar un immunoblot aprèp un cribratge negatiu, sens rason clinica per tornar considerar lo moment o l’adequacion de l’assaig, passa per dessús la sequéncia dont las performàncias son estadas avaloradas. Demandatz 3 informacions: lo resultat del cribratge, l’interpretacion del segond nivèl e se totes dos fan partida del meteis percors de testatge validat; un rapòrt incomplet deu pas èsser reconstituït a partir de las bendas solas.
Explicacion de las bendas del Western blot de Lyme: critèris IgM e IgG
Segon los critèris convencionals dels Estats Units, un immunoblot IgM positiu exigís almens 2 de las bendas 23–25, 39 e 41 kDa. Un immunoblot IgG positiu requires at least 5 of the 18, 23, 28, 30, 39, 41, 45, 58, 66 and 93 kDa bands.
Kilodaltons, abbreviated kDa, describe approximate protein molecular mass, not antibody concentration or disease severity. The approximately 23–25 kDa band commonly represents outer surface protein C, 39 kDa represents BmpA and 41 kDa represents flagellin; the numbers identify antigen regions, so a higher-numbered band does not mean a more advanced infection.
The IgG list's 58 kDa criterion excludes GroEL, and reports may use assay-specific names or approximate mass conventions rather than identical labels. Because not every commercial strip uses the same antigen preparation, our guida dels marcadors sanguins should complement—not replace—the actual laboratory legend and the assay manufacturer's interpretation instructions.
Bands at 31 and 34 kDa are not part of the conventional CDC IgG counting criteria, even though they may appear on some reports. Their absence from that list does not make them meaningless biologically, but adding them to manufacture a 5-band positive result changes the validated rule; neither band darkness nor extra bands quantify bacterial burden.
Perqué la benda 41 e d'autras bendas reactivas pòdon èsser de falses senhals
Lo 41 kDa band reacts with flagellin, a protein associated with bacterial movement, and can cross-react with antibodies unrelated to Lyme disease. A single reactive 41 kDa band is therefore insufficient to diagnose Lyme disease, even when a patient has fatigue, aching or a remembered tick bite.
Moore et al. (2016) cited a study in which 41 kDa reactivity occurred in 43% of healthy controls, illustrating why this band cannot stand alone. That percentage is not a universal false-positive rate for every modern assay; it is evidence that recognizable antigen binding can occur in people without the clinical condition being investigated.
Epstein–Barr virus, syphilis, relapsing-fever Borrelia and some autoimmune conditions can contribute to false-positive Lyme serology, although the mechanism and affected assay vary. A recent mononucleosis-like illness should prompt attention to the complete EBV antibody pattern, not the assumption that 1 Lyme band proves a simultaneous tick-borne infection.
Cross-reactivity is not a reason to order every alternative antibody panel: 1 unexplained band usually does not justify broad autoimmune screening. When examination findings genuinely suggest an immune disorder, complement e de l’ANA belongs to a separate clinical question; repeated low-probability testing can generate additional misleading positives rather than a clearer answer.
IgM contra IgG de Lyme: perqué la règla dels 30 jorns de simptòmas es importanta
Lyme IgM should not be used to support a diagnosis when symptoms have lasted more than 30 days. IgM is most useful early, whereas an appropriate IgG response carries greater diagnostic weight later; the clock starts with symptoms of the suspected illness, not the testing date or remembered tick removal.

Lo 30-day restriction reduces misclassification from persistent or nonspecific IgM responses when later disease should usually have an established IgG response. It is an interpretation rule, not a biological switch that flips overnight: antibody maturation varies, and early treatment may alter seroconversion, but those exceptions do not make isolated late IgM reliable evidence.
For a hypothetical patient tested on day 75 of continuous symptoms, IgM bands 23 and 41 with negative IgG should not be used as proof of Lyme disease. By contrast, the same IgM pattern on day 12, following a reactive first-tier assay and compatible exposure, can support an early diagnosis; the numerical band count is identical, but its evidential value changes.
A positive IgM result does not automatically mean a new infection, a misconception also addressed in our Mycoplasma IgM interpretation guide. If symptoms began 8 weeks ago but one symptom appeared yesterday, clinicians need to decide whether this is a genuinely new illness or another feature of the original episode—not simply restart the IgM clock.
Bendas de Lyme positivas, mas resultat global negatiu: exemples detalhats
Positive Lyme bands but negative overall usually means the report did not meet the required pattern within the testing algorithm. For example, 3 designated IgG bands are below the conventional 5-of-10 threshold; that result is negative, not a smaller positive, and it does not measure how much infection is present.

Consider a clearly hypothetical 42-year-old with 10 weeks of fatigue, a reactive screening assay and IgG bands 18, 41 and 58. The IgG immunoblot is negative because only 3 qualifying bands are present; if the examination lacks objective Lyme findings, the next step is a symptom-focused assessment rather than antibiotics prescribed to treat the band's molecular masses.
A second hypothetical patient has a reactive screen, IgM bands 23 and 39, and compatible symptoms beginning 14 days earlier. This can meet the traditional early serologic criteria, but an atypical exposure history or a stronger alternative diagnosis still affects the clinical conclusion; Kantesti AI can explain the 2-of-3 rule without converting it into an independent diagnosis.
A third report lists 5 IgG bands but provides no first-tier result; the missing screening stage prevents straightforward confirmation of a standard 2-tier outcome. Confirmation requirements are assay-specific, as our HSV IgG confirmation guide also illustrates, so request the complete laboratory report rather than borrowing a cutoff or confirmation rule from another infection.
En qué lo testatge modificat en dos nivèls diferís del Western blot
Modified two-tier testing, or MTTT, uses 2 sequential enzyme immunoassays instead of an enzyme immunoassay followed by an immunoblot. A report from this pathway may have no bands at all; its overall interpretation depends on the particular assay combination and its cleared instructions, not the conventional immunoblot band-count criteria.

Lo 2019 CDC recommendation accepted modified algorithms using FDA-cleared assays for that purpose, following clearance of relevant test combinations (Mead et al., 2019). The change was not permission to combine any 2 tests: the evaluated pairing matters, and some combinations improve early sensitivity while preserving high specificity compared with standard two-tier testing.
Some modified algorithms measure total antibodies, while others report separate IgM and IgG components; consequently, the familiar 30-day IgM restriction cannot be mechanically applied to a total-antibody result. Kantesti is an plataforma d’interpretacion d’analisi de sang d’AI that can help distinguish a 2-immunoassay report from an immunoblot report before discussing what its positive or negative designation means.
A second immunoassay is not simply a repeat of the same screening test, and an immunoblot is not routinely needed after a completed validated MTTT result. Our guida de confirmacion de la malautiá de Chagas illustrates the broader principle of complementary assays, but its 2-test rules are different; ask your laboratory which Lyme algorithm produced the final interpretation.
Lo testatge de Lyme pòt èsser negatiu d'ora malgrat una infeccion?
Lyme antibody testing can be negative early because antibodies have not yet reached detectable levels. A typical erythema migrans rash with an appropriate exposure history is diagnosed clinically rather than by waiting for a positive immunoblot; a negative result during the first 1–2 weeks does not safely exclude that presentation.
Across early-infection settings, conventional 2-tier sensitivity has been reported at approximately 30–40%, while specificity remains high when testing and interpretation are appropriate (Moore et al., 2016). These are population estimates, not a personal probability: sensitivity changes with the clinical manifestation, time since onset and whether the patient has already received antibiotics.
For a rash suggestive of but not typical for erythema migrans, the 2020 IDSA/AAN/ACR guideline supports acute serology and, if initially negative, a convalescent sample at least 2–3 weeks later (Lantos et al., 2021). The same guideline recommends clinical diagnosis for a typical lesion; a rash need not have textbook concentric rings to warrant assessment.
Repeating a test 24 hours later usually offers little advantage when the limitation is antibody development rather than a processing error. Our spotted fever testing guide explains a related timing problem, but suspected spotted fever has its own urgent treatment rules; do not delay care for an expanding rash or significant illness while waiting for more bands.
Una IgG de Lyme positiva significa una infeccion activa o un fracàs del tractament?
Positive Lyme IgG cannot distinguish active infection from a previous infection that has resolved. Lyme antibodies can remain detectable for years or decades, and repeat immunoblot testing is not a test of cure; neither a persistent 5-band pattern nor changes in band intensity establish that treatment failed.
Lo 2020 IDSA/AAN/ACR guideline describes persistence of both IgM and IgG responses after infection, which complicates interpretation in previously affected patients (Lantos et al., 2021). A positive result obtained 4 years after treatment must therefore be compared with the clinical history, not interpreted as a laboratory photograph of living bacteria in the body.
Reinfection can occur because previous Lyme disease does not provide reliable lifelong protection, but an old positive antibody result cannot prove a new episode. For a hypothetical person with positive IgG from 2019 and a new expanding rash after recent tick exposure, the new clinical findings matter more than whether a sixth band appears; patrons d'anticòrs CMV illustrate why exposure history and current illness are separate questions.
Persistent fatigue, pain or cognitive symptoms deserve evaluation even when no new laboratory evidence appears. The guideline recommends against additional antibiotics for persistent nonspecific symptoms after recommended treatment when there is no objective evidence of reinfection or treatment failure; 1 positive antibody panel cannot identify the cause of those symptoms or justify an open-ended antibiotic course.
Çò que significa l'IgG en cas de sospècha d'artritis de Lyme o de malautiá neurologica
Lyme arthritis usually produces a strong IgG response, so isolated IgM is poor evidence for that diagnosis. Conventional two-tier serology has approximately 95–100% sensitivity in Lyme arthritis, according to the 2020 IDSA/AAN/ACR guideline; a negative appropriate IgG result should prompt serious consideration of other causes of joint swelling.

A hypothetical patient with a markedly swollen knee and only 2 IgM bands after 3 months of symptoms does not have the expected serologic pattern for Lyme arthritis. The clinician should reassess alternative causes and assay reliability rather than call this late Lyme based on IgM alone; when indicated, joint fluid examination answers additional questions that the antibody test cannot.
Suspected central nervous system Lyme disease requires clinical assessment and, when cerebrospinal fluid testing is undertaken, simultaneous CSF and serum for a validated antibody index. Testing CSF antibody alone or running a standalone CSF immunoblot is not the preferred approach; 1 elevated index may also persist after treatment, so it must be interpreted alongside the neurological findings and CSF cell response.
Numb feet or tingling do not become Lyme-specific because 41 kDa is reactive; neuropathy has metabolic, mechanical and immune causes. Our anti-MAG neuropathy guide explains one targeted alternative, while immunoglobulin panel interpretation clarifies that total serum IgG is different from the 5-of-10 Lyme-specific IgG immunoblot criterion.
Perqué los laboratòris e los païses pòdon utilizar de critèris diferents per Lyme
Lyme immunoblot criteria are assay- and region-dependent, so conventional US 5-of-10 IgG counting rules should not automatically be imposed on every European report. European assays may use different Borrelia antigens and recombinant line blots because the species causing human Lyme borreliosis differ across regions.
B. burgdorferi sensu stricto predominates in North America, while European disease also commonly involves B. afzelii and B. garinii. A report using VlsE, OspC or other recombinant antigen labels may therefore not resemble a 10-position conventional US blot; the clinically useful question is whether the assay was validated for the exposure setting and interpreted according to its instructions.
Different laboratory criteria are not automatically inferior, but claims that 1 or 2 bands prove disease require evidence for that assay's complete diagnostic performance. When reading a report described by Kantesti, consult the laboratory's interpretation and our encastre de validacion medica separately; general AI assessment or a software benchmark is not proof that a particular Lyme assay has validated sensitivity and specificity.
Record 3 details before comparing reports from different laboratories: assay manufacturer, algorithm type and the country where exposure occurred. Our guia de verificacion de la font del rapòrt IA explains why preserving source wording matters; apparent conversion from negative to positive may reflect a changed method or cutoff rather than a newly acquired infection or worsening illness.
Las bendas de Lyme identifican Babesia, Anaplasma o d'autras coinfeccions?
Lyme Western blot bands do not diagnose tick-borne coinfections. Babesia, Anaplasma and Ehrlichia require their own clinical assessment and tests; 1 positive Lyme antibody result neither confirms nor excludes these infections, even when an exposure setting allows more than one tick-borne organism to be transmitted.

Babesiosi deserves consideration when relevant exposure accompanies fever and evidence such as anemia, low platelets or hemolysis, especially if fever persists during Lyme-directed treatment. A Babesia antibody titer of 1:256 alone does not establish current infection; our Babesia test interpretation guide explains why a cellular sample examination or PCR may be needed to demonstrate active infection.
Anaplasmòsi can produce fever, leukopenia, thrombocytopenia and elevated liver enzymes, findings that should not be explained away as extra Lyme bands. PCR is most useful during the first week of illness and becomes less sensitive after appropriate antibiotics; our Anaplasma sample timing guide separates this early direct-detection window from later antibody interpretation.
Ehrlichiosis follows a different organism-specific testing pathway, and a negative early antibody result is not a safe reason to dismiss significant febrile illness. Our Ehrlichia PCR and titer guide explains why 2 samples collected at different times may help establish seroconversion; targeted testing should follow symptoms, geography and laboratory abnormalities rather than an indiscriminate panel ordered for isolated fatigue.
De qué cal far amb un compte rendu de test de Lyme pas clar?
For an unclear Lyme report, obtain the complete 2-tier interpretation, write down symptom onset and discuss exposure plus objective findings with a clinician. Faint or isolated bands do not determine urgency; fainting, chest pain, breathlessness, a markedly slow pulse or new neurological deficits require prompt assessment regardless of the antibody result.
Lyme carditis can cause heart conduction block, so fainting or palpitations after compatible exposure should not wait for an immunoblot to become positive. The 2020 IDSA/AAN/ACR guideline identifies a PR interval greater than 300 milliseconds, other arrhythmias or features of myopericarditis as reasons for hospital admission with monitoring; that interval is measured on an ECG, not inferred from band intensity.
New facial weakness warrants urgent assessment, and sudden facial droop with arm weakness or speech difficulty needs emergency evaluation for stroke rather than attribution to Lyme. Our guida dels signes d’avertiment d’un AVC explains that distinction; for a routine appointment, bring 4 dates—possible exposure, first symptom, sample collection and antibiotic initiation—because each changes a different part of the reasoning.
Kantesti es un Outil d’analisi de sang amb IA that can help organize the 2-tier result, reported bands and missing clinical context into questions for your appointment. Our guia de tecnologia amb IA describes the explanation workflow, but our AI cannot examine a rash, measure an ECG interval, confirm Lyme disease independently or decide whether you should start, stop or extend antibiotics.
Publicacions de recèrca, limits de las evidéncias e interpretacion segura
The clinical interpretation in this article rests on 3 directly relevant sources: a laboratory-diagnosis review, the CDC's modified two-tier recommendation and the IDSA/AAN/ACR Lyme guideline. The 2 additional Figshare publications listed below concern other health topics and must not be treated as validation of Lyme band interpretation or Lyme diagnosis.

Moore et al. (2016) explains why individual bands and incomplete testing sequences create diagnostic errors; Mead et al. (2019) establishes the CDC recommendation for appropriately cleared modified algorithms. Lantos et al. (2021), publishing the 2020 guideline, connects testing to clinical manifestations, including early rash, arthritis and neurological disease; these sources support different parts of the reasoning rather than one universal band shortcut.
The 2 Figshare records address women's hormonal health and multilingual AI-assisted hantavirus triage, respectively, not Lyme immunoblot performance. A deployment involving 50,000 interpreted reports, as described in the hantavirus publication's title, cannot establish sensitivity, specificity or patient benefit for Lyme diagnosis; those claims would require Lyme-specific methods, reference standards and evaluation populations.
Los documents de Kantesti principis d’IA responsabla place report explanation alongside—not above—the laboratory and clinician, including when IgM appears after 30 days of symptoms. For symptoms linked to cycle changes or menopausal transition, our hormonal symptom guide addresses a separate assessment pathway; symptom overlap is a reason to investigate carefully, not evidence that a reactive Lyme band explains everything.
Preguntes més freqüents
Una sola banda positiva en lo Western blot per la malautiá de Lyme pòt significar que soi malaut de Lyme?
Una banda reactiva en una immunotransferéncia de Lyme non establís pas una malautiá de Lyme. Los critèris convencionals dels Estats Units exigisson almens 2 de las 3 bandas IgM designadas pendent los primièrs 30 jorns dels simptòmas, o 5 de las 10 bandas IgG designadas, dins l’encastre aproprià d’analisis en doas etapas. Una banda unica pòt reflectir una reactivitat crosada o una responsa anticossala precoça incomplèta, segon lo cas. Una erupcion tipica d’eritema migrant après una exposicion adequada pòt encara sosténer un diagnostic clinic malgrat una serologia precoça negativa.
Perqué d’unes bendas de Lyme son positivas, mas lo tèst global es negatiu?
Un tèst de Lyme pòt conténer de bendas reactivas mas demorar negatiu, perque l’immunoblot a pas atench lo perfil validat exigit per son algoritme de tèst. Per exemple, 3 bendas IgG qualificantas demoran en dejós del lindal convencional de 5 sus 10 bendas IgG. Un test de primièr nivèl positiu o equivòc seguit d’immunoblots apropriats negatius s’interprèta coma negatiu dins los tèsts estandards en dos nivèls. Se los simptòmas son fòrça recents, un professional de santat pòt envisatjar de tornar far lo tèst après un interval apropriats, puslèu que de requalificar lo perfil incomplet de positiu.
Qué significa una banda de Lyme positiva de 41 kDa?
La banda de Lyme de 41 kDa reflectís generalament la fixacion d’anticòsses a la flagellina, una proteïna bacteriana relacionada amb la motilitat que pòt reagir de biais crosat amb d’anticòsses sens rapòrt amb la malautiá de Lyme. Es pas qu’una de las bandas designadas utilizadas dins los critèris convencionals d’immunoblot e pòt pas, tota sola, diagnosticar la malautiá de Lyme. Moore et al. (2016) citèron un estudi que trobèt aquesta banda en 43% dels contraròtles sans, mas aquel percentatge es pas un taus universal per totes los tèsts. La sequéncia completa dels tèsts e la presentacion clinica determinan se lo resultat sosten la diagnostica de la malautiá de Lyme.
Una IgM anti-Lyme positiva e una IgG negativa son la pròva d’una infeccion recenta ?
La positivitat de les IgM contra la malaltia de Lyme amb IgG negatives només pot avalar una infecció precoç si concorda amb l’algoritme de proves pertinent, la presentació clínica i el moment de l’evolució. No s’ha de fer servir una IgM aïllada per avalar un diagnòstic de malaltia de Lyme quan els símptomes duren més de 30 dies, perquè una IgM persistent o inespecífica pot induir a error en la interpretació. Per exemple, 2 bandes d’IgM qualificants el dia 14 tenen un significat diferent del mateix patró després de 3 mesos de símptomes continus. La regla temporal fa referència a l’inici dels símptomes, no al dia en què es va recollir la mostra de laboratori.
Pòdi aver un test de Lyme positiu sens cap banda sus lo Western blot?
Òc: un algorisme de Lyme modificat e validat, basat sus dos imunoassaigs enzimatics consecutius, pòt èsser utilizat sens efectuar cap d’immunoblot Western. En 2019, los CDC recomandèron d’algorismes modificats autorizats per la FDA e apropriats. Qualques combinasons d’assaigs mesuran los anticòrs totals, mentre que d’autras donan de resultats separats per las IgM e las IgG; las règlas convencionalas de comptatge de bendas s’aplican doncas pas a totes los rapòrts. Demandatz al laboratòri quin algorisme e quina combinason d’assaigs an servit a establir l’interpretacion finala.
Las bendas del Western blot de Lyme devon desaparéisser après los antibiotics?
Las bandes del Western blot per la malautiá de Lyme an desapareisson pas necessàriament aprèp un tractament capitat, perque los anticòrs pòdon persistir pendent d’annadas o de decennis. Un perfil IgG persistent de 5 bandes prova pas que l’infeccion siá encara activa, e repetir lo tèst de las bandes es pas un tèst de guison validat. La responsa al tractament s’avalua en foncion de l’evolucion clinica e de las constatacions objectivas pertinents, e non pas en exigent que lo panèl d’anticòrs vengue negatiu. De simptòmas novèls o una novèla exposicion a una tissa necessitan una novèla avaloracion clinica, perque d’ancians anticòrs pòdon pas establir una reinfeccion.
Fasètz-vos explicar los resultats analisi de sang
Telecargatz vòstre compte rendut de laboratòri e l’IA de Kantesti explica cada biomarcador en lenga simpla en qualques segondas. Utilizat per mai de 2 milions de personas dins lo mond.
Referéncias
- Klein, T., Mitchell, S., & Weber, H. (2026). Guia de santat de las femnas: ovulacion, menopausa e simptòmas ormonals. Recèrca medicala per IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Ajuda multilingüa a la presa de decisions clinicas amb IA per al triatge precoç de l’hantavirus: concepcion, validacion de l’engenharia e desplegament en condicions realas sus 50,000 rapòrts d’interpretacion d’analisis de sang. Recèrca medicala per IA de Kantesti. DOI
- Moore A et al. (2016). Current Guidelines, Common Clinical Pitfalls, and Future Directions for Laboratory Diagnosis of Lyme Disease, United States. Emerging Infectious Diseases. DOI PubMed
- Mead P et al. (2019). Updated CDC Recommendation for Serologic Diagnosis of Lyme Disease. MMWR Morbidity and Mortality Weekly Report. DOI
- Lantos PM et al. (2021). Clinical Practice Guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease. Clinical Infectious Diseases. DOI
- 2M+Tèsts analisats
- 127+Païses
- 100+Lengas
A prepaus de l’equipa medicala


Senhals de confiança E-E-A-T
Experiéncia
Revisión clinica menada pel metge de las practicas d’interpretacion de las analisis.
Expertisa
Fòcus sus la medicina de laboratòri sus cossí los biomarcadors se comportan dins un contèxte clinic.
Autoritat
Revisat medicalament pel Dr Thomas Klein, amb de contribucions de la Dr Sarah Mitchell e del Prof. Dr Hans Weber.
Fisança
Interpretacion basada sus d’evidéncias amb de camins de seguiment clars per reduzir l’alarmisme.






Avís medical
Aqueste article es solament per tòcas educatius e constituís pas de conselh medical. Consultatz totjorn un professional de la sant qualificat per las decisions de diagnostica e de tractament.
Publicat · Contactar l’equipa editoriala
Publicat per Kantesti Ltd, enregistrada en Anglatèrra e País de Galas, n° d’entrepresa. 17090423, Londres, Reialme Unit.
