
Pita reaktif menunjukkan pengikatan antibodi—bukan diagnosis. Algoritme pengujian lengkap, riwayat paparan, dan linimasa gejala menentukan apakah temuan tersebut mendukung penyakit Lyme.

Poin-poin penting
- Pita individual tidak memastikan penyakit Lyme; bahkan pita yang relatif spesifik pun perlu ditafsirkan dalam algoritme pengujian 2 tingkat yang tervalidasi.
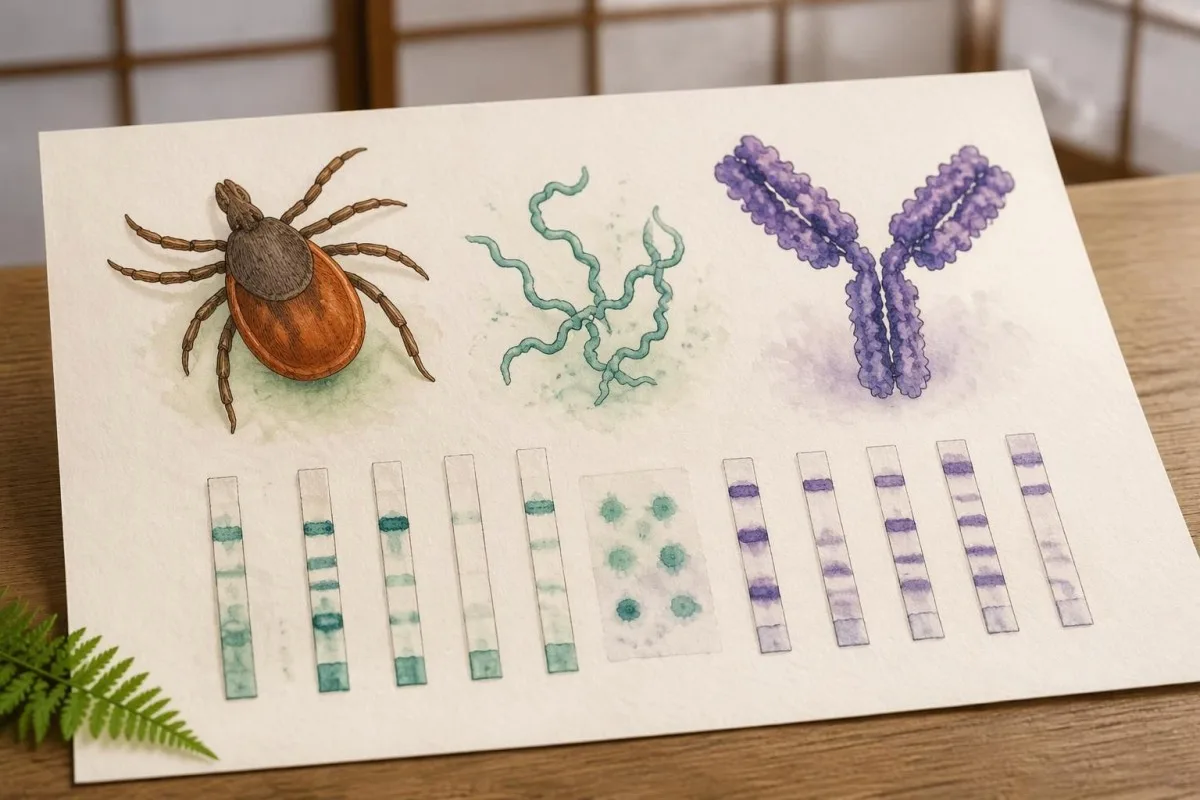
- Kriteria IgM tradisional mensyaratkan setidaknya 2 dari 3 pita yang ditentukan: sekitar 23–25, 39, dan 41 kDa.
- Kriteria IgG tradisional mensyaratkan setidaknya 5 dari 10 pita yang ditentukan: 18, 23, 28, 30, 39, 41, 45, 58, 66, dan 93 kDa.
- Aturan 30 hari berarti IgM tunggal tidak seharusnya mendukung diagnosis Lyme ketika gejala telah berlangsung lebih dari 30 hari.
- Hasil keseluruhan negatif dapat muncul bersamaan dengan pita reaktif karena laboratorium mengevaluasi pola yang telah divalidasi, bukan apakah ada pita yang muncul.
- Pengujian dua tingkat yang dimodifikasi menggunakan 2 uji imunoasai berurutan alih-alih imunoblot; hasilnya mungkin tidak mencantumkan daftar pita.
- Pengujian awal dapat memberikan hasil negatif sebelum antibodi terbentuk; ruam eritema migrans yang khas dalam konteks paparan yang sesuai didiagnosis secara klinis.
- Antibodi yang menetap dapat tetap terdeteksi selama bertahun-tahun setelah pengobatan dan tidak dapat memastikan adanya infeksi yang masih berlangsung atau mengukur kesembuhan.
Apa sebenarnya arti pita Western blot Lyme yang positif?
A pita Western blot Lyme positif berarti antibodi berikatan dengan antigen uji; hal ini tidak secara independen memastikan penyakit Lyme. Dalam pengujian dua tingkat tradisional di AS, IgM memerlukan 2 dari 3 pita yang ditetapkan selama 30 hari pertama gejala, sedangkan IgG memerlukan 5 dari 10; pengujian yang dimodifikasi menggunakan 2 uji imunoasai.

Itu hasil keseluruhan menggabungkan uji skrining tingkat pertama dengan hasil tingkat kedua yang sesuai, alih-alih memperlakukan setiap garis yang terlihat sebagai diagnosis terpisah. Karena itu, laporan yang menunjukkan 1 pita reaktif dapat dengan tepat menyatakan hasil negatif, dan bahkan hasil antibodi lengkap yang positif harus dipertimbangkan berdasarkan paparan, temuan yang sesuai, dan riwayat penyakit Lyme sebelumnya.
Identitas pita menjawab pertanyaan yang sempit: antigen mana yang menarik ikatan antibodi dalam kondisi uji ini? Hal itu tidak menjawab 3 pertanyaan yang biasanya menjadi perhatian pasien—apakah infeksi sedang terjadi sekarang, apakah infeksi itu menjelaskan gejala mereka, atau apakah antibiotik diperlukan; panduan kami tentang hasil antibodi positif membedakan hal-hal ini.
Kantesti adalah seorang Analisa tes darah AI yang dapat membantu menjelaskan mengapa laporan Lyme memuat pita reaktif tetapi interpretasi dua tingkatnya negatif. Kami menganggap interpretasi akhir laboratorium, metode uji, dan durasi gejala sebagai konteks yang penting—bukan detail yang dapat dikesampingkan dengan menghitung baris yang disorot dalam laporan yang diunggah.
Cara pengujian Lyme dua tingkat tradisional menentukan hasil
Pengujian dua tingkat standar dimulai dengan uji imunoasai enzim, atau terkadang uji imunofluoresensi, lalu dilanjutkan dengan imunoblot jika hasil tes pertama positif atau meragukan. Kedua tahap bekerja bersama; hasil skrining positif saja bukanlah hasil serologi Lyme positif yang terkonfirmasi.

A hasil uji tingkat pertama positif atau meragukan yang diikuti imunoblot yang sesuai dengan hasil negatif diinterpretasikan sebagai negatif menurut algoritme standar. Skrining awal sengaja menangkap lebih banyak kemungkinan respons, sedangkan tahap kedua menyaring reaktivitas nonspesifik; Moore et al. menjelaskan keseimbangan ini dan kesalahan interpretasinya yang umum dalam Emerging Infectious Diseases pada tahun 2016.
Indeks 1.4 pada satu uji skrining tidak dapat disamakan dengan 1.4 pada uji lainnya, karena komposisi antigen dan nilai ambang produsen berbeda. Demikian pula, hasil skrining yang meragukan merupakan instruksi untuk menyelesaikan algoritme—bukan diagnosis di tengah-tengah antara infeksi dan tidak adanya infeksi; hasil kualitatif versus kuantitatif menjelaskan mengapa format laporan penting.
Memesan imunoblot setelah hasil skrining negatif, tanpa alasan klinis untuk mempertimbangkan kembali waktu pengujian atau kesesuaian uji, berarti melewati urutan yang kinerjanya telah dievaluasi. Mintalah 3 informasi: hasil skrining, interpretasi tingkat kedua, dan apakah keduanya termasuk dalam alur pengujian tervalidasi yang sama; laporan yang tidak lengkap tidak boleh direkonstruksi hanya dari pita.
Penjelasan pita Western blot Lyme: kriteria IgM dan IgG
Menurut kriteria konvensional AS, hasil imunoblot IgM positif memerlukan setidaknya 2 dari pita 23–25, 39, dan 41 kDa. Hasil imunoblot IgG positif requires at least 5 of the 18, 23, 28, 30, 39, 41, 45, 58, 66 and 93 kDa bands.
Kilodaltons, abbreviated kDa, describe approximate protein molecular mass, not antibody concentration or disease severity. The approximately 23–25 kDa band commonly represents outer surface protein C, 39 kDa represents BmpA and 41 kDa represents flagellin; the numbers identify antigen regions, so a higher-numbered band does not mean a more advanced infection.
The IgG list's 58 kDa criterion excludes GroEL, and reports may use assay-specific names or approximate mass conventions rather than identical labels. Because not every commercial strip uses the same antigen preparation, our panduan penanda tes darah kami should complement—not replace—the actual laboratory legend and the assay manufacturer's interpretation instructions.
Bands at 31 and 34 kDa are not part of the conventional CDC IgG counting criteria, even though they may appear on some reports. Their absence from that list does not make them meaningless biologically, but adding them to manufacture a 5-band positive result changes the validated rule; neither band darkness nor extra bands quantify bacterial burden.
Mengapa pita 41 dan pita reaktif lainnya dapat menjadi sinyal palsu
Itu 41 kDa band reacts with flagellin, a protein associated with bacterial movement, and can cross-react with antibodies unrelated to Lyme disease. A single reactive 41 kDa band is therefore insufficient to diagnose Lyme disease, even when a patient has fatigue, aching or a remembered tick bite.
Moore et al. (2016) cited a study in which 41 kDa reactivity occurred in 43% of healthy controls, illustrating why this band cannot stand alone. That percentage is not a universal false-positive rate for every modern assay; it is evidence that recognizable antigen binding can occur in people without the clinical condition being investigated.
Epstein–Barr virus, syphilis, relapsing-fever Borrelia and some autoimmune conditions can contribute to false-positive Lyme serology, although the mechanism and affected assay vary. A recent mononucleosis-like illness should prompt attention to the complete EBV antibody pattern, not the assumption that 1 Lyme band proves a simultaneous tick-borne infection.
Cross-reactivity is not a reason to order every alternative antibody panel: 1 unexplained band usually does not justify broad autoimmune screening. When examination findings genuinely suggest an immune disorder, interpretasi komplemen dan ANA belongs to a separate clinical question; repeated low-probability testing can generate additional misleading positives rather than a clearer answer.
IgM vs IgG Lyme: mengapa aturan gejala 30 hari penting
Lyme IgM should not be used to support a diagnosis when symptoms have lasted more than 30 days. IgM is most useful early, whereas an appropriate IgG response carries greater diagnostic weight later; the clock starts with symptoms of the suspected illness, not the testing date or remembered tick removal.

Itu 30-day restriction reduces misclassification from persistent or nonspecific IgM responses when later disease should usually have an established IgG response. It is an interpretation rule, not a biological switch that flips overnight: antibody maturation varies, and early treatment may alter seroconversion, but those exceptions do not make isolated late IgM reliable evidence.
For a hypothetical patient tested on day 75 of continuous symptoms, IgM bands 23 and 41 with negative IgG should not be used as proof of Lyme disease. By contrast, the same IgM pattern on day 12, following a reactive first-tier assay and compatible exposure, can support an early diagnosis; the numerical band count is identical, but its evidential value changes.
A positive IgM result does not automatically mean a new infection, a misconception also addressed in our Mycoplasma IgM interpretation guide. If symptoms began 8 weeks ago but one symptom appeared yesterday, clinicians need to decide whether this is a genuinely new illness or another feature of the original episode—not simply restart the IgM clock.
Pita Lyme positif tetapi hasil keseluruhan negatif: contoh kasus
Positive Lyme bands but negative overall usually means the report did not meet the required pattern within the testing algorithm. For example, 3 designated IgG bands are below the conventional 5-of-10 threshold; that result is negative, not a smaller positive, and it does not measure how much infection is present.

Consider a clearly hypothetical 42-year-old with 10 weeks of fatigue, a reactive screening assay and IgG bands 18, 41 and 58. The IgG immunoblot is negative because only 3 qualifying bands are present; if the examination lacks objective Lyme findings, the next step is a symptom-focused assessment rather than antibiotics prescribed to treat the band's molecular masses.
A second hypothetical patient has a reactive screen, IgM bands 23 and 39, and compatible symptoms beginning 14 days earlier. This can meet the traditional early serologic criteria, but an atypical exposure history or a stronger alternative diagnosis still affects the clinical conclusion; Kantesti AI can explain the 2-of-3 rule without converting it into an independent diagnosis.
A third report lists 5 IgG bands but provides no first-tier result; the missing screening stage prevents straightforward confirmation of a standard 2-tier outcome. Confirmation requirements are assay-specific, as our HSV IgG confirmation guide also illustrates, so request the complete laboratory report rather than borrowing a cutoff or confirmation rule from another infection.
Perbedaan pengujian dua tingkat termodifikasi dengan Western blot
Modified two-tier testing, or MTTT, uses 2 sequential enzyme immunoassays instead of an enzyme immunoassay followed by an immunoblot. A report from this pathway may have no bands at all; its overall interpretation depends on the particular assay combination and its cleared instructions, not the conventional immunoblot band-count criteria.

Itu 2019 CDC recommendation accepted modified algorithms using FDA-cleared assays for that purpose, following clearance of relevant test combinations (Mead et al., 2019). The change was not permission to combine any 2 tests: the evaluated pairing matters, and some combinations improve early sensitivity while preserving high specificity compared with standard two-tier testing.
Some modified algorithms measure total antibodies, while others report separate IgM and IgG components; consequently, the familiar 30-day IgM restriction cannot be mechanically applied to a total-antibody result. Kantesti is an platform interpretasi tes darah AI that can help distinguish a 2-immunoassay report from an immunoblot report before discussing what its positive or negative designation means.
A second immunoassay is not simply a repeat of the same screening test, and an immunoblot is not routinely needed after a completed validated MTTT result. Our panduan konfirmasi Chagas kami illustrates the broader principle of complementary assays, but its 2-test rules are different; ask your laboratory which Lyme algorithm produced the final interpretation.
Dapatkah hasil pengujian Lyme negatif pada tahap awal meski terdapat infeksi?
Lyme antibody testing can be negative early because antibodies have not yet reached detectable levels. A typical erythema migrans rash with an appropriate exposure history is diagnosed clinically rather than by waiting for a positive immunoblot; a negative result during the first 1–2 weeks does not safely exclude that presentation.
Across early-infection settings, conventional 2-tier sensitivity has been reported at approximately 30–40%, while specificity remains high when testing and interpretation are appropriate (Moore et al., 2016). These are population estimates, not a personal probability: sensitivity changes with the clinical manifestation, time since onset and whether the patient has already received antibiotics.
For a rash suggestive of but not typical for erythema migrans, the 2020 IDSA/AAN/ACR guideline supports acute serology and, if initially negative, a convalescent sample at least 2–3 weeks later (Lantos et al., 2021). The same guideline recommends clinical diagnosis for a typical lesion; a rash need not have textbook concentric rings to warrant assessment.
Repeating a test 24 hours later usually offers little advantage when the limitation is antibody development rather than a processing error. Our spotted fever testing guide explains a related timing problem, but suspected spotted fever has its own urgent treatment rules; do not delay care for an expanding rash or significant illness while waiting for more bands.
Apakah IgG Lyme positif berarti infeksi aktif atau pengobatan gagal?
Positive Lyme IgG cannot distinguish active infection from a previous infection that has resolved. Lyme antibodies can remain detectable for years or decades, and repeat immunoblot testing is not a test of cure; neither a persistent 5-band pattern nor changes in band intensity establish that treatment failed.
Itu 2020 IDSA/AAN/ACR guideline describes persistence of both IgM and IgG responses after infection, which complicates interpretation in previously affected patients (Lantos et al., 2021). A positive result obtained 4 years after treatment must therefore be compared with the clinical history, not interpreted as a laboratory photograph of living bacteria in the body.
Reinfection can occur because previous Lyme disease does not provide reliable lifelong protection, but an old positive antibody result cannot prove a new episode. For a hypothetical person with positive IgG from 2019 and a new expanding rash after recent tick exposure, the new clinical findings matter more than whether a sixth band appears; pola antibodi CMV yang umum illustrate why exposure history and current illness are separate questions.
Persistent fatigue, pain or cognitive symptoms deserve evaluation even when no new laboratory evidence appears. The guideline recommends against additional antibiotics for persistent nonspecific symptoms after recommended treatment when there is no objective evidence of reinfection or treatment failure; 1 positive antibody panel cannot identify the cause of those symptoms or justify an open-ended antibiotic course.
Arti IgG pada dugaan artritis Lyme atau penyakit neurologis
Lyme arthritis usually produces a strong IgG response, so isolated IgM is poor evidence for that diagnosis. Conventional two-tier serology has approximately 95–100% sensitivity in Lyme arthritis, according to the 2020 IDSA/AAN/ACR guideline; a negative appropriate IgG result should prompt serious consideration of other causes of joint swelling.

A hypothetical patient with a markedly swollen knee and only 2 IgM bands after 3 months of symptoms does not have the expected serologic pattern for Lyme arthritis. The clinician should reassess alternative causes and assay reliability rather than call this late Lyme based on IgM alone; when indicated, joint fluid examination answers additional questions that the antibody test cannot.
Suspected central nervous system Lyme disease requires clinical assessment and, when cerebrospinal fluid testing is undertaken, simultaneous CSF and serum for a validated antibody index. Testing CSF antibody alone or running a standalone CSF immunoblot is not the preferred approach; 1 elevated index may also persist after treatment, so it must be interpreted alongside the neurological findings and CSF cell response.
Numb feet or tingling do not become Lyme-specific because 41 kDa is reactive; neuropathy has metabolic, mechanical and immune causes. Our anti-MAG neuropathy guide explains one targeted alternative, while immunoglobulin panel interpretation clarifies that total serum IgG is different from the 5-of-10 Lyme-specific IgG immunoblot criterion.
Mengapa laboratorium dan negara dapat menggunakan kriteria Lyme yang berbeda
Lyme immunoblot criteria are assay- and region-dependent, so conventional US 5-of-10 IgG counting rules should not automatically be imposed on every European report. European assays may use different Borrelia antigens and recombinant line blots because the species causing human Lyme borreliosis differ across regions.
B. burgdorferi sensu stricto predominates in North America, while European disease also commonly involves B. afzelii and B. garinii. A report using VlsE, OspC or other recombinant antigen labels may therefore not resemble a 10-position conventional US blot; the clinically useful question is whether the assay was validated for the exposure setting and interpreted according to its instructions.
Different laboratory criteria are not automatically inferior, but claims that 1 or 2 bands prove disease require evidence for that assay's complete diagnostic performance. When reading a report described by Kantesti, consult the laboratory's interpretation and our kerangka validasi medis separately; general AI assessment or a software benchmark is not proof that a particular Lyme assay has validated sensitivity and specificity.
Record 3 details before comparing reports from different laboratories: assay manufacturer, algorithm type and the country where exposure occurred. Our AI report source-check kami explains why preserving source wording matters; apparent conversion from negative to positive may reflect a changed method or cutoff rather than a newly acquired infection or worsening illness.
Apakah pita Lyme mengidentifikasi Babesia, Anaplasma, atau koinfeksi lainnya?
Lyme Western blot bands do not diagnose tick-borne coinfections. Babesia, Anaplasma and Ehrlichia require their own clinical assessment and tests; 1 positive Lyme antibody result neither confirms nor excludes these infections, even when an exposure setting allows more than one tick-borne organism to be transmitted.

Babesiosis deserves consideration when relevant exposure accompanies fever and evidence such as anemia, low platelets or hemolysis, especially if fever persists during Lyme-directed treatment. A Babesia antibody titer of 1:256 alone does not establish current infection; our Babesia test interpretation guide explains why a cellular sample examination or PCR may be needed to demonstrate active infection.
Anaplasmosis can produce fever, leukopenia, thrombocytopenia and elevated liver enzymes, findings that should not be explained away as extra Lyme bands. PCR is most useful during the first week of illness and becomes less sensitive after appropriate antibiotics; our Anaplasma sample timing guide separates this early direct-detection window from later antibody interpretation.
Ehrlichiosis follows a different organism-specific testing pathway, and a negative early antibody result is not a safe reason to dismiss significant febrile illness. Our Ehrlichia PCR and titer guide explains why 2 samples collected at different times may help establish seroconversion; targeted testing should follow symptoms, geography and laboratory abnormalities rather than an indiscriminate panel ordered for isolated fatigue.
Apa yang harus Anda lakukan jika laporan tes Lyme tidak jelas?
For an unclear Lyme report, obtain the complete 2-tier interpretation, write down symptom onset and discuss exposure plus objective findings with a clinician. Faint or isolated bands do not determine urgency; fainting, chest pain, breathlessness, a markedly slow pulse or new neurological deficits require prompt assessment regardless of the antibody result.
Lyme carditis can cause heart conduction block, so fainting or palpitations after compatible exposure should not wait for an immunoblot to become positive. The 2020 IDSA/AAN/ACR guideline identifies a PR interval greater than 300 milliseconds, other arrhythmias or features of myopericarditis as reasons for hospital admission with monitoring; that interval is measured on an ECG, not inferred from band intensity.
New facial weakness warrants urgent assessment, and sudden facial droop with arm weakness or speech difficulty needs emergency evaluation for stroke rather than attribution to Lyme. Our panduan tanda peringatan stroke explains that distinction; for a routine appointment, bring 4 dates—possible exposure, first symptom, sample collection and antibiotic initiation—because each changes a different part of the reasoning.
Kantesti adalah seorang Alat analisis pemeriksaan darah berbasis AI that can help organize the 2-tier result, reported bands and missing clinical context into questions for your appointment. Our panduan teknologi AI describes the explanation workflow, but our AI cannot examine a rash, measure an ECG interval, confirm Lyme disease independently or decide whether you should start, stop or extend antibiotics.
Publikasi penelitian, batas bukti, dan interpretasi yang aman
The clinical interpretation in this article rests on 3 directly relevant sources: a laboratory-diagnosis review, the CDC's modified two-tier recommendation and the IDSA/AAN/ACR Lyme guideline. The 2 additional Figshare publications listed below concern other health topics and must not be treated as validation of Lyme band interpretation or Lyme diagnosis.

Moore et al. (2016) explains why individual bands and incomplete testing sequences create diagnostic errors; Mead et al. (2019) establishes the CDC recommendation for appropriately cleared modified algorithms. Lantos et al. (2021), publishing the 2020 guideline, connects testing to clinical manifestations, including early rash, arthritis and neurological disease; these sources support different parts of the reasoning rather than one universal band shortcut.
The 2 Figshare records address women's hormonal health and multilingual AI-assisted hantavirus triage, respectively, not Lyme immunoblot performance. A deployment involving 50,000 interpreted reports, as described in the hantavirus publication's title, cannot establish sensitivity, specificity or patient benefit for Lyme diagnosis; those claims would require Lyme-specific methods, reference standards and evaluation populations.
Materi Kantesti AI yang bertanggung jawab place report explanation alongside—not above—the laboratory and clinician, including when IgM appears after 30 days of symptoms. For symptoms linked to cycle changes or menopausal transition, our hormonal symptom guide addresses a separate assessment pathway; symptom overlap is a reason to investigate carefully, not evidence that a reactive Lyme band explains everything.
Pertanyaan yang sering diajukan
Apakah satu pita positif pada Western blot Lyme berarti saya menderita penyakit Lyme?
Satu pita Western blot Lyme yang reaktif tidak menegakkan diagnosis penyakit Lyme. Kriteria konvensional di AS mensyaratkan setidaknya 2 dari 3 pita IgM yang ditetapkan selama 30 hari pertama gejala, atau 5 dari 10 pita IgG yang ditetapkan, dalam alur pemeriksaan dua tahap yang sesuai. Satu pita dapat mencerminkan reaktivitas silang atau respons antibodi dini yang belum lengkap, bergantung pada situasinya. Ruam eritema migrans yang khas setelah paparan yang sesuai tetap dapat mendukung diagnosis klinis meskipun serologi dini negatif.
Mengapa beberapa pita Lyme positif, tetapi hasil tes secara keseluruhan negatif?
Tes Lyme dapat menunjukkan pita reaktif tetapi tetap negatif karena imunoblot tidak memenuhi pola tervalidasi yang disyaratkan oleh algoritme pengujiannya. Sebagai contoh, 3 pita IgG yang memenuhi kriteria masih di bawah ambang konvensional 5 dari 10 pita IgG. Hasil skrining lini pertama yang positif atau meragukan, diikuti imunoblot yang sesuai tetapi negatif, ditafsirkan sebagai negatif dalam pengujian dua tingkat standar. Jika gejalanya baru muncul, klinisi dapat mempertimbangkan pengujian ulang pada interval yang sesuai alih-alih menyatakan pola yang belum lengkap tersebut sebagai positif.
Apa arti pita Lyme 41 kDa yang positif?
Pita Lyme 41 kDa biasanya mencerminkan pengikatan antibodi pada flagelin, protein bakteri yang terkait dengan pergerakan dan dapat bereaksi silang dengan antibodi yang tidak terkait dengan penyakit Lyme. Pita ini hanya 1 dari pita yang ditetapkan dalam kriteria imunoblot konvensional dan tidak dapat mendiagnosis penyakit Lyme secara mandiri. Moore et al. (2016) mengutip sebuah penelitian yang menemukan pita ini pada 43% kontrol sehat, meskipun persentase tersebut bukan angka universal untuk semua uji. Rangkaian pemeriksaan lengkap dan gambaran klinis menentukan apakah hasil tersebut mendukung diagnosis penyakit Lyme.
Apakah hasil IgM Lyme positif dan IgG negatif membuktikan adanya infeksi baru-baru ini?
Hasil positif IgM Lyme dengan IgG negatif hanya dapat mendukung diagnosis infeksi dini jika sesuai dengan algoritme pemeriksaan, gambaran klinis, dan waktu yang tepat. IgM terisolasi tidak boleh digunakan untuk mendukung diagnosis penyakit Lyme jika gejala telah berlangsung lebih dari 30 hari karena IgM persisten atau nonspesifik dapat menyesatkan interpretasi. Misalnya, 2 pita IgM yang memenuhi kriteria pada hari ke-14 memiliki makna yang berbeda dari pola yang sama setelah 3 bulan gejala berkelanjutan. Aturan waktu mengacu pada awal munculnya gejala, bukan hari sampel laboratorium diambil.
Apakah hasil tes Lyme saya bisa positif tanpa adanya pita Western blot?
Ya: algoritme Lyme dua tingkat termodifikasi yang telah divalidasi menggunakan 2 immunoassay enzimatik secara berurutan dan mungkin sama sekali tidak melakukan Western blot. CDC merekomendasikan algoritme termodifikasi yang telah mendapatkan izin FDA yang sesuai pada 2019. Beberapa kombinasi pemeriksaan mengukur antibodi total, sedangkan yang lain memberikan hasil IgM dan IgG secara terpisah, sehingga aturan penghitungan pita konvensional tidak berlaku untuk setiap laporan. Tanyakan kepada laboratorium algoritme dan kombinasi pemeriksaan mana yang menghasilkan interpretasi akhir.
Apakah pita Western blot Lyme harus menghilang setelah pemberian antibiotik?
Pita Western blot Lyme tidak harus menghilang setelah pengobatan berhasil karena antibodi dapat bertahan selama bertahun-tahun atau bahkan puluhan tahun. Pola IgG 5 pita yang menetap tidak membuktikan adanya infeksi yang masih berlangsung, dan pengujian pita berulang bukanlah tes kesembuhan yang tervalidasi. Respons terhadap pengobatan dinilai melalui perjalanan klinis dan temuan objektif yang relevan, bukan dengan mensyaratkan panel antibodi menjadi negatif. Gejala baru atau paparan kutu lainnya perlu dinilai secara klinis kembali karena antibodi lama tidak dapat memastikan terjadinya reinfeksi.
Dapatkan penjelasan tentang hasil tes darah Anda
Unggah laporan lab Anda dan AI Kantesti menjelaskan setiap biomarker dengan bahasa sederhana dalam hitungan detik. Digunakan oleh lebih dari 2 juta orang di seluruh dunia.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). Panduan Kesehatan Perempuan: Ovulasi, Menopause & Gejala Hormonal. Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Dukungan Keputusan Klinis dengan Bantuan AI Multibahasa untuk Triase Dini Hantavirus: Desain, Validasi Rekayasa, dan Penerapan di Dunia Nyata pada 50.000 Laporan Interpretasi Tes Darah. Riset Medis AI Kantesti. DOI
- Moore A et al. (2016). Current Guidelines, Common Clinical Pitfalls, and Future Directions for Laboratory Diagnosis of Lyme Disease, United States. Emerging Infectious Diseases. DOI PubMed
- Mead P et al. (2019). Updated CDC Recommendation for Serologic Diagnosis of Lyme Disease. Laporan Mingguan Morbiditas dan Mortalitas MMWR. DOI
- Lantos PM et al. (2021). Clinical Practice Guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease. Clinical Infectious Diseases. DOI
- 2 juta+Pemeriksaan yang dianalisis
- 127+Negara
- 100+Bahasa
Tentang tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis yang dipimpin dokter terhadap alur kerja interpretasi hasil lab.
Keahlian
Fokus pada kedokteran laboratorium tentang bagaimana biomarker berperilaku dalam konteks klinis.
Kewenangan
Ditinjau secara medis oleh Dr. Thomas Klein, dengan kontribusi dari Dr. Sarah Mitchell dan Prof. Dr. Hans Weber.
Kepercayaan
Interpretasi berbasis bukti dengan jalur tindak lanjut yang jelas untuk mengurangi kepanikan.






Penafian medis
Artikel ini hanya untuk tujuan edukasi dan tidak merupakan nasihat medis. Selalu konsultasikan dengan penyedia layanan kesehatan yang berkualifikasi untuk keputusan diagnosis dan perawatan.
Diterbitkan · Hubungi tim editorial
Diterbitkan oleh Kantesti Ltd, terdaftar di Inggris & Wales, nomor perusahaan. 17090423, London, Britania Raya.
