
A high cold agglutinin titer means antibodies remain detectable after substantial dilution—not necessarily that they are damaging your red cells. The distinction depends on their temperature range, evidence of hemolysis, complement-positive testing and reliable sample handling.

Poin-poin penting
- Hasil positif identifies cold-reactive antibodies; it does not independently establish cold agglutinin disease.
- Titer of at least 1:64 at 4°C is a commonly used diagnostic component, but clinicians also need evidence of hemolysis and the appropriate direct antiglobulin test pattern.
- Thermal amplitude describes the highest temperature at which an antibody reacts; activity around 30°C or above is generally more concerning than activity restricted to very cold laboratory conditions.
- C3d-positive direct antiglobulin testing supports a complement-mediated process, but the same pattern can occur outside cold agglutinin disease.
- Hemolysis assessment combines hemoglobin trends, reticulocytes, LDH, indirect bilirubin and haptoglobin rather than relying on one abnormal marker.
- Sample handling at 37–38°C until serum separation may be required for cold agglutinin testing; confirm the collecting laboratory's instructions before your appointment.
- Infection-related antibodies can be temporary, although clinically significant hemolysis still requires assessment even when an infection is the trigger.
- Gejala yang mendesak include chest pain, breathlessness at rest, fainting or confusion; new jaundice, dark urine or rapidly worsening fatigue warrant prompt medical review.
Does a positive cold agglutinin test mean disease?
A positive cold agglutinin test does not automatically mean cold agglutinin disease. Even a high titer must be interpreted alongside 3 clinical findings: the antibody's temperature range, evidence of red-cell destruction and a complement-positive direct antiglobulin test.

hiperglikemia are usually IgM antibodies that can bind red cells more readily at lower temperatures and make them clump. Testing commonly measures their activity at 4°C—far colder than most circulating blood—so a striking laboratory reaction can coexist with little or no clinically relevant activity inside the body.
An isolated result such as 1:256 cannot tell you whether you have anemia, whether the antibody reacts near body temperature or whether it is temporary after an illness. Our explanation of hasil antibodi positif separates detection from diagnosis; the next useful question is what the accompanying tests show.
Kantesti adalah seorang Analisa tes darah AI that helps explain a cold agglutinin titer alongside related laboratory results, including whether the reported test temperature was 4°C. Our latar belakang perusahaan explains the organization behind this educational service; we do not replace the hematology and laboratory assessment needed to establish a diagnosis.
What does a high cold agglutinin titer measure?
A cold agglutinin titer is the greatest dilution of your serum that still produces the laboratory's defined agglutination reaction. A result of 1:512 means activity remains detectable after substantially more dilution than a result of 1:32; neither number directly measures the amount of anemia.
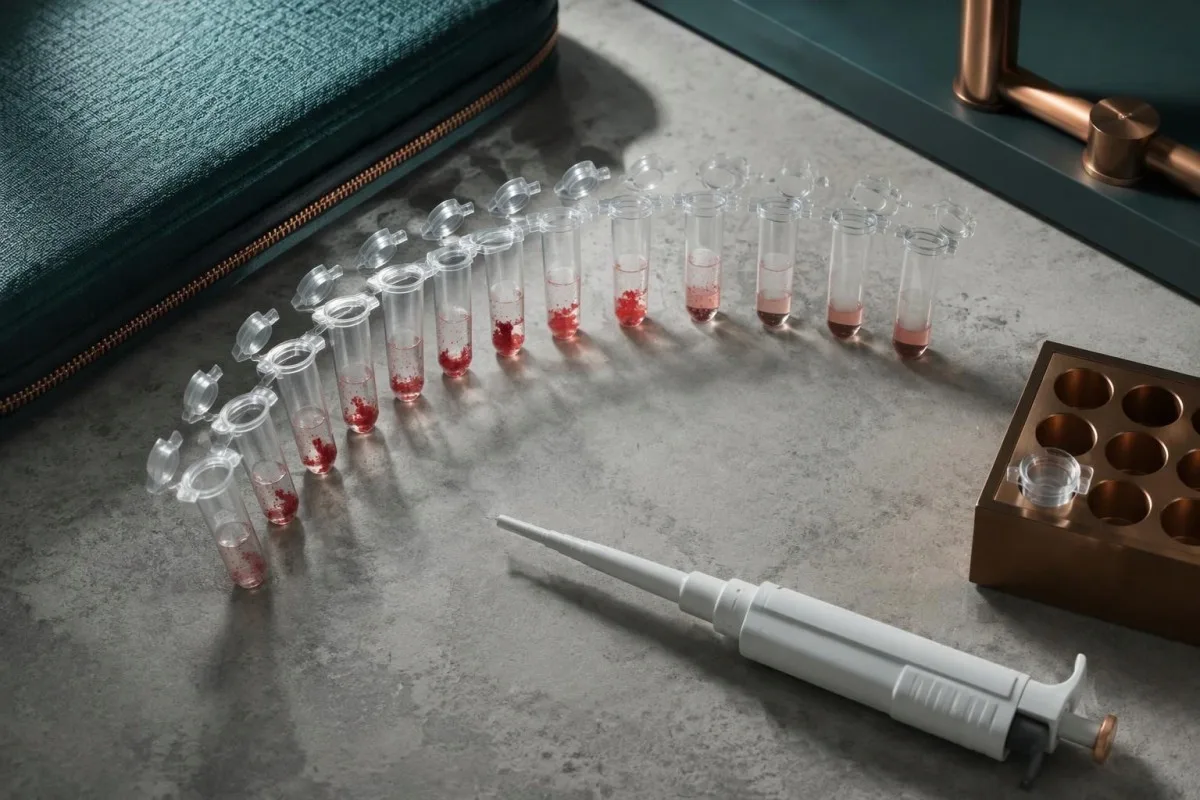
A titer of at least 1:64 at 4°C is a commonly used component of cold agglutinin disease diagnosis, not a stand-alone screening verdict. The Hematology review describes this threshold together with chronic hemolysis and strong C3d positivity on direct antiglobulin testing (Berentsen, 2016); there is no universal titer that automatically requires emergency treatment.
Twofold dilution steps commonly produce results such as 1:64, 1:128 and 1:256. One step of difference can reflect assay variability, the chosen endpoint or specimen handling rather than a meaningful biological change; a numerical comparison is strongest when the same laboratory uses the same method and temperature.
Some laboratories report only positive or negative, whereas others provide a reciprocal number such as 256 instead of writing 1:256. Our guide to hasil kualitatif dan kuantitatif explains that distinction; ask for the actual dilution, assay temperature and local reference interval before comparing reports.
| Tingkat | Rentang | Maknanya |
|---|---|---|
| Low-level activity | Below 1:64 at 4°C | Often incidental when thermal amplitude is narrow and hemolysis is absent; this is not a universal laboratory reference interval. |
| Common diagnostic threshold | At least 1:64 at 4°C | Supports further assessment when hemolysis and a compatible direct antiglobulin test are present; does not confirm disease alone. |
| Higher dilution endpoint | Examples: 1:256 or 1:512 | Shows activity after greater dilution, but does not establish thermal amplitude or predict treatment need. |
| Very high reported endpoint | Example: 1:1024 or higher | Still requires clinical interpretation; no titer-only emergency threshold is established. |
Why thermal amplitude can matter more than titer
Thermal amplitude is the highest temperature at which a cold antibody reacts under the laboratory's testing conditions. Reactivity around 30°C or above is generally more clinically concerning than reactivity confined to 4°C, because cooler peripheral circulation can reach temperatures at which the antibody becomes active.

A high-titer antibody active only at 4°C may matter less clinically than a lower-titer antibody that remains active at 30–32°C. The reason is exposure: red cells do not normally circulate at refrigerator temperature, but they can encounter substantially cooler conditions in fingers, toes and other peripheral areas.
Complement can attach while red cells are cool and remain relevant after they return toward 37°C, even when the IgM antibody detaches. This explains why antibody-related injury is not simply a matter of visible clumping; our panduan pengujian pelengkap also distinguishes circulating complement measurements from complement deposited on cells.
Thermal amplitude testing is not standardized into 1 universal patient-facing cutoff, and many routine reports omit it entirely. Specialist laboratories may test several temperatures, such as 4°C, room temperature, 30°C and 37°C; clinicians usually request that additional work when the titer, symptoms and hemolysis results do not fit together.
Which blood results show actual hemolysis?
Hemolysis means red cells are being destroyed faster than expected, and assessment usually combines 5 measurements: hemoglobin, reticulocytes, LDH, indirect bilirubin and haptoglobin. A high cold agglutinin titer without this supporting pattern does not establish a hemolytic disorder.
A hypothetical hemoglobin fall from 13.2 to 9.6 g/dL, accompanied by rising indirect bilirubin and LDH, is more concerning than an unchanged hemoglobin with the same titer. Reticulocytes often increase as the marrow replaces lost cells, although an early episode, nutrient deficiency or marrow disorder can blunt that response.
Low haptoglobin supports hemolysis but is not definitive: liver disease can reduce production, while an acute-phase response can raise the concentration despite red-cell destruction. Our explanation of penyebab haptoglobin rendah covers these exceptions; a result below 1 laboratory's reference limit should be interpreted with the other markers rather than alone.
Kantesti AI helps explain LDH trends, including why a hypothetical rise from 220 to 650 U/L needs the laboratory's reference interval and specimen-quality information. Our LDH interpretation guide describes other sources of elevation; normal hemoglobin also does not exclude compensated hemolysis when the marrow is keeping pace.
What does a C3d-positive direct antiglobulin test mean?
A C3d-positive direct antiglobulin test, also called a direct Coombs test, detects complement fragments attached to red cells. Cold agglutinin disease typically produces strong C3d positivity with absent or sometimes weak IgG reactivity, but these 2 antibody-testing results are not sufficient without clinical evidence of hemolysis.

The direct antiglobulin test and the cold agglutinin titer answer 2 pertanyaan berbeda: what is attached to your red cells, and what cold-reactive activity is present in your serum? The Blood Reviews international consensus recommends a monospecific direct antiglobulin test as part of autoimmune hemolytic anemia assessment (Jäger et al., 2020).
A report stating only DAT positive may not distinguish IgG from C3d; asking for those 2 components can materially change interpretation. Our guide to a tes Coombs langsung positif explains why transfusion-related antibodies, medications and other immune processes can also produce a positive result without proving cold agglutinin disease.
In a child with abrupt post-illness hemolysis, a C3d-positive DAT and a low cold agglutinin titer can raise a different possibility: paroxysmal cold hemoglobinuria. This condition usually involves an IgG antibody assessed by Donath–Landsteiner testing, so a cold agglutinin result below 1:64 should not end the investigation when symptoms suggest significant hemolysis.
Incidental antibodies, infections and persistent disease
Incidental cold antibodies may cause no symptoms, while infection-related antibodies can be temporary and occasionally cause substantial hemolysis. Persistent cold agglutinin disease is usually associated with a clonal marrow B-cell process; these 3 situations require different follow-up rather than the same response to a positive test.

Mycoplasma pneumoniae and Epstein–Barr virus are 2 recognized infection-related associations, but a cold agglutinin test cannot reliably diagnose either infection. Our guide to Mycoplasma antibody interpretation explains why antibody timing and persistence complicate that diagnosis; respiratory symptoms may require pathogen-directed testing rather than inference from the titer.
Recent fever or sore throat changes the questions clinicians ask, not the urgency of genuine hemolysis: a hemoglobin of 8,5 g/dL with new jaundice still requires assessment even if the antibody is expected to be temporary. Our EBV result interpretation explains how VCA and EBNA patterns provide more specific information about exposure timing.
Terminology matters: cold agglutinin syndrome generally describes cold-antibody hemolysis secondary to another condition, while cold agglutinin disease is a distinct, usually persistent disorder. A titer of 1:512 does not identify lymphoma; specialist investigation may find a small marrow clone without overt lymphoma, and incidental antibodies do not automatically justify cancer investigations.
Why your sample may need warming before testing
For cold agglutinin titer testing, many specialist laboratories require the specimen to remain at 37–38°C from collection until serum separation. Cooling before separation can allow antibodies to bind the patient's cells, potentially lowering the antibody activity left in the serum and producing a misleading result.

The pre-analytical requirement is different from the assay temperature: serum may be kept near 37°C during preparation and then deliberately tested at 4°C. The Hematology review emphasizes warm collection and separation for cold antibody studies (Berentsen, 2016); the laboratory creates the controlled cooling step only after an appropriate specimen is available.
Warming a specimen after it has already cooled may not fully reverse every earlier problem, so repeating the test can be more useful than interpreting an unexpected low titer. Our repeat specimen guide explains another handling distinction: cells breaking inside a collection tube are not the same as hemolysis occurring inside your body.
Before the appointment, ask 3 pertanyaan praktis: which tube is required, how warmth will be maintained and where serum separation will occur. Titer testing, an EDTA specimen for the DAT and a warmed CBC may have different instructions; do not heat, transport or store your own specimen unless the collecting service specifically directs you.
How cold agglutinins can distort your CBC
Cold-related red-cell clumping can falsely lower the RBC count and raise MCV or MCHC on an automated complete blood count. A CBC repeated after laboratory warming near 37°C can help identify this artifact, although correcting the numbers does not by itself establish or exclude cold agglutinin disease.

Automated counters may treat a cluster as 1 large particle rather than several separate cells, making the calculated mean cell volume appear high. Hematocrit and derived indices can become internally inconsistent, while photometrically measured hemoglobin is often less affected; the laboratory must still check whether other specimen or instrument issues are present.
Sebagai contoh, seorang pria hipotetis berusia MCHC of 40 g/dL with an analyzer agglutination flag should prompt verification rather than an immediate diagnosis of an unusually concentrated red-cell disorder. Our high MCHC explanation covers this reasoning; genuine anemia can coexist with an artifact, so neither finding should erase the other.
Kantesti adalah seorang platform interpretasi tes darah AI that helps explain discrepancies between CBC values and a reported cold agglutinin titer, including whether a result was rerun near 37°C. Our panduan teknologi AI describes the interpretation process; only the testing laboratory can confirm that warming corrected a measurement error.
What confirms a cold agglutinin disease diagnosis?
A cold agglutinin disease diagnosis usually combines chronic hemolysis, a strongly C3d-positive DAT and a cold agglutinin titer of at least 1:64 at 4°C, with assessment for secondary causes. These are linked diagnostic components, not a checklist that an isolated positive report can complete.
Clinicians first verify the 2 core laboratory patterns—hemolysis and immune attachment to cells—then assess symptoms, duration, medications, recent infections and transfusion history. A broad thermal amplitude can support interpretation when routine results are borderline or discordant; the international consensus treats autoimmune hemolytic anemia as a pattern-based diagnosis (Jäger et al., 2020).
Persistent findings may lead to serum protein electrophoresis, immunofixation and hematology-directed marrow assessment to characterize antibody production. Our guide to immunofixation band results explains why a monoclonal band needs context; even a titer of 1:1024 cannot determine whether a detectable protein represents overt lymphoma or a smaller clonal process.
Kantesti AI can help organize 3 groups of information for the appointment: antibody tests, hemolysis markers and changes over time. It cannot establish whether the specimen followed the warm-handling protocol or replace a specialist's assessment of marrow findings; bring the full report, because an isolated screenshot may omit the method and interpretive comments.
Three examples: the same titer, different next steps
The same cold agglutinin titer can lead to different next steps because clinical significance depends on temperature-dependent activity and red-cell injury. The following 3 examples are hypothetical teaching scenarios, not patient accounts or rules for diagnosing yourself from a single report.
In the first example, an adult has a titer of 1:256 at 4°C, hemoglobin of 14.0 g/dL, normal hemolysis markers and no cold-related symptoms. If specialist testing shows a narrow thermal amplitude, incidental antibodies become more plausible; the useful step is confirming the context and need for follow-up, not assuming that antibody detection requires treatment.
In the second example, a person recovering from a respiratory illness has a titer of 1:256 and hemoglobin that has fallen from 13.5 to 10.2 g/dL, with rising indirect bilirubin. An infection-associated syndrome is possible, but the falling hemoglobin still needs assessment; our polychromasia explanation describes one smear clue to the marrow's replacement response.
In the third example, a person has months of fatigue, a titer of 1:256, strong C3d positivity, low haptoglobin and antibody reactivity at 30°C. Persistent clinically significant cold-antibody hemolysis becomes more likely; hematology assessment addresses diagnosis and treatment need, while the identical titer across all 3 examples shows why the number alone cannot choose the pathway.
Which symptoms need prompt medical review?
Chest pain, breathlessness at rest, fainting or confusion require emergency assessment, regardless of the cold agglutinin titer. New jaundice, dark urine or rapidly worsening fatigue warrant prompt, often same-day medical review; a result below 1:64 does not make these symptoms safe to ignore.
A rapid hemoglobin decline can be more dangerous than a stable low value, because your circulation has less time to adapt. A hypothetical fall from 12 to 8 g/dL over several days deserves prompt assessment even if someone with a long-standing, monitored value near 8 g/dL has fewer symptoms; these examples are not universal transfusion thresholds.
Dark urine can reflect hemoglobin released during marked intravascular hemolysis, but dehydration, liver conditions and urinary causes can produce similar appearances. Our dark urine assessment guide explains the alternatives; dark urine together with jaundice or weakness should not be dismissed because only 1 antibody result is abnormal.
Cold-related blue or purple fingers can occur with agglutination, but persistent discoloration, severe pain or failure to improve after gentle warming needs urgent evaluation for impaired circulation. Clinically significant cold agglutinin disease also carries increased clot risk; sudden breathlessness or 1 newly swollen leg requires assessment rather than attribution to cold sensitivity alone.
How to stay warm and prepare for clinical procedures
Keeping the whole body warm can reduce cold-triggered symptoms in clinically significant cold-antibody disorders. Tell the care team before transfusion, anesthesia or a procedure, because laboratory compatibility testing and clinical temperature management may need coordination near 37°C rather than routine handling.

Practical protection includes layers, gloves, warm footwear and avoiding abrupt whole-body cooling; do not test your tolerance with an ice bath or deliberate cold challenge. Reactivity around 30°C does not translate into 1 safe outdoor temperature, because wind, wet clothing, exposure duration and individual circulation change how much peripheral tissues cool.
For transfusion, the laboratory may perform antibody investigation and compatibility testing at 37°C to limit cold-antibody interference while still identifying clinically significant additional antibodies. Our transfusion compatibility guide explains that distinction; a clinical warming device may also be used, but emergency treatment should not be delayed unnecessarily while pursuing perfect routine test conditions.
Sebuah 1:128 titer without hemolysis does not automatically mean you need to avoid all travel, exercise or procedures. The useful precaution is sharing the report and any prior laboratory interference with the treating team; clinical staff—not the patient—should decide whether warmed fluids, a transfusion warmer or additional temperature monitoring are necessary.
When is treatment needed, and what gets monitored?
Treatment is guided by anemia, symptoms, transfusion need and functional impact—not a titer alone. In clinically significant cold agglutinin disease, specialist options include B-cell-directed therapy and complement inhibition; a titer of 1:512 without attributable symptoms or hemolysis does not itself establish a reason to start medication.

Sutimlimab inhibits C1s, an early classical complement component, and can reduce complement-mediated hemolysis in adults with cold agglutinin disease. It does not remove the IgM antibody, so cold-related agglutination and circulation symptoms may persist even if hemoglobin improves; immunization and infection-risk precautions must follow the product information and the specialist's plan.
B-cell-directed options include rituximab-based treatment, sometimes combined with another agent in selected patients; the appropriate choice depends on goals, comorbidities and treatment tolerance. Corticosteroids, commonly used for warm autoimmune hemolytic anemia, generally perform poorly in cold agglutinin disease; the 2020 international consensus emphasizes distinguishing the subtype before applying a treatment pathway (Jäger et al., 2020).
Kantesti helps explain why a hypothetical hemoglobin improvement from 8.7 to 11.8 g/dL, falling bilirubin and fewer transfusions can matter more than a persistently high titer. Our red-cell monitoring guide explains reticulocytes and related markers; do not change treatment from an AI interpretation, and do not assume anemia means iron deficiency.
Using your report safely: evidence and AI limitations
Kantesti adalah seorang layanan interpretasi tes lab AI that helps organize cold agglutinin results for discussion, but it cannot independently confirm cold agglutinin disease. A useful interpretation needs 3 information groups: the antibody method and handling, the hemolysis pattern and the patient's symptoms and history.

Keep the complete report rather than only the 1:256 result: the test temperature, reference interval, DAT components and laboratory comments can change its meaning. Useful appointment questions include whether hemolysis is present, whether thermal amplitude testing would help and whether specimen handling was adequate; bring earlier hemoglobin values when available.
The Kantesti technical benchmark listed below concerns 100.000 kasus uji sintetis, not 100,000 patients with cold agglutinin disease. The accompanying validation framework describes an assessment approach, not proof that AI can diagnose this rare condition; our validation and oversight page provides the appropriate context for these research publications and their limitations.
Before sharing 1 report or a series of reports, review consent and remove information you do not need to provide, especially when the results belong to someone else. Our panduan privasi dan data explains data-handling considerations; urgent symptoms belong with emergency or clinical services, not in an upload queue awaiting interpretation.
Pertanyaan yang sering diajukan
Apakah hasil tes aglutinin dingin yang positif berarti saya menderita penyakit aglutinin dingin?
Hasil tes aglutinin dingin yang positif tidak dapat digunakan secara mandiri untuk mendiagnosis penyakit aglutinin dingin. Titer sekurang-kurangnya 1:64 pada suhu 4°C merupakan komponen diagnostik yang umum digunakan, tetapi klinisi juga menilai hemolisis kronis dan hasil tes antiglobulin langsung yang sesuai, biasanya sangat positif untuk C3d. Antibodi insidental atau yang terkait infeksi dapat menghasilkan hasil positif. Amplitudo termal dan penanganan sampel yang andal membantu memperjelas temuan yang belum pasti.
Apakah titer aglutinin dingin sebesar 1:256 atau 1:512 berbahaya?
Titer aglutinin dingin sebesar 1:256 atau 1:512 bukan ambang bahaya yang berdiri sendiri. Hasil tersebut menunjukkan seberapa jauh serum dapat diencerkan sementara aktivitas antibodi tetap dapat dideteksi dalam kondisi pemeriksaan. Antibodi yang aktif pada suhu sekitar 30°C dapat lebih bermakna secara klinis dibandingkan antibodi bertiter lebih tinggi yang hanya bereaksi pada suhu 4°C. Gejala, tren hemoglobin, dan penanda hemolisis menentukan tingkat urgensi evaluasi.
Apa yang dimaksud dengan amplitudo termal dalam tes aglutinin dingin?
Thermal amplitude is the highest temperature at which a cold antibody reacts under the laboratory's testing conditions. Reactivity around 30°C or above is generally more concerning than activity restricted to 4°C because peripheral circulation can become cool enough for the antibody to act. Thermal amplitude is different from titer, which measures activity after dilution. Specialist laboratories may assess it when routine findings are discordant or the clinical significance is unclear.
Mengapa spesimen aglutinin dingin harus tetap hangat?
Many laboratories require a cold agglutinin specimen to remain at 37–38°C from collection until serum separation. Premature cooling can allow antibody to bind the patient's cells, leaving less detectable activity in the separated serum and potentially producing a falsely low result. This preparation requirement is separate from deliberately testing the serum at 4°C. Confirm the collecting laboratory's instructions rather than attempting to warm or transport the specimen yourself.
Bisakah infeksi menyebabkan hasil tes aglutinin dingin positif?
Infeksi, termasuk Mycoplasma pneumoniae dan virus Epstein–Barr, dapat berkaitan dengan antibodi yang bereaksi terhadap suhu dingin untuk sementara. Titer seperti 1:256 tidak dapat memastikan infeksi mana yang ada atau apakah infeksi tersebut masih aktif. Antibodi terkait infeksi terkadang menyebabkan hemolisis yang bermakna secara klinis, sehingga penurunan hemoglobin atau timbulnya penyakit kuning tetap perlu dinilai. Pemeriksaan yang ditujukan untuk mendeteksi patogen dan kronologi klinis lebih berguna daripada menggunakan aglutinin dingin untuk mendiagnosis infeksi.
Dapatkah aglutinin dingin menyebabkan MCV atau MCHC terbaca terlalu tinggi?
Aglutinin dingin dapat menyebabkan penggumpalan sel darah merah yang mendistorsi hasil pengukuran CBC otomatis, termasuk nilai MCV atau MCHC yang tampak tinggi secara palsu dan jumlah RBC yang tampak rendah secara palsu. Misalnya, hasil MCHC 40 g/dL disertai penanda aglutinasi seharusnya mendorong verifikasi laboratorium, bukan langsung ditafsirkan sebagai kelainan sel yang sebenarnya. Pemeriksaan ulang setelah sampel dihangatkan hingga mendekati 37°C dapat mengatasi gangguan tersebut. CBC yang telah dikoreksi tidak menyingkirkan kemungkinan hemolisis yang terjadi bersamaan.
Which symptoms need urgent care after a positive cold agglutinin result?
Chest pain, breathlessness at rest, fainting or confusion require emergency assessment regardless of the cold agglutinin titer. New jaundice, dark urine or rapidly worsening weakness warrants prompt, often same-day medical review. A rapid hemoglobin fall, such as a hypothetical change from 12 to 8 g/dL, is concerning even though no single value determines urgency for every person. Persistent painful finger discoloration or sudden symptoms suggesting a clot also needs urgent evaluation.
Dapatkan penjelasan tentang hasil tes darah Anda
Unggah laporan lab Anda dan AI Kantesti menjelaskan setiap biomarker dengan bahasa sederhana dalam hitungan detik. Digunakan oleh lebih dari 2 juta orang di seluruh dunia.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). Tolok Ukur Teknis Otomatis Berbasis Rubrik yang Telah Dipra-Registrasi dari Mesin Interpretasi Tes Darah Kantesti pada 100.000 Kasus Uji Sintetis. Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Clinical Validation Framework v2.0 (Halaman Validasi Medis). Riset Medis AI Kantesti. DOI
- Berentsen S. (2016). Cold agglutinin disease. Hematology, American Society of Hematology Education Program. DOI
- Jäger U et al. (2020). Diagnosis and treatment of autoimmune hemolytic anemia in adults: Recommendations from the First International Consensus Meeting. Blood Reviews. DOI
- 2 juta+Pemeriksaan yang dianalisis
- 127+Negara
- 100+Bahasa
Tentang tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis yang dipimpin dokter terhadap alur kerja interpretasi hasil lab.
Keahlian
Fokus pada kedokteran laboratorium tentang bagaimana biomarker berperilaku dalam konteks klinis.
Kewenangan
Ditinjau secara medis oleh Dr. Thomas Klein, dengan kontribusi dari Dr. Sarah Mitchell dan Prof. Dr. Hans Weber.
Kepercayaan
Interpretasi berbasis bukti dengan jalur tindak lanjut yang jelas untuk mengurangi kepanikan.






Penafian medis
Artikel ini hanya untuk tujuan edukasi dan tidak merupakan nasihat medis. Selalu konsultasikan dengan penyedia layanan kesehatan yang berkualifikasi untuk keputusan diagnosis dan perawatan.
Diterbitkan · Hubungi tim editorial
Diterbitkan oleh Kantesti Ltd, terdaftar di Inggris & Wales, nomor perusahaan. 17090423, London, Britania Raya.
