
سرد تجمعی مادوں کا بلند ٹائٹر یہ بتاتا ہے کہ خاصی رقت کے بعد بھی اینٹی باڈیز قابلِ شناخت رہتی ہیں—ضروری نہیں کہ وہ آپ کے سرخ خلیوں کو نقصان پہنچا رہی ہوں۔ اس فرق کا انحصار ان کے درجۂ حرارت کی حد، ہیمولائسز کے شواہد، کمپلیمنٹ پازیٹو ٹیسٹنگ اور نمونے کو قابلِ اعتماد طریقے سے سنبھالنے پر ہے۔

اہم نکات
- مثبت نتیجہ سرد ردِعمل دینے والی اینٹی باڈیز کی شناخت کرتا ہے؛ یہ بذاتِ خود سرد تجمعی مادوں کی بیماری کی تشخیص قائم نہیں کرتا۔
- 4°C پر کم از کم 1:64 کا ٹائٹر تشخیصی معیار کا ایک عام جزو ہے، لیکن معالجین کو ہیمولائسز کے شواہد اور ڈائریکٹ اینٹی گلوبیولن ٹیسٹ کے مناسب نمونے کی بھی ضرورت ہوتی ہے۔
- تھرمل ایمپلی ٹیوڈ اس بلند ترین درجۂ حرارت کو بیان کرتی ہے جس پر کوئی اینٹی باڈی ردِعمل دیتی ہے؛ عموماً تقریباً 30°C یا اس سے زیادہ پر سرگرمی، انتہائی سرد لیبارٹری حالات تک محدود سرگرمی کے مقابلے میں زیادہ تشویش ناک ہوتی ہے۔
- C3d-پازیٹو ڈائریکٹ اینٹی گلوبیولن ٹیسٹنگ کمپلیمنٹ کے ذریعے ہونے والے عمل کی تائید کرتی ہے، لیکن یہی نمونہ سرد تجمعی مادوں کی بیماری کے علاوہ بھی دیکھا جا سکتا ہے۔
- ہیمولائسز کا جائزہ ہیموگلوبن کے رجحانات، ریٹیکولوسائٹس، LDH، اِن ڈائریکٹ بلیروبن اور ہیپٹوگلوبن کو یکجا کرتا ہے، بجائے اس کے کہ صرف ایک غیر معمولی نشان پر انحصار کیا جائے۔
- نمونے کو 37–38°C پر سنبھالنا کولڈ ایگلوٹینن ٹیسٹ کے لیے سیرم الگ ہونے تک یہ درجۂ حرارت برقرار رکھنا ضروری ہو سکتا ہے؛ اپائنٹمنٹ سے پہلے نمونہ جمع کرنے والی لیبارٹری کی ہدایات کی تصدیق کریں۔
- انفیکشن سے متعلق اینٹی باڈیز عارضی ہو سکتی ہیں، تاہم انفیکشن محرک ہونے کے باوجود طبی لحاظ سے اہم ہیمولائسز کا جائزہ لینا ضروری ہے۔
- فوری توجہ کی علامات میں سینے کا درد، آرام کی حالت میں سانس پھولنا، بے ہوشی یا الجھن شامل ہیں؛ نیا یرقان، گہرا پیشاب یا تیزی سے بڑھتی تھکن فوری طبی معائنے کے متقاضی ہیں۔
کیا سرد تجمعی مادوں کا مثبت ٹیسٹ بیماری کی علامت ہے؟
A کولڈ ایگلوٹینن ٹیسٹ کا مثبت نتیجہ خودبخود کولڈ ایگلوٹینن بیماری کا مطلب نہیں ہوتا۔ زیادہ ٹائٹر کی بھی 3 طبی نتائج کے ساتھ تشریح ضروری ہے: اینٹی باڈی کی درجۂ حرارت کی حد، سرخ خلیات کے ٹوٹنے کے شواہد، اور کمپلیمنٹ-مثبت ڈائریکٹ اینٹی گلوبیولن ٹیسٹ۔

کولڈ ایگلوٹیننز (Cold agglutinins) عموماً IgM اینٹی باڈیز ہوتی ہیں جو کم درجۂ حرارت پر سرخ خلیات سے زیادہ آسانی سے جڑ سکتی ہیں اور انہیں اکٹھا چپکا سکتی ہیں۔ جانچ میں عموماً 4°C پر ان کی سرگرمی ناپی جاتی ہے—جو دورانِ خون میں موجود زیادہ تر خون سے کہیں زیادہ سرد ہے—اس لیے لیبارٹری میں نمایاں ردِعمل کے باوجود جسم کے اندر طبی لحاظ سے اہم سرگرمی بہت کم یا بالکل نہیں ہو سکتی۔
ایک الگ تھلگ نتیجہ، مثلاً 1:256 یہ نہیں بتا سکتا کہ آپ کو خون کی کمی ہے یا نہیں، اینٹی باڈی جسمانی درجۂ حرارت کے قریب ردِعمل کرتی ہے یا نہیں، یا بیماری کے بعد یہ عارضی ہے یا نہیں۔ ہماری وضاحت مثبت اینٹی باڈی کے نتائج شناخت اور تشخیص میں فرق واضح کرتی ہے؛ اگلا مفید سوال یہ ہے کہ ساتھ کیے گئے ٹیسٹ کیا ظاہر کرتے ہیں۔
کنٹیسٹی ایک ہے۔ اے آئی بلڈ ٹیسٹ تجزیہ کار جو متعلقہ لیبارٹری نتائج کے ساتھ کولڈ ایگلوٹینن ٹائٹر کی تشریح میں مدد کرتی ہے، بشمول یہ کہ رپورٹ شدہ ٹیسٹ درجۂ حرارت 4°C تھا یا نہیں۔ ہمارا کمپنی کا پس منظر اس تعلیمی خدمت کے پسِ پشت تنظیم کی وضاحت کرتا ہے؛ تشخیص قائم کرنے کے لیے درکار ہیماتولوجی اور لیبارٹری کے جائزے کا متبادل ہم نہیں ہیں۔
سرد تجمعی مادوں کا بلند ٹائٹر کیا پیمائش کرتا ہے؟
A کولڈ ایگلوٹینن ٹائٹر آپ کے سیرم کی وہ سب سے زیادہ تخفیف ہے جس پر بھی لیبارٹری کا مقررہ ایگلوٹینیشن ردِعمل ظاہر ہوتا ہے۔ 1:512 کے نتیجے کا مطلب ہے کہ سرگرمی، 1:32 کے نتیجے کے مقابلے میں، کہیں زیادہ تخفیف کے بعد بھی قابلِ شناخت رہتی ہے؛ ان میں سے کوئی بھی عدد براہِ راست خون کی کمی کی مقدار نہیں ناپتا۔
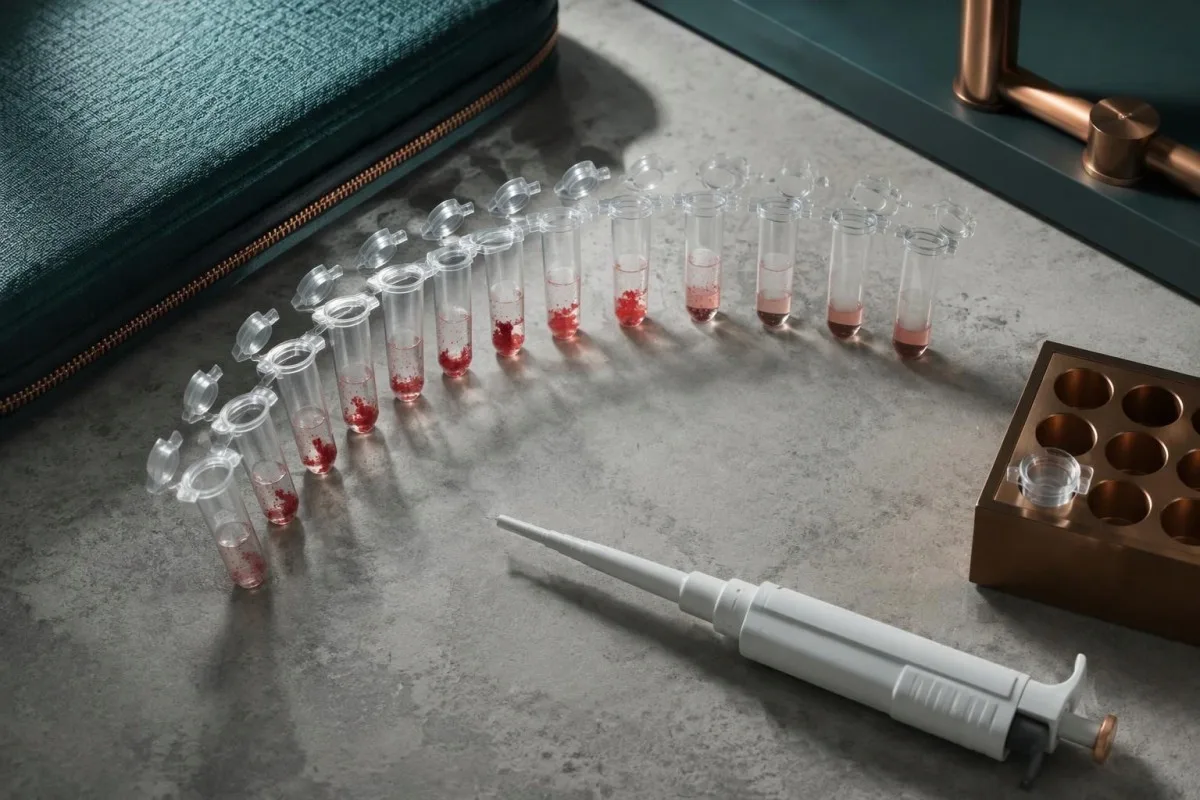
4°C پر کم از کم 1:64 کا ٹائٹر کولڈ ایگلوٹینن بیماری کی تشخیص میں عام طور پر استعمال ہونے والا ایک جزو ہے، بذاتِ خود اسکریننگ کا حتمی فیصلہ نہیں۔ ہیماتولوجی جائزے میں اس حد کو مزمن ہیمولائسز اور ڈائریکٹ اینٹی گلوبیولن ٹیسٹنگ میں نمایاں C3d مثبتیت کے ساتھ بیان کیا گیا ہے (Berentsen, 2016)؛ ایسا کوئی عالمگیر ٹائٹر نہیں جو خودبخود ہنگامی علاج کا تقاضا کرے۔
دوگنی تخفیف کے مراحل سے عموماً ایسے نتائج حاصل ہوتے ہیں جیسے 1:64، 1:128 اور 1:256۔ ایک مرحلے کا فرق، کسی اہم حیاتیاتی تبدیلی کے بجائے، ٹیسٹ کے تغیر، منتخب کردہ اختتامی نقطے یا نمونے کو سنبھالنے کے طریقے کی وجہ سے ہو سکتا ہے؛ عددی موازنہ اس وقت زیادہ معتبر ہوتا ہے جب ایک ہی لیبارٹری ایک ہی طریقہ اور درجۂ حرارت استعمال کرے۔
کچھ لیبارٹریاں صرف مثبت یا منفی, رپورٹ کرتی ہیں، جبکہ دیگر 1:256 لکھنے کے بجائے 256 جیسا معکوس عدد دیتی ہیں۔ ہماری رہنمائی برائے گنوتی اور مقداری نتائج explains that distinction; ask for the actual dilution, assay temperature and local reference interval before comparing reports.
| سطح | حد | اس کا مطلب |
|---|---|---|
| Low-level activity | Below 1:64 at 4°C | Often incidental when thermal amplitude is narrow and hemolysis is absent; this is not a universal laboratory reference interval. |
| Common diagnostic threshold | At least 1:64 at 4°C | Supports further assessment when hemolysis and a compatible direct antiglobulin test are present; does not confirm disease alone. |
| Higher dilution endpoint | Examples: 1:256 or 1:512 | Shows activity after greater dilution, but does not establish thermal amplitude or predict treatment need. |
| Very high reported endpoint | Example: 1:1024 or higher | Still requires clinical interpretation; no titer-only emergency threshold is established. |
ٹائٹر کے مقابلے میں تھرمل ایمپلی ٹیوڈ زیادہ اہم کیوں ہو سکتی ہے
تھرمل ایمپلی ٹیوڈ is the highest temperature at which a cold antibody reacts under the laboratory's testing conditions. Reactivity around 30°C or above is generally more clinically concerning than reactivity confined to 4°C, because cooler peripheral circulation can reach temperatures at which the antibody becomes active.

A high-titer antibody active only at 4°C may matter less clinically than a lower-titer antibody that remains active at 30–32°C. The reason is exposure: red cells do not normally circulate at refrigerator temperature, but they can encounter substantially cooler conditions in fingers, toes and other peripheral areas.
Complement can attach while red cells are cool and remain relevant after they return toward 37°C, even when the IgM antibody detaches. This explains why antibody-related injury is not simply a matter of visible clumping; our تکمیل ٹیسٹنگ گائیڈ also distinguishes circulating complement measurements from complement deposited on cells.
Thermal amplitude testing is not standardized into 1 universal patient-facing cutoff, and many routine reports omit it entirely. Specialist laboratories may test several temperatures, such as 4°C, room temperature, 30°C and 37°C; clinicians usually request that additional work when the titer, symptoms and hemolysis results do not fit together.
کون سے خون کے نتائج حقیقی ہیمولائسز ظاہر کرتے ہیں؟
Hemolysis means red cells are being destroyed faster than expected, and assessment usually combines 5 measurements: hemoglobin, reticulocytes, LDH, indirect bilirubin and haptoglobin. A high cold agglutinin titer without this supporting pattern does not establish a hemolytic disorder.
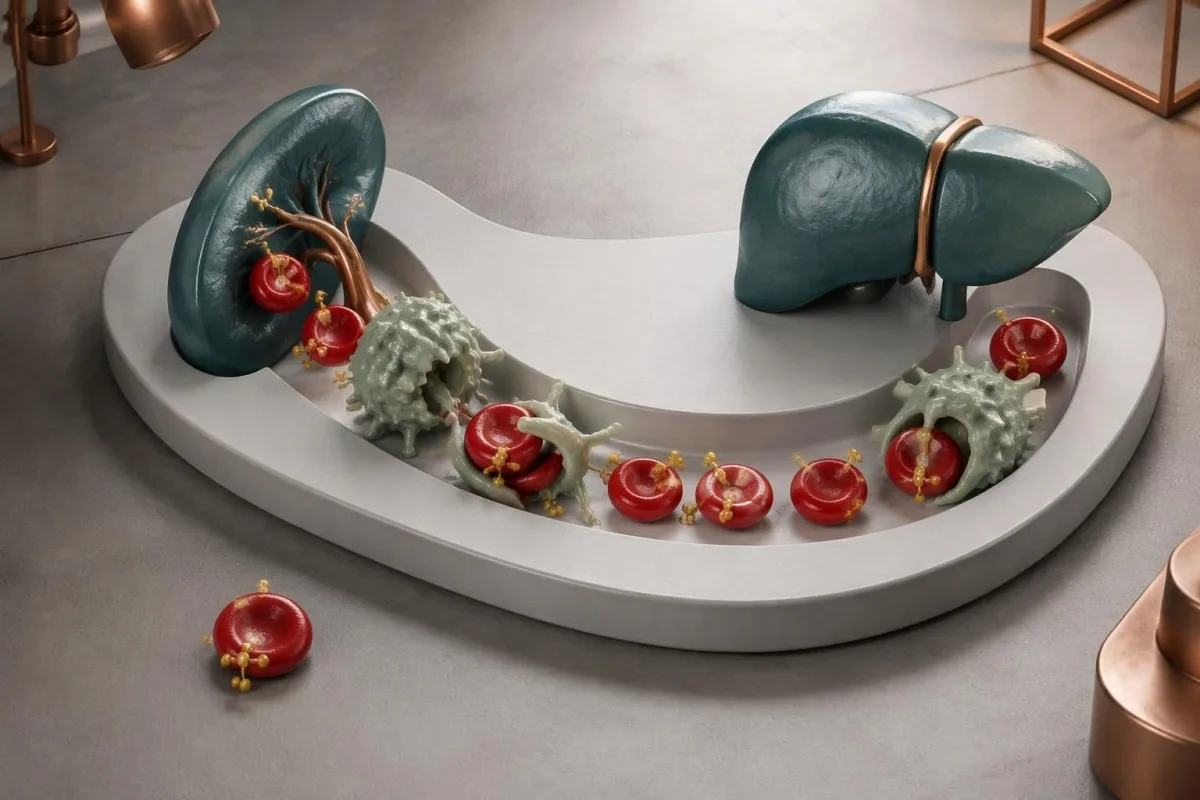
A hypothetical hemoglobin fall from 13.2 to 9.6 g/dL, accompanied by rising indirect bilirubin and LDH, is more concerning than an unchanged hemoglobin with the same titer. Reticulocytes often increase as the marrow replaces lost cells, although an early episode, nutrient deficiency or marrow disorder can blunt that response.
Low haptoglobin supports hemolysis but is not definitive: liver disease can reduce production, while an acute-phase response can raise the concentration despite red-cell destruction. Our explanation of کم ہپٹوگلوبن کی وجوہات covers these exceptions; a result below 1 laboratory's reference limit should be interpreted with the other markers rather than alone.
Kantesti AI helps explain LDH trends, including why a hypothetical rise from 220 to 650 U/L needs the laboratory's reference interval and specimen-quality information. Our LDH interpretation guide describes other sources of elevation; normal hemoglobin also does not exclude compensated hemolysis when the marrow is keeping pace.
C3d-پازیٹو ڈائریکٹ اینٹی گلوبیولن ٹیسٹ کا کیا مطلب ہے؟
A C3d-positive direct antiglobulin test, also called a direct Coombs test, detects complement fragments attached to red cells. Cold agglutinin disease typically produces strong C3d positivity with absent or sometimes weak IgG reactivity, but these 2 antibody-testing results are not sufficient without clinical evidence of hemolysis.

The direct antiglobulin test and the cold agglutinin titer answer 2 مختلف سوالات: what is attached to your red cells, and what cold-reactive activity is present in your serum? The Blood Reviews international consensus recommends a monospecific direct antiglobulin test as part of autoimmune hemolytic anemia assessment (Jäger et al., 2020).
A report stating only DAT positive may not distinguish IgG from C3d; asking for those 2 components can materially change interpretation. Our guide to a مثبت ڈائریکٹ کومبس ٹیسٹ explains why transfusion-related antibodies, medications and other immune processes can also produce a positive result without proving cold agglutinin disease.
In a child with abrupt post-illness hemolysis, a C3d-positive DAT and a low cold agglutinin titer can raise a different possibility: paroxysmal cold hemoglobinuria. This condition usually involves an IgG antibody assessed by Donath–Landsteiner testing, so a cold agglutinin result below 1:64 should not end the investigation when symptoms suggest significant hemolysis.
اتفاقی اینٹی باڈیز، انفیکشنز اور مستقل بیماری
Incidental cold antibodies may cause no symptoms, while infection-related antibodies can be temporary and occasionally cause substantial hemolysis. Persistent cold agglutinin disease is usually associated with a clonal marrow B-cell process; these 3 situations require different follow-up rather than the same response to a positive test.

Mycoplasma pneumoniae and Epstein–Barr virus are 2 recognized infection-related associations, but a cold agglutinin test cannot reliably diagnose either infection. Our guide to Mycoplasma antibody interpretation explains why antibody timing and persistence complicate that diagnosis; respiratory symptoms may require pathogen-directed testing rather than inference from the titer.
Recent fever or sore throat changes the questions clinicians ask, not the urgency of genuine hemolysis: a hemoglobin of 8.5 g/dL with new jaundice still requires assessment even if the antibody is expected to be temporary. Our EBV result interpretation explains how VCA and EBNA patterns provide more specific information about exposure timing.
Terminology matters: cold agglutinin syndrome generally describes cold-antibody hemolysis secondary to another condition, while cold agglutinin disease is a distinct, usually persistent disorder. A titer of 1:512 does not identify lymphoma; specialist investigation may find a small marrow clone without overt lymphoma, and incidental antibodies do not automatically justify cancer investigations.
ٹیسٹ سے پہلے آپ کے نمونے کو گرم کرنے کی ضرورت کیوں پڑ سکتی ہے
For cold agglutinin titer testing, many specialist laboratories require the specimen to remain at 37–38°C from collection until serum separation. Cooling before separation can allow antibodies to bind the patient's cells, potentially lowering the antibody activity left in the serum and producing a misleading result.

The pre-analytical requirement is different from the assay temperature: serum may be kept near 37°C during preparation and then deliberately tested at 4°C. The Hematology review emphasizes warm collection and separation for cold antibody studies (Berentsen, 2016); the laboratory creates the controlled cooling step only after an appropriate specimen is available.
Warming a specimen after it has already cooled may not fully reverse every earlier problem, so repeating the test can be more useful than interpreting an unexpected low titer. Our repeat specimen guide explains another handling distinction: cells breaking inside a collection tube are not the same as hemolysis occurring inside your body.
Before the appointment, ask 3 عملی سوالات: which tube is required, how warmth will be maintained and where serum separation will occur. Titer testing, an EDTA specimen for the DAT and a warmed CBC may have different instructions; do not heat, transport or store your own specimen unless the collecting service specifically directs you.
سرد تجمعی مادے آپ کے CBC کو کیسے بگاڑ سکتے ہیں
Cold-related red-cell clumping can falsely lower the RBC count and raise MCV or MCHC on an automated complete blood count. A CBC repeated after laboratory warming near 37°C can help identify this artifact, although correcting the numbers does not by itself establish or exclude cold agglutinin disease.

Automated counters may treat a cluster as 1 large particle rather than several separate cells, making the calculated mean cell volume appear high. Hematocrit and derived indices can become internally inconsistent, while photometrically measured hemoglobin is often less affected; the laboratory must still check whether other specimen or instrument issues are present.
مثال کے طور پر، ایک مفروضہ MCHC of 40 g/dL with an analyzer agglutination flag should prompt verification rather than an immediate diagnosis of an unusually concentrated red-cell disorder. Our high MCHC explanation covers this reasoning; genuine anemia can coexist with an artifact, so neither finding should erase the other.
کنٹیسٹی ایک ہے۔ AI خون کے ٹیسٹ کی رپورٹ کی تشریح that helps explain discrepancies between CBC values and a reported cold agglutinin titer, including whether a result was rerun near 37°C. Our اے آئی ٹیکنالوجی گائیڈ describes the interpretation process; only the testing laboratory can confirm that warming corrected a measurement error.
سرد تجمعی مادوں کی بیماری کی تشخیص کی تصدیق کیسے ہوتی ہے؟
A cold agglutinin disease diagnosis usually combines chronic hemolysis, a strongly C3d-positive DAT and a cold agglutinin titer of at least 1:64 at 4°C, with assessment for secondary causes. These are linked diagnostic components, not a checklist that an isolated positive report can complete.
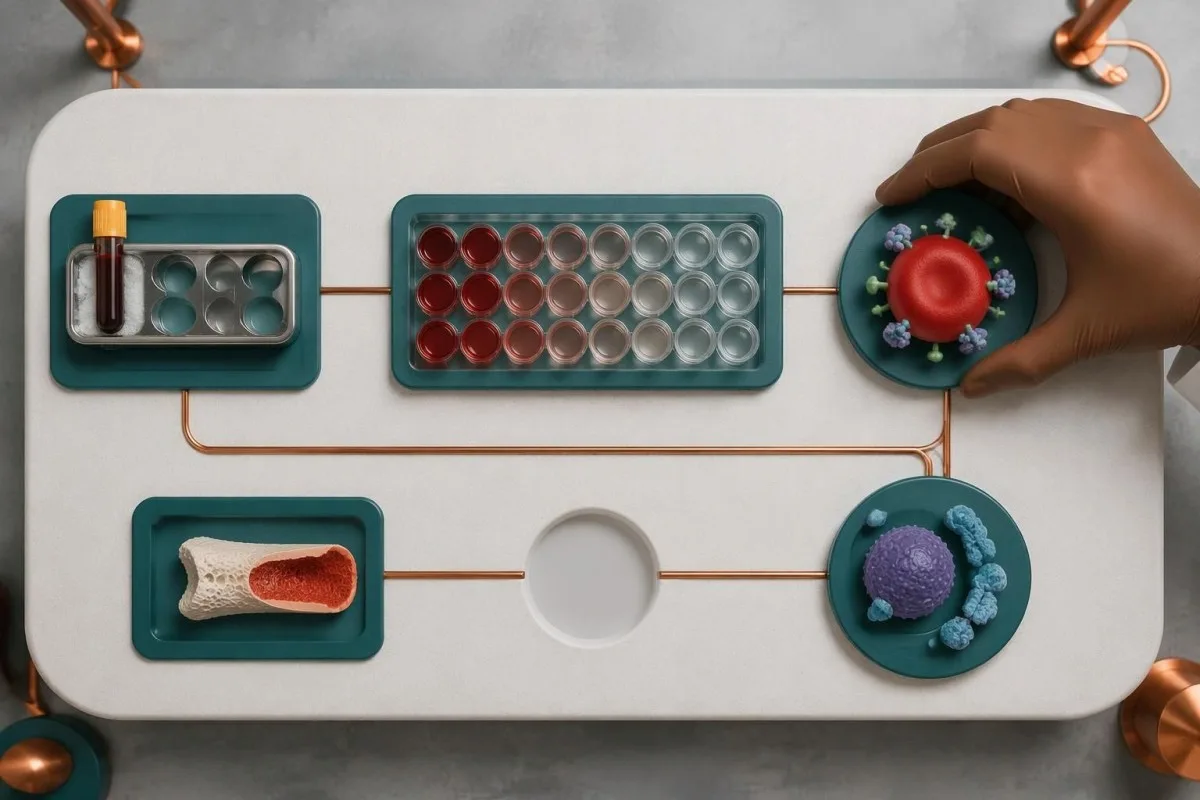
Clinicians first verify the 2 core laboratory patterns—hemolysis and immune attachment to cells—then assess symptoms, duration, medications, recent infections and transfusion history. A broad thermal amplitude can support interpretation when routine results are borderline or discordant; the international consensus treats autoimmune hemolytic anemia as a pattern-based diagnosis (Jäger et al., 2020).
Persistent findings may lead to serum protein electrophoresis, immunofixation and hematology-directed marrow assessment to characterize antibody production. Our guide to immunofixation band results explains why a monoclonal band needs context; even a titer of 1:1024 cannot determine whether a detectable protein represents overt lymphoma or a smaller clonal process.
Kantesti AI can help organize 3 groups of information for the appointment: antibody tests, hemolysis markers and changes over time. It cannot establish whether the specimen followed the warm-handling protocol or replace a specialist's assessment of marrow findings; bring the full report, because an isolated screenshot may omit the method and interpretive comments.
تین مثالیں: ایک جیسا ٹائٹر، اگلے اقدامات مختلف
The same cold agglutinin titer can lead to different next steps because clinical significance depends on temperature-dependent activity and red-cell injury. The following 3 examples are hypothetical teaching scenarios, not patient accounts or rules for diagnosing yourself from a single report.
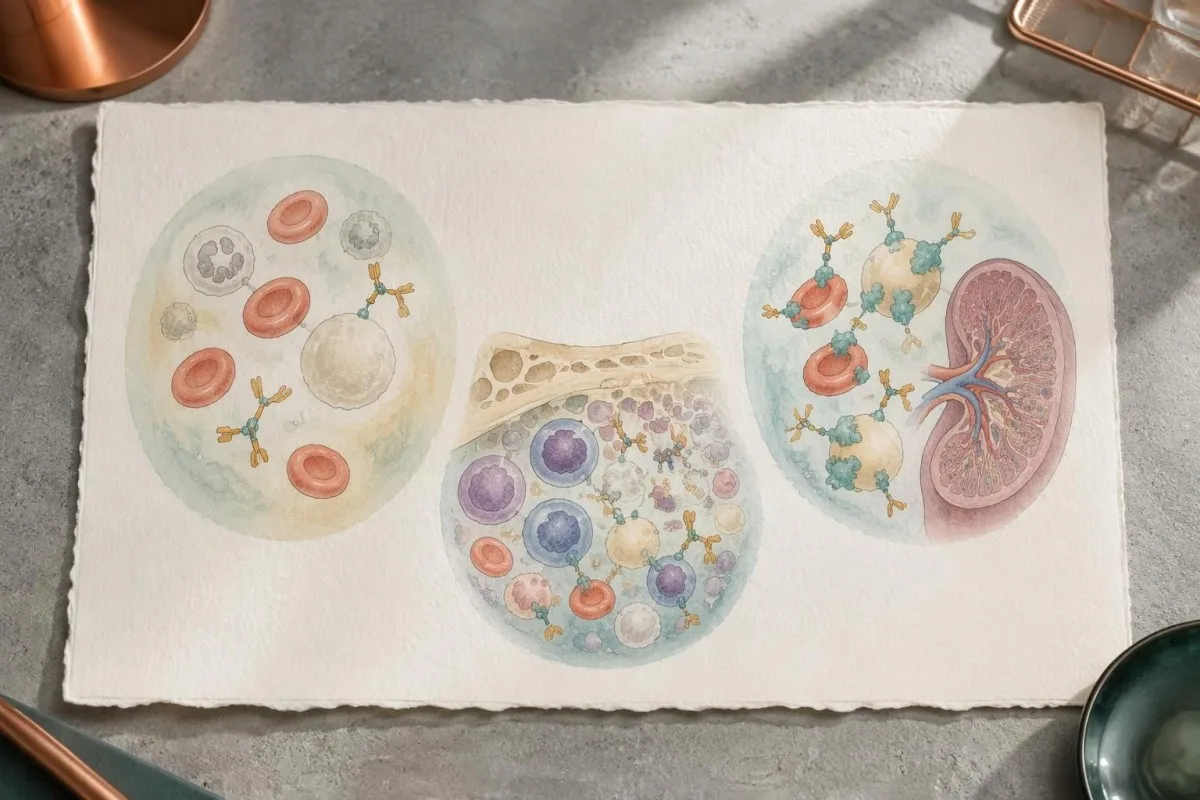
In the first example, an adult has a titer of 1:256 at 4°C, hemoglobin of 14.0 g/dL, normal hemolysis markers and no cold-related symptoms. If specialist testing shows a narrow thermal amplitude, incidental antibodies become more plausible; the useful step is confirming the context and need for follow-up, not assuming that antibody detection requires treatment.
In the second example, a person recovering from a respiratory illness has a titer of 1:256 and hemoglobin that has fallen from 13.5 to 10.2 g/dL, with rising indirect bilirubin. An infection-associated syndrome is possible, but the falling hemoglobin still needs assessment; our polychromasia explanation describes one smear clue to the marrow's replacement response.
In the third example, a person has months of fatigue, a titer of 1:256, strong C3d positivity, low haptoglobin and antibody reactivity at 30°C. Persistent clinically significant cold-antibody hemolysis becomes more likely; hematology assessment addresses diagnosis and treatment need, while the identical titer across all 3 examples shows why the number alone cannot choose the pathway.
کن علامات کے لیے فوری طبی معائنے کی ضرورت ہے؟
Chest pain, breathlessness at rest, fainting or confusion require emergency assessment, regardless of the cold agglutinin titer. New jaundice, dark urine or rapidly worsening fatigue warrant prompt, often same-day medical review; a result below 1:64 does not make these symptoms safe to ignore.
A rapid hemoglobin decline can be more dangerous than a stable low value, because your circulation has less time to adapt. A hypothetical fall from 12 to 8 g/dL over several days deserves prompt assessment even if someone with a long-standing, monitored value near 8 g/dL has fewer symptoms; these examples are not universal transfusion thresholds.
Dark urine can reflect hemoglobin released during marked intravascular hemolysis, but dehydration, liver conditions and urinary causes can produce similar appearances. Our dark urine assessment guide explains the alternatives; dark urine together with jaundice or weakness should not be dismissed because only 1 antibody result is abnormal.
Cold-related blue or purple fingers can occur with agglutination, but persistent discoloration, severe pain or failure to improve after gentle warming needs urgent evaluation for impaired circulation. Clinically significant cold agglutinin disease also carries increased clot risk; sudden breathlessness or 1 newly swollen leg requires assessment rather than attribution to cold sensitivity alone.
گرم کیسے رہیں اور طبی کارروائیوں کے لیے تیاری کیسے کریں
Keeping the whole body warm can reduce cold-triggered symptoms in clinically significant cold-antibody disorders. Tell the care team before transfusion, anesthesia or a procedure, because laboratory compatibility testing and clinical temperature management may need coordination near 37°C rather than routine handling.

Practical protection includes layers, gloves, warm footwear and avoiding abrupt whole-body cooling; do not test your tolerance with an ice bath or deliberate cold challenge. Reactivity around 30°C does not translate into 1 safe outdoor temperature, because wind, wet clothing, exposure duration and individual circulation change how much peripheral tissues cool.
For transfusion, the laboratory may perform antibody investigation and compatibility testing at 37°C to limit cold-antibody interference while still identifying clinically significant additional antibodies. Our transfusion compatibility guide explains that distinction; a clinical warming device may also be used, but emergency treatment should not be delayed unnecessarily while pursuing perfect routine test conditions.
ایک الگ تھلگ 1:128 titer without hemolysis does not automatically mean you need to avoid all travel, exercise or procedures. The useful precaution is sharing the report and any prior laboratory interference with the treating team; clinical staff—not the patient—should decide whether warmed fluids, a transfusion warmer or additional temperature monitoring are necessary.
علاج کب ضروری ہوتا ہے، اور کن چیزوں کی نگرانی کی جاتی ہے؟
Treatment is guided by anemia, symptoms, transfusion need and functional impact—not a titer alone. In clinically significant cold agglutinin disease, specialist options include B-cell-directed therapy and complement inhibition; a titer of 1:512 without attributable symptoms or hemolysis does not itself establish a reason to start medication.

Sutimlimab inhibits C1s, an early classical complement component, and can reduce complement-mediated hemolysis in adults with cold agglutinin disease. It does not remove the IgM antibody, so cold-related agglutination and circulation symptoms may persist even if hemoglobin improves; immunization and infection-risk precautions must follow the product information and the specialist's plan.
B-cell-directed options include rituximab-based treatment, sometimes combined with another agent in selected patients; the appropriate choice depends on goals, comorbidities and treatment tolerance. Corticosteroids, commonly used for warm autoimmune hemolytic anemia, generally perform poorly in cold agglutinin disease; the 2020 international consensus emphasizes distinguishing the subtype before applying a treatment pathway (Jäger et al., 2020).
Kantesti helps explain why a hypothetical hemoglobin improvement from 8.7 to 11.8 g/dL, falling bilirubin and fewer transfusions can matter more than a persistently high titer. Our red-cell monitoring guide explains reticulocytes and related markers; do not change treatment from an AI interpretation, and do not assume anemia means iron deficiency.
اپنی رپورٹ کا محفوظ استعمال: شواہد اور AI کی حدود
کنٹیسٹی ایک ہے۔ اے آئی لیب ٹیسٹ کی تشریح کی خدمت that helps organize cold agglutinin results for discussion, but it cannot independently confirm cold agglutinin disease. A useful interpretation needs 3 information groups: the antibody method and handling, the hemolysis pattern and the patient's symptoms and history.

Keep the complete report rather than only the 1:256 result: the test temperature, reference interval, DAT components and laboratory comments can change its meaning. Useful appointment questions include whether hemolysis is present, whether thermal amplitude testing would help and whether specimen handling was adequate; bring earlier hemoglobin values when available.
The Kantesti technical benchmark listed below concerns 100,000 مصنوعی ٹیسٹ کیسز, not 100,000 patients with cold agglutinin disease. The accompanying validation framework describes an assessment approach, not proof that AI can diagnose this rare condition; our validation and oversight page provides the appropriate context for these research publications and their limitations.
Before sharing 1 report or a series of reports, review consent and remove information you do not need to provide, especially when the results belong to someone else. Our رازداری اور ڈیٹا سے متعلق رہنمائی explains data-handling considerations; urgent symptoms belong with emergency or clinical services, not in an upload queue awaiting interpretation.
اکثر پوچھے جانے والے سوالات
کیا کولڈ ایگلوٹینن ٹیسٹ کا مثبت نتیجہ اس بات کا مطلب ہے کہ مجھے کولڈ ایگلوٹینن بیماری ہے؟
مثبت کولڈ ایگلوٹینن ٹیسٹ سے اکیلے کولڈ ایگلوٹینن بیماری کی تشخیص نہیں ہوتی۔ 4°C پر کم از کم 1:64 ٹائٹر تشخیصی عمل میں عام طور پر استعمال ہونے والا ایک جزو ہے، لیکن معالجین دائمی ہیمولائسز اور مطابقت رکھنے والے، عموماً مضبوط C3d-مثبت براہِ راست اینٹی گلوبیولن ٹیسٹ کا بھی جائزہ لیتے ہیں۔ اتفاقی یا انفیکشن سے متعلق اینٹی باڈیز مثبت نتائج پیدا کر سکتی ہیں۔ تھرمل ایمپلیٹیوڈ اور نمونے کو قابلِ اعتماد طریقے سے سنبھالنا غیر یقینی نتائج کی وضاحت میں مدد دیتے ہیں۔
کیا کولڈ ایگلوٹینن ٹائٹر 1:256 یا 1:512 خطرناک ہے؟
کولڈ ایگلوٹینن ٹائٹر 1:256 یا 1:512 بذاتِ خود خطرے کی حد نہیں ہے۔ یہ نتیجہ ظاہر کرتا ہے کہ اسیس کے حالات میں اینٹی باڈی کی سرگرمی قابلِ شناخت رہتے ہوئے سیرم کو کس حد تک پتلا کیا جا سکتا ہے۔ تقریباً 30°C پر فعال اینٹی باڈی طبی لحاظ سے اُس زیادہ ٹائٹر والی اینٹی باڈی سے زیادہ اہم ہو سکتی ہے جو صرف 4°C پر ردِعمل ظاہر کرتی ہے۔ علامات، ہیموگلوبن کے رجحانات اور ہیمولائسز کے مارکرز طے کرتے ہیں کہ معائنے کی کتنی فوری ضرورت ہے۔
کولڈ ایگلوٹینن ٹیسٹ میں تھرمل ایمپلی ٹیوڈ کیا ہوتی ہے؟
Thermal amplitude is the highest temperature at which a cold antibody reacts under the laboratory's testing conditions. Reactivity around 30°C or above is generally more concerning than activity restricted to 4°C because peripheral circulation can become cool enough for the antibody to act. Thermal amplitude is different from titer, which measures activity after dilution. Specialist laboratories may assess it when routine findings are discordant or the clinical significance is unclear.
کولڈ ایگلوٹینن کے نمونے کو گرم رکھنا کیوں ضروری ہے؟
Many laboratories require a cold agglutinin specimen to remain at 37–38°C from collection until serum separation. Premature cooling can allow antibody to bind the patient's cells, leaving less detectable activity in the separated serum and potentially producing a falsely low result. This preparation requirement is separate from deliberately testing the serum at 4°C. Confirm the collecting laboratory's instructions rather than attempting to warm or transport the specimen yourself.
کیا کوئی انفیکشن کولڈ ایگلوٹینن ٹیسٹ کا نتیجہ مثبت آنے کا سبب بن سکتا ہے؟
انفیکشنز، جن میں مائکوپلازما نمونیا اور ایپسٹین–بار وائرس شامل ہیں، عارضی طور پر سردی پر ردِعمل دینے والی اینٹی باڈیز سے وابستہ ہو سکتے ہیں۔ 1:256 جیسا ٹائٹر یہ ثابت نہیں کر سکتا کہ کون سا انفیکشن موجود ہے یا آیا وہ اب بھی فعال ہے۔ انفیکشن سے متعلق اینٹی باڈیز بعض اوقات طبی طور پر اہم ہیمولائسز کا سبب بنتی ہیں، اس لیے ہیموگلوبن میں کمی یا نئے یرقان کی صورت میں اب بھی جانچ ضروری ہے۔ انفیکشن کی تشخیص کے لیے کولڈ ایگلوٹیننز استعمال کرنے کے بجائے، مخصوص پیتھوجن کی جانچ اور علامات کی طبی زمانی ترتیب زیادہ مفید ہیں۔
کیا سرد ایگلوٹیننز کی وجہ سے MCV یا MCHC کی غلط طور پر زیادہ قدریں آ سکتی ہیں؟
سرد ایگلوٹیننز سرخ خلیوں کے ایسے جھرمٹ بنا سکتے ہیں جو خودکار CBC پیمائشوں کو بگاڑ دیتے ہیں، جن میں MCV یا MCHC کا غلط طور پر زیادہ اور RBC شمار کا غلط طور پر کم آنا شامل ہے۔ مثال کے طور پر، ایگلوٹینیشن کے فلیگ کے ساتھ 40 g/dL کا MCHC فوری طور پر خلیوں کی حقیقی خرابی سمجھنے کے بجائے لیبارٹری سے تصدیق کا تقاضا کرتا ہے۔ تقریباً 37°C پر گرم کرنے کے بعد ٹیسٹ دوبارہ کرنے سے یہ مداخلت درست ہو سکتی ہے۔ CBC کی درست شدہ رپورٹ بیک وقت ہیمولائسز کے امکان کو خارج نہیں کرتی۔
کولڈ ایگلوٹینن کا نتیجہ مثبت آنے کے بعد کن علامات کے لیے فوری طبی امداد درکار ہوتی ہے؟
سینے میں درد، آرام کی حالت میں سانس پھولنا، بے ہوشی یا ذہنی الجھن کی صورت میں سرد اجتماع کرنے والے اینٹی باڈی کے ٹائٹر سے قطع نظر ہنگامی طبی جانچ ضروری ہے۔ نیا یرقان، گہرے رنگ کا پیشاب یا تیزی سے بڑھتی ہوئی کمزوری کی صورت میں فوری، اکثر اسی دن، طبی معائنہ کروانا چاہیے۔ ہیموگلوبن میں تیزی سے کمی، مثلاً فرضی طور پر 12 سے 8 g/dL تک، تشویش ناک ہے، اگرچہ کوئی ایک قدر ہر شخص میں فوری طبی امداد کی ضرورت کا تعین نہیں کرتی۔ انگلیوں کی رنگت میں مسلسل دردناک تبدیلی یا اچانک ایسی علامات جو خون کے لوتھڑے کی نشاندہی کریں، ان کے لیے بھی فوری طبی معائنہ ضروری ہے۔
اپنے خون کے ٹیسٹ کے نتائج کی وضاحت حاصل کریں
اپنی لیب رپورٹ اپ لوڈ کریں اور Kantesti کا AI چند سیکنڈ میں ہر بائیومارکر کو آسان زبان میں سمجھائے گا۔ دنیا بھر میں 2 ملین سے زیادہ افراد استعمال کرتے ہیں۔.
حوالہ جات
- Klein, T., Mitchell, S., & Weber, H. (2026). Kantesti Blood-Test Interpretation Engine کی 100,000 مصنوعی ٹیسٹ کیسز پر ایک Pre-Registered، Rubric-Based Automated Technical Benchmark۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Klein, T., Mitchell, S., & Weber, H. (2026). کلینیکل ویلیڈیشن فریم ورک v2.0 (میڈیکل ویلیڈیشن پیج)۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Berentsen S. (2016). Cold agglutinin disease. Hematology, American Society of Hematology Education Program. ڈی او آئی
- Jäger U et al. (2020). Diagnosis and treatment of autoimmune hemolytic anemia in adults: Recommendations from the First International Consensus Meeting. Blood Reviews. ڈی او آئی
- 2M+تجزیہ کیے گئے ٹیسٹ
- 127+ممالک
- 100+زبانیں
طبی ٹیم کے بارے میں


E-E-A-T اعتماد کے اشارے
تجربہ
معالج کی قیادت میں لیب تشریح کے ورک فلو کا کلینیکل جائزہ۔.
مہارت
لیبارٹری میڈیسن کا فوکس یہ کہ بایومارکرز کلینیکل سیاق میں کیسے برتاؤ کرتے ہیں۔.
مستندیت
ڈاکٹر تھامس کلائن نے طبی جائزہ لیا، جبکہ ڈاکٹر سارہ مچل اور پروفیسر ڈاکٹر ہانس ویبر نے بھی تعاون کیا۔.
امانت داری
شواہد پر مبنی تشریح واضح فالو اپ راستوں کے ساتھ تاکہ گھبراہٹ کم ہو۔.






طبی دستبرداری
یہ مضمون صرف تعلیمی مقاصد کے لیے ہے اور طبی مشورہ نہیں ہے۔ تشخیص اور علاج کے فیصلوں کے لیے ہمیشہ کسی مستند صحت کے ماہر سے رجوع کریں۔.
شائع ہوا۔ · ادارتی ٹیم سے رابطہ کریں
Kantesti Ltd کی جانب سے شائع کردہ، انگلینڈ اور ویلز میں رجسٹرڈ، کمپنی نمبر. 17090423, ، لندن، برطانیہ۔.
