
En patogen BRCA1- eller BRCA2-variant ökar den ärftliga cancerrisken; den innebär inte en cancerdiagnos. En variant med osäker signifikans bör inte ligga till grund för förebyggande kirurgi. Ett negativt resultat är ett sant negativt resultat endast om det utesluter en känd familjevariant – annars kan den ärftliga risken förbli oklar.

Viktiga slutsatser
- Positivt resultat betyder att en patogen eller sannolikt patogen variant har identifierats; ärftlig mottaglighet är inte en cancerdiagnos.
- Fem klassificeringar beskriver genetiska varianter: patogen, sannolikt patogen, osäker signifikans, sannolikt benign och benign.
- BRCA1-risk i en prospektiv JAMA-studie uppgick till cirka 72% för bröstcancer och 44% för äggstockscancer vid 80 års ålder hos kvinnor som bär på patogena varianter.
- BRCA2-risk i samma studie uppgick till cirka 69% för bröstcancer och 17% för äggstockscancer vid 80 års ålder; detta är skattningar för grupper, inte personliga förutsägelser.
- Hantering av VUS bör baseras på personlig anamnes och familjeanamnes, inte den osäkra varianten; en VUS motiverar inte i sig förebyggande kirurgi.
- Verkligt negativt resultat betyder att laboratoriet inte hittade den specifika patogena varianten som redan har fastställts i din familj.
- Icke-informativt negativt betyder att testningen inte fann någon förklaring till den misstänkta ärftliga risken; en stark familjeanamnes kan ändå motivera ytterligare bedömning.
- Nedärvning i familjen innebär vanligtvis att varje barn till en bärare av en patogen könscellsvariant i BRCA1 eller BRCA2 har 50 % sannolikhet att ärva den varianten.
- Genetisk rådgivning hjälper till att koppla samman den exakta varianten, testets täckning, båda sidorna av familjen och åldersberoende val av screening eller prevention.
Vad innebär resultaten av BRCA-gentestet egentligen?
Resultat av genetiska BRCA-test delas vanligtvis in i 3 praktiska grupper: positiva, osäkra eller negativa. Ett positivt ärftligt resultat identifierar cancerbenägenhet, en variant av osäker betydelse är fortfarande olöst, och ett negativt resultat behöver sättas i familjesammanhang innan det kan betraktas som lugnande.

A könscellstest för BRCA undersöker DNA, vanligtvis från ett blod- eller salivprov som analyseras på laboratorium, snarare än att mäta en proteinkoncentration. Resultatet kan inte tolkas som ett värde i ng/mL: den kliniskt användbara informationen är genen, den exakta varianten, klassificeringen och testningens omfattning.
De flesta har 2 kopior av BRCA1 och 2 kopior av BRCA2, där en kopia av varje gen ärvs från vardera biologiska föräldern. En skadlig förändring i en kopia kan öka cancerbenägenheten, men ytterligare förändringar i cellerna bidrar i regel till cancerutvecklingen – ärftlighet är ingen nedräkning till sjukdom.
För en hypotetisk 38-åring utan cancer kan ett patogent BRCA2-resultat påverka framtida diskussioner om screening och prevention utan att fastställa någon aktuell cancerdiagnos. För någon som redan får cancerbehandling kan samma ärftliga fynd även påverka behandlingsbehörighet och bedömningen av framtida cancerfall.
Kantesti är en AI blodprovsanalysator för rutinmässig laboratorietolkning, inte en ersättning för ett kliniskt genetiskt laboratorium. Information om vår organisation hjälper till att skilja vår utbildande roll från det specialistarbete som krävs för att tolka ett ärftligt cancerresultat.
Vilka uppgifter i en BRCA-laboratorierapport är viktiga?
De mest användbara uppgifterna i en BRCA-rapport är gen, exakt variant, klassificering, provtyp och testmetod. Kliniska laboratorier använder vanligtvis 5 variantklassificeringar, och ordet “variant” ensamt talar inte om huruvida ett fynd är skadligt.

ACMG/AMP-ramverket skiljer mellan patogena, sannolikt patogena, varianter av oklar signifikans, sannolikt benigna och benigna fynd (Richards et al., 2015). Patogena och sannolikt patogena varianter ger i regel stöd för samma kliniska handläggning; skillnaden beskriver graden av säkerhet i evidensen, inte två olika procentsatser för cancerrisk.
Variantbeskrivningar kan omfatta en förändring på DNA-nivå som börjar med c. and a protein-level consequence beginning with p. These are coordinates, not severity scores; two reports may describe the same change differently because they use different transcripts or historical naming conventions.
Look for both sequence analysis och deletion/duplication analysis when evaluating a comprehensive BRCA1/BRCA2 test. Reading individual DNA changes and detecting missing or extra gene segments require complementary methods, so a report stating “sequencing negative” may not answer every relevant question.
A hypothetical report can contain 2 findings: a pathogenic BRCA1 variant and an unrelated BRCA2 VUS. Management follows the established pathogenic finding, not an average of the two classifications; our guide to categorical versus numerical results explains why laboratory result types require different reading strategies.
Vad betyder ett positivt BRCA1-resultat: anlag, inte visshet
BRCA1 positive meaning depends on the classification: a germline pathogenic or likely pathogenic BRCA1 variant indicates inherited cancer susceptibility. In a prospective study, women carrying pathogenic BRCA1 variants had an estimated 72% breast cancer risk and 44% ovarian cancer risk by age 80.
Kuchenbaecker et al. reported those age-80 estimates in JAMA, with 95% confidence intervals of 65–79% for breast cancer och 36–53% for ovarian cancer (2017). The intervals describe uncertainty around population estimates; they do not mean an individual’s risk can be read directly from the laboratory report.
A hypothetical 30-year-old BRCA1 carrier should not interpret a 72% age-80 estimate as a 72% risk this year. Personal counseling separates near-term risk from longer-term risk and considers age, prior cancer, relatives’ diagnoses and any preventive procedures already completed.
BRCA1-associated breast cancers are more often triple-negative than breast cancers in the general population, but receptor status cannot be predicted from an inherited result alone. An existing cancer still requires its own pathological and receptor assessment; a genetic finding does not replace those separate tests.
One family can also have more than one inherited explanation for cancer, particularly when diagnoses cluster on both parental branches. For example, several colorectal and endometrial cancers may justify a separate assessment of Lynch syndrome results rather than assuming a BRCA1 finding explains every diagnosis.
Hur skiljer sig cancerrisken vid BRCA2-mutation?
BRCA2 mutation cancer risk includes breast and ovarian cancer susceptibility, with particular relevance to male breast, prostate and pancreatic cancer assessment. In the same prospective JAMA study, women carrying pathogenic BRCA2 variants had estimated risks of 69% for breast cancer and 17% for ovarian cancer by age 80.
The BRCA2 estimates had 95% confidence intervals of 61–77% for breast cancer och 11–25% for ovarian cancer (Kuchenbaecker et al., 2017). BRCA2’s lower average ovarian cancer risk compared with BRCA1 helps explain why preventive ovary-and-tube removal is commonly discussed later for BRCA2 carriers.
A previous breast cancer creates a different risk question: the chance of another cancer in the opposite breast. Kuchenbaecker et al. estimated 20-year contralateral breast cancer risks of 26% for BRCA2 and 40% for BRCA1; those figures are not the same as first-cancer risk and should not be substituted for it.
Prostate screening discussions may begin around age 40 in men with pathogenic BRCA2 variants, depending on the applicable clinical pathway. PSA is a screening measurement rather than a symptom generator; our explanation of what elevated PSA means separates the laboratory number from a diagnosis.
Pancreatic surveillance is another area where eligibility criteria differ, including the importance assigned to family history. A hypothetical 52-year-old BRCA2 carrier with an affected first-degree relative needs a specialist discussion about MRI-based imaging or endoscopic ultrasound—not routine CA 19-9 testing as a substitute.
Vad betyder en BRCA-variant med osäker signifikans?
A BRCA variant of uncertain significance, or VUS, means available evidence cannot establish whether a DNA change increases cancer risk. A VUS is not a positive result, and it should not independently determine preventive mastectomy or removal of the ovaries and fallopian tubes.

The ACMG/AMP standards state that a VUS inte ska användas i kliniskt beslutsfattande (Richards et al., 2015). Among the 5 classification categories, uncertainty is an evidence status—not a diagnosis, not a halfway-positive result and not a 50% probability that the variant causes cancer.
For example, a hypothetical 42-year-old with a BRCA1 VUS and no significant family history should not be offered risk-reducing surgery because of that VUS alone. Another 42-year-old with the same VUS and a substantial family history may qualify for intensified surveillance because of the history, not because the uncertain variant became actionable.
Ancestry can affect how often laboratories encounter uncertainty because population databases do not represent every group equally. Two people with the same cancer history can therefore receive different levels of interpretive certainty; this reflects evidence gaps and does not establish a biological difference in the seriousness of their results.
At Kantesti, we separate finding a genetic change from proving that the change warrants action. The same distinction helps readers understand common MTHFR variant findings, although MTHFR results and BRCA-associated cancer susceptibility have very different clinical implications.
Kan klassificeringen av en BRCA-VUS ändras senare?
A BRCA VUS can be reclassified when new evidence clarifies its clinical significance. Many reclassified VUS move toward benign categories, but neither the direction nor the timing can be promised for an individual finding; reinterpretation usually reviews existing DNA data rather than requiring another sample.

Useful new evidence can come from 3 broad sources: population frequency, carefully validated functional work and observations of the variant in families. A computer prediction alone is usually insufficient; expert curation weighs whether the evidence actually addresses the disease mechanism and meets classification standards.
Laboratories can disagree because their evidence differs or their interpretations were issued at different times. Record 2 separate dates when available—the original report date and the most recent classification date—and ask whether a specialist expert-panel assessment exists, rather than counting database entries as votes.
Routine testing of unaffected relatives for a VUS usually does not guide care, although a genetics team may arrange selected family studies to help classification. A hypothetical family with 3 affected relatives should not independently order VUS testing for everyone and interpret who carries it as proof of causation.
Ask which laboratory manages reinterpretation, how amended reports reach you and whether your contact details remain current; there is no universal recontact interval. Our discussion of inherited TTR variant interpretation illustrates the broader need to connect exact genetic findings with disease-specific evidence.
När är ett negativt BRCA-resultat ett sant negativt resultat?
A true negative BRCA result means testing did not find the specific pathogenic or likely pathogenic variant already identified in a biological relative. It removes the inherited risk attributable to that familial variant, but it does not eliminate ordinary cancer risk or unrelated risks from the other family branch.

Suppose a hypothetical mother has a confirmed pathogenic BRCA1 variant and her adult daughter’s targeted test excludes that exact variant. Before testing, the daughter generally had a 50% ärftlighetssannolikhet; afterward, she is not considered a carrier of that maternal finding and cannot pass that uncarried variant to her children.
A negative result becomes less definitive if nobody knows the affected relative’s exact finding. Bring a copy of the original family report rather than a verbal account of “BRCA positive”; a gene name alone cannot distinguish a pathogenic variant from a VUS or identify which change the laboratory should test.
An independently concerning paternal history can remain relevant despite a maternal true negative. For example, 2 close paternal relatives with early breast cancer may warrant separate risk assessment, because excluding one maternal variant does not explain another branch of the pedigree.
The logic of matching a relative’s exact finding also appears in family-based Alport genetic testing, although the genes and inheritance patterns differ. Ask for a written statement identifying which familial variant was excluded and what remaining screening recommendation follows from your own history.
Varför kan ett negativt BRCA-resultat vara informativt?
En icke-informativt negativt testresultat means no actionable BRCA finding was detected, but testing has not explained a suspicious personal or family cancer history. The result may reflect another gene, a technical limitation or a familial risk pattern that cannot currently be assigned to one detectable variant.

Testing an affected relative first usually provides more information than testing an unaffected relative. A hypothetical unaffected 35-year-old’s negative panel does not prove that her mother’s ovarian cancer lacked an inherited cause; testing the mother, when possible, can establish whether there is a familial finding to exclude.
A broader panel may consider genes such as PALB2, ATM, CHEK2, RAD51C, RAD51D and BRIP1, depending on the cancer pattern. These genes do not share identical cancer risks or prevention recommendations, so “panel positive” still requires gene-specific interpretation rather than applying the BRCA pathway to every result.
Older tests or limited consumer tests may assess only selected variants, whereas comprehensive clinical testing can include sequencing and deletion/duplication analysis. Our explanation of hidden carrier-screening limitations illustrates why a reassuring-looking result can still depend on methodology, although SMA uses a different genetic model.
Kantesti AI does not establish the completeness of a genetic assay or certify that a family’s inherited risk has been excluded. If a hypothetical family has 3 related cancers despite negative testing, clinical genetics can decide whether updated testing, another affected relative or a formal family-history risk model would answer the unresolved question.
Innebär ett BRCA-fynd i en tumör att det är ärftligt?
A BRCA variant found in tumor tissue is not automatically inherited. Tumor testing can detect acquired changes confined to cancer cells; germline testing examines a suitable non-tumor specimen to determine whether the finding is constitutional and relevant to relatives.

A tumor report may show a variant allele fraction near 50%, but that number does not prove germline origin. Tumor purity, copy-number changes and loss of the other gene copy can all shift the fraction; a percentage on a tumor report cannot replace a properly selected germline test.
Some oncology reports describe homologous recombination deficiency, or HRD, rather than a specific inherited variant. HRD can arise through more than one mechanism, and an HRD-positive result does not establish that a person or their children carry a pathogenic BRCA1 or BRCA2 variant.
After an allogeneic stem-cell transplant, a blood-derived DNA sample may reflect the donor, and saliva can also contain donor-derived cells. A hypothetical transplant recipient therefore needs the genetics laboratory to select an appropriate specimen—sometimes cultured skin fibroblasts—rather than assuming that 2 easily obtained samples answer the inheritance question.
The distinction between acquired and inherited DNA changes also matters in UBA1-related VEXAS testing, although VEXAS is a different condition. For a tumor BRCA finding, ask whether germline confirmation has been completed, is pending or was never requested.
När är genetisk vägledning till störst hjälp?
Genetic counseling helps before testing and whenever a result could change screening, treatment or family testing. It is especially useful for pathogenic findings, unresolved VUS, limited negative tests and family patterns involving young diagnoses, ovarian cancer, male breast cancer or multiple related cancers.

A practical pedigree usually covers 3 generationer and records cancer type, age at diagnosis, biological relationships and both maternal and paternal branches. “Abdominal cancer” is less useful than a confirmed primary site; ovarian, pancreatic and metastatic cancers can otherwise be misremembered as the same diagnosis.
Small families, early deaths and few female relatives can hide hereditary breast-and-ovarian cancer patterns. A hypothetical father with 2 sons and no sisters can carry and transmit a BRCA variant even when the family has no obvious breast cancer cluster; paternal inheritance deserves the same attention as maternal inheritance.
Kantesti är en AI-plattform för tolkning av blodprov, not a genetic counseling service. Our guidance on age-appropriate family testing separates routine laboratory needs from predictive BRCA testing, which is generally deferred in children under 18 because management usually begins in adulthood.
Before an appointment, gather the actual family report, pathology details if available and your previous test methods. Use separate consent for each relative’s records; our discussion of family health consent explains why a shared family history does not give one person automatic permission to access everyone’s medical information.
Vilken uppföljning görs efter ett patogent BRCA-resultat?
A germline pathogenic BRCA result warrants a personalized prevention plan, not automatic surgery. Options include enhanced breast screening, discussion of risk-reducing procedures and assessment of other gene-associated cancers; age, reproductive plans, previous cancer and local guidance determine the timing.

Many high-risk pathways use annual breast MRI beginning around ages 25–30, with mammography commonly added around age 30, but national recommendations differ. The reason for combining methods is that each detects some findings the other can miss; more imaging is not simply a substitute for understanding age-specific benefit and false-positive risk.
NICE guideline NG241 lists risk-reducing removal of ovaries and fallopian tubes no earlier than age 35 for BRCA1 and 40 for BRCA2, with individualized assessment (NICE, 2024). Common clinical discussions use windows of approximately 35–40 and 40–45 years, respectively, after childbearing; these are planning ranges, not instructions for every carrier.
Removing only the fallopian tubes while delaying ovary removal has not been established as equivalent protection and remains a trial-based strategy in NICE guidance. Surgical menopause can affect symptoms, cardiovascular health and bones; our guide för kvinnors hormonella hälsa explains why prevention planning includes consequences beyond cancer risk.
Hormone treatment after premenopausal risk-reducing surgery may be considered until the usual menopause age, approximately 51, but previous breast cancer and other contraindications change that discussion. Bone-density assessment and evaluation of secondary bone-loss causes are distinct tasks; our guide to bone health laboratory assessment explains what routine tests can and cannot answer.
Vad innebär ett BRCA-resultat för släktingar och barn?
Each child of a germline BRCA pathogenic-variant carrier usually has a 50% chance of inheriting the variant, regardless of sex. Adult relatives can consider targeted testing for the established family finding; inheriting susceptibility does not mean inheriting an existing cancer.
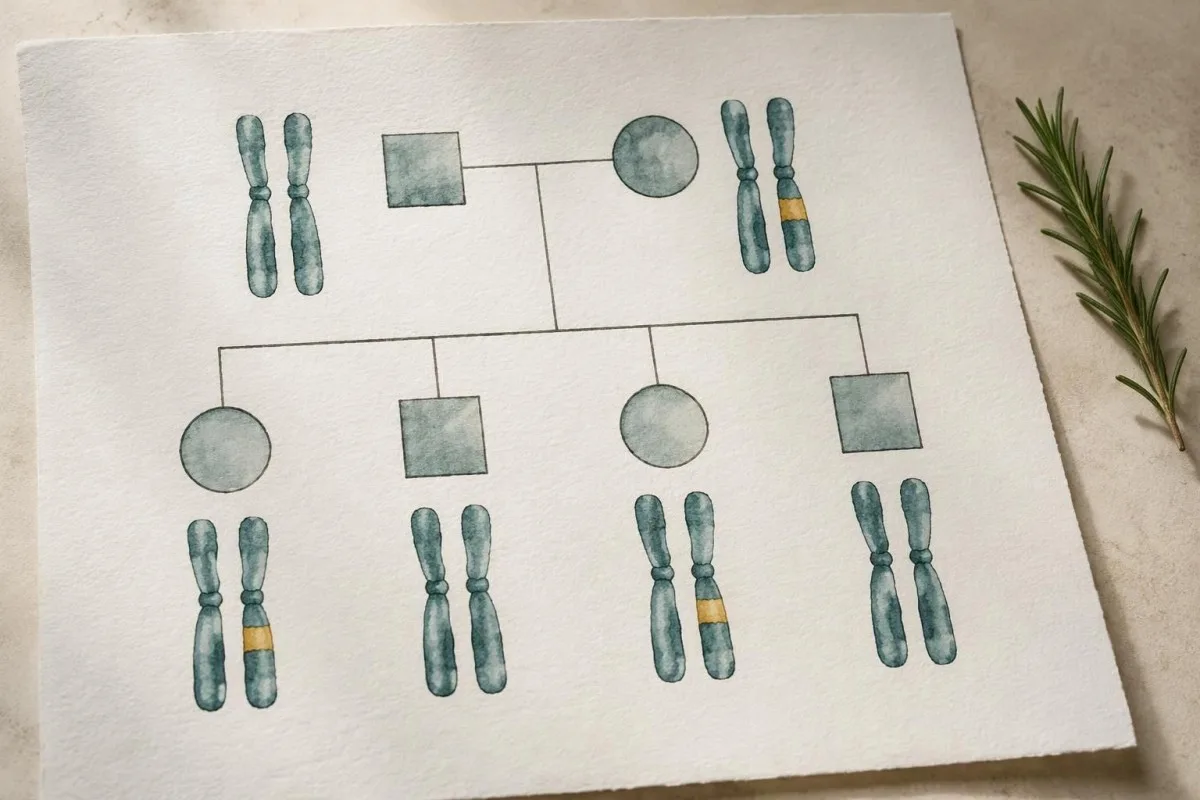
Four children do not imply that exactly 2 will inherit a parent’s BRCA variant. Each pregnancy is an independent event, so all, none or any number in between can inherit it; the 50% figure describes probability rather than a guaranteed family distribution.
A carrier’s siblings often have a 50% risk of sharing the variant when a parent carries it, but that estimate should not be applied without checking the pedigree. Identifying which parent carries the finding helps determine which cousins, aunts and uncles should receive an invitation to discuss testing.
Reproductive options can include natural conception, prenatal diagnosis or IVF with preimplantation genetic testing for a known familial variant. These are preference-sensitive choices, not obligations; our explanation of reproductive genetic result counseling shows why gene-specific inheritance matters, although FMR1 repeat expansion behaves differently from BRCA inheritance.
A rare additional question arises when both partners carry pathogenic variants in BRCA2: each pregnancy has a 25% chance of inheriting pathogenic variants in both copies, which can cause a Fanconi anemia phenotype. Partner testing is not automatically required for every BRCA carrier, but ancestry, relatedness and reproductive planning can justify specialist assessment.
Kan symtom eller tumörmarkörer bekräfta BRCA-relaterad cancer?
Neither a BRCA result nor a tumor-marker concentration confirms that cancer is present. New symptoms need their own assessment, and a negative genetic result does not make them harmless; examination, imaging and sometimes tissue assessment answer a different question from inherited susceptibility testing.

CA-125 can rise in benign conditions and can remain normal in ovarian cancer, particularly earlier disease. Routine CA-125 and ultrasound screening have not demonstrated a mortality benefit sufficient to replace established risk-reduction discussions; our guide to CA-125 limits and symptoms explains why the usual 35 U/mL cutoff is not a cancer yes-or-no boundary.
CA 15-3 and CA 27-29 are not appropriate tests for deciding whether an unaffected BRCA carrier has developed breast cancer. A hypothetical carrier with a normal marker still needs assessment of a new breast lump; our explanation of CA 15-3 interpretation separates selected monitoring uses from screening.
Kantesti does not infer BRCA carrier status from routine laboratory markers. For example, a CA 19-9 result of 80 U/mL can have non-cancer explanations and cannot establish pancreatic cancer or inherited BRCA2 risk; our guide to CA 19-9 limitations explains the need for clinical and imaging context.
Persistent bloating, early satiety, unexplained weight loss, a new breast change or unexplained jaundice deserve timely medical review regardless of genetic classification. A hypothetical person with 3 weeks of new persistent symptoms should not wait for VUS reclassification or a routine genetics appointment before seeking a separate assessment.
Använd AI-förklaringar utan att ersätta genetisk vägledning
AI explanations can support understanding, but they cannot independently classify a BRCA variant or authorize preventive surgery. A safe workflow preserves 3 essentials: the original laboratory report, specialist interpretation and a written follow-up plan that distinguishes inherited risk from evaluation of any current symptoms.

Kantesti är en Plattform för tolkning av AI-biomarkörer that explains routine laboratory findings, with interpretation generally available in about 60 seconds. That turnaround is not a timetable for genetic counseling, and our klinisk metodikinformation should not be read as validation of independent BRCA classification or hereditary cancer risk calculation.
Genetic reports can reveal information relevant to more than 1 person, including biological relatives who have not chosen testing. Read our sekretess- och datahanteringsrutiner before sharing sensitive documents, and avoid uploading another relative’s identifiable report without their permission.
The 2 research publications listed below concern our global routine-test report and RDW educational material; they are not BRCA cancer-risk studies, clinical prevention guidelines or evidence supporting surgery. The medical recommendations in this article instead draw on the ACMG/AMP classification standards, the prospective JAMA risk study and NICE familial ovarian cancer guidance.
Before acting, ask your genetics team to document whether the result is germline, which exact variant is actionable and whether a negative is true or uninformative. Our principer för ansvarsfull AI support keeping those clinical decisions with qualified professionals rather than treating an automated explanation as another laboratory classification.
Vanliga frågor
Betyder ett positivt BRCA1- eller BRCA2-test att jag har cancer?
Ett positivt test för nedärvd BRCA1 eller BRCA2 visar att det finns en patogen eller sannolikt patogen ärftlig variant; det diagnostiserar inte cancer. I den prospektiva studien av Kuchenbaecker et al. i JAMA uppskattades risken för bröstcancer fram till 80 års ålder till 72% för BRCA1 och 69% för BRCA2 hos kvinnor med patogena varianter. Det är skattningar för en population, inte sannolikheten för att cancer finns just nu. För att diagnostisera en pågående cancer krävs en separat klinisk bedömning.
Bör jag genomgå förebyggande kirurgi på grund av en BRCA-variant av oklar betydelse?
En BRCA-variant av osäker betydelse bör inte ensam avgöra om förebyggande kirurgi ska genomföras. ACMG/AMP-ramverket omfattar fem evidensbaserade klassificeringar av varianter och anger att varianter av osäker betydelse inte ska användas vid kliniska beslut. Den egna sjukdomshistorien eller familjehistorien kan i sig motivera vård för personer med högre risk, men beslutet får inte utgå från att varianten av osäker betydelse är patogen. En genetisk rådgivare kan förklara vilken evidens som faktiskt ligger till grund för ett föreslaget ingrepp.
Vad är skillnaden mellan ett sant negativt och ett icke-informativt negativt BRCA-resultat?
Ett sant negativt resultat utesluter den specifika patogena eller sannolikt patogena BRCA-varianten som redan har påvisats hos en biologisk släkting. För ett barn till en bärare kan detta klargöra den ursprungliga sannolikheten på 50 % att ha ärvt den aktuella familjevarianten. Ett icke-informativt negativt resultat påvisar ingen handlingsbar variant utan att fastställa varför cancer har uppstått i familjen. Andra familjegrenar, ytterligare gener och testbegränsningar kan fortfarande vara relevanta efter båda typerna av resultat.
Kan en BRCA-VUS senare bli positiv?
En BRCA-VUS kan senare omklassificeras som patogen eller sannolikt patogen, men den kan också omklassificeras till sannolikt benign eller benign. Vid omklassificeringen granskas evidensen inom samma femgradiga klassificeringssystem; det innebär inte att personens DNA har förändrats. Det finns ingen generell tidsfrist eller garanterad riktning för en enskild variant. Fråga det ursprungliga laboratoriet eller den genetiska mottagningen hur ändrade rapporter och återkontakt hanteras.
Kan jag ärva en BRCA-variant från min far?
En patogen BRCA1- eller BRCA2-variant kan ärvas från endera biologiska föräldern. Varje barn till en person som bär på en könscellsvariant har vanligtvis 50 % sannolikhet att ärva varianten, oavsett om det är mamman eller pappan som bär på den. En familj på faderns sida med få kvinnliga släktingar kan ha få synliga fall av bröst- eller äggstockscancer trots att den bär på en variant. Därför bör genetisk vägledning ta hänsyn till båda släktgrenarna.
Innebär en BRCA-mutation som påvisats i min tumör att mina barn löper risk?
En BRCA-mutation som hittas i tumörvävnad visar inte att den är ärftlig. Även en variantallelfrekvens på nära 50 % i tumören kan inte på ett tillförlitligt sätt bevisa att den är av germinalt ursprung, eftersom tumörens renhet och förändringar i kopietal påverkar denna andel. Germinaltestning med ett lämpligt prov krävs för att fastställa ärftlig status. Den vanliga sannolikheten på 50 % för nedärvning gäller endast när föräldern bär på en germinal variant.
Behöver jag upprepa ett negativt BRCA-test varje år?
Annual repeat BRCA DNA testing is not generally needed because an inherited variant does not appear simply with aging. A negative result may deserve review if the original assay was limited, a new family variant is identified or another relative develops a relevant cancer. For example, testing only 3 selected variants is not equivalent to comprehensive BRCA1/BRCA2 sequencing plus deletion/duplication analysis. Ask a genetics service whether reinterpretation, targeted family testing or a different panel would add information.
Få dina blodprovsresultat förklarade
Ladda upp din laboratorierapport så förklarar Kantesti:s AI varje biomarkör på ett lättbegripligt språk inom några sekunder. Används av mer än 2 miljoner människor världen över.
Referenser
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2,5M tester analyserade | Global Health Report 2026. Kantesti AI Medicinsk forskning. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW-blodprov: komplett guide till RDW-CV, MCV och MCHC. Kantesti AI Medicinsk forskning. DOI
- Richards S et al. (2015). Standarder och riktlinjer för tolkning av sekvensvarianter: en gemensam konsensusrekommendation från American College of Medical Genetics and Genomics och Association for Molecular Pathology. Genetics in Medicine. DOI PubMed
- Kuchenbaecker KB et al. (2017). Risks of Breast, Ovarian, and Contralateral Breast Cancer for BRCA1 and BRCA2 Mutation Carriers. JAMA. DOI PubMed
- National Institute for Health and Care Excellence (2024). Ovarian cancer: identifying and managing familial and genetic risk. NICE guideline NG241.
- 2 miljoner+Analyserade tester
- 127+Länder
- 100+Språk
Om det medicinska teamet


E-E-A-T förtroendesignaler
Uppleva
Läkarledd klinisk granskning av arbetsflöden för laboratorietolkning.
Expertis
Laboratoriemedicinskt fokus på hur biomarkörer beter sig i kliniskt sammanhang.
Auktoritet
Medicinskt granskad av Dr. Thomas Klein, med bidrag från Dr. Sarah Mitchell och Prof. Dr. Hans Weber.
Trovärdighet
Evidensbaserad tolkning med tydliga uppföljningsspår för att minska larm.






Medicinsk friskrivning
Den här artikeln är endast avsedd för utbildningsändamål och utgör inte medicinsk rådgivning. Rådgör alltid med en behörig vårdgivare för beslut om diagnos och behandling.
Publicerad · Kontakta redaktionen
Publicerad av Kantesti Ltd, registrerat i England och Wales, företagsnr. 17090423, London, Storbritannien.
