
A pathogenic BRCA1 or BRCA2 variant increases inherited cancer risk; it does not diagnose cancer. A variant of uncertain significance should not drive preventive surgery. A negative result is a true negative only when it excludes a known familial variant—otherwise, it may leave inherited risk unresolved.

Asosiy xulosalar
- Musbat natija means a pathogenic or likely pathogenic variant was identified; inherited susceptibility is not a cancer diagnosis.
- Five classifications describe genetic variants: pathogenic, likely pathogenic, uncertain significance, likely benign and benign.
- BRCA1 risk in a prospective JAMA study reached approximately 72% for breast cancer and 44% for ovarian cancer by age 80 in women carrying pathogenic variants.
- BRCA2 risk in the same study reached approximately 69% for breast cancer and 17% for ovarian cancer by age 80; these are group estimates, not personal predictions.
- VUS management should follow personal and family history, not the uncertain variant; a VUS alone does not justify preventive surgery.
- Haqiqiy manfiy natija means the laboratory did not find the specific pathogenic variant already established in your family.
- Uninformative negative means testing found no explanation for suspected inherited risk; strong family history can still justify additional assessment.
- Oilaviy irsiylanish usually gives each child of a germline BRCA1 or BRCA2 pathogenic-variant carrier a 50% chance of inheriting that variant.
- Genetika maslahati helps connect the exact variant, test coverage, both sides of the family and age-dependent screening or prevention choices.
What do BRCA genetic test results actually mean?
BRCA genetic test results usually fall into 3 practical groups: positive, uncertain or negative. A positive inherited result identifies cancer susceptibility, a ahamiyatsiz variant remains unresolved, and a negative result needs family context before it can be called reassuring.

A germline BRCA test examines DNA, usually from a laboratory blood or saliva sample, rather than measuring a protein concentration. Its result cannot be interpreted like a value in ng/mL: the clinically useful information is the gene, exact variant, classification and scope of testing.
Aksariyat odamlarda 2 copies of BRCA1 and 2 copies of BRCA2, with one copy of each inherited from each biological parent. A harmful change in one copy can increase cancer susceptibility, but additional cellular changes generally contribute to cancer development—inheritance is not a countdown to disease.
For a hypothetical 38-year-old without cancer, a pathogenic BRCA2 result can change future screening and prevention discussions without establishing any current cancer diagnosis. For someone already receiving cancer treatment, the same inherited finding may also affect treatment eligibility and assessment of future cancers.
Kantesti - bu AI qon testi analizatori for routine laboratory interpretation, not a substitute for a clinical genetics laboratory. Information about bizning tashkilotimizda helps distinguish our educational role from the specialist work required to interpret an inherited cancer result.
Which details on a BRCA laboratory report matter?
The most useful details on a BRCA report are the gene, exact variant, classification, specimen type and testing method. Clinical laboratories commonly use 5 variant classifications, and the word “variant” alone does not tell you whether a finding is harmful.

The ACMG/AMP framework separates pathogenic, likely pathogenic, uncertain significance, likely benign and benign findings (Richards et al., 2015). Pathogenic and likely pathogenic variants generally support the same clinical management pathway; the distinction describes confidence in the evidence, not two different percentages of cancer risk.
Variant descriptions can include a DNA-level change beginning with c. and a protein-level consequence beginning with p. These are coordinates, not severity scores; two reports may describe the same change differently because they use different transcripts or historical naming conventions.
Look for both sequence analysis va deletion/duplication analysis when evaluating a comprehensive BRCA1/BRCA2 test. Reading individual DNA changes and detecting missing or extra gene segments require complementary methods, so a report stating “sequencing negative” may not answer every relevant question.
A hypothetical report can contain 2 findings: a pathogenic BRCA1 variant and an unrelated BRCA2 VUS. Management follows the established pathogenic finding, not an average of the two classifications; our guide to categorical versus numerical results explains why laboratory result types require different reading strategies.
BRCA1 positive meaning: susceptibility, not certainty
BRCA1 positive meaning depends on the classification: a germline pathogenic or likely pathogenic BRCA1 variant indicates inherited cancer susceptibility. In a prospective study, women carrying pathogenic BRCA1 variants had an estimated 72% breast cancer risk and 44% ovarian cancer risk by age 80.
Kuchenbaecker et al. reported those age-80 estimates in JAMA, with 95% confidence intervals of 65–79% for breast cancer va 36–53% for ovarian cancer (2017). The intervals describe uncertainty around population estimates; they do not mean an individual’s risk can be read directly from the laboratory report.
A hypothetical 30-year-old BRCA1 carrier should not interpret a 72% age-80 estimate as a 72% risk this year. Personal counseling separates near-term risk from longer-term risk and considers age, prior cancer, relatives’ diagnoses and any preventive procedures already completed.
BRCA1-associated breast cancers are more often triple-negative than breast cancers in the general population, but receptor status cannot be predicted from an inherited result alone. An existing cancer still requires its own pathological and receptor assessment; a genetic finding does not replace those separate tests.
One family can also have more than one inherited explanation for cancer, particularly when diagnoses cluster on both parental branches. For example, several colorectal and endometrial cancers may justify a separate assessment of Lynch syndrome results rather than assuming a BRCA1 finding explains every diagnosis.
How does BRCA2 mutation cancer risk differ?
BRCA2 mutation cancer risk includes breast and ovarian cancer susceptibility, with particular relevance to male breast, prostate and pancreatic cancer assessment. In the same prospective JAMA study, women carrying pathogenic BRCA2 variants had estimated risks of 69% for breast cancer and 17% for ovarian cancer by age 80.
The BRCA2 estimates had 95% confidence intervals of 61–77% for breast cancer va 11–25% for ovarian cancer (Kuchenbaecker et al., 2017). BRCA2’s lower average ovarian cancer risk compared with BRCA1 helps explain why preventive ovary-and-tube removal is commonly discussed later for BRCA2 carriers.
A previous breast cancer creates a different risk question: the chance of another cancer in the opposite breast. Kuchenbaecker et al. estimated 20-year contralateral breast cancer risks of 26% for BRCA2 and 40% for BRCA1; those figures are not the same as first-cancer risk and should not be substituted for it.
Prostate screening discussions may begin around age 40 in men with pathogenic BRCA2 variants, depending on the applicable clinical pathway. PSA is a screening measurement rather than a symptom generator; our explanation of what elevated PSA means separates the laboratory number from a diagnosis.
Pancreatic surveillance is another area where eligibility criteria differ, including the importance assigned to family history. A hypothetical 52-year-old BRCA2 carrier with an affected first-degree relative needs a specialist discussion about MRI-based imaging or endoscopic ultrasound—not routine CA 19-9 testing as a substitute.
What does a BRCA variant of uncertain significance mean?
A BRCA variant of uncertain significance, or VUS, means available evidence cannot establish whether a DNA change increases cancer risk. A VUS is not a positive result, and it should not independently determine preventive mastectomy or removal of the ovaries and fallopian tubes.

The ACMG/AMP standards state that a VUSni klinik qaror qabul qilishda (Richards et al., 2015). Among the 5 classification categories, uncertainty is an evidence status—not a diagnosis, not a halfway-positive result and not a 50% probability that the variant causes cancer.
For example, a hypothetical 42-year-old with a BRCA1 VUS and no significant family history should not be offered risk-reducing surgery because of that VUS alone. Another 42-year-old with the same VUS and a substantial family history may qualify for intensified surveillance because of the history, not because the uncertain variant became actionable.
Ancestry can affect how often laboratories encounter uncertainty because population databases do not represent every group equally. Two people with the same cancer history can therefore receive different levels of interpretive certainty; this reflects evidence gaps and does not establish a biological difference in the seriousness of their results.
At Kantesti, we separate finding a genetic change from proving that the change warrants action. The same distinction helps readers understand common MTHFR variant findings, although MTHFR results and BRCA-associated cancer susceptibility have very different clinical implications.
Can a BRCA VUS change classification later?
A BRCA VUS can be reclassified when new evidence clarifies its clinical significance. Many reclassified VUS move toward benign categories, but neither the direction nor the timing can be promised for an individual finding; reinterpretation usually reviews existing DNA data rather than requiring another sample.

Useful new evidence can come from 3 broad sources: population frequency, carefully validated functional work and observations of the variant in families. A computer prediction alone is usually insufficient; expert curation weighs whether the evidence actually addresses the disease mechanism and meets classification standards.
Laboratories can disagree because their evidence differs or their interpretations were issued at different times. Record 2 separate dates when available—the original report date and the most recent classification date—and ask whether a specialist expert-panel assessment exists, rather than counting database entries as votes.
Routine testing of unaffected relatives for a VUS usually does not guide care, although a genetics team may arrange selected family studies to help classification. A hypothetical family with 3 affected relatives should not independently order VUS testing for everyone and interpret who carries it as proof of causation.
Ask which laboratory manages reinterpretation, how amended reports reach you and whether your contact details remain current; there is no universal recontact interval. Our discussion of inherited TTR variant interpretation illustrates the broader need to connect exact genetic findings with disease-specific evidence.
When is a negative BRCA result a true negative?
A true negative BRCA result means testing did not find the specific pathogenic or likely pathogenic variant already identified in a biological relative. It removes the inherited risk attributable to that familial variant, but it does not eliminate ordinary cancer risk or unrelated risks from the other family branch.

Suppose a hypothetical mother has a confirmed pathogenic BRCA1 variant and her adult daughter’s targeted test excludes that exact variant. Before testing, the daughter generally had a 50% irsiylanish ehtimoli; afterward, she is not considered a carrier of that maternal finding and cannot pass that uncarried variant to her children.
A negative result becomes less definitive if nobody knows the affected relative’s exact finding. Bring a copy of the original family report rather than a verbal account of “BRCA positive”; a gene name alone cannot distinguish a pathogenic variant from a VUS or identify which change the laboratory should test.
An independently concerning paternal history can remain relevant despite a maternal true negative. For example, 2 close paternal relatives with early breast cancer may warrant separate risk assessment, because excluding one maternal variant does not explain another branch of the pedigree.
The logic of matching a relative’s exact finding also appears in family-based Alport genetic testing, although the genes and inheritance patterns differ. Ask for a written statement identifying which familial variant was excluded and what remaining screening recommendation follows from your own history.
Why can a negative BRCA result be uninformative?
An ma’lumotsiz manfiy means no actionable BRCA finding was detected, but testing has not explained a suspicious personal or family cancer history. The result may reflect another gene, a technical limitation or a familial risk pattern that cannot currently be assigned to one detectable variant.

Testing an affected relative first usually provides more information than testing an unaffected relative. A hypothetical unaffected 35-year-old’s negative panel does not prove that her mother’s ovarian cancer lacked an inherited cause; testing the mother, when possible, can establish whether there is a familial finding to exclude.
A broader panel may consider genes such as PALB2, ATM, CHEK2, RAD51C, RAD51D and BRIP1, depending on the cancer pattern. These genes do not share identical cancer risks or prevention recommendations, so “panel positive” still requires gene-specific interpretation rather than applying the BRCA pathway to every result.
Older tests or limited consumer tests may assess only selected variants, whereas comprehensive clinical testing can include sequencing and deletion/duplication analysis. Our explanation of hidden carrier-screening limitations illustrates why a reassuring-looking result can still depend on methodology, although SMA uses a different genetic model.
Kantesti AI does not establish the completeness of a genetic assay or certify that a family’s inherited risk has been excluded. If a hypothetical family has 3 related cancers despite negative testing, clinical genetics can decide whether updated testing, another affected relative or a formal family-history risk model would answer the unresolved question.
Does a BRCA finding in a tumor mean it is inherited?
A BRCA variant found in tumor tissue is not automatically inherited. Tumor testing can detect acquired changes confined to cancer cells; germline testing examines a suitable non-tumor specimen to determine whether the finding is constitutional and relevant to relatives.

A tumor report may show a variant allele fraction near 50%, but that number does not prove germline origin. Tumor purity, copy-number changes and loss of the other gene copy can all shift the fraction; a percentage on a tumor report cannot replace a properly selected germline test.
Some oncology reports describe homologous recombination deficiency, or HRD, rather than a specific inherited variant. HRD can arise through more than one mechanism, and an HRD-positive result does not establish that a person or their children carry a pathogenic BRCA1 or BRCA2 variant.
After an allogeneic stem-cell transplant, a blood-derived DNA sample may reflect the donor, and saliva can also contain donor-derived cells. A hypothetical transplant recipient therefore needs the genetics laboratory to select an appropriate specimen—sometimes cultured skin fibroblasts—rather than assuming that 2 easily obtained samples answer the inheritance question.
The distinction between acquired and inherited DNA changes also matters in UBA1-related VEXAS testing, although VEXAS is a different condition. For a tumor BRCA finding, ask whether germline confirmation has been completed, is pending or was never requested.
When does genetic counseling help most?
Genetic counseling helps before testing and whenever a result could change screening, treatment or family testing. It is especially useful for pathogenic findings, unresolved VUS, limited negative tests and family patterns involving young diagnoses, ovarian cancer, male breast cancer or multiple related cancers.

A practical pedigree usually covers 3 avlod and records cancer type, age at diagnosis, biological relationships and both maternal and paternal branches. “Abdominal cancer” is less useful than a confirmed primary site; ovarian, pancreatic and metastatic cancers can otherwise be misremembered as the same diagnosis.
Small families, early deaths and few female relatives can hide hereditary breast-and-ovarian cancer patterns. A hypothetical father with 2 sons and no sisters can carry and transmit a BRCA variant even when the family has no obvious breast cancer cluster; paternal inheritance deserves the same attention as maternal inheritance.
Kantesti - bu AI qon tahlili natijalari platformasi, not a genetic counseling service. Our guidance on age-appropriate family testing separates routine laboratory needs from predictive BRCA testing, which is generally deferred in children under 18 because management usually begins in adulthood.
Before an appointment, gather the actual family report, pathology details if available and your previous test methods. Use separate consent for each relative’s records; our discussion of family health consent explains why a shared family history does not give one person automatic permission to access everyone’s medical information.
What follow-up follows a pathogenic BRCA result?
A germline pathogenic BRCA result warrants a personalized prevention plan, not automatic surgery. Options include enhanced breast screening, discussion of risk-reducing procedures and assessment of other gene-associated cancers; age, reproductive plans, previous cancer and local guidance determine the timing.

Many high-risk pathways use annual breast MRI beginning around ages 25–30, with mammography commonly added around age 30, but national recommendations differ. The reason for combining methods is that each detects some findings the other can miss; more imaging is not simply a substitute for understanding age-specific benefit and false-positive risk.
NICE guideline NG241 lists risk-reducing removal of ovaries and fallopian tubes no earlier than age 35 for BRCA1 and 40 for BRCA2, with individualized assessment (NICE, 2024). Common clinical discussions use windows of approximately 35–40 and 40–45 years, respectively, after childbearing; these are planning ranges, not instructions for every carrier.
Removing only the fallopian tubes while delaying ovary removal has not been established as equivalent protection and remains a trial-based strategy in NICE guidance. Surgical menopause can affect symptoms, cardiovascular health and bones; our ayollar gormonal salomatligi bo‘yicha qo‘llanma explains why prevention planning includes consequences beyond cancer risk.
Hormone treatment after premenopausal risk-reducing surgery may be considered until the usual menopause age, approximately 51, but previous breast cancer and other contraindications change that discussion. Bone-density assessment and evaluation of secondary bone-loss causes are distinct tasks; our guide to bone health laboratory assessment explains what routine tests can and cannot answer.
What does a BRCA result mean for relatives and children?
Each child of a germline BRCA pathogenic-variant carrier usually has a 50% chance of inheriting the variant, regardless of sex. Adult relatives can consider targeted testing for the established family finding; inheriting susceptibility does not mean inheriting an existing cancer.
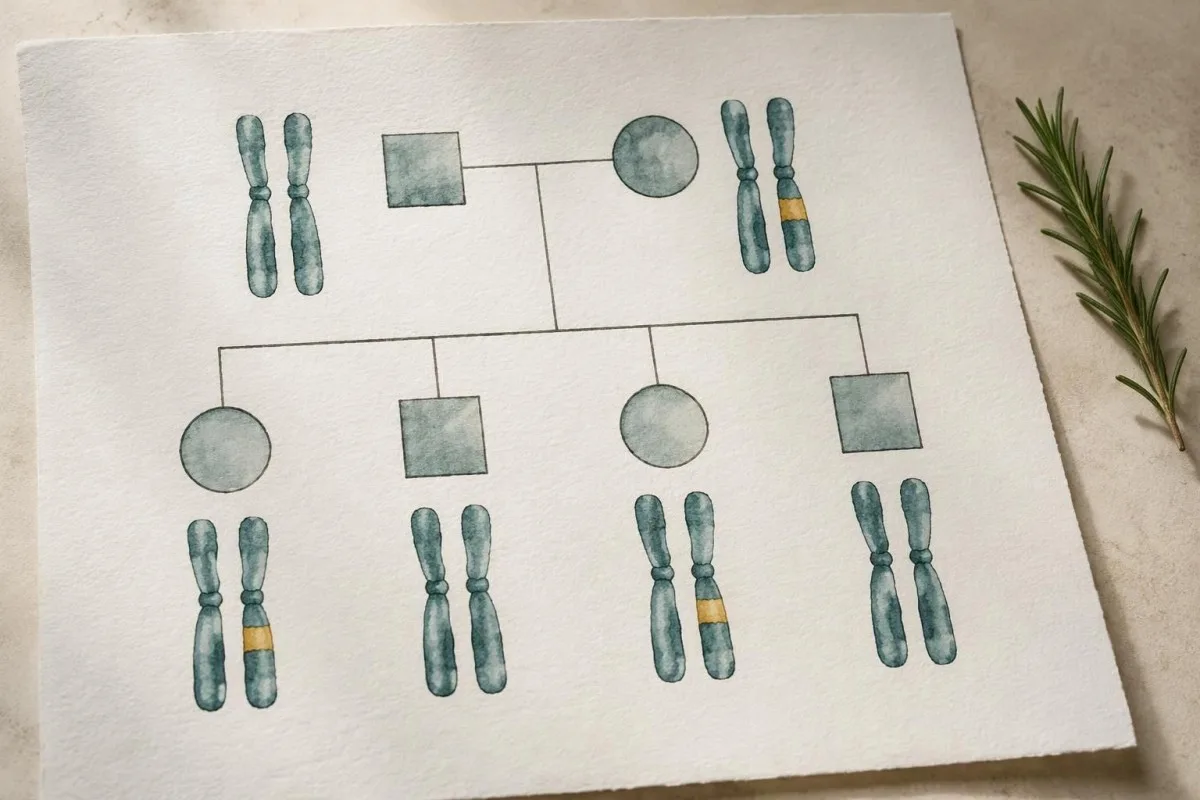
Four children do not imply that exactly 2 will inherit a parent’s BRCA variant. Each pregnancy is an independent event, so all, none or any number in between can inherit it; the 50% figure describes probability rather than a guaranteed family distribution.
A carrier’s siblings often have a 50% meros qilib olish ehtimoli of sharing the variant when a parent carries it, but that estimate should not be applied without checking the pedigree. Identifying which parent carries the finding helps determine which cousins, aunts and uncles should receive an invitation to discuss testing.
Reproductive options can include natural conception, prenatal diagnosis or IVF with preimplantation genetic testing for a known familial variant. These are preference-sensitive choices, not obligations; our explanation of reproductive genetic result counseling shows why gene-specific inheritance matters, although FMR1 repeat expansion behaves differently from BRCA inheritance.
A rare additional question arises when both partners carry pathogenic variants in BRCA2: each pregnancy has a 25% chance of inheriting pathogenic variants in both copies, which can cause a Fanconi anemia phenotype. Partner testing is not automatically required for every BRCA carrier, but ancestry, relatedness and reproductive planning can justify specialist assessment.
Can symptoms or tumor markers confirm BRCA-related cancer?
Neither a BRCA result nor a tumor-marker concentration confirms that cancer is present. New symptoms need their own assessment, and a negative genetic result does not make them harmless; examination, imaging and sometimes tissue assessment answer a different question from inherited susceptibility testing.

CA-125 can rise in benign conditions and can remain normal in ovarian cancer, particularly earlier disease. Routine CA-125 and ultrasound screening have not demonstrated a mortality benefit sufficient to replace established risk-reduction discussions; our guide to CA-125 limits and symptoms explains why the usual 35 U/mL cutoff is not a cancer yes-or-no boundary.
CA 15-3 and CA 27-29 are not appropriate tests for deciding whether an unaffected BRCA carrier has developed breast cancer. A hypothetical carrier with a normal marker still needs assessment of a new breast lump; our explanation of CA 15-3 interpretation separates selected monitoring uses from screening.
Kantesti does not infer BRCA carrier status from routine laboratory markers. For example, a CA 19-9 result of 80 U/mL can have non-cancer explanations and cannot establish pancreatic cancer or inherited BRCA2 risk; our guide to CA 19-9 limitations explains the need for clinical and imaging context.
Persistent bloating, early satiety, unexplained weight loss, a new breast change or unexplained jaundice deserve timely medical review regardless of genetic classification. A hypothetical person with 3 weeks of new persistent symptoms should not wait for VUS reclassification or a routine genetics appointment before seeking a separate assessment.
Use AI explanations without replacing genetic counseling
AI explanations can support understanding, but they cannot independently classify a BRCA variant or authorize preventive surgery. A safe workflow preserves 3 essentials: the original laboratory report, specialist interpretation and a written follow-up plan that distinguishes inherited risk from evaluation of any current symptoms.

Kantesti - bu AI biomarker talqin platformasi that explains routine laboratory findings, with interpretation generally available in about 60 seconds. That turnaround is not a timetable for genetic counseling, and our klinik metodologiya haqidagi ma’lumot should not be read as validation of independent BRCA classification or hereditary cancer risk calculation.
Genetic reports can reveal information relevant to more than kishiga, including biological relatives who have not chosen testing. Read our maxfiylik va ma’lumotlar bilan ishlash amaliyoti before sharing sensitive documents, and avoid uploading another relative’s identifiable report without their permission.
The 2 research publications listed below concern our global routine-test report and RDW educational material; they are not BRCA cancer-risk studies, clinical prevention guidelines or evidence supporting surgery. The medical recommendations in this article instead draw on the ACMG/AMP classification standards, the prospective JAMA risk study and NICE familial ovarian cancer guidance.
Before acting, ask your genetics team to document whether the result is germline, which exact variant is actionable and whether a negative is true or uninformative. Our mas’uliyatli sun’iy intellekt tamoyillarimiz support keeping those clinical decisions with qualified professionals rather than treating an automated explanation as another laboratory classification.
Tez-tez beriladigan savollar
BRCA1 yoki BRCA2 testining ijobiy natijasi menda saraton borligini anglatadimi?
Irsiy BRCA1 yoki BRCA2 testi ijobiy chiqishi patogen yoki ehtimol patogen irsiy variantni aniqlaydi; bu saraton tashxisi degani emas. Kuchenbaecker va boshqalarning JAMA jurnalida chop etilgan prospektiv tadqiqotida patogen variantlarni tashuvchi ayollarda 80 yoshgacha ko‘krak bezi saratoni xavfi BRCA1 uchun 72%, BRCA2 uchun esa 69% deb baholangan. Bu aholi guruhiga oid hisob-kitoblar bo‘lib, ayni paytda saraton borligi ehtimolini bildirmaydi. Hozirgi saratonni aniqlash uchun alohida klinik baholash zarur.
BRCA noaniq klinik ahamiyatga ega varianti bo‘lsa, profilaktik operatsiya qildirishim kerakmi?
Klinik ahamiyati noaniq BRCA varianti profilaktik operatsiya qarorini mustaqil ravishda belgilamasligi kerak. ACMG/AMP tizimi VUSni dalillarga asoslangan 5 ta tasnifdan biri sifatida ko‘rsatadi va noaniq variantlardan klinik qarorlar qabul qilishda foydalanmaslik kerakligini ta’kidlaydi. Shaxsiy yoki oilaviy anamnez yuqori xavfli yordamni alohida ravishda asoslab berishi mumkin, biroq bunday qarorda VUS patogen deb taxmin qilinmasligi kerak. Genetika bo‘yicha mutaxassis taklif etilgan muolajani aslida qaysi dalillar qo‘llab-quvvatlashini tushuntirib bera oladi.
Haqiqiy manfiy va ma’lumot bermaydigan manfiy BRCA natijasi o‘rtasidagi farq nima?
Haqiqiy manfiy natija biologik qarindoshda avval aniqlangan muayyan patogen yoki ehtimol patogen BRCA variantini inkor etadi. Variant tashuvchisining farzandi uchun bu oilada aniqlangan variantni meros qilib olishning dastlabki 50% ehtimolini aniqlashtirishi mumkin. Ma’lumot bermaydigan manfiy natijada esa oilada saraton kasalliklari nima sababdan yuzaga kelgani aniqlanmasdan, klinik jihatdan ahamiyatli variant topilmaydi. Har ikkala natijadan keyin ham oilaning boshqa tarmoqlari, qo‘shimcha genlar va test cheklovlari ahamiyatli bo‘lib qolishi mumkin.
BRCA VUS keyinchalik ijobiy natijaga o‘zgarishi mumkinmi?
BRCA VUS keyinchalik patogen yoki ehtimol patogen deb qayta tasniflanishi mumkin, ammo ehtimol benign yoki benign tomonga ham o‘zgarishi mumkin. Qayta tasniflash ayni 5 toifali tizim doirasidagi dalillarni ko‘rib chiqadi; bu odamning DNKsi o‘zgarganini anglatmaydi. Alohida variant uchun umumiy muddat yoki o‘zgarish yo‘nalishi kafolatlanmaydi. Yangilangan hisobotlar va qayta bog‘lanish qanday amalga oshirilishini dastlabki laboratoriya yoki genetika xizmatidan so‘rang.
BRCA variantini otamdan meros qilib olishim mumkinmi?
BRCA1 yoki BRCA2 dagi patogen variant biologik ota-onaning har ikkisidan ham meros bo‘lib o‘tishi mumkin. Germinal variant tashuvchisining har bir farzandida, tashuvchi ona yoki ota bo‘lishidan qat’i nazar, odatda bu variantni meros qilib olish ehtimoli 50% ga teng. Ayol qarindoshlari kam bo‘lgan ota tomondagi oilada variant mavjud bo‘lsa-da, ko‘krak bezi yoki tuxumdon saratoni bilan bog‘liq yaqqol oilaviy tarix bo‘lmasligi mumkin. Shu sababli, genetik maslahatda oilaning ota va ona tomonlari ham hisobga olinishi lozim.
O‘simtamda BRCA mutatsiyasi aniqlangani bolalarim xavf ostida ekanini anglatadimi?
O‘sma to‘qimasida BRCA mutatsiyasi aniqlanishi uning irsiy ekanini tasdiqlamaydi. Hatto o‘smadagi variant allelining ulushi 50% ga yaqin bo‘lsa ham, bu mutatsiyaning germinal kelib chiqishini ishonchli isbotlay olmaydi, chunki o‘sma to‘qimasining tozaligi va nusxa sonidagi o‘zgarishlar bu foizga ta’sir qiladi. Irsiy holatni aniqlash uchun tegishli namunadan foydalanib germinal test o‘tkazish kerak. Odatdagi 50% lik avlodga o‘tish ehtimoli faqat ota-onadan birida germinal variant mavjud bo‘lgandagina amal qiladi.
BRCA testi manfiy chiqqan bo‘lsa, uni har yili takrorlashim kerakmi?
Irsiy variant shunchaki yosh o‘tishi bilan paydo bo‘lmagani sababli, BRCA DNK testini har yili takrorlash odatda kerak bo‘lmaydi. Dastlabki tahlil cheklangan bo‘lsa, oilada yangi variant aniqlansa yoki boshqa qarindoshda tegishli saraton turi rivojlansa, manfiy natijani qayta ko‘rib chiqish maqsadga muvofiq bo‘lishi mumkin. Masalan, faqat tanlangan 3 ta variantni tekshirish BRCA1/BRCA2 genlarini to‘liq sekvenslash va deletsiya/duplikatsiya tahlili bilan teng emas. Natijalarni qayta talqin qilish, oilada muayyan variantni tekshirish yoki boshqa panel qo‘shimcha ma’lumot berishi mumkinmi, deb genetik xizmat mutaxassisidan so‘rang.
Qon tahlili natijalarini qanday o‘qish kerak
Laboratoriya hisobotingizni yuklang va Kantesti sun’iy intellekti har bir biomarkerni soniyalar ichida sodda tilda tushuntiradi. Dunyo bo‘ylab 2 milliondan ortiq kishi foydalanadi.
Adabiyotlar
- Klein, T., Mitchell, S., & Weber, H. (2026). AI qon tahlil analizatori: 2,5M ta test tahlil qilindi | Global Health Report 2026. Kantesti AI tibbiy tadqiqotlari. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW qon tahlili: RDW-CV, MCV va MCHC bo‘yicha to‘liq qo‘llanma. Kantesti AI tibbiy tadqiqotlari. DOI
- Richards S va boshq. (2015). Ketma-ketlik variantlarini talqin qilish bo‘yicha standartlar va ko‘rsatmalar: Amerika Tibbiy Genetika va Genomika kolleji hamda Molekulyar patologiya assotsiatsiyasining qo‘shma konsensus tavsiyasi. Tibbiyotdagi genetika. DOI PubMed
- Kuchenbaecker KB et al. (2017). Risks of Breast, Ovarian, and Contralateral Breast Cancer for BRCA1 and BRCA2 Mutation Carriers. JAMA. DOI PubMed
- National Institute for Health and Care Excellence (2024). Ovarian cancer: identifying and managing familial and genetic risk. NICE guideline NG241.
- 2M+Tahlil qilingan testlar
- 127+Mamlakatlar
- 100+Tillar
Tibbiy guruh haqida


E-E-A-T ishonch signallari
Tajriba
Shifokor boshchiligidagi laboratoriya talqin qilish ish jarayonlarini klinik ko‘rib chiqish.
Tajriba
Laboratoriya tibbiyoti biomarkerlarning klinik kontekstda qanday o‘zini tutishini yoritadi.
Vakolatlilik
Doktor Thomas Klein tomonidan tibbiy jihatdan ko‘rib chiqilgan, doktor Sarah Mitchell va professor doktor Hans Weber hissalari bilan.
Ishonchlilik
Xavotirni kamaytirish uchun aniq keyingi qadamlar yo‘nalishlari bilan dalillarga asoslangan talqin.






Tibbiy ogohlantirish
Ushbu maqola faqat ta’lim maqsadlari uchun mo‘ljallangan va tibbiy maslahatni anglatmaydi. Tashxis va davolash bo‘yicha qarorlar uchun har doim malakali sog‘liqni saqlash mutaxassisiga murojaat qiling.
Nashr etilgan · Tahririyat jamoasi bilan bog‘laning
Angliya va Uelsda ro‘yxatdan o‘tgan Kantesti Ltd tomonidan nashr etilgan, kompaniya raqami. 17090423, London, Birlashgan Qirollik.
