
Pinatataas ng pathogenic na variant sa BRCA1 o BRCA2 ang minamanang panganib sa kanser; hindi nito tinutukoy na may kanser. Hindi dapat maging batayan ng preventive surgery ang variant na hindi tiyak ang kahalagahan. Ang negatibong resulta ay tunay na negatibo lamang kung hindi kasama rito ang kilalang variant sa pamilya—kung hindi, maaaring hindi pa rin malinaw ang minamanang panganib.

Mahahalagang punto
- Positive result nangangahulugang natukoy ang pathogenic o malamang na pathogenic na variant; ang minamanang pagkamaramdamin ay hindi diagnosis ng kanser.
- Limang klasipikasyon ang naglalarawan sa mga genetic variant: pathogenic, malamang na pathogenic, hindi tiyak ang kahalagahan, malamang na benign at benign.
- Panganib sa BRCA1 sa isang prospective na pag-aaral sa JAMA ay umabot sa humigit-kumulang 72% para sa kanser sa suso at 44% para sa kanser sa obaryo pagsapit ng edad na 80 sa mga babaeng may pathogenic na variant.
- Panganib sa BRCA2 sa kaparehong pag-aaral ay umabot sa humigit-kumulang 69% para sa kanser sa suso at 17% para sa kanser sa obaryo pagsapit ng edad na 80; mga pagtatantiya ito para sa grupo, hindi mga prediksiyon para sa isang tao.
- Pamamahala sa VUS dapat sumunod sa personal at family history, hindi sa hindi tiyak na variant; hindi sapat na batayan ang VUS lamang para sa preventive surgery.
- Tunay na negatibo ay nangangahulugang hindi nakita ng laboratoryo ang partikular na pathogenic variant na dati nang natukoy sa iyong pamilya.
- Hindi nagbibigay-kaalamang negatibo ay nangangahulugang walang nakitang paliwanag sa pagsusuri para sa pinaghihinalaang minanang panganib; maaari pa ring magbigay-katwiran ang matibay na family history para sa karagdagang pagtatasa.
- Pagmamana sa pamilya karaniwang nagbibigay sa bawat anak ng isang carrier ng germline BRCA1 o BRCA2 pathogenic variant ng 50% posibilidad na mamana ang variant na iyon.
- Ang genetic counseling tumutulong na iugnay ang eksaktong variant, saklaw ng pagsusuri, magkabilang panig ng pamilya, at mga pagpipilian sa screening o pag-iwas na nakabatay sa edad.
Ano ba talaga ang ibig sabihin ng mga resulta ng genetic test para sa BRCA?
Mga resulta ng BRCA genetic test karaniwang nahahati sa 3 praktikal na grupo: positibo, hindi tiyak o negatibo. Tinutukoy ng minanang positibong resulta ang pagiging madaling kapitan sa kanser, samantalang ang isang variant na may hindi tiyak na kahulugan ay nananatiling hindi pa nalulutas, at kailangan ng negatibong resulta ang konteksto ng pamilya bago ito maituturing na nakapagpapaginhawa.

A germline BRCA test sumusuri sa DNA, karaniwan mula sa sample ng dugo o laway sa laboratoryo, sa halip na sukatin ang konsentrasyon ng protina. Hindi maaaring bigyang-kahulugan ang resulta nito gaya ng halagang nasa ng/mL: ang klinikal na kapaki-pakinabang na impormasyon ay ang gene, eksaktong variant, klasipikasyon at saklaw ng pagsusuri.
Karamihan sa mga tao ay may 2 kopya ng BRCA1 at 2 kopya ng BRCA2, kung saan minana ang isang kopya ng bawat isa mula sa bawat biyolohikal na magulang. Maaaring magpataas ng pagiging madaling kapitan sa kanser ang mapaminsalang pagbabago sa isang kopya, ngunit karaniwang nakaaambag sa pag-unlad ng kanser ang mga karagdagang pagbabago sa mga selula—hindi countdown sa sakit ang pagmamana.
Para sa isang hipotetikal na 38-taong-gulang na walang kanser, maaaring baguhin ng pathogenic BRCA2 result ang mga talakayan tungkol sa screening at pag-iwas sa hinaharap nang hindi nagpapatunay ng kasalukuyang diagnosis ng kanser. Para sa isang taong sumasailalim na sa paggamot sa kanser, maaari ring makaapekto ang gayunding minanang resulta sa pagiging kwalipikado sa paggamot at pagtatasa ng mga kanser sa hinaharap.
Si Kantesti ay isang AI blood test analyzer para sa karaniwang interpretasyon sa laboratoryo, hindi pamalit sa klinikal na genetics laboratoryo. Impormasyon tungkol sa aming organisasyon ay tumutulong na maiba ang aming papel sa edukasyon sa espesyalisadong gawaing kailangan para bigyang-kahulugan ang minanang resulta ng kanser.
Aling mga detalye sa ulat ng laboratoryo para sa BRCA ang mahalaga?
Ang pinakamahahalagang detalye sa ulat ng BRCA ay ang gene, eksaktong variant, klasipikasyon, uri ng specimen at paraan ng pagsusuri. Karaniwang gumagamit ang mga klinikal na laboratoryo ng 5 klasipikasyon ng variant, at hindi sinasabi ng salitang “variant” lamang kung mapaminsala ang isang natuklasan.

Pinaghihiwalay ng balangkas ng ACMG/AMP ang pathogenic, likely pathogenic, hindi tiyak ang kahalagahan, likely benign at benign na mga natuklasan (Richards et al., 2015). Karaniwang sinusuportahan ng pathogenic at likely pathogenic na mga variant ang iisang landas ng klinikal na pangangasiwa; inilalarawan ng pagkakaiba ang antas ng kumpiyansa sa ebidensiya, hindi ang dalawang magkaibang porsiyento ng panganib sa kanser.
Maaaring magsimula sa isang pagbabago sa antas ng DNA ang mga paglalarawan ng variant na nagsisimula sa c. and a protein-level consequence beginning with p. These are coordinates, not severity scores; two reports may describe the same change differently because they use different transcripts or historical naming conventions.
Look for both sequence analysis at deletion/duplication analysis when evaluating a comprehensive BRCA1/BRCA2 test. Reading individual DNA changes and detecting missing or extra gene segments require complementary methods, so a report stating “sequencing negative” may not answer every relevant question.
A hypothetical report can contain 2 findings: a pathogenic BRCA1 variant and an unrelated BRCA2 VUS. Management follows the established pathogenic finding, not an average of the two classifications; our guide to categorical versus numerical results explains why laboratory result types require different reading strategies.
Kahulugan ng positibong BRCA1: pagkamaramdamin, hindi katiyakan
BRCA1 positive meaning depends on the classification: a germline pathogenic or likely pathogenic BRCA1 variant indicates inherited cancer susceptibility. In a prospective study, women carrying pathogenic BRCA1 variants had an estimated 72% breast cancer risk and 44% ovarian cancer risk by age 80.
Kuchenbaecker et al. reported those age-80 estimates in JAMA, with 95% confidence intervals of 65–79% for breast cancer at 36–53% for ovarian cancer (2017). The intervals describe uncertainty around population estimates; they do not mean an individual’s risk can be read directly from the laboratory report.
A hypothetical 30-year-old BRCA1 carrier should not interpret a 72% age-80 estimate as a 72% risk this year. Personal counseling separates near-term risk from longer-term risk and considers age, prior cancer, relatives’ diagnoses and any preventive procedures already completed.
BRCA1-associated breast cancers are more often triple-negative than breast cancers in the general population, but receptor status cannot be predicted from an inherited result alone. An existing cancer still requires its own pathological and receptor assessment; a genetic finding does not replace those separate tests.
One family can also have more than one inherited explanation for cancer, particularly when diagnoses cluster on both parental branches. For example, several colorectal and endometrial cancers may justify a separate assessment of Lynch syndrome results rather than assuming a BRCA1 finding explains every diagnosis.
Paano naiiba ang panganib sa kanser dahil sa mutation ng BRCA2?
BRCA2 mutation cancer risk includes breast and ovarian cancer susceptibility, with particular relevance to male breast, prostate and pancreatic cancer assessment. In the same prospective JAMA study, women carrying pathogenic BRCA2 variants had estimated risks of 69% for breast cancer and 17% for ovarian cancer by age 80.
The BRCA2 estimates had 95% confidence intervals of 61–77% for breast cancer at 11–25% for ovarian cancer (Kuchenbaecker et al., 2017). BRCA2’s lower average ovarian cancer risk compared with BRCA1 helps explain why preventive ovary-and-tube removal is commonly discussed later for BRCA2 carriers.
A previous breast cancer creates a different risk question: the chance of another cancer in the opposite breast. Kuchenbaecker et al. estimated 20-year contralateral breast cancer risks of 26% for BRCA2 and 40% for BRCA1; those figures are not the same as first-cancer risk and should not be substituted for it.
Prostate screening discussions may begin around age 40 in men with pathogenic BRCA2 variants, depending on the applicable clinical pathway. PSA is a screening measurement rather than a symptom generator; our explanation of what elevated PSA means separates the laboratory number from a diagnosis.
Pancreatic surveillance is another area where eligibility criteria differ, including the importance assigned to family history. A hypothetical 52-year-old BRCA2 carrier with an affected first-degree relative needs a specialist discussion about MRI-based imaging or endoscopic ultrasound—not routine CA 19-9 testing as a substitute.
Ano ang ibig sabihin ng variant na hindi tiyak ang kahalagahan sa BRCA?
A BRCA variant of uncertain significance, or VUS, means available evidence cannot establish whether a DNA change increases cancer risk. A VUS is not a positive result, and it should not independently determine preventive mastectomy or removal of the ovaries and fallopian tubes.

The ACMG/AMP standards state that a VUS ay hindi dapat gamitin sa klinikal na pagpapasya (Richards et al., 2015). Among the 5 classification categories, uncertainty is an evidence status—not a diagnosis, not a halfway-positive result and not a 50% probability that the variant causes cancer.
For example, a hypothetical 42-year-old with a BRCA1 VUS and no significant family history should not be offered risk-reducing surgery because of that VUS alone. Another 42-year-old with the same VUS and a substantial family history may qualify for intensified surveillance because of the history, not because the uncertain variant became actionable.
Ancestry can affect how often laboratories encounter uncertainty because population databases do not represent every group equally. Two people with the same cancer history can therefore receive different levels of interpretive certainty; this reflects evidence gaps and does not establish a biological difference in the seriousness of their results.
At Kantesti, we separate finding a genetic change from proving that the change warrants action. The same distinction helps readers understand common MTHFR variant findings, although MTHFR results and BRCA-associated cancer susceptibility have very different clinical implications.
Maaari bang magbago kalaunan ang klasipikasyon ng BRCA VUS?
A BRCA VUS can be reclassified when new evidence clarifies its clinical significance. Many reclassified VUS move toward benign categories, but neither the direction nor the timing can be promised for an individual finding; reinterpretation usually reviews existing DNA data rather than requiring another sample.

Useful new evidence can come from 3 broad sources: population frequency, carefully validated functional work and observations of the variant in families. A computer prediction alone is usually insufficient; expert curation weighs whether the evidence actually addresses the disease mechanism and meets classification standards.
Laboratories can disagree because their evidence differs or their interpretations were issued at different times. Record 2 separate dates when available—the original report date and the most recent classification date—and ask whether a specialist expert-panel assessment exists, rather than counting database entries as votes.
Routine testing of unaffected relatives for a VUS usually does not guide care, although a genetics team may arrange selected family studies to help classification. A hypothetical family with 3 affected relatives should not independently order VUS testing for everyone and interpret who carries it as proof of causation.
Ask which laboratory manages reinterpretation, how amended reports reach you and whether your contact details remain current; there is no universal recontact interval. Our discussion of inherited TTR variant interpretation illustrates the broader need to connect exact genetic findings with disease-specific evidence.
Kailan tunay na negatibo ang negatibong resulta ng BRCA?
A true negative BRCA result means testing did not find the specific pathogenic or likely pathogenic variant already identified in a biological relative. It removes the inherited risk attributable to that familial variant, but it does not eliminate ordinary cancer risk or unrelated risks from the other family branch.

Suppose a hypothetical mother has a confirmed pathogenic BRCA1 variant and her adult daughter’s targeted test excludes that exact variant. Before testing, the daughter generally had a 50% posibilidad ng pagmamana; afterward, she is not considered a carrier of that maternal finding and cannot pass that uncarried variant to her children.
A negative result becomes less definitive if nobody knows the affected relative’s exact finding. Bring a copy of the original family report rather than a verbal account of “BRCA positive”; a gene name alone cannot distinguish a pathogenic variant from a VUS or identify which change the laboratory should test.
An independently concerning paternal history can remain relevant despite a maternal true negative. For example, 2 close paternal relatives with early breast cancer may warrant separate risk assessment, because excluding one maternal variant does not explain another branch of the pedigree.
The logic of matching a relative’s exact finding also appears in family-based Alport genetic testing, although the genes and inheritance patterns differ. Ask for a written statement identifying which familial variant was excluded and what remaining screening recommendation follows from your own history.
Bakit maaaring hindi nagbibigay ng tiyak na impormasyon ang negatibong resulta ng BRCA?
Isang negatibong resultang hindi nagbibigay ng impormasyon means no actionable BRCA finding was detected, but testing has not explained a suspicious personal or family cancer history. The result may reflect another gene, a technical limitation or a familial risk pattern that cannot currently be assigned to one detectable variant.

Testing an affected relative first usually provides more information than testing an unaffected relative. A hypothetical unaffected 35-year-old’s negative panel does not prove that her mother’s ovarian cancer lacked an inherited cause; testing the mother, when possible, can establish whether there is a familial finding to exclude.
A broader panel may consider genes such as PALB2, ATM, CHEK2, RAD51C, RAD51D and BRIP1, depending on the cancer pattern. These genes do not share identical cancer risks or prevention recommendations, so “panel positive” still requires gene-specific interpretation rather than applying the BRCA pathway to every result.
Older tests or limited consumer tests may assess only selected variants, whereas comprehensive clinical testing can include sequencing and deletion/duplication analysis. Our explanation of hidden carrier-screening limitations illustrates why a reassuring-looking result can still depend on methodology, although SMA uses a different genetic model.
Kantesti AI does not establish the completeness of a genetic assay or certify that a family’s inherited risk has been excluded. If a hypothetical family has 3 related cancers despite negative testing, clinical genetics can decide whether updated testing, another affected relative or a formal family-history risk model would answer the unresolved question.
Ibig bang sabihin ng nakita sa BRCA sa tumor na namana ito?
A BRCA variant found in tumor tissue is not automatically inherited. Tumor testing can detect acquired changes confined to cancer cells; germline testing examines a suitable non-tumor specimen to determine whether the finding is constitutional and relevant to relatives.

A tumor report may show a variant allele fraction near 50%, but that number does not prove germline origin. Tumor purity, copy-number changes and loss of the other gene copy can all shift the fraction; a percentage on a tumor report cannot replace a properly selected germline test.
Some oncology reports describe homologous recombination deficiency, or HRD, rather than a specific inherited variant. HRD can arise through more than one mechanism, and an HRD-positive result does not establish that a person or their children carry a pathogenic BRCA1 or BRCA2 variant.
After an allogeneic stem-cell transplant, a blood-derived DNA sample may reflect the donor, and saliva can also contain donor-derived cells. A hypothetical transplant recipient therefore needs the genetics laboratory to select an appropriate specimen—sometimes cultured skin fibroblasts—rather than assuming that 2 easily obtained samples answer the inheritance question.
The distinction between acquired and inherited DNA changes also matters in UBA1-related VEXAS testing, although VEXAS is a different condition. For a tumor BRCA finding, ask whether germline confirmation has been completed, is pending or was never requested.
Kailan pinakamalaking tulong ang genetic counseling?
Genetic counseling helps before testing and whenever a result could change screening, treatment or family testing. It is especially useful for pathogenic findings, unresolved VUS, limited negative tests and family patterns involving young diagnoses, ovarian cancer, male breast cancer or multiple related cancers.

A practical pedigree usually covers 3 henerasyon and records cancer type, age at diagnosis, biological relationships and both maternal and paternal branches. “Abdominal cancer” is less useful than a confirmed primary site; ovarian, pancreatic and metastatic cancers can otherwise be misremembered as the same diagnosis.
Small families, early deaths and few female relatives can hide hereditary breast-and-ovarian cancer patterns. A hypothetical father with 2 sons and no sisters can carry and transmit a BRCA variant even when the family has no obvious breast cancer cluster; paternal inheritance deserves the same attention as maternal inheritance.
Si Kantesti ay isang AI blood test interpretation platform, not a genetic counseling service. Our guidance on age-appropriate family testing separates routine laboratory needs from predictive BRCA testing, which is generally deferred in children under 18 because management usually begins in adulthood.
Before an appointment, gather the actual family report, pathology details if available and your previous test methods. Use separate consent for each relative’s records; our discussion of family health consent explains why a shared family history does not give one person automatic permission to access everyone’s medical information.
Anong follow-up ang ginagawa matapos ang pathogenic na resulta ng BRCA?
A germline pathogenic BRCA result warrants a personalized prevention plan, not automatic surgery. Options include enhanced breast screening, discussion of risk-reducing procedures and assessment of other gene-associated cancers; age, reproductive plans, previous cancer and local guidance determine the timing.

Many high-risk pathways use annual breast MRI beginning around ages 25–30, with mammography commonly added around age 30, but national recommendations differ. The reason for combining methods is that each detects some findings the other can miss; more imaging is not simply a substitute for understanding age-specific benefit and false-positive risk.
NICE guideline NG241 lists risk-reducing removal of ovaries and fallopian tubes no earlier than age 35 for BRCA1 and 40 for BRCA2, with individualized assessment (NICE, 2024). Common clinical discussions use windows of approximately 35–40 and 40–45 years, respectively, after childbearing; these are planning ranges, not instructions for every carrier.
Removing only the fallopian tubes while delaying ovary removal has not been established as equivalent protection and remains a trial-based strategy in NICE guidance. Surgical menopause can affect symptoms, cardiovascular health and bones; our gabay sa hormonal na kalusugan ng kababaihan explains why prevention planning includes consequences beyond cancer risk.
Hormone treatment after premenopausal risk-reducing surgery may be considered until the usual menopause age, approximately 51, but previous breast cancer and other contraindications change that discussion. Bone-density assessment and evaluation of secondary bone-loss causes are distinct tasks; our guide to bone health laboratory assessment explains what routine tests can and cannot answer.
Ano ang ibig sabihin ng resulta ng BRCA para sa mga kamag-anak at anak?
Each child of a germline BRCA pathogenic-variant carrier usually has a 50% chance of inheriting the variant, regardless of sex. Adult relatives can consider targeted testing for the established family finding; inheriting susceptibility does not mean inheriting an existing cancer.
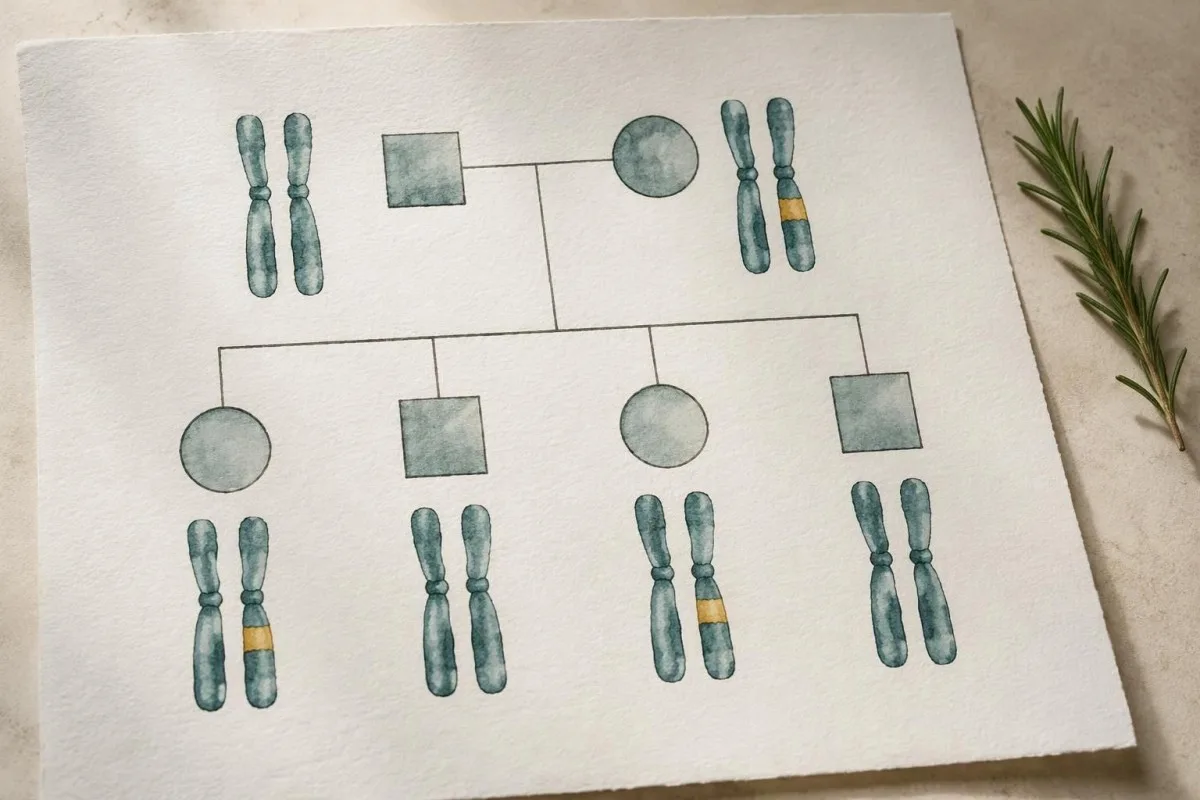
Four children do not imply that exactly 2 will inherit a parent’s BRCA variant. Each pregnancy is an independent event, so all, none or any number in between can inherit it; the 50% figure describes probability rather than a guaranteed family distribution.
A carrier’s siblings often have a 50% na posibilidad of sharing the variant when a parent carries it, but that estimate should not be applied without checking the pedigree. Identifying which parent carries the finding helps determine which cousins, aunts and uncles should receive an invitation to discuss testing.
Reproductive options can include natural conception, prenatal diagnosis or IVF with preimplantation genetic testing for a known familial variant. These are preference-sensitive choices, not obligations; our explanation of reproductive genetic result counseling shows why gene-specific inheritance matters, although FMR1 repeat expansion behaves differently from BRCA inheritance.
A rare additional question arises when both partners carry pathogenic variants in BRCA2: each pregnancy has a 25% chance of inheriting pathogenic variants in both copies, which can cause a Fanconi anemia phenotype. Partner testing is not automatically required for every BRCA carrier, but ancestry, relatedness and reproductive planning can justify specialist assessment.
Maaari bang kumpirmahin ng mga sintomas o tumor marker ang kanser na may kaugnayan sa BRCA?
Neither a BRCA result nor a tumor-marker concentration confirms that cancer is present. New symptoms need their own assessment, and a negative genetic result does not make them harmless; examination, imaging and sometimes tissue assessment answer a different question from inherited susceptibility testing.

CA-125 can rise in benign conditions and can remain normal in ovarian cancer, particularly earlier disease. Routine CA-125 and ultrasound screening have not demonstrated a mortality benefit sufficient to replace established risk-reduction discussions; our guide to CA-125 limits and symptoms explains why the usual 35 U/mL cutoff is not a cancer yes-or-no boundary.
CA 15-3 and CA 27-29 are not appropriate tests for deciding whether an unaffected BRCA carrier has developed breast cancer. A hypothetical carrier with a normal marker still needs assessment of a new breast lump; our explanation of CA 15-3 interpretation separates selected monitoring uses from screening.
Kantesti does not infer BRCA carrier status from routine laboratory markers. For example, a CA 19-9 result of 80 U/mL can have non-cancer explanations and cannot establish pancreatic cancer or inherited BRCA2 risk; our guide to CA 19-9 limitations explains the need for clinical and imaging context.
Persistent bloating, early satiety, unexplained weight loss, a new breast change or unexplained jaundice deserve timely medical review regardless of genetic classification. A hypothetical person with 3 weeks of new persistent symptoms should not wait for VUS reclassification or a routine genetics appointment before seeking a separate assessment.
Gumamit ng mga paliwanag ng AI nang hindi ipinapalit ang mga ito sa genetic counseling
AI explanations can support understanding, but they cannot independently classify a BRCA variant or authorize preventive surgery. A safe workflow preserves 3 essentials: the original laboratory report, specialist interpretation and a written follow-up plan that distinguishes inherited risk from evaluation of any current symptoms.

Si Kantesti ay isang platform ng interpretasyon ng biomarker ng AI that explains routine laboratory findings, with interpretation generally available in about 60 seconds. That turnaround is not a timetable for genetic counseling, and our impormasyon tungkol sa klinikal na pamamaraan should not be read as validation of independent BRCA classification or hereditary cancer risk calculation.
Genetic reports can reveal information relevant to more than 1 tao, including biological relatives who have not chosen testing. Read our mga patakaran sa privacy at paggamit ng datos before sharing sensitive documents, and avoid uploading another relative’s identifiable report without their permission.
The 2 research publications listed below concern our global routine-test report and RDW educational material; they are not BRCA cancer-risk studies, clinical prevention guidelines or evidence supporting surgery. The medical recommendations in this article instead draw on the ACMG/AMP classification standards, the prospective JAMA risk study and NICE familial ovarian cancer guidance.
Before acting, ask your genetics team to document whether the result is germline, which exact variant is actionable and whether a negative is true or uninformative. Our mga prinsipyo ng responsableng AI support keeping those clinical decisions with qualified professionals rather than treating an automated explanation as another laboratory classification.
Mga Madalas Itanong
Nangangahulugan ba na may kanser ako ang positibong resulta ng pagsusuri sa BRCA1 o BRCA2?
Tinutukoy ng positibong pagsusuri sa germline na BRCA1 o BRCA2 ang isang namamanang variant na pathogenic o malamang na pathogenic; hindi ito nagdidiyagnos ng kanser. Sa prospective na pag-aaral nina Kuchenbaecker et al. sa JAMA, ang tinatayang panganib ng kanser sa suso pagsapit ng edad na 80 ay 72% para sa BRCA1 at 69% para sa BRCA2 sa mga babaeng may pathogenic na variant. Mga pagtataya ito para sa populasyon, hindi ang posibilidad na may kanser sa kasalukuyan. Nangangailangan ng hiwalay na klinikal na pagsusuri upang matukoy kung may kasalukuyang kanser.
Dapat ba akong magpaopera bilang pag-iwas kung mayroon akong BRCA variant of uncertain significance?
Hindi dapat mag-isa ang BRCA variant of uncertain significance ang magpasya kung isasagawa ang preventive surgery. Inilalagay ng balangkas ng ACMG/AMP ang VUS sa limang klasipikasyong nakabatay sa ebidensiya at nagsasaad na hindi dapat gamitin ang mga hindi tiyak na variant sa pagpapasya sa klinikal na pangangalaga. Maaaring maging batayan nang hiwalay ang personal o pampamilyang kasaysayan para sa pangangalagang angkop sa mas mataas na panganib, ngunit hindi dapat ipagpalagay sa pagpapasyang iyon na pathogenic ang VUS. Maaaring ipaliwanag ng isang propesyonal sa genetics kung aling ebidensiya ang tunay na sumusuporta sa anumang iminumungkahing pamamaraan.
Ano ang pagkakaiba ng tunay na negatibong resulta ng BRCA at ng negatibong resultang walang sapat na impormasyon?
Inaalis ng tunay na negatibo ang partikular na pathogenic o likely pathogenic na BRCA variant na natukoy na sa isang biyolohikal na kamag-anak. Para sa anak ng isang carrier, maaari nitong malinawan ang paunang 50% posibilidad na mamana ang variant na iyon sa pamilya. Walang natutukoy na actionable variant ang isang hindi nagbibigay-kaalamang negatibong resulta, nang hindi naitatatag kung bakit nagkaroon ng mga kanser sa pamilya. Maaari pa ring maging mahalaga ang iba pang sangay ng pamilya, mga karagdagang gene at mga limitasyon ng pagsusuri pagkatapos ng alinman sa mga resultang ito.
Maaari bang maging positibo sa kalaunan ang isang BRCA VUS?
Maaaring mauri muli sa kalaunan ang BRCA VUS bilang pathogenic o malamang na pathogenic, ngunit maaari rin itong mauri bilang malamang na benign o benign. Sinusuri sa muling pag-uuri ang ebidensiya gamit ang parehong balangkas na may 5 kategorya; hindi ito nangangahulugang nagbago ang DNA ng tao. Walang pangkalahatang takdang panahon o garantisadong direksiyon para sa isang partikular na variant. Itanong sa orihinal na laboratoryo o serbisyong genetika kung paano nila pinangangasiwaan ang mga binagong ulat at muling pakikipag-ugnayan.
Maaari ba akong magmana ng baryanteng BRCA mula sa aking ama?
Maaaring mamana ang isang pathogenic na variant ng BRCA1 o BRCA2 mula sa alinman sa biyolohikal na magulang. Karaniwang may 50% posibilidad na mamana ng bawat anak ng isang germline carrier ang variant na iyon, maging ina o ama man ang carrier. Maaaring kakaunti ang nakikitang kasaysayan ng kanser sa suso o obaryo sa isang pamilyang mula sa panig ng ama na kakaunti ang mga babaeng kamag-anak, kahit may dala silang variant. Kaya dapat isaalang-alang sa pagpapayo sa genetika ang magkabilang panig ng pamilya.
Nangangahulugan ba na nanganganib ang mga anak ko kung may natagpuang BRCA mutation sa tumor ko?
Hindi pinatutunayan ng mutasyon ng BRCA na natagpuan sa tisyu ng tumor na namamana ito. Kahit malapit sa 50% ang proporsyon ng variant allele sa tumor, hindi nito mapatutunayang nagmula ito sa germline, dahil naaapektuhan ng kadalisayan ng tumor at mga pagbabago sa bilang ng kopya ang porsiyentong iyon. Kailangan ang pagsusuri sa germline gamit ang angkop na specimen upang matukoy kung namamana ito. Nalalapat lamang ang karaniwang 50% na posibilidad ng pagpasa kapag may germline variant ang magulang.
Kailangan ko bang ulitin taun-taon ang negatibong pagsusuri sa BRCA?
Karaniwang hindi kinakailangan ang taunang pag-uulit ng BRCA DNA testing dahil hindi basta lumilitaw habang tumatanda ang isang namamanang variant. Maaaring kailanganing muling suriin ang negatibong resulta kung limitado ang orihinal na pagsusuri, may matukoy na bagong variant sa pamilya, o magkaroon ng kaugnay na kanser ang isa pang kamag-anak. Halimbawa, hindi katumbas ng komprehensibong sequencing ng BRCA1/BRCA2 kasama ang pagsusuri para sa deletion/duplication ang pagsusuri sa 3 piling variant lamang. Magtanong sa serbisyong panggenetika kung may maidaragdag na impormasyon ang muling interpretasyon, naka-target na pagsusuri sa pamilya o ibang panel.
Ipaliwanag sa iyo ang resulta ng blood test
I-upload ang iyong ulat sa laboratoryo at ipapaliwanag ng AI ng Kantesti ang bawat biomarker sa payak na pananalita sa loob ng ilang segundo. Ginagamit ng mahigit 2 milyong tao sa buong mundo.
Mga Sanggunian
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2.5M Tests Analyzed | Global Health Report 2026. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Pagsusuri ng RDW sa Dugo: Kumpletong Gabay sa RDW-CV, MCV at MCHC. Kantesti AI Medical Research. DOI
- Richards S et al. (2015). Mga pamantayan at alituntunin para sa interpretasyon ng mga baryante ng sequence: magkasanib na rekomendasyon ng pinagkasunduan ng American College of Medical Genetics and Genomics at Association for Molecular Pathology. Genetics in Medicine. DOI PubMed
- Kuchenbaecker KB et al. (2017). Risks of Breast, Ovarian, and Contralateral Breast Cancer for BRCA1 and BRCA2 Mutation Carriers. JAMA. DOI PubMed
- National Institute for Health and Care Excellence (2024). Ovarian cancer: identifying and managing familial and genetic risk. NICE guideline NG241.
- 2M+Mga sinuring pagsusuri
- 127+Mga bansa
- 100+Mga wika
Tungkol sa pangkat medikal


Mga Signal ng Tiwala ng E-E-A-T
Karanasan
Pinamumunuan ng manggagamot na klinikal na pagsusuri ng mga daloy ng interpretasyon ng mga pagsusuri sa laboratoryo.
Kadalubhasaan
Pokus sa laboratoryong medisina kung paano kumikilos ang mga biomarker sa kontekstong klinikal.
Pagka-awtoridad
Sinuri sa medikal na aspeto ni Dr. Thomas Klein, kasama ang mga kontribusyon nina Dr. Sarah Mitchell at Prof. Dr. Hans Weber.
Pagiging Mapagkakatiwalaan
Interpretasyong nakabatay sa ebidensya na may malinaw na mga susunod na hakbang upang mabawasan ang pag-aalarma.






Paunawang medikal
Ang artikulong ito ay para sa mga layuning pang-edukasyon lamang at hindi ito bumubuo ng medikal na payo. Palaging kumonsulta sa isang kwalipikadong tagapagbigay ng pangangalagang pangkalusugan para sa mga desisyon sa diagnosis at paggamot.
Inilathala · Makipag-ugnayan sa pangkat ng editoryal
Inilathala ng Kantesti Ltd, nakarehistro sa England at Wales, numero ng kumpanya. 17090423, London, United Kingdom.
