
A pathogenic BRCA1 or BRCA2 variant increases inherited cancer risk; it does not diagnose cancer. A variant of uncertain significance should not drive preventive surgery. A negative result is a true negative only when it excludes a known familial variant—otherwise, it may leave inherited risk unresolved.

مهم ټکي
- مثبتې پایله means a pathogenic or likely pathogenic variant was identified; inherited susceptibility is not a cancer diagnosis.
- Five classifications describe genetic variants: pathogenic, likely pathogenic, uncertain significance, likely benign and benign.
- BRCA1 risk in a prospective JAMA study reached approximately 72% for breast cancer and 44% for ovarian cancer by age 80 in women carrying pathogenic variants.
- BRCA2 risk in the same study reached approximately 69% for breast cancer and 17% for ovarian cancer by age 80; these are group estimates, not personal predictions.
- VUS management should follow personal and family history, not the uncertain variant; a VUS alone does not justify preventive surgery.
- ریښتیا منفي means the laboratory did not find the specific pathogenic variant already established in your family.
- Uninformative negative means testing found no explanation for suspected inherited risk; strong family history can still justify additional assessment.
- د کورنۍ له لارې ارثي لېږد usually gives each child of a germline BRCA1 or BRCA2 pathogenic-variant carrier a 50% chance of inheriting that variant.
- جینیټیک مشورې helps connect the exact variant, test coverage, both sides of the family and age-dependent screening or prevention choices.
What do BRCA genetic test results actually mean?
BRCA genetic test results usually fall into 3 practical groups: positive, uncertain or negative. A positive inherited result identifies cancer susceptibility, a د نامعلوم اهمیت تغیر remains unresolved, and a negative result needs family context before it can be called reassuring.

A germline BRCA test examines DNA, usually from a laboratory blood or saliva sample, rather than measuring a protein concentration. Its result cannot be interpreted like a value in ng/mL: the clinically useful information is the gene, exact variant, classification and scope of testing.
ډېری خلک 2 copies of BRCA1 and 2 copies of BRCA2, with one copy of each inherited from each biological parent. A harmful change in one copy can increase cancer susceptibility, but additional cellular changes generally contribute to cancer development—inheritance is not a countdown to disease.
For a hypothetical 38-year-old without cancer, a pathogenic BRCA2 result can change future screening and prevention discussions without establishing any current cancer diagnosis. For someone already receiving cancer treatment, the same inherited finding may also affect treatment eligibility and assessment of future cancers.
کانټیسټي یو دی د AI د وینې معاینې شنونکی for routine laboratory interpretation, not a substitute for a clinical genetics laboratory. Information about زموږ سازمان کې helps distinguish our educational role from the specialist work required to interpret an inherited cancer result.
Which details on a BRCA laboratory report matter?
The most useful details on a BRCA report are the gene, exact variant, classification, specimen type and testing method. Clinical laboratories commonly use 5 variant classifications, and the word “variant” alone does not tell you whether a finding is harmful.

The ACMG/AMP framework separates pathogenic, likely pathogenic, uncertain significance, likely benign and benign findings (Richards et al., 2015). Pathogenic and likely pathogenic variants generally support the same clinical management pathway; the distinction describes confidence in the evidence, not two different percentages of cancer risk.
Variant descriptions can include a DNA-level change beginning with c. and a protein-level consequence beginning with p. These are coordinates, not severity scores; two reports may describe the same change differently because they use different transcripts or historical naming conventions.
Look for both sequence analysis او deletion/duplication analysis when evaluating a comprehensive BRCA1/BRCA2 test. Reading individual DNA changes and detecting missing or extra gene segments require complementary methods, so a report stating “sequencing negative” may not answer every relevant question.
A hypothetical report can contain 2 findings: a pathogenic BRCA1 variant and an unrelated BRCA2 VUS. Management follows the established pathogenic finding, not an average of the two classifications; our guide to categorical versus numerical results explains why laboratory result types require different reading strategies.
BRCA1 positive meaning: susceptibility, not certainty
BRCA1 positive meaning depends on the classification: a germline pathogenic or likely pathogenic BRCA1 variant indicates inherited cancer susceptibility. In a prospective study, women carrying pathogenic BRCA1 variants had an estimated 72% breast cancer risk and 44% ovarian cancer risk by age 80.
Kuchenbaecker et al. reported those age-80 estimates in JAMA, with 95% confidence intervals of 65–79% for breast cancer او 36–53% for ovarian cancer (2017). The intervals describe uncertainty around population estimates; they do not mean an individual’s risk can be read directly from the laboratory report.
A hypothetical 30-year-old BRCA1 carrier should not interpret a 72% age-80 estimate as a 72% risk this year. Personal counseling separates near-term risk from longer-term risk and considers age, prior cancer, relatives’ diagnoses and any preventive procedures already completed.
BRCA1-associated breast cancers are more often triple-negative than breast cancers in the general population, but receptor status cannot be predicted from an inherited result alone. An existing cancer still requires its own pathological and receptor assessment; a genetic finding does not replace those separate tests.
One family can also have more than one inherited explanation for cancer, particularly when diagnoses cluster on both parental branches. For example, several colorectal and endometrial cancers may justify a separate assessment of Lynch syndrome results rather than assuming a BRCA1 finding explains every diagnosis.
How does BRCA2 mutation cancer risk differ?
BRCA2 mutation cancer risk includes breast and ovarian cancer susceptibility, with particular relevance to male breast, prostate and pancreatic cancer assessment. In the same prospective JAMA study, women carrying pathogenic BRCA2 variants had estimated risks of 69% for breast cancer and 17% for ovarian cancer by age 80.
The BRCA2 estimates had 95% confidence intervals of 61–77% for breast cancer او 11–25% for ovarian cancer (Kuchenbaecker et al., 2017). BRCA2’s lower average ovarian cancer risk compared with BRCA1 helps explain why preventive ovary-and-tube removal is commonly discussed later for BRCA2 carriers.
A previous breast cancer creates a different risk question: the chance of another cancer in the opposite breast. Kuchenbaecker et al. estimated 20-year contralateral breast cancer risks of 26% for BRCA2 and 40% for BRCA1; those figures are not the same as first-cancer risk and should not be substituted for it.
Prostate screening discussions may begin around age 40 in men with pathogenic BRCA2 variants, depending on the applicable clinical pathway. PSA is a screening measurement rather than a symptom generator; our explanation of what elevated PSA means separates the laboratory number from a diagnosis.
Pancreatic surveillance is another area where eligibility criteria differ, including the importance assigned to family history. A hypothetical 52-year-old BRCA2 carrier with an affected first-degree relative needs a specialist discussion about MRI-based imaging or endoscopic ultrasound—not routine CA 19-9 testing as a substitute.
What does a BRCA variant of uncertain significance mean?
A BRCA variant of uncertain significance, or VUS, means available evidence cannot establish whether a DNA change increases cancer risk. A VUS is not a positive result, and it should not independently determine preventive mastectomy or removal of the ovaries and fallopian tubes.

The ACMG/AMP standards state that a VUS باید په کلینیکي پرېکړهنیونه کې د (Richards et al., 2015). Among the 5 classification categories, uncertainty is an evidence status—not a diagnosis, not a halfway-positive result and not a 50% probability that the variant causes cancer.
For example, a hypothetical 42-year-old with a BRCA1 VUS and no significant family history should not be offered risk-reducing surgery because of that VUS alone. Another 42-year-old with the same VUS and a substantial family history may qualify for intensified surveillance because of the history, not because the uncertain variant became actionable.
Ancestry can affect how often laboratories encounter uncertainty because population databases do not represent every group equally. Two people with the same cancer history can therefore receive different levels of interpretive certainty; this reflects evidence gaps and does not establish a biological difference in the seriousness of their results.
At Kantesti, we separate finding a genetic change from proving that the change warrants action. The same distinction helps readers understand common MTHFR variant findings, although MTHFR results and BRCA-associated cancer susceptibility have very different clinical implications.
Can a BRCA VUS change classification later?
A BRCA VUS can be reclassified when new evidence clarifies its clinical significance. Many reclassified VUS move toward benign categories, but neither the direction nor the timing can be promised for an individual finding; reinterpretation usually reviews existing DNA data rather than requiring another sample.

Useful new evidence can come from 3 broad sources: population frequency, carefully validated functional work and observations of the variant in families. A computer prediction alone is usually insufficient; expert curation weighs whether the evidence actually addresses the disease mechanism and meets classification standards.
Laboratories can disagree because their evidence differs or their interpretations were issued at different times. Record 2 separate dates when available—the original report date and the most recent classification date—and ask whether a specialist expert-panel assessment exists, rather than counting database entries as votes.
Routine testing of unaffected relatives for a VUS usually does not guide care, although a genetics team may arrange selected family studies to help classification. A hypothetical family with 3 affected relatives should not independently order VUS testing for everyone and interpret who carries it as proof of causation.
Ask which laboratory manages reinterpretation, how amended reports reach you and whether your contact details remain current; there is no universal recontact interval. Our discussion of inherited TTR variant interpretation illustrates the broader need to connect exact genetic findings with disease-specific evidence.
When is a negative BRCA result a true negative?
A true negative BRCA result means testing did not find the specific pathogenic or likely pathogenic variant already identified in a biological relative. It removes the inherited risk attributable to that familial variant, but it does not eliminate ordinary cancer risk or unrelated risks from the other family branch.

Suppose a hypothetical mother has a confirmed pathogenic BRCA1 variant and her adult daughter’s targeted test excludes that exact variant. Before testing, the daughter generally had a 50% د وراثت احتمال; afterward, she is not considered a carrier of that maternal finding and cannot pass that uncarried variant to her children.
A negative result becomes less definitive if nobody knows the affected relative’s exact finding. Bring a copy of the original family report rather than a verbal account of “BRCA positive”; a gene name alone cannot distinguish a pathogenic variant from a VUS or identify which change the laboratory should test.
An independently concerning paternal history can remain relevant despite a maternal true negative. For example, 2 close paternal relatives with early breast cancer may warrant separate risk assessment, because excluding one maternal variant does not explain another branch of the pedigree.
The logic of matching a relative’s exact finding also appears in family-based Alport genetic testing, although the genes and inheritance patterns differ. Ask for a written statement identifying which familial variant was excluded and what remaining screening recommendation follows from your own history.
Why can a negative BRCA result be uninformative?
یو ناخبرهکوونکی منفي means no actionable BRCA finding was detected, but testing has not explained a suspicious personal or family cancer history. The result may reflect another gene, a technical limitation or a familial risk pattern that cannot currently be assigned to one detectable variant.

Testing an affected relative first usually provides more information than testing an unaffected relative. A hypothetical unaffected 35-year-old’s negative panel does not prove that her mother’s ovarian cancer lacked an inherited cause; testing the mother, when possible, can establish whether there is a familial finding to exclude.
A broader panel may consider genes such as PALB2, ATM, CHEK2, RAD51C, RAD51D and BRIP1, depending on the cancer pattern. These genes do not share identical cancer risks or prevention recommendations, so “panel positive” still requires gene-specific interpretation rather than applying the BRCA pathway to every result.
Older tests or limited consumer tests may assess only selected variants, whereas comprehensive clinical testing can include sequencing and deletion/duplication analysis. Our explanation of hidden carrier-screening limitations illustrates why a reassuring-looking result can still depend on methodology, although SMA uses a different genetic model.
Kantesti AI does not establish the completeness of a genetic assay or certify that a family’s inherited risk has been excluded. If a hypothetical family has 3 related cancers despite negative testing, clinical genetics can decide whether updated testing, another affected relative or a formal family-history risk model would answer the unresolved question.
Does a BRCA finding in a tumor mean it is inherited?
A BRCA variant found in tumor tissue is not automatically inherited. Tumor testing can detect acquired changes confined to cancer cells; germline testing examines a suitable non-tumor specimen to determine whether the finding is constitutional and relevant to relatives.

A tumor report may show a variant allele fraction near 50%, but that number does not prove germline origin. Tumor purity, copy-number changes and loss of the other gene copy can all shift the fraction; a percentage on a tumor report cannot replace a properly selected germline test.
Some oncology reports describe homologous recombination deficiency, or HRD, rather than a specific inherited variant. HRD can arise through more than one mechanism, and an HRD-positive result does not establish that a person or their children carry a pathogenic BRCA1 or BRCA2 variant.
After an allogeneic stem-cell transplant, a blood-derived DNA sample may reflect the donor, and saliva can also contain donor-derived cells. A hypothetical transplant recipient therefore needs the genetics laboratory to select an appropriate specimen—sometimes cultured skin fibroblasts—rather than assuming that 2 easily obtained samples answer the inheritance question.
The distinction between acquired and inherited DNA changes also matters in UBA1-related VEXAS testing, although VEXAS is a different condition. For a tumor BRCA finding, ask whether germline confirmation has been completed, is pending or was never requested.
When does genetic counseling help most?
Genetic counseling helps before testing and whenever a result could change screening, treatment or family testing. It is especially useful for pathogenic findings, unresolved VUS, limited negative tests and family patterns involving young diagnoses, ovarian cancer, male breast cancer or multiple related cancers.

A practical pedigree usually covers ۳ نسلونو and records cancer type, age at diagnosis, biological relationships and both maternal and paternal branches. “Abdominal cancer” is less useful than a confirmed primary site; ovarian, pancreatic and metastatic cancers can otherwise be misremembered as the same diagnosis.
Small families, early deaths and few female relatives can hide hereditary breast-and-ovarian cancer patterns. A hypothetical father with 2 sons and no sisters can carry and transmit a BRCA variant even when the family has no obvious breast cancer cluster; paternal inheritance deserves the same attention as maternal inheritance.
کانټیسټي یو دی AI د وینې ازموینې تشریح پلیټفارم, not a genetic counseling service. Our guidance on age-appropriate family testing separates routine laboratory needs from predictive BRCA testing, which is generally deferred in children under 18 because management usually begins in adulthood.
Before an appointment, gather the actual family report, pathology details if available and your previous test methods. Use separate consent for each relative’s records; our discussion of family health consent explains why a shared family history does not give one person automatic permission to access everyone’s medical information.
What follow-up follows a pathogenic BRCA result?
A germline pathogenic BRCA result warrants a personalized prevention plan, not automatic surgery. Options include enhanced breast screening, discussion of risk-reducing procedures and assessment of other gene-associated cancers; age, reproductive plans, previous cancer and local guidance determine the timing.

Many high-risk pathways use annual breast MRI beginning around ages 25–30, with mammography commonly added around age 30, but national recommendations differ. The reason for combining methods is that each detects some findings the other can miss; more imaging is not simply a substitute for understanding age-specific benefit and false-positive risk.
NICE guideline NG241 lists risk-reducing removal of ovaries and fallopian tubes no earlier than age 35 for BRCA1 and 40 for BRCA2, with individualized assessment (NICE, 2024). Common clinical discussions use windows of approximately 35–40 and 40–45 years, respectively, after childbearing; these are planning ranges, not instructions for every carrier.
Removing only the fallopian tubes while delaying ovary removal has not been established as equivalent protection and remains a trial-based strategy in NICE guidance. Surgical menopause can affect symptoms, cardiovascular health and bones; our د ښځو د هورموني روغتیا لارښود (women’s hormonal health guide) په کارولو سره پراخې بیاکتنې ته اړتیا ولري. explains why prevention planning includes consequences beyond cancer risk.
Hormone treatment after premenopausal risk-reducing surgery may be considered until the usual menopause age, approximately 51, but previous breast cancer and other contraindications change that discussion. Bone-density assessment and evaluation of secondary bone-loss causes are distinct tasks; our guide to bone health laboratory assessment explains what routine tests can and cannot answer.
What does a BRCA result mean for relatives and children?
Each child of a germline BRCA pathogenic-variant carrier usually has a 50% chance of inheriting the variant, regardless of sex. Adult relatives can consider targeted testing for the established family finding; inheriting susceptibility does not mean inheriting an existing cancer.
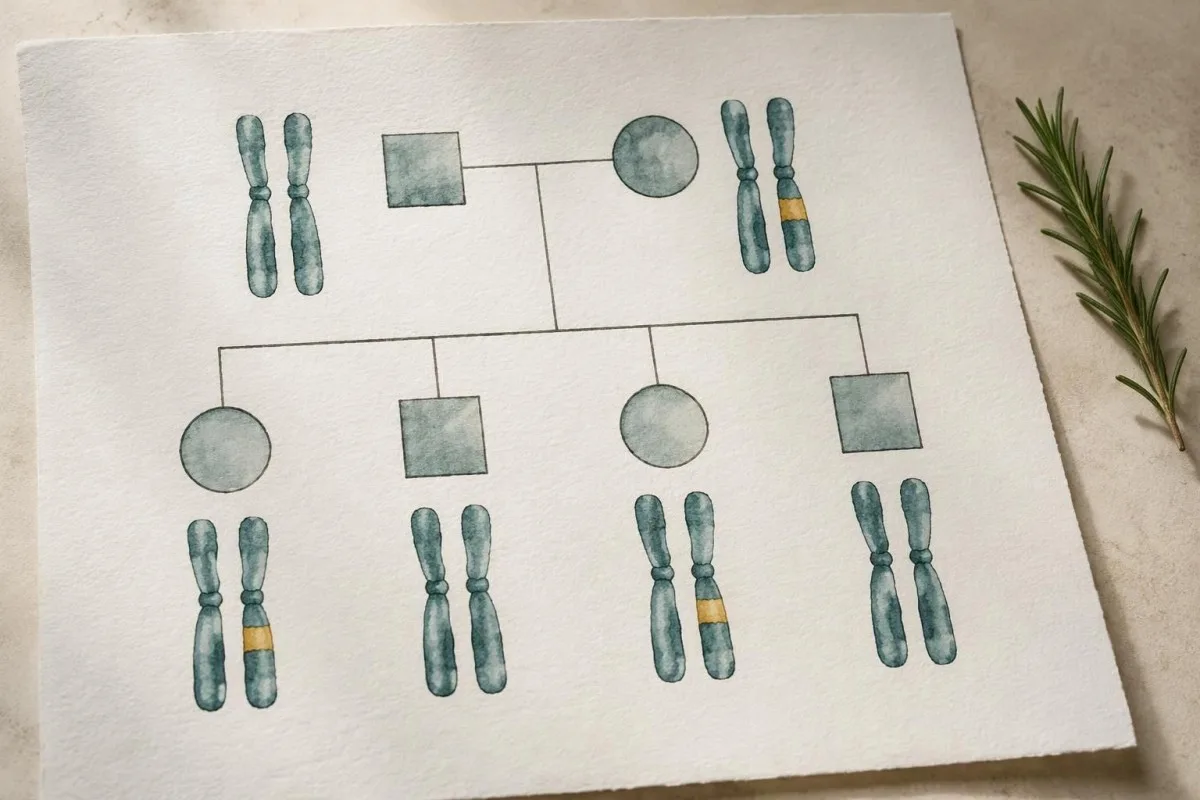
Four children do not imply that exactly 2 will inherit a parent’s BRCA variant. Each pregnancy is an independent event, so all, none or any number in between can inherit it; the 50% figure describes probability rather than a guaranteed family distribution.
A carrier’s siblings often have a 50% د میراثي ورته LDL-لوړونکي تغیر چانس of sharing the variant when a parent carries it, but that estimate should not be applied without checking the pedigree. Identifying which parent carries the finding helps determine which cousins, aunts and uncles should receive an invitation to discuss testing.
Reproductive options can include natural conception, prenatal diagnosis or IVF with preimplantation genetic testing for a known familial variant. These are preference-sensitive choices, not obligations; our explanation of reproductive genetic result counseling shows why gene-specific inheritance matters, although FMR1 repeat expansion behaves differently from BRCA inheritance.
A rare additional question arises when both partners carry pathogenic variants in BRCA2: each pregnancy has a 25% chance of inheriting pathogenic variants in both copies, which can cause a Fanconi anemia phenotype. Partner testing is not automatically required for every BRCA carrier, but ancestry, relatedness and reproductive planning can justify specialist assessment.
Can symptoms or tumor markers confirm BRCA-related cancer?
Neither a BRCA result nor a tumor-marker concentration confirms that cancer is present. New symptoms need their own assessment, and a negative genetic result does not make them harmless; examination, imaging and sometimes tissue assessment answer a different question from inherited susceptibility testing.

CA-125 can rise in benign conditions and can remain normal in ovarian cancer, particularly earlier disease. Routine CA-125 and ultrasound screening have not demonstrated a mortality benefit sufficient to replace established risk-reduction discussions; our guide to CA-125 limits and symptoms explains why the usual 35 U/mL cutoff is not a cancer yes-or-no boundary.
CA 15-3 and CA 27-29 are not appropriate tests for deciding whether an unaffected BRCA carrier has developed breast cancer. A hypothetical carrier with a normal marker still needs assessment of a new breast lump; our explanation of CA 15-3 interpretation separates selected monitoring uses from screening.
Kantesti does not infer BRCA carrier status from routine laboratory markers. For example, a CA 19-9 result of 80 U/mL can have non-cancer explanations and cannot establish pancreatic cancer or inherited BRCA2 risk; our guide to CA 19-9 limitations explains the need for clinical and imaging context.
Persistent bloating, early satiety, unexplained weight loss, a new breast change or unexplained jaundice deserve timely medical review regardless of genetic classification. A hypothetical person with 3 weeks of new persistent symptoms should not wait for VUS reclassification or a routine genetics appointment before seeking a separate assessment.
Use AI explanations without replacing genetic counseling
AI explanations can support understanding, but they cannot independently classify a BRCA variant or authorize preventive surgery. A safe workflow preserves 3 essentials: the original laboratory report, specialist interpretation and a written follow-up plan that distinguishes inherited risk from evaluation of any current symptoms.

کانټیسټي یو دی د AI بایومارکر تفسیر پلیټفارم that explains routine laboratory findings, with interpretation generally available in about 60 seconds. That turnaround is not a timetable for genetic counseling, and our د کلینیکي مېتودولوژۍ معلومات should not be read as validation of independent BRCA classification or hereditary cancer risk calculation.
Genetic reports can reveal information relevant to more than 1 کس, including biological relatives who have not chosen testing. Read our د محرمیت او معلوماتو کړنلارې before sharing sensitive documents, and avoid uploading another relative’s identifiable report without their permission.
The 2 research publications listed below concern our global routine-test report and RDW educational material; they are not BRCA cancer-risk studies, clinical prevention guidelines or evidence supporting surgery. The medical recommendations in this article instead draw on the ACMG/AMP classification standards, the prospective JAMA risk study and NICE familial ovarian cancer guidance.
Before acting, ask your genetics team to document whether the result is germline, which exact variant is actionable and whether a negative is true or uninformative. Our د مصنوعي ځیرکتیا مسؤلانه اصول support keeping those clinical decisions with qualified professionals rather than treating an automated explanation as another laboratory classification.
پرله پسې پوښتل شوي پوښتنې
ایا د BRCA1 یا BRCA2 مثبت ټېسټ دا معنا لري چې زه سرطان لرم؟
د BRCA1 یا BRCA2 د ارثي جنیټیکي ازموینې مثبته پایله یوه ناروغيزېږوونکې یا په احتمالي ډول ناروغيزېږوونکې ارثي بڼه په ګوته کوي؛ خو د سرطان تشخیص نه کوي. په JAMA کې د Kuchenbaecker او همکارانو په راتلونکيپوهاندې څېړنه کې، د ناروغيزېږوونکو بڼو لرونکو ښځو لپاره تر ۸۰ کلنۍ پورې د سینې د سرطان اټکل شوی خطر د BRCA1 لپاره 72% او د BRCA2 لپاره ۶۹٪ و. دا د ټول نفوس اټکلونه دي، نه دا احتمال چې سرطان همدا اوس موجود وي. د اوسني سرطان تشخیص لپاره جلا کلینیکي ارزونې ته اړتیا ده.
ایا زه باید د BRCA د نامعلوم اهمیت د ډول لپاره مخنیوی کوونکې جراحي وکړم؟
د BRCA هغه ډول چې د اهمیت له پلوه نامعلوم وي، باید په خپلواک ډول د مخنیوي جراحي پرېکړه ونه ټاکي. د ACMG/AMP چوکاټ، VUS د شواهدو پر بنسټ د پنځو ډلبندیو له ډلې ګڼي او څرګندوي چې د نامعلومو ډولونو پر بنسټ باید په کلینیکي پرېکړو کې عمل ونه شي. شخصي یا کورنۍ مخینه جلا توګه د لوړ خطر پاملرنې توجیه کولی شي، خو دا پرېکړه باید داسې ونه انګیري چې VUS ناروغيزېږوونکی دی. د جنیټیک متخصص کولای شي تشریح کړي چې کوم شواهد د وړاندیز شوې هرې کړنلارې ملاتړ کوي.
د ریښتینې منفي او د BRCA د غیرمعلوماتي منفي پایلې ترمنځ څه توپیر دی؟
ریښتینې منفي پایله هغه ځانګړی ناروغيرامنځتهکوونکی یا په احتمالي ډول ناروغيرامنځتهکوونکی BRCA ډول له منځه وړي چې مخکې په بیولوژیکي خپلوان کې تثبیت شوی وي. د یوه ناقل د ماشوم لپاره، دا د کورنۍ د موندنې له مخې د وراثت لومړنی ۵۰٪ احتمال روښانه کولای شي. په غیرمعلوماتي منفي پایله کې هېڅ د اقدام وړ ډول نه موندل کېږي، خو دا نه روښانوي چې په کورنۍ کې سرطانونه ولې رامنځته شوي دي. د کورنۍ نورې څانګې، اضافي جینونه او د ازموینې محدودیتونه له دواړو پایلو وروسته هم اړوند پاتې کېدای شي.
ایا د BRCA نامعلوم اهمیت لرونکی ډول وروسته مثبت کېدای شي؟
د BRCA VUS بیا وروسته د ناروغۍپارونکي یا احتمالي ناروغۍپارونکي په توګه بیا طبقهبندي کېدای شي، خو کېدای شي احتمالي بېضرره یا بېضرره هم وبلل شي. په بیا طبقهبندۍ کې شواهد د هماغه ۵ کټګوریو په چوکاټ کې ارزول کېږي؛ دا په دې معنا نه ده چې د شخص DNA بدل شوی دی. د هرې ځانګړې جنیټیکي بڼې لپاره کومه نړیواله وروستۍ نېټه یا تضمین شوی لوری نشته. له اصلي لابراتوار یا د جنیټیک خدمتونو له څانګې وپوښتئ چې اصلاح شوي راپورونه او د بیا اړیکې نیول څنګه سمبالوي.
ایا زه د BRCA جینیټیکي بڼه له خپل پلار څخه په میراث اخیستلی شم؟
د BRCA1 یا BRCA2 ناروغيزېږنده بڼه له هر یوه بیولوژیکي والد څخه په میراث اخیستل کېدای شي. د جرثومي کرښې د بڼې د لرونکي هر ماشوم عموماً 50% چانس لري چې دغه بڼه په میراث واخلي، که د بڼې لرونکی مور وي او که پلار. په پلرني اړخ کې د ښځینه خپلوانو د لږوالي له امله، ښايي د سینې یا تخمدان د سرطان ډېرې څرګندې کورنۍ مخینې نه وي، سره له دې چې یوه بڼه موجوده وي. له همدې امله، جنیټیکي مشوره باید د کورنۍ دواړه څانګې په پام کې ونیسي.
ایا زما په تومور کې د BRCA بدلون موندل دا معنا لري چې زما ماشومان له خطر سره مخ دي؟
په توموري نسج کې د BRCA بدلون موندل دا نه ثابتوي چې په میراث کې لېږدول شوی دی. ان د تومور د ویرینټ د الیل سلنه چې نږدې ۵۰٪ وي، د جرثومي کرښې سرچینه په باوري ډول نه شي ثابتولای، ځکه د تومور پاکوالی او د کاپي شمېر بدلونونه پر دې سلنه اغېز کوي. د میراثي حالت د ثابتولو لپاره د مناسبې نمونې په کارولو سره د جرثومي کرښې ازموینې ته اړتیا ده. د لېږد معمول ۵۰٪ احتمال یوازې هغه وخت تطبیقېږي چې مور یا پلار د جرثومي کرښې ویرینټ ولري.
ایا اړتیا لرم چې د BRCA منفي ازموینه هر کال تکرار کړم؟
د BRCA د DNA کلنۍ تکراري ازموینې ته عموماً اړتیا نشته، ځکه چې ارثي بدلون یوازې د عمر په زیاتېدو نه راڅرګندېږي. که لومړنۍ ازموینه محدوده وه، په کورنۍ کې نوی بدلون وموندل شي، یا بل خپلوان په اړوند سرطان اخته شي، نو د منفي پایلې بیاکتنه ښايي اړینه وي. د بېلګې په توګه، یوازې د ۳ ټاکل شویو بدلونونو ازموینه د BRCA1/BRCA2 له هر اړخیز ترتیبموندنې او د حذف/تکرار له تحلیل سره برابره نه ده. د جنیټیک له خدمت څخه وپوښتئ چې ایا د پایلو بیا تفسیر، د کورنۍ هدفمنه ازموینه یا د ازموینو بله مجموعه به نور معلومات درکړي.
د وینې ازموینې پایلې څنګه ولولئ
خپل لابراتواري راپور پورته کړئ، او د Kantesti AI به په څو ثانیو کې هر بایومارکر په ساده ژبه تشریح کړي. په ټوله نړۍ کې له 2 میلیونو څخه زیاتو کسانو ترې کار اخیستی.
ماخذونه
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د AI وینې د ازموینې شنونکی: 2.5M ازموینې تحلیل شوې | د نړیوال روغتیا راپور 2026. د Kantesti AI طبي څېړنه. د دفاع وزارت
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د RDW د وینې ازموینه: د RDW-CV، MCV او MCHC بشپړ لارښود. د Kantesti AI طبي څېړنه. د دفاع وزارت
- ریچارډز او نور (2015). د تسلسلي بڼو د تفسیر معیارونه او لارښوونې: د طبي جنیټیک او جینومیک د امریکایي کالج او د مالیکولي پتالوژۍ د ټولنې ګډه توافقلیک سپارښتنه. په طب کې جنیټیک. د دفاع وزارت پب میډ
- Kuchenbaecker KB et al. (2017). Risks of Breast, Ovarian, and Contralateral Breast Cancer for BRCA1 and BRCA2 Mutation Carriers. JAMA. د دفاع وزارت پب میډ
- National Institute for Health and Care Excellence (2024). Ovarian cancer: identifying and managing familial and genetic risk. NICE guideline NG241.
- ۲ میلیونه+تحلیل شوې ازموینې
- 127+هېوادونه
- 100+ژبې
د طبي ټیم په اړه


د E-E-A-T باور نښې
تجربه
د ډاکټر تر مشرۍ لاندې کلینیکي بیاکتنه د لابراتواري تفسیر د کاري بهیرونو لپاره.
تخصص
د لابراتواري طب تمرکز پر دې چې بایومارکرونه په کلینیکي شرایطو کې څنګه چلند کوي.
واک ورکول
د ډاکټر توماس کلاین له خوا طبي بیاکتنه شوې، د ډاکټر سارا میچل او پروفیسور ډاکټر هانس وېبر په مرسته.
اعتبار
د شواهدو پر بنسټ تفسیر د روښانه تعقیبي لارو چارو سره، تر څو اندیښنه کمه شي.






طبي سلبِ مسئولیت
دا مقاله یوازې د زده کړې لپاره ده او طبي مشوره نه جوړوي. د تشخیص او درملنې د پرېکړو لپاره تل د وړ روغتیايي خدمت وړاندې کوونکي سره سلا وکړئ.
خپور شوی · له تحریري ټیم سره اړیکه ونیسئ
خپروونکی یې Kantesti Ltd دی، چې په انګلستان او وېلز کې ثبت شوی، د شرکت شمېره. 17090423, ، لندن، بریتانیا.
