
Kết quả xét nghiệm kháng thể Schistosoma dương tính có thể là căn cứ để điều trị sau khi có phơi nhiễm nước ngọt đáng tin cậy nếu bạn chưa từng được điều trị đầy đủ, nhưng kết quả này không thể chứng minh đang nhiễm bệnh hoặc xác nhận đã khỏi bệnh. Thời điểm phơi nhiễm, tiền sử điều trị và các xét nghiệm bổ sung sẽ quyết định bước tiếp theo.

Những điểm chính cần ghi nhớ
- Kháng thể dương tính cho biết có đáp ứng miễn dịch với kháng nguyên Schistosoma; 1 kết quả dương tính không thể phân biệt nhiễm chưa điều trị với nhiễm đã được điều trị trước đó.
- Cửa sổ xét nghiệm có ý nghĩa: CDC khuyến nghị lấy mẫu xét nghiệm kháng thể ít nhất 6–8 tuần sau khi nghi ngờ nhiễm mới.
- Phơi nhiễm nước ngọt nghĩa là da tiếp xúc với hồ, sông hoặc kênh rạch có khả năng bị ô nhiễm—không đơn thuần là đến thăm một quốc gia có dịch.
- Soi kính hiển vi cho nhiều thông tin hơn khi bác sĩ yêu cầu lấy 3 mẫu phân hoặc nước tiểu vào những ngày khác nhau.
- Praziquantel liều dùng thường có tổng cộng 40 mg/kg trong 1 ngày đối với S. mansoni và S. haematobium, nhưng việc kê đơn phụ thuộc vào loài và tình trạng lâm sàng.
- Thời điểm điều trị thường có nghĩa là chờ ít nhất 6–8 tuần sau lần phơi nhiễm nước ngọt gần nhất ở những người đi du lịch có tình trạng sức khỏe ổn định, vì praziquantel có hiệu quả tốt nhất đối với giun trưởng thành.
- Soi kính hiển vi theo dõi có thể được yêu cầu 1–2 tháng sau điều trị khi trước điều trị có trứng.
- IgG tồn tại dai dẳng có thể vẫn dương tính trong nhiều năm sau khi điều trị thành công; một kết quả dương tính khác không tự động là lý do để điều trị thêm một đợt.
Kết quả xét nghiệm kháng thể Schistosoma dương tính có cần điều trị không?
Kết quả kháng thể Schistosoma dương tính không tự động có nghĩa là bạn cần điều trị. Các bác sĩ thường khuyến nghị điều trị khi có căn cứ xác đáng về việc tiếp xúc với nước ngọt và chưa có liệu pháp trước đó phù hợp, ngay cả khi soi kính hiển vi cho kết quả âm tính; sau khi đã ghi nhận điều trị và không tái phơi nhiễm, 1 kết quả dương tính dai dẳng thường không đủ để biện minh cho việc điều trị lại.

Ý nghĩa của kết quả Schistosoma IgG dương tính được hiểu chính xác nhất là bằng chứng về sự nhận diện của hệ miễn dịch, chứ không phải phép đo giun còn sống. Đáp ứng kháng thể có thể tồn tại lâu hơn ký sinh trùng nhiều năm, và 2 người có cùng kết quả được báo cáo vẫn có thể cần chăm sóc khác nhau—một người sau khi phơi nhiễm chưa được điều trị, người kia sau khi điều trị thành công và không tiếp xúc với nước ngọt sau đó.
Phơi nhiễm trước đây và điều trị trước đây là hai vấn đề riêng biệt: nhiễm trùng cũ có thể chưa được điều trị, trong khi kết quả xét nghiệm dương tính cũ có thể vẫn tồn tại sau khi khỏi bệnh. Trước khi diễn giải 1 báo cáo là bệnh đang hoạt động hay tiền sử vô hại, hãy kiểm tra tên thuốc điều trị, liều dùng, ngày điều trị và mọi lần tiếp xúc với nước sau đó; phần giải thích của chúng tôi về kết quả kháng thể dương tính phân biệt các loại bằng chứng khác nhau này.
Kantesti là công cụ phân tích xét nghiệm máu AI giúp giải thích vì sao 1 kết quả Schistosoma IgG dương tính không thể xác định tình trạng nhiễm trùng đang hoạt động, ngay cả khi xét nghiệm công thức máu bình thường. Vai trò của chúng tôi là giải thích báo cáo—không phải nhận diện ký sinh trùng hay kê đơn—và và mục đích của chúng tôi của chúng tôi cần được hiểu tách biệt với các quyết định do bác sĩ lâm sàng đưa ra như mô tả ở đây.
Những trường hợp phơi nhiễm nước ngọt nào khiến kết quả đáng tin cậy hơn?
Tiếp xúc da với nước ngọt trong khu vực có lây truyền khiến kết quả dương tính có ý nghĩa lâm sàng hơn. Bơi lội, lội nước, tắm, chèo bè hoặc giặt giũ ở hồ, sông và kênh tưới tiêu đều có thể gây phơi nhiễm; hãy ghi lại 3 chi tiết cho mỗi lần: địa điểm chính xác, hoạt động và ngày tiếp xúc gần nhất.

Ấu trùng Schistosoma do ốc nước ngọt phóng thích xâm nhập qua da; không cần phải nuốt nước. Một lần lội nước ngắn vẫn được tính là phơi nhiễm, và không có ban ngứa cũng không loại trừ khả năng đó, vì vậy một du khách giả định từng xuống hồ trong 5 phút nên khai báo sự việc đó thay vì chỉ ghi lại những lần bơi lâu hơn.
Nước biển và bể bơi được khử trùng bằng clo đúng cách không phải là nguồn phơi nhiễm điển hình gây bệnh sán máng. Tiếp xúc với nước ngọt cũng có thể làm dấy lên lo ngại về các bệnh khác cần xét nghiệm và điều trị khác, bao gồm bệnh leptospirosis sau khi tiếp xúc với nước; không nên quy kết sốt khởi phát 1 tuần sau một hoạt động trên sông là do kháng thể Schistosoma nếu chưa đánh giá toàn diện hơn.
Chỉ dựa vào tên một quốc gia không thể xác định nguy cơ của từng cá nhân vì tình hình lây truyền khác nhau giữa các khu vực và nguồn nước trong cùng một quốc gia. Hãy nhớ lại dù chỉ 1 hoạt động đã quên—chẳng hạn như rửa thiết bị bên bờ sông—và phân biệt phơi nhiễm ký sinh trùng với hồ sơ tiêm chủng; xét nghiệm kháng thể khi đi du lịch giải đáp một vấn đề khác và không bảo vệ khỏi bệnh sán máng.
Nên xét nghiệm bệnh sán máng sau chuyến đi khi nào?
Xét nghiệm kháng thể bệnh sán máng thường có nhiều thông tin hơn khi thực hiện ít nhất 6–8 tuần sau lần nhiễm mới nghi ngờ. Hướng dẫn Xét nghiệm lâm sàng và Chẩn đoán bệnh sán máng của CDC giải thích rằng khoảng thời gian này cho phép kháng thể hình thành; kết quả âm tính được lấy sớm hơn không thể loại trừ đáng tin cậy tình trạng nhiễm trùng mới mắc do tiếp xúc với nước ngọt.

The last freshwater contact is a practical anchor when a trip involved several possible exposures. For example, a hypothetical traveler who swam on both the first and final day of a 3-week holiday should calculate the testing interval from the final swim, rather than assuming that the first exposure makes an immediate post-trip result conclusive.
Seroconversion is not identical across people or assays, so 6–8 weeks is a useful testing window rather than a guarantee of detection. When exposure is persuasive and an initial result is negative, a clinician may arrange another sample later, sometimes around 12 weeks after exposure; a second date should be agreed rather than inferred from a generic laboratory reference range.
Fever or significant symptoms after travel should be assessed without waiting for an antibody window to close, especially after a malaria-risk itinerary. At Kantesti, we encourage readers to keep 2 dates visible—last freshwater contact and sample collection—because thời điểm xét nghiệm nhiễm trùng can change the meaning of a negative report even though each organism requires its own diagnostic strategy.
Kháng thể Schistosoma có thể cho kết quả dương tính giả không?
Schistosoma antibody tests can produce false-positive or cross-reactive results, and their performance varies by assay. There is no universal IgG concentration or index that proves active schistosomiasis; 2 laboratories may use different antigen preparations, reporting units and thresholds, making direct numerical comparisons unreliable.

Cross-reactivity with other helminth antibodies depends on the test rather than occurring uniformly in every person. A laboratory may recommend an alternative assay or reference-laboratory review when the exposure history does not fit; 1 additional positive parasite antibody result also needs independent interpretation, as explained in our discussion of Toxocara antibody findings.
A hypothetical probability example shows why background risk matters: assume an imaginary test has 90% sensitivity and 95% specificity in 10,000 people, of whom 1% have the target infection. It would identify approximately 90 true positives and 495 false positives, so only about 15% of positive results would be true positives—these are teaching assumptions, not measured Schistosoma assay performance.
A high index should not be read as a high worm count, and a borderline index should not automatically be dismissed when exposure is strong. Ask for the assay name and the laboratory's interpretation of 1 equivocal or weakly positive result; confirmation with a different method can address assay uncertainty, but another antibody test still cannot reliably separate active infection from treated history.
Soi phân và nước tiểu có thể xác định được điều gì?
Finding characteristic Schistosoma eggs provides direct parasitological evidence, whereas negative microscopy does not exclude a light infection. CDC recommends examining 3 stool or urine samples collected on different days to improve sensitivity, because egg output can be sparse and intermittent, particularly in travelers with a low parasite burden.
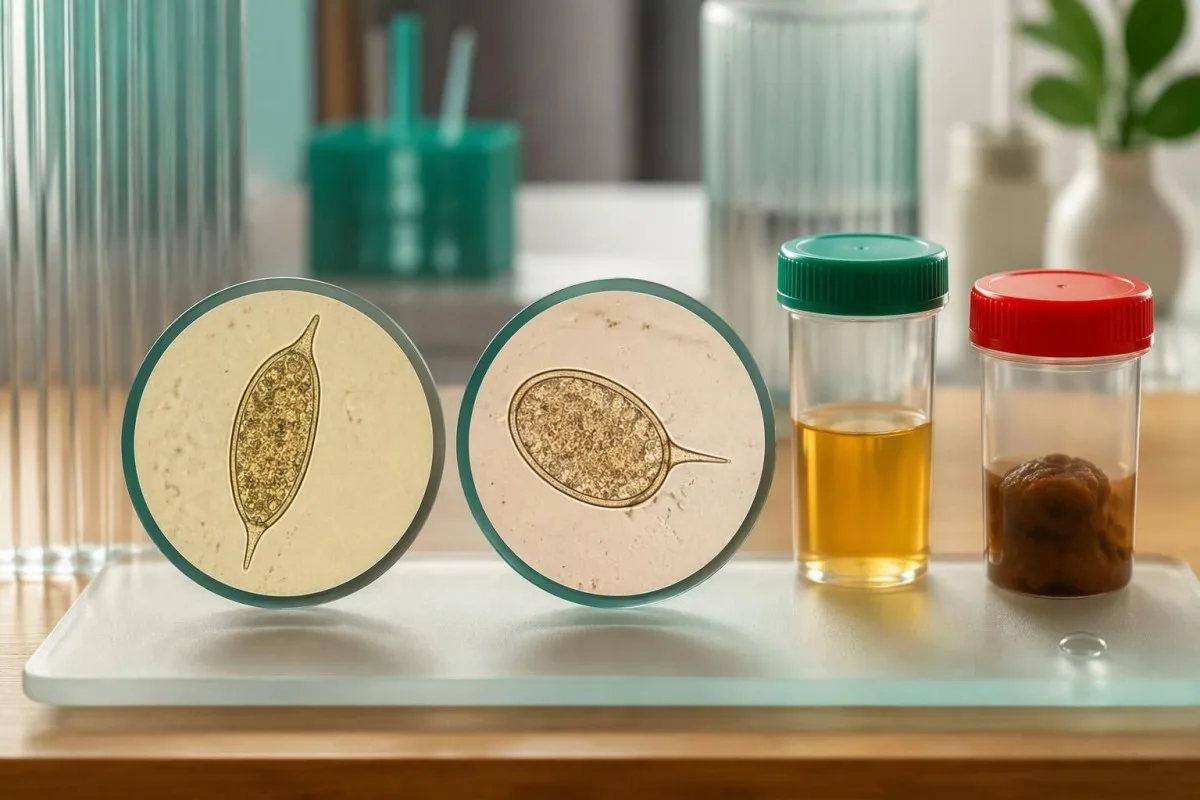
The suspected species determines specimen choice: S. mansoni and S. japonicum are usually investigated through stool, while S. haematobium is usually investigated through urine. Some exposure histories warrant both, so 1 negative stool examination does not address a possible urinary infection; diễn giải cặn nước tiểu also explains why ordinary urinary findings are not equivalent to parasite identification.
Urinary egg excretion often peaks around midday, and laboratories may request a sample between approximately 12 noon and 3 pm. Urine filtration may use a measured volume such as 10 mL, but collection, transport and processing instructions vary; follow the receiving laboratory's protocol rather than improvising exercise, fluid restriction or a collection time.
Routine dipstick testing is not a substitute for a specific Schistosoma egg examination, and 1 routine stool pathogen panel may omit the parasite entirely. Check the exact tests ordered, including concentration or filtration methods when appropriate; our urinalysis method guide helps distinguish screening for cells and chemistry from targeted parasitology.
Xét nghiệm kháng nguyên hoặc PCR có thể cho thấy tình trạng nhiễm bệnh đang hoạt động rõ hơn không?
Schistosoma antigen tests can provide evidence more closely linked to living worms than antibody tests, but access and performance differ. Circulating anodic antigen, or CAA, and circulating cathodic antigen, or CCA, are 2 distinct targets; PCR detects parasite DNA and needs interpretation according to specimen, timing and the laboratory method.

CAA assays can detect antigens released by living schistosomes, including some low-burden infections that microscopy misses. Urine CCA testing is used especially for S. mansoni, but trace readings and performance for other species complicate interpretation; 1 negative point-of-care CCA test should not be treated as a universal exclusion of urinary or intestinal schistosomiasis.
PCR may support diagnosis when microscopy is negative, but DNA detection is not identical to proving that every detected parasite component remains viable after treatment. The specimen matters—serum, stool and urine are not interchangeable—and 1 positive molecular result must be interpreted against the laboratory's validated application; antibodies versus direct detection illustrates this distinction in a different parasitic condition.
Kantesti is an AI lab test interpretation service that can explain the difference between 2 reports labeled Schistosoma IgG and Schistosoma PCR without treating them as interchangeable evidence. Our các phương pháp diễn giải AI do not replace reference-laboratory expertise, and an antigen test's usefulness depends on whether the local service can obtain and validate it for your clinical question.
Những phát hiện nào đi kèm trong xét nghiệm máu và nước tiểu cần lưu ý?
Eosinophilia, urinary abnormalities and signs of organ involvement can strengthen the case for further assessment, but none proves schistosomiasis alone. An absolute eosinophil count above approximately 0.5 × 10⁹/L is commonly considered elevated; a normal count does not exclude infection, especially outside the early immune-response phase.
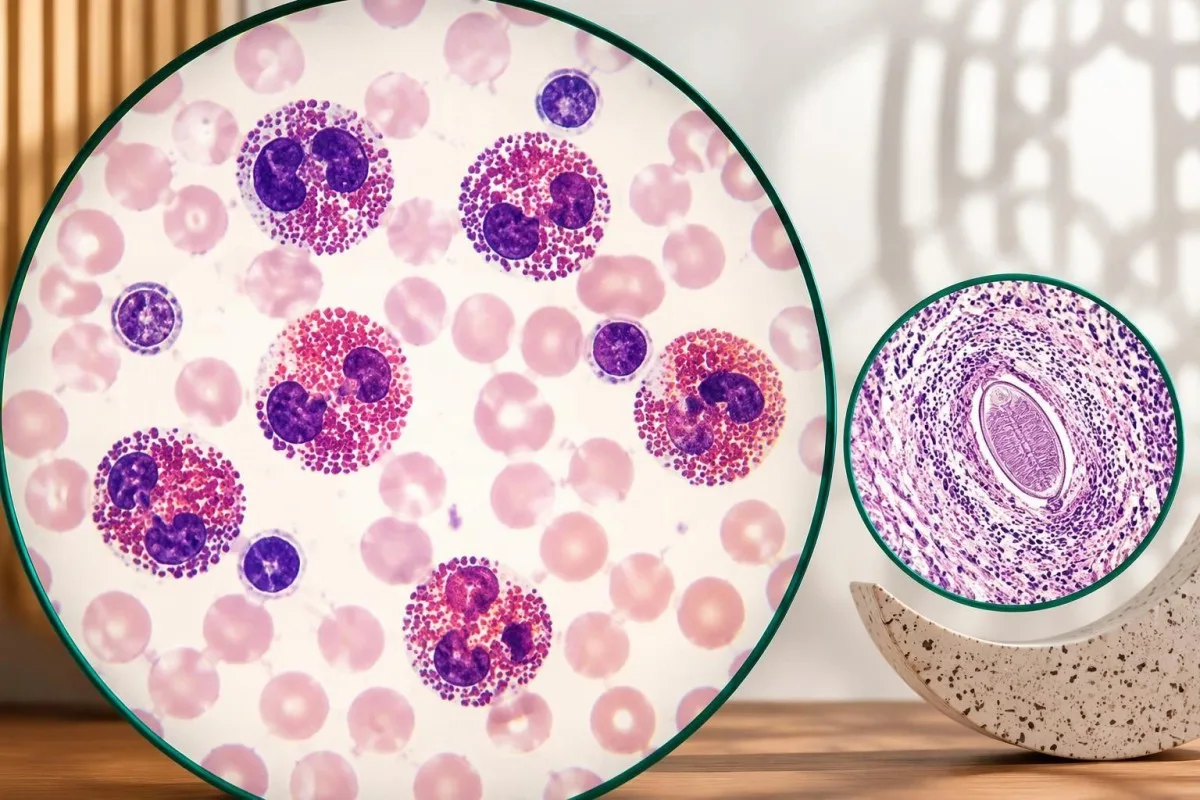
The absolute eosinophil count is usually more informative than the percentage because a percentage depends on the other white-cell populations. A hypothetical count of 0.8 × 10⁹/L may reflect schistosomiasis, another parasite, allergy or a medicine effect; persistent counts at or above 1.5 × 10⁹/L generally warrant broader evaluation, as discussed in our eosinophil count guide.
Normal liver enzymes do not reliably exclude hepatosplenic schistosomiasis because periportal fibrosis and portal hypertension can occur without the usual pattern of cirrhosis. For example, an ALT of 24 IU/L cannot overrule an enlarged spleen or suggestive ultrasound; diễn giải bảng xét nghiệm chức năng gan explains why enzyme results answer different questions from structural imaging.
Blood in urine, protein in urine, persistent diarrhea or genital symptoms can change which investigations are appropriate. At Kantesti, we encourage keeping at least 3 evidence categories separate—exposure, parasite tests and organ findings—because a positive antibody result should not obscure a urinary obstruction, significant anemia or another explanation that requires its own assessment.
Vì sao có thể được đề nghị điều trị khi soi kính hiển vi cho kết quả âm tính?
Clinicians may treat a seropositive person with credible exposure and no adequate treatment history despite negative microscopy. This approach recognizes that light infections can escape egg detection and untreated adult worms can persist for years; the decision balances 3 factors: exposure probability, diagnostic limitations and the person's treatment risks.

Absence of symptoms does not establish absence of infection or eliminate the potential benefit of treatment. A hypothetical traveler tested 10 weeks after a lake swim, with positive IgG and 3 negative stool examinations, may still be offered praziquantel if the exposure was credible and no earlier treatment occurred; negative microscopy lowers certainty but does not settle the question.
Documented earlier treatment changes the reasoning, particularly when no freshwater re-exposure has occurred. A person with a positive test 5 years after an appropriately timed course does not automatically need another course; the clinician should investigate whether treatment was complete, whether the initial infection was confirmed and whether any symptoms or direct tests now suggest persistence.
Visible blood in urine requires assessment even when Schistosoma antibodies are positive, because 1 parasite result does not exclude stones, other infections or cancer. Chronic urinary schistosomiasis is associated with increased bladder cancer risk, but risk is not diagnosis; our guide to bladder warning symptoms explains why persistent or recurrent urinary changes deserve separate attention.
Liều praziquantel và thời điểm điều trị được lựa chọn như thế nào?
Praziquantel is the standard medicine for schistosomiasis, but dose and timing depend on species and clinical circumstances. CDC's Clinical Care of Schistosomiasis guidance lists 40 mg/kg over 1 day in 2 divided doses for S. mansoni, S. haematobium and S. intercalatum, and 60 mg/kg in 3 divided doses for S. japonicum and S. mekongi.

Praziquantel works best against mature worms, so otherwise stable travelers are generally treated at least 6–8 weeks after their last freshwater exposure. Taking it immediately after a swim is not reliable preventive treatment; if a course was given very early, the clinician may plan another course after maturation rather than assuming the initial prescription covered all developing worms.
A clearly hypothetical calculation illustrates a 40 mg/kg regimen: a 60 kg adult would receive 2,400 mg total over 1 day, split into 2 doses of 1,200 mg. Where 600 mg tablets are supplied, that arithmetic corresponds to 2 tablets per dose, but it is not an individual prescription—species, available formulation, rounding, swallowing ability and medical history must be checked.
Repeat treatment after 2–4 weeks may be appropriate in selected patients, especially with light infections or concerns about an incomplete response; it is not required solely because IgG remains positive. Medication review matters because rifampicin and enzyme-inducing antiseizure medicines can reduce praziquantel exposure, so patients taking carbamazepine should bring their regimen and any carbamazepine monitoring information rather than adjusting either medicine themselves.
Những triệu chứng nào cần được đánh giá khẩn cấp hoặc cấp cứu?
Fever after travel needs prompt assessment, and new weakness, seizures or bladder-control changes need emergency evaluation. Acute schistosomiasis can cause fever, cough, rash, diarrhea and eosinophilia around 2–8 weeks after exposure, but these symptoms overlap with other conditions and cannot be diagnosed from antibodies alone.
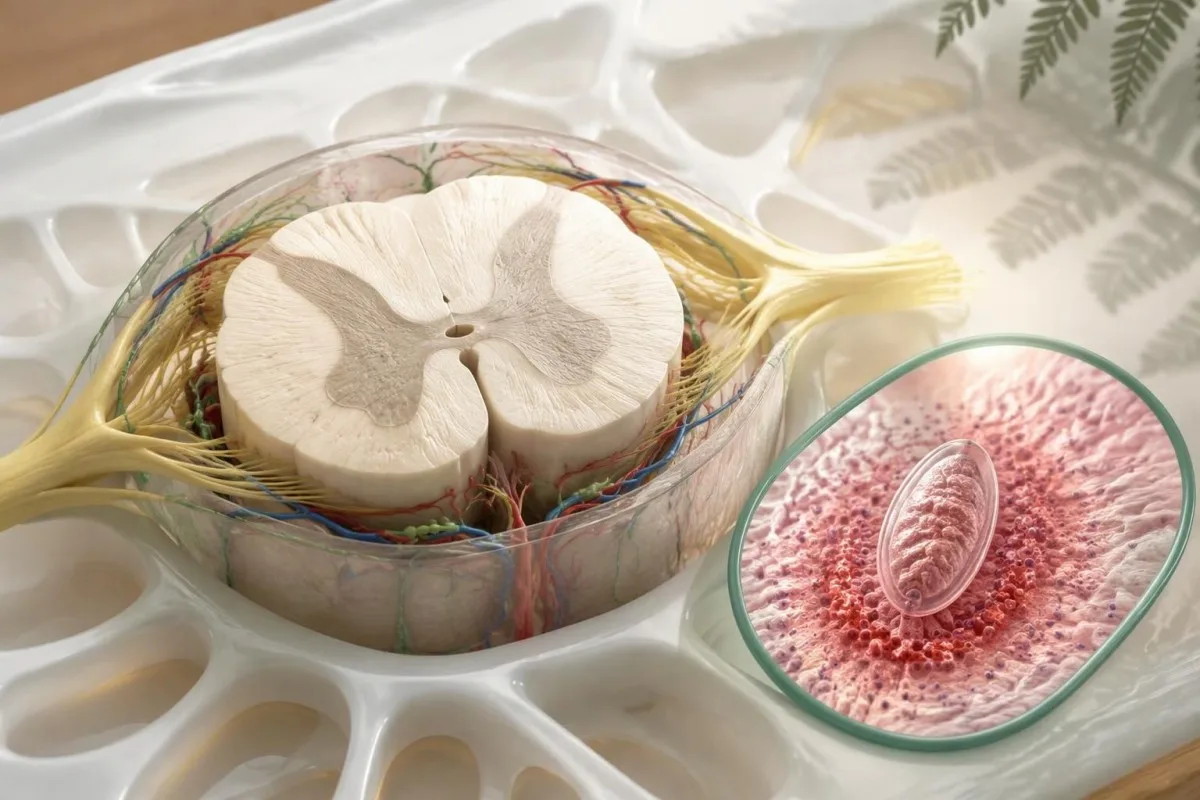
New leg weakness, difficulty walking, urinary retention or loss of bowel control can signal spinal cord involvement and should not wait for routine repeat serology. Schistosoma eggs can occasionally affect neurological tissue, but 1 positive antibody result does not establish the cause; emergency clinicians may need imaging and a broad differential diagnosis before specialist treatment is selected.
Acute systemic or neurological schistosomiasis may require specialist-directed corticosteroids alongside a carefully timed antiparasitic plan. If the exposure history also suggests Strongyloides, assess that possibility before immunosuppression when feasible, because steroids can precipitate dangerous hyperinfection; a Strongyloides IgG result needs its own management rather than assuming 1 antiparasitic medicine treats both organisms.
Fever after a malaria-risk itinerary should be assessed the same day, even if Schistosoma antibodies offer a plausible alternative explanation. Do not wait 6–8 weeks for repeat serology when there is persistent high fever, breathing difficulty, confusion, fainting, significant gastrointestinal bleeding or inability to pass urine; the immediate priority is identifying and treating the acute problem.
Thai kỳ, tuổi thơ ấu và các tình trạng khác làm thay đổi việc chăm sóc ra sao?
Pregnancy, young age and complex illness require individualized treatment decisions rather than automatically withholding or prescribing praziquantel. The WHO guideline on control and elimination of human schistosomiasis (2022) supports preventive treatment from age 2 years and includes pregnant women after the first trimester and lactating women in eligible programs.

WHO program recommendations and treatment of an individual imported infection answer related but different questions. A hypothetical patient at 10 weeks of pregnancy needs a clinician-led balance of infection likelihood, severity and treatment timing; the recommendation to include pregnancy after the first trimester in preventive programs should not be turned into a blanket rule for every symptomatic patient.
Children's dosing requires an accurate weight and a formulation they can take safely; adult tablet arithmetic is not enough. WHO's inclusion of children aged 2 years and older in preventive chemotherapy does not make every product licensed for every younger age in every country, and our discussion of children's interpretation limits explains why pediatric results need age-specific clinical oversight.
A history of seizures, possible cysticercosis, significant liver disease or neurological symptoms should be reviewed before treatment. For 1 person with a straightforward travel-acquired infection, routine outpatient prescribing may be appropriate; another with possible central nervous system involvement may need specialist planning because the immune response to parasite treatment can itself affect symptoms.
Vì sao IgG kháng Schistosoma có thể vẫn dương tính sau khi điều trị thành công?
Schistosoma IgG can remain positive for years after successful treatment and is not a reliable test of cure. CDC recommends considering repeat stool or urine examination 1–2 months after treatment when eggs were detected before treatment; follow-up must match the evidence used to establish infection and the person's subsequent clinical course.

A positive IgG result 6 months after treatment does not, by itself, demonstrate treatment failure. Antibody decline varies, and a stable or temporarily higher signal cannot reliably quantify surviving worms; comparing results from 2 different laboratories adds assay differences, making numerical trend interpretation even less suitable for declaring cure.
Persistent symptoms or eosinophilia deserve reassessment, but neither automatically proves living Schistosoma remain. If eggs are still found at the 1–2 month follow-up, specialists may consider egg viability, collection details, treatment timing and whether another course is needed; PCR positivity can also require caution because detecting parasite DNA is not the same as identifying viable adult worms.
Kantesti can help organize 3 follow-up dates—treatment, specimen collection and any re-exposure—without labeling persistent IgG as treatment failure. Our hướng dẫn phân tích xu hướng thuốc explains why trends must be matched to the right clinical endpoint; an available validated antigen assay may be more useful than serial antibodies, but its follow-up schedule belongs to the treating service.
Vì sao cùng một kết quả dương tính có thể dẫn đến các quyết định khác nhau?
The same positive Schistosoma IgG result can lead to treatment, additional testing or observation because the surrounding evidence differs. The following 4 examples are hypothetical teaching scenarios—not patient encounters—and illustrate how exposure dates, prior therapy, assay uncertainty and organ findings can outweigh the apparent simplicity of a positive flag.
A hypothetical 28-year-old returns from a freshwater swim, tests positive 10 weeks later and has never received praziquantel; treatment may be reasonable despite negative microscopy. A hypothetical 44-year-old treated appropriately 4 years earlier, with no further exposure and no concerning findings, may not need retreatment; the timeline of laboratory results helps keep these histories distinct.
A hypothetical 35-year-old with no plausible freshwater exposure has a weakly positive screening assay and normal supporting investigations. The next step may be checking the original indication, assay and cross-reactivity rather than immediate treatment; changing a report from weak positive to strong positive on 1 repeat antibody assay still does not create a documented exposure or prove active infection.
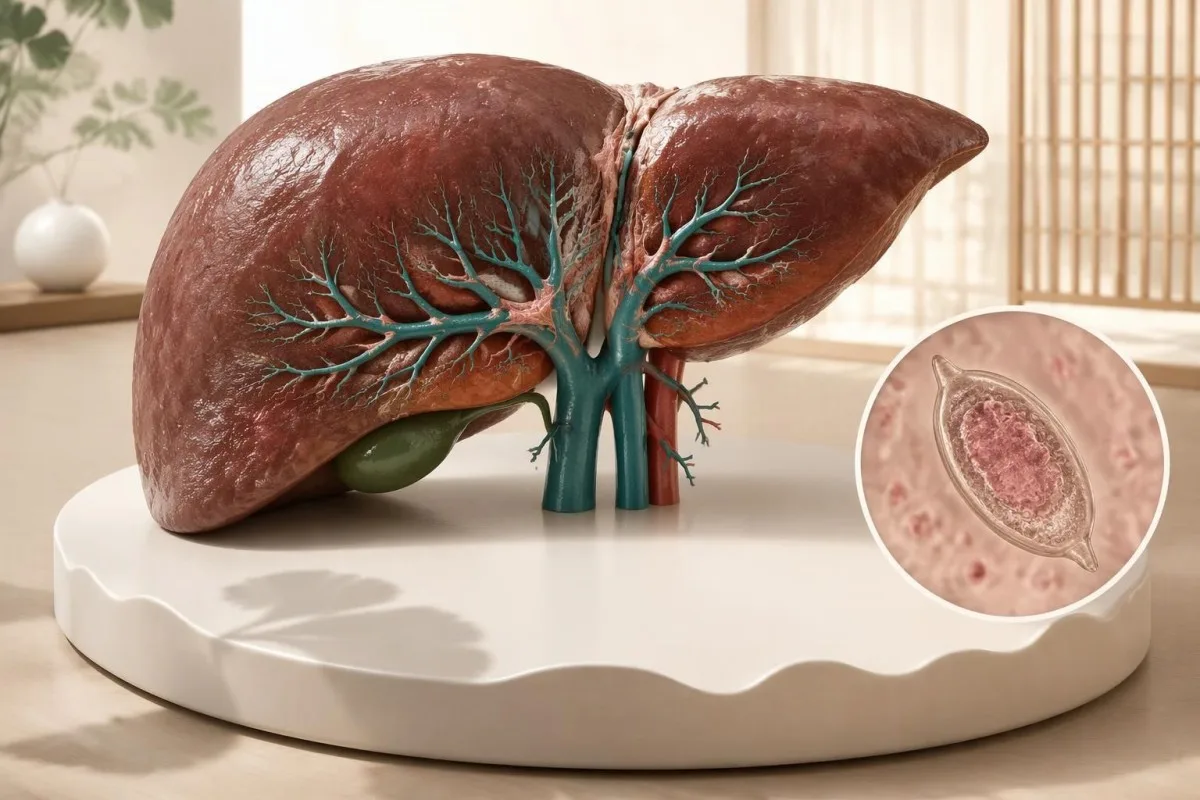
A hypothetical 54-year-old who lived near endemic freshwater 20 years earlier has positive IgG, an enlarged spleen and an ALT of 24 IU/L within the local range. That combination merits assessment for portal and other organ disease despite normal enzymes; an old exposure is not automatically resolved, and common liver fibrosis scores should not be assumed validated for schistosomal periportal fibrosis.
Bạn nên mang theo gì khi tái khám, và những nguồn nào hỗ trợ việc chăm sóc?
Bring your exposure history, complete laboratory report and treatment record to a clinician experienced in travel medicine, infectious diseases or tropical medicine. Prepare 3 questions: whether the result fits your exposure, which direct tests could change the decision and how treatment response will be assessed without relying on antibody disappearance.

Your report should retain the assay name, units or index, reference interpretation and collection date, rather than only a cropped positive flag. Add 1 concise exposure timeline, previous praziquantel doses and dates, current medicines, pregnancy status where relevant and any urinary or neurological symptoms; this makes uncertainty visible and reduces the chance of repeating an uninformative antibody test.
Kantesti is an AI blood test interpretation platform that helps explain why 1 Schistosoma antibody result must be considered alongside exposure and treatment history, not used as a prescribing instruction. Our khung thẩm định lâm sàng describes methodology and oversight, while our quyền riêng tư và xử lý dữ liệu information explains how to review data choices before sharing a travel or laboratory record.
The 2 Zenodo publications below describe Kantesti's validation framework and aggregate platform reporting; they are not clinical schistosomiasis guidelines and do not establish the sensitivity of a Schistosoma assay. Clinical recommendations in this article draw on CDC diagnostic and treatment guidance and the WHO guideline (2022), with our các tiêu chuẩn về nội dung y khoa distinguishing published evidence, hypothetical calculations and the limits of AI-supported explanation.
Câu hỏi thường gặp
Schistosoma IgG dương tính có nghĩa là tôi đang bị nhiễm bệnh không?
Kết quả Schistosoma IgG dương tính không thể phân biệt một cách đáng tin cậy giữa nhiễm trùng đang hoạt động và nhiễm trùng đã được điều trị trước đó. Kháng thể có thể vẫn được phát hiện trong nhiều năm, vì vậy 1 báo cáo dương tính phải được diễn giải cùng với tiền sử tiếp xúc với nước ngọt và điều trị. Bác sĩ lâm sàng có thể sử dụng phương pháp soi phân hoặc nước tiểu, xét nghiệm kháng nguyên hoặc PCR khi thích hợp để thu thập bằng chứng trực tiếp hơn. Tiền sử phơi nhiễm đáng tin cậy mà chưa được điều trị đầy đủ trước đó có thể là cơ sở để điều trị ngay cả khi kết quả soi kính hiển vi âm tính.
Tôi có thể mắc bệnh sán máng dù xét nghiệm phân và nước tiểu âm tính không?
Soi phân hoặc nước tiểu âm tính không loại trừ bệnh sán máng, đặc biệt là sau khi đi du lịch khi gánh nặng ký sinh trùng có thể thấp. CDC khuyến nghị xét nghiệm 3 mẫu được thu thập vào những ngày khác nhau vì trứng có thể được thải ra không liên tục. Loài nghi ngờ cũng quyết định cần xét nghiệm phân, nước tiểu hay cả hai. Bác sĩ vẫn có thể khuyến nghị điều trị khi kháng thể dương tính, có cơ sở tin cậy rằng đã phơi nhiễm và không có hồ sơ ghi nhận điều trị đầy đủ trước đó.
Sau khi tiếp xúc với nước ngọt bao lâu thì tôi nên đi xét nghiệm?
CDC khuyến nghị lấy mẫu xét nghiệm kháng thể Schistosoma ít nhất 6–8 tuần sau khi nghi ngờ nhiễm mới. Khi có nhiều lần phơi nhiễm trong chuyến đi, hãy lấy lần tiếp xúc với nước ngọt cuối cùng làm mốc tham chiếu thực tế. Có thể cần xét nghiệm lại nếu kết quả âm tính sớm vì kháng thể có thể chưa phát hiện được. Sốt hoặc các triệu chứng đáng kể khác cần được đánh giá kịp thời, không nên chờ đến thời điểm xét nghiệm này.
Tại sao tôi vẫn dương tính với kháng thể Schistosoma sau khi dùng praziquantel?
0 Kháng thể Schistosoma có thể vẫn dương tính trong nhiều năm sau khi điều trị bằng praziquantel thành công vì đáp ứng miễn dịch kéo dài hơn sự tồn tại của ký sinh trùng. Kết quả dương tính sau điều trị 6 tháng, tự nó, không chứng minh rằng điều trị thất bại hoặc biện minh cho việc điều trị thêm một đợt nữa. Khi phát hiện trứng trước khi điều trị, bác sĩ lâm sàng có thể yêu cầu xét nghiệm lại phân hoặc nước tiểu sau đó 1–2 tháng. Việc phơi nhiễm mới, các triệu chứng dai dẳng và kết quả xét nghiệm trực tiếp có giá trị hơn tình trạng kháng thể còn tồn tại đơn thuần.
Liều praziquantel nào được dùng để điều trị bệnh sán máng?
0 CDC liệt kê praziquantel 40 mg/kg trong 1 ngày, chia thành 2 liều, cho S. mansoni, S. haematobium và S. intercalatum. Phác đồ được liệt kê cho S. japonicum và S. mekongi là 60 mg/kg trong 1 ngày, chia thành 3 liều. Những người đi du lịch có tình trạng ổn định thường được điều trị ít nhất 6–8 tuần sau lần tiếp xúc cuối cùng với nước ngọt, vì praziquantel có tác dụng tốt nhất đối với giun trưởng thành. Bác sĩ phải lựa chọn phác đồ và xem xét các thuốc đang dùng, tình trạng mang thai, tuổi và khả năng có tổn thương thần kinh.
Xét nghiệm kháng thể Schistosoma dương tính có thể là dương tính giả không?
Xét nghiệm kháng thể Schistosoma có thể cho kết quả dương tính giả hoặc phản ứng chéo với kháng thể chống lại các ký sinh trùng khác, tùy thuộc vào xét nghiệm được sử dụng. Không có giá trị chỉ số chung nào xác định tình trạng nhiễm đang hoạt động, và 2 phòng xét nghiệm có thể sử dụng các chế phẩm kháng nguyên và ngưỡng khác nhau. Kết quả dương tính yếu khi không có tiền sử phơi nhiễm với nước ngọt hợp lý có thể cần được phòng xét nghiệm xem xét hoặc xác nhận bằng một phương pháp khác. Chỉ lặp lại xét nghiệm kháng thể vẫn không thể phân biệt đáng tin cậy tiền sử đã được điều trị với giun còn sống.
Tìm hiểu cách đọc kết quả xét nghiệm máu của bạn
Tải lên báo cáo xét nghiệm của bạn và AI của Kantesti sẽ giải thích từng dấu ấn sinh học bằng ngôn ngữ dễ hiểu chỉ trong vài giây. Được hơn 2 triệu người trên toàn thế giới sử dụng.
Tài liệu tham khảo
- Klein, T., Mitchell, S., & Weber, H. (2026). Khung xác thực lâm sàng v2.0 (Trang xác thực y khoa). Nghiên cứu y khoa của Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Trình phân tích xét nghiệm máu AI: 2,5M xét nghiệm được phân tích | Báo cáo sức khỏe toàn cầu 2026. Nghiên cứu y khoa của Kantesti AI. DOI
- Trung tâm Kiểm soát và Phòng ngừa Dịch bệnh (2024). Clinical Testing and Diagnosis for Schistosomiasis. CDC Schistosomiasis Clinical Guidance.
- Trung tâm Kiểm soát và Phòng ngừa Dịch bệnh (2024). Clinical Care of Schistosomiasis. CDC Schistosomiasis Clinical Guidance.
- World Health Organization (2022). WHO guideline on control and elimination of human schistosomiasis. World Health Organization Guidelines.
- 2 triệu+Các xét nghiệm được phân tích
- 127+Các quốc gia
- 100+Ngôn ngữ
Về đội ngũ y tế


Tín hiệu tin cậy E-E-A-T
Kinh nghiệm
Đánh giá lâm sàng do bác sĩ phụ trách đối với quy trình diễn giải kết quả xét nghiệm.
Chuyên môn
Tập trung vào y học xét nghiệm: cách các chỉ dấu sinh học (biomarker) hoạt động trong bối cảnh lâm sàng.
Tính uy quyền
Được Tiến sĩ Thomas Klein đánh giá về mặt y khoa, với sự đóng góp của Tiến sĩ Sarah Mitchell và Giáo sư, Tiến sĩ Hans Weber.
Độ tin cậy
Diễn giải dựa trên bằng chứng, kèm các lộ trình theo dõi rõ ràng để giảm mức độ báo động.






Tuyên bố miễn trừ trách nhiệm y tế
Bài viết này chỉ nhằm mục đích giáo dục và không cấu thành lời khuyên y tế. Luôn tham khảo ý kiến của nhà cung cấp dịch vụ chăm sóc sức khỏe đủ năng lực để đưa ra quyết định chẩn đoán và điều trị.
Đã xuất bản · Liên hệ với ban biên tập
Xuất bản bởi Kantesti Ltd, đăng ký tại Anh và xứ Wales, số công ty. 17090423, London, Vương quốc Anh.
