
A positive Schistosoma antibody result may justify treatment after credible freshwater exposure if you have never received adequate therapy, but it cannot prove active infection or confirm cure. Your exposure dates, previous treatment and additional tests determine the next step.

Pokok-pokok penting
- Antibodi positif indicate an immune response to Schistosoma antigens; 1 positive result cannot distinguish untreated infection from previously treated infection.
- Jendela pengujian matters: CDC recommends collecting antibody samples at least 6–8 weeks after a suspected new infection.
- Freshwater exposure means skin contact with potentially contaminated lakes, rivers or canals—not simply visiting an affected country.
- Microscopy is more informative when clinicians request 3 stool or urine specimens collected on different days.
- Praziquantel dosing commonly totals 40 mg/kg over 1 day for S. mansoni and S. haematobium, but prescribing depends on species and clinical circumstances.
- Wektu perawatan usually means waiting at least 6–8 weeks after the last freshwater exposure in otherwise stable travelers because praziquantel works best against mature worms.
- Follow-up microscopy may be requested 1–2 months after treatment when eggs were present before treatment.
- Persistent IgG can remain positive for years after successful treatment; another positive result does not automatically justify another course.
Does a positive Schistosoma antibody result need treatment?
A schistosoma antibody positive result does not automatically mean you need treatment. Clinicians often recommend treatment when freshwater exposure is credible and adequate previous therapy is absent, even if microscopy is negative; after documented treatment without re-exposure, 1 persistent positive result usually is not enough to justify retreatment.

Schistosoma IgG positive meaning is best understood as evidence of immune recognition, not a measurement of living worms. The antibody response may outlast the parasite by years, and 2 people with the same reported result can need different care—one after an untreated exposure, another after successful treatment with no subsequent freshwater contact.
Previous exposure and previous treatment are separate questions: an old infection can remain untreated, whereas an old positive test can persist after cure. Before interpreting 1 report as either active disease or harmless history, check the treatment name, dose, date and any later water contact; our explanation of asil antibodi positif distinguishes these different kinds of evidence.
Kantesti is an AI blood test analyzer that helps explain why 1 positive Schistosoma IgG result cannot establish active infection, even when the complete blood count is normal. Our role is report explanation—not parasite identification or prescribing—and our lan tujuan should be understood separately from the clinician-led decisions described here.
Which freshwater exposures make the result more convincing?
Skin contact with freshwater in a transmission area makes a positive result more clinically meaningful. Swimming, wading, bathing, rafting or washing in lakes, rivers and irrigation canals can provide exposure; record 3 details for each event: the precise location, the activity and the date of your last contact.

Schistosoma larvae released by freshwater snails enter through the skin; swallowing water is not required. A brief wade still counts as exposure, and the absence of an itchy rash does not exclude it, so a hypothetical traveler who entered a lake for 5 minutes should mention that event rather than recording only longer swimming sessions.
Seawater and properly chlorinated swimming pools are not typical schistosomiasis exposure sources. Freshwater contact can also raise concern for other conditions with different tests and treatment, including leptospirosis after water exposure; fever beginning 1 week after a river activity should not be attributed to Schistosoma antibodies without a broader assessment.
A country's name alone cannot establish individual risk because transmission varies within countries and water bodies. Reconstruct even 1 forgotten activity—such as washing equipment beside a river—and distinguish parasite exposure from vaccination records; travel antibody checks answer a different question and do not provide protection against schistosomiasis.
When should schistosomiasis testing after travel happen?
Schistosomiasis antibody testing is generally more informative at least 6–8 weeks after a suspected new infection. CDC's Clinical Testing and Diagnosis for Schistosomiasis guidance explains that this interval allows antibodies to develop; a negative result collected earlier cannot reliably exclude a recent freshwater-acquired infection.

The last freshwater contact is a practical anchor when a trip involved several possible exposures. For example, a hypothetical traveler who swam on both the first and final day of a 3-week holiday should calculate the testing interval from the final swim, rather than assuming that the first exposure makes an immediate post-trip result conclusive.
Seroconversion is not identical across people or assays, so 6–8 weeks is a useful testing window rather than a guarantee of detection. When exposure is persuasive and an initial result is negative, a clinician may arrange another sample later, sometimes around 12 weeks after exposure; a second date should be agreed rather than inferred from a generic laboratory reference range.
Fever or significant symptoms after travel should be assessed without waiting for an antibody window to close, especially after a malaria-risk itinerary. At Kantesti, we encourage readers to keep 2 dates visible—last freshwater contact and sample collection—because wektu tes infeksi can change the meaning of a negative report even though each organism requires its own diagnostic strategy.
Can Schistosoma antibodies be falsely positive?
Schistosoma antibody tests can produce false-positive or cross-reactive results, and their performance varies by assay. There is no universal IgG concentration or index that proves active schistosomiasis; 2 laboratories may use different antigen preparations, reporting units and thresholds, making direct numerical comparisons unreliable.

Cross-reactivity with other helminth antibodies depends on the test rather than occurring uniformly in every person. A laboratory may recommend an alternative assay or reference-laboratory review when the exposure history does not fit; 1 additional positive parasite antibody result also needs independent interpretation, as explained in our discussion of Toxocara antibody findings.
A hypothetical probability example shows why background risk matters: assume an imaginary test has 90% sensitivity and 95% specificity in 10,000 people, of whom 1% have the target infection. It would identify approximately 90 true positives and 495 false positives, so only about 15% of positive results would be true positives—these are teaching assumptions, not measured Schistosoma assay performance.
A high index should not be read as a high worm count, and a borderline index should not automatically be dismissed when exposure is strong. Ask for the assay name and the laboratory's interpretation of 1 equivocal or weakly positive result; confirmation with a different method can address assay uncertainty, but another antibody test still cannot reliably separate active infection from treated history.
What can stool and urine microscopy establish?
Finding characteristic Schistosoma eggs provides direct parasitological evidence, whereas negative microscopy does not exclude a light infection. CDC recommends examining 3 stool or urine samples collected on different days to improve sensitivity, because egg output can be sparse and intermittent, particularly in travelers with a low parasite burden.
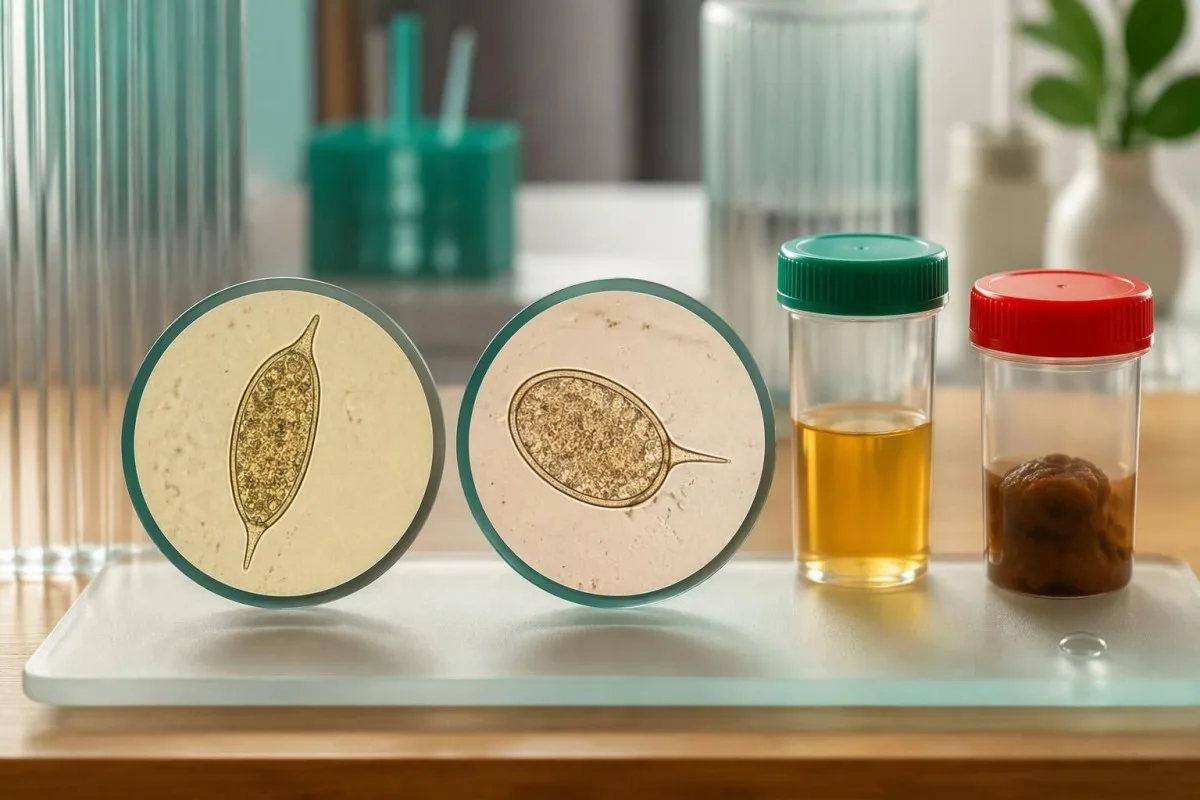
The suspected species determines specimen choice: S. mansoni and S. japonicum are usually investigated through stool, while S. haematobium is usually investigated through urine. Some exposure histories warrant both, so 1 negative stool examination does not address a possible urinary infection; interpretasi sedimen urin also explains why ordinary urinary findings are not equivalent to parasite identification.
Urinary egg excretion often peaks around midday, and laboratories may request a sample between approximately 12 noon and 3 pm. Urine filtration may use a measured volume such as 10 mL, but collection, transport and processing instructions vary; follow the receiving laboratory's protocol rather than improvising exercise, fluid restriction or a collection time.
Routine dipstick testing is not a substitute for a specific Schistosoma egg examination, and 1 routine stool pathogen panel may omit the parasite entirely. Check the exact tests ordered, including concentration or filtration methods when appropriate; our urinalysis method guide helps distinguish screening for cells and chemistry from targeted parasitology.
Do antigen tests or PCR show active infection more clearly?
Schistosoma antigen tests can provide evidence more closely linked to living worms than antibody tests, but access and performance differ. Circulating anodic antigen, or CAA, and circulating cathodic antigen, or CCA, are 2 distinct targets; PCR detects parasite DNA and needs interpretation according to specimen, timing and the laboratory method.

CAA assays can detect antigens released by living schistosomes, including some low-burden infections that microscopy misses. Urine CCA testing is used especially for S. mansoni, but trace readings and performance for other species complicate interpretation; 1 negative point-of-care CCA test should not be treated as a universal exclusion of urinary or intestinal schistosomiasis.
PCR may support diagnosis when microscopy is negative, but DNA detection is not identical to proving that every detected parasite component remains viable after treatment. The specimen matters—serum, stool and urine are not interchangeable—and 1 positive molecular result must be interpreted against the laboratory's validated application; antibodies versus direct detection illustrates this distinction in a different parasitic condition.
Kantesti is an AI lab test interpretation service that can explain the difference between 2 reports labeled Schistosoma IgG and Schistosoma PCR without treating them as interchangeable evidence. Our metode interpretasi AI do not replace reference-laboratory expertise, and an antigen test's usefulness depends on whether the local service can obtain and validate it for your clinical question.
Which accompanying blood and urine findings matter?
Eosinophilia, urinary abnormalities and signs of organ involvement can strengthen the case for further assessment, but none proves schistosomiasis alone. An absolute eosinophil count above approximately 0.5 × 10⁹/L is commonly considered elevated; a normal count does not exclude infection, especially outside the early immune-response phase.
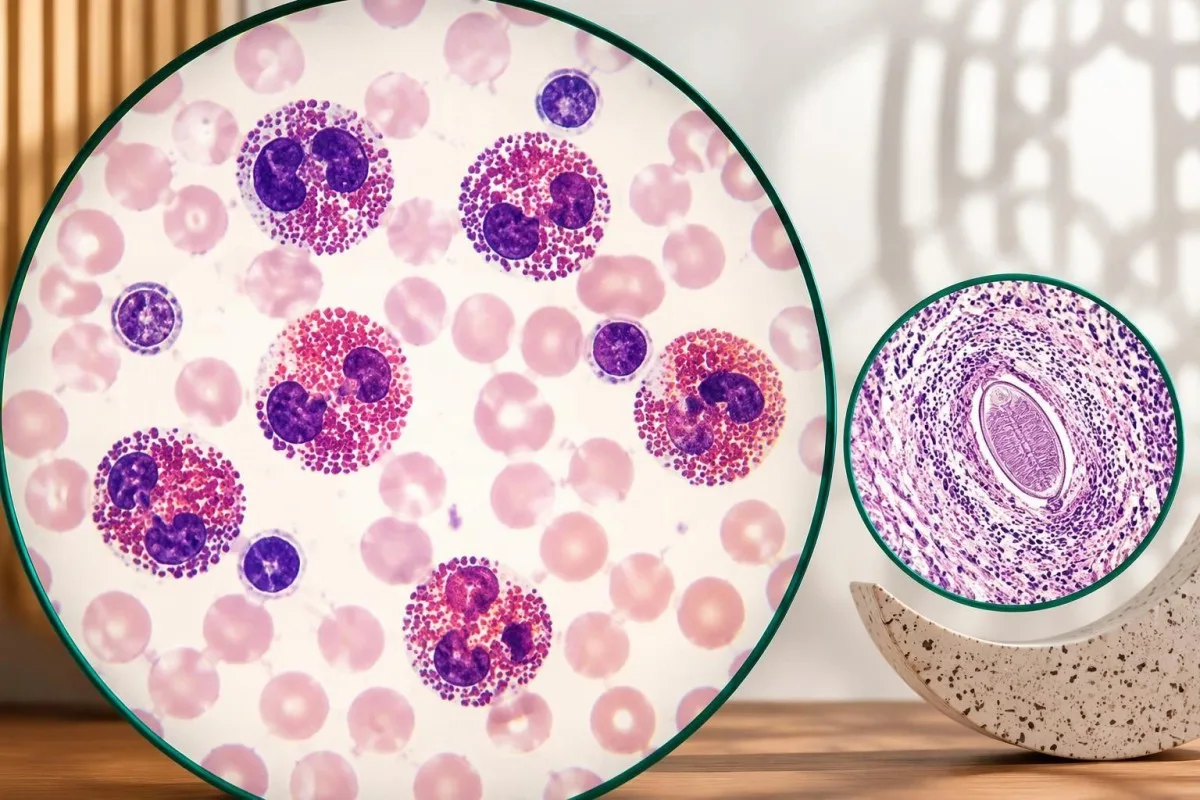
The absolute eosinophil count is usually more informative than the percentage because a percentage depends on the other white-cell populations. A hypothetical count of 0.8 × 10⁹/L may reflect schistosomiasis, another parasite, allergy or a medicine effect; persistent counts at or above 1.5 × 10⁹/L generally warrant broader evaluation, as discussed in our eosinophil count guide.
Normal liver enzymes do not reliably exclude hepatosplenic schistosomiasis because periportal fibrosis and portal hypertension can occur without the usual pattern of cirrhosis. For example, an ALT of 24 IU/L cannot overrule an enlarged spleen or suggestive ultrasound; interpretasi panel ati explains why enzyme results answer different questions from structural imaging.
Blood in urine, protein in urine, persistent diarrhea or genital symptoms can change which investigations are appropriate. At Kantesti, we encourage keeping at least 3 evidence categories separate—exposure, parasite tests and organ findings—because a positive antibody result should not obscure a urinary obstruction, significant anemia or another explanation that requires its own assessment.
Why might treatment be offered when microscopy is negative?
Clinicians may treat a seropositive person with credible exposure and no adequate treatment history despite negative microscopy. This approach recognizes that light infections can escape egg detection and untreated adult worms can persist for years; the decision balances 3 factors: exposure probability, diagnostic limitations and the person's treatment risks.

Absence of symptoms does not establish absence of infection or eliminate the potential benefit of treatment. A hypothetical traveler tested 10 weeks after a lake swim, with positive IgG and 3 negative stool examinations, may still be offered praziquantel if the exposure was credible and no earlier treatment occurred; negative microscopy lowers certainty but does not settle the question.
Documented earlier treatment changes the reasoning, particularly when no freshwater re-exposure has occurred. A person with a positive test 5 years after an appropriately timed course does not automatically need another course; the clinician should investigate whether treatment was complete, whether the initial infection was confirmed and whether any symptoms or direct tests now suggest persistence.
Visible blood in urine requires assessment even when Schistosoma antibodies are positive, because 1 parasite result does not exclude stones, other infections or cancer. Chronic urinary schistosomiasis is associated with increased bladder cancer risk, but risk is not diagnosis; our guide to bladder warning symptoms explains why persistent or recurrent urinary changes deserve separate attention.
How are praziquantel dose and treatment timing chosen?
Praziquantel is the standard medicine for schistosomiasis, but dose and timing depend on species and clinical circumstances. CDC's Clinical Care of Schistosomiasis guidance lists 40 mg/kg over 1 day in 2 divided doses for S. mansoni, S. haematobium and S. intercalatum, and 60 mg/kg in 3 divided doses for S. japonicum and S. mekongi.

Praziquantel works best against mature worms, so otherwise stable travelers are generally treated at least 6–8 weeks after their last freshwater exposure. Taking it immediately after a swim is not reliable preventive treatment; if a course was given very early, the clinician may plan another course after maturation rather than assuming the initial prescription covered all developing worms.
A clearly hypothetical calculation illustrates a 40 mg/kg regimen: a 60 kg adult would receive 2,400 mg total over 1 day, split into 2 doses of 1,200 mg. Where 600 mg tablets are supplied, that arithmetic corresponds to 2 tablets per dose, but it is not an individual prescription—species, available formulation, rounding, swallowing ability and medical history must be checked.
Repeat treatment after 2–4 weeks may be appropriate in selected patients, especially with light infections or concerns about an incomplete response; it is not required solely because IgG remains positive. Medication review matters because rifampicin and enzyme-inducing antiseizure medicines can reduce praziquantel exposure, so patients taking carbamazepine should bring their regimen and any carbamazepine monitoring information rather than adjusting either medicine themselves.
Gejala apa sing mbutuhaké pemeriksaan enggal utawa darurat?
Fever after travel needs prompt assessment, and new weakness, seizures or bladder-control changes need emergency evaluation. Acute schistosomiasis can cause fever, cough, rash, diarrhea and eosinophilia around 2–8 weeks after exposure, but these symptoms overlap with other conditions and cannot be diagnosed from antibodies alone.
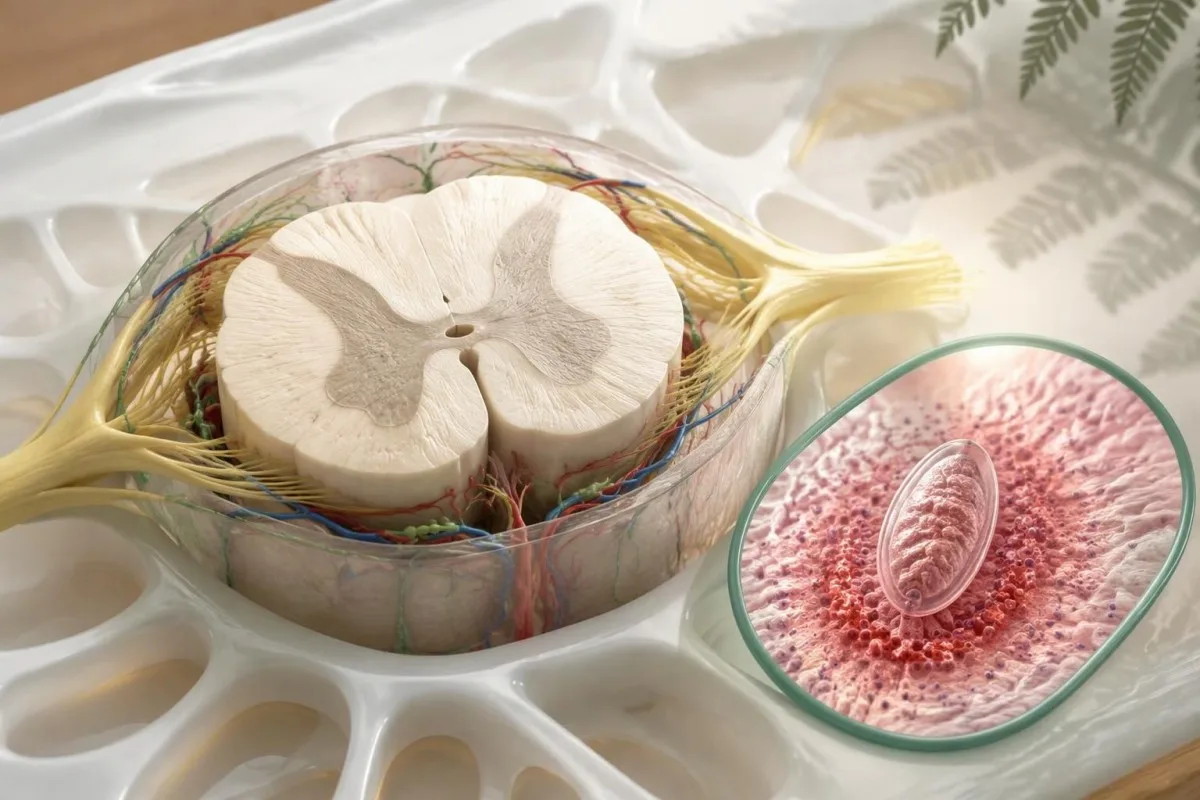
New leg weakness, difficulty walking, urinary retention or loss of bowel control can signal spinal cord involvement and should not wait for routine repeat serology. Schistosoma eggs can occasionally affect neurological tissue, but 1 positive antibody result does not establish the cause; emergency clinicians may need imaging and a broad differential diagnosis before specialist treatment is selected.
Acute systemic or neurological schistosomiasis may require specialist-directed corticosteroids alongside a carefully timed antiparasitic plan. If the exposure history also suggests Strongyloides, assess that possibility before immunosuppression when feasible, because steroids can precipitate dangerous hyperinfection; a Strongyloides IgG result needs its own management rather than assuming 1 antiparasitic medicine treats both organisms.
Fever after a malaria-risk itinerary should be assessed the same day, even if Schistosoma antibodies offer a plausible alternative explanation. Do not wait 6–8 weeks for repeat serology when there is persistent high fever, breathing difficulty, confusion, fainting, significant gastrointestinal bleeding or inability to pass urine; the immediate priority is identifying and treating the acute problem.
How do pregnancy, childhood and other conditions change care?
Pregnancy, young age and complex illness require individualized treatment decisions rather than automatically withholding or prescribing praziquantel. The WHO guideline on control and elimination of human schistosomiasis (2022) supports preventive treatment from age 2 years and includes pregnant women after the first trimester and lactating women in eligible programs.

WHO program recommendations and treatment of an individual imported infection answer related but different questions. A hypothetical patient at 10 weeks of pregnancy needs a clinician-led balance of infection likelihood, severity and treatment timing; the recommendation to include pregnancy after the first trimester in preventive programs should not be turned into a blanket rule for every symptomatic patient.
Children's dosing requires an accurate weight and a formulation they can take safely; adult tablet arithmetic is not enough. WHO's inclusion of children aged 2 years and older in preventive chemotherapy does not make every product licensed for every younger age in every country, and our discussion of children's interpretation limits explains why pediatric results need age-specific clinical oversight.
A history of seizures, possible cysticercosis, significant liver disease or neurological symptoms should be reviewed before treatment. For 1 person with a straightforward travel-acquired infection, routine outpatient prescribing may be appropriate; another with possible central nervous system involvement may need specialist planning because the immune response to parasite treatment can itself affect symptoms.
Why can Schistosoma IgG stay positive after successful treatment?
Schistosoma IgG can remain positive for years after successful treatment and is not a reliable test of cure. CDC recommends considering repeat stool or urine examination 1–2 months after treatment when eggs were detected before treatment; follow-up must match the evidence used to establish infection and the person's subsequent clinical course.

A positive IgG result 6 months after treatment does not, by itself, demonstrate treatment failure. Antibody decline varies, and a stable or temporarily higher signal cannot reliably quantify surviving worms; comparing results from 2 different laboratories adds assay differences, making numerical trend interpretation even less suitable for declaring cure.
Persistent symptoms or eosinophilia deserve reassessment, but neither automatically proves living Schistosoma remain. If eggs are still found at the 1–2 month follow-up, specialists may consider egg viability, collection details, treatment timing and whether another course is needed; PCR positivity can also require caution because detecting parasite DNA is not the same as identifying viable adult worms.
Kantesti can help organize 3 follow-up dates—treatment, specimen collection and any re-exposure—without labeling persistent IgG as treatment failure. Our pandhuan analisis tren obat explains why trends must be matched to the right clinical endpoint; an available validated antigen assay may be more useful than serial antibodies, but its follow-up schedule belongs to the treating service.
How can the same positive result lead to different decisions?
The same positive Schistosoma IgG result can lead to treatment, additional testing or observation because the surrounding evidence differs. The following 4 examples are hypothetical teaching scenarios—not patient encounters—and illustrate how exposure dates, prior therapy, assay uncertainty and organ findings can outweigh the apparent simplicity of a positive flag.
A hypothetical 28-year-old returns from a freshwater swim, tests positive 10 weeks later and has never received praziquantel; treatment may be reasonable despite negative microscopy. A hypothetical 44-year-old treated appropriately 4 years earlier, with no further exposure and no concerning findings, may not need retreatment; the timeline of laboratory results helps keep these histories distinct.
A hypothetical 35-year-old with no plausible freshwater exposure has a weakly positive screening assay and normal supporting investigations. The next step may be checking the original indication, assay and cross-reactivity rather than immediate treatment; changing a report from weak positive to strong positive on 1 repeat antibody assay still does not create a documented exposure or prove active infection.
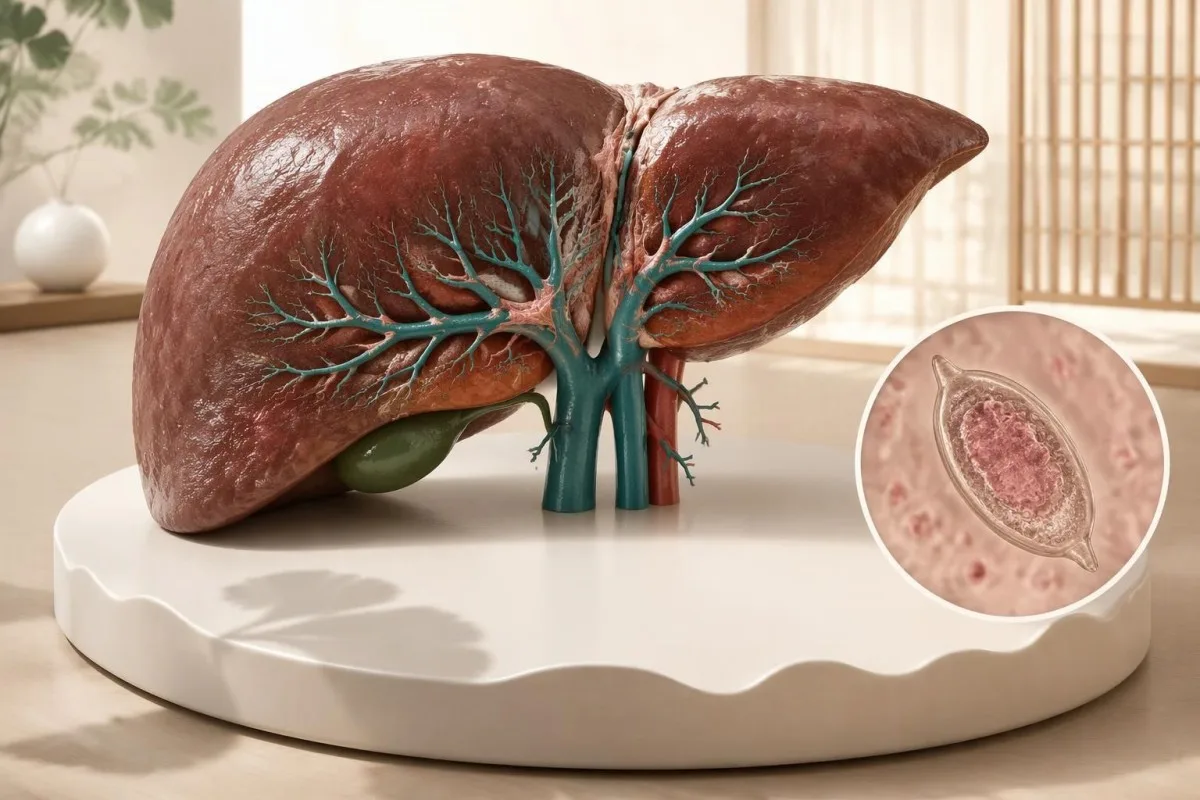
A hypothetical 54-year-old who lived near endemic freshwater 20 years earlier has positive IgG, an enlarged spleen and an ALT of 24 IU/L within the local range. That combination merits assessment for portal and other organ disease despite normal enzymes; an old exposure is not automatically resolved, and common liver fibrosis scores should not be assumed validated for schistosomal periportal fibrosis.
What should you bring to follow-up, and which sources support care?
Bring your exposure history, complete laboratory report and treatment record to a clinician experienced in travel medicine, infectious diseases or tropical medicine. Prepare 3 questions: whether the result fits your exposure, which direct tests could change the decision and how treatment response will be assessed without relying on antibody disappearance.

Your report should retain the assay name, units or index, reference interpretation and collection date, rather than only a cropped positive flag. Add 1 concise exposure timeline, previous praziquantel doses and dates, current medicines, pregnancy status where relevant and any urinary or neurological symptoms; this makes uncertainty visible and reduces the chance of repeating an uninformative antibody test.
Kantesti is an AI blood test interpretation platform that helps explain why 1 Schistosoma antibody result must be considered alongside exposure and treatment history, not used as a prescribing instruction. Our kerangka validasi klinis describes methodology and oversight, while our privasi lan pangolahan data information explains how to review data choices before sharing a travel or laboratory record.
The 2 Zenodo publications below describe Kantesti's validation framework and aggregate platform reporting; they are not clinical schistosomiasis guidelines and do not establish the sensitivity of a Schistosoma assay. Clinical recommendations in this article draw on CDC diagnostic and treatment guidance and the WHO guideline (2022), with our standar konten medis distinguishing published evidence, hypothetical calculations and the limits of AI-supported explanation.
Pitakon sing kerep ditakoni
Apa asil Schistosoma IgG positif tegese aku kena infeksi aktif?
Asil Schistosoma IgG positif ora bisa mbedakake kanthi andal infeksi aktif saka infeksi sing wis tau diobati. Antibodi bisa tetep bisa dideteksi nganti pirang-pirang taun, mula 1 laporan positif kudu ditafsirake kanthi nimbang paparan banyu tawar lan riwayat perawatan. Klinisi bisa nggunakake mikroskopi tinja utawa cipratan, tes antigen utawa PCR yen cocog kanggo entuk bukti sing luwih langsung. Paparan sing bisa dipercaya tanpa perawatan sadurunge sing cukup bisa dadi alasan kanggo menehi perawatan sanajan asil mikroskopi negatif.
Apa aku bisa kena skistosomiasis senajan asil tes tinja lan cipratan urin negatif?
Mikroskopi tinja utawa urin sing negatif ora nyingkirake kemungkinan skistosomiasis, mliginé sawisé lelungan nalika beban parasit bisa uga sithik. CDC nyaranaké mriksa 3 sampel sing diklumpukaké ing dina-dina sing béda amarga pangeluaran endhog bisa ora ajeg. Spesies sing dicurigai uga nemtokaké apa tinja, urin utawa loro-loroné sing kudu dipriksa. Klinisi isih bisa nyaranaké perawatan nalika antibodi positif, paparan bisa dipercaya lan ora ana cathetan terapi sadurungé sing cukup.
Pira suwene sawisé kena banyu tawar aku kudu tes?
CDC nyaranake nglumpukake sampel antibodi Schistosoma paling ora 6–8 minggu sawisé diduga kena infeksi anyar. Gunakna kontak pungkasan karo banyu tawar minangka patokan praktis nalika ana sawetara paparan sajrone lelungan. Asil negatif sing luwih awal bisa uga kudu dipriksa manèh amarga antibodi bisa uga durung bisa dideteksi. Demam utawa gejala wigati liyané mbutuhake pemeriksaan kanthi cepet, aja ngenteni nganti wektu tes iki.
Yagene aku isih positif antibodi Schistosoma sawisé praziquantel?
0 Antibodi Schistosoma bisa tetep positif nganti pirang-pirang taun sawisé pengobatan praziquantel kasil amarga respons imun luwih suwé tinimbang parasit. Asil positif 6 wulan sawisé pengobatan ora kanthi otomatis mbuktekake pengobatan gagal utawa dadi alesan kanggo pengobatan kaping pindho. Yen endhog dideteksi sadurungé pengobatan, klinisi bisa njaluk pemeriksaan tinja utawa urin maneh 1–2 wulan sawisé kuwi. Pajanan anyar, gejala sing tetep ana lan temuan tes langsung luwih informatif tinimbang antibodi sing tetep ana waé.
Pira dosis praziquantel sing digunakake kanggo schistosomiasis?
0. CDC nyathet praziquantel 40 mg/kg sajrone 1 dina kanthi 2 dosis sing dipérang kanggo S. mansoni, S. haematobium lan S. intercalatum. Regimen sing kacathet kanggo S. japonicum lan S. mekongi yaiku 60 mg/kg sajrone 1 dina kanthi 3 dosis sing dipérang. Yen ora, wong sing lelungan lan kondhisiné stabil umume diobati paling ora 6–8 minggu sawisé paparan banyu tawar pungkasan amarga praziquantel paling efektif tumrap cacing diwasa. Klinisi kudu milih regimen lan mriksa obat-obatan, meteng, umur lan kemungkinan keterlibatan neurologis.
Apa asil tes antibodi Schistosoma sing positif bisa dadi positif palsu?
0 Schistosoma антинбодийн шинжилгээ нь ашигласан сорилоос хамааран хуурамч эерэг гарах эсвэл бусад шимэгчийн эсрэг антинбиетэй харилцан урвалд орж болно. Идэвхтэй халдварыг батлах түгээмэл индексийн утга гэж байхгүй бөгөөд 2 лаборатори өөр өөр антиген бэлдмэл, босго утга ашиглаж болно. Цэнгэг устай харьцсан байх магадлалгүй үед сул эерэг хариу гарвал лабораториор хянуулах эсвэл өөр баталгаажуулах арга хэрэглэх шаардлагатай байж болно. Зөвхөн антинбодийн шинжилгээг давтах нь өмнө эмчлүүлсэн халдварыг амьд хорхойноос найдвартай ялгаж чадахгүй.
Entuk penjelasan babagan asil tes getih sampeyan
Unggah laporan laboratorium sampeyan lan AI Kantesti bakal nerangake saben biomarker nganggo basa sing prasaja sajrone sawetara detik. Digunakake luwih saka 2 yuta wong ing saindenging donya.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). Clinical Validation Framework v2.0 (Halaman Validasi Medis). Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2.5M Tes Didhaptar | Laporan Kesehatan Global 2026. Riset Medis AI Kantesti. DOI
- Pusat Kontrol lan Pencegahan Penyakit (2024). Clinical Testing and Diagnosis for Schistosomiasis. CDC Schistosomiasis Clinical Guidance.
- Pusat Kontrol lan Pencegahan Penyakit (2024). Clinical Care of Schistosomiasis. CDC Schistosomiasis Clinical Guidance.
- World Health Organization (2022). WHO guideline on control and elimination of human schistosomiasis. World Health Organization Guidelines.
- 2M+Tes sing dianalisis
- 127+negara-negara
- 100+Basa
Babagan tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis sing dipimpin dokter babagan alur kerja interpretasi lab.
Keahlian
Fokus kedokteran laboratorium babagan carane biomarker tumindak ing konteks klinis.
Kewibawaan
Ditinjau sacara medis dening Dr. Thomas Klein, kanthi kontribusi saka Dr. Sarah Mitchell lan Prof. Dr. Hans Weber.
Kapercayan
Interpretasi adhedhasar bukti kanthi tindak lanjut sing cetha kanggo nyuda rasa kaget.






Sanggahan medis
Artikel iki mung kanggo tujuan edukasi lan ora dadi saran medis. Tansah konsultasi karo panyedhiya layanan kesehatan sing mumpuni kanggo keputusan diagnosis lan perawatan.
Diterbitake · Hubungi tim editorial
Diterbitake dening Kantesti Ltd, kadhaptar ing Inggris & Wales, nomer perusahaan. 17090423, London, Britania Raya.
