
Ang mababang aktibidad ng antitrombin ay hindi awtomatikong nangangahulugan ng minanang kakulangan: maaaring pansamantalang bumaba ito dahil sa isang matinding pamumuo ng dugo, heparin, malubhang karamdaman o pagkawala ng protina. Kinukumpirma ng mga clinician ang nagpapatuloy na mga abnormalidad sa pamamagitan ng pagsusuri ng aktibidad na isinagawa sa angkop na panahon, kung minsan ay pagsusuri rin ng antigen, at isang plano sa laboratoryo na isinasaalang-alang ang mga iniinom na gamot—kadalasan pagkatapos ng unang 3 buwan ng paggamot sa pamumuo ng dugo.

Mahahalagang punto
- Saklaw ng Sanggunian: Karaniwang nasa 80–120% ang aktibidad ng antitrombin sa mga adulto; gamitin ang saklaw na nakasaad sa sarili mong ulat.
- Isang mababang resulta: Hindi sapat ang aktibidad na 65% habang may bagong pamumuo ng dugo o ginagamot ng heparin upang matukoy ang minanang kakulangan sa antitrombin.
- Timing ng pag-uulit: Inirerekomenda ng British Society for Haematology na suriin ang mga kakulangan sa mga natural na anticoagulant pagkatapos lamang ng 3 buwan ng anticoagulation para sa acute thrombosis.
- Aktibidad kumpara sa antigen: Karaniwang bumababa ang dalawang sukat sa Type I deficiency; bumababa naman ang paggana sa Type II deficiency habang maaaring manatiling normal ang antigen.
- Pakikialam ng gamot: Maaaring magdulot ang apixaban, rivaroxaban at edoxaban ng maling pagtaas ng aktibidad sa mga pagsusuring batay sa factor Xa; gayon din ang maaaring gawin ng dabigatran sa mga pagsusuring batay sa thrombin.
- Pagkawala ng protina: Karaniwang hindi bababa sa 3.5 g kada 24 na oras ang proteinuria na nasa saklaw ng nephrotic sa mga nasa hustong gulang at maaari itong mag-ambag sa nakuhang pagbaba ng antithrombin.
- Pagsusuri sa pamilya: Sa kumpirmadong heterozygous na minanang kakulangan, karaniwang may 50% na posibilidad ang bawat anak na mamanahin ang kaugnay na variant—hindi 50% na katiyakang magkakaroon ng namuong dugo.
- Kaligtasan ng gamot: Huwag kailanman ihinto ang anticoagulation upang makakuha ng mas malinis na resulta sa laboratoryo nang walang indibiduwalisadong plano mula sa nagreseta ng gamot.
Ano nga ba ang ibig sabihin ng mababang aktibidad ng antitrombin?
Mababang aktibidad ng antithrombin ay nangangahulugang natukoy sa pagsusuri sa laboratoryo ang mas mababang paggana ng anticoagulant kaysa sa inaasahan; hindi nito, sa ganang sarili, tinutukoy ang sanhi. Ang resultang mas mababa sa pinakamababang limitasyon ng laboratoryo para sa mga nasa hustong gulang—kadalasang nasa 80%—ay maaaring sumalamin sa minanang kakulangan, pansamantalang pagkonsumo, nabawasang produksiyon, pagkawala ng protina o problema sa pagsusuri.

Nililimitahan ng antithrombin ang pamumuo ng dugo sa pamamagitan ng pagpigil sa mga enzyme kabilang ang thrombin, na tinatawag ding factor IIa, at factor Xa. Inilalarawan ng resulta ng aktibidad na 60% ang paggana kaugnay ng pamantayan sa kalibrasyon ng pagsusuri; hindi ito nangangahulugang 60% ang proteksiyon ng iyong sirkulasyon o 40% ang posibilidad mong magkaroon ng namuong dugo.
Hindi inaalis ng normal na karaniwang panel ng pagsusuri sa pamumuo ng dugo ang posibilidad ng kakulangan sa antithrombin, dahil hindi mga pagsusuri sa pag-screen para sa bawat minanang tendensiyang mamuo ang PT at aPTT. Ipinapaliwanag ng aming mga limitasyon ng normal na panel ng pamumuo ng dugo kung paano pag-ibahin ang mga tanong na ito: kung mahaba ang mga oras ng pamumuo at kung normal na gumagana ang isang partikular na likas na anticoagulant ay 2 magkaibang pagsusuri.
Ang Kantesti ay isang AI analyzer ng pagsusuri sa dugo na tumutulong na isaalang-alang ang porsiyento ng aktibidad kasabay ng kasaysayan ng paggamit ng gamot at mga kaugnay na resulta sa laboratoryo, sa halip na ituring ang 1 abnormal na flag bilang diagnosis. Ipinapaliwanag ng aming pinagmulan at layunin ng kompanya ang papel na iyon; kailangan pa rin ng kumpirmasyong pinangungunahan ng clinician para sa minanang kakulangan, at kailangang masuri nang hiwalay ang mga agarang sintomas anuman ang interpretasyon ng AI.
Anong saklaw ng aktibidad ng antitrombin ang itinuturing na mababa?
Aktibidad ng antithrombin sa mga nasa hustong gulang ay karaniwang may saklaw na sanggunian na tinatayang 80–120%, bagaman gumagamit ang ilang laboratoryo ng 80–130% o ibang napatunayang saklaw. Samakatuwid, madalas na bahagyang mababa ang aktibidad na 75%, ngunit hindi pinatutunayan ng 75% o ng anumang iba pang iisang hangganan ang minanang kakulangan o itinatakda ang pang-emerhensiyang paggamot.

Maraming taong may heterozygous na minanang kakulangan sa antithrombin ang may aktibidad na nasa humigit-kumulang 40–70%, ngunit maaari ring magdulot ng gayong mga halaga ang mga nakuhang kondisyon. Sa kabaligtaran, ang ilang minanang variant ay nagdudulot ng mas banayad na pagbaba o hindi natutukoy ng ilang partikular na pagsusuri; binibigyang-kahulugan ng mga clinician ang tindi ng pagbaba kasama ng mga inuulit na resulta, hindi bilang nag-iisang palatandaang henetiko.
Malaki ang epekto ng edad sa interpretasyon: ang mga malulusog na bagong silang na ipinanganak sa takdang panahon ay maaaring magkaroon ng aktibidad ng antithrombin na humigit-kumulang 40–60% ng mga halaga sa nasa hustong gulang, at tumataas ang mga antas habang sanggol pa. Nagdudulot ng dagdag na pagkakaiba-iba ang pagiging kulang sa buwan, at maaari ring makaapekto sa mga resulta ang huling bahagi ng pagbubuntis o ang maagang panahon pagkatapos manganak; maaaring magbigay ng mapanlinlang na label ang walang-pinipiling paggamit ng pinakamababang limitasyong 80% para sa nasa hustong gulang.
Bilang isang malinaw na kathang-isip na halimbawa, nangangailangan ng ibang pagsusuri ang isang nasa hustong gulang na maayos naman ang kalusugan, may aktibidad na 78% at walang dating namuong dugo, kaysa sa isang nasa hustong gulang na may 42% habang may malubhang sepsis. Maaaring magpakita ng parehong mababang flag ang dalawang ulat, ngunit ipinapaliwanag ng aming gabay sa mga resulta ng laboratoryo na labas sa saklaw kung bakit hindi mapagpapalit ang mga hangganan ng sanggunian at ang mga hangganan para sa diagnosis o paggamot.
| Antas | Saklaw | Kahulugan |
|---|---|---|
| Karaniwang saklaw para sa nasa hustong gulang | Tinatayang 80–120% | Karaniwang nasa saklaw, ngunit mas matimbang ang sariling saklaw ng laboratoryo at ang sensitivity ng pagsusuri. |
| Bahagyang pagbaba | 70–79% | Often warrants context review and appropriately timed confirmation; not a diagnosis. |
| Clear reduction | 50–69% | Compatible with inherited or acquired deficiency; activity alone cannot distinguish them. |
| Malaking pagbaba | Below 50% | Requires clinical review, especially during illness or thrombosis; the percentage alone does not establish an emergency. |
Antigen kumpara sa aktibidad ng antitrombin: ano ang pagkakaiba?
Isang antithrombin activity test measures how effectively the protein inhibits a coagulation enzyme, while antithrombin antigen measures how much protein is present. Type I inherited deficiency generally lowers both; type II generally lowers activity despite a relatively normal antigen concentration, making these 2 tests complementary rather than interchangeable.

Most routine activity methods are chromogenic assays: the laboratory adds an enzyme and measures how much remains after antithrombin has inhibited it. The ISTH laboratory recommendations favor activity testing first, followed by antigen measurement when activity is low, with exclusion of acquired causes and assay interference before classification (Van Cott et al., 2020).
Consider 2 hypothetical repeat profiles obtained under suitable conditions: activity 52% with antigen 49% supports a quantitative pattern, whereas activity 52% with antigen 101% supports a qualitative pattern. These examples are not diagnostic formulas, because acquired illness can lower both measurements and antigen assays do not explain whether a functional result was distorted by medication.
Type II deficiency includes reactive-site, heparin-binding-site and other functional abnormalities; the choice of assay can change how readily a variant is detected. Kantesti’s explanations therefore distinguish quantity from performance, a distinction also illustrated by protein level versus function in C1 esterase inhibitor testing—but those are different proteins with different clinical consequences.
Maaari bang pansamantalang magpababa ng antitrombin ang isang matinding pamumuo ng dugo?
Acute thrombosis can temporarily reduce antithrombin activity through consumption, particularly when accompanied by illness, procedures or treatment effects. A value such as 58% during a newly diagnosed deep vein thrombosis therefore cannot reliably distinguish an inherited baseline deficiency from a reduction caused by the current event.
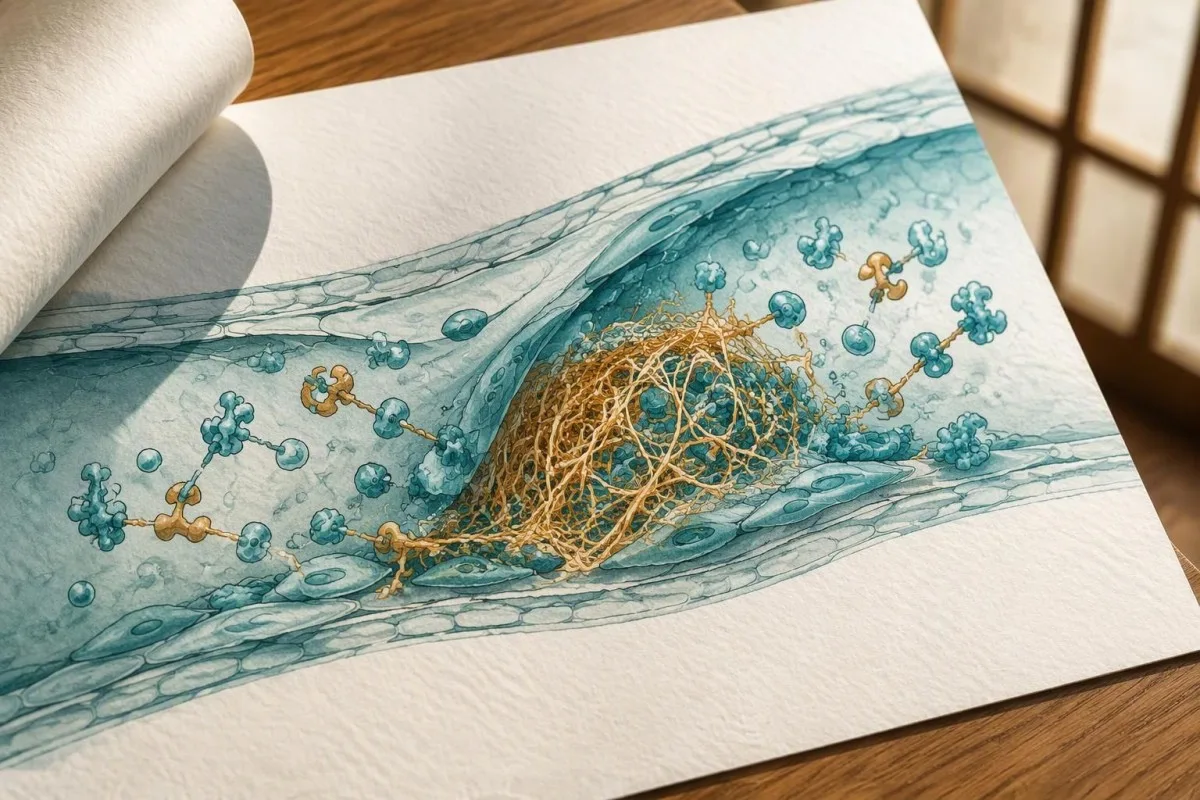
The British Society for Haematology recommends testing deficiencies of natural anticoagulants only after 3 months of anticoagulation for acute thrombosis, because early results are unreliable and rarely change immediate management (Arachchillage et al., 2022). This is a recommendation about diagnostic timing, not an instruction to delay treating a suspected clot or to stop anticoagulants at month 3.
A hypothetical patient has activity of 61% during a pulmonary embolism and 96% after recovery using an appropriate assay. That change supports a temporary reduction, but comparing 2 percentages remains incomplete unless the clinician knows whether heparin, a direct oral anticoagulant, replacement products or different laboratory methods affected either measurement.
D-dimer answers a different question: it reflects fibrin formation and breakdown, not antithrombin quantity or inherited status. Our clotting tests and D-dimer guide explains why an elevated D-dimer and low activity can occur together during 1 acute event without proving that the low antithrombin caused the clot.
Bakit maaaring magpababa ng aktibidad ng antitrombin ang paggamot na heparin?
Heparin can lower circulating antithrombin during treatment, so a low result obtained while receiving unfractionated or low-molecular-weight heparin may reflect an acquired reduction. Heparin also depends on antithrombin for much of its anticoagulant effect; activity of 50% during treatment can therefore raise both diagnostic and medication-monitoring questions.

Reduced antithrombin can contribute to apparent heparin resistance, but an unexpectedly high dose requirement does not prove inherited deficiency. During 1 episode of severe illness, increased factor VIII or fibrinogen may shorten aPTT-based impressions of anticoagulation even when heparin exposure is adequate, so clinicians may reassess the monitoring method rather than simply escalate treatment.
Some heparin anti-Xa assays add exogenous antithrombin and others do not; this difference can affect what the result says about heparin concentration versus its activity in the patient. Ask the laboratory about 2 separate methods—the antithrombin activity assay and the heparin monitoring assay—because their handling of antithrombin and heparin is not necessarily identical.
A platelet fall of more than 50% during heparin exposure raises a separate possibility, heparin-induced thrombocytopenia, which is not diagnosed by low antithrombin. Our explanation of PF4 testing and HIT assessment describes that distinction; decisions about changing heparin, using replacement antithrombin or scheduling a repeat require the treating team, not a self-directed medication pause.
Paano nagpapababa ng antitrombin ang malubhang karamdaman at DIC?
Sepsis, disseminated intravascular coagulation and major physiological stress can reduce antithrombin through consumption, impaired production and altered distribution. A markedly low result—for example, 35%—during critical illness is often an acquired finding; it cannot be used alone to label someone with lifelong hereditary antithrombin deficiency.

DIC is assessed from a pattern, not 1 abnormal protein: falling platelets, prolonged PT, increased fibrin-related markers and sometimes reduced fibrinogen provide the relevant context. Fibrinogen may initially remain normal or elevated because it is an acute-phase protein, so a preserved fibrinogen concentration does not automatically rule out evolving consumption.
For a hypothetical example, activity of 38%, platelets of 72 × 10^9/L and worsening PT during a major systemic illness point toward an acquired coagulation disturbance rather than an isolated inherited finding. Our DIC laboratory pattern explanation shows why trends across several measurements are more informative than repeatedly checking antithrombin while the illness remains active.
Recent antithrombin concentrate or plasma treatment can raise measured activity and obscure the underlying baseline, adding a second source of uncertainty during the same hospital stay. A result of 105% after replacement does not exclude inherited deficiency, just as 35% before recovery does not prove it; document the product and timing before interpreting either percentage.
Maaari bang magdulot ng mababang aktibidad ng antitrombin ang pagkawala ng protina sa bato?
Heavy urinary protein loss can contribute to acquired antithrombin reduction, particularly in nephrotic syndrome. Adult nephrotic-range proteinuria is conventionally at least 3.5 g per 24 hours; clinicians interpret antithrombin alongside urine protein, serum albumin and the underlying kidney disorder, rather than relying on creatinine or eGFR alone.
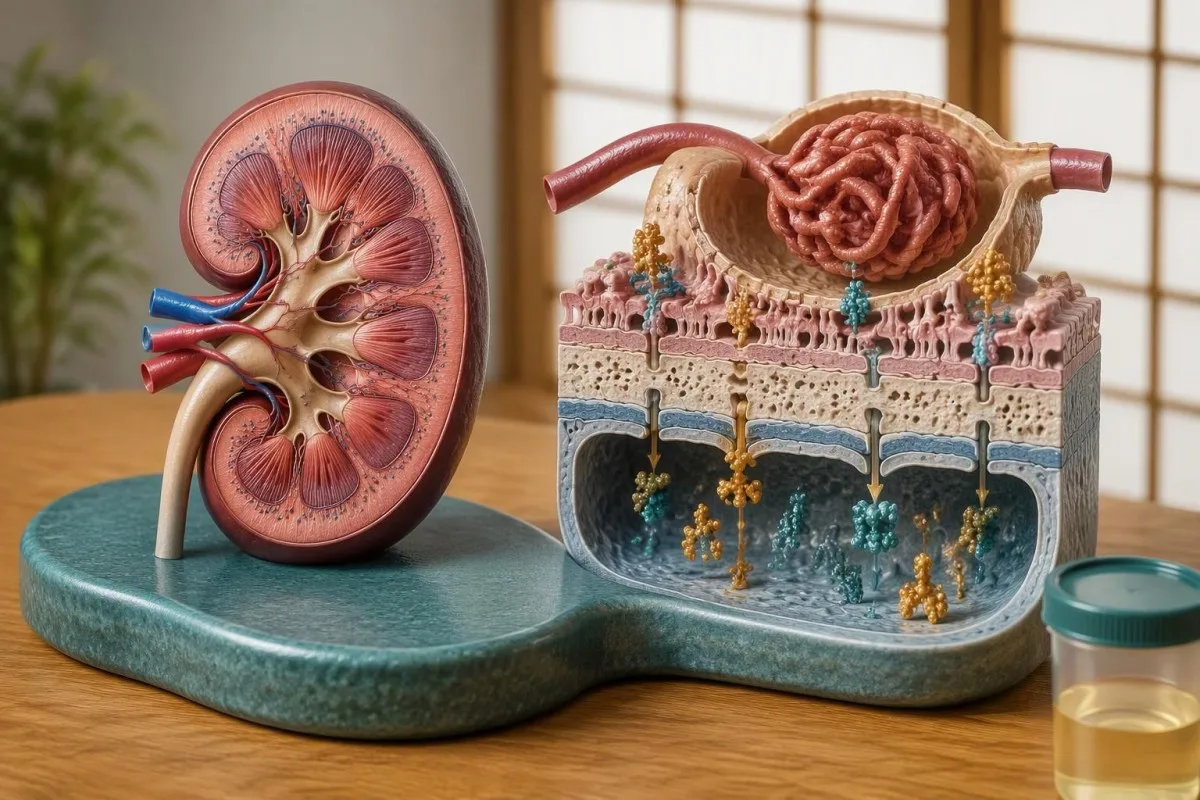
A normal eGFR does not exclude substantial protein leakage through the glomerular filtration barrier. For example, an adult with eGFR 95 mL/min/1.73 m², albumin 22 g/L and urine protein 6 g per day may have a strong acquired explanation for low activity despite apparently reassuring filtration results; persistent bula sa ihi at pagsusuri ng protina deserve assessment in that context.
The relationship between nephrotic syndrome, antithrombin levels and clot risk is not uniform: not every person with nephrotic syndrome has low antithrombin, and the thrombotic tendency involves more than urinary loss of 1 protein. Underlying diagnosis matters, including membranous nephropathy, where PLA2R results and kidney monitoring help explain the kidney process rather than prove an inherited clotting disorder.
Kantesti is an AI blood test interpretation platform that can organize an antithrombin percentage alongside albumin and kidney markers, but it cannot infer the amount of urinary protein from eGFR alone. If activity remains 62% while heavy protein loss continues, repeat testing may still describe the acquired condition; the cleaner inherited assessment usually follows clinical stabilization and improvement of that competing explanation.
Maaari bang magpababa ng antitrombin ang sakit sa atay o iba pang paggamot?
Reduced liver synthesis can lower antithrombin, especially in advanced liver disease, while certain treatments such as L-asparaginase can also cause acquired reductions. An activity of 55% alongside other abnormalities requires review of protein production, protein loss and treatment history before clinicians consider a genetic explanation.
ALT and AST reflect injury more than protein-making capacity, so normal or mildly elevated enzymes do not guarantee normal antithrombin production. If activity is 57%, albumin is 25 g/L and INR is 1.6, impaired synthesis becomes a possibility—but warfarin, nutrition and protein loss can confound that pattern, as our gabay sa interpretasyon ng liver test na nagpapaliwanag.
Albumin cannot serve as a substitute antithrombin test because the 2 proteins have different turnover and can respond differently to illness or therapy. Our albumin and serum protein guide helps interpret the surrounding panel; a normal albumin does not exclude inherited antithrombin deficiency, and a low albumin does not prove that the liver caused it.
L-asparaginase can reduce anticoagulant proteins during cancer treatment, creating an acquired thrombosis risk that may need active management rather than merely a future repeat test. Major procedures, extracorporeal support and recent replacement products can also complicate 1 measurement; eating more protein or taking a vitamin supplement does not correct a SERPINC1-related defect or replace treatment of the underlying acquired cause.
Aling mga anticoagulant ang nakaaapekto sa pagsusuri ng antitrombin?
Direct oral anticoagulants can falsely increase antithrombin activity, potentially masking deficiency rather than causing a low flag. Apixaban, rivaroxaban and edoxaban interfere with factor Xa-based activity assays, while dabigatran can interfere with thrombin-based assays; the same patient’s 2 results may therefore differ because of assay design.

The mechanism is straightforward: the medication inhibits the assay’s added enzyme, and the instrument can misread that inhibition as stronger antithrombin function. The ISTH communication explicitly identifies these drug–assay combinations, including effects from direct thrombin inhibitors such as argatroban and bivalirudin (Van Cott et al., 2020); antigen testing usually avoids this particular functional interference, but does not replace an activity assessment.
A hypothetical activity of 108% on a factor Xa-based assay while taking rivaroxaban may conceal an underlying reduction; activity of 66% on that same drug still cannot be mathematically corrected into a true baseline. Anticoagulants also affect lupus anticoagulant test interpretation, but the direction and mechanism of interference are test-specific, not a universal rule for all thrombophilia assays.
Kantesti AI should support medication-aware interpretation rather than claim that 1 uploaded report identifies the laboratory’s reagent or removes a drug effect. Depending on the situation, the laboratory may use a less-affected assay, measure drug exposure or apply a validated removal procedure; our teknikal na pagbe-validate at pangangasiwa describes the broader standards behind interpretation, not a guarantee that AI can resolve missing assay information.
Maaari bang ipaliwanag ng paghawak sa sample ang hindi inaasahang mababang resulta?
Sample quality and assay differences can make antithrombin results unreliable, especially when the laboratory flags collection or processing problems. Coagulation samples typically require a 9:1 ratio of sample to citrate anticoagulant; underfilling, inappropriate handling or an unsuitable specimen should be considered before interpreting an isolated abnormal percentage.
A hematocrit above approximately 55% may require citrate adjustment for coagulation testing because the amount of plasma relative to citrate is reduced. This is a laboratory preparation issue, not evidence of hereditary deficiency; if activity is 73% in a flagged specimen, ask whether the laboratory accepted the sample as valid and whether recollection is preferable to repeating the same material.
Hemolysis, lipemia and marked discoloration can interfere with optical methods, although the effect depends on the instrument and reagent rather than having 1 predictable direction. Our guides to hemolysis-related result distortion at lipemic specimens and redraws explain why a specimen-quality warning needs a method-specific answer instead of an automatic diagnosis.
Changing laboratories can create a second problem: an activity of 76% by one method and 84% by another may reflect analytical differences rather than biological recovery. Using the same laboratory helps trend comparison, but persistent clinical suspicion may justify a specialist laboratory using an alternative assay that is more sensitive to certain inherited variants; consistency and diagnostic sensitivity are 2 different goals.
Kailan dapat ulitin ang pagsusuri ng mababang aktibidad ng antitrombin?
Repeat antithrombin testing should occur after temporary causes have settled and medication effects have been addressed. Following an acute clot, the BSH recommendation is to wait until after 3 months of anticoagulation before testing natural anticoagulant deficiencies; the safest collection date then depends on the drug, assay and clinical situation.

An incidental borderline result in a well adult without a recent clot does not automatically require the same 3-month wait, because that interval addresses acute thrombosis. The clinician may instead arrange a separate repeat once collection issues and acquired causes are reviewed, adding antigen testing if activity remains low; there is no universally validated waiting interval that fits every outpatient finding.
Heparin-related reductions may recover after treatment ends, but laboratory policies and ongoing illness affect when a repeat becomes meaningful. For a DOAC, a fixed 48-hour pause is not universally adequate or safe: kidney function, dose timing, drug accumulation and assay sensitivity matter, and choosing a compatible method may avoid interrupting treatment entirely.
Kantesti’s trend tools can help organize 2 measurements with their dates, but a timeline should also record clot onset, heparin exposure, the last relevant medication dose and any replacement products. Our explanation of mga resulta pagkatapos ng paglabas mula sa ospital supports that workflow; warfarin does not usually lower antithrombin as it lowers vitamin K-dependent proteins, so protein C or S stopping rules should not be copied automatically.
Anong mga resulta ng pagsusuri ang sumusuporta sa minanang kakulangan sa antitrombin?
Inherited antithrombin deficiency becomes more likely when activity remains low on separate, interpretable samples, acquired causes are excluded and the personal or family history fits. Two concordant results provide stronger evidence than 1 result during illness, but activity, antigen and sometimes SERPINC1 testing must still be considered together.

A clearly hypothetical profile of activity 54% and 56% on 2 suitable occasions, antigen 51%, no major protein loss and a first-degree relative with confirmed deficiency would support a quantitative inherited pattern. Early or recurrent venous thrombosis increases suspicion, but age alone is not diagnostic, and absence of a family history does not exclude a new variant or previously unrecognized disease.
SERPINC1 testing can help establish a molecular explanation when the laboratory phenotype is convincing and the result could affect management or family counseling. A variant of uncertain significance is not equivalent to a diagnosis, while a negative genetic test does not necessarily exclude every relevant change; the ISTH recommendations also note that molecular testing may identify defects missed by activity assays (Van Cott et al., 2020).
Antithrombin and protein S deficiency require different interpretive rules, even when they appear on the same thrombophilia panel. Our guide to low protein S activity explains several contrasting confounders; a type II antithrombin heparin-binding-site variant can also have a different risk profile from type I deficiency, so 1 generic risk estimate should not be applied to all confirmed variants.
Kailan nararapat suriin ang mga kapamilya?
Family evaluation is usually considered after the original patient’s inherited deficiency is convincingly confirmed, especially when the result could change prevention, hormone choices or pregnancy planning. Most inherited antithrombin deficiency is autosomal dominant, giving each child of a heterozygous carrier a 50% chance of inheriting the relevant variant—not a certainty of thrombosis.

The BSH guideline discourages routine thrombophilia testing of all first-degree relatives but supports selective evaluation for relatives of people with antithrombin, protein C or protein S deficiency when results could influence management (Arachchillage et al., 2022). Our gabay sa pagsubok ng pamilya batay sa panganib explains why testing 1 relevant inherited condition can be more useful than ordering a broad panel without a clinical question.
ASH’s 2023 thrombophilia guideline similarly supports selective testing in certain families with known high-risk deficiencies, including decisions about estrogen exposure and prophylaxis during particular risk situations (Middeldorp et al., 2023). Many recommendations are conditional and based on very low-certainty evidence; antithrombin deficiency should not be treated as interchangeable with factor V Leiden results, which often carry a different risk profile.
Kantesti’s Family Health Risk feature can help organize information shared with consent, but it cannot determine whether a relative inherited a SERPINC1 variant from 1 family member’s activity percentage. Testing children requires age-aware laboratory interpretation and an assessment of whether the result would change care now; predictive testing also deserves counseling about privacy, uncertainty and the difference between inherited susceptibility and an actual clot.
Ano ang dapat isama sa plano ng follow-up at pagsusuri ng mga sanggunian?
Bring the original percentage, reference interval, medication list and sampling date to follow-up, along with details of the clot, illness or protein loss that could explain the result. Two decisions come first: whether the current finding needs clinical action and whether repeat testing would genuinely change treatment or family counseling.

A low activity percentage alone does not automatically require lifelong anticoagulation or antithrombin concentrate; treatment depends on previous thrombosis, the provoking circumstances, bleeding risk and the confirmed diagnosis. New one-sided leg swelling needs prompt assessment, while sudden shortness of breath, chest pain or fainting requires emergency care even if the last activity was 100%—do not wait for a repeat thrombophilia panel.
Kantesti is an AI lab test interpretation service that can help organize the 2-stage workflow of context review followed by clinician-directed confirmation, not replace hematology advice or authorize medication interruption. Our mga prinsipyo ng responsableng AI describe that boundary; use AI explanations to prepare precise questions, including which enzyme the assay uses and whether activity and antigen should be collected together.
The clinical recommendations here draw on 3 directly relevant external sources: the ISTH laboratory communication, the BSH testing guideline and the ASH thrombophilia guideline. The 2 Zenodo publications below provide background on serum proteins and immune-related laboratory context—not clinical trials validating antithrombin diagnosis; our mga pamantayan sa nilalamang medikal at pagsusuri sa complement at mga pagsusuring autoimmune help readers distinguish supporting education from condition-specific evidence.
Mga Madalas Itanong
Nangangahulugan ba palagi ng namamanang kakulangan ang mababang aktibidad ng antithrombin?
0 Mababang aktibidad ng antithrombin ay hindi palaging nangangahulugan ng minanang kakulangan. Maaaring magkaroon ng aktibidad na 60% habang may acute thrombosis, ginagamot ng heparin, malubhang karamdaman, malalang sakit sa atay o matinding pagkawala ng protina sa ihi. Sinusuri ng mga clinician kung nananatiling mababa ito sa magkakahiwalay at angkop ang pagkakakuha ng mga sample matapos isaalang-alang ang mga nakuhang sanhi na ito. Nakakatulong ang pagsusuri ng antigen at kung minsan ay ang pagsusuri sa SERPINC1 sa pagtukoy sa uri ng kumpirmadong abnormalidad.
Kailan dapat ulitin ang pagsusuri sa aktibidad ng antitrombin pagkatapos magkaroon ng namuong dugo?
Pagkatapos ng isang acute na namuong dugo, inirerekomenda ng British Society for Haematology na pagsusuri sa mga kakulangan sa natural na anticoagulant lamang pagkatapos ng 3 buwan ng anticoagulation. Dapat ding isaalang-alang sa aktuwal na plano ng pagkuha ng sample ang paggaling, ang ginagamit na anticoagulant, at ang pagsusuri sa laboratoryo. Hindi nangangahulugan ang rekomendasyong ito na dapat itigil ng lahat ang gamot pagkalipas ng 3 buwan. Huwag kailanman ihinto ang anticoagulation para sa pagsusuri nang walang tagubilin ng nagreseta ng gamot.
Ano ang pagkakaiba ng antithrombin antigen at aktibidad?
Sinusukat ng aktibidad ng antithrombin ang paggana nito, samantalang sinusukat ng antigen ng antithrombin ang dami ng protina. Karaniwang pinabababa ng kakulangan sa Type I ang parehong resulta; karaniwang pinabababa ng kakulangan sa Type II ang aktibidad kahit medyo normal ang antigen. Halimbawa, ang paulit-ulit na aktibidad na 52% na may antigen na 101% ay nagpapahiwatig ng kwalitatibong pattern, ngunit hindi nito pinatutunayan ang namamanang sanhi nang hindi sinusuri ang mga nakuhang kondisyon at epekto ng mga gamot. Hindi maaaring ipalit ang pagsusuri ng antigen sa wastong pagtatasa ng paggana.
Maaari bang makaapekto ang apixaban o rivaroxaban sa mga resulta ng antithrombin?
Maaaring magdulot ang apixaban at rivaroxaban ng maling pagtaas sa aktibidad ng antithrombin sa mga pagsusuring nakabatay sa factor Xa, na posibleng magkubli ng kakulangan. Gayundin, maaaring magpataas ang dabigatran sa ipinapakitang aktibidad sa mga pagsusuring nakabatay sa thrombin. Samakatuwid, maaaring hindi kasing-reassuring ng inaakala ang resultang 100% habang umiinom ng gamot na nakikialam sa pagsusuri. Maaaring pumili ang laboratoryo ng paraang hindi gaanong naaapektuhan o ng ibang napatunayang estratehiya; hindi ligtas ang kusang paghinto sa pag-inom ng gamot.
Mapanganib ba ang aktibidad ng antithrombin na 70%?
Ang antithrombin activity na 70% ay mas mababa kaysa sa maraming saklaw ng sanggunian ng laboratoryo para sa mga nasa hustong gulang, ngunit hindi sapat ang porsiyento lamang upang matukoy kung may emerhensiya o masukat ang personal na panganib ng pamumuo ng dugo. Nakadepende ang kahulugan nito sa pagsusuri, mga gamot, mga naunang pamumuo ng dugo, kasaysayan sa pamilya at kasalukuyang karamdaman. Karaniwang kailangan ng klinikal na pagsusuri ang isang hiwalay na resulta at plano para sa angkop na pagkumpirma. Nangangailangan ng pagsusuri ang biglaang paghingal, pananakit ng dibdib, pagkahimatay o bagong pamamaga sa isang panig ng binti, anuman ang porsiyentong iyon.
Dapat bang magpasuri ang aking pamilya kung mayroon akong kakulangan sa antitrombin?
Maaaring angkop ang piling pagsusuri sa pamilya matapos makumpirma nang may matibay na ebidensiya ang minanang kakulangan sa antithrombin, lalo na kung mababago ng mga resulta ang pag-iwas sa sakit, mga pagpipilian sa hormone, o pagpaplano ng pagbubuntis. Karaniwang may 50% posibilidad ang heterozygous na carrier na maipasa ang kaugnay na baryante sa bawat anak, ngunit hindi ito 50% katiyakan na magkakaroon ng trombosis ang anak. Sinusuportahan ng mga gabay ng BSH at ASH ang pagsusuring nakabatay sa mga desisyon sa halip na walang-piling pagsusuri sa bawat kamag-anak. Kailangan ng mga bata ng interpretasyong naaangkop sa kanilang edad at pagtalakay kung mababago ng pagsusuri ang pangangalaga sa kanila sa kasalukuyan.
Ipaliwanag sa iyo ang resulta ng blood test
I-upload ang iyong ulat sa laboratoryo at ipapaliwanag ng AI ng Kantesti ang bawat biomarker sa payak na pananalita sa loob ng ilang segundo. Ginagamit ng mahigit 2 milyong tao sa buong mundo.
Mga Sanggunian
- Klein, T., Mitchell, S., & Weber, H. (2026). Gabay sa Serum Protein: Pagsusuri ng Dugo para sa mga Globulin, Albumin at A/G Ratio. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Gabay sa pagsusuri ng dugo para sa C3 C4 Complement at ANA Titer. Kantesti AI Medical Research. DOI
- Van Cott EM et al. (2020). Recommendations for clinical laboratory testing for antithrombin deficiency; Communication from the SSC of the ISTH. Journal of Thrombosis and Haemostasis. DOI
- Arachchillage DJ et al. (2022). Pagsusuri para sa thrombophilia: Isang gabay ng British Society for Haematology. British Journal of Haematology. DOI
- Middeldorp S et al. (2023). Mga gabay ng American Society of Hematology noong 2023 para sa pamamahala ng venous thromboembolism: pagsusuri para sa thrombophilia. Blood Advances. DOI
- 2M+Mga sinuring pagsusuri
- 127+Mga bansa
- 100+Mga wika
Tungkol sa pangkat medikal


Mga Signal ng Tiwala ng E-E-A-T
Karanasan
Pinamumunuan ng manggagamot na klinikal na pagsusuri ng mga daloy ng interpretasyon ng mga pagsusuri sa laboratoryo.
Kadalubhasaan
Pokus sa laboratoryong medisina kung paano kumikilos ang mga biomarker sa kontekstong klinikal.
Pagka-awtoridad
Sinuri sa medikal na aspeto ni Dr. Thomas Klein, kasama ang mga kontribusyon nina Dr. Sarah Mitchell at Prof. Dr. Hans Weber.
Pagiging Mapagkakatiwalaan
Interpretasyong nakabatay sa ebidensya na may malinaw na mga susunod na hakbang upang mabawasan ang pag-aalarma.






Paunawang medikal
Ang artikulong ito ay para sa mga layuning pang-edukasyon lamang at hindi ito bumubuo ng medikal na payo. Palaging kumonsulta sa isang kwalipikadong tagapagbigay ng pangangalagang pangkalusugan para sa mga desisyon sa diagnosis at paggamot.
Inilathala · Makipag-ugnayan sa pangkat ng editoryal
Inilathala ng Kantesti Ltd, nakarehistro sa England at Wales, numero ng kumpanya. 17090423, London, United Kingdom.
