Sindrom PFAPA bisa nyebabake mriyang dhuwur sing bola-bali, kanthi sariawan, lara tenggorokan lan kelenjar gulu abuh, biasane suwene 3–7 dina kanthi mari kanthi tuntas ing antarane serangan. Diagnosis gumantung marang pola sing bola-bali lan panyingkiran panyebab liyane—dudu siji asil tes getih sing ora normal. Cathetan gejala migunani; episode sing ora lumrah abote utawa beda mbutuhake pambiji anyar.

Pokok-pokok penting
- Sindrom PFAPA umume nyebabake episode mriyang suwene 3–7 dina, dipisahake sawetara minggu nalika kahanane sehat.
- Gejala PFAPA kalebu sariawan aftosa, faringitis lan kelenjar getah bening servikal sing abuh; ora kabeh 3 pratandha kudu katon bebarengan.
- Wektu mriyang kerep manut siklus kira-kira 2–8 minggu, nanging keteraturan tanggalan sing pas ora dadi syarat diagnosis.
- Cathetan gejala kudu nyathet tanggal episode, suhu paling dhuwur ing °C utawa °F, gejala, obat-obatan lan pamulihan ing antarane serangan.
- Tes getih bisa nuduhake CRP lan neutrofil sing mundhak nalika serangan; CRP 80 mg/L ora mbedakake PFAPA saka infeksi.
- Neutropenia siklik bisa kambuh kira-kira saben 21 dina lan bisa mbutuhake pemeriksaan cacah getih serial, dudu mung siji asil CBC sing nyenengake.
- Keputusan perawatan bisa uga kalebu kortikosteroid resep klinisi, obat pencegahan utawa tonsilektomi; ora ana siji wae sing kudune ditindakake mung adhedhasar asil laboratorium.
- Evaluasi kanthi cepet dibutuhake kanggo bayi umur kurang saka 3 sasi sing suhu awaké 38°C utawa luwih, utawa bocah sing angel ambegan, responsé mudhun utawa ruam sing ora memucat nalika ditekan.
Apa kuwi sindrom PFAPA, lan apa sing nyebabake mriyang?
Sindrom PFAPA minangka kahanan autoinflamasi sing nyebabake episode demam bola-bali bebarengan karo sariawan aftosa, faringitis lan adenitis servikal. Serangan biasane suwéné 3–7 dina; bocah biasane bali menyang tingkat energi, napsu mangan lan tuwuh kembang sing normal ing antarane episode.
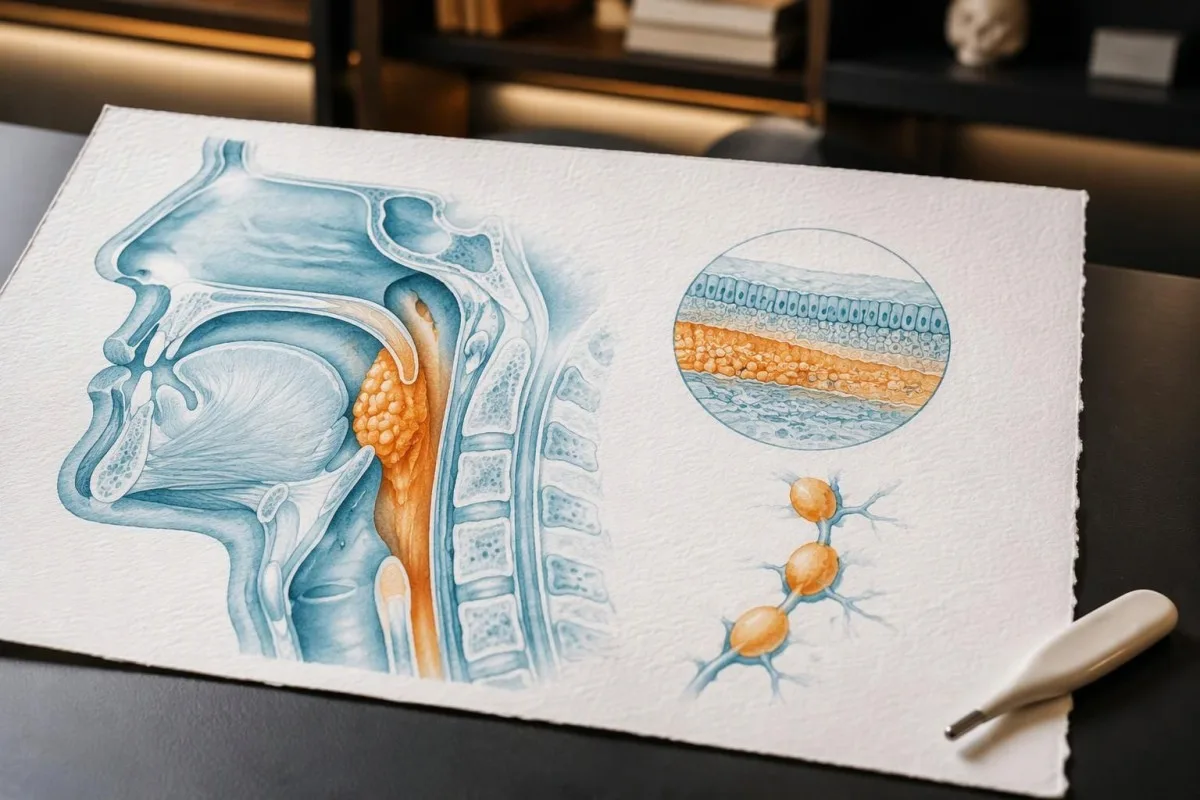
PFAPA nggambarake aktivasi jalur inflamasi sing ora trep, dudu penyakit nular anyar saben sawetara minggu. Wiwitan paling kerep sadurunge umur 5 taun, nanging bocah sing luwih tuwa lan wong diwasa uga bisa kena; mula wates umur sing adhedhasar riwayat minangka pitunjuk, dudu patokan mutlak kanggo nyingkirake diagnosis (Wang et al., 2021). PFAPA ora ateges saben demam ing mangsa ngarep mesthi dudu amarga infeksi.
Akronim iki nggambarake 4 komponèn: demam periodik, stomatitis aftosa, faringitis lan adenitis. Beda karo sawetara kahanan demam periodik warisan, PFAPA ora nduwèni siji tes genetik sing wis baku kanggo ngonfirmasi diagnosis, sanajan bisa kedadéan ing sawetara anggota kulawarga; asil negatif saka panel genetik sing jembar ora mbuktekake PFAPA lan uga ora nyingkirake kabèh kelainan inflamasi alternatif.
Kantesti iku sawijining Analisa tes getih AI sing bisa mbantu nerangake sebabe asil CRP 80 mg/L mbutuhake konteks klinis, dudu label diagnosis. Kita organisasi lan pendekatan njlentrehake layanan kasebut, nanging kanggo ngenali PFAPA klinisi kudu nggayutake gejala saka pirang-pirang episode, mriksa bocah kasebut lan nimbang kahanan sing ora bisa katangkep ing laporan laboratorium.
Gejala PFAPA endi sing ndadekake polane gampang dingerteni?
Gejala PFAPA biasane nggabungake demam karo tenggorokan lara, kelenjar gulu sing nyeri nalika didemek utawa sariawan cilik. Gabungan sing padha lan bola-bali sajrone 3 episode utawa luwih sing kacathet luwih menehi informasi tinimbang gejala tunggal apa wae, sanajan ora ana cacah episode minimal universal sing bisa ngonfirmasi PFAPA.
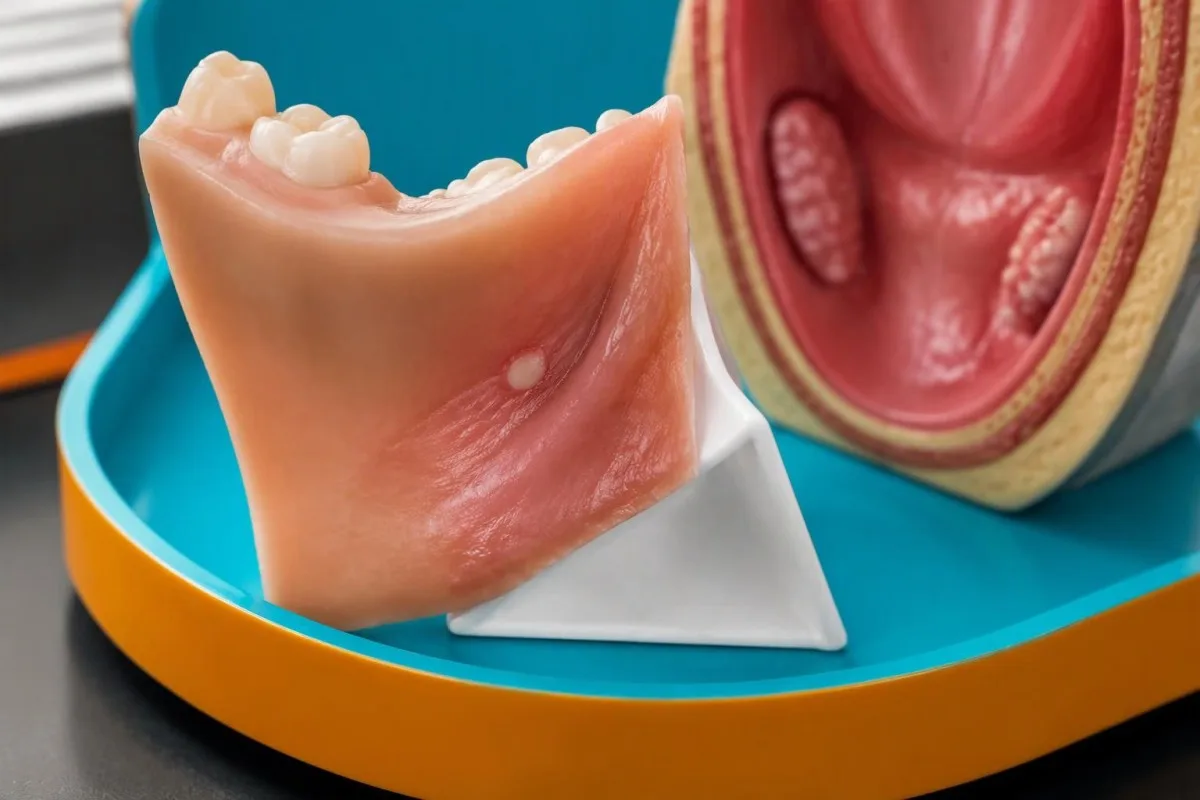
Sariawan aftosa biasane awujud tatu cilik lan cethek ing sisih njero lambe, pipi utawa lumahing cangkem liyane—ora padha karo lepuh sing nglumpuk ing lambe njaba. Bocah bisa mung duwe 1 utawa 2 tatu, lan sariawan bisa uga ora ana nalika sawetara serangan; motret tatu sing katon bisa mbantu yen tatu mau wis ilang sadurunge janjian.
Faringitis bisa nyakup tenggorokan sing abang utawa lapisan ing amandel, mula saka tampilan waé ora bisa mbedakake PFAPA saka infeksi streptokokus. Kelenjar sing abuh biasane nyakup kelenjar getah bening servikal ing sakupenge gulu, dene kelenjar sing terus saya gedhé, abuhé kelenjar sing nyebar utawa gejala sing suwéné ngluwihi serangan 3–7 dina mbutuhake panjelasan liya, dudu kanthi otomatis digandhengake karo PFAPA.
Sariawan ing cangkem waé dudu diagnosis demam periodik. Sariawan ing cangkem sing bola-bali bareng karo sariawan kelamin, mripat abang sing nyeri, owah-owahan pandeleng utawa temuan kulit sing ora lumrah nuduhake kemungkinan liya, kalebu pola gejala Behçet; malah 1 episode nyeri mripat sing diiringi gangguan pandeleng mbutuhake pemeriksaan kanthi cepet, tanpa ngenteni siklus demam sabanjure.
Suwene pira mriyang PFAPA, lan sepira kerepe bali maneh?
Demam PFAPA biasane suwéné 3–7 dina lan kambuh kira-kira saben 2–8 minggu, kerep kanthi gejala sing meh padha banget. Sawetara bocah nduwèni irama sing bisa diprakirakake, nanging jarak wektu sing owah-owahan ora kanthi otomatis nyingkirake PFAPA.

Temperatures during PFAPA attacks often reach 39–40°C, but fever height does not determine the diagnosis or reliably measure danger. The timing of associated throat symptoms, the child's appearance and the return to baseline matter more; measuring temperature with the same method also makes comparisons more useful than alternating between forehead, ear and underarm readings.
For a hypothetical child, fevers beginning on days 1, 29 and 58 with 4-day attacks suggest a repeated cycle—not proof of PFAPA. Count start-to-start intervals separately from fever-free days, and record whether corticosteroid treatment changed an interval; a shortened next cycle after treatment can otherwise make a previously regular pattern look inexplicably irregular.
A fever that does not stop is not a series of separate PFAPA episodes. If symptoms persist beyond 7 days, or recovery never occurs, clinicians reconsider infection and other inflammatory conditions; our explanation of efek wektu tes getih also shows why a sample taken on day 1 cannot be interpreted like one taken after recovery.
Apa wae sing kudu dicathet ing buku cathetan gejala PFAPA?
A PFAPA symptom diary should record episode start and finish dates, measured temperature, mouth and throat findings, neck swelling, medication timing and wellness between attacks. Even 3 carefully documented episodes can reveal details that a single clinic visit misses.

Document the thermometer method and the highest measured temperature, not just 'very hot.' For each day of a 4-day attack, note drinking, urine output, activity, cough, runny nose, abdominal symptoms and whether anyone nearby was ill; these observations distinguish a repeated inflammatory pattern from unrelated respiratory or gastrointestinal illnesses more effectively than recording fever alone.
Medication entries need the name, dose, administration time and observed response. If a prescribed medicine is given at 09:00 and fever settles by 14:00, record that interval without claiming the medicine established PFAPA; include throat swab results and whether a laboratory sample preceded treatment, because both antibiotics and corticosteroids can complicate interpretation of subsequent findings.
Well days deserve entries too. A weekly note of normal appetite, play, school attendance and any lingering symptoms prevents a diary from becoming an attack-only record; when a clinician requests a recovery sample, our persiapan tes pangukuran dhasar explains how to record recent illness and medicines rather than treating a sample 2 days after fever as an unquestionable baseline.
Apa sebabé kahanan sehat ing antarane episode PFAPA penting banget?
Complete wellness between episodes strongly supports a typical PFAPA pattern: normal activity, appetite and growth should return after the 3–7-day attack. Persistent symptoms or continuing inflammation between attacks make clinicians reconsider the diagnosis.
A child who is fever-free but remains exhausted, loses weight or develops daily pain has not truly returned to baseline. Growth is assessed through serial height and weight measurements, not 1 percentile in isolation; crossing growth centiles over time may justify investigation even when individual fever episodes resemble PFAPA and routine examinations during attacks look familiar.
Repeated ordinary infections are common in young children, but unusually severe, prolonged or unusual infections suggest a different evaluation. A history of 2 hospital-treated infections or recurrent deep infections matters differently from several mild colds; clinicians consider the organisms, sites, treatment response and family history, as discussed in our guide to tes infeksi sing kerep.
Inflammatory markers usually fall toward the laboratory reference range between PFAPA attacks, but an immediately post-fever sample may still reflect recovery. A persistent CRP of 25 mg/L on repeated genuinely well-day samples is not proof of another disease, yet it deserves explanation; a clinician may check for an unnoticed infection, ongoing inflammatory symptoms or a sampling timeline that was mislabeled.
Apa sing dituduhake CRP, ESR lan cacah sel getih ing PFAPA?
PFAPA attacks can raise CRP, ESR and neutrophil counts, but none of these tests confirms PFAPA or excludes infection. Many laboratories use a CRP upper reference limit around 5 mg/L, dene liyane nggunakake 10 mg/L; the report's own range matters.
Consider a hypothetical child with CRP 80 mg/L during fever and 3 mg/L after recovery. That change supports an episodic inflammatory process but does not identify its cause; infection can produce the same pattern, while ESR may normalize more slowly than CRP, making a modestly raised recovery ESR less surprising than persistent symptoms or repeatedly elevated CRP.
White-cell interpretation must use age-appropriate absolute counts rather than adult ranges or percentages alone. At Kantesti, we emphasize that CRP 8 mg/dL equals 80 mg/L—a tenfold unit conversion that can otherwise create a false impression of improvement; our perbandingan WBC lan CRP explains why these markers can disagree because they change at different rates.
Procalcitonin is sometimes considered when serious bacterial infection is suspected, but it is not a standalone PFAPA discriminator. A low result, including a value below 0.1 ng/mL, cannot safely overrule a concerning examination or very early illness; the limits described in our pandhuan interpretasi prokalcitonin matter more than using one reassuring number to justify home treatment.
Kepiye tenaga klinis netepake diagnosis PFAPA?
PFAPA diagnosis is clinical: clinicians identify repeated characteristic attacks, document recovery between them and exclude plausible alternatives. Onset before age 5 supports traditional criteria, but later onset does not prevent a diagnosis when the overall pattern fits.
The diagnostic process usually starts with history and examination rather than an extensive panel of rare-disease tests. Wang et al. (2021) describe the value of stereotyped episodes, absence of typical respiratory symptoms, negative relevant cultures and response to prescribed corticosteroids; however, 1 negative throat swab or 1 rapid response cannot independently establish PFAPA, and classification criteria are not identical to bedside diagnosis.
Streptococcal testing addresses the current throat illness, while an ASO antibody test mainly reflects previous exposure. An ASO result of 400 IU/mL does not prove that today's recurrent fever is active strep infection; age, local reference ranges and symptom timing affect interpretation, as explained in our discussion of ASO and recent exposure.
Kantesti iku sawijining Piranti analisis tes getih berbasis AI that can contextualize laboratory units and repeated results, but 2 matching reports cannot confirm PFAPA. Our teknis lan klinis kita information should not be read as validation of a PFAPA diagnostic test; pediatric or rheumatology assessment remains necessary when the pattern is atypical, severe or uncertain.
Kepiye PFAPA dibedakake saka infeksi sing bola-bali?
Repeated infections are more likely when episodes follow sick contacts, have varying symptoms or include cough, runny nose, diarrhea or a confirmed pathogen. PFAPA more often repeats a similar 3–7-day pattern with complete wellness between attacks, but the two can coexist.
A positive respiratory PCR does not always explain the entire fever history. Adenovirus can remain detectable after an illness, so 1 positive result must be matched to current symptoms, examination and timing; our discussion of deteksi lan keluare adenovirus explains why a molecular result may indicate recent exposure rather than the cause of every subsequent attack.
Longer-lasting sore throat, fatigue and gland enlargement can suggest a different illness rather than PFAPA. EBV antibody patterns distinguish recent infection from prior exposure more effectively than a single positive IgG result; our Pandhuan pola antibodi EBV explains the roles of 3 commonly reported markers—VCA IgM, VCA IgG and EBNA IgG—without equating past exposure with today's symptoms.
Antibiotic response is also easy to misread. If an antibiotic begins on day 4 and the fever ends on day 5, spontaneous resolution of a PFAPA attack is possible; conversely, a confirmed bacterial infection still requires appropriate treatment, and neither previous PFAPA nor prior antibiotic failure permits a new illness with different symptoms to be dismissed without assessment.
Kelainan mriyang periodik liyane endi sing bisa mirip PFAPA?
Neutropenia siklik and inherited autoinflammatory disorders can resemble PFAPA, especially when mouth sores accompany recurring fever. Approximately 21-day cycles, severe infections, marked abdominal or chest pain, unusual rashes or persistent inflammation help clinicians decide which alternatives to investigate.
Cyclic neutropenia can produce recurrent fever, mouth sores and gum problems while a blood count between low-count periods looks normal. When suspected, clinicians may request CBCs 2–3 times weekly for about 6 weeks to identify repeated neutrophil nadirs; an absolute neutrophil count below 0.5 × 10^9/L during fever requires urgent clinical assessment rather than being labeled a routine PFAPA attack.
Familial Mediterranean fever often causes shorter attacks, commonly 12–72 hours, with abdominal or chest pain from serosal inflammation or joint symptoms. Our tes MEFV kita shows why genotype and symptoms must be interpreted together; TRAPS may produce longer attacks, sometimes over 7 days, while mevalonate kinase deficiency can involve diarrhea, vomiting and attacks triggered by vaccination or other stressors.
Ancestry and family history guide assessment, but neither should become a gatekeeper that excludes an inherited disorder. Persistently raised serum amyloid A between attacks can indicate ongoing inflammation and requires context, as our serum amyloid A guide explains; a single high value during a 4-day fever does not diagnose amyloidosis, and typical PFAPA should not automatically be assigned the complication risks of other syndromes.
Tandha bebaya mriyang endi sing mbutuhake evaluasi darurat?
Enggal golek pitulungan darurat for fever with breathing difficulty, reduced responsiveness, a stiff neck, a non-blanching rash or severe dehydration. An infant younger than 3 sasi kanthi suhu 38°C utawa luwih needs urgent medical assessment, even if a family member has PFAPA.
Difficulty swallowing saliva, drooling, a muffled voice or marked one-sided throat swelling can indicate an airway-threatening problem rather than a usual PFAPA flare. A child aged 3–6 months with a temperature of 39°C or higher also needs urgent assessment; contact local emergency services for immediate danger instead of waiting for a blood result or an expected fever endpoint.
Fever lasting 5 days or longer warrants prompt medical review, particularly with red eyes, cracked lips, rash or swollen hands and feet. These findings can suggest Kawasaki disease, discussed in our Kawasaki assessment guide; incomplete presentations occur, so clinicians do not require every classic feature, and concerning symptoms should be assessed before day 5 rather than waiting for a threshold.
New severe localized abdominal pain, persistent vomiting or inability to walk normally should not be attributed to PFAPA without examination. Even 1 normal WBC or CRP result cannot reliably exclude an early abdominal emergency, as our appendicitis laboratory limits explain; children with a known fever syndrome can still develop unrelated illnesses, especially when the attack looks different from their established pattern.
Kepiye serangan PFAPA diobati, lan apa tegesé respons marang steroid?
PFAPA attack treatment focuses on comfort, hydration and, when prescribed, corticosteroids that often stop fever within hours. Published prednisone or prednisolone regimens range from 0.5–2 mg/kg, but dosing, maximum dose and eligibility must be set by the treating clinician.
Vanoni et al. (2016) describe rapid corticosteroid responses alongside the limitation that treatment may shorten the interval to the next attack. Reports summarized in that review estimated shorter intervals in approximately 25–50% of patients, but these observations come from heterogeneous studies rather than a precise prediction for an individual child; attack control and long-term prevention are separate treatment goals.
For a hypothetical 20-kg child, a clinician-selected dose of 1 mg/kg would equal 20 mg; this calculation illustrates weight-based prescribing, not a home-treatment recommendation. Families need a written plan explaining when a familiar attack qualifies for treatment, when to seek assessment first and what to do if the expected response does not occur—especially if symptoms suggest a new infection.
Antipyretics may improve discomfort even when they do not end the inflammatory episode. Choose child-appropriate preparations with a clinician or pharmacist, avoid aspirin unless specifically prescribed and do not duplicate paracetamol/acetaminophen across 2 products; Kantesti cannot authorize steroid treatment, and our discussion of interpretasi AI ing bocah-bocah explains why pediatric decisions need more than laboratory pattern recognition.
Kapan obat pencegah utawa tonsilektomi dipikirake?
Prevention or tonsillectomy may be considered when PFAPA attacks repeatedly disrupt daily life or attack treatment is unsatisfactory. A Cochrane review included 2 randomized trials involving 67 children, finding benefit from tonsil surgery while emphasizing the limited size of the evidence base.
Burton et al. (2019) judged the evidence for several tonsillectomy outcomes to be of moderate certainty, but the trials were too small to characterize uncommon harms confidently. The evidence concerns selected children rather than every person with recurrent sore throat; a child missing 4 school days each month may value potential benefit differently from a child with infrequent, easily managed attacks.
Colchicine is sometimes used to reduce attacks under specialist supervision, whereas cimetidine has less convincing evidence. Treatment selection should consider the diagnosis, kidney and liver function, other medicines and the possibility of an inherited fever disorder; when several options exist, agree in advance on a measurable goal, such as fewer attacks across 3 months, rather than assuming a changed laboratory number demonstrates success.
Tonsillectomy carries postoperative pain, dehydration, anesthesia-related risks and bleeding risk, even when it improves PFAPA. Kantesti's AI sing tanggung jawab supports a clear boundary: neither 1 elevated inflammatory marker nor an automated report can decide whether surgery is appropriate; that discussion belongs with the treating pediatric team and an ENT specialist who can assess the child's individual risks.
Tindak lanjut apa sing migunani kanggo bocah, wong diwasa lan kulawarga sing ngalami PFAPA?
PFAPA follow-up should track attack burden, growth or weight, treatment response and any symptoms between episodes. Many childhood cases improve over several years, but persistence, relapse and adult-onset disease occur; a 3-month review interval can be a practical individualized plan rather than a universal rule.

Adults require the same attention to repeated patterns and alternative causes, not an assumption that PFAPA is impossible after childhood. Fever with oral sores and pharyngitis can support the diagnosis, but new constitutional symptoms, persistent gland enlargement or abnormal findings between attacks need assessment; a 35-year-old with a first prolonged fever should not self-diagnose PFAPA from an online symptom match.
Prepare a concise appointment summary: attack dates, duration, associated features, well-day symptoms, test results and response to prescribed treatment. Include 1 clearly labeled attack sample and any clinician-requested recovery sample, rather than ordering a broad panel every month; repeated testing is useful only when it answers a specific question, such as whether inflammation persists or neutrophil counts cycle.
Kantesti iku sawijining platform interpretasi hasil tes getih AI that can help explain uploaded CBC and inflammatory-marker reports alongside their dates, units and stated reference ranges. For a family sharing 2 or more records, check each person's identity and consent before upload, and review our privasi lan pangolahan data; AI explanation does not replace pediatric examination, urgent triage or a specialist diagnosis.
Publikasi riset: bukti dibandhing pandhuan latar mburi laboratorium
PFAPA evidence comes from clinical descriptions, differential-diagnosis research and treatment studies—not from a specific clotting or serum-protein test. The 2 background publications below explain other laboratory topics and should not be mistaken for studies validating PFAPA diagnosis.
The peer-reviewed PFAPA review by Wang et al. (2021), treatment review by Vanoni et al. (2016) and Cochrane analysis by Burton et al. (2019) directly inform this article's clinical discussion. The surgical review's 67-child evidence base illustrates why certainty must be proportionate to study size; a named source supports a specific claim, not every recommendation made elsewhere on the page.
Bahan-bahan Kantesti clotting test background guide lan pandhuan latar mburi protein serum accompany the 2 Zenodo records listed below. Neither aPTT nor an albumin/globulin ratio confirms PFAPA, and neither guide establishes that routine testing of those markers improves PFAPA care; additional tests should follow an identified clinical concern rather than the availability of a panel.
Evidence interpretation should distinguish a repository-hosted educational guide from a peer-reviewed condition-specific study or systematic review. Our standar konten medis explain the editorial approach; for a child with 3 apparently similar attacks, the practical priority remains documented recovery, targeted exclusion of alternatives and a clear safety plan, not accumulating more citations or tests that do not answer the clinical question.
Pitakon sing kerep ditakoni
Apa iku sindrom PFAPA?
Sindrom PFAPA minangka kondisi autoinflamasi sing nyebabake demam kambuh-kambuhan, disertai ulkus aftosa ing tutuk, faringitis lan pembengkakan kelenjar getah bening ing gulu. Episode umume suwéné 3–7 dina lan kambuh saben sawetara minggu, kanthi kondisi kesehatan normal ing antarané serangan. Kondisi iki biasané diwiwiti sadurungé umur 5 taun, sanajan bocah sing luwih gedhé lan wong diwasa uga bisa kena. Ora ana siji tes getih sing bisa ngonfirmasi PFAPA, mula diagnosis gumantung marang pola klinis sing bola-bali lan pamriksan kanggo nemtokaké panyebab liya.
Sepira kerepe mriyang PFAPA kedadeyan?
Mriyang PFAPA biasané kambuh kira-kira saben 2–8 minggu, lan saben serangan lumrahé suwéné 3–7 dina. Sawetara bocah ngalami siklus sing ajeg banget, déné liyané jarak wektuné owah-owahan. Pangobatan kortikosteroid bisa nyepetaké wektu nganti episode sabanjuré, mula wektu ngonsumsi obat kudu dicathet ing buku harian mriyang. Mriyang sing terus-terusan utawa ora pulih ing antarané serangan kudu dievaluasi manèh, ora langsung dianggep cocog karo PFAPA.
Apa tes getih CRP sing dhuwur bisa kanggo diagnosa PFAPA?
Asil CRP sing dhuwur ora bisa kanggo ndandani PFAPA amarga infèksi lan gangguan inflamasi liyané bisa njalari paningkatan sing padha. Contoné, asil CRP 80 mg/L nalika mriyang lan 3 mg/L sawisé pulih ndhukung anané inflamasi episodik, nanging ora ngenali panyebabe. Akeh laboratorium nggunakake wates ndhuwur rujukan CRP watara 5 mg/L, déné sawetara nggunakake 10 mg/L. Dokter napsiraké asil kasebut bebarengan karo gejala, pamriksan, wektu pangambilan sampel lan tes infèksi sing cocog.
Apa PFAPA bisa nular, lan apa perlu antibiotik?
PFAPA dhewe ora nular lan antibiotik ora ngobati proses inflamasi sing dadi dhasare. Serangan khas sing suwene 3–7 dina bisa rampung kanthi alami sawisé antibiotik diwènèhaké, saéngga njalari kesan sing mblusukaké yèn antibiotik kuwi manjur. Bocah sing nandhang PFAPA isih bisa kena penyakit virus sing nular utawa infeksi bakteri. Demam anyar kanthi gejala sing béda, kontak karo wong sing lara, utawa panyebab bakteri sing wis dikonfirmasi kudu dipriksa lan diobati miturut kondisine dhewe.
Apa respons sing cepet marang prednison mbuktekake PFAPA?
Tanggepan cepet marang prednisone utawa prednisolone sing diwènèhaké dhokter ndhukung diagnosis PFAPA, nanging ora mbuktekake diagnosis kasebut. Regimen PFAPA sing wis diterbitaké kalebu dosis 0,5–2 mg/kg, kanthi dosis nyata lan dosis maksimal ditemtokaké déning klinisi sing nangani. Kortikosteroid bisa nyuda gejala saka kondisi liya lan bisa nyepetaké jarak wektu nganti serangan PFAPA sabanjuré. Kulawarga kuduné nggunakake rencana perawatan tinulis lan njaluk pamriksan sadurungé perawatan yèn sawijining épisode luwih parah utawa béda saka biasané.
Kapan bocah sing dicurigai nandhang PFAPA kudu enggal-enggal oleh perawatan?
Bocah sing dicurigani ngalami PFAPA mbutuhake pitulungan darurat yen demam dibarengi angel ambegan, kurang tanggap, gulu kaku, ruam sing ora pucet nalika ditekan utawa dehidrasi abot. Sembarang bayi sing umuré kurang saka 3 sasi kanthi suhu 38°C utawa luwih kudu enggal dipriksa dening tenaga medis. Demam sing suwéné 5 dina utawa luwih uga mbutuhake pemeriksaan kanthi cepet, utamané yen mripaté abang, ana ruam, lambe pecah-pecah utawa tangan lan sikilé abuh. Diagnosis PFAPA sadurungé ora ateges penyakit anyar kanthi gejala sing béda kena dianggep sepele.
Entuk penjelasan babagan asil tes getih sampeyan
Unggah laporan laboratorium sampeyan lan AI Kantesti bakal nerangake saben biomarker nganggo basa sing prasaja sajrone sawetara detik. Digunakake luwih saka 2 yuta wong ing saindenging donya.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). Rentang Normal aPTT: Pandhuan D-Dimer, Protein C lan Pembekuan Getih. Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Pandhuan Protein Serum: Globulin, Albumin & Rasio A/G ing Tes Getih. Riset Medis AI Kantesti. DOI
- Wang A et al. (2021). Periodic fever, aphthous stomatitis, pharyngitis, and adenitis (PFAPA) syndrome: A review. World Journal of Otorhinolaryngology - Head and Neck Surgery. DOI
- Vanoni F et al. (2016). PFAPA syndrome: a review on treatment and outcome. Pediatric Rheumatology. DOI
- Burton MJ et al. (2019). Tonsillectomy for periodic fever, aphthous stomatitis, pharyngitis and cervical adenitis syndrome (PFAPA). Cochrane Database of Systematic Reviews. DOI
- 2M+Tes sing dianalisis
- 127+negara-negara
- 100+Basa
Babagan tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis sing dipimpin dokter babagan alur kerja interpretasi lab.
Keahlian
Fokus kedokteran laboratorium babagan carane biomarker tumindak ing konteks klinis.
Kewibawaan
Ditinjau sacara medis dening Dr. Thomas Klein, kanthi kontribusi saka Dr. Sarah Mitchell lan Prof. Dr. Hans Weber.
Kapercayan
Interpretasi adhedhasar bukti kanthi tindak lanjut sing cetha kanggo nyuda rasa kaget.





Sanggahan medis
Artikel iki mung kanggo tujuan edukasi lan ora dadi saran medis. Tansah konsultasi karo panyedhiya layanan kesehatan sing mumpuni kanggo keputusan diagnosis lan perawatan.
Diterbitake · Hubungi tim editorial
Diterbitake dening Kantesti Ltd, kadhaptar ing Inggris & Wales, nomer perusahaan. 17090423, London, Britania Raya.
