Kadar gentamisin hanya bermakna jika dikaitkan dengan dosis, regimen pemberian dosis, dan waktu pengambilan sampel yang tepat. Pengobatan konvensional menggunakan target kadar puncak dan lembah; pengobatan dengan interval diperpanjang sering menggunakan konsentrasi pada waktu tertentu dan bagan khusus protokol, sedangkan pemeriksaan ginjal serta gejala pendengaran atau keseimbangan memberikan pemeriksaan keamanan yang terpisah.

Poin-poin penting
- Kadar gentamisin mengukur konsentrasi antibiotik, biasanya dalam mg/L; 1 mg/L sama dengan 1 µg/mL.
- Kadar puncak konvensional umumnya memiliki target sekitar 5–10 mg/L pada orang dewasa, tetapi infeksi, indikasi, dan metode pengambilan sampel menentukan target yang sebenarnya.
- Kadar lembah konvensional sering kali memiliki target di bawah 1 mg/L; beberapa protokol menggunakan target di bawah 2 mg/L. Tidak satu pun ambang tersebut menjamin bebas dari toksisitas.
- Waktu pengambilan sampel harus dicatat secara tepat: kadar puncak intravena konvensional umumnya diambil 30 menit setelah infus selesai, dan kadar lembah dalam waktu 30 menit sebelum dosis aktual berikutnya.
- Pemantauan dengan interval diperpanjang berbeda: protokol Hartford menggunakan konsentrasi yang diambil 6–14 jam setelah dimulainya dosis 7 mg/kg yang memenuhi syarat.
- Cedera ginjal dapat memenuhi kriteria KDIGO dengan kenaikan kreatinin setidaknya 0,3 mg/dL, atau 26,5 µmol/L, dalam 48 jam—bahkan ketika hasilnya tetap berada dalam rentang laboratorium.
- Toksisitas pendengaran dan keseimbangan dapat terjadi meskipun konsentrasi tampak dapat diterima; tinnitus baru, perubahan pendengaran, gangguan keseimbangan, atau penglihatan yang memantul memerlukan peninjauan klinis segera.
- Keputusan dosis merupakan tanggung jawab tim pemberi resep atau apoteker klinis. Jangan pernah mengubah dosis secara mandiri, menunda infus, atau menggunakan nomogram daring.
Apa sebenarnya yang diukur oleh kadar gentamisin?
Kadar gentamisin mengukur konsentrasi gentamisin dalam sampel laboratorium, bukan fungsi ginjal atau keberhasilan pengobatan secara tersendiri. Hasil 2 mg/L dapat meyakinkan, mengkhawatirkan, atau tidak dapat ditafsirkan, bergantung pada apakah sampel tersebut merupakan kadar palung, sampel pascadosis dini, atau pengukuran interval diperpanjang dengan waktu pengambilan tertentu.
Laboratorium umumnya melaporkan gentamisin dalam mg/L atau µg/mL, yang secara numerik setara: 1 mg/L sama dengan 1 µg/mL. Rentang terapeutik yang tercetak di samping hasil mungkin hanya menggambarkan pemberian dosis konvensional; rentang tersebut tidak boleh otomatis diterapkan pada pengobatan sekali sehari atau pengobatan kombinasi dosis rendah untuk regimen endokarditis tertentu.
Kantesti adalah seorang Analisa tes darah AI yang dapat membantu menjelaskan mengapa konsentrasi gentamisin sebesar 2 mg/L memerlukan konteks dosis dan waktu pengambilan sebelum ditafsirkan. Kami organisasi dan tujuan klinis kami terpisah dari layanan pemberian resep rumah sakit; kami tidak mengizinkan pemberian dosis antibiotik atau menggantikan pemantauan kadar obat terapeutik.
Tanda abnormal laboratorium yang berdiri sendiri bukanlah diagnosis. Sebagai contoh, laporan hipotetis yang ditandai tinggi pada 12 mg/L mungkin mencerminkan konsentrasi yang diambil pada waktu yang tepat setelah dosis interval diperpanjang, bukan puncak konvensional yang berlebihan; penjelasan kami tentang penanda lab di luar batas menjelaskan mengapa rentang rujukan yang terlampir dapat menyesatkan.
Mengapa waktu pemantauan gentamisin mengubah hasil?
Waktu pemantauan gentamisin penting karena konsentrasinya meningkat selama pemberian, menyebar ke dalam cairan tubuh, lalu menurun saat ginjal membersihkannya. Klinisi memerlukan setidaknya 3 penanda waktu: dimulainya infus, berakhirnya infus, dan pengambilan sampel, serta waktu dosis berikutnya yang sebenarnya saat menafsirkan kadar palung.
Dengan fungsi ginjal normal, waktu paruh eliminasi gentamisin sering kali sekitar 2–3 jam, meskipun penyakit dan perubahan distribusi dapat mengubah kurva konsentrasi. Sampel yang diambil segera setelah infus dapat menangkap fase distribusi; sampel tersebut tidak dapat dipertukarkan dengan kadar puncak yang diambil kemudian menggunakan metode yang ditentukan rumah sakit.
Waktu dosis yang dijadwalkan tidak dapat menggantikan catatan pemberian obat. Dalam contoh hipotetis dosis pukul 08:00 yang tertunda hingga pukul 09:10, sampel yang diambil pukul 09:00 tetap merupakan sampel pradosis, sedangkan bagan yang mengasumsikan obat diberikan pukul 08:00 mungkin keliru menandainya sebagai pascadosis; perbedaan ini mengubah pertanyaan klinis sepenuhnya.
Pengambilan sampel dari jalur infus dapat menghasilkan hasil yang keliru tinggi jika sisa gentamisin mencemari spesimen, sehingga staf mengikuti prosedur pengambilan dan pembilasan setempat. Masalah waktu juga terjadi pada obat lain, tetapi masa tunggu yang diperlukan berbeda; penjelasan kami tentang waktu pengambilan sampel digoksin tidak boleh digunakan sebagai jadwal pemberian gentamisin.
Bagaimana cara kerja pemantauan kadar puncak dan lembah konvensional?
Pemantauan gentamisin konvensional menggunakan kadar puncak pascadosis untuk menilai paparan dan kadar palung pradosis untuk menilai sisa obat sebelum pemberian berikutnya. For selected adults receiving divided doses, intervals may be 8 or 12 hours, but kidney function and the treatment indication determine the prescribed schedule.

After an intravenous infusion, a conventional gentamicin peak level is commonly collected 30 minutes after the infusion finishes; some protocols specify a different time. A gentamicin trough level is commonly collected within 30 minutes before the next actual dose, and intramuscular administration uses a different post-dose sampling convention.
Some services obtain the first paired measurements around the 3rd or 4th dose, when concentrations are approaching a repeatable pattern in patients with stable clearance. That is not a reason to postpone assessment in someone with worsening kidney function, unexpected dosing, or symptoms; such patients may require earlier measurements and individualized pharmacokinetic review.
A peak and trough are useful only if the preceding doses were actually administered as documented. A missed dose, a changed infusion duration, or a sample collected 2 hours early can invalidate an otherwise neat-looking pair; similar documentation principles appear in our carbamazepine trough timing guide, although the therapeutic targets are unrelated.
Kadar puncak gentamisin berapa yang menjadi target klinisi?
A conventional gentamicin peak level commonly targets approximately 5–10 mg/L in adults, but there is no universal target for every infection. Some low-dose synergy protocols use peaks around 3–5 mg/L, while extended-interval concentrations must not be judged against the conventional peak range.
Gentamicin exhibits concentration-dependent antibacterial activity: for susceptible Gram-negative organisms, a peak-to-minimum inhibitory concentration ratio around 8–10 is a commonly used pharmacodynamic goal. The minimum inhibitory concentration, or MIC, describes the organism's susceptibility; a peak of 8 mg/L has a different meaning when the MIC is 0.5 rather than 2 mg/L.
A low measured peak does not always mean the prescribed dose was too small. A hypothetical patient with major fluid expansion might have a larger distribution volume, while a peak sample collected 90 minutes late could be lower simply because elimination has continued; the pharmacist distinguishes these possibilities before changing treatment.
Selected combination regimens use gentamicin for synergy, not the same exposure goals used for stand-alone Gram-negative treatment. High-level aminoglycoside resistance can prevent that synergy and is not solved by chasing a higher concentration; our antifungal trough target discussion illustrates why drug-specific targets cannot be borrowed across treatments.
| Tingkat | Rentang | Maknanya |
|---|---|---|
| Conventional adult peak | Commonly 5–10 mg/L | Illustrative target used by some protocols; indication and the specified collection time determine interpretation. |
| Selected synergy peak | Often 3–5 mg/L | Applies only to particular low-dose combination protocols, not every endocarditis regimen. |
| Conventional adult trough | Often <1 mg/L; some protocols <2 mg/L | Lower residual exposure reduces concern about accumulation but does not exclude toxicity. |
| Extended-interval concentration | No universal peak-and-trough reference interval | Interpret using the actual elapsed time and the validated protocol for the administered dose. |
Apa yang ditunjukkan oleh kadar lembah gentamisin yang tinggi?
A high, correctly timed gentamicin trough level suggests that substantial drug remains before the next dose, often because clearance is reduced or the interval is too short. Many conventional protocols aim below 1 mg/L; others accept below 2 mg/L, so the prescribing service's target must be checked.

A trough is a clearance signal, not a direct measurement of kidney tissue exposure. Gentamicin can accumulate within renal proximal tubular cells over repeated treatment, so a trough below 1 mg/L does not erase the effects of cumulative exposure, concurrent nephrotoxic medicines, or a kidney problem that is only beginning.
The direction of causation can run both ways: reduced kidney function raises gentamicin concentrations, and gentamicin-associated tubular injury can further reduce clearance. For example, a hypothetical trough rising from 0.6 to 1.4 mg/L on an unchanged schedule may prompt review of creatinine trends, actual dose times, fluid status, and other medicines rather than a conclusion based on the concentration alone.
A sample collected 2 hours before the next dose will usually be higher than a true pre-dose trough and should not be casually relabeled. Conversely, a sample after an unusually long delay may look reassuring without representing the usual schedule; our tacrolimus trough interpretation guide explains the same documentation problem with a different drug.
Apa perbedaan pemantauan gentamisin dengan interval diperpanjang?
Extended-interval gentamicin uses a larger individual dose followed by a longer drug-free interval, and monitoring often relies on a timed post-dose concentration rather than conventional paired levels. Selected adult protocols use approximately 5–7 mg/kg per dose, but the exact dose, interval, and eligibility criteria are service-specific.

The rationale combines concentration-dependent killing with a post-antibiotic effect, meaning bacterial growth may remain suppressed after the circulating concentration falls. A once-daily regimen therefore does not require a conventional trough to remain detectably therapeutic; intentionally low late concentrations are part of the strategy, not proof that treatment has stopped working.
Selected extended-interval protocols use 24-, 36-, or 48-hour intervals, but once-daily is an imprecise label when impaired clearance requires longer spacing. Some hospitals use a pre-dose concentration, some a single timed nomogram sample, and others 2 concentrations or model-based exposure estimates; these approaches are not interchangeable without their accompanying dosing rules.
Extended-interval treatment is not suitable for every patient or indication, and reduced renal toxicity in selected populations does not mean zero risk. Our vancomycin exposure monitoring guide explains another antibiotic-specific approach; the vancomycin AUC target of 400–600 mg·h/L is not a gentamicin target.
Kapan nomogram Hartford dapat digunakan untuk menginterpretasikan kadar gentamisin?
The Hartford nomogram applies to qualifying extended-interval aminoglycoside treatment using a 7 mg/kg dose and a concentration collected 6–14 hours after infusion start. It helps clinicians choose an interval; it is not a universal chart for any gentamicin dose, any collection time, or any patient.

The original Hartford experience described 2,184 adult patients receiving a once-daily aminoglycoside program, providing the clinical background for its dose-and-time framework (Nicolau et al., 1995). The 6–14-hour measurement is sometimes called a random level, but random here means not a conventional peak or trough—not that its timing is optional.
Hospitals restrict or modify this approach in populations such as pregnancy, dialysis, unstable renal function, major burns, cystic fibrosis, or selected endocarditis regimens. A hypothetical concentration of 2.2 mg/L collected 10 hours after a 5 mg/kg dose cannot simply be plotted on an unmodified 7 mg/kg Hartford chart to obtain a reliable interval.
If the sample falls outside the validated window, clinicians may request another level or calculate individualized pharmacokinetics rather than force a point onto the chart. Our delayed drug-clearance explanation illustrates why elapsed time is part of a drug result, although methotrexate rescue thresholds have no role in gentamicin dosing.
Bagaimana perbandingan dua laporan gentamisin hipotetis?
Two identical gentamicin results can mean different things when the sampling schedules differ. The following 2 hypothetical examples demonstrate conventional and extended-interval interpretation; they are not dosing instructions, and neither example supplies enough information for a patient to choose the next dose.

In hypothetical example A, a conventional infusion starts at 08:00, ends at 08:30, and the prescribed peak sample is collected at 09:00. A result of 8 mg/L fits many conventional peak targets if the indication agrees; a separate 15:40 sample before a 16:00 dose provides the trough information that the peak cannot supply.
In hypothetical example B, an eligible 70 kg adult receives a clinician-prescribed 490 mg dose, corresponding to 7 mg/kg, with infusion start at 08:00. A sample at 18:00 is 10 hours after infusion start and is interpreted under the applicable extended-interval protocol; calling that result a low peak or a high trough would ask the wrong question.
Neither timeline establishes kidney safety without baseline and follow-up renal information, and the prescribed dosing weight may differ from scale weight. Before collection, patients can confirm that staff have the actual administration record and the intended test type; our baseline sample preparation checklist helps distinguish useful preparation from unnecessary fasting or medication changes.
Bagaimana klinisi mendeteksi cedera ginjal terkait gentamisin?
Clinicians assess possible gentamicin-associated kidney injury using creatinine changes, urine output, exposure history, and alternative causes—not the gentamicin concentration alone. KDIGO defines acute kidney injury by a creatinine rise of at least 0.3 mg/dL within 48 hours, a rise to at least 1.5 times baseline within 7 days, or qualifying low urine output.
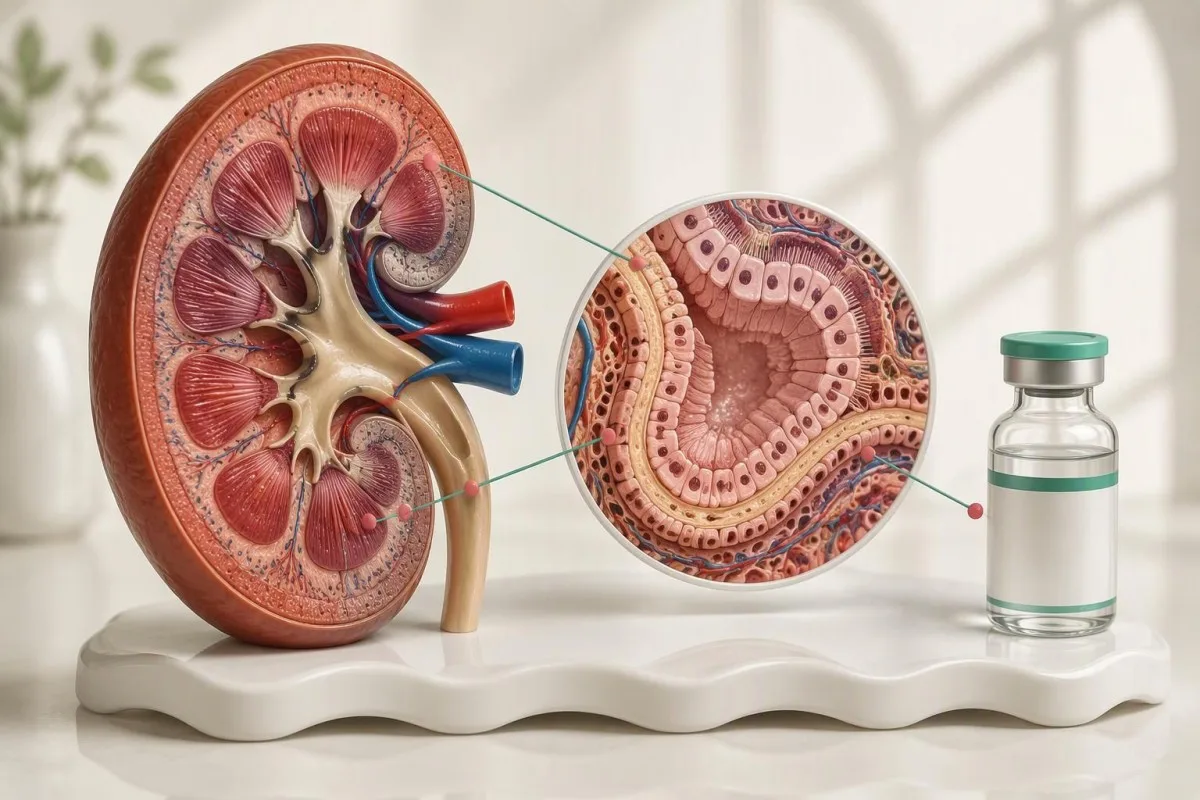
Itu 0.3 mg/dL threshold equals 26.5 µmol/L, and it can identify injury even when both values sit inside the laboratory interval (KDIGO Acute Kidney Injury Work Group, 2012). For example, a hypothetical creatinine increase from 0.7 to 1.0 mg/dL within 48 hours meets that criterion; normal-looking is not the same as unchanged.
KDIGO's urine-output criterion includes less than 0.5 mL/kg/hour for 6 hours: for a 70 kg adult, that is below 35 mL/hour over the specified period. Gentamicin-associated injury can also be non-oliguric, meaning urine output remains relatively preserved, so passing urine normally does not rule out an important creatinine rise.
Sepsis, low blood pressure, dehydration, urinary obstruction, and other medicines can produce similar changes, and attribution requires clinical assessment. Our rasio BUN dan kreatinin explains useful context without treating the ratio as diagnostic; seek prompt advice for markedly reduced urine or the warning signs described in our low kidney function symptoms artikel.
Pemeriksaan ginjal dan elektrolit apa yang menyertai pemeriksaan kadar gentamisin?
Gentamicin safety monitoring usually includes baseline and repeat serum creatinine, with electrolytes and urine assessment when clinically indicated. Hospitalized adults often have daily renal checks during ongoing treatment, but outpatient schedules depend on stability, treatment duration, local protocol, and whether a change occurs within 24–48 hours.
Creatinine is a delayed marker of changing filtration, and automated eGFR assumes relatively steady creatinine production and clearance. During evolving acute kidney injury, an eGFR reported as 60 mL/min/1.73 m² may not accurately describe current clearance; clinicians often rely on the trajectory and an appropriate drug-dosing renal assessment rather than the printed number alone.
Aminoglycoside-related tubular dysfunction can cause magnesium or potassium wasting, sometimes before a major creatinine increase. For example, a hypothetical magnesium of 0.55 mmol/L with new weakness deserves assessment of renal losses, gastrointestinal losses, and medicines; our electrolyte safety patterns explain why replacement must reflect the whole clinical picture.
Urinary granular casts can support tubular injury but neither prove gentamicin caused it nor reliably exclude injury when absent. Our granular cast interpretation guide separates suggestive findings from diagnosis; the broader urinalisis yang lebih luas explains why 1 urine specimen cannot substitute for serial renal assessment.
Siapa yang memerlukan pemantauan keamanan gentamisin yang lebih individual?
Patients with unstable kidney function, major changes in body-fluid volume, repeated exposure, or concurrent nephrotoxic medicines need particularly individualized gentamicin monitoring. Older adults, neonates, pregnancy, dialysis, obesity, and severe illness can also make standard adult dosing assumptions unreliable; a 7 mg/kg protocol should not be generalized across these groups.

Risk generally increases with cumulative exposure and longer treatment, particularly when courses extend beyond approximately 5–7 days, although shorter courses are not risk-free. Concurrent vancomycin, amphotericin B, some chemotherapy agents, and nonsteroidal anti-inflammatory medicines can complicate renal safety; dehydration or low blood pressure may add a second stressor rather than an independent laboratory clue.
The dosing weight is not always the measured weight: obesity may require an adjusted-weight method, while ascites, edema, major burns, or critical illness can alter the distribution volume. A hypothetical 100 kg patient therefore should not calculate a dose by multiplying scale weight by 7; the hospital's weight convention and renal method are part of the prescription.
A creatinine clearance expressed in mL/menit is not identical to an indexed eGFR expressed in mL/min/1.73 m², and low muscle mass can hide impaired filtration behind a modest creatinine value. Our dehydration and filtration explanation describes reversible changes, but a new decline during gentamicin treatment still needs review rather than being assumed temporary.
Dapatkah gentamisin memengaruhi pendengaran atau keseimbangan meskipun kadarnya dapat diterima?
Gentamicin can cause hearing or vestibular toxicity even when measured concentrations fall within the prescribed targets. New tinnitus, hearing change, unsteadiness, or oscillopsia—vision that appears to bounce during walking—requires prompt contact with the treatment team; there is no serum concentration that guarantees inner-ear safety.

Gentamicin is particularly associated with vestibular toxicity, which affects balance and visual stability rather than hearing alone. Bilateral vestibular impairment may cause difficulty walking in darkness or bouncing vision without dramatic spinning vertigo; after even 1 new symptom, patients should report the change instead of waiting for the next routine blood test.
Baseline hearing and balance history helps interpret subsequent changes, and clinicians may arrange audiometry, including high-frequency assessment, or vestibular testing for prolonged or higher-risk treatment. A normal conventional hearing test does not exclude early high-frequency change or a vestibular problem; symptoms can emerge or progress after the final dose, and some effects are permanent.
Itu MT-RNR1 variants m.1555A>G and m.1494C>T are associated with increased aminoglycoside-related hearing-loss risk. The CPIC guideline recommends avoiding aminoglycosides in people with relevant high-risk variants unless the seriousness of the condition and lack of suitable alternatives justify treatment (McDermott et al., 2022); genetic testing must not delay urgent treatment without a clinician-directed plan.
Kantesti adalah seorang platform interpretasi tes darah AI, but a gentamicin concentration of 0.8 mg/L cannot establish normal hearing or vestibular function. Our AI yang bertanggung jawab explain why laboratory interpretation must remain separate from examination, audiology, emergency assessment, and decisions about the next antibiotic administration.
Apa yang harus Anda lakukan jika hasil pemeriksaan gentamisin tidak terduga?
Contact the prescribing team or clinical pharmacist about an unexpected gentamicin result, especially when the next dose is approaching or symptoms have appeared. Do not independently change the dose or interval; a concentration of 2 mg/L means different things under different protocols, and an urgent decision needs the administration record.

Provide 5 practical details: the reported concentration and units, dose, infusion start and finish, sample collection time, and the latest creatinine with its earlier baseline. Also mention missed or delayed doses, urine changes, tinnitus, hearing change, imbalance, and nonprescription medicines; symptoms deserve attention even when the laboratory has not marked the result high.
If you are in hospital, alert the nurse or treatment team immediately rather than altering the infusion equipment yourself. If you receive home infusions, use the service's urgent contact route before the next planned administration when there is a concerning result; our secure clinical result-sharing guide explains how to preserve the original report and its timestamps.
Kantesti AI can support explanation of units and trends, but it cannot confirm whether an 18:00 sample belongs on a hospital's nomogram or authorize a treatment change. When sharing results for educational interpretation, remove unnecessary identifiers and review our informasi privasi dan data; privacy precautions must never delay urgent medical contact.
Konteks penelitian dan keterbatasan interpretasi gentamisin oleh AI
Clinical interpretation of gentamicin levels depends on validated dosing protocols, kidney-injury definitions, and separate assessment of hearing and balance. The 3 external medical references below support those clinical discussions; the 2 additional Kantesti publications describe platform or educational work and are not gentamicin dosing or toxicity-validation studies.

The Hartford program, KDIGO acute kidney injury criteria, and CPIC aminoglycoside pharmacogenetics guideline answer 3 different questions: how to interpret a qualifying timed level, how to recognize kidney injury, and when genetic susceptibility changes antibiotic selection. None can turn an unlabeled concentration into a complete treatment decision, and differences between hospital targets should be resolved using the patient's actual protocol.
Kantesti adalah seorang Alat analisis pemeriksaan darah berbasis AI that can help organize gentamicin results alongside creatinine and electrolyte trends when the required context is supplied. A 0.3 mg/dL creatinine rise still requires clinician assessment regardless of how a report is summarized; our pengawasan teknis dan klinis describes evaluation boundaries rather than claiming validation for autonomous gentamicin dosing.
The Global Health Report 2026 and the RDW guide listed below are 2 separate publications, not evidence that AI can prevent aminoglycoside toxicity. Kantesti's standar konten medis distinguish educational interpretation from prescribing; patients should use this article to ask better timing and safety questions, not to choose their next dose.
Pertanyaan yang sering diajukan
Berapa kadar gentamisin trough yang normal?
Kadar gentamisin lembah konvensional sering ditargetkan di bawah 1 mg/L, meskipun beberapa protokol menggunakan batas di bawah 2 mg/L. Sampel biasanya perlu diambil dalam waktu 30 menit sebelum dosis berikutnya benar-benar diberikan, bukan sekadar sebelum waktu pemberian yang dijadwalkan. Regimen interval panjang mungkin menggunakan ambang pradosis yang berbeda atau konsentrasi pada waktu tertentu untuk nomogram. Kadar lembah yang dapat diterima tidak menyingkirkan kemungkinan toksisitas pada ginjal, pendengaran, atau keseimbangan.
Kapan kadar puncak gentamisin harus diambil?
A conventional intravenous gentamicin peak level is commonly collected 30 minutes after the infusion ends, but the prescribing service's protocol determines the exact time. For example, an infusion ending at 08:30 may require collection at 09:00 under that protocol. A sample collected immediately after infusion or much later cannot automatically be compared with the same target. Extended-interval monitoring and intramuscular administration use different sampling conventions.
Apakah kadar gentamisin 2 mg/L terlalu tinggi?
Kadar gentamisin 2 mg/L tidak dapat diklasifikasikan tanpa mengetahui regimen dosis dan waktu pengambilan sampel. Kadar tersebut akan melebihi target pada banyak protokol kadar palung konvensional, tetapi dapat menjadi konsentrasi terukur yang diharapkan pada regimen interval diperpanjang. Sampel yang diambil terlalu awal, terlambat, atau dari jalur infus yang terkontaminasi juga dapat mengubah interpretasinya. Hubungi tim yang meresepkan obat, bukan mengubah dosis berikutnya sendiri.
Kapan kadar gentamisin diukur untuk pemberian dosis sekali sehari?
Untuk regimen Hartford 7 mg/kg yang memenuhi syarat, konsentrasi gentamisin diambil 6–14 jam setelah infus dimulai. Protokol interval panjang lainnya mungkin menggunakan pengukuran sebelum dosis, 2 pengukuran setelah dosis, atau bagan dosis dan waktu yang berbeda. Kata acak tidak berarti waktu pengambilan sampel tidak penting. Konsentrasi hanya boleh ditafsirkan menggunakan protokol yang sesuai dengan dosis yang diberikan dan pasien.
Apakah gentamisin dapat merusak ginjal ketika kadarnya normal?
Cedera ginjal terkait gentamisin dapat terjadi meskipun konsentrasinya berada dalam kisaran target yang diresepkan, karena paparan kumulatif dan risiko spesifik pasien juga berpengaruh. Peningkatan kreatinin minimal 0,3 mg/dL, atau 26,5 µmol/L, dalam 48 jam memenuhi kriteria cedera ginjal akut KDIGO. Keluaran urine dapat tetap relatif normal pada cedera tubulus terkait aminoglikosida. Klinisi menilai kadar kreatinin serial, keluaran urine, obat-obatan lain, dan penyebab alternatif, alih-alih hanya mengandalkan satu kadar obat.
Apakah gentamisin dapat menyebabkan gangguan pendengaran atau pusing setelah pengobatan?
Gejala pendengaran atau keseimbangan terkait gentamisin dapat muncul atau memburuk setelah pengobatan berakhir, dan kadar serum yang dapat diterima tidak meniadakan kemungkinan ini. Bahkan 1 gejala baru—seperti tinnitus, perubahan pendengaran, gangguan keseimbangan yang menetap, atau penglihatan yang tampak memantul saat berjalan—perlu segera ditinjau oleh tenaga klinis. Gentamisin dapat memengaruhi fungsi vestibular tanpa gangguan pendengaran yang jelas atau vertigo berputar. Pemeriksaan dapat mencakup tes pendengaran dan vestibular karena kadar gentamisin bukanlah tes fungsi telinga bagian dalam.
Dapatkan penjelasan tentang hasil tes darah Anda
Unggah laporan lab Anda dan AI Kantesti menjelaskan setiap biomarker dengan bahasa sederhana dalam hitungan detik. Digunakan oleh lebih dari 2 juta orang di seluruh dunia.
Referensi
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2,5M Tes Dianalisis | Global Health Report 2026. Riset Medis AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Tes Darah RDW: Panduan Lengkap RDW-CV, MCV & MCHC. Riset Medis AI Kantesti. DOI
- Nicolau DP et al. (1995). Experience with a once-daily aminoglycoside program administered to 2,184 adult patients. Antimicrobial Agents and Chemotherapy. DOI
- KDIGO Acute Kidney Injury Work Group (2012). KDIGO Clinical Practice Guideline for Acute Kidney Injury. Kidney International Supplements.
- McDermott JH et al. (2022). Clinical Pharmacogenetics Implementation Consortium Guideline for the Use of Aminoglycosides Based on MT-RNR1 Genotype. Clinical Pharmacology & Therapeutics. DOI
- 2 juta+Pemeriksaan yang dianalisis
- 127+Negara
- 100+Bahasa
Tentang tim medis


Sinyal Kepercayaan E-E-A-T
Pengalaman
Tinjauan klinis yang dipimpin dokter terhadap alur kerja interpretasi hasil lab.
Keahlian
Fokus pada kedokteran laboratorium tentang bagaimana biomarker berperilaku dalam konteks klinis.
Kewenangan
Ditinjau secara medis oleh Dr. Thomas Klein, dengan kontribusi dari Dr. Sarah Mitchell dan Prof. Dr. Hans Weber.
Kepercayaan
Interpretasi berbasis bukti dengan jalur tindak lanjut yang jelas untuk mengurangi kepanikan.






Penafian medis
Artikel ini hanya untuk tujuan edukasi dan tidak merupakan nasihat medis. Selalu konsultasikan dengan penyedia layanan kesehatan yang berkualifikasi untuk keputusan diagnosis dan perawatan.
Diterbitkan · Hubungi tim editorial
Diterbitkan oleh Kantesti Ltd, terdaftar di Inggris & Wales, nomor perusahaan. 17090423, London, Britania Raya.
