Nivelet e gentamicinës kanë kuptim vetëm kur vlerësohen së bashku me dozën, skemën e dozimit dhe kohën e saktë të marrjes së mostrës. Trajtimi konvencional përdor objektiva për nivelet kulmore dhe minimale; trajtimi me intervale të zgjatura shpesh përdor një përqendrim të matur në një kohë të caktuar dhe një grafik specifik për protokollin, ndërsa analizat e funksionit të veshkave dhe simptomat që lidhen me dëgjimin ose ekuilibrin shërbejnë si kontrolle të veçanta të sigurisë.

Përfundimet kryesore
- Nivelet e gentamicinës matin përqendrimin e antibiotikut, zakonisht në mg/L; 1 mg/L është i barabartë me 1 µg/mL.
- Niveli kulmor konvencional objektivat zakonisht variojnë rreth 5–10 mg/L te të rriturit, por infeksioni, indikacioni dhe mënyra e marrjes së mostrës përcaktojnë objektivin konkret.
- Niveli minimal konvencional objektivat shpesh janë nën 1 mg/L; disa protokolle përdorin vlerën nën 2 mg/L. Asnjëra nga këto pragje nuk garanton mungesën e toksicitetit.
- Koha e marrjes së mostrës duhet të regjistrohet me saktësi: një nivel kulmor konvencional pas administrimit intravenoz zakonisht merret 30 minuta pas përfundimit të infuzionit, ndërsa niveli minimal brenda 30 minutave para dozës së ardhshme të planifikuar.
- Monitorimi me intervale të zgjatura ndryshon: protokolli Hartford përdor një përqendrim të matur 6–14 orë pas fillimit të një doze kualifikuese prej 7 mg/kg.
- Dëmtimi i veshkave mund të plotësojë kriteret KDIGO me një rritje të kreatininës prej të paktën 0.3 mg/dL, ose 26.5 µmol/L, brenda 48 orëve—edhe kur rezultati mbetet brenda intervalit laboratorik.
- Toksiciteti për dëgjimin dhe ekuilibrin mund të ndodhë edhe kur përqendrimet duken të pranueshme; shfaqja e re e zhurmës në veshë, ndryshimeve në dëgjim, humbjes së ekuilibrit ose shikimit kërcyes kërkon vlerësim të menjëhershëm klinik.
- Vendimet e dozës janë përgjegjësi e ekipit që përshkruan trajtimin ose e farmacistit klinik. Mos e ndryshoni kurrë vetë dozën, mos e shtyni infuzionin dhe mos përdorni një nomogram në internet.
Çfarë matin në të vërtetë nivelet e gentamicinës?
Nivelet e gentamicinës matin përqendrimin e gentamicinës në një mostër laboratorike, jo funksionin e veshkave apo suksesin e trajtimit më vete. Një rezultat prej 2 mg/L mund të jetë qetësues, shqetësues ose i pamundur për t’u interpretuar, në varësi të faktit nëse është nivel minimal para dozës së radhës, mostër e hershme pas dozës apo matje me interval të përcaktuar kohor për dozimin me intervale të zgjatura.
Laboratorët zakonisht e raportojnë gentamicinën në mg/L ose µg/mL, të cilat janë numerikisht ekuivalente: 1 mg/L është e barabartë me 1 µg/mL. Intervali terapeutik i shënuar pranë rezultatit mund të përshkruajë vetëm dozimin konvencional; ai nuk duhet zbatuar automatikisht për trajtimin një herë në ditë ose për trajtimin e kombinuar me doza të ulëta në skema të caktuara për endokarditin.
Kantesti është një Analizues i testeve të gjakut AI që mund të ndihmojnë të shpjegohet pse një përqendrim i gentamicinës prej 2 mg/L kërkon kontekstin e dozës dhe kohës së marrjes së mostrës përpara interpretimit. Tona organizata dhe qëllimi ynë klinike janë të ndara nga shërbimi spitalor i përshkrimit të barnave; ne nuk autorizojmë dozat e antibiotikëve dhe nuk zëvendësojmë monitorimin terapeutik të barnave.
Një sinjalizim i veçuar laboratorik nuk është diagnozë. Për shembull, një raport hipotetik i shënuar si i lartë me 12 mg/L mund të pasqyrojë një përqendrim të matur në kohën e duhur pas një doze me interval të zgjatur, dhe jo një kulm tepër të lartë konvencional; shpjegimi ynë për flamujt laboratorikë jashtë intervalit përshkruan pse intervali i referencës bashkëngjitur mund të jetë çorientues.
Pse koha e monitorimit të gentamicinës ndryshon rezultatin?
Koha e monitorimit të gentamicinës ka rëndësi, sepse përqendrimi rritet gjatë administrimit, shpërndahet në lëngjet trupore dhe më pas ulet ndërsa veshkat e eliminojnë. Mjekëve u duhen të paktën 3 shënime kohore: fillimi i infuzionit, përfundimi i infuzionit dhe marrja e mostrës, si dhe koha reale e dozës së radhës kur interpretohet niveli minimal para dozës së radhës.
Me funksion normal të veshkave, gjysmëjeta e eliminimit të gentamicinës është shpesh afërsisht 2–3 orë, megjithëse sëmundja dhe ndryshimet në shpërndarje mund të ndryshojnë kurbën e përqendrimit. Një mostër e marrë menjëherë pas infuzionit mund të pasqyrojë fazën e shpërndarjes; ajo nuk është e këmbyeshme me një kulm të mëvonshëm të matur sipas metodës së përcaktuar nga spitali.
Koha e planifikuar e dozës nuk mund të zëvendësojë regjistrin e administrimit. Në një rast hipotetik, kur doza e planifikuar për në 08:00 vonohet deri në 09:10, një mostër e marrë në 09:00 është ende para dozës, ndërsa një kartelë që supozon se doza u administrua në 08:00 mund ta etiketojë gabimisht si mostër pas dozës; kjo diferencë e ndryshon krejtësisht pyetjen klinike.
Marrja e mostrës nga linja e infuzionit mund të japë rezultat rrejshëm të lartë nëse gentamicina e mbetur ndot mostrën, ndaj personeli zbaton procedurat lokale të marrjes së mostrës dhe shpëlarjes së linjës. Probleme me kohën ndodhin edhe me barna të tjera, por periudha e kërkuar e pritjes ndryshon; shpjegimi ynë për kohën e marrjes së mostrës për digoksinën nuk duhet përdorur si orar për gentamicinën.
Si funksionon monitorimi konvencional i niveleve kulmore dhe minimale?
Monitorimi konvencional i gentamicinës përdor kulmin pas dozës për të vlerësuar ekspozimin dhe nivelin minimal para dozës për të vlerësuar sasinë e mbetur të barit para administrimit të radhës. For selected adults receiving divided doses, intervals may be 8 or 12 hours, but kidney function and the treatment indication determine the prescribed schedule.

After an intravenous infusion, a conventional gentamicin peak level is commonly collected 30 minutes after the infusion finishes; some protocols specify a different time. A gentamicin trough level is commonly collected within 30 minutes before the next actual dose, and intramuscular administration uses a different post-dose sampling convention.
Some services obtain the first paired measurements around the 3rd or 4th dose, when concentrations are approaching a repeatable pattern in patients with stable clearance. That is not a reason to postpone assessment in someone with worsening kidney function, unexpected dosing, or symptoms; such patients may require earlier measurements and individualized pharmacokinetic review.
A peak and trough are useful only if the preceding doses were actually administered as documented. A missed dose, a changed infusion duration, or a sample collected 2 hours early can invalidate an otherwise neat-looking pair; similar documentation principles appear in our carbamazepine trough timing guide, although the therapeutic targets are unrelated.
Çfarë niveli kulmor të gentamicinës synojnë klinicistët?
A conventional gentamicin peak level commonly targets approximately 5–10 mg/L in adults, but there is no universal target for every infection. Some low-dose synergy protocols use peaks around 3–5 mg/L, while extended-interval concentrations must not be judged against the conventional peak range.
Gentamicin exhibits concentration-dependent antibacterial activity: for susceptible Gram-negative organisms, a peak-to-minimum inhibitory concentration ratio around 8–10 is a commonly used pharmacodynamic goal. The minimum inhibitory concentration, or MIC, describes the organism's susceptibility; a peak of 8 mg/L has a different meaning when the MIC is 0.5 rather than 2 mg/L.
A low measured peak does not always mean the prescribed dose was too small. A hypothetical patient with major fluid expansion might have a larger distribution volume, while a peak sample collected 90 minutes late could be lower simply because elimination has continued; the pharmacist distinguishes these possibilities before changing treatment.
Selected combination regimens use gentamicin for synergy, not the same exposure goals used for stand-alone Gram-negative treatment. High-level aminoglycoside resistance can prevent that synergy and is not solved by chasing a higher concentration; our antifungal trough target discussion illustrates why drug-specific targets cannot be borrowed across treatments.
| Niveli | Intervali | Çfarë do të thotë |
|---|---|---|
| Conventional adult peak | Commonly 5–10 mg/L | Illustrative target used by some protocols; indication and the specified collection time determine interpretation. |
| Selected synergy peak | Often 3–5 mg/L | Applies only to particular low-dose combination protocols, not every endocarditis regimen. |
| Conventional adult trough | Often <1 mg/L; some protocols <2 mg/L | Lower residual exposure reduces concern about accumulation but does not exclude toxicity. |
| Extended-interval concentration | No universal peak-and-trough reference interval | Interpret using the actual elapsed time and the validated protocol for the administered dose. |
Çfarë sugjeron një nivel i lartë minimal i gentamicinës?
A high, correctly timed gentamicin trough level suggests that substantial drug remains before the next dose, often because clearance is reduced or the interval is too short. Many conventional protocols aim below 1 mg/L; others accept below 2 mg/L, so the prescribing service's target must be checked.

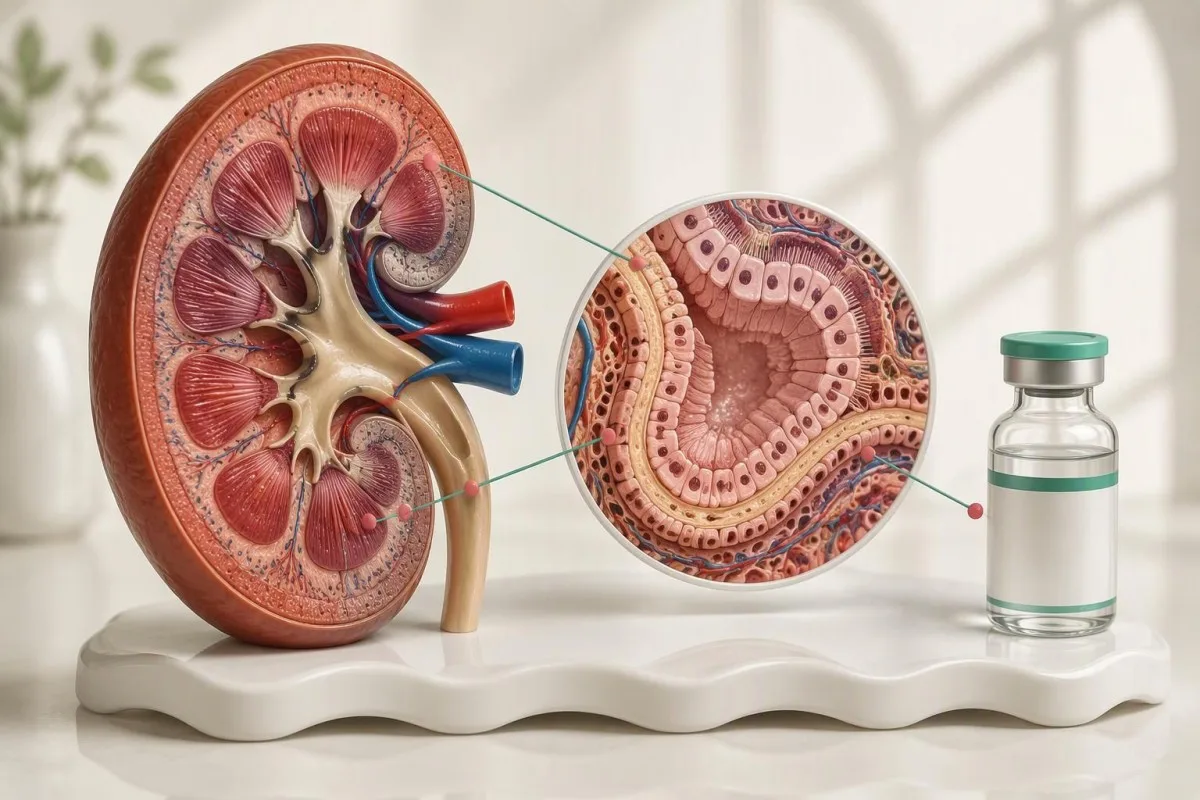
A trough is a clearance signal, not a direct measurement of kidney tissue exposure. Gentamicin can accumulate within renal proximal tubular cells over repeated treatment, so a trough below 1 mg/L does not erase the effects of cumulative exposure, concurrent nephrotoxic medicines, or a kidney problem that is only beginning.
The direction of causation can run both ways: reduced kidney function raises gentamicin concentrations, and gentamicin-associated tubular injury can further reduce clearance. For example, a hypothetical trough rising from 0.6 to 1.4 mg/L on an unchanged schedule may prompt review of creatinine trends, actual dose times, fluid status, and other medicines rather than a conclusion based on the concentration alone.
A sample collected 2 hours before the next dose will usually be higher than a true pre-dose trough and should not be casually relabeled. Conversely, a sample after an unusually long delay may look reassuring without representing the usual schedule; our tacrolimus trough interpretation guide explains the same documentation problem with a different drug.
Si ndryshon monitorimi i gentamicinës me intervale të zgjatura?
Extended-interval gentamicin uses a larger individual dose followed by a longer drug-free interval, and monitoring often relies on a timed post-dose concentration rather than conventional paired levels. Selected adult protocols use approximately 5–7 mg/kg per dose, but the exact dose, interval, and eligibility criteria are service-specific.

The rationale combines concentration-dependent killing with a post-antibiotic effect, meaning bacterial growth may remain suppressed after the circulating concentration falls. A once-daily regimen therefore does not require a conventional trough to remain detectably therapeutic; intentionally low late concentrations are part of the strategy, not proof that treatment has stopped working.
Selected extended-interval protocols use 24-, 36-, or 48-hour intervals, but once-daily is an imprecise label when impaired clearance requires longer spacing. Some hospitals use a pre-dose concentration, some a single timed nomogram sample, and others 2 concentrations or model-based exposure estimates; these approaches are not interchangeable without their accompanying dosing rules.
Extended-interval treatment is not suitable for every patient or indication, and reduced renal toxicity in selected populations does not mean zero risk. Our vancomycin exposure monitoring guide explains another antibiotic-specific approach; the vancomycin AUC target of 400–600 mg·h/L is not a gentamicin target.
Kur mund të përdoret nomograma e Hartford-it për interpretimin e niveleve të gentamicinës?
The Hartford nomogram applies to qualifying extended-interval aminoglycoside treatment using a 7 mg/kg dose and a concentration collected 6–14 hours after infusion start. It helps clinicians choose an interval; it is not a universal chart for any gentamicin dose, any collection time, or any patient.

The original Hartford experience described 2,184 adult patients receiving a once-daily aminoglycoside program, providing the clinical background for its dose-and-time framework (Nicolau et al., 1995). The 6–14-hour measurement is sometimes called a random level, but random here means not a conventional peak or trough—not that its timing is optional.
Hospitals restrict or modify this approach in populations such as pregnancy, dialysis, unstable renal function, major burns, cystic fibrosis, or selected endocarditis regimens. A hypothetical concentration of 2.2 mg/L collected 10 hours after a 5 mg/kg dose cannot simply be plotted on an unmodified 7 mg/kg Hartford chart to obtain a reliable interval.
If the sample falls outside the validated window, clinicians may request another level or calculate individualized pharmacokinetics rather than force a point onto the chart. Our delayed drug-clearance explanation illustrates why elapsed time is part of a drug result, although methotrexate rescue thresholds have no role in gentamicin dosing.
Si krahasohen dy raporte hipotetike të gentamicinës?
Two identical gentamicin results can mean different things when the sampling schedules differ. The following 2 hypothetical examples demonstrate conventional and extended-interval interpretation; they are not dosing instructions, and neither example supplies enough information for a patient to choose the next dose.

In hypothetical example A, a conventional infusion starts at 08:00, ends at 08:30, and the prescribed peak sample is collected at 09:00. A result of 8 mg/L fits many conventional peak targets if the indication agrees; a separate 15:40 sample before a 16:00 dose provides the trough information that the peak cannot supply.
In hypothetical example B, an eligible 70 kg adult receives a clinician-prescribed 490 mg dose, corresponding to 7 mg/kg, with infusion start at 08:00. A sample at 18:00 is 10 hours after infusion start and is interpreted under the applicable extended-interval protocol; calling that result a low peak or a high trough would ask the wrong question.
Neither timeline establishes kidney safety without baseline and follow-up renal information, and the prescribed dosing weight may differ from scale weight. Before collection, patients can confirm that staff have the actual administration record and the intended test type; our baseline sample preparation checklist helps distinguish useful preparation from unnecessary fasting or medication changes.
Si e zbulojnë klinicistët dëmtimin e veshkave të lidhur me gentamicinën?
Clinicians assess possible gentamicin-associated kidney injury using creatinine changes, urine output, exposure history, and alternative causes—not the gentamicin concentration alone. KDIGO defines acute kidney injury by a creatinine rise of at least 0.3 mg/dL within 48 hours, a rise to at least 1.5 times baseline within 7 days, or qualifying low urine output.
I/E/Të/Të 0.3 mg/dL threshold equals 26.5 µmol/L, and it can identify injury even when both values sit inside the laboratory interval (KDIGO Acute Kidney Injury Work Group, 2012). For example, a hypothetical creatinine increase from 0.7 to 1.0 mg/dL within 48 hours meets that criterion; normal-looking is not the same as unchanged.
KDIGO's urine-output criterion includes less than 0.5 mL/kg/hour for 6 hours: for a 70 kg adult, that is below 35 mL/hour over the specified period. Gentamicin-associated injury can also be non-oliguric, meaning urine output remains relatively preserved, so passing urine normally does not rule out an important creatinine rise.
Sepsis, low blood pressure, dehydration, urinary obstruction, and other medicines can produce similar changes, and attribution requires clinical assessment. Our raporti BUN dhe kreatininë udhëzon explains useful context without treating the ratio as diagnostic; seek prompt advice for markedly reduced urine or the warning signs described in our low kidney function symptoms artikull.
Cilat kontrolle të funksionit të veshkave dhe të elektroliteve shoqërojnë matjen e niveleve të gentamicinës?
Gentamicin safety monitoring usually includes baseline and repeat serum creatinine, with electrolytes and urine assessment when clinically indicated. Hospitalized adults often have daily renal checks during ongoing treatment, but outpatient schedules depend on stability, treatment duration, local protocol, and whether a change occurs within 24–48 hours.
Creatinine is a delayed marker of changing filtration, and automated eGFR assumes relatively steady creatinine production and clearance. During evolving acute kidney injury, an eGFR reported as 60 mL/min/1.73 m² may not accurately describe current clearance; clinicians often rely on the trajectory and an appropriate drug-dosing renal assessment rather than the printed number alone.
Aminoglycoside-related tubular dysfunction can cause magnesium or potassium wasting, sometimes before a major creatinine increase. For example, a hypothetical magnesium of 0.55 mmol/L with new weakness deserves assessment of renal losses, gastrointestinal losses, and medicines; our electrolyte safety patterns explain why replacement must reflect the whole clinical picture.
Urinary granular casts can support tubular injury but neither prove gentamicin caused it nor reliably exclude injury when absent. Our granular cast interpretation guide separates suggestive findings from diagnosis; the broader udhëzues për interpretimin e analizës së urinës explains why 1 urine specimen cannot substitute for serial renal assessment.
Kush ka nevojë për monitorim më të individualizuar të sigurisë gjatë përdorimit të gentamicinës?
Patients with unstable kidney function, major changes in body-fluid volume, repeated exposure, or concurrent nephrotoxic medicines need particularly individualized gentamicin monitoring. Older adults, neonates, pregnancy, dialysis, obesity, and severe illness can also make standard adult dosing assumptions unreliable; a 7 mg/kg protocol should not be generalized across these groups.

Risk generally increases with cumulative exposure and longer treatment, particularly when courses extend beyond approximately 5–7 days, although shorter courses are not risk-free. Concurrent vancomycin, amphotericin B, some chemotherapy agents, and nonsteroidal anti-inflammatory medicines can complicate renal safety; dehydration or low blood pressure may add a second stressor rather than an independent laboratory clue.
The dosing weight is not always the measured weight: obesity may require an adjusted-weight method, while ascites, edema, major burns, or critical illness can alter the distribution volume. A hypothetical 100 kg patient therefore should not calculate a dose by multiplying scale weight by 7; the hospital's weight convention and renal method are part of the prescription.
A creatinine clearance expressed in mL/min is not identical to an indexed eGFR expressed in mL/min/1.73 m², and low muscle mass can hide impaired filtration behind a modest creatinine value. Our dehydration and filtration explanation describes reversible changes, but a new decline during gentamicin treatment still needs review rather than being assumed temporary.
A mund të ndikojë gentamicina në dëgjim ose ekuilibër edhe kur nivelet janë të pranueshme?
Gentamicin can cause hearing or vestibular toxicity even when measured concentrations fall within the prescribed targets. New tinnitus, hearing change, unsteadiness, or oscillopsia—vision that appears to bounce during walking—requires prompt contact with the treatment team; there is no serum concentration that guarantees inner-ear safety.

Gentamicin is particularly associated with vestibular toxicity, which affects balance and visual stability rather than hearing alone. Bilateral vestibular impairment may cause difficulty walking in darkness or bouncing vision without dramatic spinning vertigo; after even 1 new symptom, patients should report the change instead of waiting for the next routine blood test.
Baseline hearing and balance history helps interpret subsequent changes, and clinicians may arrange audiometry, including high-frequency assessment, or vestibular testing for prolonged or higher-risk treatment. A normal conventional hearing test does not exclude early high-frequency change or a vestibular problem; symptoms can emerge or progress after the final dose, and some effects are permanent.
I/E/Të/Të MT-RNR1 variants m.1555A>G and m.1494C>T are associated with increased aminoglycoside-related hearing-loss risk. The CPIC guideline recommends avoiding aminoglycosides in people with relevant high-risk variants unless the seriousness of the condition and lack of suitable alternatives justify treatment (McDermott et al., 2022); genetic testing must not delay urgent treatment without a clinician-directed plan.
Kantesti është një platformë e interpretimit të analizave të gjakut AI, but a gentamicin concentration of 0.8 mg/L cannot establish normal hearing or vestibular function. Our kufijtë e përdorimit të përgjegjshëm të inteligjencës artificiale explain why laboratory interpretation must remain separate from examination, audiology, emergency assessment, and decisions about the next antibiotic administration.
Çfarë duhet të bëni nëse rezultati i gentamicinës është i papritur?
Contact the prescribing team or clinical pharmacist about an unexpected gentamicin result, especially when the next dose is approaching or symptoms have appeared. Do not independently change the dose or interval; a concentration of 2 mg/L means different things under different protocols, and an urgent decision needs the administration record.

Provide 5 practical details: the reported concentration and units, dose, infusion start and finish, sample collection time, and the latest creatinine with its earlier baseline. Also mention missed or delayed doses, urine changes, tinnitus, hearing change, imbalance, and nonprescription medicines; symptoms deserve attention even when the laboratory has not marked the result high.
If you are in hospital, alert the nurse or treatment team immediately rather than altering the infusion equipment yourself. If you receive home infusions, use the service's urgent contact route before the next planned administration when there is a concerning result; our secure clinical result-sharing guide explains how to preserve the original report and its timestamps.
Kantesti AI can support explanation of units and trends, but it cannot confirm whether an 18:00 sample belongs on a hospital's nomogram or authorize a treatment change. When sharing results for educational interpretation, remove unnecessary identifiers and review our informacionin për privatësinë dhe të dhënat; privacy precautions must never delay urgent medical contact.
Konteksti i kërkimeve dhe kufizimet e interpretimit të gentamicinës nga AI
Clinical interpretation of gentamicin levels depends on validated dosing protocols, kidney-injury definitions, and separate assessment of hearing and balance. The 3 external medical references below support those clinical discussions; the 2 additional Kantesti publications describe platform or educational work and are not gentamicin dosing or toxicity-validation studies.

The Hartford program, KDIGO acute kidney injury criteria, and CPIC aminoglycoside pharmacogenetics guideline answer 3 different questions: how to interpret a qualifying timed level, how to recognize kidney injury, and when genetic susceptibility changes antibiotic selection. None can turn an unlabeled concentration into a complete treatment decision, and differences between hospital targets should be resolved using the patient's actual protocol.
Kantesti është një Mjet për analizën e testeve të gjakut me AI that can help organize gentamicin results alongside creatinine and electrolyte trends when the required context is supplied. A 0.3 mg/dL creatinine rise still requires clinician assessment regardless of how a report is summarized; our teknike dhe klinike describes evaluation boundaries rather than claiming validation for autonomous gentamicin dosing.
The Global Health Report 2026 and the RDW guide listed below are 2 separate publications, not evidence that AI can prevent aminoglycoside toxicity. Kantesti's standardet e përmbajtjes mjekësore distinguish educational interpretation from prescribing; patients should use this article to ask better timing and safety questions, not to choose their next dose.
Pyetjet e bëra shpesh
Cili është niveli normal i gentamicinës në fund të intervalit të dozimit?
Niveli minimal i gentamicinës zakonisht synohet të jetë nën 1 mg/L, megjithëse disa protokolle përdorin vlerën nën 2 mg/L. Zakonisht, mostra duhet të merret brenda 30 minutave para dozës së ardhshme reale, jo thjesht para orarit të saj të caktuar. Regjimet me interval të zgjatur mund të përdorin një prag tjetër para dozës ose një përqendrim të përcaktuar me nomogram sipas kohës. Një nivel minimal i pranueshëm nuk përjashton toksicitetin ndaj veshkave, dëgjimit ose ekuilibrit.
Kur duhet të merret mostra për matjen e nivelit maksimal të gentamicinës?
A conventional intravenous gentamicin peak level is commonly collected 30 minutes after the infusion ends, but the prescribing service's protocol determines the exact time. For example, an infusion ending at 08:30 may require collection at 09:00 under that protocol. A sample collected immediately after infusion or much later cannot automatically be compared with the same target. Extended-interval monitoring and intramuscular administration use different sampling conventions.
A është shumë i lartë niveli i gentamicinës prej 2 mg/L?
Një nivel gentamicine prej 2 mg/L nuk mund të klasifikohet pa regjimin e dozimit dhe kohën e marrjes së mostrës. Ai do të tejkalonte objektivin në shumë protokolle konvencionale të përqendrimit minimal para dozës, por mund të jetë një përqendrim i pritshëm i matur në një kohë të caktuar gjatë një regjimi me interval të zgjatur. Një mostër e marrë herët, vonë ose nga një linjë infuzioni e kontaminuar mund të ndikojë gjithashtu në interpretimin e saj. Kontaktoni ekipin që ka përshkruar trajtimin, në vend që ta ndryshoni vetë dozën e ardhshme.
Kur merret niveli i gentamicinës për dozimin një herë në ditë?
Për një skemë Hartford prej 7 mg/kg që plotëson kriteret, përqendrimi i gentamicinës matet 6–14 orë pas fillimit të infuzionit. Protokollet e tjera me interval të zgjatur mund të përdorin një matje para dozës, 2 matje pas dozës ose një grafik tjetër të dozës dhe kohës. Fjala «rastësor» nuk do të thotë se koha e marrjes së mostrës nuk ka rëndësi. Përqendrimi duhet interpretuar vetëm sipas protokollit të përshtatshëm për dozën e administruar dhe pacientin.
A mund t’i dëmtojë gentamicina veshkat kur niveli është normal?
Dëmtimi i veshkave i lidhur me gentamicinën mund të ndodhë edhe kur përqendrimet janë brenda objektivave të përshkruar, sepse kanë rëndësi edhe ekspozimi kumulativ dhe rreziku specifik për pacientin. Rritja e kreatininës me të paktën 0,3 mg/dL, ose 26,5 µmol/L, brenda 48 orëve plotëson një kriter KDIGO për dëmtimin akut të veshkave. Sasia e urinës mund të mbetet relativisht normale në dëmtimin tubular të lidhur me aminoglikozidet. Mjekët vlerësojnë kreatininën në matje të njëpasnjëshme, sasinë e urinës, barnat e tjera dhe shkaqet alternative, në vend që të mbështeten te një nivel i vetëm i barit.
A mund të shkaktojë gentamicina humbje të dëgjimit ose marramendje pas trajtimit?
Simptomat e dëgjimit ose ekuilibrit të lidhura me gentamicinën mund të shfaqen ose të përparojnë pasi trajtimi të ketë përfunduar, dhe nivelet e pranueshme në serum nuk e përjashtojnë këtë mundësi. Edhe 1 simptomë e re—si zhurma në veshë, ndryshimi i dëgjimit, ekuilibri i dëmtuar vazhdimisht ose lëkundja e shikimit gjatë ecjes—meriton vlerësim të menjëhershëm klinik. Gentamicina mund të ndikojë në funksionin vestibular pa humbje të dukshme të dëgjimit ose marramendje rrotulluese. Vlerësimi mund të përfshijë teste të dëgjimit dhe vestibulare, sepse përqendrimi i gentamicinës nuk është test i funksionit të veshit të brendshëm.
Merrni shpjegimin e rezultateve të analizave të gjakut
Ngarkoni raportin tuaj laboratorik dhe AI e Kantesti shpjegon çdo biomarker me gjuhë të thjeshtë brenda pak sekondash. Përdoret nga më shumë se 2 milionë njerëz në mbarë botën.
Referencat
- Klein, T., Mitchell, S., & Weber, H. (2026). Analizues i Analizave të Gjaku me AI: 2.5M Teste të Analizuara | Raporti Global i Shëndetit 2026. Kërkim mjekësor me Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Analiza e gjakut RDW: Udhëzues i plotë për RDW-CV, MCV dhe MCHC. Kërkim mjekësor me Kantesti AI. DOI
- Nicolau DP et al. (1995). Experience with a once-daily aminoglycoside program administered to 2,184 adult patients. Antimicrobial Agents and Chemotherapy. DOI
- KDIGO Acute Kidney Injury Work Group (2012). KDIGO Clinical Practice Guideline for Acute Kidney Injury. Kidney International Supplements.
- McDermott JH et al. (2022). Clinical Pharmacogenetics Implementation Consortium Guideline for the Use of Aminoglycosides Based on MT-RNR1 Genotype. Clinical Pharmacology & Therapeutics. DOI
- 2M+Analizat e kryera
- 127+Vendet
- 100+Gjuhët
Rreth ekipit mjekësor


Sinjalet e Besimit E-E-A-T
Përvoja
Rishikim klinik i udhëhequr nga mjeku i flukseve të punës për interpretimin e analizave.
Ekspertizë
Fokus i mjekësisë laboratorike mbi mënyrën se si sillen biomarkerët në kontekstin klinik.
Autoritariteti
Rishikuar nga ana mjekësore nga Dr. Thomas Klein, me kontribute nga Dr. Sarah Mitchell dhe Prof. Dr. Hans Weber.
Besueshmëria
Interpretim i bazuar në prova, me rrugë të qarta për ndjekje për të reduktuar alarmin.






Mohim përgjegjësie mjekësore
Ky artikull është vetëm për qëllime edukative dhe nuk përbën këshilla mjekësore. Gjithmonë konsultohuni me një ofrues të kualifikuar të kujdesit shëndetësor për vendimet e diagnozës dhe trajtimit.
Botuar · Kontaktoni ekipin redaktues
Botuar nga Kantesti Ltd, e regjistruar në Angli dhe Uells, nr. i kompanisë. 17090423, Londër, Mbretëria e Bashkuar.
