
PCR detects the organism; antibodies record the immune response. Matching both results to symptom onset and antibiotic timing explains apparent contradictions.

Vigtigste pointer
- Tidlig PCR is most useful during the first week of illness; positive whole-blood PCR provides clear evidence of active anaplasmosis.
- Early antibodies can remain negative during week 1, so a positive PCR with negative IgG is an expected pattern—not necessarily a laboratory mistake.
- Negativ PCR does not exclude anaplasmosis, especially after antibiotics; PCR sensitivity can decrease within 48 hours of appropriate treatment.
- Paired IgG samples are collected during the first 2 weeks of illness and again 2–10 weeks later; a fourfold rise supports confirmation of recent infection.
- Single positive IgG cannot establish a new infection. A titer of at least 1:128 is supportive evidence under CDC guidance, not a stand-alone treatment instruction.
- Behandlingstidspunkt depends on clinical suspicion, not confirmation alone. Clinicians should not delay doxycycline while awaiting results when anaplasmosis is suspected.
- Other tick-borne illnesses require their own tests. Anaplasma PCR does not test for Lyme disease, babesiosis, ehrlichiosis, or Rocky Mountain spotted fever.
- Akutte symptomer such as confusion, difficulty breathing, new bleeding, or markedly reduced urination require emergency assessment rather than waiting for a repeat sample.
Why can early PCR and antibody results disagree?
Anaplasmosis test results can disagree because PCR detects bacterial DNA while IgG detects an immune response that develops later. During the first week, PCR may be positive and antibodies negative; after treatment, PCR may become negative while IgG rises, and suspected infection may still require treatment before laboratory confirmation.
Anaplasma phagocytophilum causes human granulocytic anaplasmosis and primarily affects neutrophils, a type of white blood cell. Symptoms usually begin 5–14 days after an infected tick bite, but many people never notice the tick; the useful laboratory clock starts with the first day of illness, not an uncertain exposure date.
A result collected on illness day 3 answers a different question from one collected on day 24, even when both reports say Anaplasma. The real-time PCR comparison published in the Journal of Clinical Microbiology found that diagnostic yield depended on illness timing, explaining why direct detection and serology should be interpreted together rather than ranked as interchangeable tests (Schotthoefer et al., 2013).
Kantesti er en AI blodprøveanalysator that can help explain the relationship between an Anaplasma report and accompanying CBC or liver results, but it cannot establish the diagnosis from numbers alone. For a useful interpretation, provide 3 details: symptom onset, sample collection date, and the first antibiotic dose; information about vores organisation explains the service's role.
What does an Anaplasma PCR positive result mean?
An anaplasma PCR positive result means the assay detected Anaplasma DNA in the submitted specimen. In a person with a compatible acute illness, a positive species-specific whole-blood PCR is clear evidence of active anaplasmosis; it does not measure antibody levels, establish illness severity, or identify every possible tick-borne coinfection.

EDTA whole blood is commonly used for Anaplasma PCR because the organism is associated with circulating cellular elements. A serum antibody specimen is not automatically an acceptable substitute: before interpreting 2 apparently conflicting results, check that the laboratory received the specimen required for each assay and that both collection dates are correctly recorded.
A hypothetical report reading 'A. phagocytophilum DNA detected' on illness day 4, with fever and falling platelets, strongly supports the clinical diagnosis. A report reading only 'Anaplasma species detected' may come from a broader assay, so the exact target matters; ask whether the result identifies A. phagocytophilum specifically or requires additional laboratory clarification.
A qualitative PCR is not a bacterial-load score. Even if a report includes a cycle-threshold value, there is no universal Anaplasma threshold that predicts hospitalization or dictates treatment length; our explanation of kvalitativ versus kvantitativ resultat helps distinguish detection from a standardized concentration measurement.
When is Anaplasma PCR most useful?
Anaplasma PCR is most sensitive during the first week of illness, before appropriate antibiotics reduce circulating bacterial DNA. CDC guidance states that sensitivity decreases within 48 hours of appropriate antibiotic administration; this is a reduction in diagnostic yield, not a guarantee that every treated sample will become negative at the same hour.

Obtain the PCR specimen before treatment when that can be done immediately, but never postpone necessary treatment to arrange the draw. For example, a sample collected on day 5 before the first doxycycline dose is generally more informative than one collected on day 7 after several doses; the MMWR guideline explicitly prioritizes prompt treatment over waiting for confirmation (Biggs et al., 2016).
The 48-hour statement does not apply equally to every antibiotic a person may have taken. A prior course of an antibiotic that does not reliably treat anaplasmosis cannot be assumed to have the same effect as doxycycline; record the drug name, dose, and dose times rather than writing only 'already on antibiotics.'
If the first PCR was collected after 3 days of doxycycline, a negative result should be interpreted with that limitation visible on the report review. Repeating PCR without changing the timing problem may add little; arranging convalescent IgG may be more informative, and a dated blood test timeline prevents treatment-related changes from being mistaken for contradictory evidence.
What is the meaning of an Anaplasma IgG positive result?
The anaplasma IgG positive meaning is evidence of an antibody response, not automatic proof of a current infection. A single IgG result may reflect recent illness, previous exposure, or cross-reactivity; CDC considers a single titer of at least 1:128 supportive laboratory evidence, while confirmation usually requires the clinical picture and direct detection or paired serology.

Anaplasma IgG can remain elevated for months, and high titers have been reported up to 4 years after illness. Persistently positive antibodies in a well person do not by themselves justify another antibiotic course; the relevant question is whether there is a new compatible illness, a new exposure, or evidence that the antibody level has changed meaningfully.
In some areas, approximately 5–10% of healthy people may have elevated Anaplasma antibodies because of previous exposure or related organisms, according to CDC testing guidance. That estimate is geographically dependent, not a universal false-positive rate; a low positive in someone with no fever or plausible tick exposure carries a different meaning from the same result during an acute illness.
Kantesti treats 1 positive antibody result as a finding to explain, not a diagnosis to announce. The distinction between immune memory and active disease is covered in fortolkning af positive antistofresultater; unlike some vaccine antibody tests, Anaplasma IgG does not provide an established protective-immunity threshold.
How do paired IgG samples confirm recent infection?
Paired Anaplasma IgG testing compares an acute specimen from the first 2 weeks of illness with a convalescent specimen collected 2–10 weeks later. A fourfold rise in IgG titer by indirect fluorescent antibody testing is evidence of seroconversion and helps confirm recent infection when the early result was negative or PCR was unavailable.

A rise from 1:64 to 1:256 is fourfold; a rise from 1:128 to 1:256 is only twofold. In a hypothetical case, an illness-day-4 titer of 1:64 and a day-28 titer of 1:256 would meet the fourfold criterion, while the smaller increase would not independently confirm infection by that criterion.
Titers are reciprocal dilutions, not concentrations in mg/dL or arbitrary screen-index units. If the acute report gives an index of 1.4 and the later report gives a titer of 1:256, a fourfold change cannot be calculated directly; use the same laboratory and method where possible, and ask whether archived samples can be compared together.
Antibody responses may be weaker or delayed in people receiving immunosuppressive treatment. A person taking B-cell-depleting therapy, for example, may not produce the expected rise over 2 samples, so clinicians may rely more heavily on PCR, clinical findings, and exposure history; IgG, IgA, and IgM patterns can provide background context but do not replace organism-specific testing.
Why are IgM and cross-reactive antibodies unreliable?
Anaplasma IgM is not a reliable stand-alone marker of recent anaplasmosis, and antibodies can cross-react with related Ehrlichia organisms. When both illnesses are plausible, clinicians may request 2 separate organism-specific PCR tests and side-by-side IgG testing; dual antibody positivity does not automatically establish 2 active infections.
IgM does not consistently mean 'new infection' in anaplasmosis. An isolated IgM positive result with negative IgG and negative PCR is therefore insufficient confirmation, particularly if it was obtained on day 2 of a nonspecific illness; the recommended serologic approach is paired IgG interpreted alongside symptoms and the direct-detection window.
Anaplasma phagocytophilum and Ehrlichia species are different organisms, despite overlapping fever, headache, cytopenias, and antibody cross-reactivity. A positive Ehrlichia antibody assay does not substitute for an Anaplasma PCR result; our guide to ehrlichiosis PCR and titers explains why testing for each target matters when 2 diagnoses remain plausible.
Babesia requires separate assessment because doxycycline does not treat babesiosis. In a patient with anemia, elevated LDH, low haptoglobin, or persistent fever after 48 hours of appropriate anaplasmosis treatment, clinicians may consider Babesia PCR or a manually reviewed smear; Babesia-antistoffer versus infektion explains why an antibody result alone can also mislead.
Can negative results still be anaplasmosis?
An anaplasmosis test false negative is possible when antibodies are checked too early or PCR is collected after its best detection window or after treatment. Negative PCR plus negative IgG during week 1 does not reliably exclude the illness; clinicians must weigh exposure, symptoms, CBC changes, liver enzymes, and the timing of both tests.

There is no single dependable false-negative percentage for every Anaplasma test. PCR assays differ, studies use different reference standards, and patients present on different illness days; a sensitivity estimate from untreated day-3 specimens cannot simply be applied to a day-9 sample obtained after 4 days of doxycycline (Schotthoefer et al., 2013).
A hypothetical person has fever, platelets of 78 × 10^9/L, a WBC of 2.9 × 10^9/L, and recent woodland exposure, but both tests are negative on illness day 4. That pattern leaves substantial clinical concern even without confirmation; by contrast, the same negative tests in a well person with normal counts and no plausible exposure answer a much lower-risk question.
Kantesti er en AI blodprøvefortolkningsplatform that can explain why 2 negative tests may be limited by their collection dates, but it cannot determine whether antibiotics are needed. Our kliniske valideringsstrategi beskriver sikkerhedsforanstaltninger ved fortolkning, mens checking report source details helps readers verify specimen type, method, and reference comments before relying on a summary.
Which CBC and liver findings support the diagnosis?
Low white blood cells, low platelets, and raised AST or ALT commonly support suspicion of anaplasmosis, but none is diagnostic alone. Many adult laboratories use WBC reference intervals around 4.0–11.0 × 10^9/L and platelet intervals around 150–450 × 10^9/L; use the ranges printed on your own report.
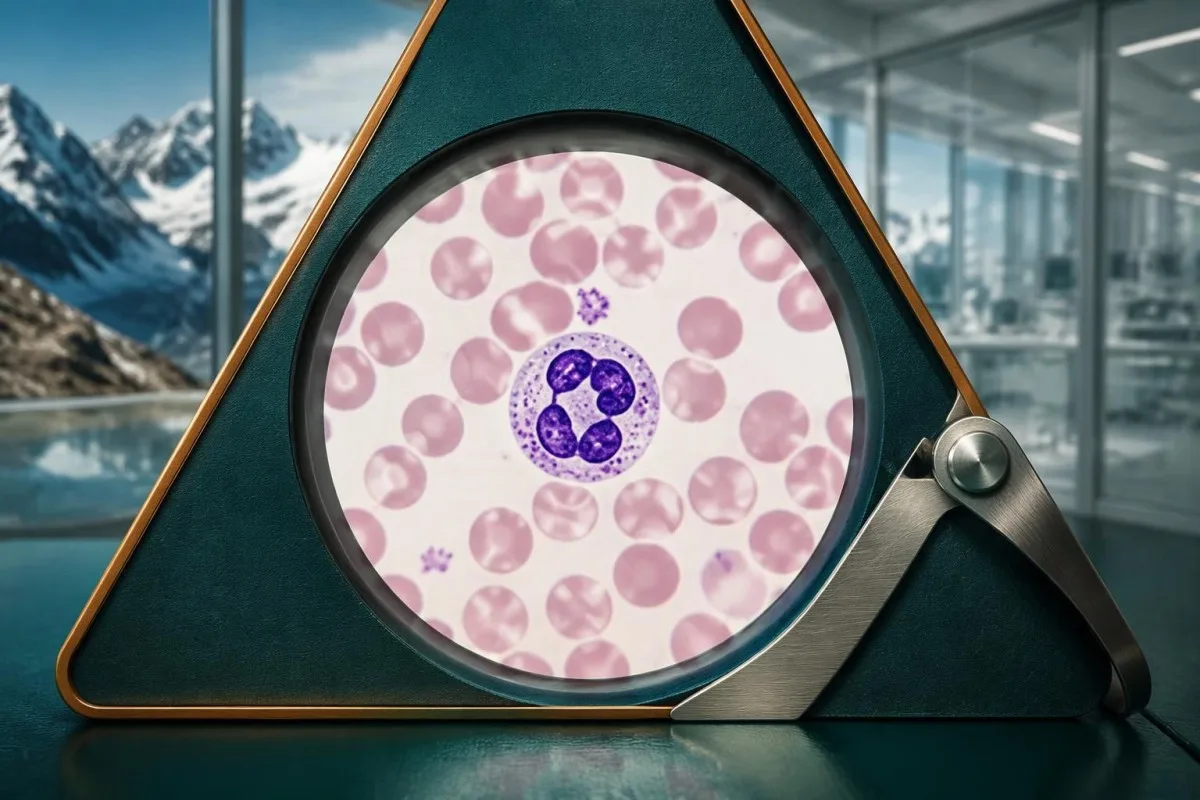
A falling platelet count can be more informative than one mildly low result. A hypothetical decline from 182 to 84 × 10^9/L over 3 days during fever suggests an acute process, whereas a stable count of 138 × 10^9/L for years has a different context; plateletcrit and platelet count are related measurements, but plateletcrit is not an Anaplasma diagnostic test.
AST and ALT indicate cellular injury rather than identifying the organism. An AST of 84 IU/L is approximately 2.1 times an upper limit of 40 IU/L, but muscle injury, other infections, and medication effects can also produce that result; what ALT measures helps distinguish supportive liver findings from proof of a specific cause.
Morulae are clusters of organisms that may be visible inside granulocytes during the first week. Their absence does not exclude anaplasmosis, and their presence is not reliably species-specific because some Ehrlichia organisms can also affect granulocytes; manual microscopy can provide a fast clue, but PCR is needed for clearer organism identification (Bakken and Dumler, 2015).
| Niveau | Interval | Hvad det betyder |
|---|---|---|
| Almindeligt WBC-interval for voksne | 4,0–11,0 × 10^9/L | Laboratory-dependent reference interval; a normal WBC does not exclude early anaplasmosis. |
| WBC below the local interval | Often <4.0 × 10^9/L | Leukopenia supports suspicion during a compatible acute illness but has many other causes. |
| Common adult platelet interval | 150–450 × 10^9/L | Check the local interval and previous results before interpreting a borderline value. |
| Platelets below the local interval | Often <150 × 10^9/L | Thrombocytopenia is a supportive clue; rapid decline and symptoms determine urgency. |
How do Anaplasma tests differ from other tick-borne tests?
Anaplasma PCR, Lyme serology, Babesia testing, Ehrlichia PCR, and spotted-fever serology detect different targets and cannot substitute for one another. A laboratory panel tests only the organisms explicitly listed; a negative result for 1 target is not a negative result for all tick-borne illnesses.
Lyme disease is usually evaluated with a validated two-tier antibody algorithm when testing is indicated. A classic expanding erythema migrans rash can be diagnosed clinically without waiting for positive antibodies, while marked leukopenia or thrombocytopenia should raise concern for an additional diagnosis; an Anaplasma PCR result does not answer either of these 2 Lyme questions.
Rocky Mountain spotted fever may have negative early serology, and whole-blood PCR is less reassuring when negative than it is for some circulating-cell infections. Rash appearance and specimen choice matter, but absence of rash does not make waiting safe; spotted-fever testing windows explains why the Anaplasma PCR window cannot simply be transferred to that illness.
Alpha-gal syndrome is a tick-associated allergy, not an Anaplasma infection. Delayed allergic symptoms roughly 2–6 hours after mammalian meat exposure require an allergy-focused history and appropriate IgE testing rather than PCR or paired Anaplasma IgG; alpha-gal IgE interpretation illustrates how one exposure category can lead to very different diagnostic pathways.
Why might treatment start before confirmation?
Suspected anaplasmosis should be treated promptly because early tests can be negative and delayed therapy can allow severe illness to develop. The MMWR guideline recommends that clinicians neither delay treatment while awaiting laboratory results nor withhold treatment because an early test is negative; the usual adult doxycycline dose is 100 mg every 12 hours (Biggs et al., 2016).

CDC recommends doxycycline for anaplasmosis in adults and children of all ages. For children weighing less than 45 kg, the usual dose is 2.2 mg/kg every 12 hours, with a maximum of 100 mg per dose; these are clinician-prescribed regimens, not instructions to start leftover medication or adjust a child's dose without assessment.
Treatment commonly lasts 10–14 days to provide coverage for possible concurrent Borrelia infection. Duration still depends on the suspected coinfections and clinical course, so an improving fever after 2 doses is not a reason to stop early; pregnancy, severe drug allergy, vomiting, or organ dysfunction require individualized decisions, sometimes with infectious-disease input.
Starting doxycycline is a clinical decision based on exposure, symptoms, examination, and the overall pattern—not on a single CRP or WBC cutoff. A WBC of 3.0 × 10^9/L during acute fever may strengthen concern even when CRP is only modestly raised; inkonsistent infektion blodmarkører explains why one reassuring-looking number should not overrule the complete assessment.
What response is expected, and when is care urgent?
Fever from anaplasmosis usually improves within 24–48 hours of doxycycline, but severe illness may take longer. Difficulty breathing, confusion, new bleeding, fainting, or markedly reduced urination requires emergency assessment; failure to improve is a reason for reassessment, not an instruction to increase the antibiotic dose yourself.
Persistent fever beyond about 48 hours should prompt review of the diagnosis, medication delivery, and possible coinfections. The person may not be absorbing oral treatment because of vomiting, may have an additional illness such as babesiosis, or may have developed a complication; the interval is a practical reassessment point rather than an absolute recovery deadline.
Severe anaplasmosis can involve respiratory failure, kidney injury, or coagulation abnormalities. Falling platelets accompanied by rising creatinine, prolonged clotting times, or new bleeding should not be dismissed as a routine CBC fluctuation; disseminated coagulation laboratory patterns explains why 2 or more changing systems can signal a problem beyond an isolated low count.
Clotting tests assess complications rather than confirming Anaplasma itself. For example, an INR of 1.8 in someone not taking warfarin needs explanation in context, but does not establish anaplasmosis or DIC on its own; our vejledning til fortolkning af koagulationsprøver helps separate PT, aPTT, D-dimer, and platelet findings without treating them as interchangeable measurements.
Should PCR or antibodies be repeated after treatment?
Routine PCR or IgG testing is generally not needed to prove cure after clinically successful anaplasmosis treatment. A convalescent IgG sample collected 2–10 weeks after the acute sample can document the diagnosis, but persistent antibodies alone do not demonstrate treatment failure and should not trigger repeated antibiotics in a well person.

A persistently positive IgG is not a test-of-cure result. If a person is well after a completed 10–14-day course, an elevated titer may simply reflect immune memory; if symptoms recur, clinicians should reassess the new symptoms and exposure history rather than assume that the old antibody result proves persistent infection.
CBC, creatinine, and liver enzymes may be repeated when they were abnormal or the illness was severe, but there is no universal day-7 retesting schedule for everyone. Kantesti AI can help organize serial results—for example, platelets rising from 82 to 164 × 10^9/L—while gennemgang af medicinsikkerhedstendenser explains why recovery patterns still require clinical context.
Antibiotic prophylaxis after a tick bite is not recommended specifically to prevent anaplasmosis. After an asymptomatic bite, monitor for fever or other illness over the following 2 weeks and obtain medical advice if symptoms appear; a separate Lyme prophylaxis decision, when indicated, should not be mistaken for an Anaplasma prevention protocol.
How can you organize a confusing report safely?
The safest report review separates organism detection, antibody evidence, supportive blood findings, and clinical timing into 4 distinct questions. Record the assay target, specimen type, result format, collection date, symptom-onset date, and antibiotic start; missing context should remain explicitly unknown rather than being filled in by an AI explanation.

Kantesti er en AI lab testfortolkningsservice that can explain uploaded laboratory reports and help readers identify questions for their clinician. In a hypothetical 2-report review, our AI should distinguish 'PCR not detected after treatment' from 'paired IgG rise consistent with recent infection,' rather than flattening both statements into a single positive-or-negative label.
An upload is not a substitute for urgent assessment. A photo showing platelets of 74 × 10^9/L cannot reveal whether the person is confused, dehydrated, pregnant, or short of breath; our AI fortolkningsteknologi describes the analytical workflow, but clinical observations and prescribing decisions remain outside what the report alone can establish.
Before sharing 2 samples, check that both belong to the same person and remove identifiers if they are not needed for your purpose. Kantesti does not perform Anaplasma PCR, validate specimen handling, or confirm that an uploaded titer used the same laboratory method; retain the original PDF and ask the laboratory to resolve unclear assay comments or mismatched result units.
Which evidence should guide your next steps?
Anaplasmosis testing decisions should follow condition-specific guidance and diagnostic research, not general blood-test publications. The 2016 MMWR guideline, the 2013 PCR comparison, and the 2015 clinical review support the distinction between early direct detection, later antibody confirmation, and treatment based on clinical suspicion rather than a single laboratory result.

Bring 3 questions to the clinical review: was PCR collected early enough, is paired IgG needed, and do other tick-borne targets require separate testing? If the first specimen followed several doxycycline doses, say so; if the report is a single low-positive IgG, ask what evidence supports current illness before assuming that another antibiotic course is required.
At Kantesti, we distinguish externally published medical evidence from our own educational resources. Our standarder for medicinsk indhold explain that distinction; the 2 Figshare publications listed below are supplementary general laboratory and digestive-health guides, not studies establishing Anaplasma assay accuracy, treatment efficacy, or diagnostic thresholds.
The general hematology guide can help explain LDH and reticulocyte results when anemia raises a separate concern such as hemolysis. Use the hematology marker background guide for that limited purpose, not to interpret Anaplasma PCR; a 4-fold IgG rise, a positive organism-specific PCR, and the patient's clinical course each provide different kinds of evidence.
Ofte stillede spørgsmål
Kan Anaplasma-PCR være positiv, når antistofferne er negative?
Anaplasma-PCR kan være positiv, mens IgG-antistofferne er negative i sygdommens første uge, fordi bakterielt DNA kan påvises, før antistofresponset udvikles. Dette mønster kan understøtte aktiv anaplasmose frem for at tyde på en laboratoriefejl. En akut IgG-prøve kan sammenlignes med en konvalescent prøve, der er indsamlet 2–10 uger senere. Behandlingen bør ikke udsættes, mens man afventer serokonversion, når der er klinisk mistanke om sygdommen.
Betyder et positivt Anaplasma-IgG, at jeg har brug for antibiotika?
Et enkelt positivt Anaplasma-IgG-resultat betyder ikke automatisk, at der er behov for antibiotika, da antistoffer kan afspejle tidligere eksponering eller krydsreaktivitet. CDC betragter en enkelt titer på mindst 1:128 som understøttende evidens, men ikke som endeligt bevis på en ny infektion. Antistoffer kan forblive forhøjede i flere måneder, og der er rapporteret høje titere op til 4 år efter sygdommen. Klinikere baserer behandlingen på aktuelle symptomer, eksponering, PCR-resultater og parrede antistofresultater frem for IgG, der alene forbliver forhøjet.
Hvor hurtigt kan doxycyclin gøre Anaplasma-PCR negativ?
Anaplasma PCR sensitivity can decrease within 48 hours of appropriate antibiotic treatment, according to CDC guidance. That does not mean every person's PCR becomes negative at exactly 48 hours, because assay performance and circulating organism levels differ. A negative PCR collected after treatment is therefore less reassuring than a well-timed pretreatment result. Record the first doxycycline dose and specimen collection time so the clinician can interpret the result correctly.
Hvad tæller som en firedobling af antistoffer mod Anaplasma?
A rise in Anaplasma IgG titer from 1:64 to 1:256 is fourfold, while a rise from 1:128 to 1:256 is only twofold. Paired testing generally compares an acute specimen from the first 2 weeks of illness with a convalescent specimen collected 2–10 weeks later. The comparison should use compatible methods, ideally the same laboratory's IgG indirect fluorescent antibody assay. An antibody screen index cannot be directly converted into a dilution titer for this calculation.
Kan jeg have anaplasmose, hvis både PCR og IgG er negative?
Anaplasmose kan stadig være til stede, selvom både PCR og IgG er negative, særligt hvis IgG-prøven blev taget i uge 1, og PCR-prøven blev taget efter relevant antibiotikabehandling. Feber, sandsynlig eksponering for flåter, lavt antal blodplader, lavt antal hvide blodlegemer og forhøjede leverenzymer kan opretholde den kliniske mistanke trods negative testresultater. Klinikere kan bestille en konvalescent IgG-prøve 2–10 uger efter den akutte prøve og vurdere andre mulige diagnoser. Mistanke om anaplasmose bør ikke stå ubehandlet alene, fordi de tidlige testresultater er negative.
How quickly should symptoms improve, and do I need a test of cure?
Fever from anaplasmosis usually improves within 24–48 hours of doxycycline, although severe illness may take longer. Persistent fever should prompt reassessment for medication absorption problems, another diagnosis, coinfection, or complications. Routine PCR or antibody testing is generally unnecessary to prove cure after successful treatment; paired IgG is mainly used to document recent infection. Difficulty breathing, confusion, new bleeding, or markedly reduced urination requires urgent assessment regardless of the laboratory result.
Få dine blodprøveresultater forklaret
Upload din laboratorierapport, så forklarer Kantesti's AI hver biomarkør i et letforståeligt sprog på få sekunder. Bruges af mere end 2 millioner mennesker verden over.
Referencer
- Klein, T., Mitchell, S., & Weber, H. (2026). Vejledning om blodtype B negativ, LDH-blodprøve og retikulocyttal. Kantesti AI Medicinsk forskning. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Diarré efter faste, sorte prikker i afføringen og mave-tarm-vejledning 2026. Kantesti AI Medicinsk forskning. DOI
- Biggs HM et al. (2016). Diagnose og behandling af flåtbårne rickettsiesygdomme: Rocky Mountain spotted fever og andre rickettsioser i spotted fever-gruppen, ehrlichiose og anaplasmose — USA. MMWR Recommendations and Reports. DOI PubMed
- Schotthoefer AM et al. (2013). Comparison of a real-time PCR method with serology and blood smear analysis for diagnosis of human anaplasmosis: importance of infection time course for optimal test utilization. Journal of Clinical Microbiology. DOI
- Bakken JS and Dumler JS (2015). Human granulocytic anaplasmosis. Infectious Disease Clinics of North America.
- 2 mio.+Analyserede test
- 127+lande
- 100+Sprog
Om det medicinske team


E-E-A-T Trust Signals
Erfaring
Lægefagligt ledet klinisk gennemgang af arbejdsgange til laboratorietolkning.
Ekspertise
Fokus på laboratoriemedicin på, hvordan biomarkører opfører sig i klinisk kontekst.
Autoritet
Medicinsk gennemgået af Dr. Thomas Klein med bidrag fra Dr. Sarah Mitchell og Prof. Dr. Hans Weber.
Troværdighed
Evidensbaseret fortolkning med klare opfølgningsspor for at reducere alarm.






Medicinsk ansvarsfraskrivelse
Denne artikel er kun til undervisningsformål og udgør ikke lægelig rådgivning. Rådfør dig altid med en kvalificeret sundhedsprofessionel for beslutninger om diagnose og behandling.
Publiceret · Kontakt redaktionen
Udgivet af Kantesti Ltd, registreret i England og Wales, virksomhedsnummer. 17090423, London, Storbritannien.
