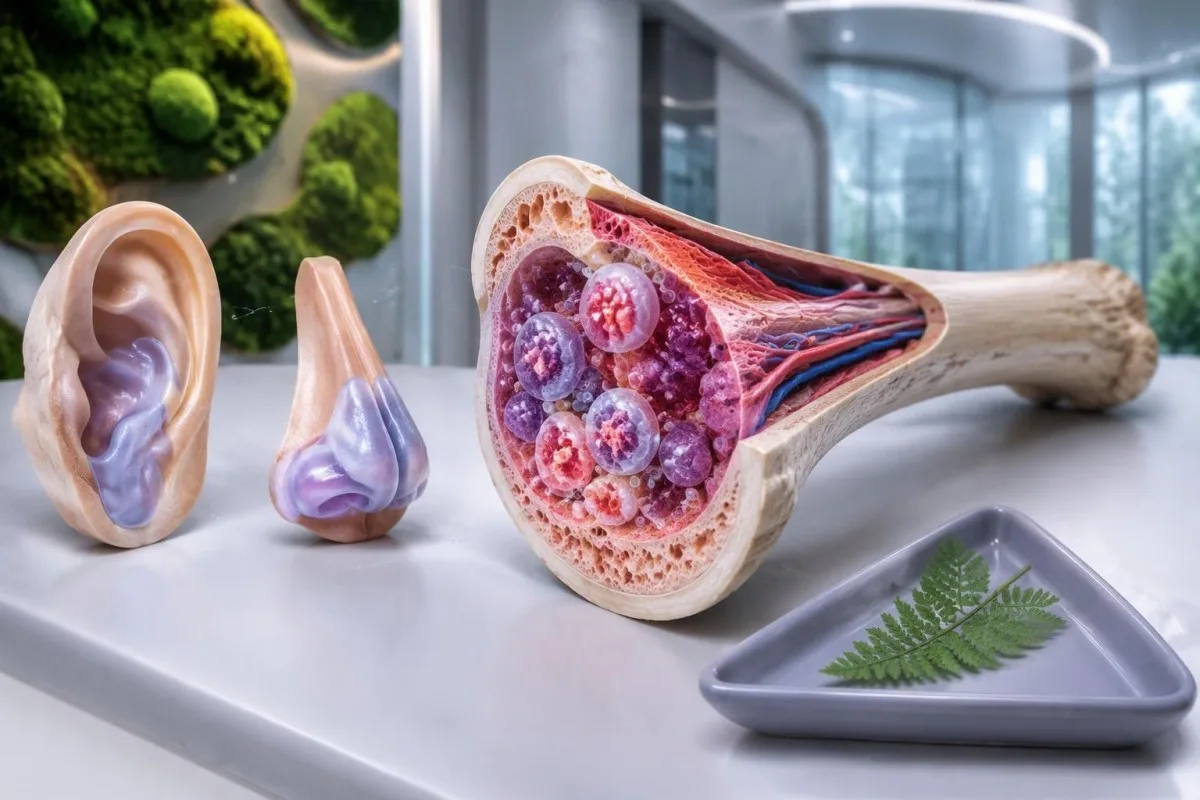
VEXAS ရောဂါလက္ခဏာစုသည် သွေးဆဲလ်များဖြစ်ပေါ်စေသော ဆဲလ်များတွင် ဖြစ်ပွားသည့် somatic UBA1 ဗီဇပြောင်းလဲမှုများကြောင့် ဖြစ်သော၊ နောက်ပိုင်းမှ ရရှိလာသည့် ရောင်ရမ်းမှုအခြေအနေတစ်ခုဖြစ်သည်။ ထပ်ခါတလဲလဲ ဖျားခြင်း၊ နား သို့မဟုတ် နှာခေါင်းရှိ အရိုးနုများ ဖောင်းရောင်ခြင်းနှင့် အကြောင်းရင်းမသိရသော macrocytic သွေးအားနည်းရောဂါတို့ရှိပါက အထူးကုဆရာဝန်နှင့် စစ်ဆေးသင့်သည်။ ရောဂါသတ်မှတ်ရန် သင့်လျော်သော မျိုးဗီဇစစ်ဆေးမှု လိုအပ်ပြီး ပုံမှန် autoimmune စစ်ဆေးမှုအစုဖြင့် မသတ်မှတ်နိုင်ပါ။.

အဓိက မှတ်သားစရာများ
- VEXAS ရောဂါလက္ခဏာစု သည် များသောအားဖြင့် အသက် 50 ကျော်မှ စတင်ကာ တစ်ကိုယ်လုံးဆိုင်ရာ ရောင်ရမ်းမှုနှင့် သွေးဆဲလ်များဖြစ်ပေါ်စေသော ဆဲလ်များတွင် မူမမှန်မှုများကို တွဲဖက်ဖြစ်စေသည်။.
- အရိုးနုဖောင်းရောင်ခြင်း သည် နား၊ နှာခေါင်း သို့မဟုတ် အသက်ရှူလမ်းကြောင်းကို ထိခိုက်နိုင်သည်။ နားအရိုးနုရောင်ရမ်းခြင်းတွင် နားရွက်အောက်ပိုင်း ပျော့ပျောင်းသောအပိုင်းကို မထိခိုက်ဘဲ ချန်ထားလေ့ရှိသည်။.
- Macrocytosis ဆိုသည်မှာ အရွယ်ရောက်သူများတွင် MCV 100 fL ခန့်ထက် မြင့်နေခြင်းဖြစ်သော်လည်း ဤတွေ့ရှိချက်တစ်ခုတည်းဖြင့် VEXAS ကို ရောဂါမသတ်မှတ်နိုင်ပါ။.
- သွေးပြားနည်းခြင်း 150 × 10^9/L အောက်ဖြစ်ပါက ထပ်ခါတလဲလဲ ရောင်ရမ်းမှုနှင့် အကြောင်းရင်းမသိရသော သွေးအားနည်းရောဂါတို့နှင့်အတူ တွေ့ရှိသည့်အခါ သံသယပိုမိုခိုင်မာစေနိုင်သည်။.
- CRP ပုံမှန်အားဖြင့် အထက်ရည်ညွှန်းကန့်သတ်ချက်မှာ 5 mg/L ဖြစ်ပြီး အချို့ဓာတ်ခွဲခန်းများတွင် 10 mg/L ကို အသုံးပြုသော်လည်း CRP သတ်မှတ်ချက်တစ်ခုမျှဖြင့် VEXAS ကို အတည်မပြုနိုင်ပါ။.
- UBA1 ဗီဇပြောင်းလဲမှု စစ်ဆေးခြင်း သည် နောက်ပိုင်းမှ ရရှိလာသော ရောဂါဖြစ်စေနိုင်သည့် မျိုးကွဲတစ်ခုကို ရှာဖွေခြင်းဖြစ်ပြီး ပုံမှန်အားဖြင့် မျိုးရိုးလိုက်နိုင်ခြေအတွက် စစ်ဆေးသည့် panel ကို အသုံးပြုခြင်းထက် အရံသွေး သို့မဟုတ် ရိုးတွင်းခြင်ဆီကို အသုံးပြုသည်။.
- ကိုယ်ခံအားစနစ်ဆိုင်ရာ စစ်ဆေးမှုများ ဥပမာ ANA၊ rheumatoid factor နှင့် ANCA တို့သည် VEXAS syndrome ရှိကြောင်း အတည်ပြုခြင်း သို့မဟုတ် မရှိကြောင်း ပယ်ချခြင်း မပြုနိုင်ပါ။.
- အရေးပေါ် လက္ခဏာများ သိသာထင်ရှားသော ကိုယ်ခံအားနှိမ်နင်းမှုခံယူနေစဉ် အသက်ရှူမဝခြင်းအသစ်ဖြစ်ပေါ်ခြင်း၊ ရင်ဘတ်နာခြင်း၊ အသက်ရှူလမ်းကြောင်းဆိုင်ရာ အခက်အခဲဖြစ်ခြင်း သို့မဟုတ် အဖျား 38°C နှင့်အထက်ရှိခြင်းတို့ ပါဝင်သည်။.
VEXAS ရောဂါလက္ခဏာစုဆိုသည်မှာ အဘယ်နည်း၊ သွေးဆဲလ်အရေအတွက်များက အဘယ်ကြောင့် အရေးကြီးသနည်း။
VEXAS ရောဂါလက္ခဏာစု သည် ခန္ဓာကိုယ်ဆဲလ်တစ်ခုတွင် ဖြစ်ပေါ်သော UBA1 ပြောင်းလဲမှု ကြောင့် ဖြစ်ပွားသည့် နောက်မှဖြစ်ပေါ်လာသော အလိုအလျောက်ရောင်ရမ်းရောဂါဖြစ်သည်။ ထပ်တလဲလဲရောင်ရမ်းခြင်း၊ အရိုးနုဖောင်းရောင်ခြင်းနှင့် အကြောင်းရင်းမသိသော ပုံမှန်မဟုတ်သည့် သွေးဆဲလ်အရေအတွက်များ—အထူးသဖြင့် အသက် 50 ကျော်သူတွင် ဖြစ်သော မက်ခရိုဆိုက်တစ် သွေးအားနည်းရောဂါ—တို့ ပေါင်းစပ်တွေ့ရှိပါက သံသယရှိသင့်သည်။ သို့သော် ရောဂါသတ်မှတ်ရန်မှာ ဆေးဘက်ဆိုင်ရာအခြေအနေနှင့် ကိုက်ညီသည့် ရောဂါဖြစ်စေနိုင်သော UBA1 မျိုးကွဲကို ဖော်ထုတ်နိုင်ခြင်းအပေါ် မူတည်သည်။.

အမည်တွင် အင်္ဂါရပ် 5 ခုကို ဖော်ပြထားသည်—vacuoles၊ E1 enzyme၊ X-linked၊ autoinflammatory နှင့် somatic တို့ဖြစ်သည်။ ၎င်းတို့သည် ဇီဝဗေဒဆိုင်ရာ သဲလွန်စများသာဖြစ်ပြီး လူတိုင်းတွင် မဖြစ်မနေ ပြည့်စုံရမည့် စစ်ဆေးစာရင်း မဟုတ်ပါ။ ပထမဆုံးဆေးခန်းလာပြချိန်တွင် ရိုးတွင်းခြင်ဆီ၌ မြင်ရသော vacuoles၊ အရိုးနုဆိုင်ရာ လက္ခဏာများနှင့် ပြင်းထန်သော သွေးအားနည်းရောဂါတို့သည် တစ်ပြိုင်နက်တည်း ပေါ်လာမည်ဟု မဆိုလိုပါ။.
Beck et al. သည် VEXAS ကို 2020 ခုနှစ်တွင် New England Journal of Medicine ၌ ပထမဆုံးဖော်ပြခဲ့ပြီး၊ အရွယ်ရောက်ပြီးနောက် စတင်ဖြစ်ပွားသော ရောင်ရမ်းမှုကို နောက်မှဖြစ်ပေါ်လာသည့် UBA1 မျိုးကွဲများနှင့် ဆက်စပ်ဖော်ထုတ်ခဲ့သည်။ ထိုတွေ့ရှိချက်ကြောင့် လူတစ်ဦးတွင် အရင်းခံအကြောင်းရင်းတစ်ခုတည်းကို မသိရှိမီ ပြန်ဖြစ်တတ်သော အရိုးနုရောင်ရောဂါနှင့် ရိုးတွင်းခြင်ဆီရောဂါကဲ့သို့ ရောဂါသတ်မှတ်ချက် 1 ခုထက်ပို၍ ယခင်က ရရှိထားနိုင်ပုံကို ရှင်းပြနိုင်သည်။.
CRP မြင့်တက်နေသည့် ရလဒ်တစ်ခုတည်းက VEXAS ကို အတိအကျညွှန်ပြခြင်းမရှိသလို၊ MCV 103 fL ဖြစ်ခြင်းတွင်လည်း ပိုမိုအဖြစ်များသည့် အခြားရှင်းလင်းချက်များ ရှိတတ်သည်။ ရောင်ရမ်းမှုအကြိမ်ကြိမ်ဖြစ်ပွားခြင်းနှင့်အတူ သွေးဆဲလ်အရေအတွက်နည်းခြင်း ဆက်လက်ရှိနေခြင်း သို့မဟုတ် ပိုဆိုးလာခြင်းတို့ တွဲဖက်ဖြစ်ပေါ်ပါက စိုးရိမ်မှုမြင့်တက်လာသည်။ အကြောင်းမှာ ထိုပုံစံသည် ဓာတ်ခွဲခန်းရလဒ် ယာယီပြောင်းလဲမှုတစ်ခုတည်းထက် ပုံမှန်မဟုတ်သော သွေးဆဲလ်ထုတ်လုပ်မှုနှင့် ဆက်စပ်သည့် ရောင်ရမ်းဖြစ်စဉ်ကို ပိုမိုညွှန်ပြသောကြောင့်ဖြစ်သည်။.
ကန်တက်စတီသည် AI သွေးစမ်းသပ်မှုခွဲခြမ်းစိတ်ဖြာ ဟေမိုဂလိုဘင်၊ MCV၊ သွေးဥမွှားများနှင့် CRP တို့ မည်သို့ဆက်စပ်နေသည်ကို ရှင်းပြနိုင်သော်လည်း VEXAS ရောဂါသတ်မှတ်ခြင်းကို အထူးကုများထံတွင်သာ ထားရှိသည်။ ကျွန်ုပ်တို့၏ အဖွဲ့အစည်းနှင့် ရည်ရွယ်ချက် ကို သီးခြားဖော်ပြထားသည်။ တင်ထားသော CBC 1 ခုတည်းဖြင့် UBA1 ပြောင်းလဲမှုကို မဖော်ထုတ်နိုင်သလို ဆေးဘက်ဆိုင်ရာ စစ်ဆေးမှုကိုလည်း အစားထိုးမပေးနိုင်ပါ။.
VEXAS ကို မည်သူများတွင် ဖြစ်ပွားသနည်း၊ UBA1 ဗီဇပြောင်းလဲမှုသည် မျိုးရိုးလိုက်ပါသလား။
VEXAS syndrome သည် အသက်ကြီးသော အမျိုးသားများတွင် အများဆုံးဖြစ်ပွားသည်, ၊ လက္ခဏာများသည် များသောအားဖြင့် အသက် 50 ကျော်မှ စတင်သည်။ ရောဂါဖြစ်စေသော UBA1 ပြောင်းလဲမှုသည် မိဘထံမှ အမွေဆက်ခံလာခြင်း သို့မဟုတ် မွေးကတည်းက ခန္ဓာကိုယ်ဆဲလ်အားလုံးတွင် ရှိနေခြင်းမဟုတ်ဘဲ သွေးဆဲလ်များဖြစ်ပေါ်စေသော ဆဲလ်အစုအဝေးတစ်ခုအတွင်း ယေဘုယျအားဖြင့် နောက်မှဖြစ်ပေါ်လာခြင်းဖြစ်သည်။.

UBA1 သည် X ခရိုမိုဆုမ်းပေါ်တွင် တည်ရှိပြီး၊ ရောဂါခံစားနေရသော အမျိုးသားအများစုတွင် X ခရိုမိုဆုမ်း 1 ခုရှိသည်။ အမျိုးသမီးများတွင်လည်း VEXAS ဖြစ်ပွားနိုင်ပြီး၊ တစ်ခါတစ်ရံ ရောဂါရှိသောဆဲလ်များအတွင်း X ခရိုမိုဆုမ်းတစ်ခု ဆုံးရှုံးခြင်းနှင့် ဆက်စပ်နိုင်သည်။ သို့သော် ဆေးဘက်ဆိုင်ရာပုံစံက ပြင်းပြင်းထန်ထန် သံသယဖြစ်စေပါက လိင်အမျိုးအစားတစ်ခုတည်းကြောင့် စစ်ဆေးမှုကို မရပ်တန့်သင့်ပါ။.
အမေရိကန် ကျန်းမာရေးစနစ်အုပ်စုမှ ပါဝင်သူ 163,096 ဦးကို လေ့လာသည့် JAMA သုတေသနတစ်ခုတွင် Beck et al. သည် ရောဂါနှင့်ဆက်စပ်သော UBA1 မျိုးကွဲများရှိသူ 11 ဦးကို ဖော်ထုတ်ခဲ့သည်။ အသက် 50 ကျော်အမျိုးသားများအကြား ခန့်မှန်းအကြိမ်ရေမှာ 4,269 ဦးတွင် 1 ဦးခန့်ဖြစ်သည်။ ဤအချက်သည် အဓိကအားဖြင့် ဥရောပမျိုးရိုးရှိသူများပါဝင်သော သီးခြားအုပ်စုတစ်ခုမှ ရရှိခြင်းဖြစ်ပြီး ကမ္ဘာတစ်ဝန်း ပျံ့နှံ့နှုန်းကို ခန့်မှန်းထားခြင်း မဟုတ်ပါ။.
သက်ဆိုင်ရာပြောင်းလဲမှုသည် လူတစ်ဦး၏ဘဝတစ်လျှောက်တွင် ပေါ်ပေါက်လာသောကြောင့် မိသားစုရာဇဝင် မရှိတတ်ပါ။ ဤအချက်သည် ကျွန်ုပ်တို့၏ MEFV စစ်ဆေးမှု ရှင်းလင်းချက်; တွင် ဖော်ပြထားသော အမွေဆက်ခံသည့် ထပ်တလဲလဲအဖျားရောဂါများနှင့် ကွာခြားသည်။ မိသားစုမှ မျိုးကွဲတစ်ခုကို ရှာဖွေရန် ဆွေမျိုး 2 ဦးအား စစ်ဆေးခြင်းသည် ပုံမှန်အားဖြင့် somatic VEXAS အတွက် စတင်စစ်ဆေးသည့် နည်းလမ်း မဟုတ်ပါ။.
မျိုးရိုးဗီဇဆိုင်ရာဟု ဆိုတိုင်း အလိုအလျောက် အမွေဆက်ခံသည်ဟု မဆိုလိုသကဲ့သို့၊ X-linked ဗီဇဟု ဆိုတိုင်းလည်း သားသမီးများထံ လက်ဆင့်ကမ်းမည်ဟု အလိုအလျောက် မဆိုလိုပါ။ အစီရင်ခံစာတွင် ကိုယ်ခန္ဓာဆဲလ်အားလုံး၌ရှိသော မျိုးကွဲတစ်ခုဟု ဖော်ပြထားခြင်း သို့မဟုတ် အသက် 50 မတိုင်မီ ပုံမှန်မဟုတ်သော လက္ခဏာပြခြင်းရှိပါက၊ ထပ်မံတစ်ရှူးစစ်ဆေးမှု သို့မဟုတ် မိသားစုအကြံပေးဆွေးနွေးမှု လိုအပ်ခြင်းရှိမရှိကို ဆေးဘက်ဆိုင်ရာ မျိုးရိုးဗီဇအထူးကုက ရှင်းလင်းပေးနိုင်သည်။.
VEXAS ရောဂါလက္ခဏာစု၏ မည်သည့်လက္ခဏာများရှိပါက သံသယရှိသင့်သနည်း။
VEXAS syndrome ၏ လက္ခဏာများ တွင် မကြာခဏ ထပ်တလဲလဲအဖျားတက်ခြင်း၊ အရေပြားရောင်ရမ်းမှုဆိုင်ရာ ပြောင်းလဲခြင်းများ၊ ပင်ပန်းနွမ်းနယ်ခြင်း၊ အဆုတ်ပါဝင်ထိခိုက်ခြင်းနှင့် အရိုးနုရောင်ရမ်းခြင်းတို့ ပါဝင်သည်။ အသက် 50 ကျော်အရွယ်ရောက်သူတစ်ဦးတွင် အကြောင်းရင်းမသိသော သွေးအားနည်းရောဂါ သို့မဟုတ် အခြားပုံမှန်မဟုတ်သော သွေးဆဲလ်အရေအတွက်များနှင့်အတူ နား သို့မဟုတ် နှာခေါင်းအရိုးနု ဖောင်းရောင်ခြင်းဖြစ်ပေါ်ပါက အထူးသဖြင့် ရောဂါခွဲခြားရာတွင် အသုံးဝင်သည်။.

နားအရိုးနုရောင်ခြင်းသည် မကြာခဏ နားအပေါ်ပိုင်းရှိ တင်းမာသောအပိုင်းကို ထိခိုက်ပြီး အရိုးနုမရှိသော ပျော့ပျောင်းသည့် နားရွက်အောက်ပိုင်းကို မထိခိုက်တတ်ပါ။ ထိုခန္ဓာဗေဒဆိုင်ရာ ကွာခြားချက်သည် ဖြစ်စဉ်တစ်ခုကို တိကျစွာဖော်ပြရာတွင် အထောက်အကူဖြစ်နိုင်သော်လည်း နားတစ်ဖက်နီရဲခြင်း 1 ခုဖြစ်ရုံဖြင့်ပင် နေရာကူးစက်မှု၊ ထိခိုက်ဒဏ်ရာ သို့မဟုတ် အရေပြားရောင်ရမ်းမှုကဲ့သို့ ပိုအဖြစ်များသော အကြောင်းရင်းများကို စစ်ဆေးရန် လိုအပ်သေးသည်။.
အရေပြားတွင် နာကျင်သော အဖုအပိမ့်များ၊ အကွက်များ သို့မဟုတ် ခရမ်းရောင်သန်းသော အပြောင်းအလဲများ ဖြစ်နိုင်သော်လည်း အသွင်အပြင်တစ်ခုတည်းဖြင့် အကြောင်းရင်းကို မဖော်ထုတ်နိုင်ပါ။ တစ်ရှူးစစ်ဆေးခြင်းသည် နျူထရိုဖီးလ်ဆဲလ်များကြောင့်ဖြစ်သော အရေပြားရောဂါ၊ သွေးကြောရောင်ရမ်းမှုနှင့် အခြားဖြစ်စဉ်များကို ခွဲခြားရာတွင် အထောက်အကူပြုနိုင်ပြီး၊ မကုသရသေးသော ဖြစ်စဉ် 2 ခုကို သီးခြားရိုက်ထားသည့် ဓာတ်ပုံများက ထပ်တလဲလဲဖြစ်ပေါ်သည့် ပုံစံကို အထူးကုက သိရှိရာတွင် အထောက်အကူဖြစ်နိုင်သည်။.
ရောင်ရမ်းမှုတိုက်ခိုက်မှုများသည် ပြန်ဖြစ်တတ်သော အရိုးနုရောင်ရောဂါ သို့မဟုတ် ပေါ်လီမိုင်ယဲလ်ဂျီးယား ရူမက်တစ်ကာကဲ့သို့ သတ်မှတ်ပြီးသား ရူမက်တစ်ရောဂါများနှင့် ဆင်တူနိုင်သည်။ ကျွန်ုပ်တို့၏ ရှင်းလင်းချက် PMR ဓာတ်ခွဲခန်းစစ်ဆေးမှု၏ ကန့်သတ်ချက်များ တွင် ရောင်ရမ်းမှုအမှတ်အသားများသည် ရောဂါတစ်မျိုးတည်းအတွက် သီးသန့်မဟုတ်ကြောင်း ရှင်းပြထားသည်။ 100 fL ထက်ကျော်သော မက်ခရိုဆိုက်တိုစစ် အခြေအနေ ဆက်လက်ရှိခြင်း သို့မဟုတ် သွေးဥမွှားများ ကျဆင်းခြင်းသည် ပထမဆုံးသတ်မှတ်လိုက်သော ရောဂါအမည်ကို အလိုအလျောက် လက်ခံခြင်းထက် ပိုမိုကျယ်ပြန့်စွာ စစ်ဆေးအကဲဖြတ်ရန် လိုအပ်ကြောင်း ညွှန်ပြသင့်သည်။.
အသံဝင်ခြင်းအသစ်၊ အသက်ရှူသံမြည်ခြင်း သို့မဟုတ် အသက်ရှူရခက်ခဲခြင်းရှိပါက အသက်ရှူလမ်းကြောင်းရှိ အရိုးနုများ ပါဝင်ထိခိုက်နိုင်သောကြောင့် အရေးပေါ်စစ်ဆေးအကဲဖြတ်ရန် လိုအပ်သည်။ အသုံးဝင်သော လက္ခဏာမှတ်တမ်းတွင် ဖြစ်စဉ်တစ်ခုစီအတွက် အသေးစိတ် 3 ချက် ပါဝင်သင့်သည်—ထိခိုက်သည့်နေရာ၊ ကြာချိန်နှင့် အဖျား သို့မဟုတ် ဆေးဝါးပြောင်းလဲမှုတစ်ခုခု တွဲဖက်ဖြစ်ပေါ်ခဲ့ခြင်း ရှိမရှိတို့ဖြစ်သည်။ အသက်ရှူမှု ထိခိုက်နေပါက နောက်တစ်ကြိမ် ရောဂါလက္ခဏာပြန်ပေါ်လာသည်အထိ မစောင့်ပါနှင့်။.
မည်သည့်သွေးစစ်ဆေးမှုပုံစံက VEXAS ရောဂါလက္ခဏာစုကို ညွှန်ပြနိုင်သနည်း။
Macrocytic anemia, ၊ တစ်ခါတစ်ရံ သွေးဥမွှားနည်းခြင်း သို့မဟုတ် အခြားသွေးဆဲလ်အမျိုးအစားများ နည်းပါးခြင်းတို့နှင့် တွဲဖက်ဖြစ်ပေါ်ခြင်းသည် VEXAS ၏ အရေးကြီးသော ဓာတ်ခွဲခန်းဆိုင်ရာ သဲလွန်စတစ်ခုဖြစ်သည်။ အရွယ်ရောက်သူများတွင် MCV သည် ပုံမှန်အားဖြင့် ခန့်မှန်းခြေအားဖြင့် 80–100 fL, ဖြစ်သော်လည်း 100 fL ထက်ကျော်သော MCV ရလဒ်တစ်ခုတည်းဖြင့်ဖြစ်စေ၊ CRP မြင့်တက်နေသော ရလဒ်ဖြင့်ဖြစ်စေ ဤအခြေအနေကို အတည်ပြု၍မရပါ။.

ဟီမိုဂလိုဘင်သည် သွေးအားနည်းခြင်းကို တိုင်းတာပြီး MCV သည် သွေးနီဥ၏ ပျမ်းမျှအရွယ်အစားကို တိုင်းတာသည်။ ရလဒ် 2 ခုက မတူညီသော မေးခွန်းများကို ဖြေဆိုပေးသည်။ ရောင်ရမ်းမှုလက္ခဏာများလည်း ရှိနေသည့်အခါ ဟီမိုဂလိုဘင် 10.2 g/dL နှင့် MCV 108 fL ဖြစ်ခြင်းသည် ဟီမိုဂလိုဘင်တည်ငြိမ်နေပြီး MCV 101 fL သာ သီးခြားရှိနေခြင်းနှင့် မတူညီသော စစ်ဆေးအကဲဖြတ်မှုကို လိုအပ်သည်။.
ဓာတ်ခွဲခန်းများစွာတွင် သွေးဥမွှားရည်ညွှန်းတန်ဖိုးအပိုင်းအခြားကို ခန့်မှန်းခြေအားဖြင့် 150–450 × 10^9/L သတ်မှတ်ထားသည်။ သွေးဥမွှားအရေအတွက်သည် အောက်ဆုံးကန့်သတ်ချက်ကို မကျော်လွန်မီကတည်းက ကျဆင်းလာခြင်းသည် အရေးပါနိုင်ပြီး၊ ကျွန်ုပ်တို့၏ နယ်နိမိတ်တန်ဖိုးနီးပါးရှိသော MCV ရှင်းလင်းချက် တွင် နယ်နိမိတ်တန်ဖိုးနီးပါးရှိသည့် ကိန်းဂဏန်းတစ်ခုတည်းကို ရောဂါသတ်မှတ်ချက်အဖြစ် သဘောထားခြင်းထက် ဆက်လက်ဖြစ်ပေါ်နေသော လမ်းကြောင်းများက မကြာခဏ ပိုမိုအသုံးဝင်ရသည့်အကြောင်းကို ဖော်ပြထားသည်။.
တက်ကြွသော VEXAS အခြေအနေတွင် CRP သည် မကြာခဏ သိသိသာသာ မြင့်တက်နေသော်လည်း ပိုးဝင်ခြင်းနှင့် အခြားရောင်ရမ်းမှုဆိုင်ရာ ရောဂါများစွာကြောင့်လည်း အလားတူရလဒ် ဖြစ်ပေါ်နိုင်သည်။ ဥပမာအဖြစ် CRP 80 mg/L သည် အပေါ်ဆုံးကန့်သတ်ချက် 5 mg/L ထက် 16 ဆဖြစ်သည်။ ထိုနှိုင်းယှဉ်ချက်က ရောင်ရမ်းမှု ပြင်းထန်မှုကို ဖော်ပြခြင်းသာဖြစ်ပြီး UBA1 ဗီဇပြောင်းလဲမှု ဖြစ်နိုင်ခြေကို မဖော်ပြပါ။.
RDW သည် သွေးနီဥအရွယ်အစား ကွဲပြားမှုကို ဖော်ပြပြီး ရောနှောနေသော CBC ပုံစံကို ရှင်းလင်းရာတွင် အထောက်အကူပြုနိုင်သော်လည်း VEXAS အတွက် သီးသန့်ဇီဝအမှတ်အသား မဟုတ်ပါ။ ကျွန်ုပ်တို့၏ RDW နှင့် MCV လမ်းညွှန် တွင် သံဓာတ်ချို့တဲ့ခြင်းနှင့် မက်ခရိုဆိုက်တိုစစ်ကဲ့သို့ ထပ်နေသော ဖြစ်စဉ် 2 ခုကြောင့် ပျမ်းမျှ MCV သည် ထင်ယောင်ထင်မှားဖြစ်စေပြီး သာမန်တန်ဖိုးကဲ့သို့ ဖြစ်နိုင်ပုံကို ရှင်းပြထားသည်။.
| အဆင့် | အပိုင်းအခြား | အဓိပ္ပာယ် |
|---|---|---|
| အရွယ်ရောက်သူများအတွက် ပုံမှန် MCV အပိုင်းအခြား | 80–100 fL | အစီရင်ခံစာထုတ်ပေးသော ဓာတ်ခွဲခန်း၏ အပိုင်းအခြားကို အသုံးပြုပါ။ ပုံမှန်အပိုင်းအခြားအတွင်းရှိ ရလဒ်ဖြစ်ခြင်းသည် အစောပိုင်းအဆင့် သို့မဟုတ် ဖုံးကွယ်နေသော မက်ခရိုဆိုက်တိုစစ်ကို မပယ်ဖျက်နိုင်ပါ။. |
| Macrocytosis | >100 fL | အာဟာရ၊ ဆေးဝါး၊ အသည်း၊ သိုင်းရွိုက်နှင့် ရိုးတွင်းခြင်ဆီဆိုင်ရာ အကြောင်းရင်းများကို စစ်ဆေးပါ။ ဤသည်မှာ VEXAS ကို ရောဂါရှာဖွေသတ်မှတ်ရန် သတ်မှတ်ထားသော အတိုင်းအတာ မဟုတ်ပါ။. |
| သွေးဥနည်းခြင်း (Thrombocytopenia) | <150 × 10^9/L | ဆက်လက်ဖြစ်ပေါ်နေသော ရောင်ရမ်းမှုနှင့် အကြောင်းရင်းမသိသော သွေးအားနည်းခြင်းတို့နှင့် တွဲဖက်ရှိနေပါက သွေးဥမွှားနည်းခြင်းသည် စိုးရိမ်မှုကို ပိုမိုထောက်ခံနိုင်သည်။. |
| ဓာတ်ခွဲခန်းကန့်သတ်ချက်ထက် မြင့်သော CRP | မကြာခဏ >5 mg/L ဖြစ်ပြီး အချို့ဓာတ်ခွဲခန်းများတွင် >10 mg/L ကို အသုံးပြုသည်။ | အကြောင်းရင်းကို မသတ်မှတ်ဘဲ ရောင်ရမ်းတုံ့ပြန်မှုရှိကြောင်း ဖော်ပြသည်။. |
ပုံမှန် autoimmune စစ်ဆေးမှုအစုများဖြင့် VEXAS ကို အဘယ်ကြောင့် အတည်မပြုနိုင်သနည်း။
ပုံမှန်အော်တိုအင်မြူးစစ်ဆေးမှုများဖြင့် VEXAS ရောဂါစုကို အတည်မပြုနိုင်ပါ အကြောင်းမှာ ၎င်းတို့သည် ရရှိလာသော UBA1 ဗီဇပြောင်းလဲမှုများကို မဟုတ်ဘဲ ပဋိပစ္စည်းများ သို့မဟုတ် ဆက်စပ်ကိုယ်ခံအားအမှတ်အသားများကို တိုင်းတာသောကြောင့်ဖြစ်သည်။ ANA၊ ရူမက်တစ်ဖက်တာ၊ ANCA နှင့် ကွန်ပလီမင့်ရလဒ်များသည် အခြားဖြစ်နိုင်သော သို့မဟုတ် ထပ်နေသော အခြေအနေများကို စစ်ဆေးအကဲဖြတ်ရာတွင် အထောက်အကူပြုနိုင်သော်လည်း မည်သည့်ရလဒ်ပေါင်းစပ်မှုမျှ သင့်လျော်သော မော်လီကျူးစစ်ဆေးမှုကို အစားထိုး၍မရပါ။.

ANA စစ်ဆေးမှုသည် နျူကလီးယားအစိတ်အပိုင်းများကို ဦးတည်သည့် ပဋိပစ္စည်းများကို ရှာဖွေစစ်ဆေးခြင်းဖြစ်ပြီး UBA1 ဗီဇကို ဖတ်ရှုခြင်း မဟုတ်ပါ။ 1:160 ရှိသော ANA အပေါင်းရလဒ်ကို ၎င်း၏ သီးခြားလက်တွေ့အခြေအနေအရ အဓိပ္ပာယ်ဖော်သင့်နိုင်သော်လည်း ANA အနုတ်ရလဒ်ကြောင့် အကြောင်းရင်းမသိသော အဖျား၊ အရိုးနုရောင်ရောဂါနှင့် မက်ခရိုဆိုက်တစ်သွေးအားနည်းခြင်းတို့ကို အရေးမကြီးသကဲ့သို့ ပယ်ချရန် မသင့်ပါ။.
ပဋိပစ္စည်းစစ်ဆေးမှုအစုများကို အကြိမ်ကြိမ်ပြုလုပ်ခြင်းသည် အဓိကမေးခွန်းကို မဖြေရှင်းနိုင်ဘဲ မမျှော်လင့်ထားသော အပေါင်းရလဒ်များကို ဖြစ်စေနိုင်သည်။ ကျွန်ုပ်တို့၏ ANA ရလဒ်ရှင်းလင်းချက် တွင် အပေါင်းရလဒ် ၁ ခုရှိခြင်းသည် ရောဂါအတည်ပြုချက်နှင့် မတူကြောင်း ရှင်းပြထားသည်။ VEXAS သံသယဖြင့် စစ်ဆေးနေစဉ် ပဋိပစ္စည်းတစ်မျိုး တွေ့ရှိသည့်အခါတွင်လည်း အလားတူ သတိထားရမည်။.
ဆရာဝန်များက ကိုယ်ခံအားကွန်ပလက်စ်ရောဂါတစ်မျိုးကို သံသယရှိသည့်အခါ ကွန်ပလီမင့်စစ်ဆေးမှုသည် အသုံးဝင်နိုင်သော်လည်း C3 နှင့် C4 ပုံမှန်ဖြစ်ခြင်းက VEXAS ကို ပယ်ချနိုင်မည်မဟုတ်ပါ။ ကျွန်ုပ်တို့၏ ကွန်ပလီမင့်နှင့် ပဋိပစ္စည်းလမ်းညွှန် တွင် ဤပရိုတင်း ၂ မျိုးအကြောင်း ရှင်းပြထားသည်။ ၎င်းတို့၏ ဇီဝဗေဒဆိုင်ရာ အခန်းကဏ္ဍသည် ရောဂါနှင့်ဆက်စပ်သော UBA1 မျိုးကွဲကြောင့် ဖြစ်ပေါ်သည့် အင်ဇိုင်းလုပ်ဆောင်မှု ရရှိလာသော ချို့ယွင်းချက်နှင့် ကွဲပြားသည်။.
အလိုအလျောက်ရောင်ရမ်းမှုနှင့် ကိုယ်ခံအားစနစ်က ကိုယ်ကိုတိုက်ခိုက်မှုတို့သည် ဆက်စပ်သော်လည်း အစားထိုးသုံး၍မရသော ဖော်ပြချက်များဖြစ်သည်။ VEXAS သည် အဓိကအားဖြင့် မျိုးဗီဇပြောင်းလဲထားသော သွေးဖွဲ့စည်းဆဲလ်များနှင့် ဆက်စပ်သည့် ပုံမှန်မဟုတ်သော မွေးရာပါကိုယ်ခံအားလုပ်ဆောင်မှုကြောင့် ဖြစ်ပွားသည်။ ဆရာဝန်များသည် အခြားဖြစ်နိုင်သောရောဂါများအတွက် ပဋိပစ္စည်းစစ်ဆေးမှုနှင့် VEXAS အတွက် မော်လီကျူးစစ်ဆေးမှုတို့ကို တစ်ပြိုင်နက်မှာယူနိုင်သည်။ အဘယ်ကြောင့်ဆိုသော် အခြားရောဂါတစ်မျိုးသည် ပျောက်ကွယ်သွားခြင်းမဟုတ်ဘဲ တစ်ပြိုင်နက်တည်း ရှိနေနိုင်သောကြောင့်ဖြစ်သည်။.
VEXAS ကြောင့်ဟု မသတ်မှတ်မီ အခြားမည်သည့်အကြောင်းရင်းများကို စစ်ဆေးရမည်နည်း။
ဗီတာမင် B12 သို့မဟုတ် ဖောလိတ်ချို့တဲ့ခြင်း၊ ဆေးဝါးသက်ရောက်မှုများ၊ အရက်သောက်သုံးမှု၊ အသည်းရောဂါ၊ သိုင်းရွိုက်လုပ်ဆောင်မှုနည်းခြင်းနှင့် ရိုးတွင်းခြင်ဆီရောဂါများသည် သွေးနီဥကြီးခြင်းကို ဖြစ်စေနိုင်သည်။ MCV 100 fL ထက်မြင့်ပါက ဤဖြစ်နိုင်ခြေများကို အကဲဖြတ်သင့်ပြီး၊ ထပ်တလဲလဲဖြစ်သော အရိုးနုရောင်ခြင်း သို့မဟုတ် အကြောင်းရင်းမသိသော ရောင်ရမ်းမှုဖြစ်စဉ်များရှိပါက VEXAS ကိုလည်း တစ်ချိန်တည်း စစ်ဆေးရန် သင့်လျော်နိုင်သည်။.

ဗီတာမင် B12 နှင့် ဖောလိတ်ရလဒ်များကို လက္ခဏာများ၊ ကုသမှုမှတ်တမ်းနှင့် CBC တို့နှင့်အတူ အဓိပ္ပာယ်ဖော်ရန် လိုအပ်သည်။ B12 ရလဒ်သည် ပုံမှန်အကန့်အသတ်နှင့် နီးနေပါက MCV 107 fL ကို VEXAS ကြောင့်ဟု ချက်ချင်းသတ်မှတ်မည့်အစား ထပ်မံစစ်ဆေးအကဲဖြတ်ရန် လိုအပ်နိုင်သည်။ ကျွန်ုပ်တို့၏ B12 နှင့် ဖောလိတ် နှိုင်းယှဉ်ရှင်းလင်းချက် တွင် ဖောလိတ်ကုသမှုက B12 ချို့တဲ့မှု၏ အထောက်အထားအချို့ကို အဘယ်ကြောင့် ဖုံးကွယ်နိုင်ကြောင်းလည်း ရှင်းပြထားသည်။.
ကြေးနီချို့တဲ့ခြင်းသည် သွေးဆဲလ်အရေအတွက်နည်းခြင်းနှင့် ရိုးတွင်းခြင်ဆီဆဲလ်ရှေ့ပြေးများတွင် ဗက်ကျူအိုးလ်များ ဖြစ်ပေါ်ခြင်းကို ဖြစ်စေနိုင်သဖြင့် အထူးသက်ဆိုင်သော အခြားအခြေအနေတစ်ခုဖြစ်သည်။ ထို့ကြောင့် ဇင့်ပမာဏမြင့်သော ဖြည့်စွက်စာများကို ပြန်လည်စစ်ဆေးခြင်းသည် အသုံးဝင်ပြီး ကျွန်ုပ်တို့၏ သွေးထဲတွင် ကြေးနီနည်းပါးခြင်းကို အကဲဖြတ်ရန် လမ်းညွှန် တွင် ယေဘုယျကိုယ်ခံအားအထောက်အပံ့အတွက်ဟု ဈေးကွက်တင်ထားသော ထုတ်ကုန်ဖြစ်သော်လည်း ဖြည့်စွက်စာပါဝင်ပစ္စည်း ၂ မျိုးဖြစ်သည့် ဇင့်နှင့် ကြေးနီတို့သည် အဘယ်ကြောင့် အရေးပါနိုင်ကြောင်း ရှင်းပြထားသည်။.
မိုင်လိုဒစ်ပလတ်စတစ်ရောဂါစုသည် သွေးနီဥအရွယ်အစားကြီးသည့် သွေးအားနည်းခြင်းကို ဖြစ်စေနိုင်ပြီး၊ VEXAS ၏ အခြားရှင်းလင်းချက်တစ်ခုအဖြစ် ပြိုင်ဘက်ဖြစ်ရုံသာမက VEXAS နှင့်အတူလည်း ရှိနေနိုင်သည်။ ကျွန်ုပ်တို့၏ MDS အတည်ပြုလမ်းညွှန် တွင် CBC မှရသော အရိပ်အယောင်များနှင့် ရိုးတွင်းခြင်ဆီအထောက်အထားများကို ခွဲခြားထားသည်။ ပုံမှန်မဟုတ်သော သွေးဆဲလ်အရေအတွက်တစ်ခုတည်းဖြင့် ရောဂါတစ်ခုခုကို အတည်ပြု၍မရသကဲ့သို့ ရောဂါနှစ်မျိုးလုံး ရှိမရှိကိုလည်း ဆုံးဖြတ်၍မရပါ။.
ဆေးဝါးနှင့် ကူးစက်ရောဂါမှတ်တမ်းများကို ပြန်လည်သုံးသပ်ခြင်းသည် မရှိမဖြစ်လိုအပ်သည်၊ အကြောင်းမှာ ကုသမှုက စစ်ဆေးနေသည့် ကိန်းဂဏန်းများကိုပင် ပြောင်းလဲစေနိုင်သောကြောင့်ဖြစ်သည်။ ဥပမာ၊ ဂလူကိုကော်တီကိုက်ဆေးများသည် နျူထရိုဖီးလ်များကို တိုးစေပြီး CRP ကို လျော့ကျစေနိုင်သကဲ့သို့ မကြာသေးမီက သွေးသွင်းထားခြင်းက MCV ကို ပြောင်းလဲစေနိုင်သည်။ တစ်ခုနှင့်တစ်ခု မကိုက်ညီသကဲ့သို့ ထင်ရသော ဓာတ်ခွဲခန်းအစီရင်ခံစာ ၂ ခုသာမက ဤဖြစ်ရပ်များ ဖြစ်ပွားခဲ့သည့် ရက်စွဲများကိုပါ ယူလာပါ။.
somatic UBA1 စစ်ဆေးမှုက VEXAS ရောဂါသတ်မှတ်မှုကို မည်သို့အထောက်အကူပြုသနည်း။
VEXAS ရောဂါကို ကိုက်ညီသော လက်တွေ့အခြေအနေတွင် ရောဂါနှင့်ဆက်စပ်သော ကိုယ်ခန္ဓာဆဲလ်အတွင်း ရရှိလာသည့် UBA1 မျိုးကွဲကို တွေ့ရှိခြင်းဖြင့် အတည်ပြုသည်။. စစ်ဆေးမှုအတွက် အများအားဖြင့် သွေးပြန်ကြောသွေးကို အသုံးပြုကြပြီး၊ ရလဒ်အတည်မပြုနိုင်ပါက ရိုးတွင်းခြင်ဆီနမူနာ သို့မဟုတ် ပိုမိုထိခိုက်လွယ်သော နည်းလမ်းကို အသုံးပြုရန် သင့်လျော်နိုင်သည်။ အသိအမှတ်ပြုထားသော မျိုးကွဲများစွာသည် အနေအထား 41 ရှိ မက်သီယိုနင်းကို ထိခိုက်စေသည်။.

စစ်ဆေးမှုတောင်းဆိုချက်တွင် ယေဘုယျ မျိုးရိုးလိုက်ရောဂါအစုစစ်ဆေးမှုအစား VEXAS သံသယရှိကြောင်းနှင့် ကိုယ်ခန္ဓာဆဲလ်အတွင်း ရရှိလာသော UBA1 မျိုးကွဲများကို စစ်ဆေးရန် တိတိကျကျ ဖော်ပြသင့်သည်။ ဤအရာများသည် ရောဂါရှာဖွေရေးလုပ်ငန်း ၂ မျိုး ကွဲပြားခြင်းဖြစ်သည်။ မျိုးရိုးလိုက်နိုင်ခြေစစ်ဆေးမှုတစ်ခုတွင် ရရှိလာသော ဆဲလ်အုပ်စုကို ရှာဖွေဖော်ထုတ်ရန် လိုအပ်သည့် သက်ဆိုင်ရာ ဗီဇဒေသများ၊ ဆဲလ်ရင်းမြစ် သို့မဟုတ် ရှာဖွေတွေ့ရှိနိုင်စွမ်းတို့ မပါဝင်နိုင်ပါ။.
Beck နှင့်အဖွဲ့သည် 2020 ခုနှစ် New England Journal of Medicine အစီရင်ခံစာတွင် UBA1 မျိုးကွဲများကို ယူဘီကွီတင်အသက်သွင်းအင်ဇိုင်း၏ လုပ်ဆောင်မှု ပြောင်းလဲခြင်းနှင့် ဆက်စပ်ကြောင်း ဖော်ပြခဲ့သည်။ အနေအထား 41 သည် အဓိက မျိုးကွဲဖြစ်ပွားရာနေရာဖြစ်သော်လည်း ထိုနေရာတစ်ခုတည်းကိုသာ စစ်ဆေးခြင်းသည် သက်ဆိုင်ရာ UBA1 ကို ပြည့်စုံစွာ ဆန်းစစ်ခြင်းနှင့် မတူပါ၊ အကြောင်းမှာ ရောဂါနှင့်ဆက်စပ်သော ပုံမှန်မဟုတ်သည့် မျိုးကွဲများကိုလည်း ဖော်ပြထားသောကြောင့်ဖြစ်သည်။.
အနုတ်ရလဒ်တစ်ခု၏ အဓိပ္ပာယ်ကို ရှင်းလင်းစွာသိရန် ဓာတ်ခွဲခန်းအသုံးပြုသည့် နည်းလမ်းကိုလည်း သိထားရန်လိုသည်။ 5% မျိုးကွဲအယ်လီလ်အချိုးကို ရှာဖွေတွေ့ရှိရန် အတည်ပြုထားသော စစ်ဆေးမှုနည်းလမ်းသည် ပိုမိုသေးငယ်သော ဆဲလ်အုပ်စုကို လွတ်သွားနိုင်သည်။ မည်သည့်ဒေသများကို စစ်ဆေးလွှမ်းခြုံထားကြောင်း၊ ဖော်ပြထားသော ရှာဖွေတွေ့ရှိနိုင်မှု အနိမ့်ဆုံးကန့်သတ်ချက်မှာ မည်မျှဖြစ်ကြောင်းနှင့် နမူနာသည် ကိုယ်ခန္ဓာဆဲလ်အတွင်း ရရှိလာသော မျိုးကွဲစစ်ဆေးမှုအတွက် သင့်လျော်မှုရှိမရှိကို မေးမြန်းပါ။.
ကန်တက်စတီသည် AI သွေးစစ်ဆေးမှု ရလဒ် ပလက်ဖောင်း that can help explain accompanying CBC and inflammatory-marker results, but it cannot infer a UBA1 sequence from 1 routine report. Our AI தொழில்நுட்ப விளக்கம் describes report interpretation; molecular diagnosis still requires an accredited laboratory and specialist interpretation.
UBA1 ဗီဇပြောင်းလဲမှုစစ်ဆေးချက်အစီရင်ခံစာကို မည်သို့ဖတ်ရှုရမည်နည်း။
A UBA1 report should state the variant, classification, sample type and testing limitations, often including variant allele fraction. A pathogenic or likely pathogenic disease-associated variant can support VEXAS, but a variant of uncertain significance is not diagnostic, and a 10% allele fraction is not a 10% severity score.

Variant allele fraction is the proportion of analyzed sequence reads carrying a particular change at that location. In a simple 1-X-chromosome model it may approximate the proportion of affected sampled cells, but cell mixtures, chromosome changes and laboratory methods complicate that estimate; it does not directly measure organ damage.
A hypothetical report showing a recognized disease-associated variant at 12% allele fraction may be meaningful even though most reads are unchanged. By contrast, a novel uncertain variant at 40% still requires expert assessment, because abundance cannot turn an unproven genetic finding into an established cause of symptoms.
Different clonal disorders require different molecular or cellular tests, even when anemia and thrombosis overlap. Our PNH clone testing guide explains a separate disorder assessed by flow cytometry; 1 negative PNH test does not evaluate UBA1, and a UBA1 result does not replace PNH testing when indicated.
Kantesti cannot determine whether an uncertain UBA1 finding is disease-causing simply by matching it to an elevated CRP of 70 mg/L. Ask the specialist whether additional sequencing, another specimen or formal variant review is needed, and keep the complete report rather than a screenshot containing only the word positive.
ရိုးတွင်းခြင်ဆီရှိ vacuole များဖြင့်သာ VEXAS ကို ရောဂါသတ်မှတ်နိုင်ပါသလား။
Bone marrow vacuoles are a clue, not proof of VEXAS syndrome. Vacuoles may appear in early myeloid and erythroid precursors, but they are neither completely specific nor universally present; an adult with an MCV above 100 fL still needs the broader clinical and molecular assessment.
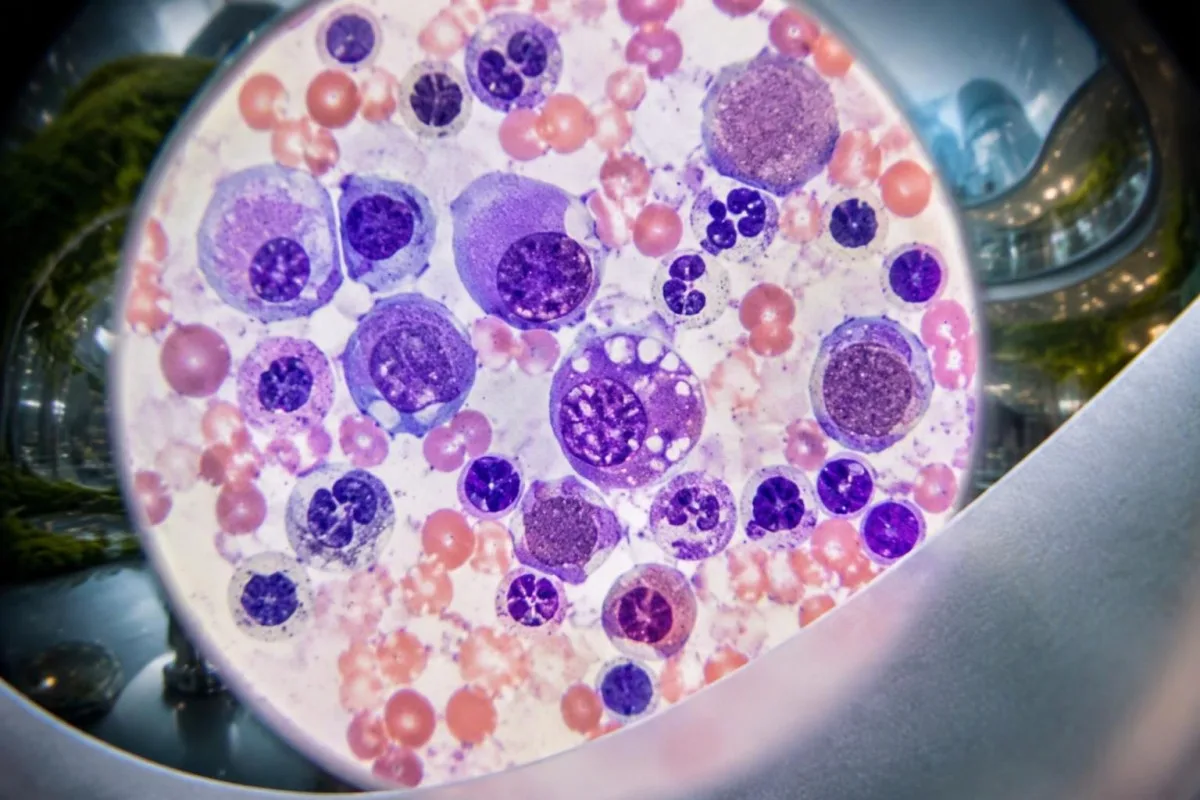
Vacuoles are small clear spaces visible within cells under microscopy, not holes that a patient can see on an ordinary CBC. Their absence on 1 marrow examination does not automatically exclude VEXAS, particularly when specimen quality, disease stage or the specific UBA1 variant affects the appearance.
Copper deficiency, alcohol-related effects and other conditions can produce vacuolated precursors. That overlap is why 2 complementary investigations may be needed: laboratory assessment for reversible mimics and somatic UBA1 testing, rather than treating a descriptive pathology finding as the final diagnosis.
Marrow examination also assesses cellularity, dysplasia and other abnormalities that may influence treatment decisions. Our explanation of teardrop cells and marrow clues describes a different microscopy finding; neither teardrop cells nor vacuoles can independently explain a platelet count of 95 × 10^9/L.
A marrow procedure is not automatically necessary for every isolated MCV of 102 fL, and a positive molecular result may already establish VEXAS in the right context. Hematology decides whether marrow assessment is needed to investigate persistent cytopenias, suspected MDS or another process that would change management.
အဆစ်ရောဂါအထူးကု သို့မဟုတ် သွေးရောဂါအထူးကုထံ မည်သည့်အချိန်တွင် စစ်ဆေးသင့်သနည်း။
Specialist assessment is appropriate when recurrent unexplained inflammation accompanies macrocytic anemia, falling platelets or other persistent cytopenias. Suspicion is higher after age 50, especially with chondritis, inflammatory skin findings or lung involvement; rheumatology and hematology often need to evaluate the pattern together.
There is no universal CRP level, age boundary or number of attacks that automatically mandates UBA1 testing. A person aged 68 with recurrent ear chondritis and unexplained anemia has a different pretest probability from a person aged 28 with 1 viral fever and an otherwise stable CBC.
Steroid-responsive inflammation that repeatedly returns during dose reduction deserves reassessment, particularly when blood counts remain abnormal. Improvement over 2 days may show that symptoms are inflammatory, but it does not distinguish VEXAS from several other disorders and should not become the only justification for ongoing treatment.
Unexplained pain needs a broader workup when it accompanies constitutional symptoms or changing counts. Our အကြောင်းမသိသော နာကျင်မှု စစ်ဆေးမှု လမ်းညွှန် explains why inflammatory markers are only part of that workup; an MCV above 100 fL adds a marrow-related question that a pain score cannot answer.
A referral should highlight 3 elements: documented inflammatory episodes, the CBC trend and the results of common-cause investigations. If symptoms are progressing rapidly, new organs are involved or transfusions are being considered, ask the referring clinician whether the appointment needs to be expedited rather than waiting for another routine repeat test.
လက်တွေ့ဥပမာတစ်ခု - နားထပ်ခါတလဲလဲ ဖောင်းရောင်ခြင်းနှင့် ပြောင်းလဲနေသော CBC
A hypothetical combination of recurrent chondritis, macrocytic anemia and low platelets warrants specialist evaluation, not an AI-generated diagnosis. Consider a 68-year-old man with hemoglobin 10.2 g/dL, MCV 108 fL, platelets 112 × 10^9/L and CRP 86 mg/L during a third episode of upper-ear swelling.

The first reasoning step is to separate symptom severity from diagnostic specificity: CRP of 86 mg/L confirms a substantial inflammatory response but does not identify its cause. The MCV of 108 fL and platelet count of 112 × 10^9/L add evidence that blood-cell production also needs investigation.
Suppose the person's B12, folate and thyroid assessments do not reveal an explanation, and medication, alcohol and liver reviews are unrevealing. A negative ANA would not close the case; the combination of 3 inflammatory episodes and persistent unexplained cytopenias would justify discussing somatic UBA1 testing with hematology and rheumatology.
Now suppose CRP falls to 12 mg/L after prescribed glucocorticoids, but hemoglobin falls to 9.8 g/dL. Those 2 trends are not contradictory: inflammatory activity may improve while marrow dysfunction or another anemia mechanism persists, so treatment response cannot be used as a substitute for investigating the falling hemoglobin.
Kantesti can help explain why those 2 trends deserve separate attention, but cannot establish VEXAS or choose immunosuppressive treatment. Our ဆေးဝါးခေတ်ရေစီးကြောင်း ခွဲခြမ်းစိတ်ဖြာမှု လမ်းညွှန် explains why dose changes, transfusions and intercurrent illness should be recorded beside each result; the example here is entirely hypothetical.
အတည်ပြုပြီးသော VEXAS ရောဂါလက္ခဏာစုကို အထူးကုများက မည်သို့ကုသသနည်း။
VEXAS treatment aims to control inflammation, manage cytopenias and reduce treatment-related harm. Glucocorticoids often suppress symptoms but may be difficult to taper; other options include selected immunomodulators, marrow-directed treatment and allogeneic stem-cell transplantation, with no single regimen appropriate for every adult over 50.
A falling CRP does not by itself establish treatment success if anemia, thrombosis or lung disease is worsening. Specialists follow at least 2 dimensions—clinical inflammatory activity and hematological status—and weigh these against cumulative glucocorticoid exposure, because prolonged treatment can cause infections, diabetes, osteoporosis and muscle weakness.
JAK inhibitors and IL-6-directed therapy are among approaches used by specialists, while azacitidine may be considered in selected patients, particularly with associated marrow disease. Evidence and access vary, and much published experience is observational; a response lasting 6 months in one cohort does not reliably predict an individual's longer-term benefit.
Allogeneic stem-cell transplantation can potentially eliminate the abnormal blood-forming clone and produce sustained remission in selected patients. It also carries substantial risks, including graft-versus-host disease and serious infection, so 2 people of the same age may receive different recommendations because fitness, organ involvement and donor availability differ.
Infection prevention deserves planning before immunosuppression, not only after fever develops. Depending on exposures and the proposed regimen, clinicians may consider screening or prevention measures described in our Strongyloides testing explanation; even 1 relevant past exposure can matter before corticosteroids, and prescribed steroids should never be stopped abruptly without guidance.
မည်သည့်ရောဂါလက္ခဏာများရှိပါက အရေးပေါ် သို့မဟုတ် ချက်ချင်းဆေးကုသမှုခံယူရန် လိုအပ်သနည်း။
New breathing difficulty, chest pain, airway symptoms, neurological deficits or significant bleeding require urgent assessment in someone with suspected or confirmed VEXAS. Fever of 38°C or higher during substantial immunosuppression also needs prompt clinical advice, particularly when neutrophils are low.
VEXAS is associated with venous thrombosis, so a painful swollen leg or sudden breathlessness should not be dismissed as another inflammatory flare. Normal routine clotting times do not exclude a clot; our သွေးခဲမှုစစ်ဆေးမှုအစု၏ ကန့်သတ်ချက်များ explain why 2 normal tests, PT and aPTT, cannot provide that reassurance.
An absolute neutrophil count below 0.5 × 10^9/L represents severe neutropenia and increases concern when fever occurs. Treatment can also blunt the temperature response, so feeling acutely unwell with shaking chills, confusion or rapidly worsening weakness can require urgent assessment even when a thermometer reads below 38°C.
Breathlessness can reflect lung inflammation, infection, pulmonary embolism or worsening anemia, and these require different treatments. Our breathlessness blood test guide explains why hemoglobin of 8 g/dL may contribute without proving the entire cause; new chest pain or sudden breathing difficulty should not wait for an uploaded report.
Persistent nose or gum bleeding, black stools or a severe new headache needs urgent advice, especially if platelets are very low. A count below 20 × 10^9/L generally warrants prompt clinical review, but the urgency depends on symptoms and context; significant bleeding is an emergency even above that number.
နောက်ဆက်တွဲစစ်ဆေးမှု၊ AI ၏ ကန့်သတ်ချက်များနှင့် သုတေသနစာတမ်းများ
Useful VEXAS follow-up combines symptoms, treatment history, CBC trends and inflammatory markers, with molecular and marrow findings interpreted by specialists. An AI explanation of 1 laboratory report can support preparation for care, but it cannot diagnose VEXAS, exclude infection or establish whether a UBA1 variant is pathogenic.
Bring original CBC reports, inflammatory markers and the complete UBA1 result, including specimen type and detection limit. Record 3 timeline features beside them: flare dates, medication changes and transfusions; this makes it easier to distinguish a true disease trend from a treatment effect or a change in testing conditions.
ကန်တက်စတီသည် AI-powered သွေးစစ်ဆေးမှု ခွဲခြမ်းစိတ်ဖြာ ကိရိယာ that can explain laboratory patterns without converting an MCV above 100 fL into a rare-disease diagnosis. Genetic reports can reveal sensitive information, so review our ကိုယ်ရေးလုံခြုံမှုနှင့် ဒေတာဆိုင်ရာ အချက်အလက်များ before sharing records, and include only documents you are authorized to upload.
Kantesti's 2 DOI-linked publications below concern broader blood-test interpretation and RDW education, not clinical trials of VEXAS diagnosis or UBA1 sequencing. They should therefore be read separately from the disease-specific medical studies listed in the external references; neither publication establishes VEXAS-specific diagnostic sensitivity or treatment effectiveness.
ကျွန်တော်တို့ရဲ့ နည်းလမ်းနှင့် ဆေးခန်း စံနှုန်းများကို အသိပေးသည်။ explain the distinction between report interpretation and medical diagnosis. Before the next appointment, write 2 questions: whether the laboratory method adequately assessed somatic UBA1 variants, and whether persistent cytopenias need marrow evaluation; these are more actionable than asking an AI to calculate an unsupported VEXAS probability.
ተደጋግሞ የሚጠየቁ ጥያቄዎች
VEXAS ရောဂါစု၏ ပထမဆုံးလက္ခဏာများမှာ အဘယ်နည်း။
VEXAS ရောဂါစုသည် အသက် ၅၀ ကျော်နောက်ပိုင်းတွင် အကြောင်းရင်းမသိဘဲ အဖျားထပ်ခါတလဲလဲတက်ခြင်း၊ အရေပြားရောင်ရမ်းပြောင်းလဲမှုများ၊ ပင်ပန်းနွမ်းနယ်ခြင်း သို့မဟုတ် နားရွက်/နှာခေါင်းရှိ အရိုးနုများ ဖောင်းရောင်ခြင်းတို့ဖြင့် စတင်လေ့ရှိသည်။ ဤလက္ခဏာများ မပေါ်မီ၊ ၎င်းတို့နှင့်အတူ သို့မဟုတ် ၎င်းတို့ပေါ်ပြီးနောက်တွင် မက်ခရိုဆိုက်တစ် သွေးအားနည်းရောဂါ သို့မဟုတ် အခြားပုံမှန်မဟုတ်သော သွေးဆဲလ်အရေအတွက်များ ပေါ်လာနိုင်သည်။ အရွယ်ရောက်သူတွင် MCV 100 fL ခန့်ထက် မြင့်နေခြင်းသည် သဲလွန်စတစ်ခုသာဖြစ်ပြီး ရောဂါအတည်ပြုချက် မဟုတ်ပါ။ ရောင်ရမ်းလက္ခဏာများ ထပ်ခါတလဲလဲဖြစ်ခြင်းနှင့် အကြောင်းရင်းမသိဘဲ ဆက်လက်တည်ရှိနေသော သွေးဆဲလ်လျော့နည်းမှုများ ပေါင်းစပ်ဖြစ်ပေါ်ပါက အဆစ်အမြစ်ရောဂါအထူးကုနှင့် သွေးရောဂါအထူးကုတို့၏ စစ်ဆေးအကဲဖြတ်မှုခံယူရန် ဆွေးနွေးသင့်သည်။.
မည်သည့်စစ်ဆေးမှုက VEXAS syndrome ကို အတည်ပြုနိုင်သနည်း။
သင့်လျော်သော လက်တွေ့အခြေအနေတွင် ရောဂါနှင့်ဆက်စပ်သော somatic UBA1 မျိုးကွဲကို ဖော်ထုတ်ခြင်းဖြင့် VEXAS ရောဂါစုကို ရောဂါသတ်မှတ်သည်။ စမ်းသပ်မှုတွင် အများအားဖြင့် အရံသွေးကို အသုံးပြုသော်လည်း ရွေးချယ်ထားသောအခြေအနေများတွင် ရိုးတွင်းခြင်ဆီ သို့မဟုတ် ပိုမိုအာရုံခံနိုင်စွမ်းမြင့်သော စမ်းသပ်နည်း လိုအပ်နိုင်သည်။ အသိအမှတ်ပြုထားသော မျိုးကွဲများစွာသည် အနေအထား ၄၁ ရှိ methionine ကို သက်ရောက်သော်လည်း hotspot ကိုသာ ကန့်သတ်စစ်ဆေးခြင်းသည် အခြားရောဂါနှင့်ဆက်စပ်သော မျိုးကွဲများကို လွတ်သွားစေနိုင်သည်။ အစီရင်ခံစာကို ၎င်း၏ မျိုးကွဲအမျိုးအစားခွဲခြားမှု၊ ဗီဇလွှမ်းခြုံမှုနှင့် ရှာဖွေတွေ့ရှိနိုင်မှု ကန့်သတ်ချက်တို့နှင့်အတူ အဓိပ္ပာယ်ဖွင့်ဆိုရမည်။.
ပုံမှန် ANA သို့မဟုတ် ကိုယ်ခံအားစနစ် အလိုအလျောက်တိုက်ခိုက်မှုဆိုင်ရာ စစ်ဆေးမှုအစုတစ်ခုက VEXAS ကို ပယ်ချနိုင်ပါသလား။
ပုံမှန် ANA သို့မဟုတ် ပုံမှန်ပြုလုပ်နေကျ autoimmune panel ဖြင့် VEXAS syndrome ကို ပယ်ချ၍မရပါ၊ အကြောင်းမှာ ဤစစ်ဆေးမှုများသည် somatic UBA1 mutations များကို မတွေ့ရှိနိုင်သောကြောင့် ဖြစ်သည်။ 1:160 တွင် ANA positive ဖြစ်ခြင်းသည်လည်း VEXAS ကို အတည်ပြုခြင်းမဟုတ်သလို အခြား autoimmune disease တစ်မျိုးရှိကြောင်း သေချာစွာ သတ်မှတ်ပေးခြင်းလည်း မဟုတ်ပါ။ Antibody စစ်ဆေးမှုများသည် အခြားဖြစ်နိုင်ခြေများကို စုံစမ်းရာတွင် အထောက်အကူပြုနိုင်ပြီး CBC ပုံစံများ၊ ရောဂါလက္ခဏာများနှင့် molecular testing တို့က သီးခြားမေးခွန်းများကို ဖြေဆိုပေးသည်။ Antibody စစ်ဆေးမှုများ negative ဖြစ်ခြင်းတစ်ခုတည်းကြောင့် ဆက်လက်ဖြစ်ပွားနေသော macrocytic anemia နှင့် cartilage ရောင်ရမ်းမှု ထပ်တလဲလဲဖြစ်ခြင်းကို လျစ်လျူမရှုသင့်ပါ။.
VEXAS ရောဂါစုသည် မျိုးရိုးလိုက်သလား၊ ကျွန်ုပ်၏ကလေးများကို စစ်ဆေးသင့်ပါသလား။
ပုံမှန် VEXAS syndrome သည် မျိုးရိုးလိုက်ခြင်းထက် နောက်ပိုင်းတွင် ရရှိလာခြင်းဖြစ်သဖြင့် ကလေးများကို ပုံမှန်စစ်ဆေးရန် ယေဘုယျအားဖြင့် မလိုအပ်ပါ။ သက်ဆိုင်ရာ UBA1 ဗီဇပြောင်းလဲမှုသည် အရွယ်ရောက်ပြီးနောက် သွေးဆဲလ်များဖြစ်ပေါ်စေသော ဆဲလ်များအတွင်း ပုံမှန်အားဖြင့် ပေါ်ပေါက်လာပြီး အသက် ၅၀ ကျော်မှ ရောဂါလက္ခဏာများ ဖြစ်ပေါ်လေ့ရှိသည်။ UBA1 သည် X ခရိုမိုဆုန်းပေါ်တွင် ရှိသော်လည်း ထိုအချက်ကြောင့် ကိုယ်ခန္ဓာဆဲလ်များတွင် ဖြစ်ပေါ်သော VEXAS မျိုးကွဲသည် အလိုအလျောက် မျိုးရိုးလိုက်ကူးစက်နိုင်သည်ဟု မဆိုလိုပါ။ ထူးခြားသော သို့မဟုတ် မွေးရာပါဖြစ်နိုင်သည့် တွေ့ရှိချက်များကို ဆေးဘက်ဆိုင်ရာ မျိုးရိုးဗီဇအထူးကုနှင့် ပြန်လည်သုံးသပ်သင့်သည်။.
အမျိုးသမီးများတွင် VEXAS ရောဂါစု ဖြစ်ပွားနိုင်ပါသလား။
အမျိုးသမီးများတွင် VEXAS ရောဂါစု ဖြစ်ပွားနိုင်သော်လည်း၊ အသိအမှတ်ပြုထားသော ဖြစ်ရပ်အများစုမှာ အသက်ကြီးသော အမျိုးသားများတွင် ဖြစ်ပွားသည်။ UBA1 သည် X ခရိုမိုဆုန်းပေါ်တွင် တည်ရှိပြီး၊ ထိခိုက်နေသော ဆဲလ်များ၌ X ခရိုမိုဆုန်း ၁ ခု ဆုံးရှုံးခြင်းသည် အမျိုးသမီးများတွင် တွေ့ရှိထားသော ယန္တရားတစ်ခုဖြစ်သည်။ ၂၀၂၃ ခုနှစ် JAMA ကျန်းမာရေးစနစ်လေ့လာမှုတစ်ခုတွင် ရောဂါနှင့်ဆက်စပ်သော UBA1 မျိုးဗီဇပြောင်းလဲမှုများရှိသည့် ပါဝင်သူ ၁၁ ဦးအနက် အမျိုးသမီး ၂ ဦးကို တွေ့ရှိခဲ့သည်။ ထပ်တလဲလဲ ရောင်ရမ်းမှုနှင့် အကြောင်းရင်းမရှင်းလင်းသော သွေးဆဲလ်အရေအတွက် မူမမှန်မှုများက ပြင်းထန်စွာ သံသယဖြစ်စေပါက လိင်အမျိုးအစားတစ်ခုတည်းကြောင့် အထူးကုဆရာဝန်၏ စစ်ဆေးအကဲဖြတ်မှုကို မတားဆီးသင့်ပါ။.
UBA1 စစ်ဆေးမှုရလဒ် အနုတ်ဖြစ်ပါက VEXAS ရောဂါစုကို ဖယ်ထုတ်နိုင်ပါသလား။
0 အနုတ်လက္ခဏာ UBA1 စစ်ဆေးမှုရလဒ်သည် အသုံးပြုသည့်နမူနာနှင့် စစ်ဆေးမှုနည်းလမ်း သင့်လျော်မှသာ VEXAS ဖြစ်နိုင်ခြေကို လျော့နည်းစေသည်။ မျိုးကွဲအယ်လီလ်အချိုး 5% ကို ရှာဖွေတွေ့ရှိနိုင်သည့် ကန့်သတ်ချက်ရှိသော စစ်ဆေးမှုသည် ပိုမိုသေးငယ်သည့် ကလိုနာကို လွတ်သွားနိုင်ပြီး၊ ဟော့စပေါ့နေရာများကိုသာ စစ်ဆေးခြင်းသည် စစ်ဆေးမှုအပိုင်းအခြားပြင်ပရှိ မျိုးကွဲများကို လွတ်သွားနိုင်သည်။ ဆေးဘက်ဆိုင်ရာ သံသယပြင်းထန်ပါက စစ်ဆေးမှုအပိုင်းအခြား၊ အာရုံခံနိုင်စွမ်းနှင့် နမူနာအမျိုးအစားတို့ကို အထူးကုထံ ပြန်လည်သုံးသပ်စေနိုင်သည်။ သင့်လျော်စွာ ပြုလုပ်ထားသည့် အနုတ်လက္ခဏာရလဒ်သည်လည်း ရှင်းလင်းသော အကြောင်းပြချက်မရှိဘဲ ထပ်မံစစ်ဆေးနေခြင်းထက် အခြားဖြစ်နိုင်သော ရောဂါရှာဖွေချက်များကို ဂရုတစိုက် ပြန်လည်သုံးသပ်ရန် လှုံ့ဆော်သင့်သည်။.
VEXAS ရောဂါစုကို ပျောက်ကင်းအောင် ကုသနိုင်ပါသလား?
0 Allogeneic stem-cell transplantation သည် ပုံမှန်မဟုတ်သော သွေးဆဲလ်ဖွဲ့စည်းသည့် ဆဲလ်မျိုးရိုးကို အစားထိုးခြင်းဖြင့် ရေရှည်သက်သာမှု ရရှိစေနိုင်သော်လည်း ရွေးချယ်ထားသော လူနာများအတွက်သာ သင့်လျော်ပြီး သိသာထင်ရှားသော အန္တရာယ်များ ရှိသည်။ အခြားကုသမှုများသည် ဆဲလ်မျိုးရိုးကို ယုံကြည်စိတ်ချစွာ ဖယ်ရှားရန်ထက် ရောင်ရမ်းမှုကို ထိန်းချုပ်ရန်၊ သွေးဆဲလ်အရေအတွက်နည်းခြင်းကို စီမံရန်နှင့် glucocorticoid သုံးစွဲမှုကို လျှော့ချရန် ရည်ရွယ်သည်။ အသက် ၅၀ ကျော် အရွယ်ရောက်သူများတွင် ကိုယ်ခန္ဓာကြံ့ခိုင်မှု၊ ကိုယ်တွင်းအင်္ဂါများ ပါဝင်ထိခိုက်မှုနှင့် ဆက်စပ်သည့် ရိုးတွင်းခြင်ဆီရောဂါတို့သည် ကုသမှုရွေးချယ်မှုများအပေါ် အလွန်သက်ရောက်နိုင်သည်။ ဖြည့်စွက်စာ၊ အစားအသောက်အစီအစဉ် သို့မဟုတ် AI ဖြင့် သွေးစစ်ဆေးမှုရလဒ် အဓိပ္ပာယ်ကောက်ယူခြင်းတို့သည် VEXAS ကို ပျောက်ကင်းစေနိုင်ကြောင်း သက်သေပြထားခြင်း မရှိပါ။.
သင့်သွေးစစ်ဆေးမှု ရလဒ်ကို ရှင်းလင်းချက်ရယူပါ
သင့်ဓာတ်ခွဲခန်းအစီရင်ခံစာကို တင်ပါ၊ Kantesti ၏ AI က ဇီဝအမှတ်အသားတစ်ခုစီကို နားလည်လွယ်သော ဘာသာစကားဖြင့် စက္ကန့်ပိုင်းအတွင်း ရှင်းပြပေးမည်။ ကမ္ဘာတစ်ဝန်းရှိ လူ ၂ သန်းကျော် အသုံးပြုထားသည်။.
ကိုးကားချက်များ
- Klein, T., Mitchell, S., & Weber, H. (2026)။. AI Blood Test Analyzer: 2.5M Tests Analyzed | Global Health Report 2026။. Kantesti AI ဆေးဘက်ဆိုင်ရာသုတေသန။. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026)။. RDW သွေးစစ်ဆေးမှု - RDW-CV၊ MCV နှင့် MCHC အတွက် ပြည့်စုံသောလမ်းညွှန်။. Kantesti AI ဆေးဘက်ဆိုင်ရာသုတေသန။. DOI
- Beck DB et al. (2020). Somatic Mutations in UBA1 and Severe Adult-Onset Autoinflammatory Disease. New England Journal of Medicine။. DOI
- Beck DB et al. (2023). Estimated Prevalence and Clinical Manifestations of VEXAS Syndrome in a Large US Health Care System. JAMA. DOI
- 2M+ခွဲခြမ်းစိတ်ဖြာထားသော စစ်ဆေးမှုများ
- 127+နိုင်ငံတွေ
- 100+ဘာသာစကားများ
ဆေးဘက်ဆိုင်ရာအဖွဲ့အကြောင်း


E-E-A-T ယုံကြည်မှု အချက်ပြများ
အတွေ့အကြုံ
ဆရာဝန်ဦးဆောင်သည့် ဓာတ်ခွဲခန်း အဓိပ္ပာယ်ဖတ်ခြင်း လုပ်ငန်းစဉ်များကို ပြန်လည်သုံးသပ်ခြင်း။.
ကျွမ်းကျင်မှု
biomarker များသည် ဆေးဘက်ဆိုင်ရာ အခြေအနေတွင် မည်သို့ ပြုမူနေသည်ကို အာရုံစိုက်သည့် ဓာတ်ခွဲခန်း ဆေးပညာ။.
အခွင့်အာဏာရှိခြင်း
ဒေါက်တာ Sarah Mitchell နှင့် ပါမောက္ခ ဒေါက်တာ Hans Weber တို့၏ ပံ့ပိုးကူညီမှုဖြင့် ဒေါက်တာ Thomas Klein က ဆေးဘက်ဆိုင်ရာသုံးသပ်မှုပြုလုပ်ထားသည်။.
ယုံကြည်စိတ်ချရမှု
စိတ်ပူစရာများကို လျော့ချရန်အတွက် ရှင်းလင်းသော နောက်ဆက်တွဲ လမ်းကြောင်းများပါဝင်သည့် သက်သေအထောက်အထားအခြေပြု အဓိပ္ပာယ်ဖတ်ချက်။.






ဆေးဘက်ဆိုင်ရာ ငြင်းဆိုချက်
ဤဆောင်းပါးသည် ပညာရေးဆိုင်ရာ ရည်ရွယ်ချက်အတွက်သာ ဖြစ်ပြီး ဆေးဘက်ဆိုင်ရာ အကြံဉာဏ် မဟုတ်ပါ။ ရောဂါရှာဖွေခြင်းနှင့် ကုသမှု ဆုံးဖြတ်ချက်များအတွက် အရည်အချင်းပြည့်မီသော ကျန်းမာရေးစောင့်ရှောက်မှုပေးသူနှင့် အမြဲတမ်း တိုင်ပင်ပါ။.
ထုတ်ဝေသည်။ · အယ်ဒီတာအဖွဲ့ကို ဆက်သွယ်ပါ
Kantesti Ltd မှ ထုတ်ဝေသည်၊ အင်္ဂလန်နှင့် ဝေလနယ်တွင် မှတ်ပုံတင်ထားပြီး ကုမ္ပဏီအမှတ်. 17090423, ၊ လန်ဒန်၊ ယူနိုက်တက်ကင်းဒမ်း။.
