Gihulagway sa mga score sa PD-L1 ang pagkolor sa usa ka sample sa tisyu—dili ang personal nimong kahigayonan nga magmalampuson ang pagtambal. Ang pamaagi sa pag-score, diagnosis sa kanser, ug gisugyot nga kombinasyon sa mga tambal maoy magtino kon unsay masuportahan sa resulta.

Pangunang mga punto
- mga resulta sa pagsulay sa PD-L1 nagsukod sa pagkolor sa protina sa tisyu sa kanser; dili kini rutina nga resulta sa blood test o pagsulay sa pag-screen sa kanser.
- TPS mao ang porsiyento sa buhi nga mga selula sa tumor nga adunay kuwalipikadong pagkolor sa lamad, nga ireport gikan sa 0% hangtod sa 100%.
- CPS nag-ihap sa kuwalipikadong mga selula sa tumor, lymphocyte, ug macrophage nga positibo sa PD-L1, gibahin sa buhi nga mga selula sa tumor, ug gipadaghan sa 100; ang gi-report nga score kutob ra sa 100.
- Lainlaing mga score dili mahimong i-convert: ang TPS 10% mahimong kauban sa CPS 10, CPS 25, o laing kantidad depende sa pagkolor sa mga selula sa imyunidad.
- Mga threshold sama sa TPS 1%, TPS 50%, CPS 1, ug CPS 10 magamit sa piho nga mga kahimtang sa kanser ug pagtambal—dili sa tanang immunotherapy.
- Mga positibong resulta mahimong mosuporta sa pagpili og pagtambal apan dili garantiya sa kaayohan; ang iskor nga 50 dili 50% nga posibilidad sa pagtubag.
- Negatibo nga mga resulta dili kanunay mopugong sa paggamit sa immunotherapy kay ang pipila ka kombinasyon ug mga pagtambal nga gitakda sa biomarker wala magkinahanglan og PD-L1 positivity.
- Pagkakasigo sa sample importante: daghang kasagarang gigamit nga mga protocol sa pag-iskor nagkinahanglan og labing menos 100 ka buhi nga selula sa tumor, apan kinahanglang sundon sa laboratoryo ang mga lagda nga piho sa indikasyon niini.
Unsa gyod ang gipahibalo sa mga resulta sa pagsulay sa PD-L1?
mga resulta sa pagsulay sa PD-L1 naghulagway sa pagkolor sa protina sa tisyu sa kanser. TPS nag-ihap sa porsiyento sa mga selula sa tumor nga nakolor; CPS naglakip usab sa piniling mga selula sa imyunidad nga nakolor. Walay usa niining mga iskor nga magbuot sa pagtambal nga nag-inusara: ang tipo ug yugto sa kanser, assay, ug regimen maoy motino sa angay nga cutoff, ug ang positibo o negatibong resulta dili garantiya sa kaayohan o sa dili paggamit sa pagtambal.
PD-L1, o programmed death-ligand 1, mahimong mopilit sa PD-1 receptor sa mga selula sa imyunidad ug momenos sa ilang kalihokan. Ang mga tambal nga motarget niining interaksiyon makapabalik sa kalihokan sa imyunidad batok sa kanser, apan dili makuha sa pagsukod sa 1 ka protina ang tanang hinungdan nga motino kon mailhan ug makontrol ba sa mga selula sa imyunidad ang kanser.
Kasagarang makuha ang resulta sa PD-L1 sa tisyu pinaagi sa immunohistochemistry, nga mogamit og antibody aron ipakita ang nahimutangan sa protina sa napreserbang sample. Gihulagway sa gitaho nga numero ang mga selula sa piniling mga hiwa sa tisyu—dili ang tanang selula sa kanser sa tibuok lawas—ug mahimong magkalahi ang mga resulta sa 2 ka sample gikan sa lainlaing lugar.
Si Kantesti usa ka AI blood test analyzer, dili kapuli sa patolohiya sa tisyu o desisyon sa pagtambal sa oncology. Ang among organisasyon ug clinical scope naglain sa suporta sa pagkat-on bahin sa mga resulta sa laboratoryo gikan sa mga desisyon nga nagkinahanglan nga dungan nga tan-awon ang orihinal nga report sa patolohiya, mga hulagway sa medikal nga pagsusi, ug ang giplanong regimen sa pagtambal.
Sugdi sa 4 ka detalye sa dili pa hubaron ang numero: ang diagnosis sa kanser, kon CPS ba o TPS ang iskor, ang gigamit nga assay, ug ang gihunahuna nga pagtambal. Nagbilin og hinungdanong klinikal nga kakulang ang report nga PD-L1 positive lamang; pangayoa ang pamaagi sa pag-iskor ug ang numerikal nga resulta.
Kahulogan sa score sa PD-L1 TPS: ang porsiyento sa mga selula sa tumor
Iskor sa proporsiyon sa tumor, o TPS, mao ang porsiyento sa mga buhi nga selula sa tumor nga nagpakita sa kwalipikadong bahinon o hingpit nga pagkolor sa lamad sa PD-L1. Ang TPS gikan sa 0% hangtod 100%; wala maapil ang mga selula sa imyunidad sa numerator niini, bisan pa kon kusog ang pagkolor niini tupad sa mga selula sa kanser.
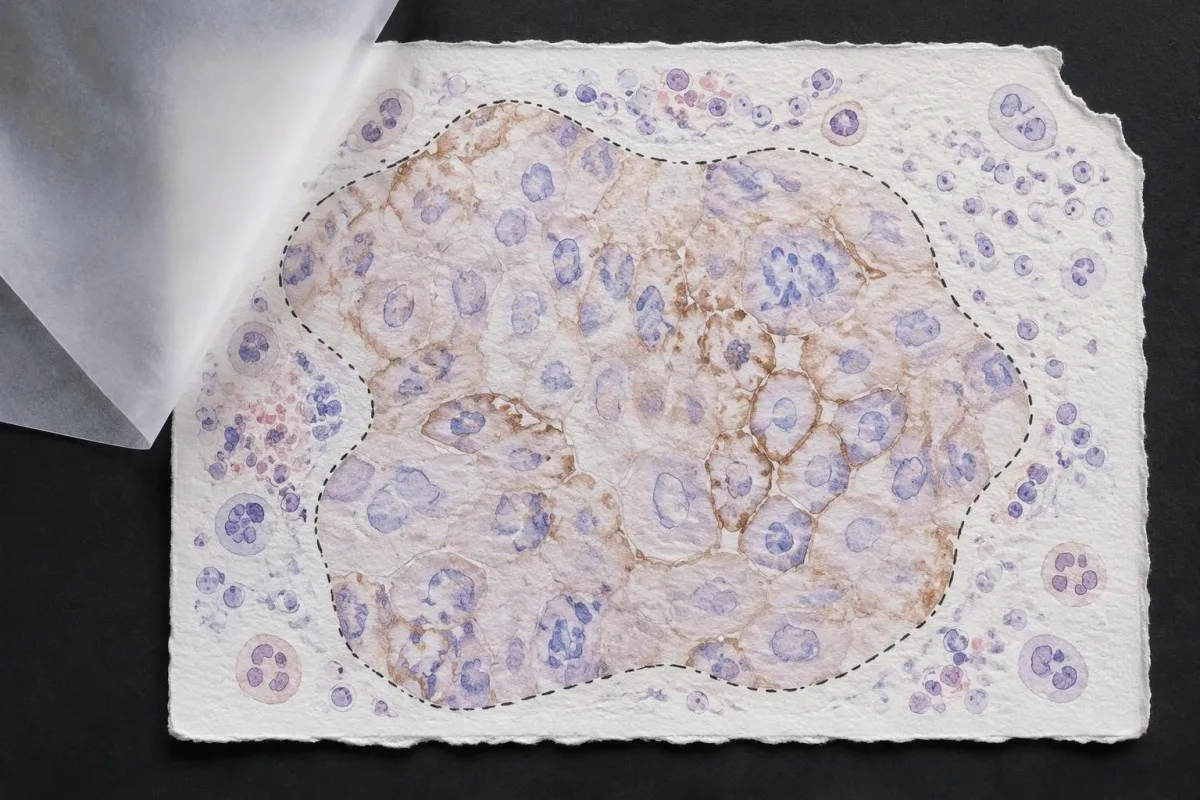
TPS = buhi nga mga selula sa tumor nga positibo sa PD-L1 ÷ tanang buhi nga selula sa tumor × 100%. Sa pananglitan nga natad sa tisyu nga adunay 200 ka buhi nga selula sa tumor, ang 80 ka kwalipikadong positibong selula mohatag og TPS 40%; dili mausab sa duol nga mga lymphocyte nga nakolor ang maong kalkulasyon, bisan og mahimong maapektuhan niini ang laing sistema sa pag-iskor.
Membrane location matters more than visual darkness alone. For commonly used TPS methods, weak qualifying membrane staining can count, whereas staining limited to tumor-cell cytoplasm does not establish a positive tumor cell; TPS 1% therefore describes the fraction of qualifying cells, not a required intensity grade.
Cutoffs such as TPS 1% ug TPS 50% were used to define populations in particular lung-cancer trials and treatment pathways. They are not boundaries between harmless and dangerous cancer, and crossing 50% does not create an abrupt biological switch from treatment resistance to guaranteed sensitivity.
Read the exact reporting format: TPS <1%, TPS 1–49%, and TPS ≥50% provide different detail from a single positive flag. Our explanation of kalidad kumpara sa gidaghanon nga mga resulta covers why a category cannot replace a number, although PD-L1 uses tissue-specific—not blood-reference-range—rules.
Kahulogan sa score sa PD-L1 CPS: nganong giihap ang mga selula sa imyunidad
Combined positive score, o CPS, includes qualifying PD-L1-positive tumor cells, lymphocytes, and macrophages. CPS divides their combined count by the number of viable tumor cells and multiplies by 100; the denominator does not become all cells simply because immune cells enter the numerator.

CPS = positive tumor cells plus qualifying positive lymphocytes and macrophages ÷ viable tumor cells × 100. In a hypothetical sample with 500 viable tumor cells, 50 positive tumor cells, and 75 qualifying positive immune cells, CPS is 25; the tumor-cell-only TPS would be 10%.
The reported CPS is capped at 100, even if the uncapped arithmetic would exceed 100 because many qualifying immune cells surround relatively few tumor cells. CPS is a unitless score, not a percentage of all cells, a blood concentration, or a probability that immunotherapy will work.
Not every stained immune cell belongs in the CPS count. The pathologist applies the assay manual's rules for eligible lymphocytes and macrophages associated with the tumor; neutrophils, unrelated inflammatory areas, and nonviable tissue are not simply added because a slide contains visible staining.
A CPS of 20 can arise from more than 1 cellular pattern: abundant tumor-cell staining, substantial immune-cell staining, or both. This denominator issue resembles the distinction between cell counts and percentages, but a circulating monocyte count cannot supply the tissue information needed to calculate CPS.
Nganong dili mahimong ilisan o i-convert ang CPS ug TPS
CPS and TPS are not interchangeable because they count different cells and were validated in different treatment settings. A TPS of 10% cannot be converted reliably into CPS 10, and a CPS of 20 does not establish that 20% of tumor cells stain.

Consider 2 hypothetical specimens with 500 viable tumor cells and 50 positive tumor cells each. The first has no qualifying positive immune cells and gives TPS 10% with CPS 10; the second contains 75 qualifying positive immune cells and gives the same TPS 10% with CPS 25.
The reverse inference fails too. A hypothetical CPS 20 could result from 20 positive tumor cells among 100 tumor cells, or from 5 positive tumor cells plus 15 qualifying positive immune cells; those examples have TPS 20% and TPS 5%, respectively, despite identical CPS values.
Usa ka immune-cell score, sometimes abbreviated IC, is another system rather than a third spelling of CPS. Some IC methods measure the proportion of tumor area occupied by stained immune cells, so an IC result of 1% must be interpreted using its own assay and indication—not a TPS threshold.
Kantesti's educational explanation should preserve all 3 scoring labels rather than flatten them into positive or negative. When using AI report explanations safely, check that the original score, assay, and specimen remain visible; an AI-generated conversion without the underlying tissue counts is not clinically dependable.
Unsang mga detalye sa report sa patolohiya ang importante labaw pa sa score?
A usable PD-L1 report should identify the specimen, assay, scoring method, numerical result, and adequacy assessment. Several commonly used protocols require at least 100 viable tumor cells, but minimum counts and acceptable specimen types depend on the particular test and cancer indication.
Antibody identifiers such as 22C3, 28-8, SP263, and SP142 describe different testing assays or antibody clones, not different PD-L1 proteins. Some assays show substantial agreement in selected settings, but laboratories should not assume universal equivalence across tumor types, scoring methods, immune-cell assessments, and treatment requirements.
The specimen date and site can change the interpretation of 1 reported number. A small primary-site sample taken before treatment may not represent a later metastatic deposit; ask whether the report describes the current treatment-setting specimen or archived tissue that the oncology team considers suitable.
Insufficient tissue is not PD-L1 negative. A sample with too few viable tumor cells, failed controls, extensive tissue change, or unsuitable processing may be unreportable; the practical next step is laboratory clarification, additional sections, or another suitable specimen—not assigning TPS 0% or CPS 0.
Comparisons between 2 reports need more than matching dates. Our test timing and comparability guide explains the general problem of comparing unlike measurements; for PD-L1, the extra checks are anatomical site, prior treatment, fixation, tissue adequacy, assay, and scoring system.
Giunsa pag-usab sa matang sa kanser ang kahulogan sa positibo nga resulta?
PD-L1 positivity is indication-specific, not a universal diagnosis. TPS thresholds such as 1% or 50% are familiar in non-small-cell lung cancer, while CPS thresholds such as 1, 5, or 10 appear in selected other cancer settings; the drug, stage, and regimen must accompany the cutoff.

For recurrent or metastatic head-and-neck squamous-cell carcinoma, KEYNOTE-048 evaluated CPS-defined populations. Pembrolizumab alone improved median overall survival in the CPS ≥20 group to 14.9 months versus 10.7 months with the comparator regimen, showing why a CPS threshold cannot be borrowed from a lung-cancer TPS report (Burtness et al., 2019).
Selected established pembrolizumab pathways use CPS ≥10 for unresectable locally advanced or metastatic triple-negative breast cancer with chemotherapy, and CPS ≥1 for certain persistent, recurrent, or metastatic cervical-cancer regimens. Those examples do not establish eligibility for every earlier-stage setting, drug combination, country, or funding pathway.
Gastric and gastroesophageal-junction cancers require particular care because treatment selection may also involve HER2 ug MSI/MMR, with PD-L1 requirements differing across regimens and jurisdictions. A serum marker described in our CA 72-4 interpretation guide cannot replace the tissue biomarker panel or define CPS.
Cancer diagnosis and treatment selection are 2 separate steps. Our persistent cough assessment guide addresses when lung symptoms need investigation; once cancer is confirmed, ask the oncology team to match the PD-L1 result to the current local product information and clinical pathway.
Nganong sama ka importante sa cutoff ang regimen sa pagtambal
Immunotherapy alone and immunotherapy combinations can have different PD-L1 requirements. A TPS below 1% may rule out one PD-L1-selected monotherapy pathway without ruling out an appropriate chemotherapy–immunotherapy combination; these are different clinical decisions, not contradictory interpretations of the same result.

KEYNOTE-024 enrolled previously untreated advanced non-small-cell lung cancer with TPS ≥50% and no sensitizing EGFR mutation or ALK rearrangement. Median progression-free survival was 10.3 months with pembrolizumab versus 6.0 months with chemotherapy, supporting that specific high-TPS monotherapy setting—not every cancer with a score above 50 (Reck et al., 2016).
Sa KEYNOTE-189, pembrolizumab plus pemetrexed and platinum chemotherapy improved outcomes in previously untreated metastatic nonsquamous non-small-cell lung cancer without EGFR or ALK alterations. Twelve-month overall survival was 69.2% versus 49.4%, and benefit was observed across PD-L1 categories, including TPS <1% (Gandhi et al., 2018).
Combination treatment may address rapid disease progression differently from a single agent, but adding drugs also adds toxicity and monitoring needs. If a proposed regimen includes fluorouracil or capecitabine, ang pagsulay sa DPYD sa dili pa ang chemotherapy concerns treatment safety; it does not measure the PD-L1 pathway or predict the same benefit.
Si Kantesti usa ka AI pagsabot sa resulta sa blood test platform that helps explain supporting laboratory measurements; it does not select between 1-drug and multidrug cancer regimens. Similarly, UGT1A1 and irinotecan safety address metabolism-related toxicity, illustrating why each biomarker should be matched to the specific medicine under discussion.
Naggarantiya ba ang positibo nga resulta sa PD-L1 nga makabenepisyo sa immunotherapy?
A positive PD-L1 result does not guarantee a response. In KEYNOTE-024's selected high-expression lung-cancer population, the objective response rate with pembrolizumab was 44.8%—substantial benefit for many participants, but clearly not a response in every person with TPS ≥50%.
The 44.8% response rate in KEYNOTE-024 describes a trial population under defined conditions, not an individual's calculated chance of success (Reck et al., 2016). Objective response also means measurable tumor shrinkage by trial criteria; stable disease and survival benefit are different outcomes that should not be collapsed into that single percentage.
PD-L1 is only 1 part of a broader immune environment. A cancer can show substantial staining while lacking effective immune-cell access, recognizable targets, or intact antigen presentation; these mechanisms help explain why expression enriches for benefit in some settings without functioning as a deterministic on–off switch.
Higher does not always mean better across different cancers and combinations. A CPS 30 in one disease cannot be ranked against TPS 60% in another, and the same CPS threshold may have different predictive value when used for monotherapy versus a combination that already provides benefit through other mechanisms.
Some melanoma immunotherapy regimens do not require a positive PD-L1 test, so a low score should not be interpreted using lung-cancer monotherapy rules. Our melanoma warning-sign guide addresses recognition and assessment, while treatment benefit must be discussed using disease-specific trial evidence and the person's overall condition.
Mahimo pa bang itanyag ang immunotherapy kon negatibo ang PD-L1?
PD-L1-negative cancers can still have appropriate immunotherapy options. TPS <1% or CPS <1 may exclude a particular PD-L1-selected regimen, but some combinations, earlier-stage pathways, and treatments selected by other biomarkers do not require PD-L1 positivity.
PD-L1-negative should first be translated into the laboratory's actual definition. TPS <1%, CPS <1, and an assay-specific IC-negative category are not identical measurements; an unreportable or inadequate sample is a fourth situation and should not be grouped with a technically valid negative result.
Usa ka MSI-high or mismatch-repair-deficient cancer may support particular immunotherapy pathways without PD-L1 selection, depending on the disease, stage, prior treatment, and local authorization. Tumor MMR testing and Pagsulay sa henetika alang sa Lynch syndrome answer related but different questions: an abnormal tumor result does not automatically prove an inherited syndrome.
Other genetic findings may point toward targeted treatment or different planning rather than immunotherapy. A result discussed in our BRCA variant interpretation guide does not turn CPS 0 into CPS 10; clinicians combine distinct biomarkers without pretending they measure the same biological feature.
No PD-L1 requirement is not the same as no selection criteria. A regimen can still require a particular histology, stage, treatment history, organ function, or absence of an actionable driver alteration; ask whether 1 negative score changes only the proposed option or the broader treatment plan.
Kanus-a mahimong makatarongan ang pagrepaso tungod sa pagkuha sa sample o score nga duol sa utlanan?
Sampling variation can change PD-L1 classification, especially near a treatment threshold. A CPS of 9 versus 10, or TPS 0.8% versus 1%, may prompt pathology review when the distinction would change an otherwise suitable treatment—but repeating every result is not automatically useful.

PD-L1 staining can be heterogeneous within 1 tissue block and between primary and metastatic sites. A small tissue examination may miss a highly expressing area or overrepresent it; the pathologist assesses the available viable tissue rather than assuming a single selected field describes the whole cancer.
Pretreatment and post-treatment specimens are not always equivalent. Chemotherapy, radiotherapy, and changes in the immune environment can alter expression, while decalcification of some bone specimens can impair antigen detection; ask whether a lower result reflects biology, processing limitations, or simply a different sampled site.
Borderline results require the actual assay rules, not homemade averaging. If 2 reports show CPS 8 and CPS 12, calculating CPS 10 does not create a newly validated result; the laboratory and oncology team should decide which specimen and assessment are appropriate for the treatment indication.
Kantesti cannot verify viable-cell counts, staining controls, or tissue suitability from a score alone. Our clinical validation ug pagdumala should be read in that limited context; when another tissue procedure is considered, its risks and likely impact on treatment need to be weighed against the uncertainty in the existing result.
Unsang ubang mga biomarker ang angay susihon kauban sa PD-L1?
Other biomarkers can take priority over PD-L1, depending on the cancer. In advanced non-small-cell lung cancer, molecular alterations such as EGFR mutations and ALK rearrangements affect treatment planning; in selected other cancers, HER2, MSI/MMR, or additional molecular findings may change the preferred pathway.
A high TPS does not cancel an actionable molecular finding. The pivotal KEYNOTE-024 ug KEYNOTE-189 populations excluded relevant EGFR or ALK alterations, so their results should not be applied unchanged to those groups; treatment sequence also matters because some targeted therapies and checkpoint inhibitors can interact through toxicity.
Tumor mutational burden, often measured in mutations per megabase, is a different biomarker from PD-L1. A threshold such as 10 mutations/Mb has been used in a specific tissue-agnostic treatment context, but assay differences, cancer type, authorization, and clinical setting prevent it from becoming a universal immunotherapy rule.
A liquid molecular test may find circulating tumor DNA, but it does not automatically replace tissue PD-L1 immunohistochemistry. The 2 tests measure different things—genetic material versus protein location within cells—and a negative liquid result may also reflect limited DNA shedding rather than absence of a tumor alteration.
Kantesti AI distinguishes the role of supporting laboratory markers from tissue-based treatment biomarkers in our giya sa reperensiya sa biomarker sa dugo. A blood-cell ratio, LDH level, or serum tumor-marker concentration should not be used to manufacture TPS 50%, estimate CPS 10, or bypass an indicated molecular workup.
Unsang mga pagsusi sa kaluwasan ang importante kon ikonsiderar ang immunotherapy?
PD-L1 scores predict neither treatment safety nor immune-related toxicity. A TPS of 90% does not make checkpoint treatment safer than TPS 1%; the team assesses medical history, organ function, medications, and the particular regimen separately from the tissue biomarker.
Checkpoint inhibitors can cause immune-related effects involving the thyroid, liver, lungs, bowel, kidneys, heart, and other organs. Baseline testing commonly includes liver chemistry, creatinine, thyroid measurements, and a complete blood count, with monitoring schedules varying by regimen; 1 normal baseline panel does not prevent later toxicity.
New chest pain, palpitations, fainting, or breathlessness during treatment requires prompt assessment because myocarditis, although uncommon, can be serious. Our myocarditis test interpretation guide explains why troponin supports evaluation but cannot determine the cause by itself; severe symptoms warrant emergency care rather than waiting for the next scheduled panel.
Kidney changes need interpretation against the person's own baseline and treatment exposures. A hypothetical creatinine rise from 0.8 to 1.6 mg/dL is a doubling even if the absolute value looks only modestly elevated; our kidney function testing guide explains supporting measurements, not an immunotherapy-specific treatment decision.
Pre-existing autoimmune disease, organ transplantation, ongoing immunosuppression, or previous severe immune-related toxicity can complicate treatment planning even when CPS is 100. Report new persistent diarrhea, worsening cough, jaundice, unusual weakness, or marked thirst promptly; neither a high PD-L1 score nor previously reassuring blood results justify delaying symptom assessment.
Unsay angay nimong ipangutana sa imong appointment sa oncology?
Dad-a ang complete PD-L1 pathology report and ask which exact treatment decision it informs. Four useful starting questions are: Which score was used? Which cutoff applies? Is the specimen adequate? What options remain if the result is below the cutoff?
A hypothetical report reading 22C3, CPS 12, adequate tissue is still incomplete as a treatment answer until the cancer, stage, and regimen are specified. Ask whether CPS ≥10 is relevant to the proposed option, whether other biomarkers are pending, and whether a combination would be considered under different selection rules.
Request explanations of 3 outcomes separately: tumor shrinkage, duration of disease control, and survival. A trial's response rate is not the same as its survival benefit, while median survival is a group midpoint—not an individual deadline—and the balance between rapid control and treatment toxicity may change the preferred regimen.
Si Kantesti usa ka AI lab test interpretation service for supporting laboratory understanding, not independent immunotherapy eligibility assessment. If blood monitoring is planned, our giya sa pag-andam sa baseline nga pagsulay can help organize previous values, units, medication lists, and collection dates so that the oncology team can compare results meaningfully.
Keep tissue scores separate from serial blood monitoring in 2 clearly labeled records. Our giya sa trend sa kaluwasan sa tambal explains why changes over time need context; our mga prinsipyo sa responsable nga AI also make clear that automated explanations should not trigger treatment changes without clinical review.
Mga publikasyon sa panukiduki ug mga limitasyon sa ebidensiya bahin sa PD-L1
PD-L1 interpretation should be grounded in cancer-specific trials and validated pathology methods. The 3 clinical references below address high-TPS lung-cancer monotherapy, lung-cancer combination treatment, and CPS-selected head-and-neck treatment; the 2 separate Zenodo publications concern other laboratory topics and do not establish PD-L1 thresholds.
KEYNOTE-024 supports a defined TPS ≥50% advanced lung-cancer population, whereas KEYNOTE-189 supports a particular combination across PD-L1 categories (Reck et al., 2016; Gandhi et al., 2018). Those different study designs explain why evidence for one regimen cannot be substituted for evidence supporting another simply because both drugs affect the same immune pathway.
KEYNOTE-048 assessed CPS-defined recurrent or metastatic head-and-neck cancer populations, including CPS ≥1 and CPS ≥20 groups (Burtness et al., 2019). When reading a trial, check the histology, stage, previous treatment, comparator, and endpoint; a subgroup survival finding does not automatically quantify an individual's chance of measurable shrinkage.
Kantesti's 2 Zenodo publications listed below are educational resources on complement/ANA testing and Nipah-virus diagnostics, not PD-L1 clinical trials or assay-validation studies. The giya sa complement ug ANA concerns different laboratory questions, and a DOI identifies a deposited publication without independently establishing clinical validity.
Use the original pathology result and current local treatment information to resolve eligibility—not a generalized positive/negative table or an AI-generated score conversion. Our mga sumbanan sa medikal nga sulod emphasize source relevance and uncertainty; ask your oncology team to document the 1 specific regimen, applicable threshold, and remaining alternatives.
Mga kanunayng gipangutana
Unsa ang kahulogan sa pagka-PD-L1 positibo?
Ang PD-L1 positive nagpasabot nga ang resulta sa tisyu nakaabot sa gitakdang sukdanan sa assay ug scoring, sama sa TPS ≥1% o CPS ≥1 sa angay nga kahimtang. Nagdepende ang sukdanan sa matang sa kanser, regimen sa pagtambal, ug lokal nga mga kinahanglanon sa pagtambal. Dili pamatuod ang positibong resulta nga molampos ang immunotherapy, ug ang report angay magpaila sa numerikal nga score, dili kay positibo ra nga timaan.
Unsa ang kalainan tali sa CPS ug TPS?
Gisukod sa TPS ang porsiyento sa mga buhing selula sa tumor nga adunay kwalipikadong pagkolor sa lamad sa PD-L1, samtang gilakip sa CPS ang mga kwalipikadong positibong selula sa tumor, lymphocyte, ug macrophage, gibahin sa mga buhing selula sa tumor ug gipadaghan sa 100. Gireport ang TPS gikan sa 0% hangtod 100%, ug kutob sa 100 ang CPS nga gireport. Dili mahimong i-convert ang mga score kay nagsalig ang CPS sa pagkolor sa mga selulang imyun nga wala giihap sa TPS.
Nagpasabot ba ang CPS 10 og 10% nga tsansa nga molampos ang immunotherapy?
Ang CPS 10 wala magpasabot nga adunay 10% nga kahigayonang motubag sa immunotherapy. Ang CPS usa ka kalkulasyon sa pagkolor sa tisyu nga buhing mga selula sa tumor ang denominator niini, dili usa ka indibidwal nga posibilidad sa pagtubag sa pagtambal. Ang CPS ≥10 nagsuporta sa pagpili alang sa pipila ka mga regimen nga espesipiko sa kanser, apan aron mabanabana ang posibleng kaayohan, kinahanglan usab mahibal-an ang diagnosis sa kanser, yugto, ubang mga biomarker, ug ebidensiya alang sa gisugyot nga pagtambal.
Mahimo ba akong makadawat og immunotherapy kon negatibo ang PD-L1?
Ang negatibong resulta sa PD-L1 wala magpasabot nga dili na mahimong kapilian ang tanang immunotherapy. Ang pipila ka kombinasyon sa chemotherapy–immunotherapy ug uban pang pamaagi nga gipili base sa mga biomarker dili manginahanglan og positibong PD-L1, bisan kon ubos sa 1% ang TPS. Magdepende gihapon ang pagkaangay sa matang sa kanser, yugto niini, mga resulta sa molekular nga pagsusi, kasaysayan sa pagtambal, kahimtang sa panglawas, ug pagtugot sa lokal nga mga awtoridad; ang dili igo nga sampol sa tisyu dili angay isipon nga balidong negatibong resulta.
Giisip ba nga taas ang PD-L1 kung 50% ang TPS?
Kasagarang gihulagway ang TPS ≥50% isip taas nga ekspresyon sa PD-L1 sa pipila ka piniling kahimtang sa kanser sa baga nga dili gagmay ang selula. Gigamit kini nga sukdanan sa KEYNOTE-024, nga nagtuon sa usa ka piho nga populasyon nga adunay abanteng kanser sa baga, nga walay sensitizing nga mga mutasyon sa EGFR o mga rearrangement sa ALK. Dili katumbas ang TPS 50% sa CPS 50, ug dili kini pangkalahatang sukdanan alang sa tanang kanser, yugto sa sakit, o regimen sa immunotherapy.
Pagsulay ba sa dugo ang PD-L1, ug angay ba kining usbon?
Ang klinikal nga pag-iskor sa PD-L1 alang sa CPS ug TPS kasagarang naggamit og napreserbar nga tisyu sa kanser nga gisusi pinaagi sa immunohistochemistry, dili ordinaryong sampol sa dugo. Makatabang ang pagsubli sa pagsusi kon dili igo ang tisyu, duol ang resulta sa cutoff nga makausab sa desisyon sama sa CPS 10, o mas angay gamiton ang laing espesimen. Ang mga team sa oncology ug pathology ang angay modesisyon kon ang pagrepaso, dugang nga mga seksiyon, o laing espesimen lagmit makausab sa pag-atiman sa igo nga sukod aron makatarunganon ang kaubang paningkamot ug mga risgo sa pamaagi.
Paipatin-aw ang imong resulta sa blood test
I-upload ang report sa imong laboratoryo ug ipatin-aw sa AI sa Kantesti ang matag biomarker sa yano nga pinulongan sulod sa pipila ka segundo. Gigamit sa kapin sa 2 ka milyon ka tawo sa tibuok kalibotan.
Mga Reperensya
- Klein, T., Mitchell, S., & Weber, H. (2026). Giya sa Pagsulay sa Dugo para sa C3 C4 Complement ug sa Titer sa ANA. Panukiduki Medikal sa Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Pagsulay sa Dugo alang sa Nipah Virus: Giya sa Sayong Pagsusi ug Pagdayagnos 2026. Panukiduki Medikal sa Kantesti AI. DOI
- Reck M et al. (2016). Pembrolizumab versus Chemotherapy for PD-L1–Positive Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Gandhi L et al. (2018). Pembrolizumab plus Chemotherapy in Metastatic Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Burtness B et al. (2019). Pembrolizumab alone or with chemotherapy versus cetuximab with chemotherapy for recurrent or metastatic squamous cell carcinoma of the head and neck (KEYNOTE-048): a randomised, open-label, phase 3 study. The Lancet. DOI
- 2M+Mga gisusi nga eksaminasyon
- 127+Mga nasud
- 100+Mga pinulongan
Mahitungod sa medikal nga team


Mga E-E-A-T Trust Signals
Kasinatian
Pagsusi sa klinika nga gipangulohan sa doktor sa mga workflow sa interpretasyon sa lab.
Kahanas
Pokus sa medisina sa laboratoryo kung giunsa paglihok ang mga biomarker sa konteksto sa klinika.
Pagka-awtorisado
Gisusi sa medisina ni Dr. Thomas Klein, uban sa mga kontribusyon ni Dr. Sarah Mitchell ug Prof. Dr. Hans Weber.
Kasaligan
Interpretasyon nga base sa ebidensya, nga adunay klaro nga mga agianan sa sunod nga buhat aron makunhuran ang kabalaka.





Disclaimer sa medisina
Kini nga artikulo para sa katuyoan sa edukasyon ra ug dili kini mosangpot sa medikal nga tambag. Kanunay mokonsulta sa usa ka kwalipikado nga healthcare provider alang sa mga desisyon sa diagnosis ug pagtambal.
Gibilin · Kontaka ang team sa editoryal
Gipatik sa Kantesti Ltd, narehistro sa England ug Wales, numero sa kompanya. 17090423, London, United Kingdom.
