Rezultati PD-L1 opisujejo obarvanje v vzorcu tkiva – ne vaše osebne možnosti za uspeh zdravljenja. Metoda točkovanja, diagnoza raka in predlagana kombinacija zdravil določajo, kaj lahko rezultat potrdi.

Ključne ugotovitve
- Rezultati testiranja PD-L1 merijo obarvanje beljakovin v rakavem tkivu; niso rutinski rezultati krvnih preiskav ali presejalni test za raka.
- TPS je odstotek živih tumorskih celic z ustreznim membranskim obarvanjem, izražen od 0 % do 100 %.
- CPS prešteje ustrezne tumorske celice, limfocite in makrofage, pozitivne na PD-L1, rezultat deli s številom živih tumorskih celic in pomnoži s 100; poročana ocena je omejena na največ 100.
- Različne ocene ni mogoče pretvoriti: TPS 10% se lahko pojavi skupaj s CPS 10, CPS 25 ali drugo vrednostjo, odvisno od obarvanja imunskih celic.
- Mejni vrednosti kot so TPS 1 %, TPS 50 %, CPS 1 in CPS 10, veljajo za določene vrste raka in načine zdravljenja – ne pa za vsako imunoterapijo.
- Pozitivni rezultati lahko pomagajo pri izbiri zdravljenja, vendar ne zagotavljajo koristi; ocena 50 ne pomeni 50-odstotne verjetnosti odziva.
- Negativni rezultati ne izključujejo vedno imunoterapije, saj pri nekaterih kombinacijah in zdravljenjih, določenih z biomarkerji, pozitivnost PD-L1 ni potrebna.
- Ustreznost vzorca je pomembna: več pogosto uporabljenih protokolov ocenjevanja zahteva vsaj 100 živih tumorskih celic, laboratorij pa mora upoštevati pravila, specifična za posamezno indikacijo.
Kaj rezultati testiranja PD-L1 dejansko povedo?
Rezultati testiranja PD-L1 opisujejo obarvanje beljakovin v rakavem tkivu. TPS šteje odstotek obarvanih tumorskih celic; CPS vključuje tudi izbrane obarvane imunske celice. Nobena od ocen sama po sebi ne določa zdravljenja: ustrezna mejna vrednost je odvisna od vrste raka, stadija, testa in režima zdravljenja, pozitivni ali negativni rezultati pa ne zagotavljajo koristi oziroma ne izključujejo zdravljenja.
PD-L1, ali ligand 1 programirane celične smrti se lahko veže na receptor PD-1 na imunskih celicah in zmanjša njihovo aktivnost. Zdravila, ki ciljajo na to interakcijo, lahko obnovijo protirakavo imunsko aktivnost, vendar merjenje ene beljakovine ne zajame vseh dejavnikov, ki določajo, ali imunske celice prepoznajo raka in ga obvladujejo.
Rezultat PD-L1 v tkivu se običajno pridobi z metodo imunohistokemije, pri kateri se z uporabo protitelesa prikaže mesto beljakovine v ohranjenem vzorcu. Sporočena vrednost opisuje celice na izbranih rezih tkiva – ne vseh rakavih celic po telesu – in 2 vzorca z različnih mest lahko dajeta različne rezultate.
Kantesti je AI analizator krvi, ne pa nadomestilo za tkivno patologijo ali odločitev o onkološkem zdravljenju. Naš organizacija in klinični obseg razlikujejo izobraževalno podporo pri laboratorijskih izvidih od odločitev, pri katerih je treba skupaj pregledati izvirno patološko poročilo, slikovne preiskave in predlagani režim zdravljenja.
Preden razlagate vrednost, najprej preverite 4 podatke: diagnozo raka, ali je ocena CPS ali TPS, uporabljeni test in predvideno zdravljenje. Izvid, ki navaja samo pozitivnost PD-L1, ne vsebuje pomembnega kliničnega podatka; povprašajte po metodi ocenjevanja in številčni vrednosti.
Pomen ocene PD-L1 TPS: odstotek tumorskih celic
Delež tumorskih celic, ali TPS, je odstotek živih tumorskih celic, ki kažejo ustrezno delno ali popolno membransko obarvanje PD-L1. TPS se giblje od 0 % do 100 %; imunske celice niso vključene v števec, tudi če so močno obarvane ob rakavih celicah.
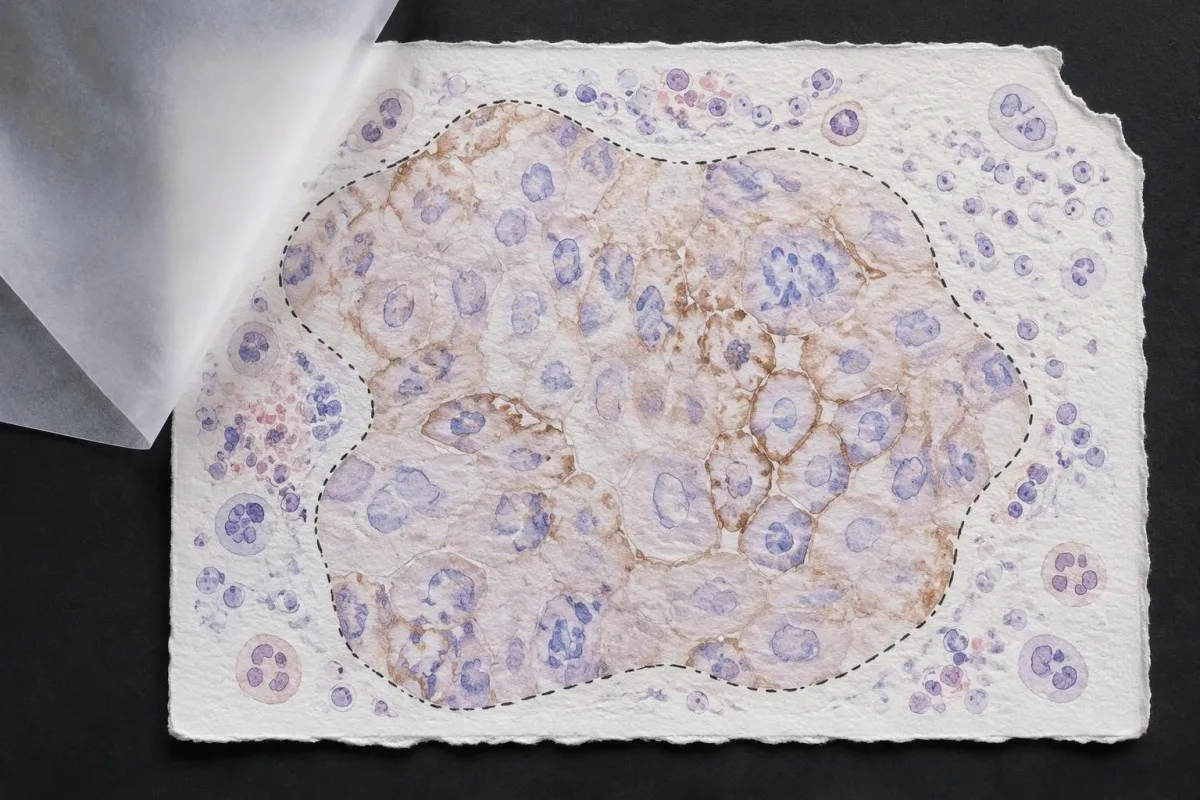
TPS = žive tumorske celice, pozitivne na PD-L1 ÷ vse žive tumorske celice × 100 %. V hipotetičnem polju tkiva z 200 živimi tumorskimi celicami 80 ustrezno pozitivnih celic pomeni TPS 40%; obarvani limfociti v bližini tega izračuna ne spremenijo, lahko pa vplivajo na drugačen sistem ocenjevanja.
Membrane location matters more than visual darkness alone. For commonly used TPS methods, weak qualifying membrane staining can count, whereas staining limited to tumor-cell cytoplasm does not establish a positive tumor cell; TPS 1% therefore describes the fraction of qualifying cells, not a required intensity grade.
Cutoffs such as TPS 1% in TPS 50% were used to define populations in particular lung-cancer trials and treatment pathways. They are not boundaries between harmless and dangerous cancer, and crossing 50% does not create an abrupt biological switch from treatment resistance to guaranteed sensitivity.
Read the exact reporting format: TPS <1%, TPS 1–49%, and TPS ≥50% provide different detail from a single positive flag. Our explanation of kvalitativni v primerjavi s kvantitativnimi rezultati covers why a category cannot replace a number, although PD-L1 uses tissue-specific—not blood-reference-range—rules.
Pomen ocene PD-L1 CPS: zakaj štejejo imunske celice
Combined positive score, ali CPS, includes qualifying PD-L1-positive tumor cells, lymphocytes, and macrophages. CPS divides their combined count by the number of viable tumor cells and multiplies by 100; the denominator does not become all cells simply because immune cells enter the numerator.

CPS = positive tumor cells plus qualifying positive lymphocytes and macrophages ÷ viable tumor cells × 100. In a hypothetical sample with 500 viable tumor cells, 50 positive tumor cells, and 75 qualifying positive immune cells, CPS is 25; the tumor-cell-only TPS would be 10%.
The reported CPS is capped at 100, even if the uncapped arithmetic would exceed 100 because many qualifying immune cells surround relatively few tumor cells. CPS is a unitless score, not a percentage of all cells, a blood concentration, or a probability that immunotherapy will work.
Not every stained immune cell belongs in the CPS count. The pathologist applies the assay manual's rules for eligible lymphocytes and macrophages associated with the tumor; neutrophils, unrelated inflammatory areas, and nonviable tissue are not simply added because a slide contains visible staining.
A CPS of 20 can arise from more than 1 cellular pattern: abundant tumor-cell staining, substantial immune-cell staining, or both. This denominator issue resembles the distinction between cell counts and percentages, but a circulating monocyte count cannot supply the tissue information needed to calculate CPS.
Zakaj ocen CPS in TPS ni mogoče zamenjati ali pretvoriti
CPS and TPS are not interchangeable because they count different cells and were validated in different treatment settings. A TPS of 10% cannot be converted reliably into CPS 10, and a CPS of 20 does not establish that 20% of tumor cells stain.

Consider 2 hypothetical specimens with 500 viable tumor cells and 50 positive tumor cells each. The first has no qualifying positive immune cells and gives TPS 10% with CPS 10; the second contains 75 qualifying positive immune cells and gives the same TPS 10% with CPS 25.
The reverse inference fails too. A hypothetical CPS 20 could result from 20 positive tumor cells among 100 tumor cells, or from 5 positive tumor cells plus 15 qualifying positive immune cells; those examples have TPS 20% and TPS 5%, respectively, despite identical CPS values.
En immune-cell score, sometimes abbreviated IC, is another system rather than a third spelling of CPS. Some IC methods measure the proportion of tumor area occupied by stained immune cells, so an IC result of 1% must be interpreted using its own assay and indication—not a TPS threshold.
Kantesti's educational explanation should preserve all 3 scoring labels rather than flatten them into positive or negative. When using AI report explanations safely, check that the original score, assay, and specimen remain visible; an AI-generated conversion without the underlying tissue counts is not clinically dependable.
Kateri podatki v patološkem izvidu so pomembni poleg ocene?
A usable PD-L1 report should identify the specimen, assay, scoring method, numerical result, and adequacy assessment. Several commonly used protocols require at least 100 viable tumor cells, but minimum counts and acceptable specimen types depend on the particular test and cancer indication.
Antibody identifiers such as 22C3, 28-8, SP263, and SP142 describe different testing assays or antibody clones, not different PD-L1 proteins. Some assays show substantial agreement in selected settings, but laboratories should not assume universal equivalence across tumor types, scoring methods, immune-cell assessments, and treatment requirements.
The specimen date and site can change the interpretation of 1 reported number. A small primary-site sample taken before treatment may not represent a later metastatic deposit; ask whether the report describes the current treatment-setting specimen or archived tissue that the oncology team considers suitable.
Insufficient tissue is not PD-L1 negative. A sample with too few viable tumor cells, failed controls, extensive tissue change, or unsuitable processing may be unreportable; the practical next step is laboratory clarification, additional sections, or another suitable specimen—not assigning TPS 0% or CPS 0.
Comparisons between 2 reports need more than matching dates. Our test timing and comparability guide explains the general problem of comparing unlike measurements; for PD-L1, the extra checks are anatomical site, prior treatment, fixation, tissue adequacy, assay, and scoring system.
Kako vrsta raka spremeni pomen pozitivnega rezultata?
PD-L1 positivity is indication-specific, not a universal diagnosis. TPS thresholds such as 1% or 50% are familiar in non-small-cell lung cancer, while CPS thresholds such as 1, 5, or 10 appear in selected other cancer settings; the drug, stage, and regimen must accompany the cutoff.

For recurrent or metastatic head-and-neck squamous-cell carcinoma, KEYNOTE-048 evaluated CPS-defined populations. Pembrolizumab alone improved median overall survival in the CPS ≥20 group to 14.9 months versus 10.7 months with the comparator regimen, showing why a CPS threshold cannot be borrowed from a lung-cancer TPS report (Burtness et al., 2019).
Selected established pembrolizumab pathways use CPS ≥10 for unresectable locally advanced or metastatic triple-negative breast cancer with chemotherapy, and CPS ≥1 for certain persistent, recurrent, or metastatic cervical-cancer regimens. Those examples do not establish eligibility for every earlier-stage setting, drug combination, country, or funding pathway.
Gastric and gastroesophageal-junction cancers require particular care because treatment selection may also involve HER2 in MSI/MMR, with PD-L1 requirements differing across regimens and jurisdictions. A serum marker described in our CA 72-4 interpretation guide cannot replace the tissue biomarker panel or define CPS.
Cancer diagnosis and treatment selection are 2 separate steps. Our persistent cough assessment guide addresses when lung symptoms need investigation; once cancer is confirmed, ask the oncology team to match the PD-L1 result to the current local product information and clinical pathway.
Zakaj je režim zdravljenja enako pomemben kot mejna vrednost
Immunotherapy alone and immunotherapy combinations can have different PD-L1 requirements. A TPS below 1% may rule out one PD-L1-selected monotherapy pathway without ruling out an appropriate chemotherapy–immunotherapy combination; these are different clinical decisions, not contradictory interpretations of the same result.

KEYNOTE-024 enrolled previously untreated advanced non-small-cell lung cancer with TPS ≥50% and no sensitizing EGFR mutation or ALK rearrangement. Median progression-free survival was 10.3 months with pembrolizumab versus 6.0 months with chemotherapy, supporting that specific high-TPS monotherapy setting—not every cancer with a score above 50 (Reck et al., 2016).
Pri KEYNOTE-189, pembrolizumab plus pemetrexed and platinum chemotherapy improved outcomes in previously untreated metastatic nonsquamous non-small-cell lung cancer without EGFR or ALK alterations. Twelve-month overall survival was 69.2% versus 49.4%, and benefit was observed across PD-L1 categories, including TPS <1% (Gandhi et al., 2018).
Combination treatment may address rapid disease progression differently from a single agent, but adding drugs also adds toxicity and monitoring needs. If a proposed regimen includes fluorouracil or capecitabine, testiranje DPYD pred kemoterapijo concerns treatment safety; it does not measure the PD-L1 pathway or predict the same benefit.
Kantesti je platforma za razlaga krvne slike z AI that helps explain supporting laboratory measurements; it does not select between 1-drug and multidrug cancer regimens. Similarly, UGT1A1 and irinotecan safety address metabolism-related toxicity, illustrating why each biomarker should be matched to the specific medicine under discussion.
Ali pozitiven rezultat PD-L1 zagotavlja korist od imunoterapije?
A positive PD-L1 result does not guarantee a response. In KEYNOTE-024's selected high-expression lung-cancer population, the objective response rate with pembrolizumab was 44.8%—substantial benefit for many participants, but clearly not a response in every person with TPS ≥50%.
The 44.8% response rate in KEYNOTE-024 describes a trial population under defined conditions, not an individual's calculated chance of success (Reck et al., 2016). Objective response also means measurable tumor shrinkage by trial criteria; stable disease and survival benefit are different outcomes that should not be collapsed into that single percentage.
PD-L1 is only 1 part of a broader immune environment. A cancer can show substantial staining while lacking effective immune-cell access, recognizable targets, or intact antigen presentation; these mechanisms help explain why expression enriches for benefit in some settings without functioning as a deterministic on–off switch.
Higher does not always mean better across different cancers and combinations. A CPS 30 in one disease cannot be ranked against TPS 60% in another, and the same CPS threshold may have different predictive value when used for monotherapy versus a combination that already provides benefit through other mechanisms.
Some melanoma immunotherapy regimens do not require a positive PD-L1 test, so a low score should not be interpreted using lung-cancer monotherapy rules. Our melanoma warning-sign guide addresses recognition and assessment, while treatment benefit must be discussed using disease-specific trial evidence and the person's overall condition.
Ali je imunoterapija še vedno možna, če je PD-L1 negativen?
PD-L1-negative cancers can still have appropriate immunotherapy options. TPS <1% or CPS <1 may exclude a particular PD-L1-selected regimen, but some combinations, earlier-stage pathways, and treatments selected by other biomarkers do not require PD-L1 positivity.
PD-L1-negative should first be translated into the laboratory's actual definition. TPS <1%, CPS <1, and an assay-specific IC-negative category are not identical measurements; an unreportable or inadequate sample is a fourth situation and should not be grouped with a technically valid negative result.
En MSI-high or mismatch-repair-deficient cancer may support particular immunotherapy pathways without PD-L1 selection, depending on the disease, stage, prior treatment, and local authorization. Tumor MMR testing and Genetsko testiranje za Lynchov sindrom answer related but different questions: an abnormal tumor result does not automatically prove an inherited syndrome.
Other genetic findings may point toward targeted treatment or different planning rather than immunotherapy. A result discussed in our BRCA variant interpretation guide does not turn CPS 0 into CPS 10; clinicians combine distinct biomarkers without pretending they measure the same biological feature.
No PD-L1 requirement is not the same as no selection criteria. A regimen can still require a particular histology, stage, treatment history, organ function, or absence of an actionable driver alteration; ask whether 1 negative score changes only the proposed option or the broader treatment plan.
Kdaj lahko vzorčenje ali mejna ocena upravičita ponovni pregled?
Sampling variation can change PD-L1 classification, especially near a treatment threshold. A CPS of 9 versus 10, or TPS 0.8% versus 1%, may prompt pathology review when the distinction would change an otherwise suitable treatment—but repeating every result is not automatically useful.

PD-L1 staining can be heterogeneous within 1 tissue block and between primary and metastatic sites. A small tissue examination may miss a highly expressing area or overrepresent it; the pathologist assesses the available viable tissue rather than assuming a single selected field describes the whole cancer.
Pretreatment and post-treatment specimens are not always equivalent. Chemotherapy, radiotherapy, and changes in the immune environment can alter expression, while decalcification of some bone specimens can impair antigen detection; ask whether a lower result reflects biology, processing limitations, or simply a different sampled site.
Borderline results require the actual assay rules, not homemade averaging. If 2 reports show CPS 8 and CPS 12, calculating CPS 10 does not create a newly validated result; the laboratory and oncology team should decide which specimen and assessment are appropriate for the treatment indication.
Kantesti cannot verify viable-cell counts, staining controls, or tissue suitability from a score alone. Our klinična validacija in nadzor should be read in that limited context; when another tissue procedure is considered, its risks and likely impact on treatment need to be weighed against the uncertainty in the existing result.
Kateri drugi biomarkerji sodijo ob PD-L1?
Other biomarkers can take priority over PD-L1, depending on the cancer. In advanced non-small-cell lung cancer, molecular alterations such as EGFR mutations and ALK rearrangements affect treatment planning; in selected other cancers, HER2, MSI/MMR, or additional molecular findings may change the preferred pathway.
A high TPS does not cancel an actionable molecular finding. The pivotal KEYNOTE-024 in KEYNOTE-189 populations excluded relevant EGFR or ALK alterations, so their results should not be applied unchanged to those groups; treatment sequence also matters because some targeted therapies and checkpoint inhibitors can interact through toxicity.
Tumor mutational burden, often measured in mutations per megabase, is a different biomarker from PD-L1. A threshold such as 10 mutations/Mb has been used in a specific tissue-agnostic treatment context, but assay differences, cancer type, authorization, and clinical setting prevent it from becoming a universal immunotherapy rule.
A liquid molecular test may find circulating tumor DNA, but it does not automatically replace tissue PD-L1 immunohistochemistry. The 2 tests measure different things—genetic material versus protein location within cells—and a negative liquid result may also reflect limited DNA shedding rather than absence of a tumor alteration.
Kantesti AI distinguishes the role of supporting laboratory markers from tissue-based treatment biomarkers in our vodnik referenčnih vrednosti za krvne biomarkerje. A blood-cell ratio, LDH level, or serum tumor-marker concentration should not be used to manufacture TPS 50%, estimate CPS 10, or bypass an indicated molecular workup.
Kateri varnostni pregledi so pomembni, če pride v poštev imunoterapija?
PD-L1 scores predict neither treatment safety nor immune-related toxicity. A TPS of 90% does not make checkpoint treatment safer than TPS 1%; the team assesses medical history, organ function, medications, and the particular regimen separately from the tissue biomarker.
Checkpoint inhibitors can cause immune-related effects involving the thyroid, liver, lungs, bowel, kidneys, heart, and other organs. Baseline testing commonly includes liver chemistry, creatinine, thyroid measurements, and a complete blood count, with monitoring schedules varying by regimen; 1 normal baseline panel does not prevent later toxicity.
New chest pain, palpitations, fainting, or breathlessness during treatment requires prompt assessment because myocarditis, although uncommon, can be serious. Our myocarditis test interpretation guide explains why troponin supports evaluation but cannot determine the cause by itself; severe symptoms warrant emergency care rather than waiting for the next scheduled panel.
Kidney changes need interpretation against the person's own baseline and treatment exposures. A hypothetical creatinine rise from 0.8 to 1.6 mg/dL is a doubling even if the absolute value looks only modestly elevated; our kidney function testing guide explains supporting measurements, not an immunotherapy-specific treatment decision.
Pre-existing autoimmune disease, organ transplantation, ongoing immunosuppression, or previous severe immune-related toxicity can complicate treatment planning even when CPS is 100. Report new persistent diarrhea, worsening cough, jaundice, unusual weakness, or marked thirst promptly; neither a high PD-L1 score nor previously reassuring blood results justify delaying symptom assessment.
Kaj vprašati na onkološkem pregledu?
Prinesite complete PD-L1 pathology report and ask which exact treatment decision it informs. Four useful starting questions are: Which score was used? Which cutoff applies? Is the specimen adequate? What options remain if the result is below the cutoff?
A hypothetical report reading 22C3, CPS 12, adequate tissue is still incomplete as a treatment answer until the cancer, stage, and regimen are specified. Ask whether CPS ≥10 is relevant to the proposed option, whether other biomarkers are pending, and whether a combination would be considered under different selection rules.
Request explanations of 3 outcomes separately: tumor shrinkage, duration of disease control, and survival. A trial's response rate is not the same as its survival benefit, while median survival is a group midpoint—not an individual deadline—and the balance between rapid control and treatment toxicity may change the preferred regimen.
Kantesti je storitvi za interpretacijo laboratorijskih testov AI for supporting laboratory understanding, not independent immunotherapy eligibility assessment. If blood monitoring is planned, our vodnik za pripravo na začetno testiranje can help organize previous values, units, medication lists, and collection dates so that the oncology team can compare results meaningfully.
Keep tissue scores separate from serial blood monitoring in 2 clearly labeled records. Our vodnik po trendih varnosti zdravil explains why changes over time need context; our načela odgovorne uporabe umetne inteligence also make clear that automated explanations should not trigger treatment changes without clinical review.
Raziskovalne publikacije in omejitve dokazov o PD-L1
PD-L1 interpretation should be grounded in cancer-specific trials and validated pathology methods. The 3 clinical references below address high-TPS lung-cancer monotherapy, lung-cancer combination treatment, and CPS-selected head-and-neck treatment; the 2 separate Zenodo publications concern other laboratory topics and do not establish PD-L1 thresholds.
KEYNOTE-024 supports a defined TPS ≥50% advanced lung-cancer population, whereas KEYNOTE-189 supports a particular combination across PD-L1 categories (Reck et al., 2016; Gandhi et al., 2018). Those different study designs explain why evidence for one regimen cannot be substituted for evidence supporting another simply because both drugs affect the same immune pathway.
KEYNOTE-048 assessed CPS-defined recurrent or metastatic head-and-neck cancer populations, including CPS ≥1 and CPS ≥20 groups (Burtness et al., 2019). When reading a trial, check the histology, stage, previous treatment, comparator, and endpoint; a subgroup survival finding does not automatically quantify an individual's chance of measurable shrinkage.
Kantesti's 2 Zenodo publications listed below are educational resources on complement/ANA testing and Nipah-virus diagnostics, not PD-L1 clinical trials or assay-validation studies. The vodilo za komplement in ANA concerns different laboratory questions, and a DOI identifies a deposited publication without independently establishing clinical validity.
Use the original pathology result and current local treatment information to resolve eligibility—not a generalized positive/negative table or an AI-generated score conversion. Our standardi za medicinske vsebine emphasize source relevance and uncertainty; ask your oncology team to document the 1 specific regimen, applicable threshold, and remaining alternatives.
Pogosta vprašanja
Kaj pomeni, da je PD-L1 pozitiven?
PD-L1 pozitiven pomeni, da rezultat analize tkiva dosega določen prag testiranja in vrednotenja, na primer TPS ≥1 % ali CPS ≥1 v ustreznem kliničnem kontekstu. Prag je odvisen od vrste raka, režima zdravljenja in lokalnih zahtev glede zdravljenja. Pozitivnost ne dokazuje, da bo imunoterapija učinkovita, zato mora izvid navajati številčno vrednost rezultata, ne le oznake »pozitiven«.
Kakšna je razlika med CPS in TPS?
TPS meri odstotek vitalnih tumorskih celic z ustreznim membranskim obarvanjem PD-L1, medtem ko CPS vključuje ustrezno pozitivne tumorske celice, limfocite in makrofage, deljene s številom vitalnih tumorskih celic in pomnožene s 100. TPS se izraža od 0 % do 100 %, poročana vrednost CPS pa je omejena na 100. Vrednosti ni mogoče pretvoriti, ker je CPS odvisen od obarvanja imunskih celic, ki jih TPS ne upošteva.
Ali CPS 10 pomeni 10% možnost, da bo imunoterapija delovala?
CPS 10 ne pomeni 10% verjetnosti odziva na imunoterapijo. CPS je izračun na podlagi obarvanja tkiva, pri katerem so v imenovalcu žive tumorske celice, in ne pomeni verjetnosti, da se bo posameznik odzval na zdravljenje. CPS ≥10 podpira izbor določenih režimov zdravljenja za posamezne vrste raka, za oceno verjetne koristi pa so potrebni tudi diagnoza raka, stadij, drugi biomarkerji in dokazi o predlaganem zdravljenju.
Ali lahko prejemam imunoterapijo, če je PD-L1 negativen?
Negativen rezultat PD-L1 ne izključuje vseh možnosti imunoterapije. Za nekatere kombinacije kemoterapije in imunoterapije ter druge možnosti zdravljenja, izbrane na podlagi biomarkerjev, pozitiven status PD-L1 ni potreben, tudi kadar je TPS pod 1 %. Primernost je še vedno odvisna od vrste raka, stadija, molekularnih izsledkov, predhodnega zdravljenja, zdravstvene primernosti in lokalne odobritve; neustreznega vzorca tkiva ne smemo obravnavati kot veljaven negativen rezultat.
Ali se TPS 50 % šteje za visoko izraženost PD-L1?
TPS ≥ 50 % se v izbranih okoliščinah pri nedrobnoceličnem pljučnem raku pogosto opisuje kot visoko izražanje PD-L1. Ta prag je bil uporabljen v raziskavi KEYNOTE-024, ki je proučevala specifično skupino bolnikov z napredovalim pljučnim rakom, brez senzibilizirajočih mutacij EGFR ali preureditev gena ALK. TPS 50 % ni enakovreden CPS 50 in ni univerzalen prag za vse vrste raka, stadije ali sheme imunoterapije.
Ali je PD-L1 krvni test in ali ga je treba ponoviti?
Klinično ocenjevanje PD-L1 za CPS in TPS običajno temelji na ohranjenem rakavem tkivu, pregledanem z imunohistokemijo, ne pa na običajnem vzorcu krvi. Ponovna ocena je lahko koristna, če je vzorca tkiva premalo, če je rezultat blizu mejne vrednosti, ki bi lahko spremenila odločitev, na primer CPS 10, ali če je primernejši drug vzorec. Onkološka in patološka ekipa naj presodita, ali bi ponovni pregled, dodatni rezi ali drug vzorec verjetno dovolj vplivali na zdravljenje, da bi upravičili s tem povezani trud in tveganja posega.
Poskrbite, da vam razložijo rezultate krvnih preiskav
Naložite svoj laboratorijski izvid in AI Kantesti bo v nekaj sekundah preprosto razložil vsak biomarker. Uporablja ga več kot 2 milijona ljudi po vsem svetu.
Reference
- Klein, T., Mitchell, S., & Weber, H. (2026). Vodnik za krvni test komplementa C3 C4 in titer ANA. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Krvni test za virus Nipah: vodnik za zgodnje odkrivanje in diagnozo 2026. Kantesti AI Medical Research. DOI
- Reck M et al. (2016). Pembrolizumab versus Chemotherapy for PD-L1–Positive Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Gandhi L et al. (2018). Pembrolizumab plus Chemotherapy in Metastatic Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Burtness B et al. (2019). Pembrolizumab alone or with chemotherapy versus cetuximab with chemotherapy for recurrent or metastatic squamous cell carcinoma of the head and neck (KEYNOTE-048): a randomised, open-label, phase 3 study. The Lancet. DOI
- 2 milijona+Analizirani testi
- 127+Države
- 100+Jeziki
O zdravstveni ekipi


E-E-A-T zaupanja vredni signali
Izkušnje
Zdravniški klinični pregled delovnih postopkov za interpretacijo laboratorijskih izvidov.
Strokovno znanje
Laboratorijska medicina s poudarkom na tem, kako se biomarkerji obnašajo v kliničnem kontekstu.
Avtoritativnost
Zdravstveno pregledal dr. Thomas Klein, s prispevki dr. Sarah Mitchell in prof. dr. Hansa Webra.
Zanesljivost
Interpretacija na podlagi dokazov z jasnimi nadaljnjimi potmi za zmanjšanje alarmiranja.





Zdravstvena omejitev odgovornosti
Ta članek je namenjen izobraževalnim namenom in ne predstavlja medicinskega nasveta. Za odločitve o diagnozi in zdravljenju se vedno posvetujte z usposobljenim izvajalcem zdravstvenih storitev.
Objavljeno · Obrnite se na uredniško ekipo
Izdala družba Kantesti Ltd, registrirana v Angliji in Walesu, matična št. 17090423, London, Združeno kraljestvo.
