PD-L1 scores describe staining in a tissue sample—not your personal chance of treatment success. The scoring method, cancer diagnosis, and proposed drug combination determine what the result can support.

Гол санаанууд
- PD-L1 test results measure protein staining in cancer tissue; they are not routine blood test results or a cancer screening test.
- TPS is the percentage of viable tumor cells with qualifying membrane staining, reported from 0% to 100%.
- CPS counts qualifying PD-L1-positive tumor cells, lymphocytes, and macrophages, divides by viable tumor cells, and multiplies by 100; the reported score is capped at 100.
- Different scores cannot be converted: TPS 10% could accompany CPS 10, CPS 25, or another value depending on immune-cell staining.
- Thresholds such as TPS 1%, TPS 50%, CPS 1, and CPS 10 apply to particular cancer and treatment settings—not every immunotherapy.
- Эерэг үр дүн may support a treatment choice but do not guarantee benefit; a score of 50 is not a 50% response probability.
- Сөрөг үр дүн do not always exclude immunotherapy because some combinations and biomarker-defined treatments do not require PD-L1 positivity.
- Sample adequacy matters: several commonly used scoring protocols require at least 100 viable tumor cells, but the laboratory must apply its indication-specific rules.
What do PD-L1 test results actually tell you?
PD-L1 test results describe protein staining in cancer tissue. TPS counts the percentage of stained tumor cells; CPS also includes selected stained immune cells. Neither score alone decides treatment: cancer type, stage, assay, and regimen determine the relevant cutoff, and positive or negative results do not guarantee benefit or exclusion.
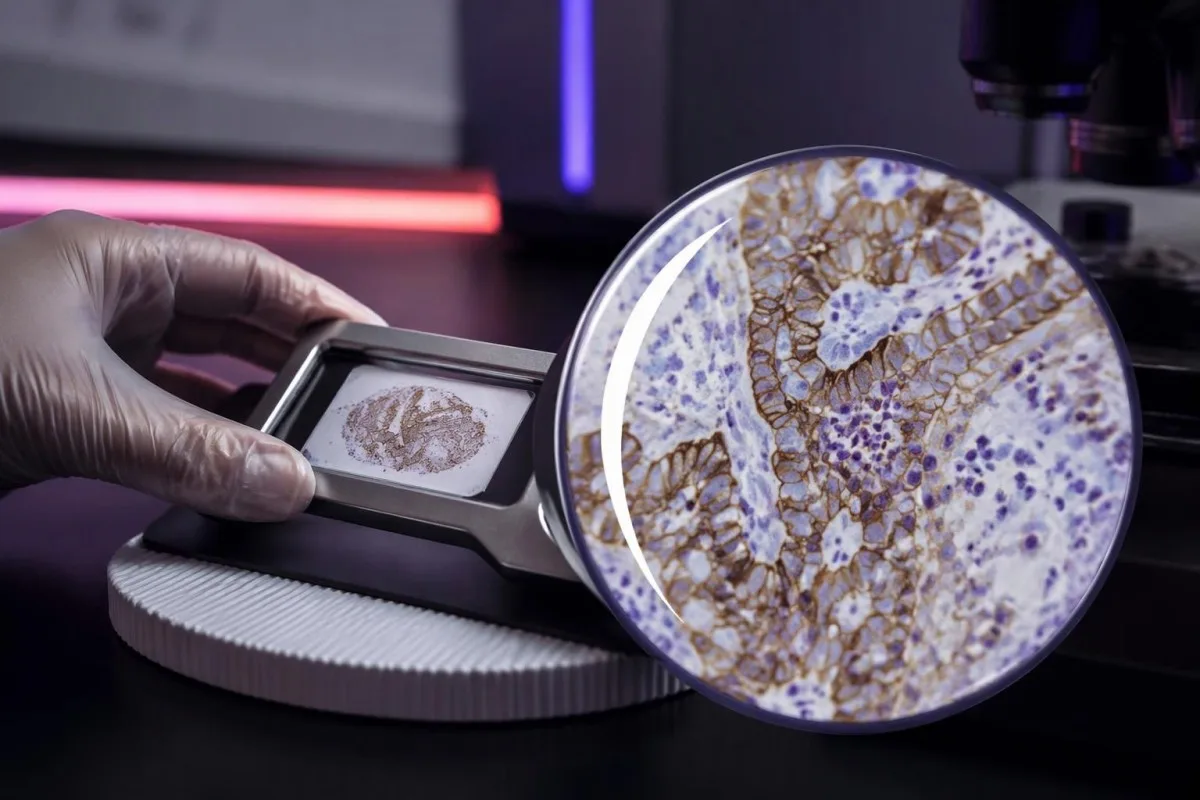
PD-L1, or programmed death-ligand 1, can bind the PD-1 receptor on immune cells and reduce their activity. Drugs targeting this interaction can restore anticancer immune activity, but measuring 1 protein does not capture every factor that determines whether immune cells recognize and control a cancer.
A tissue PD-L1 result is usually produced by immunohistochemistry, which uses an antibody to reveal protein location in a preserved sample. The reported number describes cells on selected tissue sections—not every cancer cell throughout the body—and 2 samples from different sites can produce different results.
Кантести бол AI цусны шинжилгээний анализатор, not a substitute for tissue pathology or an oncology treatment decision. Our байгууллага ба клиник хамрах хүрээ distinguish educational support for laboratory results from decisions requiring the original pathology report, imaging, and the proposed treatment regimen together.
Start with 4 details before interpreting the number: the cancer diagnosis, whether the score is CPS or TPS, the assay used, and the treatment being considered. A report saying only PD-L1 positive leaves a clinically meaningful gap; ask for the scoring method and numerical result.
PD-L1 TPS score meaning: the tumor-cell percentage
Tumor proportion score, эсвэл TPS, is the percentage of viable tumor cells showing qualifying partial or complete membrane PD-L1 staining. TPS ranges from 0% to 100%; immune cells are excluded from its numerator, even when they stain strongly beside the cancer cells.
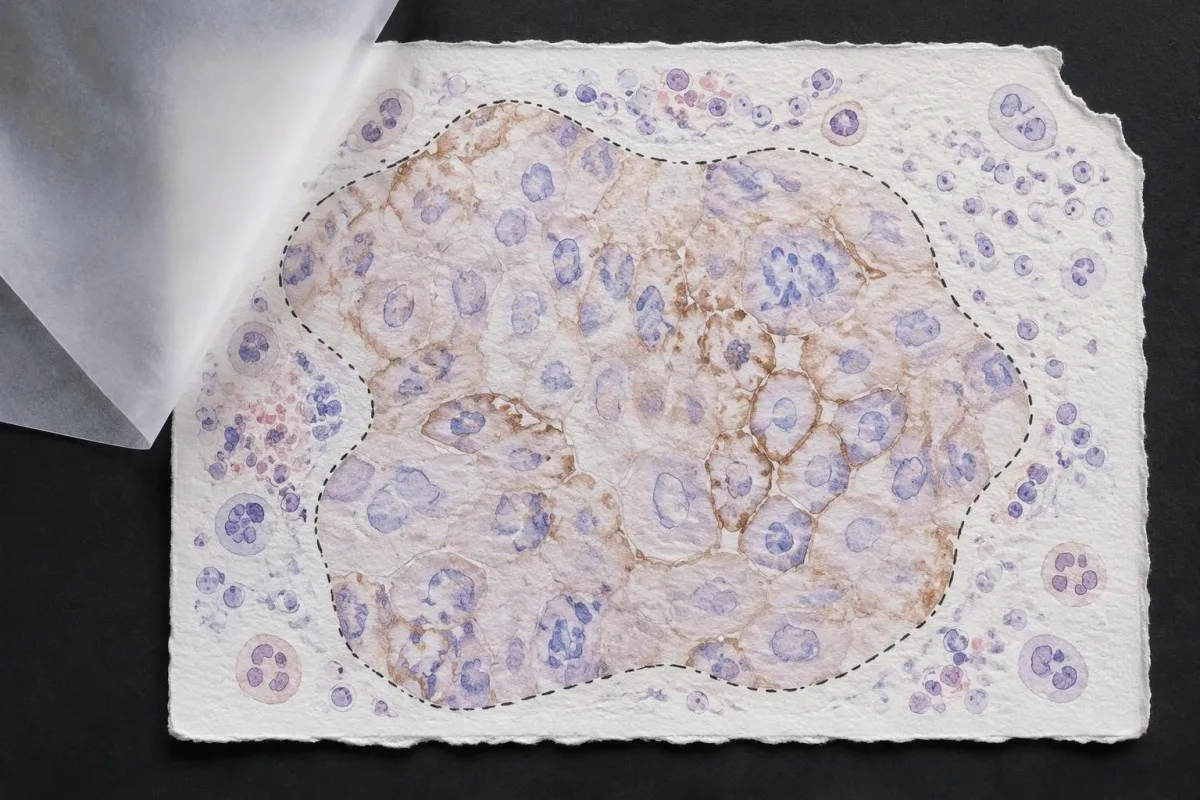
TPS = PD-L1-positive viable tumor cells ÷ all viable tumor cells × 100%. In a hypothetical tissue field containing 200 viable tumor cells, 80 qualifying positive cells produce TPS 40%; nearby stained lymphocytes do not change that calculation, although they might affect a different scoring system.
Membrane location matters more than visual darkness alone. For commonly used TPS methods, weak qualifying membrane staining can count, whereas staining limited to tumor-cell cytoplasm does not establish a positive tumor cell; TPS 1% therefore describes the fraction of qualifying cells, not a required intensity grade.
Cutoffs such as TPS 1% болон TPS 50% were used to define populations in particular lung-cancer trials and treatment pathways. They are not boundaries between harmless and dangerous cancer, and crossing 50% does not create an abrupt biological switch from treatment resistance to guaranteed sensitivity.
Read the exact reporting format: TPS <1%, TPS 1–49%, and TPS ≥50% provide different detail from a single positive flag. Our explanation of чанарын болон тоон үр дүн covers why a category cannot replace a number, although PD-L1 uses tissue-specific—not blood-reference-range—rules.
PD-L1 CPS score meaning: why immune cells count
Combined positive score, эсвэл CPS, includes qualifying PD-L1-positive tumor cells, lymphocytes, and macrophages. CPS divides their combined count by the number of viable tumor cells and multiplies by 100; the denominator does not become all cells simply because immune cells enter the numerator.

CPS = positive tumor cells plus qualifying positive lymphocytes and macrophages ÷ viable tumor cells × 100. In a hypothetical sample with 500 viable tumor cells, 50 positive tumor cells, and 75 qualifying positive immune cells, CPS is 25; the tumor-cell-only TPS would be 10%.
The reported CPS is capped at 100, even if the uncapped arithmetic would exceed 100 because many qualifying immune cells surround relatively few tumor cells. CPS is a unitless score, not a percentage of all cells, a blood concentration, or a probability that immunotherapy will work.
Not every stained immune cell belongs in the CPS count. The pathologist applies the assay manual's rules for eligible lymphocytes and macrophages associated with the tumor; neutrophils, unrelated inflammatory areas, and nonviable tissue are not simply added because a slide contains visible staining.
A CPS of 20 can arise from more than 1 cellular pattern: abundant tumor-cell staining, substantial immune-cell staining, or both. This denominator issue resembles the distinction between cell counts and percentages, but a circulating monocyte count cannot supply the tissue information needed to calculate CPS.
Why CPS and TPS cannot be substituted or converted
CPS and TPS are not interchangeable because they count different cells and were validated in different treatment settings. A TPS of 10% cannot be converted reliably into CPS 10, and a CPS of 20 does not establish that 20% of tumor cells stain.

Consider 2 hypothetical specimens with 500 viable tumor cells and 50 positive tumor cells each. The first has no qualifying positive immune cells and gives TPS 10% with CPS 10; the second contains 75 qualifying positive immune cells and gives the same TPS 10% with CPS 25.
The reverse inference fails too. A hypothetical CPS 20 could result from 20 positive tumor cells among 100 tumor cells, or from 5 positive tumor cells plus 15 qualifying positive immune cells; those examples have TPS 20% and TPS 5%, respectively, despite identical CPS values.
Ан immune-cell score, sometimes abbreviated IC, is another system rather than a third spelling of CPS. Some IC methods measure the proportion of tumor area occupied by stained immune cells, so an IC result of 1% must be interpreted using its own assay and indication—not a TPS threshold.
Kantesti's educational explanation should preserve all 3 scoring labels rather than flatten them into positive or negative. When using AI report explanations safely, check that the original score, assay, and specimen remain visible; an AI-generated conversion without the underlying tissue counts is not clinically dependable.
Which pathology report details matter beyond the score?
A usable PD-L1 report should identify the specimen, assay, scoring method, numerical result, and adequacy assessment. Several commonly used protocols require at least 100 viable tumor cells, but minimum counts and acceptable specimen types depend on the particular test and cancer indication.
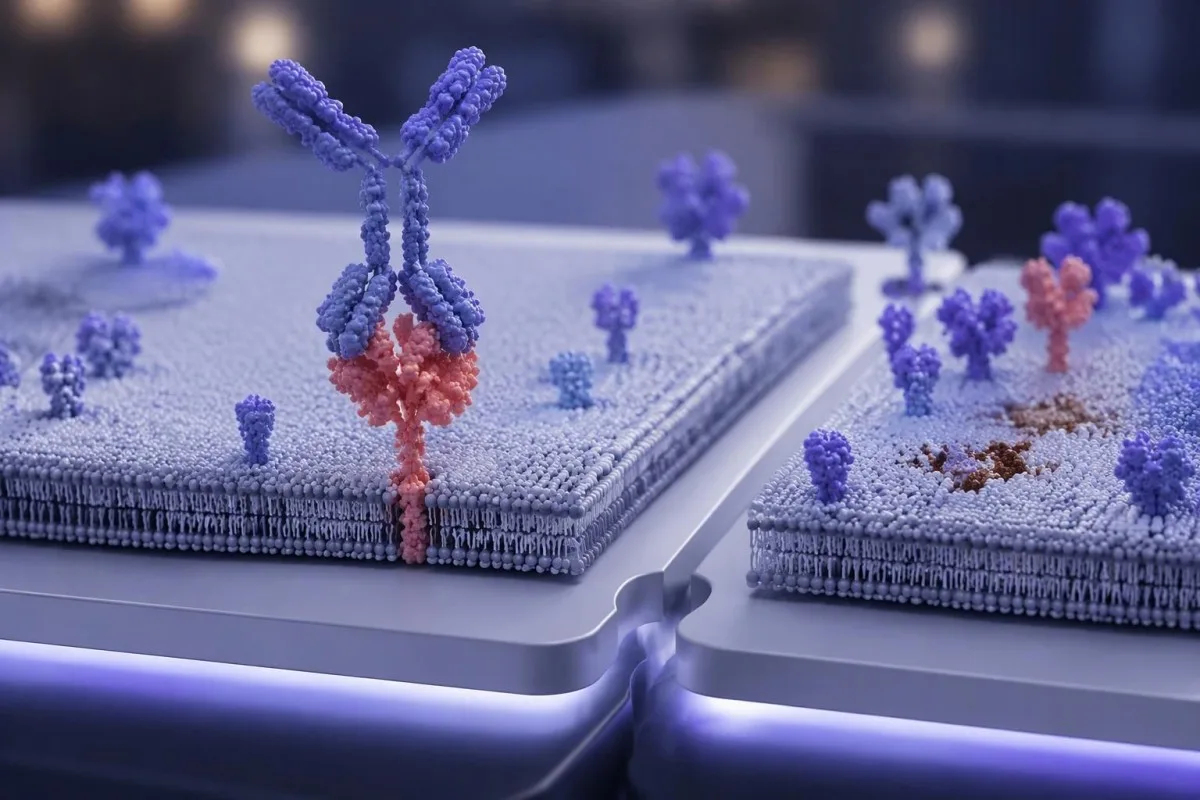
Antibody identifiers such as 22C3, 28-8, SP263, and SP142 describe different testing assays or antibody clones, not different PD-L1 proteins. Some assays show substantial agreement in selected settings, but laboratories should not assume universal equivalence across tumor types, scoring methods, immune-cell assessments, and treatment requirements.
The specimen date and site can change the interpretation of 1 reported number. A small primary-site sample taken before treatment may not represent a later metastatic deposit; ask whether the report describes the current treatment-setting specimen or archived tissue that the oncology team considers suitable.
Insufficient tissue is not PD-L1 negative. A sample with too few viable tumor cells, failed controls, extensive tissue change, or unsuitable processing may be unreportable; the practical next step is laboratory clarification, additional sections, or another suitable specimen—not assigning TPS 0% or CPS 0.
Comparisons between 2 reports need more than matching dates. Our test timing and comparability guide explains the general problem of comparing unlike measurements; for PD-L1, the extra checks are anatomical site, prior treatment, fixation, tissue adequacy, assay, and scoring system.
How does cancer type change the meaning of positivity?
PD-L1 positivity is indication-specific, not a universal diagnosis. TPS thresholds such as 1% or 50% are familiar in non-small-cell lung cancer, while CPS thresholds such as 1, 5, or 10 appear in selected other cancer settings; the drug, stage, and regimen must accompany the cutoff.

For recurrent or metastatic head-and-neck squamous-cell carcinoma, KEYNOTE-048 evaluated CPS-defined populations. Pembrolizumab alone improved median overall survival in the CPS ≥20 group to 14.9 months versus 10.7 months with the comparator regimen, showing why a CPS threshold cannot be borrowed from a lung-cancer TPS report (Burtness et al., 2019).
Selected established pembrolizumab pathways use CPS ≥10 for unresectable locally advanced or metastatic triple-negative breast cancer with chemotherapy, and CPS ≥1 for certain persistent, recurrent, or metastatic cervical-cancer regimens. Those examples do not establish eligibility for every earlier-stage setting, drug combination, country, or funding pathway.
Gastric and gastroesophageal-junction cancers require particular care because treatment selection may also involve HER2 болон MSI/MMR, with PD-L1 requirements differing across regimens and jurisdictions. A serum marker described in our CA 72-4 interpretation guide cannot replace the tissue biomarker panel or define CPS.
Cancer diagnosis and treatment selection are 2 separate steps. Our persistent cough assessment guide addresses when lung symptoms need investigation; once cancer is confirmed, ask the oncology team to match the PD-L1 result to the current local product information and clinical pathway.
Why the treatment regimen matters as much as the cutoff
Immunotherapy alone and immunotherapy combinations can have different PD-L1 requirements. A TPS below 1% may rule out one PD-L1-selected monotherapy pathway without ruling out an appropriate chemotherapy–immunotherapy combination; these are different clinical decisions, not contradictory interpretations of the same result.

KEYNOTE-024 enrolled previously untreated advanced non-small-cell lung cancer with TPS ≥50% and no sensitizing EGFR mutation or ALK rearrangement. Median progression-free survival was 10.3 months with pembrolizumab versus 6.0 months with chemotherapy, supporting that specific high-TPS monotherapy setting—not every cancer with a score above 50 (Reck et al., 2016).
, ESR нь ихэвчлэн мэдэгдэхүйц өндөр байдаг бөгөөд заримдаа KEYNOTE-189, pembrolizumab plus pemetrexed and platinum chemotherapy improved outcomes in previously untreated metastatic nonsquamous non-small-cell lung cancer without EGFR or ALK alterations. Twelve-month overall survival was 69.2% versus 49.4%, and benefit was observed across PD-L1 categories, including TPS <1% (Gandhi et al., 2018).
Combination treatment may address rapid disease progression differently from a single agent, but adding drugs also adds toxicity and monitoring needs. If a proposed regimen includes fluorouracil or capecitabine, хими эмчилгээний өмнөх DPYD шинжилгээ concerns treatment safety; it does not measure the PD-L1 pathway or predict the same benefit.
Кантести бол AI цусны шинжилгээний тайлал платформ that helps explain supporting laboratory measurements; it does not select between 1-drug and multidrug cancer regimens. Similarly, UGT1A1 and irinotecan safety address metabolism-related toxicity, illustrating why each biomarker should be matched to the specific medicine under discussion.
Does a positive PD-L1 result guarantee immunotherapy benefit?
A positive PD-L1 result does not guarantee a response. In KEYNOTE-024's selected high-expression lung-cancer population, the objective response rate with pembrolizumab was 44.8%—substantial benefit for many participants, but clearly not a response in every person with TPS ≥50%.
The 44.8% response rate in KEYNOTE-024 describes a trial population under defined conditions, not an individual's calculated chance of success (Reck et al., 2016). Objective response also means measurable tumor shrinkage by trial criteria; stable disease and survival benefit are different outcomes that should not be collapsed into that single percentage.
PD-L1 is only 1 part of a broader immune environment. A cancer can show substantial staining while lacking effective immune-cell access, recognizable targets, or intact antigen presentation; these mechanisms help explain why expression enriches for benefit in some settings without functioning as a deterministic on–off switch.
Higher does not always mean better across different cancers and combinations. A CPS 30 in one disease cannot be ranked against TPS 60% in another, and the same CPS threshold may have different predictive value when used for monotherapy versus a combination that already provides benefit through other mechanisms.
Some melanoma immunotherapy regimens do not require a positive PD-L1 test, so a low score should not be interpreted using lung-cancer monotherapy rules. Our melanoma warning-sign guide addresses recognition and assessment, while treatment benefit must be discussed using disease-specific trial evidence and the person's overall condition.
Can immunotherapy still be offered when PD-L1 is negative?
PD-L1-negative cancers can still have appropriate immunotherapy options. TPS <1% or CPS <1 may exclude a particular PD-L1-selected regimen, but some combinations, earlier-stage pathways, and treatments selected by other biomarkers do not require PD-L1 positivity.
PD-L1-negative should first be translated into the laboratory's actual definition. TPS <1%, CPS <1, and an assay-specific IC-negative category are not identical measurements; an unreportable or inadequate sample is a fourth situation and should not be grouped with a technically valid negative result.
Ан MSI-high or mismatch-repair-deficient cancer may support particular immunotherapy pathways without PD-L1 selection, depending on the disease, stage, prior treatment, and local authorization. Tumor MMR testing and Lynch хам шинжийн генетикийн шинжилгээ answer related but different questions: an abnormal tumor result does not automatically prove an inherited syndrome.
Other genetic findings may point toward targeted treatment or different planning rather than immunotherapy. A result discussed in our BRCA variant interpretation guide does not turn CPS 0 into CPS 10; clinicians combine distinct biomarkers without pretending they measure the same biological feature.
No PD-L1 requirement is not the same as no selection criteria. A regimen can still require a particular histology, stage, treatment history, organ function, or absence of an actionable driver alteration; ask whether 1 negative score changes only the proposed option or the broader treatment plan.
When can sampling or a borderline score justify review?
Sampling variation can change PD-L1 classification, especially near a treatment threshold. A CPS of 9 versus 10, or TPS 0.8% versus 1%, may prompt pathology review when the distinction would change an otherwise suitable treatment—but repeating every result is not automatically useful.

PD-L1 staining can be heterogeneous within 1 tissue block and between primary and metastatic sites. A small tissue examination may miss a highly expressing area or overrepresent it; the pathologist assesses the available viable tissue rather than assuming a single selected field describes the whole cancer.
Pretreatment and post-treatment specimens are not always equivalent. Chemotherapy, radiotherapy, and changes in the immune environment can alter expression, while decalcification of some bone specimens can impair antigen detection; ask whether a lower result reflects biology, processing limitations, or simply a different sampled site.
Borderline results require the actual assay rules, not homemade averaging. If 2 reports show CPS 8 and CPS 12, calculating CPS 10 does not create a newly validated result; the laboratory and oncology team should decide which specimen and assessment are appropriate for the treatment indication.
Kantesti cannot verify viable-cell counts, staining controls, or tissue suitability from a score alone. Our клиник баталгаажуулалт ба хяналт should be read in that limited context; when another tissue procedure is considered, its risks and likely impact on treatment need to be weighed against the uncertainty in the existing result.
Which other biomarkers belong beside PD-L1?
Other biomarkers can take priority over PD-L1, depending on the cancer. In advanced non-small-cell lung cancer, molecular alterations such as EGFR mutations and ALK rearrangements affect treatment planning; in selected other cancers, HER2, MSI/MMR, or additional molecular findings may change the preferred pathway.
A high TPS does not cancel an actionable molecular finding. The pivotal KEYNOTE-024 болон KEYNOTE-189 populations excluded relevant EGFR or ALK alterations, so their results should not be applied unchanged to those groups; treatment sequence also matters because some targeted therapies and checkpoint inhibitors can interact through toxicity.
Tumor mutational burden, often measured in mutations per megabase, is a different biomarker from PD-L1. A threshold such as 10 mutations/Mb has been used in a specific tissue-agnostic treatment context, but assay differences, cancer type, authorization, and clinical setting prevent it from becoming a universal immunotherapy rule.
A liquid molecular test may find circulating tumor DNA, but it does not automatically replace tissue PD-L1 immunohistochemistry. The 2 tests measure different things—genetic material versus protein location within cells—and a negative liquid result may also reflect limited DNA shedding rather than absence of a tumor alteration.
Kantesti AI distinguishes the role of supporting laboratory markers from tissue-based treatment biomarkers in our цусны биомаркерийн лавлах гарын авлага. A blood-cell ratio, LDH level, or serum tumor-marker concentration should not be used to manufacture TPS 50%, estimate CPS 10, or bypass an indicated molecular workup.
What safety checks matter if immunotherapy is considered?
PD-L1 scores predict neither treatment safety nor immune-related toxicity. A TPS of 90% does not make checkpoint treatment safer than TPS 1%; the team assesses medical history, organ function, medications, and the particular regimen separately from the tissue biomarker.
Checkpoint inhibitors can cause immune-related effects involving the thyroid, liver, lungs, bowel, kidneys, heart, and other organs. Baseline testing commonly includes liver chemistry, creatinine, thyroid measurements, and a complete blood count, with monitoring schedules varying by regimen; 1 normal baseline panel does not prevent later toxicity.
New chest pain, palpitations, fainting, or breathlessness during treatment requires prompt assessment because myocarditis, although uncommon, can be serious. Our myocarditis test interpretation guide explains why troponin supports evaluation but cannot determine the cause by itself; severe symptoms warrant emergency care rather than waiting for the next scheduled panel.
Kidney changes need interpretation against the person's own baseline and treatment exposures. A hypothetical creatinine rise from 0.8 to 1.6 mg/dL is a doubling even if the absolute value looks only modestly elevated; our kidney function testing guide explains supporting measurements, not an immunotherapy-specific treatment decision.
Pre-existing autoimmune disease, organ transplantation, ongoing immunosuppression, or previous severe immune-related toxicity can complicate treatment planning even when CPS is 100. Report new persistent diarrhea, worsening cough, jaundice, unusual weakness, or marked thirst promptly; neither a high PD-L1 score nor previously reassuring blood results justify delaying symptom assessment.
What should you ask at your oncology appointment?
Авчрах complete PD-L1 pathology report and ask which exact treatment decision it informs. Four useful starting questions are: Which score was used? Which cutoff applies? Is the specimen adequate? What options remain if the result is below the cutoff?
A hypothetical report reading 22C3, CPS 12, adequate tissue is still incomplete as a treatment answer until the cancer, stage, and regimen are specified. Ask whether CPS ≥10 is relevant to the proposed option, whether other biomarkers are pending, and whether a combination would be considered under different selection rules.
Request explanations of 3 outcomes separately: tumor shrinkage, duration of disease control, and survival. A trial's response rate is not the same as its survival benefit, while median survival is a group midpoint—not an individual deadline—and the balance between rapid control and treatment toxicity may change the preferred regimen.
Кантести бол AI лабораторийн шинжилгээний тайлбар үйлчилгээ for supporting laboratory understanding, not independent immunotherapy eligibility assessment. If blood monitoring is planned, our суурь түвшний шинжилгээний бэлтгэлийн гарын авлага can help organize previous values, units, medication lists, and collection dates so that the oncology team can compare results meaningfully.
Keep tissue scores separate from serial blood monitoring in 2 clearly labeled records. Our эмийн аюулгүй байдлын чиг хандлагын удирдамж explains why changes over time need context; our хариуцлагатай AI-ийн зарчмууд also make clear that automated explanations should not trigger treatment changes without clinical review.
Research publications and the limits of PD-L1 evidence
PD-L1 interpretation should be grounded in cancer-specific trials and validated pathology methods. The 3 clinical references below address high-TPS lung-cancer monotherapy, lung-cancer combination treatment, and CPS-selected head-and-neck treatment; the 2 separate Zenodo publications concern other laboratory topics and do not establish PD-L1 thresholds.
KEYNOTE-024 supports a defined TPS ≥50% advanced lung-cancer population, whereas KEYNOTE-189 supports a particular combination across PD-L1 categories (Reck et al., 2016; Gandhi et al., 2018). Those different study designs explain why evidence for one regimen cannot be substituted for evidence supporting another simply because both drugs affect the same immune pathway.
KEYNOTE-048 assessed CPS-defined recurrent or metastatic head-and-neck cancer populations, including CPS ≥1 and CPS ≥20 groups (Burtness et al., 2019). When reading a trial, check the histology, stage, previous treatment, comparator, and endpoint; a subgroup survival finding does not automatically quantify an individual's chance of measurable shrinkage.
Kantesti's 2 Zenodo publications listed below are educational resources on complement/ANA testing and Nipah-virus diagnostics, not PD-L1 clinical trials or assay-validation studies. The комплемент ба ANA-ийн заавар concerns different laboratory questions, and a DOI identifies a deposited publication without independently establishing clinical validity.
Use the original pathology result and current local treatment information to resolve eligibility—not a generalized positive/negative table or an AI-generated score conversion. Our эмнэлгийн агуулгын стандартууд emphasize source relevance and uncertainty; ask your oncology team to document the 1 specific regimen, applicable threshold, and remaining alternatives.
Түгээмэл асуултууд
PD-L1 эерэг гэдэг нь юу гэсэн үг вэ?
PD-L1 эерэг гэдэг нь эдийн шинжилгээний үр дүн холбогдох нөхцөлд TPS ≥1% эсвэл CPS ≥1 зэрэг тогтоосон шинжилгээ болон үнэлгээний босгыг хангасан гэсэн үг. Босго нь хавдрын төрөл, эмчилгээний дэглэм болон тухайн орны эмчилгээний шаардлагаас хамаарна. Эерэг гарсан нь дархлаа эмчилгээ үр дүнтэй байна гэдгийг нотлохгүй бөгөөд тайланд зөвхөн эерэг гэсэн тэмдэглэгээ бус, тоон үнэлгээг нь тусгасан байх ёстой.
CPS болон TPS хоёрын ялгаа юу вэ?
TPS нь PD-L1-ийн шаардлага хангасан мембраны будагдалттай амьд хавдрын эсийн хувийг хэмждэг бол CPS нь шаардлага хангасан эерэг хавдрын эс, лимфоцит болон макрофагийн тоог амьд хавдрын эсийн тоонд хувааж, 100-аар үржүүлэн тооцдог. TPS-ийг 0%-аас 100% хүртэл илэрхийлдэг бөгөөд мэдээлэх CPS-ийн дээд хязгаар 100 байна. CPS нь TPS-д тооцогддоггүй дархлааны эсийн будагдалтаас хамаардаг тул эдгээр оноог хооронд нь хөрвүүлэх боломжгүй.
CPS 10 гэдэг нь дархлаа эмчилгээ үр дүнтэй болох 10% магадлалтай гэсэн үг үү?
CPS 10 гэдэг нь дархлаа эмчилгээнд хариу өгөх магадлал 10% гэсэн үг биш. CPS нь амьд хавдрын эсүүдийг хуваарь болгон тооцдог эдийн будалтын үзүүлэлт болохоос эмчилгээнд хариу өгөх хувь хүний магадлал биш юм. CPS ≥10 байх нь хавдрын тодорхой төрлүүдэд зориулсан зарим эмчилгээний горимыг сонгох үндэслэл болдог ч эмчилгээний үр өгөөжийг таамаглахын тулд хавдрын онош, үе шат, бусад биомаркер болон санал болгож буй эмчилгээний үр нөлөөг нотолсон баримтыг мөн харгалзах шаардлагатай.
PD-L1 сөрөг бол дархлаа эмчилгээ хийлгэж болох уу?
PD-L1 сөрөг гарсан нь дархлаа эмчилгээний бүх сонголтыг үгүйсгэхгүй. TPS 1%-иас бага байсан ч хими эмчилгээ–дархлаа эмчилгээний зарим хослол болон биомаркерын шинжилгээний үр дүнд тулгуурлан сонгодог бусад эмчилгээний хувилбарт PD-L1 эерэг байх шаардлагагүй. Эмчилгээнд хамрагдах боломж нь хавдрын төрөл, үе шат, молекулын шинжилгээний үр дүн, өмнөх эмчилгээний түүх, өвчтөний биеийн байдал болон тухайн бүс нутгийн зөвшөөрлөөс хамаарна; эдийн сорьц хангалтгүй бол шинжилгээний хариуг хүчинтэй сөрөг гэж үзэж болохгүй.
TPS 50%-ийг PD-L1-ийн өндөр түвшин гэж үздэг үү?
TPS ≥50% нь уушгины жижиг бус эсийн хорт хавдрын зарим нөхцөлд PD-L1-ийн өндөр илэрхийлэл гэж түгээмэл тодорхойлогддог. Энэ босгыг мэдрэгжүүлэгч EGFR мутаци эсвэл ALK-ийн дахин зохион байгуулалтгүй, уушгины хорт хавдрын тодорхой бүлгийн өвчтөнүүдийг судалсан KEYNOTE-024 судалгаанд ашигласан. TPS 50% нь CPS 50-тай дүйцэхгүй бөгөөд бүх төрлийн хорт хавдар, үе шат, дархлаа эмчилгээний дэглэмд хамаарах нийтлэг босго биш юм.
Is PD-L1 a blood test, and should it be repeated?
Clinical PD-L1 scoring for CPS and TPS usually uses preserved cancer tissue examined by immunohistochemistry, not a routine blood sample. Repeat assessment may help if tissue is inadequate, the result is close to a decision-changing cutoff such as CPS 10, or a different specimen is more suitable. The oncology and pathology teams should decide whether review, additional sections, or another specimen is likely to change care enough to justify the associated effort and procedural risks.
Цусны шинжилгээний хариугаа тайлбарлуулаарай
Лабораторийн тайлангаа байршуулснаар Kantesti-ийн AI биомаркер бүрийг энгийн хэлээр хэдхэн секундэд тайлбарлана. Дэлхий даяар 2 сая гаруй хүн ашигладаг.
Лавлагаа
- Klein, T., Mitchell, S., & Weber, H. (2026). C3 C4 Комплементын цусны шинжилгээ ба ANA титрийн заавар. Kantesti AI-ийн анагаахын судалгаа. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Нипа вирусийн цусны шинжилгээ: эрт илрүүлэлт ба оношилгооны заавар 2026. Kantesti AI-ийн анагаахын судалгаа. DOI
- Reck M et al. (2016). Pembrolizumab versus Chemotherapy for PD-L1–Positive Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Gandhi L et al. (2018). Pembrolizumab plus Chemotherapy in Metastatic Non–Small-Cell Lung Cancer. New England Journal of Medicine. DOI
- Burtness B et al. (2019). Pembrolizumab alone or with chemotherapy versus cetuximab with chemotherapy for recurrent or metastatic squamous cell carcinoma of the head and neck (KEYNOTE-048): a randomised, open-label, phase 3 study. The Lancet. DOI
- 2 сая+Шинжилсэн сорилууд
- 127+Улс орнууд
- 100+Хэлнүүд
Эмнэлгийн багийн тухай


E-E-A-T итгэлийн дохио
Туршлага
Эмчийн удирдлагатай лабораторийн тайлалын ажлын урсгалын клиник хяналт.
Мэргэшсэн байдал
Биомаркерууд клиникийн нөхцөлд хэрхэн ажиллаж/өөрчлөгдөж байгаад чиглэсэн лабораторийн анагаах ухаан.
Эрх мэдэл
Доктор Томас Кляйн эмнэлзүйн хувьд хянасан бөгөөд доктор Сара Митчелл, профессор доктор Ханс Вебер нар хувь нэмэр оруулсан.
Найдвартай байдал
Сэрэмжлүүлгийг бууруулахын тулд тодорхой дараагийн алхамтай, нотолгоонд суурилсан тайлал.





Эмнэлгийн хариуцлагаас татгалзах мэдэгдэл
Энэ нийтлэл зөвхөн боловсролын зорилготой бөгөөд эмнэлгийн зөвлөгөө биш болно. Оношилгоо, эмчилгээний шийдвэр гаргахдаа мэргэшсэн эрүүл мэндийн үйлчилгээ үзүүлэгчтэй заавал зөвлөлдөнө.
Хэвлэгдсэн · Редакцын багтай холбогдох
Kantesti Ltd компани Англи, Уэльст бүртгэлтэй, компанийн дугаар. 17090423, Лондон, Нэгдсэн Хаант Улс.
