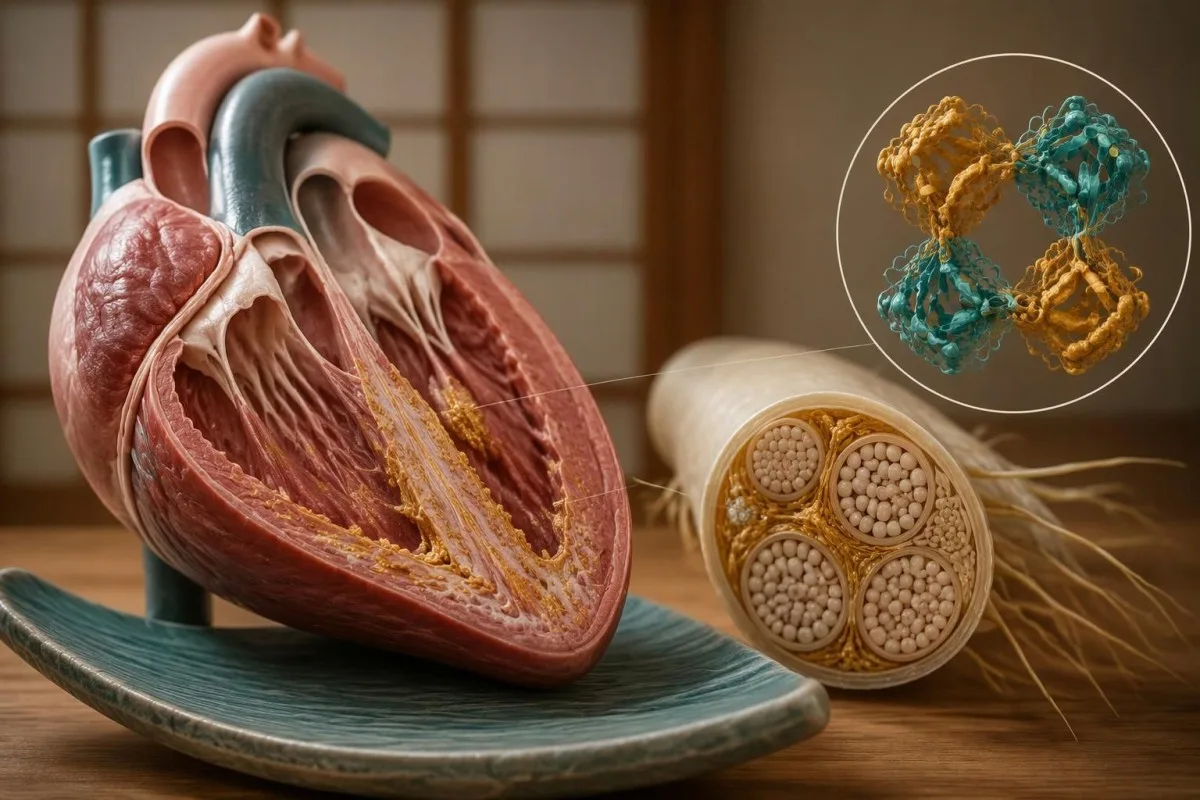
يُثبت وجود متغير مُسبِّب للمرض في TTR استعدادًا وراثيًا للداء النشواني ATTR الوراثي، وليس دليلًا على وجود مرض نشط. ولا يُثبت المتغير غير المؤكد هذا الاستعداد؛ إذ تتطلب الأعراض تقييمًا منفصلًا من اختصاصي، ويتطور داء ATTR من النوع البري دون وجود متغير موروث مُسبِّب للمرض في TTR.

أهم النقاط
- متغير ممرض في TTR يعني استعدادًا وراثيًا؛ ولا تكفي نتيجة جينية واحدة وحدها لإثبات وجود داء نشواني مصحوب بأعراض.
- خطر الوراثة يبلغ عادةً 50% لكل طفل لشخص لديه نسخة واحدة من TTR مُسبِّبة للمرض، بصرف النظر عن جنس الطفل.
- النتائج غير المؤكدة تندرج ضمن فئة واحدة من 5 فئات معيارية لتصنيف المتغيرات؛ ولا ينبغي أن يحدد متغير مجهول الدلالة (VUS) الفحوص التنبؤية أو العلاج بمفرده.
- أسماء المتغيرات قد تختلف بحسب 22 موضعًا في الأحماض الأمينية: يصف كل من p.Val50Met والاسم التاريخي Val30Met الاستبدال نفسه.
- داء ATTR من النوع البري يشمل ترانستيريتين دون تحديد متغير TTR مُسبِّب للمرض؛ ولا يمكن التمييز بشكل موثوق بين الترسبات الوراثية وتلك من النمط البري بالأعراض وحدها.
- التأكيد القلبي قد يستخدم التقاطًا بمقتفيات العظام من الدرجة 2 أو 3، ولكن فقط ضمن مسار التصوير المناسب وبعد تقييم البروتينات أحادية النسيلة.
- مراقبة حاملي المتغيرات غالبًا ما تشمل تقييمًا سنويًا، مع تحديد التوقيت بشكل فردي؛ ويُعدّ ما يقارب 10 سنوات قبل بدء المرض المتوقع لدى أفراد الأسرة وسيلةً للتخطيط، لا موعدًا نهائيًا بيولوجيًا.
- أعراض الطوارئ مثل ضيق النفس الشديد أو الانهيار أو ألم الصدر، تستلزم رعاية فورية—لا الانتظار حتى موعد المراقبة التالي بعد 6–12 شهرًا.
ما المعنى الفعلي لمتغير TTR؟
A متغير TTR مُمرِض أو مرجح الإمراض يحدد الاستعداد الوراثي لداء النشواني ATTR الوراثي، لكنه لا يُظهر بحد ذاته وجود ترسب نشواني نشط أو تلف في الأعضاء. إن متغير ذو أهمية غير مؤكدة, ، أو متغيرًا مجهول الدلالة (VUS)، لا تتوفر أدلة كافية للاستنتاج نفسه؛ فهما سؤالان منفصلان يتطلبان قرارين سريريين منفصلين.

TTR هو الجين الذي يشفّر الترانستيريتين، وهو بروتين ناقل يُنتَج أساسًا في الكبد؛ ويتكون شكله المعتاد في الدورة الدموية من 4 وحدات فرعية بروتينية. تجعل بعض المتغيرات هذا التركيب أقل استقرارًا، ما يسمح بتراكم البروتين سيئ الطي على هيئة نشواني، ولا سيما في الأعصاب أو القلب.
على سبيل المثال، تخيّل شخصًا يبلغ 46 عامًا كشف اختباره الجيني السريري عن متغير TTR معروف بأنه مسبب للمرض، لكن فحصه العصبي وتقييم قلبه لا يُظهران أي مرض. وقد يكون الوصف المناسب هو حامل متغير بلا أعراض, ، وليس شخصًا مصابًا بداء نشواني مصحوب بأعراض؛ إذ تعتمد أهلية العلاج والمتابعة على نتائج إضافية.
Kantesti هو محلل لاختبارات الدم بالذكاء الاصطناعي يساعد في شرح نتائج التحاليل المخبرية المصاحبة، مع إبقاء الاستعداد الوراثي منفصلًا عن تأكيد المرض العضوي. معلومات عن منظمتنا توضح سياق خدمتنا؛ فلا لوحة التحاليل المخبرية الروتينية ولا الشرح بالذكاء الاصطناعي يمكن أن يحل محل هذين التقييمين التخصصيين.
كيف تختلف نتائج TTR الممرضة عن متغير مجهول الدلالة (VUS)؟
النتائج الممرِضة و مُمْرِض على الأرجح تستند إلى أدلة تدعم دورها في التسبب بالمرض؛ أما VUS فيفتقر إلى أدلة كافية لتصنيفه ضارًا أو غير ضار. تستخدم المختبرات 5 فئات معيارية: ممرِض، ومرجح الإمراض، ومجهول الدلالة، ومرجح الحميدة، وحميد.

يضع إطار ACMG/AMP لتصنيف المتغيرات التسلسلية النتائج المرجح إمراضها فوق عتبة ثقة قدرها 90% فيما يتعلق بالإمراضية، لكن هذه النسبة تصف الثقة في التصنيف, ، لا احتمال إصابة الفرد بالأعراض (Richards وآخرون، 2015). شرحنا لـ نتائج اختبارات السرطان الوراثي illustrates the same distinction between a laboratory label and a person's current disease status.
A VUS should not, by itself, trigger disease-specific treatment or routine predictive testing of healthy relatives. Specialists may instead investigate whether the finding tracks with confirmed disease in a family—a segregation study involving 2 or more informative relatives when available—which is different from declaring those relatives genetically affected.
Classification can change when additional family, functional, or population evidence becomes available. Ask who will handle recontact, whether review in 12–24 months would be useful, and whether another laboratory has classified the exact same variant differently; our guide to common genetic variant misconceptions explains why the word mutation is not automatically a diagnosis.
لماذا قد يكون للمتغير نفسه في TTR اسمان؟
The same TTR variant can have modern and historical protein names because modern numbering includes a 22-amino-acid signal peptide. For example, p.Val50Met is the variant historically called Val30Met، و p.Val142Ile is the variant historically called Val122Ile.

A complete report ideally supplies the gene, transcript reference, DNA-level notation, protein-level notation, zygosity, and classification—not simply a variant nickname. Because a TTR precursor contains 149 amino acids and the mature protein contains 127, comparing reports without noticing the numbering convention can create an apparent disagreement where none exists.
p.Thr80Ala, historically Thr60Ala, can produce a mixed cardiac and neurological phenotype, whereas p.Val142Ile is often associated with predominantly cardiac disease. These are tendencies rather than guarantees: 2 relatives with the same variant may differ in age at onset, affected organs, and severity.
For a hypothetical family, a parent's report saying Val122Ile and an adult child's report saying p.Val142Ile should prompt exact-notation comparison before anyone concludes that there are 2 different familial variants. Similar nomenclature issues arise in enzyme and genetic testing; bring the original reports rather than relying on a handwritten abbreviation.
هل يعني خطر وراثة 50% خطر الإصابة بالمرض بنسبة 50%؟
A 50% inheritance risk is not a 50% risk of symptomatic disease. Hereditary ATTR usually follows autosomal dominant inheritance: a person with 1 disease-causing TTR copy has a 50% chance of passing that copy to each child, but disease expression depends on age-related penetrance and other factors.

Each pregnancy is an independent event; with 2 children, the theoretical probabilities are 25% for neither inheriting the variant, 50% for exactly one, and 25% for both. Those calculations assume one heterozygous parent and describe inheritance only—they do not predict whether or when either child will become ill.
Penetrance means the proportion of variant carriers who develop disease by a stated age, and it varies across TTR variants and populations. The often-quoted 3–4% frequency of p.Val142Ile in some populations of African ancestry is a variant-frequency estimate, not a universal estimate of amyloidosis prevalence or an individual's lifetime disease risk.
An apparently unaffected parent aged 75 can still have transmitted a pathogenic variant, while a negative family history may reflect late onset, small families, or previously unrecognized disease. Our discussion of genetic susceptibility and kidney risk offers a useful comparison, although APOL1 risk architecture should not be substituted for TTR inheritance.
كيف يختلف داء ATTR الوراثي عن داء ATTR من النوع البري؟
Hereditary ATTR involves a disease-causing TTR variant; wild-type ATTR involves amyloid formed from transthyretin without an identified disease-causing variant. Both can affect the heart, so neither age nor a cardiac scan alone reliably distinguishes these 2 forms.
TTR sequencing is recommended after ATTR cardiomyopathy is established, including in older adults, because hereditary disease can first become apparent after age 70. The ESC position statement emphasizes genetic counseling and testing to distinguish variant ATTR from wild-type ATTR, rather than assuming that an older patient's disease cannot be inherited (Garcia-Pavia et al., 2021).
A negative result for a known family variant removes that particular inherited susceptibility, but it does not guarantee that the person will never develop wild-type ATTR or another heart condition. Conversely, a VUS does not automatically convert a confirmed ATTR diagnosis into hereditary ATTR; the laboratory classification and amyloid diagnosis still need reconciliation.
ATTR is also different from الداء النشواني AL, caused by immunoglobulin light chains, and الداء النشواني AA, associated with prolonged inflammatory activity. These are at least 3 distinct amyloid types with different investigations and treatment pathways; an elevated serum amyloid A result does not diagnose TTR-related disease.
أي أعراض الداء النشواني الوراثي تستلزم التقييم؟
Hereditary amyloidosis symptoms may include progressive numbness or burning feet, weakness, altered bowel function, dizziness on standing, breathlessness, or ankle swelling. These findings are nonspecific, but involvement of 2 systems—such as neuropathy plus unexplained cardiac thickening—raises more concern than either finding alone.
Bilateral carpal tunnel syndrome, particularly when it precedes cardiac symptoms by several years, can be an ATTR clue but is far more commonly explained by other causes. Document whether 1 or both wrists are affected and when symptoms began; our guide to carpal tunnel finger patterns helps distinguish a local median-nerve pattern from broader neuropathy.
انخفاض ضغط الدم الانتصابي commonly means a sustained fall of at least 20 mmHg systolic or 10 mmHg diastolic within 3 minutes of standing. Amyloid-related autonomic dysfunction is one possible cause, but dehydration and medicines are common alternatives; it is not interchangeable with the heart-rate pattern discussed in POTS diagnostic testing.
Consider a hypothetical 58-year-old carrier who develops numb feet, unintentional weight loss, and new difficulty climbing stairs over 6 months: that combination warrants prompt specialist review rather than waiting for annual screening. Sudden weakness, severe breathlessness, chest pain, or collapse requires urgent care because immediately treatable problems must be assessed before attributing symptoms to ATTR.
ما الفحوص التي تثبت وجود داء نشواني ATTR نشط؟
Active ATTR amyloidosis requires evidence of amyloid disease, not just a genetic result. In the appropriate cardiac setting, grade 2 or 3 uptake on a validated bone-tracer scan can establish ATTR cardiomyopathy without biopsy only when monoclonal protein testing is negative and imaging confirms uptake within heart muscle.

The monoclonal screen includes serum free light chains plus serum and urine immunofixation; serum protein electrophoresis alone is insufficient. Gillmore et al.'s 2016 Circulation study evaluated 1,217 patients and established the nonbiopsy cardiac approach under defined conditions; our guide to immunofixation bands and follow-up explains why detecting a monoclonal protein changes the next step.
A monoclonal protein does not prove AL amyloidosis, because an unrelated monoclonal gammopathy can coexist with ATTR, especially in older adults. However, it prevents clinicians from using the simplified scan-only ATTR pathway; interpreting the نسبة السلسلة الخفيفة الحرة also requires kidney-function context and, where available, assay-specific renal reference intervals.
When tissue examination is needed, Congo red staining establishes amyloid, while reliable protein typing—often mass spectrometry—identifies its source. A negative abdominal fat sample does not exclude ATTR, and grade 1 cardiac uptake is not the same as the grade 2–3 diagnostic criterion; neuropathy-predominant disease may require a different combination of neurological and tissue investigations.
ما الموضوعات التي ينبغي أن تتناولها الاستشارة الوراثية بشأن TTR؟
TTR genetic counseling should explain the exact variant, classification, inheritance, limitations of risk prediction, and consequences for relatives before testing or major decisions. For most heterozygous families, the 50% transmission probability is straightforward; predicting age at onset and organ involvement is much less precise.

Counseling distinguishes diagnostic testing in someone with suspected disease from predictive testing in an unaffected relative. A person considering predictive testing should have time to discuss emotional readiness and the right not to know, similar to the consent principles described in predictive neurological genetic testing, although TTR penetrance differs substantially.
Reproductive discussions can include natural conception, prenatal diagnosis, and preimplantation genetic testing where available and legally permitted. Because a 50% transmission risk does not specify future severity, these conversations should be nondirective; confirm the familial pathogenic variant in a clinical laboratory before using it for reproductive testing or other consequential decisions.
Kantesti's explanations of الخصوصية وبياناتك help readers consider what they share, but genetic information has implications beyond ordinary laboratory values. Before adding reports for 2 or more relatives to a shared account, obtain each person's permission and ask the genetics team about local insurance rules, record access, and secure family communication.
أي الأقارب ينبغي أن يفكروا في إجراء اختبار موجّه لـTTR؟
Adult relatives at risk of a confirmed familial pathogenic or likely pathogenic TTR variant should be offered genetic counseling and the option of targeted testing. Each child of a heterozygous carrier has a 50% inheritance probability; a sibling's risk depends on whether a parent carries the variant.

Start with the relative who has confirmed disease whenever possible, then use that person's exact variant to guide cascade testing. Testing all relatives with a broad panel before establishing the family finding may generate additional VUS results; this differs from the recessive inheritance questions in SMA carrier screening, where 2 gene copies have a different meaning.
Predictive testing for adult-onset TTR disease is generally deferred in children younger than 18 when the result would not change childhood care, preserving their future choice. A child with unexplained relevant symptoms needs clinical assessment rather than automatic dismissal; any exceptional testing decision should involve pediatric and genetics specialists, not a routine family screening package.
For example, a 34-year-old who tests negative for a clinically confirmed familial p.Val50Met variant generally does not need surveillance specifically for that family variant. A symptomatic relative still needs assessment for other causes, and a 1-variant consumer screening result cannot substitute for a validated familial test if the relevant variant was not actually examined.
كيف تجري متابعة حاملي متغيرات TTR من دون أعراض؟
Asymptomatic pathogenic TTR carriers need individualized surveillance, commonly involving annual clinical review, rather than an automatic amyloidosis diagnosis or preventive prescription. Many expert pathways begin structured assessment approximately 10 years before predicted disease onset, but variant-specific evidence and family history may justify earlier or different monitoring.
Baseline assessment may include neurological examination, autonomic history, ECG, echocardiography, kidney function, and cardiac biomarkers; additional tests depend on the variant and symptoms. The ESC position statement outlines regular carrier follow-up (Garcia-Pavia et al., 2021), but a 6–12-month interval should be individualized, especially when new findings appear or expected onset approaches.
A parent's onset at 62 is not a countdown showing that a child's disease will begin at 62, and a normal baseline does not eliminate later risk. Kantesti AI can help explain the difference between a single value and a meaningful laboratory timeline, but specialist decisions also require examination and imaging that routine blood interpretation cannot supply.
Imagine NT-proBNP increasing from 180 to 620 pg/mL while eGFR falls from 62 to 43 mL/min/1.73 m²: cardiac change deserves assessment, but reduced kidney clearance can contribute to the rise. Review intercurrent illness, rhythm, and medicines before interpreting progression; our دليل نسبة وظائف الكلى explains why renal context belongs beside cardiac trends.
ما الذي تكشفه اختبارات الدم، وما الذي قد يفوتها؟
Routine blood tests cannot confirm or exclude hereditary ATTR amyloidosis. NT-proBNP, troponin, kidney function, and urine protein can help assess organ involvement or alternatives, but a normal set of results—even across 2 visits—does not establish that a pathogenic TTR carrier will remain disease-free.
التروبونين must be interpreted against the assay's 99th-percentile upper reference limit, and NT-proBNP varies with age, kidney function, atrial fibrillation, and body size. A TTR or prealbumin concentration such as 25 mg/dL does not identify a TTR gene mutation or prove amyloid deposition; the test measures circulating protein concentration rather than its genetic sequence.
Neuropathy assessment should also look for treatable alternatives, including diabetes, vitamin B12 deficiency, thyroid disease, and medication effects. A hypothetical B12 result of 210 pg/mL may need additional assessment according to the laboratory and symptoms; our discussion of نتائج فيتامين B12 الحدّية explains why a competing diagnosis should not be overlooked simply because a TTR variant exists.
Kantesti is an AI blood test interpretation platform that explains accompanying laboratory values without treating 1 protein result as an amyloidosis diagnosis. Our دليل تفسير بروتين المصل helps separate transport proteins and immunoglobulin findings; neither an ordinary protein panel nor a family-risk feature replaces clinical TTR testing and amyloid typing.
هل تعني نتيجة TTR الوراثية الإيجابية وجوب بدء العلاج؟
A positive TTR genetic result alone is not a standard indication for disease-modifying treatment. Specialists consider confirmed ATTR disease, the affected organs, functional status, and local approvals; the 2 main medication strategies are stabilizing transthyretin and reducing production of transthyretin.

TTR stabilizers aim to reduce dissociation of the 4-subunit protein, while TTR-lowering therapies reduce production, mainly in the liver. Neither approach edits the inherited DNA, so family transmission considerations remain after treatment; eligibility differs between cardiomyopathy, polyneuropathy, and mixed disease, as do approval and reimbursement rules across countries.
Monitoring depends on the chosen medicine rather than the genetic label alone: some regimens require attention to platelets, kidney function, or vitamin A handling. If vitamin A supplementation is advised during a TTR-lowering regimen, use the prescribed allowance rather than escalating the dose because a laboratory result looks low; 1 abnormal value does not establish a safe replacement dose.
Kantesti does not select amyloidosis medication or establish treatment eligibility from uploaded laboratory results; our التحقق التقني والإشراف describe a different task from specialist prescribing. For an asymptomatic carrier, discuss surveillance and research opportunities; there is no single proven preventive prescription that follows automatically from a 50% inheritance-risk calculation.
ما الذي ينبغي إحضاره إلى موعد الاختصاصي؟
Bring the original genetic report, symptom timeline, family history, and relevant cardiac or neurological investigations to an amyloidosis or clinical genetics appointment. These 4 information groups help specialists distinguish a confirmed disease-causing variant, an uncertain finding, unrelated symptoms, and early organ involvement.

Record symptom onset by month and year where possible, including numbness, bowel changes, wrist procedures, fainting, breathlessness, and reduced walking tolerance. Include at least 3 generations of family information if available, but distinguish a documented amyloidosis diagnosis from a relative's unexplained heart failure; uncertain family labels should remain visibly uncertain.
Ask 3 focused questions: Is this variant pathogenic, likely pathogenic, or uncertain; what evidence exists for active organ disease; and which relatives should be offered counseling? A written plan should also identify the clinician responsible for follow-up, what changes should trigger earlier contact, and whether a laboratory will notify anyone if the variant classification changes.
Kantesti is an AI-powered blood test analysis tool that can help explain laboratory reports before a consultation, not replace the consultation or infer another relative's genotype. Our guide to consent-based family health tracking covers shared records; our مبادئنا للذكاء الاصطناعي المسؤول explain why 1 uncertain genetic result should never become an automated family diagnosis.
أي الأبحاث تدعم التشخيص، وأيها يقيّم الذكاء الاصطناعي؟
Clinical amyloidosis research and AI technical benchmarks answer different questions. The 2016 nonbiopsy diagnostic study and 2021 ESC position statement support specific ATTR assessment pathways; the 2 repository publications listed below describe separate AI projects and do not validate TTR variant classification or diagnose hereditary ATTR amyloidosis.

The clinical evidence cited here addresses 3 distinct tasks: sequence-variant classification, cardiac amyloid confirmation, and specialist management pathways. Congo red staining can reveal amyloid but cannot, by itself, identify a TTR genotype or reliably distinguish all amyloid proteins; the same caution applies to a compelling-looking AI explanation unsupported by the required clinical tests.
Kantesti's repository publications describe early hantavirus triage across 50,000 interpreted reports and a technical benchmark involving 100,000 synthetic test cases. The blood-test engine benchmark provides context for the latter; synthetic-case performance does not establish sensitivity for detecting ATTR in real patients, and a Figshare DOI does not itself demonstrate peer review or regulatory authorization.
For patients and relatives, the next decision should follow the report category: counseling and individualized surveillance for a confirmed pathogenic variant, specialist-led clarification for a VUS, and organ assessment for relevant symptoms. Keep those 3 pathways separate; a genetic finding, an imaging result, and an AI-generated explanation are not interchangeable forms of evidence.
الأسئلة الشائعة
هل تعني طفرة في جين TTR أنني مصاب بداء النشواني ATTR الوراثي؟
0 يحمل وجود طفرة ممرضة أو يُرجح أنها ممرضة في جين TTR قابلية وراثية للإصابة، لكنه لا يثبت بحد ذاته وجود الداء النشواني الوراثي النشط الناجم عن TTR. قد يظل الشخص الذي لديه نسخة واحدة من TTR مسببة للمرض دون أعراض لسنوات عديدة، أو قد لا يُصاب أبدًا بمرض مشخص. يقيّم الاختصاصيون الأعراض ونتائج الفحص والتصوير، وأحيانًا نتائج الأنسجة، لتحديد ما إذا كان هناك مرض في أحد الأعضاء. ولا يثبت المتغير ذو الأهمية غير المؤكدة قابلية وراثية مماثلة للإصابة.
هل يمكن استخدام متغير TTR غير واضح الدلالة لفحص عائلتي؟
لا ينبغي استخدام متغير TTR ذي الأهمية غير المؤكدة بمفرده لإجراء الاختبارات التنبؤية الروتينية للأقارب الأصحاء أو لاتخاذ قرارات العلاج. وهو واحد من فئات التصنيف الخمس القياسية للمتغيرات، ويعني أن الأدلة غير كافية لتصنيف النتيجة على أنها ضارة أو غير ضارة. وقد ينسق فريق علم الوراثة إجراء اختبارات مختارة لأفراد الأسرة لدراسة ما إذا كان المتغير يترافق مع مرض مؤكد. ويساعد هذا الاستقصاء على التصنيف؛ لكنه لا يعادل تصنيف الأقارب على أنهم حاملون للمتغير ومصابون بالمرض.
ما احتمال أن يرث أطفالي داء النشواني المنقول بالوراثة (ATTR)؟
يكون لدى كل طفل لشخص لديه نسخة واحدة مسببة للمرض من TTR احتمال 50% عادةً لوراثة هذا المتغير. ويكون الاحتمال نفسه لدى الأطفال من أي جنس، كما أن كل حمل مستقل. ولا تحدد وراثة المتغير موعد بدء الأعراض أو مدى شدة المرض. ويمكن للاستشارة الوراثية توضيح الفحوص التنبؤية والخيارات الإنجابية دون اعتبار احتمال انتقال المتغير تنبؤًا بمآل المرض.
هل طفرَتا Val30Met وp.Val50Met في TTR هما الطفرة نفسها؟
يصف كلٌّ من Val30Met وp.Val50Met الاستبدال نفسه في بروتين TTR باستخدام نظامَي ترقيم مختلفين. يشمل الترقيم الحديث ببتيدًا إشارياً مكوّنًا من 22 حمضًا أمينيًا، لا يشمله الترقيم التاريخي للبروتين الناضج. وتفسّر المسألة نفسها الفرق بين Val122Ile وp.Val142Ile، وبين Thr60Ala وp.Thr80Ala. ينبغي لمتخصص في علم الوراثة مقارنة الصياغة الكاملة للحمض النووي والبروتين عند مراجعة تقارير صادرة عن مختبرات مختلفة.
هل يمكن أن تستبعد فحوصات الدم الطبيعية داء النشواني بالترانستيريتين (ATTR)؟
Normal routine blood tests cannot rule out ATTR amyloidosis or eliminate future disease risk in a pathogenic TTR carrier. Troponin is interpreted using the assay's 99th-percentile limit, while NT-proBNP and kidney results provide context about organ stress rather than amyloid identity. A normal TTR or prealbumin concentration does not exclude a TTR variant or amyloid deposits. Evaluation may still require neurological assessment, cardiac imaging, and selected tissue investigations.
هل الداء النشواني المرتبط بالترانستيريتين من النوع البري وراثي؟
0 الذُّهان النشواني من نوع ATTR البري لا يُعزى إلى متغير موروث مُسبِّب للمرض في TTR، على خلاف ATTR الوراثي. وقد يُنتج الشكلان نتائج قلبية متشابهة، لذا لا يمكن التمييز بينهما على نحو موثوق بالاعتماد على العمر والأعراض وحدهما. يُوصى بإجراء الاختبارات الجينية لـTTR بعد تأكيد اعتلال عضلة القلب النشواني من نوع ATTR، بما في ذلك لدى كبار السن. ولا يحتاج الأقارب إلى إجراء اختبار موجّه لمتغير عائلي ما لم يُحدَّد بالفعل متغير مُسبِّب للمرض.
كم مرة ينبغي لحامل طفرة TTR غير المصحوب بأعراض مراجعة اختصاصي؟
يخضع حامل TTR الممرض من دون أعراض عادةً لتقييم سنوي لدى اختصاصي، لكن ينبغي تخصيص المتابعة لكل حالة بدلًا من اعتماد جدول ثابت للجميع. تبدأ بعض المسارات مراقبةً منظمة قبل نحو 10 سنوات من العمر المتوقع لظهور المرض لدى أفراد الأسرة، مع إجراء تقييم أبكر عند ظهور أعراض أو نتائج مثيرة للقلق. وقد يشمل البرنامج فحصًا عصبيًا وتخطيطًا كهربائيًا للقلب وتخطيط صدى القلب ومؤشرات مخبرية مختارة. وينبغي أن يستدعي ضيق التنفس الجديد أو الضعف المتفاقم أو الإغماء إجراء تقييم أبكر بدلًا من انتظار الموعد المحدد.
تعرّف على نتائج تحليل الدم
حمّل تقرير المختبر الخاص بك، وسيشرح الذكاء الاصطناعي في Kantesti كل مؤشر حيوي بلغة مبسطة خلال ثوانٍ. يستخدمه أكثر من مليوني شخص حول العالم.
مراجع
- كلاين، ت.، ميتشل، س.، وآمبر، ه. (2026). دعم القرار السريري بمساعدة الذكاء الاصطناعي متعدد اللغات للفرز الأولي المبكر لحالات فيروس هانتا: التصميم، والتحقق الهندسي، والنشر في العالم الحقيقي عبر 50,000 تقرير مفسَّر لتحاليل الدم. أبحاث Kantesti الطبية بالذكاء الاصطناعي. DOI
- كلاين، ت.، ميتشل، س.، وآمبر، ه. (2026). معيار تقني آلي مُسجَّل مسبقًا ومبني على Rubric لمحرك تفسير اختبارات الدم Kantesti على 100,000 حالة اختبار اصطناعية. أبحاث Kantesti الطبية بالذكاء الاصطناعي. DOI
- Richards S وآخرون (2015). معايير وإرشادات تفسير متغيرات التسلسل: توصية توافقية مشتركة من الكلية الأمريكية لعلم الوراثة الطبية وعلم الجينوم والجمعية الأمريكية لعلم الأمراض الجزيئي. علم الوراثة في الطب. DOI ببميد
- Garcia-Pavia P et al. (2021). Diagnosis and treatment of cardiac amyloidosis: a position statement of the ESC Working Group on Myocardial and Pericardial Diseases. المجلة الأوروبية للقلب. DOI ببميد
- Gillmore JD et al. (2016). Nonbiopsy Diagnosis of Cardiac Transthyretin Amyloidosis. Circulation. DOI ببميد
- 2 مليون+الفحوصات المُحلَّلة
- 127+بلدان
- 100+اللغات
حول الفريق الطبي


إشارات الثقة E-E-A-T
خبرة
مراجعة سريرية تقودها طبيبة/طبيب لخطوات تفسير نتائج المختبر.
خبرة
تركيز طب المختبر على كيفية سلوك المؤشرات الحيوية في السياق السريري.
السلطة
راجع المحتوى طبيًا الدكتور توماس كلاين، بمساهمات من الدكتورة سارة ميتشل والأستاذ الدكتور هانس فيبر.
الجدارة بالثقة
تفسير قائم على الأدلة مع مسارات متابعة واضحة لتقليل حالة الإنذار.






إخلاء المسؤولية الطبية
هذه المقالة لأغراض تعليمية فقط ولا تشكل نصيحة طبية. استشر دائمًا مقدم رعاية صحية مؤهلًا لاتخاذ قرارات التشخيص والعلاج.
نُشر · تواصل مع فريق التحرير
نُشر بواسطة Kantesti Ltd، المسجلة في إنجلترا وويلز، رقم الشركة. 17090423, ، لندن، المملكة المتحدة.
