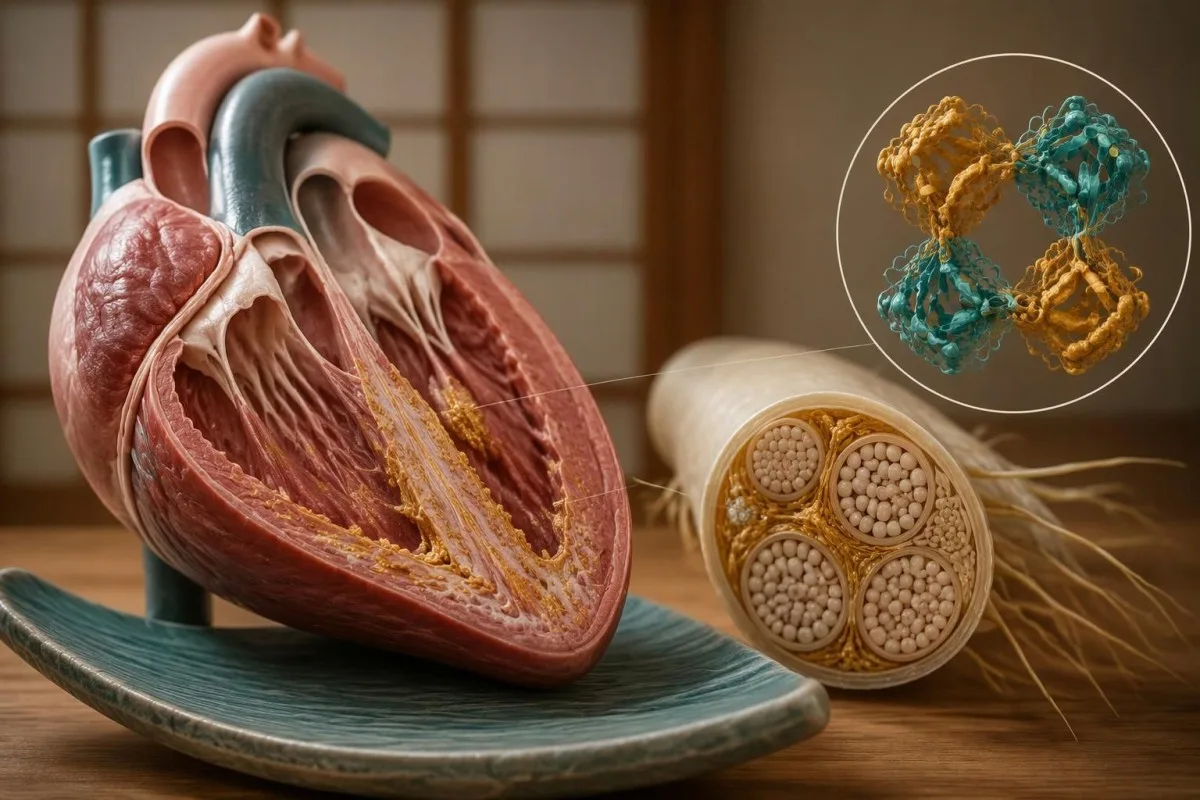
A disease-causing TTR variant establishes inherited susceptibility to hereditary ATTR amyloidosis—not proof of active disease. An uncertain variant does not establish that susceptibility; symptoms require a separate specialist assessment, and wild-type ATTR develops without a disease-causing inherited TTR variant.

Pangunang mga punto
- Pathogenic TTR variant means inherited susceptibility; 1 genetic finding alone does not establish symptomatic amyloidosis.
- Inheritance risk is usually 50% for each child of a person with 1 disease-causing TTR copy, regardless of the child's sex.
- Uncertain findings belong to 1 of 5 standard variant-classification categories; a VUS should not determine predictive testing or treatment by itself.
- Variant names can differ by 22 amino-acid positions: p.Val50Met and the historical Val30Met name describe the same substitution.
- Wild-type ATTR involves transthyretin without an identified disease-causing TTR variant; hereditary and wild-type deposits cannot reliably be distinguished by symptoms alone.
- Cardiac confirmation may use grade 2 or 3 bone-tracer uptake, but only within the appropriate imaging pathway and after monoclonal protein assessment.
- Carrier surveillance often includes annual assessment, with timing individualized; approximately 10 years before predicted family onset is a planning aid, not a biological deadline.
- Mga sintomas sa emergency such as severe breathlessness, collapse, or chest pain need immediate care—not a wait for the next 6–12-month surveillance visit.
What does a TTR variant actually mean?
A pathogenic or likely pathogenic TTR variant identifies inherited susceptibility to hereditary ATTR amyloidosis, but does not by itself show active amyloid deposition or organ damage. A variant nga walay katin-awan nga kahulogan, or VUS, has insufficient evidence for that conclusion; these are separate questions requiring separate clinical decisions.

TTR is the gene that encodes transthyretin, a transport protein produced mainly by the liver; its usual circulating structure contains 4 protein subunits. Some variants make that structure less stable, allowing misfolded protein to accumulate as amyloid, particularly in nerves or the heart.
For example, imagine a 46-year-old whose clinical genetic test identifies a known disease-causing TTR variant, but whose neurological examination and cardiac assessment show no disease. The appropriate description may be an asymptomatic variant carrier, not a person with symptomatic amyloidosis; treatment eligibility and follow-up depend on additional findings.
Kantesti is an AI blood test analyzer that helps explain accompanying laboratory results, while keeping genetic susceptibility separate from organ-disease confirmation. Information about among organisasyon explains our service context; neither a routine laboratory panel nor an AI explanation can replace these 2 specialist assessments.
How do pathogenic TTR findings differ from a VUS?
Pathogenic ug likely pathogenic findings have evidence supporting a disease-causing role; a VUS lacks sufficient evidence for either a harmful or harmless classification. Laboratories use 5 standard categories: pathogenic, likely pathogenic, uncertain significance, likely benign, and benign.

The ACMG/AMP sequence-variant framework places likely pathogenic findings above a 90% confidence threshold for pathogenicity, but that percentage describes classification confidence, not an individual's chance of developing symptoms (Richards et al., 2015). Our explanation of inherited cancer test results illustrates the same distinction between a laboratory label and a person's current disease status.
A VUS should not, by itself, trigger disease-specific treatment or routine predictive testing of healthy relatives. Specialists may instead investigate whether the finding tracks with confirmed disease in a family—a segregation study involving 2 or more informative relatives when available—which is different from declaring those relatives genetically affected.
Classification can change when additional family, functional, or population evidence becomes available. Ask who will handle recontact, whether review in 12–24 months would be useful, and whether another laboratory has classified the exact same variant differently; our guide to common genetic variant misconceptions explains why the word mutation is not automatically a diagnosis.
Why can the same TTR variant have two names?
The same TTR variant can have modern and historical protein names because modern numbering includes a 22-amino-acid signal peptide. For example, p.Val50Met is the variant historically called Val30Met, ug p.Val142Ile is the variant historically called Val122Ile.

A complete report ideally supplies the gene, transcript reference, DNA-level notation, protein-level notation, zygosity, and classification—not simply a variant nickname. Because a TTR precursor contains 149 amino acids and the mature protein contains 127, comparing reports without noticing the numbering convention can create an apparent disagreement where none exists.
p.Thr80Ala, historically Thr60Ala, can produce a mixed cardiac and neurological phenotype, whereas p.Val142Ile is often associated with predominantly cardiac disease. These are tendencies rather than guarantees: 2 relatives with the same variant may differ in age at onset, affected organs, and severity.
For a hypothetical family, a parent's report saying Val122Ile and an adult child's report saying p.Val142Ile should prompt exact-notation comparison before anyone concludes that there are 2 different familial variants. Similar nomenclature issues arise in enzyme and genetic testing; bring the original reports rather than relying on a handwritten abbreviation.
Does a 50% inheritance risk mean a 50% disease risk?
A 50% inheritance risk is not a 50% risk of symptomatic disease. Hereditary ATTR usually follows autosomal dominant inheritance: a person with 1 disease-causing TTR copy has a 50% chance of passing that copy to each child, but disease expression depends on age-related penetrance and other factors.

Each pregnancy is an independent event; with 2 children, the theoretical probabilities are 25% for neither inheriting the variant, 50% for exactly one, and 25% for both. Those calculations assume one heterozygous parent and describe inheritance only—they do not predict whether or when either child will become ill.
Penetrance means the proportion of variant carriers who develop disease by a stated age, and it varies across TTR variants and populations. The often-quoted 3–4% frequency of p.Val142Ile in some populations of African ancestry is a variant-frequency estimate, not a universal estimate of amyloidosis prevalence or an individual's lifetime disease risk.
An apparently unaffected parent aged 75 can still have transmitted a pathogenic variant, while a negative family history may reflect late onset, small families, or previously unrecognized disease. Our discussion of genetic susceptibility and kidney risk offers a useful comparison, although APOL1 risk architecture should not be substituted for TTR inheritance.
How is hereditary ATTR different from wild-type ATTR?
Hereditary ATTR involves a disease-causing TTR variant; wild-type ATTR involves amyloid formed from transthyretin without an identified disease-causing variant. Both can affect the heart, so neither age nor a cardiac scan alone reliably distinguishes these 2 forms.
TTR sequencing is recommended after ATTR cardiomyopathy is established, including in older adults, because hereditary disease can first become apparent after age 70. The ESC position statement emphasizes genetic counseling and testing to distinguish variant ATTR from wild-type ATTR, rather than assuming that an older patient's disease cannot be inherited (Garcia-Pavia et al., 2021).
A negative result for a known family variant removes that particular inherited susceptibility, but it does not guarantee that the person will never develop wild-type ATTR or another heart condition. Conversely, a VUS does not automatically convert a confirmed ATTR diagnosis into hereditary ATTR; the laboratory classification and amyloid diagnosis still need reconciliation.
ATTR is also different from AL amyloidosis, caused by immunoglobulin light chains, and AA amyloidosis, associated with prolonged inflammatory activity. These are at least 3 distinct amyloid types with different investigations and treatment pathways; an elevated serum amyloid A result does not diagnose TTR-related disease.
Which hereditary amyloidosis symptoms need assessment?
Hereditary amyloidosis symptoms may include progressive numbness or burning feet, weakness, altered bowel function, dizziness on standing, breathlessness, or ankle swelling. These findings are nonspecific, but involvement of 2 systems—such as neuropathy plus unexplained cardiac thickening—raises more concern than either finding alone.
Bilateral carpal tunnel syndrome, particularly when it precedes cardiac symptoms by several years, can be an ATTR clue but is far more commonly explained by other causes. Document whether 1 or both wrists are affected and when symptoms began; our guide to carpal tunnel finger patterns helps distinguish a local median-nerve pattern from broader neuropathy.
Orthostatic hypotension commonly means a sustained fall of at least 20 mmHg systolic or 10 mmHg diastolic within 3 minutes of standing. Amyloid-related autonomic dysfunction is one possible cause, but dehydration and medicines are common alternatives; it is not interchangeable with the heart-rate pattern discussed in POTS diagnostic testing.
Consider a hypothetical 58-year-old carrier who develops numb feet, unintentional weight loss, and new difficulty climbing stairs over 6 months: that combination warrants prompt specialist review rather than waiting for annual screening. Sudden weakness, severe breathlessness, chest pain, or collapse requires urgent care because immediately treatable problems must be assessed before attributing symptoms to ATTR.
Which tests establish active ATTR amyloidosis?
Active ATTR amyloidosis requires evidence of amyloid disease, not just a genetic result. In the appropriate cardiac setting, grade 2 or 3 uptake on a validated bone-tracer scan can establish ATTR cardiomyopathy without biopsy only when monoclonal protein testing is negative and imaging confirms uptake within heart muscle.

The monoclonal screen includes serum free light chains plus serum and urine immunofixation; serum protein electrophoresis alone is insufficient. Gillmore et al.'s 2016 Circulation study evaluated 1,217 patients and established the nonbiopsy cardiac approach under defined conditions; our guide to immunofixation bands and follow-up explains why detecting a monoclonal protein changes the next step.
A monoclonal protein does not prove AL amyloidosis, because an unrelated monoclonal gammopathy can coexist with ATTR, especially in older adults. However, it prevents clinicians from using the simplified scan-only ATTR pathway; interpreting the libre nga light chain ratio also requires kidney-function context and, where available, assay-specific renal reference intervals.
When tissue examination is needed, Congo red staining establishes amyloid, while reliable protein typing—often mass spectrometry—identifies its source. A negative abdominal fat sample does not exclude ATTR, and grade 1 cardiac uptake is not the same as the grade 2–3 diagnostic criterion; neuropathy-predominant disease may require a different combination of neurological and tissue investigations.
What should TTR genetic counseling cover?
TTR genetic counseling should explain the exact variant, classification, inheritance, limitations of risk prediction, and consequences for relatives before testing or major decisions. For most heterozygous families, the 50% transmission probability is straightforward; predicting age at onset and organ involvement is much less precise.

Counseling distinguishes diagnostic testing in someone with suspected disease from predictive testing in an unaffected relative. A person considering predictive testing should have time to discuss emotional readiness and the right not to know, similar to the consent principles described in predictive neurological genetic testing, although TTR penetrance differs substantially.
Reproductive discussions can include natural conception, prenatal diagnosis, and preimplantation genetic testing where available and legally permitted. Because a 50% transmission risk does not specify future severity, these conversations should be nondirective; confirm the familial pathogenic variant in a clinical laboratory before using it for reproductive testing or other consequential decisions.
Kantesti's explanations of pribasiya ug ang imong datos help readers consider what they share, but genetic information has implications beyond ordinary laboratory values. Before adding reports for 2 or more relatives to a shared account, obtain each person's permission and ask the genetics team about local insurance rules, record access, and secure family communication.
Which relatives should consider targeted TTR testing?
Adult relatives at risk of a confirmed familial pathogenic or likely pathogenic TTR variant should be offered genetic counseling and the option of targeted testing. Each child of a heterozygous carrier has a 50% inheritance probability; a sibling's risk depends on whether a parent carries the variant.

Start with the relative who has confirmed disease whenever possible, then use that person's exact variant to guide cascade testing. Testing all relatives with a broad panel before establishing the family finding may generate additional VUS results; this differs from the recessive inheritance questions in SMA carrier screening, where 2 gene copies have a different meaning.
Predictive testing for adult-onset TTR disease is generally deferred in children younger than 18 when the result would not change childhood care, preserving their future choice. A child with unexplained relevant symptoms needs clinical assessment rather than automatic dismissal; any exceptional testing decision should involve pediatric and genetics specialists, not a routine family screening package.
For example, a 34-year-old who tests negative for a clinically confirmed familial p.Val50Met variant generally does not need surveillance specifically for that family variant. A symptomatic relative still needs assessment for other causes, and a 1-variant consumer screening result cannot substitute for a validated familial test if the relevant variant was not actually examined.
How are asymptomatic TTR carriers followed?
Asymptomatic pathogenic TTR carriers need individualized surveillance, commonly involving annual clinical review, rather than an automatic amyloidosis diagnosis or preventive prescription. Many expert pathways begin structured assessment approximately 10 years before predicted disease onset, but variant-specific evidence and family history may justify earlier or different monitoring.
Baseline assessment may include neurological examination, autonomic history, ECG, echocardiography, kidney function, and cardiac biomarkers; additional tests depend on the variant and symptoms. The ESC position statement outlines regular carrier follow-up (Garcia-Pavia et al., 2021), but a 6–12-month interval should be individualized, especially when new findings appear or expected onset approaches.
A parent's onset at 62 is not a countdown showing that a child's disease will begin at 62, and a normal baseline does not eliminate later risk. Kantesti AI can help explain the difference between a single value and a meaningful laboratory timeline, but specialist decisions also require examination and imaging that routine blood interpretation cannot supply.
Imagine NT-proBNP increasing from 180 to 620 pg/mL while eGFR falls from 62 to 43 mL/min/1.73 m²: cardiac change deserves assessment, but reduced kidney clearance can contribute to the rise. Review intercurrent illness, rhythm, and medicines before interpreting progression; our giya sa ratio sa kidney function explains why renal context belongs beside cardiac trends.
What can blood tests reveal—and what can they miss?
Routine blood tests cannot confirm or exclude hereditary ATTR amyloidosis. NT-proBNP, troponin, kidney function, and urine protein can help assess organ involvement or alternatives, but a normal set of results—even across 2 visits—does not establish that a pathogenic TTR carrier will remain disease-free.
Troponin must be interpreted against the assay's 99th-percentile upper reference limit, and NT-proBNP varies with age, kidney function, atrial fibrillation, and body size. A TTR or prealbumin concentration such as 25 mg/dL does not identify a TTR gene mutation or prove amyloid deposition; the test measures circulating protein concentration rather than its genetic sequence.
Neuropathy assessment should also look for treatable alternatives, including diabetes, vitamin B12 deficiency, thyroid disease, and medication effects. A hypothetical B12 result of 210 pg/mL may need additional assessment according to the laboratory and symptoms; our discussion of mga borderline nga resulta sa Vitamin B12 explains why a competing diagnosis should not be overlooked simply because a TTR variant exists.
Kantesti is an AI blood test interpretation platform that explains accompanying laboratory values without treating 1 protein result as an amyloidosis diagnosis. Our giya sa interpretasyon sa serum protein helps separate transport proteins and immunoglobulin findings; neither an ordinary protein panel nor a family-risk feature replaces clinical TTR testing and amyloid typing.
Does a positive TTR genetic result mean treatment should start?
A positive TTR genetic result alone is not a standard indication for disease-modifying treatment. Specialists consider confirmed ATTR disease, the affected organs, functional status, and local approvals; the 2 main medication strategies are stabilizing transthyretin and reducing production of transthyretin.

TTR stabilizers aim to reduce dissociation of the 4-subunit protein, while TTR-lowering therapies reduce production, mainly in the liver. Neither approach edits the inherited DNA, so family transmission considerations remain after treatment; eligibility differs between cardiomyopathy, polyneuropathy, and mixed disease, as do approval and reimbursement rules across countries.
Monitoring depends on the chosen medicine rather than the genetic label alone: some regimens require attention to platelets, kidney function, or vitamin A handling. If vitamin A supplementation is advised during a TTR-lowering regimen, use the prescribed allowance rather than escalating the dose because a laboratory result looks low; 1 abnormal value does not establish a safe replacement dose.
Kantesti does not select amyloidosis medication or establish treatment eligibility from uploaded laboratory results; our technical validation ug oversight describe a different task from specialist prescribing. For an asymptomatic carrier, discuss surveillance and research opportunities; there is no single proven preventive prescription that follows automatically from a 50% inheritance-risk calculation.
Unsa ang angay nimong dad-on sa pakigtagbo sa espesyalista?
Bring the original genetic report, symptom timeline, family history, and relevant cardiac or neurological investigations to an amyloidosis or clinical genetics appointment. These 4 information groups help specialists distinguish a confirmed disease-causing variant, an uncertain finding, unrelated symptoms, and early organ involvement.

Record symptom onset by month and year where possible, including numbness, bowel changes, wrist procedures, fainting, breathlessness, and reduced walking tolerance. Include at least 3 generations of family information if available, but distinguish a documented amyloidosis diagnosis from a relative's unexplained heart failure; uncertain family labels should remain visibly uncertain.
Ask 3 focused questions: Is this variant pathogenic, likely pathogenic, or uncertain; what evidence exists for active organ disease; and which relatives should be offered counseling? A written plan should also identify the clinician responsible for follow-up, what changes should trigger earlier contact, and whether a laboratory will notify anyone if the variant classification changes.
Kantesti is an AI-powered blood test analysis tool that can help explain laboratory reports before a consultation, not replace the consultation or infer another relative's genotype. Our guide to consent-based family health tracking covers shared records; our mga prinsipyo sa responsable nga AI explain why 1 uncertain genetic result should never become an automated family diagnosis.
Which research supports diagnosis, and which evaluates AI?
Clinical amyloidosis research and AI technical benchmarks answer different questions. The 2016 nonbiopsy diagnostic study and 2021 ESC position statement support specific ATTR assessment pathways; the 2 repository publications listed below describe separate AI projects and do not validate TTR variant classification or diagnose hereditary ATTR amyloidosis.

The clinical evidence cited here addresses 3 distinct tasks: sequence-variant classification, cardiac amyloid confirmation, and specialist management pathways. Congo red staining can reveal amyloid but cannot, by itself, identify a TTR genotype or reliably distinguish all amyloid proteins; the same caution applies to a compelling-looking AI explanation unsupported by the required clinical tests.
Kantesti's repository publications describe early hantavirus triage across 50,000 interpreted reports and a technical benchmark involving 100,000 synthetic test cases. The blood-test engine benchmark provides context for the latter; synthetic-case performance does not establish sensitivity for detecting ATTR in real patients, and a Figshare DOI does not itself demonstrate peer review or regulatory authorization.
For patients and relatives, the next decision should follow the report category: counseling and individualized surveillance for a confirmed pathogenic variant, specialist-led clarification for a VUS, and organ assessment for relevant symptoms. Keep those 3 pathways separate; a genetic finding, an imaging result, and an AI-generated explanation are not interchangeable forms of evidence.
Mga kanunayng gipangutana
Nagpasabot ba ang mutation sa TTR gene nga aduna koy napanunod nga ATTR amyloidosis?
Ang pathogenic o lagmit pathogenic nga mutation sa TTR gene nagpasabot sa napanunod nga predisposisyon, apan dili kini lamang ang magpamatuod nga adunay aktibong hereditary ATTR amyloidosis. Ang usa ka tawo nga adunay 1 ka kopya sa TTR nga hinungdan sa sakit mahimong walay sintomas sulod sa daghang katuigan o dili gayod makaangkon og sakit nga mailhan. Ginasusi sa mga espesyalista ang mga sintomas, mga nakita sa eksaminasyon, imaging, ug usahay mga resulta sa tisyu aron matino kon adunay sakit sa organ. Ang variant of uncertain significance wala magpamatuod sa samang napanunod nga predisposisyon.
Mahimo bang gamiton ang TTR variant nga wala pa matino ang kahulogan sa pagsusi sa akong pamilya?
0 Usa: ang TTR variant of uncertain significance sa kaugalingon lamang alang sa naandan nga predictive testing sa himsog nga mga paryente o sa mga desisyon sa pagtambal. Usa kini sa 5 ka standard nga kategoriya sa pagklasipikar sa variant ug nagpasabot nga kulang ang ebidensiya aron maklasipikar ang nadiskobrehan nga makadaot o dili makadaot. Mahimong maghikay ang usa ka genetics team og piniling pagsulay sa pamilya aron tun-an kon ang variant makita uban sa kumpirmadong sakit. Makatabang kana nga imbestigasyon sa pagklasipikar; dili kini pareho sa pagmarka sa mga paryente isip mga carrier nga apektado.
Unsa ang posibilidad nga mapanunod sa akong mga anak ang hereditary ATTR?
0 Kada usa ka anak sa tawo nga adunay 1 ka kopya sa TTR nga hinungdan sa sakit kasagarang adunay 50% nga kahigayonan nga mapanunod ang maong baryante. Pareho ang posibilidad niini alang sa mga anak sa bisan unsang sekso, ug independente ang matag pagmabdos. Ang pagpanunod sa baryante dili makasiguro kon kanus-a magsugod ang mga sintomas o unsa ka grabe ang sakit. Ang genetic counseling makapasabot sa predictive testing ug mga kapilian sa pagpanganak nga dili isipon ang posibilidad sa pagpasa isip prognosis sa sakit.
Pareho ba ang Val30Met ug p.Val50Met nga TTR mutation?
Ang Val30Met ug p.Val50Met naghulagway sa samang substitusyon sa protina nga TTR gamit ang lainlaing mga kombensiyon sa pagnumero. Ang modernong pagnumero naglakip sa signal peptide nga adunay 22 ka amino acid, nga wala ilakip sa karaang pagnumero sa hinog nang protina. Mao usab kini ang hinungdan sa kalainan tali sa Val122Ile ug p.Val142Ile, ug sa Thr60Ala ug p.Thr80Ala. Kinahanglang itandi sa usa ka propesyonal sa henetika ang tibuok notasyon sa DNA ug protina sa pagrepaso sa mga report gikan sa nagkalainlaing laboratoryo.
Can normal blood tests rule out ATTR amyloidosis?
Normal routine blood tests cannot rule out ATTR amyloidosis or eliminate future disease risk in a pathogenic TTR carrier. Troponin is interpreted using the assay's 99th-percentile limit, while NT-proBNP and kidney results provide context about organ stress rather than amyloid identity. A normal TTR or prealbumin concentration does not exclude a TTR variant or amyloid deposits. Evaluation may still require neurological assessment, cardiac imaging, and selected tissue investigations.
Is wild-type ATTR amyloidosis inherited?
Wild-type ATTR amyloidosis is not attributed to a disease-causing inherited TTR variant, unlike hereditary ATTR. The 2 forms can produce similar cardiac findings, so age and symptoms alone cannot reliably distinguish them. TTR genetic testing is recommended after ATTR cardiomyopathy is established, including in older adults. Relatives do not need targeted testing for a familial variant unless a disease-causing variant has actually been identified.
How often should an asymptomatic TTR carrier see a specialist?
An asymptomatic pathogenic TTR carrier commonly has annual specialist assessment, but follow-up should be individualized rather than fixed for everyone. Some pathways begin structured surveillance approximately 10 years before predicted family onset, with earlier review for symptoms or concerning findings. Neurological examination, ECG, echocardiography, and selected laboratory markers may form part of the plan. New breathlessness, progressive weakness, or fainting should prompt earlier assessment instead of waiting for the scheduled visit.
Paipatin-aw ang imong resulta sa blood test
I-upload ang report sa imong laboratoryo ug ipatin-aw sa AI sa Kantesti ang matag biomarker sa yano nga pinulongan sulod sa pipila ka segundo. Gigamit sa kapin sa 2 ka milyon ka tawo sa tibuok kalibotan.
Mga Reperensya
- Klein, T., Mitchell, S., & Weber, H. (2026). Multilingual nga Suportang Pangdesisyon sa Klinika nga Gitabangan sa AI alang sa Sayo nga Pagsusi sa Hantavirus: Disenyo, Pag-validate sa Inhenyeriya ug Pagpatuman sa Tinuod nga Kalibotan sa 50,000 ka mga Report sa Pagsabot sa Resulta sa Blood Test. Panukiduki Medikal sa Kantesti AI. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Usa ka Pre-Registered, Rubric-Based Automated Technical Benchmark sa Kantesti Blood-Test Interpretation Engine sa 100,000 Synthetic Test Cases. Panukiduki Medikal sa Kantesti AI. DOI
- Richards S et al. (2015). Mga sumbanan ug giya sa paghubad sa mga baryante sa han-ay sa DNA: hiniusang rekomendasyon sa konsensus sa American College of Medical Genetics and Genomics ug sa Association for Molecular Pathology. Genetics in Medicine. DOI PubMed
- Garcia-Pavia P et al. (2021). Diagnosis and treatment of cardiac amyloidosis: a position statement of the ESC Working Group on Myocardial and Pericardial Diseases. European Heart Journal. DOI PubMed
- Gillmore JD et al. (2016). Nonbiopsy Diagnosis of Cardiac Transthyretin Amyloidosis. Circulation. DOI PubMed
- 2M+Mga gisusi nga eksaminasyon
- 127+Mga nasud
- 100+Mga pinulongan
Mahitungod sa medikal nga team


Mga E-E-A-T Trust Signals
Kasinatian
Pagsusi sa klinika nga gipangulohan sa doktor sa mga workflow sa interpretasyon sa lab.
Kahanas
Pokus sa medisina sa laboratoryo kung giunsa paglihok ang mga biomarker sa konteksto sa klinika.
Pagka-awtorisado
Gisusi sa medisina ni Dr. Thomas Klein, uban sa mga kontribusyon ni Dr. Sarah Mitchell ug Prof. Dr. Hans Weber.
Kasaligan
Interpretasyon nga base sa ebidensya, nga adunay klaro nga mga agianan sa sunod nga buhat aron makunhuran ang kabalaka.






Disclaimer sa medisina
Kini nga artikulo para sa katuyoan sa edukasyon ra ug dili kini mosangpot sa medikal nga tambag. Kanunay mokonsulta sa usa ka kwalipikado nga healthcare provider alang sa mga desisyon sa diagnosis ug pagtambal.
Gibilin · Kontaka ang team sa editoryal
Gipatik sa Kantesti Ltd, narehistro sa England ug Wales, numero sa kompanya. 17090423, London, United Kingdom.
