Robežvērtību sviedru hlorīdu rezultāts 30–59 mmol/L neapstiprina cistisko fibrozi. Tas nozīmē, ka rezultātam nepieciešama tālāka izmeklēšana: parasti atkārtota testēšana pieredzējušā centrā, simptomu un jaundzimušā skrīninga pārskatīšana, un dažreiz CFTR gēnu vai funkcionālā izvērtēšana.


- Zems sviedru hlorīds: Mazāk par 30 mmol/L padara cistisko fibrozi mazāk ticamu, bet neizslēdz to pilnībā, ja simptomi vai ģenētika ir ļoti izteikta.
- Starpposma sviedru hlorīds: Līmeņi no 30–59 mmol/L ir nenoteikti — nevis apstiprināta cistiskās fibrozes diagnoze, un nevis automātiski pārvadātāja rezultāts.
- Paaugstināts sviedru hlorīds: Derīgs rezultāts 60 mmol/L vai augstāks atbalsta cistisko fibrozi atbilstošā klīniskā situācijā un prasa speciālista apstiprinājumu.
- Atkārtota pārbaude: Starpposma rezultāts parasti prasa vēl vienu sviedru hlorīdu testu 1–2 mēnešu laikā, ar agrāku izvērtēšanu simptomātiskiem zīdaiņiem vai satraucošiem simptomiem.
- Visas vecuma grupas: Pašreizējie Cistiskās Fibrozes Fondam diagnostikas sliekšņi izmanto mazāk par 30, 30–59 un vismaz 60 mmol/L zīdaiņiem, bērniem un pieaugušajiem.
- Kolekcijas kvalitāte: Nepietiekams sviedru paraugs nevar tikt uzskatīts par ticamu negatīvu rezultātu; atsevišķas savākšanas vietas nedrīkst apvienot.
- CFTR izvērtēšana: Pastāvīgi starprezultāti, aizdomīgas simptomi vai anomāli jaundzimušo skrīninga rezultāti var attaisnot sekvenču analīzi, duplikāciju/delēciju analīzi un ģenētisko konsultēšanu.
- AI ierobežojumi: Sviedru hlorīda mērījumi ir sviedri, nevis asinis. AI interpretācija pavadošajiem laboratorijas rezultātiem nevar apstiprināt vai izslēgt cistisko fibrozi.
Ko nozīmē zemi, starpposma un paaugstināti rezultāti?
Sviedru hlorīda testu rezultāti zem 30 mmol/L padara cistisko fibrozi mazāk ticamu; 30–59 mmol/L ir starpposms; un 60 mmol/L vai augstāks atbalsta cistisko fibrozi atbilstošā klīniskā situācijā. Robežvērtība ir iemesls izmeklēšanai — nevis diagnoze, smaguma pakāpes rādītājs vai iemesls pašrocīgi uzsākt ārstēšanu.
2017. gada Cistiskās Fibrozes Fondam pieņemtā vienošanās attiecina šos 3 sliekšņus visām vecuma grupām, nevis izmanto augstāku starpposma robežu vecākiem bērniem un pieaugušajiem (Farrell et al., 2017). Daži vecāki ziņojumi joprojām apraksta 40–59 mmol/L kā robežvērtību pēc zīdaiņa vecuma; rezultāts 35 mmol/L nedrīkst tikt noraidīts tikai tāpēc, ka novecojis atsauces intervāls to nosauc par normālu.
Rezultāts 59 mmol/L un 60 mmol/L iekrīt dažādās kategorijās, taču bioloģija starp šiem skaitļiem strauji nemainās. Kolekcijas kvalitāte, simptomi, skrīninga vēsture un atkārtoti mērījumi nosaka, cik pārliecinoši kategoriju var izmantot. Mūsu skaidrojums par ārpus normas esošiem laboratorijas brīdinājumiem paskaidro, kāpēc marķēts skaitlis pats par sevi nav diagnoze.
Esmu Thomas Klein, MD, Kantesti galvenais medicīnas direktors, un mans klīniskais mērķis ir atdalīt mērījumu no diagnozes pirms jebkura no tiem apspriešanas. Kantesti ir AI asins analīžu analizators; sviedru hlorīds ir atsevišķs speciālista tests, nevis asins biomarķieris. Mūsu organizācija un klīniskais tvērums paskaidro šo atšķirību, kas ir īpaši svarīga, kad kāds augšupielādē jauktu laboratorijas ziņojumu.
Ko patiesībā mēra sviedru hlorīdu tests?
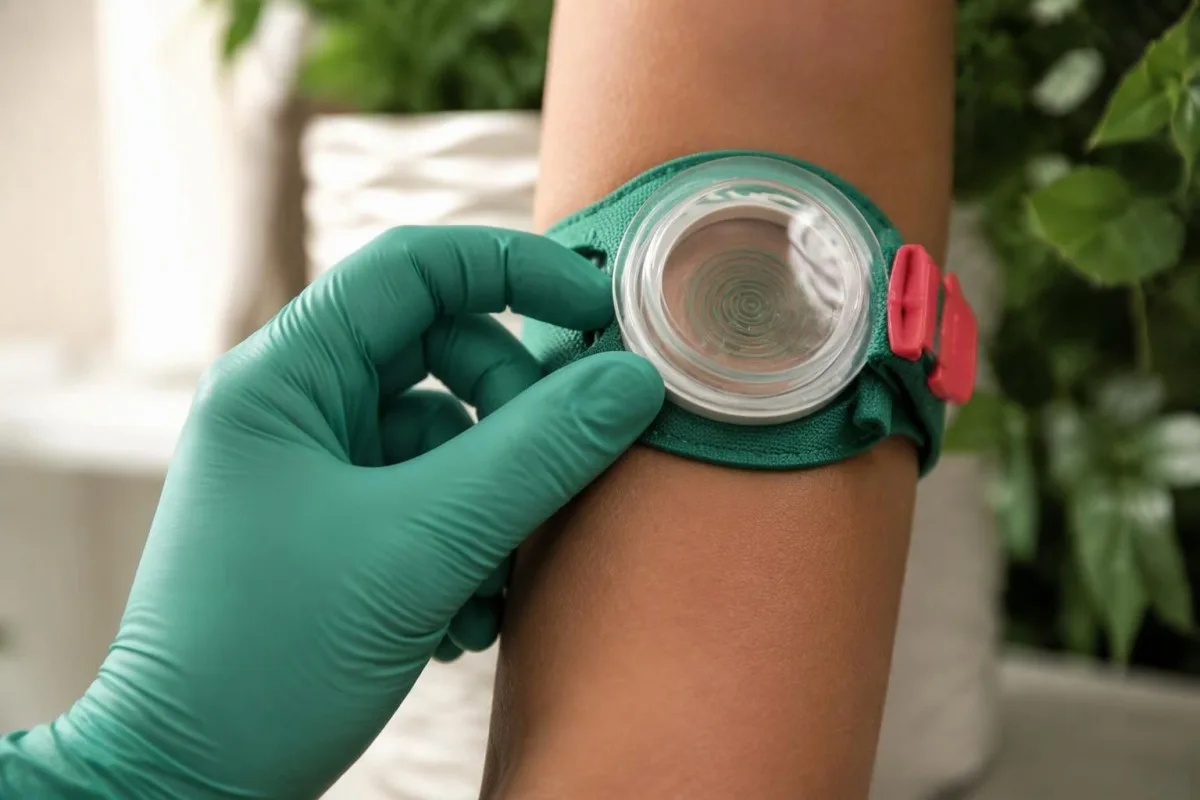
Sviedru hlorīda tests mēra hlorīda koncentrāciju sviedros pēc tam, kad pilokarpīns stimulē nelielu savākšanas laukumu. Tas novērtē vienu no CFTR kanālu darbības sekām: cik efektīvi sviedru kanāls reabsorbē hlorīdu pirms sviedru sasniegšanas virsmas. Diagnostiskais rezultāts tiek ziņots mmol/L, nevis kā saražoto sviedru daudzums.
The sweat gland first produces fluid, and its duct then reabsorbs salt. Reduced CFTR function can leave more chloride in the final sweat, producing values of 60 mmol/L or higher in many people with cystic fibrosis. This is a functional clue, but it does not directly measure lung damage, pancreatic function, or the number of genetic variants present.
Sweat chloride and serum chloride describe different compartments. A person can have elevated sweat chloride while the chloride concentration in a metabolic panel is normal—or low after substantial salt loss. Our discussion of serum chloride and fluids concerns blood chemistry; its reference intervals cannot be substituted for the 30–59 mmol/L sweat interval.
The units can also look different without representing different thresholds: for chloride, 1 mmol/L equals 1 mEq/L because chloride has a single electrical charge. Sweat conductivity is another matter—it reflects multiple ions, often expressed as sodium chloride equivalents. A conductivity result must not be interpreted using diagnostic sweat chloride thresholds, even when the report looks reassuringly numerical.
Kāpēc starpposma rezultāts neapstiprina cistisko fibrozi?
An intermediate sweat chloride result does not confirm cystic fibrosis because 30–59 mmol/L overlaps several clinical situations. These include some people with cystic fibrosis, people with other CFTR-associated conditions, and people without a CFTR disorder. The same value can therefore lead to different conclusions depending on the evidence around it.
For an illustrative comparison, consider a thriving infant with 38 mmol/L after newborn screening and an adult with 38 mmol/L plus recurrent pancreatitis and bronchiectasis. Neither number independently proves cystic fibrosis, but the second history raises different diagnostic questions. This is why I would not attach a single percentage probability to every borderline sweat chloride test without knowing the referral context.
Persistent intermediate results on 2 separate occasions can still occur in cystic fibrosis, and the 2017 consensus recommends considering extended CFTR analysis or specialized functional testing in that setting (Farrell et al., 2017). Conversely, 2 intermediate measurements do not automatically convert uncertainty into a confirmed diagnosis. Repetition establishes persistence; it does not explain the cause by itself.
Borderline is also not another word for carrier. A person with 1 identified CF-causing variant may be a carrier, but the initial genetic panel might have missed another variant, or the symptoms may have another explanation. Our discussion of borderline stool test follow-up illustrates the broader distinction between an indeterminate measurement and a named disease; the follow-up tests themselves are different.
Ko tālāk prasa pozitīvs sviedru hlorīdu tests?
A properly collected sweat chloride result of at least 60 mmol/L supports a cystic fibrosis diagnosis when there is compatible newborn screening, a relevant family history, or characteristic clinical features. Specialist assessment should follow promptly. Confirmation usually uses repeat testing on a separate date or an independent diagnostic method, such as appropriate CFTR analysis.
A report saying sweat chloride test positive deserves more than a telephone message reading only the flag. Ask for the actual concentration, the collection method, whether the sample was sufficient, and the plan for confirmation. A measured chloride of 72 mmol/L is meaningful evidence; a positive conductivity screening result is not an interchangeable diagnostic finding.
The distinction between a category and a concentration matters at both ends of the scale. Chloride concentrations above roughly 160 mmol/L are outside the expected physiological range for sweat and should trigger immediate laboratory review rather than assumptions about unusually severe disease. The collection and analytical record may be more informative than another decimal place on the report.
Positive-range sweat chloride is not, by itself, an emergency severity score. A clinically stable child with 68 mmol/L needs a timely CF specialist pathway; a child with dehydration or breathing difficulty needs urgent care regardless of the sweat value. Our guide to kvalitatīvi un kvantitatīvi rezultāti explains why the measured number should accompany the positive label.
Vai zems rezultāts var izslēgt cistisko fibrozi?
Sweat chloride below 30 mmol/L makes cystic fibrosis less likely, but cannot absolutely exclude it when symptoms or CFTR findings are strongly suggestive. A low result is most reassuring when the sample was valid, the person has no characteristic symptoms, and the screening or family-history concern has been adequately addressed.
Certain CFTR variants preserve enough sweat-duct function to produce lower chloride concentrations despite clinically relevant disease. The 2017 consensus therefore allows further evaluation when a value below 30 mmol/L conflicts with genotype or evolving clinical features (Farrell et al., 2017). A normal newborn screen also does not eliminate every possible CF diagnosis in a child who later develops suggestive symptoms.
Age does not create a separate low-result exception: a value of 27 mmol/L has the same diagnostic category in a toddler and an adult. What changes is the history available to interpret it—growth trajectory in a young child, for example, versus years of recurrent pancreatitis or unexplained bronchiectasis in an adult. The referral question should travel with the laboratory result.
A child with 24 mmol/L, persistent greasy stools, and faltering growth still needs an explanation for the symptoms, even if cystic fibrosis becomes less likely. The next step may include pancreatic, gastrointestinal, or nutritional assessment rather than simply repeating every test. Our guidance on bērnu AI interpretācijas ierobežojumi explains why pediatric decisions require age-specific clinical oversight.
Kā tiek apstrādāti starpposma rezultāti pēc jaundzimušā skrīninga?
An infant with an abnormal newborn screen and intermediate sweat chloride needs assessment through a CF specialist pathway, but may not have cystic fibrosis. Some clinically well infants receive the designation CRMS/CFSPID, meaning the screening and diagnostic findings remain inconclusive. This designation has specific criteria; it should not be applied to every borderline result.
CRMS/CFSPID generally applies after positive newborn screening when sweat chloride is below 30 mmol/L with 2 CFTR variants, at least 1 of uncertain consequence, or when chloride is 30–59 mmol/L with no more than 1 CF-causing variant. The infant should not have clinical features establishing CF. A symptomatic child or an adult with borderline chloride needs a different diagnostic framing.
The 2024 Cystic Fibrosis Foundation guideline recommends repeat sweat chloride at 6 months and annually through at least age 8 for children with CRMS/CFSPID (Green et al., 2024). Fewer than 10% are reclassified as CF in the evidence summarized by that guideline, although individual risk varies. That estimate describes a defined screened population—not all children with intermediate chloride.
For screen-positive newborns, diagnostic sweat testing is generally arranged after 10 days of age and ideally by 4 weeks, when the infant is over 2 kg and at least 36 weeks corrected gestational age. Feeding, stool pattern, and weight gain help determine urgency. Our explanation of pediatric growth assessment addresses broader growth questions; a borderline sweat result does not itself justify growth-hormone testing.
Ko pieaugušajiem nozīmē robežvērtību sviedru hlorīds?
Sweat chloride levels 30–59 mmol/L are intermediate in adults, just as they are in children. Persistent intermediate results deserve particular attention when there is unexplained bronchiectasis, recurrent pancreatitis, chronic sinus disease with other suggestive features, or obstructive infertility. Adult diagnosis is possible; age alone does not exclude cystic fibrosis.
Imagine an illustrative 34-year-old with chloride of 44 mmol/L, repeated pancreatitis, and otherwise normal routine blood chemistry. The normal metabolic panel does not settle the CFTR question, because it measures neither sweat-duct transport nor pancreatic duct function. A specialist might pursue extended genetics and pancreatic assessment while also checking more common causes of recurrent pancreatitis.
Bronchiectasis has several possible causes, and 1 intermediate sweat result should not end that investigation. Depending on the history, clinicians may evaluate immune deficiency, aspiration, ciliary disorders, and other inherited respiratory conditions. Our guide to alfa-1 antitripsīna testēšanu discusses a different inherited lung-risk pathway; it is complementary only when the clinical pattern supports testing.
Male infertility can occasionally be the first clue to CFTR-associated disease, especially when congenital absence of the vas deferens causes obstruction. A sperm count of 0 is not enough to establish that anatomy or a CF diagnosis, and hormonal explanations require different evaluation. Our semen analysis interpretation guide explains why reproductive assessment must accompany—not be replaced by—CFTR testing.
Vai savākšanas problēmas var padarīt rezultātu maldinošu?
Collection problems can make sweat chloride results unreliable, and insufficient sweat is not a negative test. Evaporation, contamination, incorrect handling, and inadequate sample volume can interfere with interpretation. Before drawing conclusions from a borderline result, confirm that the laboratory performed quantitative chloride analysis on an acceptable sample.
Common minimum quantities are 75 mg for gauze or filter-paper collection and 15 µL for a Macroduct collection system; collection generally lasts no more than 30 minutes. Samples from separate sites should not be pooled to reach the minimum. The Cystic Fibrosis Foundation sweat-testing guidance describes these collection safeguards because an apparently precise number cannot rescue an inadequate specimen (LeGrys et al., 2007).
A report marked QNS—quantity not sufficient—means no reliable diagnostic concentration was obtained. If one arm yields an acceptable sample and the other does not, the center should explain which result is valid; the unsuccessful site is not a second negative measurement. Likewise, conflicting bilateral values should prompt a quality review rather than an improvised average that hides disagreement.
Copied reports introduce another avoidable problem: 35 mmol/L can become 85 mmol/L through transcription or image-reading error. Our PDF transkripcijas kontrolsaraksts is useful for verifying numbers against the original report, not for validating the sweat procedure. Kantesti’s klīniskie standarti un ierobežojumi should also be distinguished from accreditation of the laboratory that collected and measured the sweat.
Kad testēšana jāatkārto akreditētā centrā?
An intermediate sweat chloride result generally warrants repeat quantitative testing within 1–2 months at an accredited CF center or an appropriately accredited laboratory experienced in sweat testing. Earlier specialist assessment is appropriate for symptomatic infants, poor growth, recurrent pancreatitis, or significant respiratory concerns. Persistent uncertainty should not be managed through repeated low-quality collections.
The right center depends on your country: CF-center accreditation and laboratory accreditation are related but not identical. Ask whether the laboratory regularly performs pediatric and adult sweat chloride testing, monitors insufficient-sample rates, and uses quantitative chloride rather than conductivity alone. For a result of 46 mmol/L, an experienced collection team may be more useful than choosing a laboratory solely for convenience.
Repeat tests can cross categories because of biological and analytical variation. Values of 29 and 33 mmol/L on separate dates deserve context; they do not prove that CFTR function suddenly deteriorated. Our discussion of laboratory changes over time explains the general distinction between variation and disease progression, although sweat testing has its own collection requirements.
For a valid repeat, follow the center’s instructions, maintain normal hydration, and avoid lotions or creams on the collection site. Do not fast, overdrink water, or stop prescribed medicines unless instructed; disclose all medicines, especially CFTR modulators. If the first sample was QNS, the repeat may simply be the first interpretable test—not a confirmation of any earlier diagnostic category.
Kad ir piemērota CFTR gēnu izvērtēšana?
CFTR genetic evaluation is appropriate when sweat chloride remains intermediate, newborn screening is abnormal, family history is relevant, or characteristic symptoms persist despite a low result. Testing may need to extend beyond a common-variant panel to sequencing and deletion/duplication analysis. A negative limited panel cannot exclude all clinically relevant CFTR variants.
Finding 2 variants is not automatically equivalent to finding 2 CF-causing variants. Classification matters, and the variants usually need to be on opposite gene copies—in trans—to support the recessive diagnostic explanation. Parental testing can help establish phase; 2 variants on the same copy, in cis, leave the other copy unresolved.
A variant of uncertain significance cannot be promoted to a disease-causing finding simply because sweat chloride is 41 mmol/L. Specialists combine curated variant evidence, the phenotype, family testing, and sometimes functional assessment. Genetic counseling should explain what the result establishes, what it leaves unanswered, and whether relatives or a reproductive partner need targeted evaluation.
Kantesti is an AI blood test interpretation platform, not a CFTR variant-classification laboratory. Our AI tehnoloģijas paskaidrojums describes how laboratory information is organized, but 1 unresolved genetic finding requires qualified interpretation rather than an automated disease label. When I review accompanying chemistry, I treat the genetic report as a separate evidence source with its own method, coverage, and limitations.
Kādus papildu testus var veikt, lai precizētu nenoteiktu rezultātu?
Specialist CFTR functional tests can help when sweat chloride and genetics remain inconclusive. Nasal potential difference assesses ion transport in nasal epithelium, while intestinal current measurement assesses transport in intestinal tissue. These tests require validated protocols at experienced reference centers; they are not routine blood tests or interchangeable screening tools.
The 2017 consensus recommends that nasal potential difference and intestinal current measurement be performed in validated reference centers when needed for diagnosis (Farrell et al., 2017). Availability varies internationally, and 1 abnormal functional measurement must be interpreted using the center’s protocol and clinical context. Referral is often more sensible than asking a general laboratory to improvise an unfamiliar assay.
Organ-specific tests answer different questions. Fecal elastase below 200 µg/g can suggest pancreatic exocrine insufficiency, but a watery sample may dilute the measurement and a normal result does not exclude pancreatic-sufficient CF. Our izkārnījumu elastāzes interpretācijas ceļvedis explains those limitations; pancreatic status is evidence about organ function, not a substitute for establishing CFTR-related diagnosis.
Fat malabsorption may also justify stool-fat assessment, with collection and dietary requirements determined by the laboratory. Adult fecal fat above about 7 g/day on an appropriate standardized intake suggests steatorrhea, but the cause may be pancreatic, intestinal, or biliary. Our fecal fat result guide helps separate documenting malabsorption from naming its cause.
Vai citas slimības vai medikamenti var ietekmēt sviedru hlorīdu?
Technical problems and some non-CF conditions can produce elevated or intermediate sweat chloride, while medicines can affect sweat production or CFTR function. Severe malnutrition, untreated hypothyroidism, and adrenal insufficiency are among reported non-CF associations. These possibilities require a clinically directed assessment; they should not become an excuse to dismiss a valid result of 60 mmol/L or higher.
Adrenal insufficiency deserves consideration when fatigue, weight loss, low blood pressure, pigmentation changes, or abnormal electrolytes accompany the diagnostic question. A sweat value of 48 mmol/L alone does not justify a cortisol workup, but the combined pattern may. Our guide to adrenal insufficiency warning signs explains when symptoms make that alternative urgent.
Malnutrition can be a confounder and also a consequence of an underlying disorder, so correcting nutrition does not automatically resolve the CF question. A child with 43 mmol/L and chronic diarrhea may need evaluation for celiac disease or another malabsorption cause as well as CFTR assessment. Our explanation of IgA-related celiac testing pitfalls is relevant when negative celiac antibodies conflict with a suggestive history.
CFTR modulators can lower sweat chloride because they improve channel function; a treated value below 30 mmol/L does not erase an established CF diagnosis. Drugs that reduce sweating, such as topiramate in some patients, can make adequate collection harder without providing a reliable prediction of chloride concentration. Give the center a complete medication list, and never stop treatment just to produce an untreated number.
Ko vajadzētu darīt ģimenēm, kamēr diagnoze nav skaidra?
While a borderline result is being clarified, keep specialist follow-up, monitor relevant symptoms, and avoid starting CF-specific treatment without an indication. A sweat chloride value of 30–59 mmol/L does not justify routine pancreatic enzymes, antibiotics, high-dose vitamins, or extra salt on its own. Supportive care should address demonstrated problems rather than a provisional label.
Bring the original sweat report, newborn-screening record if applicable, genetic report, medication list, and growth measurements to the appointment. Recording 2–3 concrete observations—such as stool frequency, weight trend, or repeated chest illnesses—is usually more useful than an exhaustive diary. Ask who will arrange the repeat test and who will explain a result that remains intermediate.
Nutrition testing should be driven by symptoms and growth, not by the sweat number alone. Iron deficiency can accompany restricted intake or malabsorption, but a ferritin result does not confirm CF; iron treatment also needs an appropriate indication. Our complete iron studies guide explains how to distinguish low stores from inflammation-related changes when a clinician requests that assessment.
Routine chemistry can help assess complications: low chloride and bicarbonate elevation may accompany salt depletion, while low albumin needs a separate nutritional, hepatic, or protein-loss explanation. Our seruma olbaltumvielu interpretācijas ceļvedis provides that context. Seek urgent care for breathing difficulty, marked lethargy, repeated vomiting, or substantially reduced urination—do not wait 1–2 months for the planned sweat retest.
Kā jāskaidro un jādokumentē rezultāts?
A useful sweat chloride explanation records the exact value, units, collection quality, clinical context, and next diagnostic step. As of October 8, 2026, this article uses the 2017 CF diagnostic consensus and the 2024 CRMS/CFSPID management guideline—not a newly invented 2026 cutoff. The central distinction remains unchanged: intermediate is not confirmed CF.
For a result of 42 mmol/L, a clear clinical note might say: intermediate quantitative sweat chloride, adequate sample, CF diagnosis unresolved, repeat at an experienced center and review CFTR testing. That wording is more useful than possible CF without a plan. If the repeat is below 30 mmol/L but symptoms remain concerning, the note should explain why investigation is continuing.
Kantesti is an AI lab test interpretation service that can help explain accompanying blood chemistry, but cannot confirm cystic fibrosis from sweat chloride or genetics. At Kantesti, the safe boundary is to distinguish report explanation from specialist diagnosis; our medical advisory responsibilities describe the role of clinical oversight. A value of 60 mmol/L or higher should trigger a clinical pathway, not an AI-generated treatment prescription.
As Thomas Klein, MD, my practical recommendation is to ask 3 questions: was the specimen valid, does the clinical story fit, and what evidence will resolve the uncertainty? The related Zenodo publications below address general laboratory interpretation, not sweat chloride diagnostic validation. The CF-specific external references are the sources supporting the thresholds, confirmation strategy, and follow-up recommendations in this article.
Bieži uzdotie jautājumi
Vai robežvērtība sviedru hlorīdos nozīmē cistisko fibrozi?
Robežvērtīga sviedru hlorīdu rezultāts 30–59 mmol/L pats par sevi nediagnosticē cistisko fibrozi. Šis intervāls sakrīt ar cilvēkiem ar CF, citām ar CFTR saistītām slimībām un bez CFTR traucējumiem. Ir piemēroti atkārtoti kvantitatīvi izmeklējumi pieredzējušā centrā, simptomu un skrīninga pārskatīšana un dažreiz arī paplašināta CFTR izvērtēšana. Pat 2 starpposma rezultāti prasa papildu interpretāciju, nevis automātisku diagnozi.
Kāds ir pozitīvs sviedru hlorīdu testa rezultāts?
Kvantitatīva sviedru hlorīdu koncentrācija 60 mmol/L vai augstāka ir pozitīvajā diagnostikas diapazonā un atbalsta cistisko fibrozi ar saderīgām klīniskām pazīmēm, jaundzimušo skrīningu vai ģimenes anamnēzi. Paraugam jāatbilst savākšanas un analītiskajām prasībām. Speciālistu apstiprināšana parasti ietver atkārtotu testēšanu citā datumā vai neatkarīgu diagnostikas metodi. Pozitīvs sviedru vadītspējas skrīnings nav savstarpēji aizstājams ar pozitīvu kvantitatīva hlorīda rezultātu.
Vai 35 mmol/l sviedru hlorīdu rezultāts ir normāls pieaugušam cilvēkam?
35 mmol/L sviedru hlorīdu rezultāts ir starpējs pieaugušajam saskaņā ar 2017. gada "Cystic Fibrosis Foundation" diagnostikas konsensu. Pašreizējās kategorijas ir zem 30 mmol/L, 30–59 mmol/L un vismaz 60 mmol/L visām vecuma grupām. Dažās agrākās laboratorijas diapazonās pēc zīdaiņa vecuma starpējo robežu noteica 40 mmol/L. Tāpēc pieaugušajam 35 mmol/L rezultāts jāpārskata klīniskā kontekstā, nevis jāignorē, izmantojot novecojušu intervālu.
Cik drīz jāatkārto starpposma sviedru tests?
Vidēji sviedru hlorīdu rezultāti no 30–59 mmol/L parasti prasa atkārtotu kvantitatīvu testēšanu 1–2 mēnešu laikā pieredzējušā, atbilstoši akreditētā centrā. Simptomātiskiem zīdaiņiem, slikta augšana vai nopietnas elpošanas ceļu vai aizkuņģa dziedzera problēmas prasa agrāku speciālista novērtēšanu. Bērni, kas īpaši norādīti kā CRMS/CFSPID, seko ilgtermiņa grafikam, kas ietver atkārtotu sviedru testēšanu 6 mēnešu vecumā un reizi gadā līdz vismaz 8 gadu vecumam. Diagnozes atkārtošana un turpmākā uzraudzība kalpo dažādiem mērķiem.
Vai cistiskā fibroze var rasties ar sviedru hlorīdu zem 30?
Cistiskā fibroze var retumis rasties ar sviedru hlorīdu zem 30 mmol/L, īpaši, ja noteiktas CFTR varianti saglabā sviedru kanāliņu funkciju. Zems rezultāts padara CF mazāk ticamu, taču to pilnībā neizslēdz, ja simptomi vai ģenētika ir ļoti liecinoši. Pastāvīga bronhektāze, atkārtots pankreatīts vai neizskaidrojama malabsorbcija var attaisnot tālāku speciālista izvērtēšanu. Ir jāapstiprina arī pietiekams paraugs un pareizā kvantitatīvā metode.
Vai viena CFTR mutācija izskaidro robežvērtību sviedru testu?
Viens identificēts ar CP saistīts CFTR variants pats par sevi nenosaka cistisko fibrozi vai pilnībā neizskaidro sviedru hlorīdu rezultātu 30–59 mmol/L. Ierobežots paneļa tests var nenosaka citu variantu, un klīniskajiem simptomiem var būt cits cēlonis. Ja aizdomas saglabājas, var būt nepieciešama paplašināta sekvenču analīze, delēciju/duplikāciju analīze un ģenētiskās konsultācijas. Ja tiek atrasti 2 varianti, svarīga ir to klasifikācija un tas, vai tie atrodas pretējās gēnu kopijās.
Ko nozīmē “quantity not sufficient” sviedru testā?
Daudzums nav pietiekams, vai arī QNS (Quantity not sufficient), nozīmē, ka sviedru savākts pārāk maz, lai iegūtu uzticamu diagnostikas rezultātu. Parastais minimālais daudzums ir 15 µL Macroduct savākšanai vai 75 mg marles vai filtrpapīra savākšanai. QNS nav negatīvs sviedru hlorīdu tests un nevar izslēgt cistisko fibrozi. Nepieciešama atkārtota savākšana, un atsevišķas savākšanas vietas nedrīkst apvienot, lai sasniegtu minimumu.
Iegūstiet AI vadītu asins analīžu analīzi jau šodien
Pievienojieties vairāk nekā 2 miljoniem lietotāju visā pasaulē, kuri uzticas Kantesti tūlītējai, precīzai laboratorijas analīžu interpretācijai. Augšupielādējiet savas asins analīzes rezultātus un dažu sekunžu laikā saņemiet visaptverošu 15,000+ biomarķieru interpretāciju.
📚 Atsauces pētniecības publikācijas
Kleins, T., Mičels, S., un Vēbers, H. (2026). Urobilinogēns urīna analīzē: pilnīgs urīna analīzes ceļvedis 2026. Kantesti AI Medicīnas pētījumi.
Kleins, T., Mičels, S., un Vēbers, H. (2026). Dzelzs pētījumu ceļvedis: TIBC, dzelzs piesātinājums un saistīšanās spēja. Kantesti AI Medicīnas pētījumi.
📖 Ārējās medicīniskās atsauces
Green DM et al. (2024). Cystic Fibrosis Foundation Evidence-Based Guideline for the Management of CRMS/CFSPID. Pediatrics.
LeGrys VA et al. (2007). Diagnostic Sweat Testing: The Cystic Fibrosis Foundation Guidelines. Žurnāls Pediatrics.
⚕️ Medicīniskā atruna
Šis raksts ir paredzēts tikai izglītojošiem nolūkiem un nav medicīnisks padoms. Vienmēr konsultējieties ar kvalificētu veselības aprūpes speciālistu, lai pieņemtu lēmumus par diagnostiku un ārstēšanu.
E-E-A-T uzticēšanās signāli
Pieredze
Ārstu vadīta klīniskā laboratorijas interpretācijas darbplūsmu pārskatīšana.
Ekspertīze
Laboratorijas medicīnas fokuss uz to, kā biomarķieri uzvedas klīniskā kontekstā.
Autoritāte
Sagatavojis Dr. Thomas Klein, pārskatījusi Dr. Sarah Mitchell un prof. Dr. Hans Weber.
Uzticamība
Uz pierādījumiem balstīta interpretācija ar skaidriem turpmākās rīcības ceļiem, lai mazinātu trauksmi.