Chan eil toraidhean clòraid fallais air crìoch 30–59 mmol/L a’ dearbhadh fibrosis ciostach. Tha e a’ ciallachadh gum feumar an toradh a leantainn suas: mar as trice ath-dheuchainn aig ionad le eòlas, sgrùdadh air comharran agus sgrìonadh ùr-bhreith, agus uaireannan measadh ginteil no gnìomhach CFTR.


- Clòraid fallais ìosal: Tha nas lugha na 30 mmol/L a’ dèanamh fibrosis ciostach nas dualtaich, ach chan eil e ga chuir às gu tur nuair a tha comharran no gintinneachd gu làidir a’ moladh.
- Clòraid fallais meadhanach: Tha ìrean de 30–59 mmol/L neo-chinnteach - chan e dearbhadh fibrosis ciostach a th’ ann agus chan e toradh neach-giùlan gu fèin-ghluasadach.
- Clòraid fallais àrd: Tha toradh dligheach de 60 mmol/L no nas àirde a’ toirt taic do fibrosis ciostach san t-suidheachadh clionaigeach iomchaidh agus feumar dearbhadh bho eòlaiche.
- Ath-dheuchainn: Mar as trice feumaidh toradh meadhanach deuchainn clòraid fallais eile taobh a-staigh 1–2 mìosan, le measadh nas tràithe airson ùr-bhreith le comharraidhean no comharran draghail.
- A h-uile aois: Tha crìochan dearbhaidh gnàthach an Cystic Fibrosis Foundation a’ cleachdadh nas lugha na 30, 30–59, agus co-dhiù 60 mmol/L airson ùr-bhreith, clann, agus daoine v.
- Càileachd cruinneachaidh: Chan urrainnear sampall fallais gu leòr aithris mar thoradh àicheil earbsach; cha bu chòir làraichean cruinneachaidh fa-leth a bhith air an cur còmhla.
- Measadh CFTR: Faodaidh toraidhean eadar-mheadhanach leantainneach, comharraidhean a tha a’ nochdadh, no sgrìonadh ùr-bhreith neo-àbhaisteach a bhith a’ fìreanachadh sreathadh, mion-sgrùdadh dùblachadh / sguabadh às, agus comhairleachadh ginteil.
- Crìochan AI: Tomhaisidh clòraid fallais fallas, chan e fuil. Chan urrainn mìneachadh AI de na toraidhean obair-lann a tha a’ leantainn a bhith a’ stèidheachadh no a’ dùnadh a-mach mòr-dhruim.
Dè tha toraidhean ìosal, meadhanach, agus àrd a’ ciallachadh?
Bidh toraidhean deuchainn clòraid fallais fo 30 mmol/L a’ dèanamh mòr-dhruim nas dualtaiche; tha 30–59 mmol/L eadar-mheadhanach; agus tha 60 mmol/L no nas àirde a’ toirt taic do mhòr-dhruim anns an t-suidheachadh clionaigeach cheart. Tha toradh cainnt na adhbhar airson sgrùdadh a dhèanamh—chan e breithneachadh, sgòr dian, no adhbhar airson tòiseachadh air làimhseachadh leat fhèin.
Tha dùil-rùin Chomann Mòr-dhruim 2017 a’ cur an trì bunaitean seo an sàs thar aoisean, an àite a bhith a’ cleachdadh crìoch eadar-mheadhanach nas àirde airson clann nas sine agus inbhich (Farrell et al., 2017). Tha cuid de aithisgean nas sine fhathast a’ toirt cunntas air 40–59 mmol/L mar chàraich às deidh leanabachd; cha bu chòir toradh de 35 mmol/L a dhiùltadh dìreach leis gu bheil raon iomraidh seann-fhasanta ga ghairm mar àbhaisteach.
Tha toradh de 59 mmol/L agus aon de 60 mmol/L a’ tuiteam a-steach do dhiofar roinnean, ach chan eil bith-eòlas ag atharrachadh gu h-obann eadar na h-àireamhan sin. Tha càileachd cruinneachaidh, comharraidhean, eachdraidh sgrìonaidh, agus ath-thomhas a’ dearbhadh dè cho misneachail ‘s as urrainnear an roinn a chleachdadh. Ar mìneachadh de brataichean obair-lann taobh a-muigh raon a’ mìneachadh carson nach e breithneachadh a th’ ann an àireamh air a chomharrachadh leis fhèin.
Is mise Thomas Klein, MD, Prìomh Oifigear Meidigeach aig Kantesti, agus is e an frèam clionaigeach agam an tomhas a sgaradh bhon bhreithneachadh mus beachdaich mi air gin dhiubh. Is e inneal-anailisidh deuchainn fala AI a th’ ann an Kantesti; is e deuchainn speisealaichte air leth a th’ ann an clòraid fallais, chan e biomarker fala. Tha ar buidheann agus dleastanas clionaigeach a’ mìneachadh an eadar-dhealachaidh sin, a tha cudromach gu sònraichte nuair a luchdaicheas cuideigin suas aithisg obair-lann measgaichte.
Dè a tha an deuchainn clòraid fallais a’ tomhas?
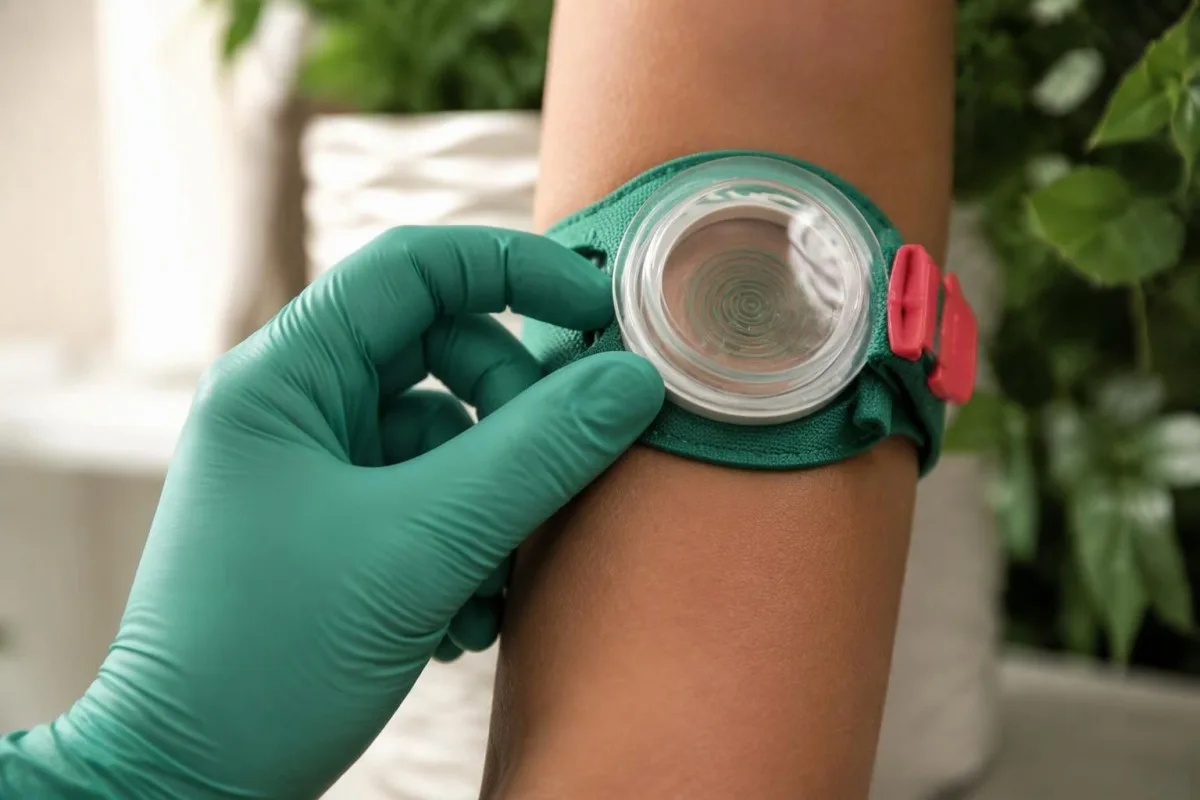
Bidh an deuchainn clòraid fallais a’ tomhas dùmhlachd clòraid ann am fallas às deidh do pilocarpine àite cruinneachaidh beag a bhrosnachadh. Bidh e a’ measadh aon bhuile air gnìomhachadh chanàl CFTR: dè cho èifeachdach ‘s a tha an duct fallais a’ ath-ghabhail clòraid mus ruig fallas an uachdar. Thèid an toradh breithneachaidh aithris ann am mmol/L, chan ann mar uiread de fhalais a chaidh a thoirt a-mach.
The sweat gland first produces fluid, and its duct then reabsorbs salt. Reduced CFTR function can leave more chloride in the final sweat, producing values of 60 mmol/L or higher in many people with cystic fibrosis. This is a functional clue, but it does not directly measure lung damage, pancreatic function, or the number of genetic variants present.
Sweat chloride and serum chloride describe different compartments. A person can have elevated sweat chloride while the chloride concentration in a metabolic panel is normal—or low after substantial salt loss. Our discussion of serum chloride and fluids concerns blood chemistry; its reference intervals cannot be substituted for the 30–59 mmol/L sweat interval.
The units can also look different without representing different thresholds: for chloride, 1 mmol/L equals 1 mEq/L because chloride has a single electrical charge. Sweat conductivity is another matter—it reflects multiple ions, often expressed as sodium chloride equivalents. A conductivity result must not be interpreted using diagnostic sweat chloride thresholds, even when the report looks reassuringly numerical.
Carson nach eil toradh meadhanach a’ dearbhadh fibrosis ciostach?
An intermediate sweat chloride result does not confirm cystic fibrosis because 30–59 mmol/L overlaps several clinical situations. These include some people with cystic fibrosis, people with other CFTR-associated conditions, and people without a CFTR disorder. The same value can therefore lead to different conclusions depending on the evidence around it.
For an illustrative comparison, consider a thriving infant with 38 mmol/L after newborn screening and an adult with 38 mmol/L plus recurrent pancreatitis and bronchiectasis. Neither number independently proves cystic fibrosis, but the second history raises different diagnostic questions. This is why I would not attach a single percentage probability to every borderline sweat chloride test without knowing the referral context.
Persistent intermediate results on 2 separate occasions can still occur in cystic fibrosis, and the 2017 consensus recommends considering extended CFTR analysis or specialized functional testing in that setting (Farrell et al., 2017). Conversely, 2 intermediate measurements do not automatically convert uncertainty into a confirmed diagnosis. Repetition establishes persistence; it does not explain the cause by itself.
Borderline is also not another word for carrier. A person with 1 identified CF-causing variant may be a carrier, but the initial genetic panel might have missed another variant, or the symptoms may have another explanation. Our discussion of borderline stool test follow-up illustrates the broader distinction between an indeterminate measurement and a named disease; the follow-up tests themselves are different.
Dè a dh’ fheumas toradh fallais adhartach a leantainn?
A properly collected sweat chloride result of at least 60 mmol/L supports a cystic fibrosis diagnosis when there is compatible newborn screening, a relevant family history, or characteristic clinical features. Specialist assessment should follow promptly. Confirmation usually uses repeat testing on a separate date or an independent diagnostic method, such as appropriate CFTR analysis.
A report saying sweat chloride test positive deserves more than a telephone message reading only the flag. Ask for the actual concentration, the collection method, whether the sample was sufficient, and the plan for confirmation. A measured chloride of 72 mmol/L is meaningful evidence; a positive conductivity screening result is not an interchangeable diagnostic finding.
The distinction between a category and a concentration matters at both ends of the scale. Chloride concentrations above roughly 160 mmol/L are outside the expected physiological range for sweat and should trigger immediate laboratory review rather than assumptions about unusually severe disease. The collection and analytical record may be more informative than another decimal place on the report.
Positive-range sweat chloride is not, by itself, an emergency severity score. A clinically stable child with 68 mmol/L needs a timely CF specialist pathway; a child with dehydration or breathing difficulty needs urgent care regardless of the sweat value. Our guide to toraidhean càileachdail agus cainneachdail explains why the measured number should accompany the positive label.
An urrainn do thoradh ìosal fibrosis ciostach a chuir às?
Sweat chloride below 30 mmol/L makes cystic fibrosis less likely, but cannot absolutely exclude it when symptoms or CFTR findings are strongly suggestive. A low result is most reassuring when the sample was valid, the person has no characteristic symptoms, and the screening or family-history concern has been adequately addressed.
Certain CFTR variants preserve enough sweat-duct function to produce lower chloride concentrations despite clinically relevant disease. The 2017 consensus therefore allows further evaluation when a value below 30 mmol/L conflicts with genotype or evolving clinical features (Farrell et al., 2017). A normal newborn screen also does not eliminate every possible CF diagnosis in a child who later develops suggestive symptoms.
Age does not create a separate low-result exception: a value of 27 mmol/L has the same diagnostic category in a toddler and an adult. What changes is the history available to interpret it—growth trajectory in a young child, for example, versus years of recurrent pancreatitis or unexplained bronchiectasis in an adult. The referral question should travel with the laboratory result.
A child with 24 mmol/L, persistent greasy stools, and faltering growth still needs an explanation for the symptoms, even if cystic fibrosis becomes less likely. The next step may include pancreatic, gastrointestinal, or nutritional assessment rather than simply repeating every test. Our guidance on crìochan mìneachaidh AI chloinne explains why pediatric decisions require age-specific clinical oversight.
Ciamar a thèid toraidhean meadhanach a làimhseachadh às deidh sgrìonadh ùr-bhreith?
An infant with an abnormal newborn screen and intermediate sweat chloride needs assessment through a CF specialist pathway, but may not have cystic fibrosis. Some clinically well infants receive the designation CRMS/CFSPID, meaning the screening and diagnostic findings remain inconclusive. This designation has specific criteria; it should not be applied to every borderline result.
CRMS/CFSPID generally applies after positive newborn screening when sweat chloride is below 30 mmol/L with 2 CFTR variants, at least 1 of uncertain consequence, or when chloride is 30–59 mmol/L with no more than 1 CF-causing variant. The infant should not have clinical features establishing CF. A symptomatic child or an adult with borderline chloride needs a different diagnostic framing.
The 2024 Cystic Fibrosis Foundation guideline recommends repeat sweat chloride at 6 months and annually through at least age 8 for children with CRMS/CFSPID (Green et al., 2024). Fewer than 10% are reclassified as CF in the evidence summarized by that guideline, although individual risk varies. That estimate describes a defined screened population—not all children with intermediate chloride.
For screen-positive newborns, diagnostic sweat testing is generally arranged after 10 days of age and ideally by 4 weeks, when the infant is over 2 kg and at least 36 weeks corrected gestational age. Feeding, stool pattern, and weight gain help determine urgency. Our explanation of pediatric growth assessment addresses broader growth questions; a borderline sweat result does not itself justify growth-hormone testing.
Dè a tha clòraid fallais air crìoch a’ ciallachadh ann an daoine v?
Sweat chloride levels 30–59 mmol/L are intermediate in adults, just as they are in children. Persistent intermediate results deserve particular attention when there is unexplained bronchiectasis, recurrent pancreatitis, chronic sinus disease with other suggestive features, or obstructive infertility. Adult diagnosis is possible; age alone does not exclude cystic fibrosis.
Imagine an illustrative 34-year-old with chloride of 44 mmol/L, repeated pancreatitis, and otherwise normal routine blood chemistry. The normal metabolic panel does not settle the CFTR question, because it measures neither sweat-duct transport nor pancreatic duct function. A specialist might pursue extended genetics and pancreatic assessment while also checking more common causes of recurrent pancreatitis.
Bronchiectasis has several possible causes, and 1 intermediate sweat result should not end that investigation. Depending on the history, clinicians may evaluate immune deficiency, aspiration, ciliary disorders, and other inherited respiratory conditions. Our guide to deuchainn alpha-1 antitrypsin discusses a different inherited lung-risk pathway; it is complementary only when the clinical pattern supports testing.
Male infertility can occasionally be the first clue to CFTR-associated disease, especially when congenital absence of the vas deferens causes obstruction. A sperm count of 0 is not enough to establish that anatomy or a CF diagnosis, and hormonal explanations require different evaluation. Our semen analysis interpretation guide explains why reproductive assessment must accompany—not be replaced by—CFTR testing.
An urrainn do dhuilgheadasan cruinneachaidh an toradh a dhèanamh ceàrr?
Collection problems can make sweat chloride results unreliable, and insufficient sweat is not a negative test. Evaporation, contamination, incorrect handling, and inadequate sample volume can interfere with interpretation. Before drawing conclusions from a borderline result, confirm that the laboratory performed quantitative chloride analysis on an acceptable sample.
Common minimum quantities are 75 mg for gauze or filter-paper collection and 15 µL for a Macroduct collection system; collection generally lasts no more than 30 minutes. Samples from separate sites should not be pooled to reach the minimum. The Cystic Fibrosis Foundation sweat-testing guidance describes these collection safeguards because an apparently precise number cannot rescue an inadequate specimen (LeGrys et al., 2007).
A report marked QNS—quantity not sufficient—means no reliable diagnostic concentration was obtained. If one arm yields an acceptable sample and the other does not, the center should explain which result is valid; the unsuccessful site is not a second negative measurement. Likewise, conflicting bilateral values should prompt a quality review rather than an improvised average that hides disagreement.
Copied reports introduce another avoidable problem: 35 mmol/L can become 85 mmol/L through transcription or image-reading error. Our clàr-obrach clò-bhualadh PDF is useful for verifying numbers against the original report, not for validating the sweat procedure. Kantesti’s inbhean clionaigeach agus crìochan should also be distinguished from accreditation of the laboratory that collected and measured the sweat.
Cuin a bu chòir deuchainn ath-aithris aig ionad barrantaichte?
An intermediate sweat chloride result generally warrants repeat quantitative testing within 1–2 months at an accredited CF center or an appropriately accredited laboratory experienced in sweat testing. Earlier specialist assessment is appropriate for symptomatic infants, poor growth, recurrent pancreatitis, or significant respiratory concerns. Persistent uncertainty should not be managed through repeated low-quality collections.
The right center depends on your country: CF-center accreditation and laboratory accreditation are related but not identical. Ask whether the laboratory regularly performs pediatric and adult sweat chloride testing, monitors insufficient-sample rates, and uses quantitative chloride rather than conductivity alone. For a result of 46 mmol/L, an experienced collection team may be more useful than choosing a laboratory solely for convenience.
Repeat tests can cross categories because of biological and analytical variation. Values of 29 and 33 mmol/L on separate dates deserve context; they do not prove that CFTR function suddenly deteriorated. Our discussion of laboratory changes over time explains the general distinction between variation and disease progression, although sweat testing has its own collection requirements.
For a valid repeat, follow the center’s instructions, maintain normal hydration, and avoid lotions or creams on the collection site. Do not fast, overdrink water, or stop prescribed medicines unless instructed; disclose all medicines, especially CFTR modulators. If the first sample was QNS, the repeat may simply be the first interpretable test—not a confirmation of any earlier diagnostic category.
Cuin a tha measadh ginteil CFTR iomchaidh?
CFTR genetic evaluation is appropriate when sweat chloride remains intermediate, newborn screening is abnormal, family history is relevant, or characteristic symptoms persist despite a low result. Testing may need to extend beyond a common-variant panel to sequencing and deletion/duplication analysis. A negative limited panel cannot exclude all clinically relevant CFTR variants.
Finding 2 variants is not automatically equivalent to finding 2 CF-causing variants. Classification matters, and the variants usually need to be on opposite gene copies—in trans—to support the recessive diagnostic explanation. Parental testing can help establish phase; 2 variants on the same copy, in cis, leave the other copy unresolved.
A variant of uncertain significance cannot be promoted to a disease-causing finding simply because sweat chloride is 41 mmol/L. Specialists combine curated variant evidence, the phenotype, family testing, and sometimes functional assessment. Genetic counseling should explain what the result establishes, what it leaves unanswered, and whether relatives or a reproductive partner need targeted evaluation.
Kantesti is an AI blood test interpretation platform, not a CFTR variant-classification laboratory. Our mìneachadh teicneòlas AI describes how laboratory information is organized, but 1 unresolved genetic finding requires qualified interpretation rather than an automated disease label. When I review accompanying chemistry, I treat the genetic report as a separate evidence source with its own method, coverage, and limitations.
Dè na deuchainnean a bharrachd a dh’ fhaodas toradh neo-chinnteach a shoilleireachadh?
Specialist CFTR functional tests can help when sweat chloride and genetics remain inconclusive. Nasal potential difference assesses ion transport in nasal epithelium, while intestinal current measurement assesses transport in intestinal tissue. These tests require validated protocols at experienced reference centers; they are not routine blood tests or interchangeable screening tools.
The 2017 consensus recommends that nasal potential difference and intestinal current measurement be performed in validated reference centers when needed for diagnosis (Farrell et al., 2017). Availability varies internationally, and 1 abnormal functional measurement must be interpreted using the center’s protocol and clinical context. Referral is often more sensible than asking a general laboratory to improvise an unfamiliar assay.
Organ-specific tests answer different questions. Fecal elastase below 200 µg/g can suggest pancreatic exocrine insufficiency, but a watery sample may dilute the measurement and a normal result does not exclude pancreatic-sufficient CF. Our stiùireadh eadar-mhìneachaidh elastase stòil explains those limitations; pancreatic status is evidence about organ function, not a substitute for establishing CFTR-related diagnosis.
Fat malabsorption may also justify stool-fat assessment, with collection and dietary requirements determined by the laboratory. Adult fecal fat above about 7 g/day on an appropriate standardized intake suggests steatorrhea, but the cause may be pancreatic, intestinal, or biliary. Our fecal fat result guide helps separate documenting malabsorption from naming its cause.
An urrainn do chumhachan no cungaidhean eile buaidh a thoirt air clòraid fallais?
Technical problems and some non-CF conditions can produce elevated or intermediate sweat chloride, while medicines can affect sweat production or CFTR function. Severe malnutrition, untreated hypothyroidism, and adrenal insufficiency are among reported non-CF associations. These possibilities require a clinically directed assessment; they should not become an excuse to dismiss a valid result of 60 mmol/L or higher.
Adrenal insufficiency deserves consideration when fatigue, weight loss, low blood pressure, pigmentation changes, or abnormal electrolytes accompany the diagnostic question. A sweat value of 48 mmol/L alone does not justify a cortisol workup, but the combined pattern may. Our guide to adrenal insufficiency warning signs explains when symptoms make that alternative urgent.
Malnutrition can be a confounder and also a consequence of an underlying disorder, so correcting nutrition does not automatically resolve the CF question. A child with 43 mmol/L and chronic diarrhea may need evaluation for celiac disease or another malabsorption cause as well as CFTR assessment. Our explanation of IgA-related celiac testing pitfalls is relevant when negative celiac antibodies conflict with a suggestive history.
CFTR modulators can lower sweat chloride because they improve channel function; a treated value below 30 mmol/L does not erase an established CF diagnosis. Drugs that reduce sweating, such as topiramate in some patients, can make adequate collection harder without providing a reliable prediction of chloride concentration. Give the center a complete medication list, and never stop treatment just to produce an untreated number.
Dè a bu chòir do theaghlaichean a dhèanamh fhad ‘s a tha an dearbhadh mì-chinnteach?
While a borderline result is being clarified, keep specialist follow-up, monitor relevant symptoms, and avoid starting CF-specific treatment without an indication. A sweat chloride value of 30–59 mmol/L does not justify routine pancreatic enzymes, antibiotics, high-dose vitamins, or extra salt on its own. Supportive care should address demonstrated problems rather than a provisional label.
Bring the original sweat report, newborn-screening record if applicable, genetic report, medication list, and growth measurements to the appointment. Recording 2–3 concrete observations—such as stool frequency, weight trend, or repeated chest illnesses—is usually more useful than an exhaustive diary. Ask who will arrange the repeat test and who will explain a result that remains intermediate.
Nutrition testing should be driven by symptoms and growth, not by the sweat number alone. Iron deficiency can accompany restricted intake or malabsorption, but a ferritin result does not confirm CF; iron treatment also needs an appropriate indication. Our complete iron studies guide explains how to distinguish low stores from inflammation-related changes when a clinician requests that assessment.
Routine chemistry can help assess complications: low chloride and bicarbonate elevation may accompany salt depletion, while low albumin needs a separate nutritional, hepatic, or protein-loss explanation. Our stiùireadh mìneachaidh pròtain serum provides that context. Seek urgent care for breathing difficulty, marked lethargy, repeated vomiting, or substantially reduced urination—do not wait 1–2 months for the planned sweat retest.
Ciamar a bu chòir an toradh a mhìneachadh agus a chlàradh?
A useful sweat chloride explanation records the exact value, units, collection quality, clinical context, and next diagnostic step. As of October 8, 2026, this article uses the 2017 CF diagnostic consensus and the 2024 CRMS/CFSPID management guideline—not a newly invented 2026 cutoff. The central distinction remains unchanged: intermediate is not confirmed CF.
For a result of 42 mmol/L, a clear clinical note might say: intermediate quantitative sweat chloride, adequate sample, CF diagnosis unresolved, repeat at an experienced center and review CFTR testing. That wording is more useful than possible CF without a plan. If the repeat is below 30 mmol/L but symptoms remain concerning, the note should explain why investigation is continuing.
Kantesti is an AI lab test interpretation service that can help explain accompanying blood chemistry, but cannot confirm cystic fibrosis from sweat chloride or genetics. At Kantesti, the safe boundary is to distinguish report explanation from specialist diagnosis; our medical advisory responsibilities describe the role of clinical oversight. A value of 60 mmol/L or higher should trigger a clinical pathway, not an AI-generated treatment prescription.
As Thomas Klein, MD, my practical recommendation is to ask 3 questions: was the specimen valid, does the clinical story fit, and what evidence will resolve the uncertainty? The related Zenodo publications below address general laboratory interpretation, not sweat chloride diagnostic validation. The CF-specific external references are the sources supporting the thresholds, confirmation strategy, and follow-up recommendations in this article.
Ceistean Bitheanta
A bheil clòr-uidhe na crìche a' ciallachadh galar dubhaig?
Chan an toradh clòraid fallais aig 30–59 mmol/L leis fhèin mar dhearbhadh air cladhach-fhallas. Tha an raon a' buntainn do dhaoine le cladhach-fhallas, tinneasan eile co-cheangailte ri CFTR, agus gun tinneas CFTR. Tha deuchainn cainnteach a-rithist ann an ionad eòlach, ath-sgrùdadh air comharran agus sgrìonadh, agus uaireannan measadh CFTR nas fharsainge, iomchaidh. Tha eadhon 2 toradh meadhanach a' cur feum air mìneachadh a bharrachd seach dearbhadh fèin-ghluasadach.
Dè tha toradh deimhinneach de dheuchainn clòraide sweat a' ciallachadh?
Tha dùmhlachd clòr-shail air a thomhas aig 60 mmol/L no nas àirde anns an raon dearbhaidh deimhinneach agus tha e a’ toirt taic do fibrosis ciùin le feartan clionaigeach freagarrach, sgrìonadh ùr-bhreith, no eachdraidh teaghlaich. Feumaidh an sampall coinneachadh ri riatanasan cruinneachaidh is anailis. Mar as trice bidh dearbhadh speisealaiche a’ toirt a-steach deuchainn ath-aithris air ceann-latha air leth no dòigh dearbhaidh neo-eisimeileach. Chan eil sgrìonadh dearbhaidh conductivity fallas eadar-ghluasadach le toradh clò-shail dearbhaidh.
A bheil toraidhean cloride fallais de 35 àbhaisteach ann an inbheach?
Tha toradh clòraide fallas de 35 mmol/L aig ìre eadar-mheadhanach ann an inbheach fon aonta breithneachaidh 2017 den Cystic Fibrosis Foundation. Tha na roinnean gnàthach nas ìsle na 30 mmol/L, 30–59 mmol/L, agus co-dhiù 60 mmol/L airson gach aois. Chleachd cuid de raointean obair-lann nas sine 40 mmol/L mar an crìoch eadar-mheadhanach às deidh leanabachd. Bu chòir do thoradh inbheach de 35 mmol/L mar sin ath-sgrùdadh ann an co-theacsa clionaigeach seach a bhith air a dhiùltadh a’ cleachdadh ùine a tha air a dhol à bith.
Cuin a bu chòir deuchainn fallas eadar-mheadhanach ath-aithris?
Leis an toradh meadhanach air chloride fallais de 30–59 mmol/L, mar as trice feumar deuchainn tomhasach ath-aithris taobh a-staigh 1–2 mìosan aig ionad le eòlas agus creideas iomchaidh. Bidh feum air measadh nas tràithe le speisealaiche airson pàistean le comharran, fàs bochd, no draghan mòra a thaobh anail no pancreas. Bidh clann a chaidh a chomharrachadh gu sònraichte mar CRMS/CFSPID a’ leantainn clàr nas fhaide a tha a’ toirt a-steach deuchainn fallais ath-aithris aig 6 mìosan agus gach bliadhna gu aois 8 co-dhiù. Tha an ath-aithris breithneachaidh agus an clàr sgrùdaidh leantainneach a’ frithealadh diofar adhbharan.
An urrainn a bhith aig fibrosis ciùin clòimh fallais fo 30?
Faodaidh fibrosis ciùin tachairt bho àm gu àm le clorid fallas nas ìsle na 30 mmol/L, gu sònraichte nuair a ghlèidheas cuid de sheòrsan CFTR gnìomh nan dùn fallas. Tha toradh ìosal a' dèanamh CF nas dualtaiche ach chan eil e ga dùnadh a-mach gu tur nuair a tha comharran no gintinneachd làidir a' moladh. Faodaidh làn-fhuilteachdan leantainneach, pancreatitis ath-chuairteach, no droch-ghabhail gun mhìneachadh a bhith a' dearbhadh tuilleadh measaidh speisealta. Feumar cuideachd dearbhadh gu bheil sampall gu leòr agus an dòigh tomhais cheart ann.
A bheil aon mhùthadh CFTR a' mìneachadh deuchainn fallas air a' chrìch?
Chan eil aon atharrachadh CFTR a tha ag adhbhrachadh CF, leis fhèin, a’ stèidheachadh mòr-chuinge no a’ mìneachadh gu tur toraidhean clorid fallas de 30–59 mmol/L. Faodaidh pannal cuingealaichte a bhith a dhìth air atharrachadh eile, agus faodaidh na comharran clionaigeach a bhith air adhbhar eile. Faodaidh ath-sgrùdadh leudaichte, mion-sgrùdadh dìth/dùblachaidh, agus comhairleachadh ginteil a bhith iomchaidh nuair a tha amharas ann fhathast. Ma lorgar 2 atharrachadh, tha an seòrsachadh aca agus an robh iad air leth-bhreacan de ghine mu choinneamh cudromach cuideachd.
Dè tha "meud gu leòr" a' ciallachadh air deuchainn fallais?
Chan eil gu leòr ann, no QNS, a’ ciallachadh gun deach glè bheag de shaillean a chruinneachadh gus toradh breithneachaidh earbsach a thoirt seachad. Tha na h-àireamhan as ìsle cumanta 15 µL airson cruinneachadh Macroduct no 75 mg airson cruinneachadh gasa no pàipear sìoltachain. Chan eil QNS na dheuchainn chloride seallaidh àicheil agus chan urrainn dha dùnadh a-mach galar nan dubhagan. Feumar cruinneachadh a-rithist, agus cha bu chòir làraichean cruinneachaidh fa leth a bhith air am measgachadh gus an ìre as ìsle a choileanadh.
Faigh Mion-sgrùdadh Deuchainn Fala le Cumhachd AI an-diugh
Thig còmhla ri còrr is 2 mhillean neach air feadh an t-saoghail a tha a’ earbsa Kantesti airson mion-sgrùdadh sa bhad, ceart air deuchainnean obair-lann. Luchdaich suas na toraidhean deuchainn fala agad agus faigh mìneachadh coileanta air biomarcair 15,000+ ann an diogan.
📚 Foillseachaidhean Rannsachaidh le Iomraidhean
Klein, T., Mitchell, S., & Weber, H. (2026). Urobilinogen ann an Deuchainn Fuaime: Stiùireadh Coileanta air Urinalysis 2026. Rannsachadh Leigheis AI Kantesti.
Klein, T., Mitchell, S., & Weber, H. (2026). Stiùireadh Sgrùdaidhean Iarainn: TIBC, Sàthadh Iarainn & Comas Ceangail. Rannsachadh Leigheis AI Kantesti.
📖 Iomraidhean Meidigeach Taobh a-muigh
Green DM et al. (2024). Cystic Fibrosis Foundation Evidence-Based Guideline for the Management of CRMS/CFSPID. Pàdraig.
LeGrys VA et al. (2007). Diagnostic Sweat Testing: The Cystic Fibrosis Foundation Guidelines. An Iris Leigheis-chloinne.
⚕️ Àicheadh Meidigeach
Tha an artaigil seo dìreach airson adhbharan foghlaim agus chan eil e a’ dèanamh comhairle mheidigeach. Cuir fios an-còmhnaidh gu solaraiche cùram slàinte teisteanasach airson co-dhùnaidhean breithneachaidh is leigheis.
Comharran earbsa E-E-A-T
Eòlas
Lèirmheas clionaigeach air a stiùireadh le lighiche air sruthan-obrach mìneachaidh obair-lann.
Eòlas
Fòcas air leigheas obair-lann air mar a bhios bith-chomharraidhean (biomarkers) a’ giùlan ann an co-theacsa clionaigeach.
Ùghdarrasachd
Air a sgrìobhadh le Dr. Thomas Klein le ath-sgrùdadh le Dr. Sarah Mitchell agus Prof. Dr. Hans Weber.
Earbsachd
Mìneachadh stèidhichte air fianais le slighean leanmhainn soilleir gus dragh a lughdachadh.