30–59 mmol/L həddindəki sərhədyanı tər xlorid nəticəsi kistik fibrozisi təsdiq etmir. Bu, nəticənin təqib edilməli olduğu deməkdir: adətən təcrübəli mərkəzdə təkrar test aparılması, simptomların və yeni doğulmuşların skrininqinin nəzərdən keçirilməsi və bəzən CFTR genetik və ya funksional qiymətləndirilməsi.


- Aşağı tər xlorid: 30 mmol/L-dən az, kistik fibrozisi daha az ehtimal edir, lakin simptomlar və ya genetikada güclü göstəricilər olduqda onu tamamilə istisna etmir.
- Aralıq tər xlorid: 30–59 mmol/L səviyyələri qeyri-müəyyəndir - təsdiqlənmiş kistik fibrozis diaqnozu deyil və avtomatik olaraq daşıyıcı nəticəsi deyil.
- Yüksəlmiş tər xlorid: 60 mmol/L və ya daha yüksək olan etibarlı nəticə uyğun kliniki şəraitdə kistik fibrozisi dəstəkləyir və mütəxəssis təsdiqi tələb edir.
- Təkrar yoxlama: Aralıq nəticə ümumiyyətlə 1–2 ay ərzində başqa bir tər xlorid testini tələb edir, simptomatik körpələr və ya narahatlıq doğuran simptomlar üçün daha erkən qiymətləndirmə aparılır.
- Bütün yaşlar: Kistik Fibrozis Fondunun cari diaqnostik həddi körpələr, uşaqlar və böyüklər üçün 30-dan az, 30–59 və ən azı 60 mmol/L istifadə edir.
- Toplama keyfiyyəti: Yetersiz tər nümunəsi etibarlı mənfi nəticə olaraq bildirilməz; ayrı toplama yerləri birləşdirilməməlidir.
- KİTF qiymətləndirilməsi: Davamlı aralıq nəticələr, şübhəli simptomlar və ya yeni doğulmuşların anormal skrininqi ardıcıllıq, silinmə/duplikasiya analizi və genetik məsləhətə haqq qazandıra bilər.
- YZ limitləri: Tər xloridi təri ölçür, qanı yox. Əlaqədar laboratoriya nəticələrinin YZ şərhi sistik fibrozun qurulması və ya istisna edilməsi mümkün deyil.
Aşağı, aralıq və yüksəlmiş nəticələr nə deməkdir?
Tər xlorid testinin nəticələri 30 mmol/L-dən aşağı olarsa, sistik fibroz daha az ehtimal olunur; 30–59 mmol/L aralıqdır; və 60 mmol/L və ya daha yüksək, uyğun klinik şəraitdə sistik fibrozun lehinədir. Hüdudda olan nəticə araşdırma səbəbidir—diaqnoz deyil, şiddət balı deyil, yaxud özbaşına müalicəyə başlamaq üçün səbəb deyil.
2017-ci ildə Kistik Fibroz Fondu konsensusu bu 3 hüdudu yaşlardan asılı olmayaraq tətbiq edir, daha böyük uşaqlar və böyüklər üçün daha yüksək aralıq hüdudundan istifadə etmək əvəzinə (Farrell et al., 2017). Bəzi köhnə hesabatlar hələ də körpəlikdən sonra 40–59 mmol/L-i həddində olaraq təsvir edir; köhnəlmiş istinad intervalı onu normal adlandırdığı üçün 35 mmol/L nəticəni sadəcə rədd etməməlidir.
59 mmol/L nəticəsi və 60 mmol/L nəticəsi fərqli kateqoriyalara düşür, lakin biologiya bu rəqəmlər arasında qəfil dəyişmir. Toplama keyfiyyəti, simptomlar, skrininq tarixi və təkrar ölçmələr kateqoriyadan nə qədər əminliklə istifadə edilə biləcəyini müəyyən edir. Bizim izahımız laboratoriya siqnallarının niyə qeyd olunmuş rəqəmin özünün diaqnoz olmadığını izah edir.
Mən Kantesti-nin Baş Tibbi Direktoru, MD, Thomas Kleinəm və mənim klinik çərçivəm hər ikisini müzakirə etməzdən əvvəl ölçməni diaqnozdan ayırmaqdır. Kantesti YZ qan testi analizatorudur; tər xloridi ayrı bir mütəxəssis testidir, qan biomarkerı deyil. Bizim təşkilatımız və klinik yurisdiksiyamız bu fərqi izah edir, bu da xüsusilə kimsə qarışıq laboratoriya hesabatını yüklədikdə əhəmiyyət kəsb edir.
Tər xlorid testi əslində nə ölçür?
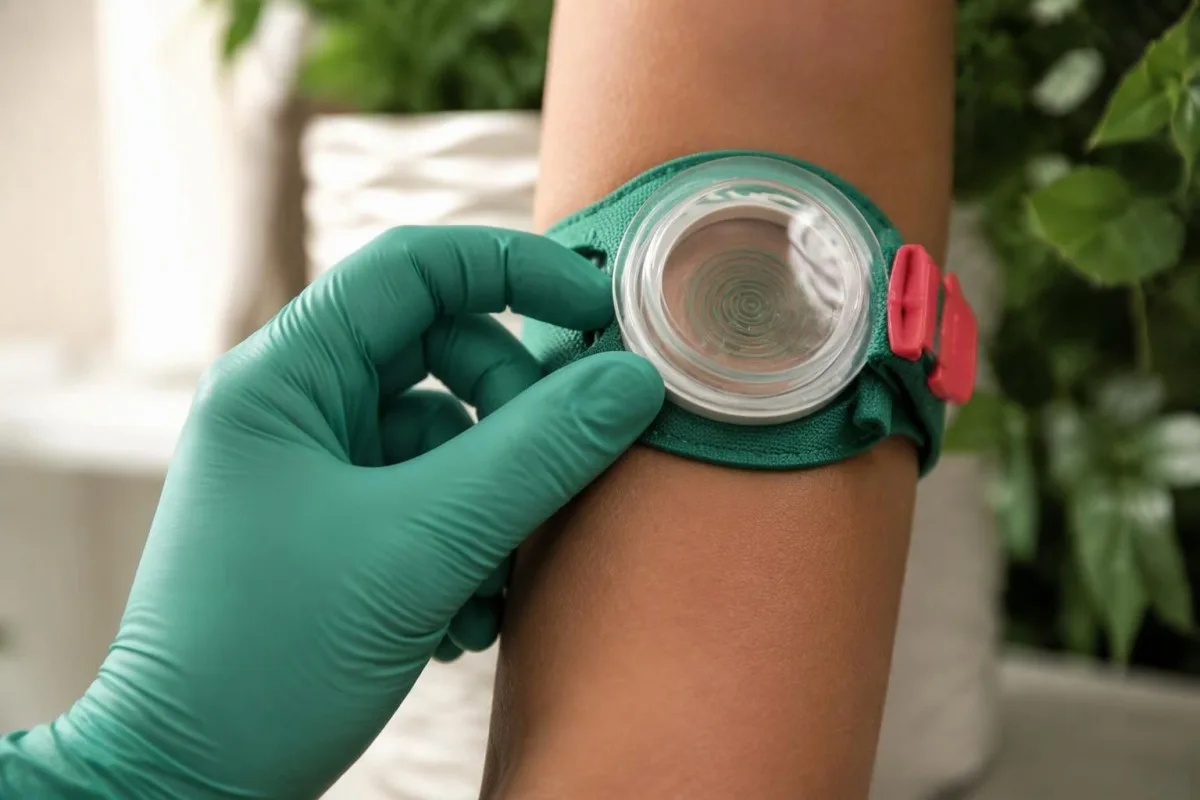
Tər xlorid testi, pilokarpinin kiçik bir toplama sahəsini stimullaşdırmasından sonra tər xlorid konsentrasiyasını ölçür. Bu, KİTF kanal funksiyasının bir nəticəsini qiymətləndirir: tərin səthə çatmadan əvvəl tərin nə qədər effektiv şəkildə xloridi geri sovurduğu. Diaqnostik nəticə tər istehsalı miqdarı kimi deyil, mmol/L-də bildirilir.
The sweat gland first produces fluid, and its duct then reabsorbs salt. Reduced CFTR function can leave more chloride in the final sweat, producing values of 60 mmol/L or higher in many people with cystic fibrosis. This is a functional clue, but it does not directly measure lung damage, pancreatic function, or the number of genetic variants present.
Sweat chloride and serum chloride describe different compartments. A person can have elevated sweat chloride while the chloride concentration in a metabolic panel is normal—or low after substantial salt loss. Our discussion of serum chloride and fluids concerns blood chemistry; its reference intervals cannot be substituted for the 30–59 mmol/L sweat interval.
The units can also look different without representing different thresholds: for chloride, 1 mmol/L equals 1 mEq/L because chloride has a single electrical charge. Sweat conductivity is another matter—it reflects multiple ions, often expressed as sodium chloride equivalents. A conductivity result must not be interpreted using diagnostic sweat chloride thresholds, even when the report looks reassuringly numerical.
Niyə aralıq nəticə kistik fibrozisi təsdiq etmir?
An intermediate sweat chloride result does not confirm cystic fibrosis because 30–59 mmol/L overlaps several clinical situations. These include some people with cystic fibrosis, people with other CFTR-associated conditions, and people without a CFTR disorder. The same value can therefore lead to different conclusions depending on the evidence around it.
For an illustrative comparison, consider a thriving infant with 38 mmol/L after newborn screening and an adult with 38 mmol/L plus recurrent pancreatitis and bronchiectasis. Neither number independently proves cystic fibrosis, but the second history raises different diagnostic questions. This is why I would not attach a single percentage probability to every borderline sweat chloride test without knowing the referral context.
Persistent intermediate results on 2 separate occasions can still occur in cystic fibrosis, and the 2017 consensus recommends considering extended CFTR analysis or specialized functional testing in that setting (Farrell et al., 2017). Conversely, 2 intermediate measurements do not automatically convert uncertainty into a confirmed diagnosis. Repetition establishes persistence; it does not explain the cause by itself.
Borderline is also not another word for carrier. A person with 1 identified CF-causing variant may be a carrier, but the initial genetic panel might have missed another variant, or the symptoms may have another explanation. Our discussion of borderline stool test follow-up illustrates the broader distinction between an indeterminate measurement and a named disease; the follow-up tests themselves are different.
Müsbət tər xlorid nəticəsi nə tələb edir?
A properly collected sweat chloride result of at least 60 mmol/L supports a cystic fibrosis diagnosis when there is compatible newborn screening, a relevant family history, or characteristic clinical features. Specialist assessment should follow promptly. Confirmation usually uses repeat testing on a separate date or an independent diagnostic method, such as appropriate CFTR analysis.
A report saying sweat chloride test positive deserves more than a telephone message reading only the flag. Ask for the actual concentration, the collection method, whether the sample was sufficient, and the plan for confirmation. A measured chloride of 72 mmol/L is meaningful evidence; a positive conductivity screening result is not an interchangeable diagnostic finding.
The distinction between a category and a concentration matters at both ends of the scale. Chloride concentrations above roughly 160 mmol/L are outside the expected physiological range for sweat and should trigger immediate laboratory review rather than assumptions about unusually severe disease. The collection and analytical record may be more informative than another decimal place on the report.
Positive-range sweat chloride is not, by itself, an emergency severity score. A clinically stable child with 68 mmol/L needs a timely CF specialist pathway; a child with dehydration or breathing difficulty needs urgent care regardless of the sweat value. Our guide to keyfiyyət və kəmiyyət nəticələri explains why the measured number should accompany the positive label.
Aşağı nəticə kistik fibrozisi istisna edə bilərmi?
Sweat chloride below 30 mmol/L makes cystic fibrosis less likely, but cannot absolutely exclude it when symptoms or CFTR findings are strongly suggestive. A low result is most reassuring when the sample was valid, the person has no characteristic symptoms, and the screening or family-history concern has been adequately addressed.
Certain CFTR variants preserve enough sweat-duct function to produce lower chloride concentrations despite clinically relevant disease. The 2017 consensus therefore allows further evaluation when a value below 30 mmol/L conflicts with genotype or evolving clinical features (Farrell et al., 2017). A normal newborn screen also does not eliminate every possible CF diagnosis in a child who later develops suggestive symptoms.
Age does not create a separate low-result exception: a value of 27 mmol/L has the same diagnostic category in a toddler and an adult. What changes is the history available to interpret it—growth trajectory in a young child, for example, versus years of recurrent pancreatitis or unexplained bronchiectasis in an adult. The referral question should travel with the laboratory result.
A child with 24 mmol/L, persistent greasy stools, and faltering growth still needs an explanation for the symptoms, even if cystic fibrosis becomes less likely. The next step may include pancreatic, gastrointestinal, or nutritional assessment rather than simply repeating every test. Our guidance on uşaqların AI təfsiri limitləri explains why pediatric decisions require age-specific clinical oversight.
Yeni doğulanların skrininqindən sonra aralıq nəticələr necə idarə olunur?
An infant with an abnormal newborn screen and intermediate sweat chloride needs assessment through a CF specialist pathway, but may not have cystic fibrosis. Some clinically well infants receive the designation CRMS/CFSPID, meaning the screening and diagnostic findings remain inconclusive. This designation has specific criteria; it should not be applied to every borderline result.
CRMS/CFSPID generally applies after positive newborn screening when sweat chloride is below 30 mmol/L with 2 CFTR variants, at least 1 of uncertain consequence, or when chloride is 30–59 mmol/L with no more than 1 CF-causing variant. The infant should not have clinical features establishing CF. A symptomatic child or an adult with borderline chloride needs a different diagnostic framing.
The 2024 Cystic Fibrosis Foundation guideline recommends repeat sweat chloride at 6 months and annually through at least age 8 for children with CRMS/CFSPID (Green et al., 2024). Fewer than 10% are reclassified as CF in the evidence summarized by that guideline, although individual risk varies. That estimate describes a defined screened population—not all children with intermediate chloride.
For screen-positive newborns, diagnostic sweat testing is generally arranged after 10 days of age and ideally by 4 weeks, when the infant is over 2 kg and at least 36 weeks corrected gestational age. Feeding, stool pattern, and weight gain help determine urgency. Our explanation of pediatric growth assessment addresses broader growth questions; a borderline sweat result does not itself justify growth-hormone testing.
Böyüklərdə sərhədyanı tər xlorid nə deməkdir?
Sweat chloride levels 30–59 mmol/L are intermediate in adults, just as they are in children. Persistent intermediate results deserve particular attention when there is unexplained bronchiectasis, recurrent pancreatitis, chronic sinus disease with other suggestive features, or obstructive infertility. Adult diagnosis is possible; age alone does not exclude cystic fibrosis.
Imagine an illustrative 34-year-old with chloride of 44 mmol/L, repeated pancreatitis, and otherwise normal routine blood chemistry. The normal metabolic panel does not settle the CFTR question, because it measures neither sweat-duct transport nor pancreatic duct function. A specialist might pursue extended genetics and pancreatic assessment while also checking more common causes of recurrent pancreatitis.
Bronchiectasis has several possible causes, and 1 intermediate sweat result should not end that investigation. Depending on the history, clinicians may evaluate immune deficiency, aspiration, ciliary disorders, and other inherited respiratory conditions. Our guide to alfa-1 antitripsin testi discusses a different inherited lung-risk pathway; it is complementary only when the clinical pattern supports testing.
Male infertility can occasionally be the first clue to CFTR-associated disease, especially when congenital absence of the vas deferens causes obstruction. A sperm count of 0 is not enough to establish that anatomy or a CF diagnosis, and hormonal explanations require different evaluation. Our semen analysis interpretation guide explains why reproductive assessment must accompany—not be replaced by—CFTR testing.
Toplama problemləri nəticəni çaşdırıcı edə bilərmi?
Collection problems can make sweat chloride results unreliable, and insufficient sweat is not a negative test. Evaporation, contamination, incorrect handling, and inadequate sample volume can interfere with interpretation. Before drawing conclusions from a borderline result, confirm that the laboratory performed quantitative chloride analysis on an acceptable sample.
Common minimum quantities are 75 mg for gauze or filter-paper collection and 15 µL for a Macroduct collection system; collection generally lasts no more than 30 minutes. Samples from separate sites should not be pooled to reach the minimum. The Cystic Fibrosis Foundation sweat-testing guidance describes these collection safeguards because an apparently precise number cannot rescue an inadequate specimen (LeGrys et al., 2007).
A report marked QNS—quantity not sufficient—means no reliable diagnostic concentration was obtained. If one arm yields an acceptable sample and the other does not, the center should explain which result is valid; the unsuccessful site is not a second negative measurement. Likewise, conflicting bilateral values should prompt a quality review rather than an improvised average that hides disagreement.
Copied reports introduce another avoidable problem: 35 mmol/L can become 85 mmol/L through transcription or image-reading error. Our PDF transkripsiyası siyahısı is useful for verifying numbers against the original report, not for validating the sweat procedure. Kantesti’s kliniki standartlar və məhdudiyyətlər should also be distinguished from accreditation of the laboratory that collected and measured the sweat.
Nə vaxt akkreditə olunmuş mərkəzdə test təkrarlanmalıdır?
An intermediate sweat chloride result generally warrants repeat quantitative testing within 1–2 months at an accredited CF center or an appropriately accredited laboratory experienced in sweat testing. Earlier specialist assessment is appropriate for symptomatic infants, poor growth, recurrent pancreatitis, or significant respiratory concerns. Persistent uncertainty should not be managed through repeated low-quality collections.
The right center depends on your country: CF-center accreditation and laboratory accreditation are related but not identical. Ask whether the laboratory regularly performs pediatric and adult sweat chloride testing, monitors insufficient-sample rates, and uses quantitative chloride rather than conductivity alone. For a result of 46 mmol/L, an experienced collection team may be more useful than choosing a laboratory solely for convenience.
Repeat tests can cross categories because of biological and analytical variation. Values of 29 and 33 mmol/L on separate dates deserve context; they do not prove that CFTR function suddenly deteriorated. Our discussion of laboratory changes over time explains the general distinction between variation and disease progression, although sweat testing has its own collection requirements.
For a valid repeat, follow the center’s instructions, maintain normal hydration, and avoid lotions or creams on the collection site. Do not fast, overdrink water, or stop prescribed medicines unless instructed; disclose all medicines, especially CFTR modulators. If the first sample was QNS, the repeat may simply be the first interpretable test—not a confirmation of any earlier diagnostic category.
CFTR genetik qiymətləndirməsi nə vaxt uyğundur?
CFTR genetic evaluation is appropriate when sweat chloride remains intermediate, newborn screening is abnormal, family history is relevant, or characteristic symptoms persist despite a low result. Testing may need to extend beyond a common-variant panel to sequencing and deletion/duplication analysis. A negative limited panel cannot exclude all clinically relevant CFTR variants.
Finding 2 variants is not automatically equivalent to finding 2 CF-causing variants. Classification matters, and the variants usually need to be on opposite gene copies—in trans—to support the recessive diagnostic explanation. Parental testing can help establish phase; 2 variants on the same copy, in cis, leave the other copy unresolved.
A variant of uncertain significance cannot be promoted to a disease-causing finding simply because sweat chloride is 41 mmol/L. Specialists combine curated variant evidence, the phenotype, family testing, and sometimes functional assessment. Genetic counseling should explain what the result establishes, what it leaves unanswered, and whether relatives or a reproductive partner need targeted evaluation.
Kantesti is an AI blood test interpretation platform, not a CFTR variant-classification laboratory. Our AI texnologiyası izahı describes how laboratory information is organized, but 1 unresolved genetic finding requires qualified interpretation rather than an automated disease label. When I review accompanying chemistry, I treat the genetic report as a separate evidence source with its own method, coverage, and limitations.
Qeyri-müəyyən nəticəni aydınlaşdırmaq üçün hansı əlavə testlər edilə bilər?
Specialist CFTR functional tests can help when sweat chloride and genetics remain inconclusive. Nasal potential difference assesses ion transport in nasal epithelium, while intestinal current measurement assesses transport in intestinal tissue. These tests require validated protocols at experienced reference centers; they are not routine blood tests or interchangeable screening tools.
The 2017 consensus recommends that nasal potential difference and intestinal current measurement be performed in validated reference centers when needed for diagnosis (Farrell et al., 2017). Availability varies internationally, and 1 abnormal functional measurement must be interpreted using the center’s protocol and clinical context. Referral is often more sensible than asking a general laboratory to improvise an unfamiliar assay.
Organ-specific tests answer different questions. Fecal elastase below 200 µg/g can suggest pancreatic exocrine insufficiency, but a watery sample may dilute the measurement and a normal result does not exclude pancreatic-sufficient CF. Our nəcis elastazının təfsiri təlimatı explains those limitations; pancreatic status is evidence about organ function, not a substitute for establishing CFTR-related diagnosis.
Fat malabsorption may also justify stool-fat assessment, with collection and dietary requirements determined by the laboratory. Adult fecal fat above about 7 g/day on an appropriate standardized intake suggests steatorrhea, but the cause may be pancreatic, intestinal, or biliary. Our fecal fat result guide helps separate documenting malabsorption from naming its cause.
Digər vəziyyətlər və ya dərmanlar tər xloridini təsir edə bilərmi?
Technical problems and some non-CF conditions can produce elevated or intermediate sweat chloride, while medicines can affect sweat production or CFTR function. Severe malnutrition, untreated hypothyroidism, and adrenal insufficiency are among reported non-CF associations. These possibilities require a clinically directed assessment; they should not become an excuse to dismiss a valid result of 60 mmol/L or higher.
Adrenal insufficiency deserves consideration when fatigue, weight loss, low blood pressure, pigmentation changes, or abnormal electrolytes accompany the diagnostic question. A sweat value of 48 mmol/L alone does not justify a cortisol workup, but the combined pattern may. Our guide to adrenal insufficiency warning signs explains when symptoms make that alternative urgent.
Malnutrition can be a confounder and also a consequence of an underlying disorder, so correcting nutrition does not automatically resolve the CF question. A child with 43 mmol/L and chronic diarrhea may need evaluation for celiac disease or another malabsorption cause as well as CFTR assessment. Our explanation of IgA-related celiac testing pitfalls is relevant when negative celiac antibodies conflict with a suggestive history.
CFTR modulators can lower sweat chloride because they improve channel function; a treated value below 30 mmol/L does not erase an established CF diagnosis. Drugs that reduce sweating, such as topiramate in some patients, can make adequate collection harder without providing a reliable prediction of chloride concentration. Give the center a complete medication list, and never stop treatment just to produce an untreated number.
Diaqnoz qeyri-müəyyən olduqda ailələr nə etməlidir?
While a borderline result is being clarified, keep specialist follow-up, monitor relevant symptoms, and avoid starting CF-specific treatment without an indication. A sweat chloride value of 30–59 mmol/L does not justify routine pancreatic enzymes, antibiotics, high-dose vitamins, or extra salt on its own. Supportive care should address demonstrated problems rather than a provisional label.
Bring the original sweat report, newborn-screening record if applicable, genetic report, medication list, and growth measurements to the appointment. Recording 2–3 concrete observations—such as stool frequency, weight trend, or repeated chest illnesses—is usually more useful than an exhaustive diary. Ask who will arrange the repeat test and who will explain a result that remains intermediate.
Nutrition testing should be driven by symptoms and growth, not by the sweat number alone. Iron deficiency can accompany restricted intake or malabsorption, but a ferritin result does not confirm CF; iron treatment also needs an appropriate indication. Our complete iron studies guide explains how to distinguish low stores from inflammation-related changes when a clinician requests that assessment.
Routine chemistry can help assess complications: low chloride and bicarbonate elevation may accompany salt depletion, while low albumin needs a separate nutritional, hepatic, or protein-loss explanation. Our serum zülallarının interpretasiya bələdçisi provides that context. Seek urgent care for breathing difficulty, marked lethargy, repeated vomiting, or substantially reduced urination—do not wait 1–2 months for the planned sweat retest.
Nəticə necə izah edilməli və sənədləşdirilməlidir?
A useful sweat chloride explanation records the exact value, units, collection quality, clinical context, and next diagnostic step. As of October 8, 2026, this article uses the 2017 CF diagnostic consensus and the 2024 CRMS/CFSPID management guideline—not a newly invented 2026 cutoff. The central distinction remains unchanged: intermediate is not confirmed CF.
For a result of 42 mmol/L, a clear clinical note might say: intermediate quantitative sweat chloride, adequate sample, CF diagnosis unresolved, repeat at an experienced center and review CFTR testing. That wording is more useful than possible CF without a plan. If the repeat is below 30 mmol/L but symptoms remain concerning, the note should explain why investigation is continuing.
Kantesti is an AI lab test interpretation service that can help explain accompanying blood chemistry, but cannot confirm cystic fibrosis from sweat chloride or genetics. At Kantesti, the safe boundary is to distinguish report explanation from specialist diagnosis; our medical advisory responsibilities describe the role of clinical oversight. A value of 60 mmol/L or higher should trigger a clinical pathway, not an AI-generated treatment prescription.
As Thomas Klein, MD, my practical recommendation is to ask 3 questions: was the specimen valid, does the clinical story fit, and what evidence will resolve the uncertainty? The related Zenodo publications below address general laboratory interpretation, not sweat chloride diagnostic validation. The CF-specific external references are the sources supporting the thresholds, confirmation strategy, and follow-up recommendations in this article.
Tez-tez verilən suallar
Ehtiyatlı tərləmə xloridi siftiş xəstəliyi deməkdir?
30–59 mmol/l səviyyəsində sərhədli tərləmə xlorid nəticəsi özlüyündə kistik fibroz diaqnozunu qoymur. Bu interval CF, digər CFTR-ə bağlı vəziyyətlər və heç bir CFTR pozğunluğu olmayan insanlar üçün də keçərlidir. Təcrübəli mərkəzdə təkrar kəmiyyətli testin aparılması, simptomların və skrininqin nəzərdən keçirilməsi və bəzən genişləndirilmiş CFTR qiymətləndirilməsi uyğundur. Hətta 2 aralıq nəticə avtomatik diaqnoz əvəzinə əlavə yozum tələb edir.
Müsbət tərləmə xlorid testi nəticəsi nədir?
60 mmol/L və ya daha yüksək kəmiyyət tər xlorid konsentrasiyası, uyğun klinik xüsusiyyətlərə, yenidoğulmuş skrininqə və ya ailə tarixçəsinə malik kistik fibrozun diaqnostik müsbət diapazonundadır və onu dəstəkləyir. Nümunə toplama və analitik tələblərə cavab verməlidir. Mütəxəssis təsdiqlənməsi adətən ayrı bir tarixdə təkrar test aparılmasını və ya müstəqil diaqnostik metodu əhatə edir. Müsbət tər keçiriciliyi skrininqi müsbət kəmiyyətli xlorid nəticəsi ilə dəyişdirilə bilməz.
Böyüklərdə 35 tərləmə xlorid nəticəsi normaldırmı?
35 mmol/L tərlə xlorid nəticəsi 2017-ci il Bədxassəli Fibroz Fondunun diaqnostik konsensusuna əsasən yetkinlərdə aralıqdır. Hazırkı kateqoriyalar hər yaş üçün 30 mmol/L-dən az, 30–59 mmol/L və ən azı 60 mmol/L-dir. Bəzi köhnə laboratoriya diapazonları körpəlikdən sonra aralıq hədd kimi 40 mmol/L-dən istifadə edirdi. Buna görə də, 35 mmol/L olan yetkin nəticəsi köhnəlmiş intervallardan istifadə edərək rədd edilməli deyil, kliniki kontekstdə nəzərdən keçirilməlidir.
İkinci sweat test nə qədər tez təkrarlanmalıdır?
30–59 mmol/l-lik tərlə ion müayinəsi nəticəsi ümumiyyətlə 1–2 ay ərzində təcrübəli, lazımi akkreditasiyadan keçmiş mərkəzdə təkrari kəmiyyətli test aparılmasını tələb edir. Simptomatik körpələr, zəif böyümə və ya əhəmiyyətli tənəffüs və ya mədəaltı vəz problemləri daha erkən mütəxəssis qiymətləndirilməsini tələb edir. Xüsusi CRMS/CFSPID olaraq təyin edilmiş uşaqlar 6 ayda və 8 yaşına qədər ildə bir dəfə təkrari tərləmə testini əhatə edən daha uzunmüddətli cədvələ riayət edirlər. Diaqnostik təkrarlanan və davam edən nəzarət cədvəli müxtəlif məqsədlərə xidmət edir.
Kistik fibroz 30-dan aşağı tərləyən xloridlə baş verə bilərmi?
Sistik fibroz nadir hallarda 30 mmol/l-dən aşağı tərləyən xlorid ilə baş verə bilər, xüsusən də müəyyən CFTR variantları tərləyən kanal funksiyasını qoruyub saxladıqda. Aşağı nəticə CF-i daha az ehtimal edir, lakin simptomlar və ya genetikada güclü şübhələr olduqda onu tamamilə istisna etmir. Davamlı bronxektaziya, təkrar-təkrar pankreatit və ya səbəbi bilinməyən malabsorbsiya daha ətraflı mütəxəssis qiymətləndirilməsini təsdiqləyə bilər. Kifayət qədər nümunə və düzgün kəmiyyət metodu da təsdiqlənməlidir.
Bir CFTR mutasiyası sərhəd tərləmə testini izah edirmi?
Bir müəyyənləşdirilmiş CF-yə səbəb olan CFTR variantı özlüyündə kistik fibroz və ya tərləmə xloridinin 30-59 mmol/L nəticəsini tam izah etmir. Məhdud panel başqa bir varianta səbəb ola bilər və klinik simptomlar fərqli bir səbəbdən ola bilər. Şübhə qaldıqda, ətraflı ardıcıllıq, silinmə/duplikasiya analizi və genetik məsləhət uyğun ola bilər. 2 variant tapılarsa, onların təsnifatı və əks gen surətlərində olub-olmaması da vacibdir.
Tər testində "miqdar kifayət deyil" nə deməkdir?
Miqdar kifayət deyil və ya QNS, diaqnostik nəticəni etibarlı şəkildə vermək üçün çox az tərləmə toplandığı anlamına gəlir. Makrodükt yığımı üçün ümumi minimum miqdarlar 15 µL və ya sarğı və ya filtr-kağız yığımı üçün 75 mq-dır. QNS mənfi tərləmə xlorid testi deyil və kistik fibrozdan istisna etmir. Təkrar toplama tələb olunur və minimuma çatmaq üçün ayrı toplama yerləri birləşdirilməməlidir.
Bu gün AI ilə gücləndirilmiş qan analizi nəticələrinin şərhini əldə edin
Ani və dəqiq laborator analiz şərhinə güvənən dünya üzrə 2 milyondan çox istifadəçiyə qoşulun. Qan analizinin nəticələrini yükləyin və bir neçə saniyəyə 15,000+ biomarkerlərinin hərtərəfli şərhini alın.
📚 İstinad edilən tədqiqat nəşrləri
Klein, T., Mitchell, S., & Weber, H. (2026). Sidikdə Urobilinogen Testi: Tam Sidik Analizi Bələdçisi 2026. Kantesti AI Tibbi Tədqiqatlar.
Klein, T., Mitchell, S., & Weber, H. (2026). Dəmir Tədqiqatları Təlimatı: TIBC, Dəmir Doyma və Bağlanma Qabiliyyəti. Kantesti AI Tibbi Tədqiqatlar.
📖 Xarici Tibbi İstinadlar
Green DM et al. (2024). Cystic Fibrosis Foundation Evidence-Based Guideline for the Management of CRMS/CFSPID. Pediatrics.
LeGrys VA et al. (2007). Diagnostic Sweat Testing: The Cystic Fibrosis Foundation Guidelines. Pediatriya jurnalı.
⚕️ Tibbi Məsuliyyətdən İmtina
Bu məqalə yalnız təhsil məqsədlidir və tibbi məsləhət təşkil etmir. Diaqnoz və müalicə qərarları üçün həmişə ixtisaslı səhiyyə işçisi ilə məsləhətləşin.
E-E-A-T Etibar Siqnalları
Təcrübə
Həkim rəhbərliyi ilə laborator şərh iş axınlarının klinik icmalı.
Ekspertiza
Biomarkerlərin klinik kontekstdə necə davrandığına dair laboratoriya təbabəti diqqəti.
Səlahiyyətlilik
Dr. Thomas Klein tərəfindən yazılıb; Dr. Sarah Mitchell və Prof. Dr. Hans Weber tərəfindən nəzərdən keçirilib.
Etibarlılıq
Aydın izləmə yolları ilə həyəcanı azaltmağa yönəlmiş sübuta əsaslanan şərh.