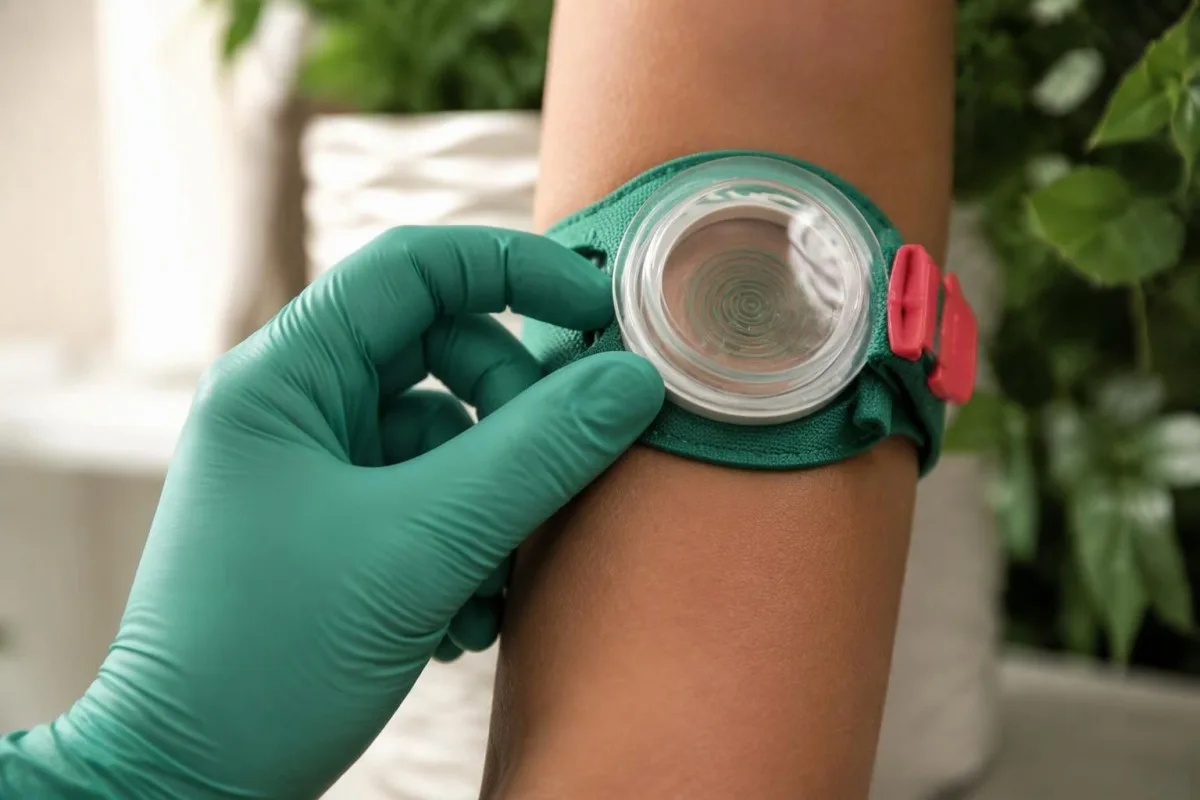
Një rezultat kufitar i klorurit të djersës prej 30–59 mmol/L nuk e konfirmon fibroza cistike. Kjo do të thotë që rezultati kërkon ndjekje: zakonisht testime të përsëritura në një qendër me përvojë, rishikim të simptomave dhe skriningun e të porsalindurve, dhe ndonjëherë vlerësim gjenetik ose funksional të CFTR.


- Kloruri i ulët i djersës: Më pak se 30 mmol/L e bën fibroza cistike më pak të mundshme, por nuk e përjashton plotësisht atë kur simptomat ose gjenetika janë sugjeruese.
- Kloruri i ndërmjetëm i djersës: Nivelet 30–59 mmol/L janë jo përfundimtare—jo një diagnozë e konfirmuar e fibroza cistike dhe jo automatikisht një rezultat bartës.
- Kloruri i ngritur i djersës: Një rezultat valid prej 60 mmol/L ose më i lartë mbështet fibroza cistike në kontekstin e duhur klinik dhe kërkon konfirmim nga specialisti.
- Përsëritja e testimit: Një rezultat i ndërmjetëm përgjithësisht justifikon një test tjetër të klorurit të djersës brenda 1–2 muajve, me vlerësim më të hershëm për foshnjat simptomatike ose simptomat shqetësuese.
- Të gjitha moshat: Pragjet aktuale diagnostikuese të Fondacionit të Fibrozës Cistike përdorin më pak se 30, 30–59, dhe të paktën 60 mmol/L për foshnjat, fëmijët dhe të rriturit.
- Cilësia e mbledhjes: Një mostër e pamjaftueshme e djersës nuk mund të raportohet si një rezultat negativ i besueshëm; vendndodhjet e veçanta të mbledhjes nuk duhet të bashkohen.
- Vlerësimi i CFTR: Rezultatet e vazhdueshme të ndërmjetme, simptomat sugjeruese, ose shqyrtimi jonormal i të porsalindurve mund të justifikojnë renditjen, analizën e fshirjes/dyfishimit, dhe këshillimin gjenetik.
- Kufijtë e AI: Kloruri i djersës mat djersën, jo gjakun. Interpretimi i AI i rezultateve shoqëruese laboratorike nuk mund të krijojë ose përjashtojë fibrozën cistike.
Çfarë nënkuptojnë rezultatet e ulëta, të ndërmjetme dhe të ngritura?
Rezultatet e testit të klorurit të djersës nën 30 mmol/L e bëjnë fibrozën cistike më pak të mundshme; 30–59 mmol/L është ndërmjetësore; dhe 60 mmol/L ose më i lartë mbështet fibrozën cistike në ambientin e duhur klinik. Një rezultat kufitar është arsye për të hetuar – jo një diagnozë, një pikë vlerësimi të ashpërsisë, ose arsye për të filluar trajtimin vetë.
Konsensusi i Fondacionit të Fibrozës Cistike të vitit 2017 i zbaton këto 3 pragje në të gjitha moshat, në vend që të përdorë një kufi më të lartë ndërmjetësues për fëmijët më të rritur dhe të rriturit (Farrell et al., 2017). Disa raporte më të vjetra ende përshkruajnë 40–59 mmol/L si kufitar pas foshnjërisë; një rezultat prej 35 mmol/L nuk duhet të hidhet poshtë thjesht sepse një intervall referimi i vjetëruar e quan atë normal.
Një rezultat prej 59 mmol/L dhe një prej 60 mmol/L bien në kategori të ndryshme, por biologjia nuk ndryshon papritur midis atyre numrave. Cilësia e mbledhjes, simptomat, historia e shqyrtimit, dhe matjet e përsëritura përcaktojnë me sa siguri mund të përdoret kategoria. Shpjegimi ynë i flamujt laboratorikë jashtë intervalit diskuton pse një numër i shënuar nuk është vetë një diagnozë.
Unë jam Thomas Klein, MD, Drejtor Kryesor Mjekësor në Kantesti, dhe korniza ime klinike është të ndaj matjen nga diagnoza para se të diskutoj cilindo. Kantesti është një analizues AI i testeve të gjakut; kloruri i djersës është një test i veçantë specialist, jo një biomaker i gjakut. Tonë organizata dhe përgjegjësia jonë klinike shpjegojnë atë dallim, i cili ka rëndësi veçanërisht kur dikush ngarkon një raport laboratorik të përzier.
Çfarë mat në fakt testi i klorurit të djersës?
Testi i klorurit të djersës mat përqendrimin e klorurit në djersë pasi pilokarpina stimulon një zonë të vogël mbledhjeje. Ai vlerëson një pasojë të funksionit të kanalit CFTR: sa efektivisht kanali i djersës riabsorbon klorurin para se djersa të arrijë në sipërfaqe. Rezultati diagnostikues raportohet në mmol/L, jo si sasi e djersës së prodhuar.
The sweat gland first produces fluid, and its duct then reabsorbs salt. Reduced CFTR function can leave more chloride in the final sweat, producing values of 60 mmol/L or higher in many people with cystic fibrosis. This is a functional clue, but it does not directly measure lung damage, pancreatic function, or the number of genetic variants present.
Sweat chloride and serum chloride describe different compartments. A person can have elevated sweat chloride while the chloride concentration in a metabolic panel is normal—or low after substantial salt loss. Our discussion of serum chloride and fluids concerns blood chemistry; its reference intervals cannot be substituted for the 30–59 mmol/L sweat interval.
The units can also look different without representing different thresholds: for chloride, 1 mmol/L equals 1 mEq/L because chloride has a single electrical charge. Sweat conductivity is another matter—it reflects multiple ions, often expressed as sodium chloride equivalents. A conductivity result must not be interpreted using diagnostic sweat chloride thresholds, even when the report looks reassuringly numerical.
Pse një rezultat i ndërmjetëm nuk e konfirmon fibroza cistike?
An intermediate sweat chloride result does not confirm cystic fibrosis because 30–59 mmol/L overlaps several clinical situations. These include some people with cystic fibrosis, people with other CFTR-associated conditions, and people without a CFTR disorder. The same value can therefore lead to different conclusions depending on the evidence around it.
For an illustrative comparison, consider a thriving infant with 38 mmol/L after newborn screening and an adult with 38 mmol/L plus recurrent pancreatitis and bronchiectasis. Neither number independently proves cystic fibrosis, but the second history raises different diagnostic questions. This is why I would not attach a single percentage probability to every borderline sweat chloride test without knowing the referral context.
Persistent intermediate results on 2 separate occasions can still occur in cystic fibrosis, and the 2017 consensus recommends considering extended CFTR analysis or specialized functional testing in that setting (Farrell et al., 2017). Conversely, 2 intermediate measurements do not automatically convert uncertainty into a confirmed diagnosis. Repetition establishes persistence; it does not explain the cause by itself.
Borderline is also not another word for carrier. A person with 1 identified CF-causing variant may be a carrier, but the initial genetic panel might have missed another variant, or the symptoms may have another explanation. Our discussion of borderline stool test follow-up illustrates the broader distinction between an indeterminate measurement and a named disease; the follow-up tests themselves are different.
Çfarë kërkon më pas një rezultat pozitiv i klorurit të djersës?
A properly collected sweat chloride result of at least 60 mmol/L supports a cystic fibrosis diagnosis when there is compatible newborn screening, a relevant family history, or characteristic clinical features. Specialist assessment should follow promptly. Confirmation usually uses repeat testing on a separate date or an independent diagnostic method, such as appropriate CFTR analysis.
A report saying sweat chloride test positive deserves more than a telephone message reading only the flag. Ask for the actual concentration, the collection method, whether the sample was sufficient, and the plan for confirmation. A measured chloride of 72 mmol/L is meaningful evidence; a positive conductivity screening result is not an interchangeable diagnostic finding.
The distinction between a category and a concentration matters at both ends of the scale. Chloride concentrations above roughly 160 mmol/L are outside the expected physiological range for sweat and should trigger immediate laboratory review rather than assumptions about unusually severe disease. The collection and analytical record may be more informative than another decimal place on the report.
Positive-range sweat chloride is not, by itself, an emergency severity score. A clinically stable child with 68 mmol/L needs a timely CF specialist pathway; a child with dehydration or breathing difficulty needs urgent care regardless of the sweat value. Our guide to rezultatet kualitative dhe kuantitative explains why the measured number should accompany the positive label.
A mund ta përjashtojë një rezultat të ulët fibroza cistike?
Sweat chloride below 30 mmol/L makes cystic fibrosis less likely, but cannot absolutely exclude it when symptoms or CFTR findings are strongly suggestive. A low result is most reassuring when the sample was valid, the person has no characteristic symptoms, and the screening or family-history concern has been adequately addressed.
Certain CFTR variants preserve enough sweat-duct function to produce lower chloride concentrations despite clinically relevant disease. The 2017 consensus therefore allows further evaluation when a value below 30 mmol/L conflicts with genotype or evolving clinical features (Farrell et al., 2017). A normal newborn screen also does not eliminate every possible CF diagnosis in a child who later develops suggestive symptoms.
Age does not create a separate low-result exception: a value of 27 mmol/L has the same diagnostic category in a toddler and an adult. What changes is the history available to interpret it—growth trajectory in a young child, for example, versus years of recurrent pancreatitis or unexplained bronchiectasis in an adult. The referral question should travel with the laboratory result.
A child with 24 mmol/L, persistent greasy stools, and faltering growth still needs an explanation for the symptoms, even if cystic fibrosis becomes less likely. The next step may include pancreatic, gastrointestinal, or nutritional assessment rather than simply repeating every test. Our guidance on limitet e interpretimit të AI-së te fëmijët explains why pediatric decisions require age-specific clinical oversight.
Si trajtohen rezultatet e ndërmjetme pas skriningut të të porsalindurve?
An infant with an abnormal newborn screen and intermediate sweat chloride needs assessment through a CF specialist pathway, but may not have cystic fibrosis. Some clinically well infants receive the designation CRMS/CFSPID, meaning the screening and diagnostic findings remain inconclusive. This designation has specific criteria; it should not be applied to every borderline result.
CRMS/CFSPID generally applies after positive newborn screening when sweat chloride is below 30 mmol/L with 2 CFTR variants, at least 1 of uncertain consequence, or when chloride is 30–59 mmol/L with no more than 1 CF-causing variant. The infant should not have clinical features establishing CF. A symptomatic child or an adult with borderline chloride needs a different diagnostic framing.
The 2024 Cystic Fibrosis Foundation guideline recommends repeat sweat chloride at 6 months and annually through at least age 8 for children with CRMS/CFSPID (Green et al., 2024). Fewer than 10% are reclassified as CF in the evidence summarized by that guideline, although individual risk varies. That estimate describes a defined screened population—not all children with intermediate chloride.
For screen-positive newborns, diagnostic sweat testing is generally arranged after 10 days of age and ideally by 4 weeks, when the infant is over 2 kg and at least 36 weeks corrected gestational age. Feeding, stool pattern, and weight gain help determine urgency. Our explanation of pediatric growth assessment addresses broader growth questions; a borderline sweat result does not itself justify growth-hormone testing.
Çfarë do të thotë kloruri i djersës kufitar te të rriturit?
Sweat chloride levels 30–59 mmol/L are intermediate in adults, just as they are in children. Persistent intermediate results deserve particular attention when there is unexplained bronchiectasis, recurrent pancreatitis, chronic sinus disease with other suggestive features, or obstructive infertility. Adult diagnosis is possible; age alone does not exclude cystic fibrosis.
Imagine an illustrative 34-year-old with chloride of 44 mmol/L, repeated pancreatitis, and otherwise normal routine blood chemistry. The normal metabolic panel does not settle the CFTR question, because it measures neither sweat-duct transport nor pancreatic duct function. A specialist might pursue extended genetics and pancreatic assessment while also checking more common causes of recurrent pancreatitis.
Bronchiectasis has several possible causes, and 1 intermediate sweat result should not end that investigation. Depending on the history, clinicians may evaluate immune deficiency, aspiration, ciliary disorders, and other inherited respiratory conditions. Our guide to testin e alfa-1 antitripsinës discusses a different inherited lung-risk pathway; it is complementary only when the clinical pattern supports testing.
Male infertility can occasionally be the first clue to CFTR-associated disease, especially when congenital absence of the vas deferens causes obstruction. A sperm count of 0 is not enough to establish that anatomy or a CF diagnosis, and hormonal explanations require different evaluation. Our semen analysis interpretation guide explains why reproductive assessment must accompany—not be replaced by—CFTR testing.
A mund të bëjnë problemet e mbledhjes rezultatin mashtrues?
Collection problems can make sweat chloride results unreliable, and insufficient sweat is not a negative test. Evaporation, contamination, incorrect handling, and inadequate sample volume can interfere with interpretation. Before drawing conclusions from a borderline result, confirm that the laboratory performed quantitative chloride analysis on an acceptable sample.
Common minimum quantities are 75 mg for gauze or filter-paper collection and 15 µL for a Macroduct collection system; collection generally lasts no more than 30 minutes. Samples from separate sites should not be pooled to reach the minimum. The Cystic Fibrosis Foundation sweat-testing guidance describes these collection safeguards because an apparently precise number cannot rescue an inadequate specimen (LeGrys et al., 2007).
A report marked QNS—quantity not sufficient—means no reliable diagnostic concentration was obtained. If one arm yields an acceptable sample and the other does not, the center should explain which result is valid; the unsuccessful site is not a second negative measurement. Likewise, conflicting bilateral values should prompt a quality review rather than an improvised average that hides disagreement.
Copied reports introduce another avoidable problem: 35 mmol/L can become 85 mmol/L through transcription or image-reading error. Our lista e kontrollit të transkriptimit PDF is useful for verifying numbers against the original report, not for validating the sweat procedure. Kantesti’s standard e limitazioni cliniche should also be distinguished from accreditation of the laboratory that collected and measured the sweat.
Kur duhet përsëritur testimi në një qendër të akredituar?
An intermediate sweat chloride result generally warrants repeat quantitative testing within 1–2 months at an accredited CF center or an appropriately accredited laboratory experienced in sweat testing. Earlier specialist assessment is appropriate for symptomatic infants, poor growth, recurrent pancreatitis, or significant respiratory concerns. Persistent uncertainty should not be managed through repeated low-quality collections.
The right center depends on your country: CF-center accreditation and laboratory accreditation are related but not identical. Ask whether the laboratory regularly performs pediatric and adult sweat chloride testing, monitors insufficient-sample rates, and uses quantitative chloride rather than conductivity alone. For a result of 46 mmol/L, an experienced collection team may be more useful than choosing a laboratory solely for convenience.
Repeat tests can cross categories because of biological and analytical variation. Values of 29 and 33 mmol/L on separate dates deserve context; they do not prove that CFTR function suddenly deteriorated. Our discussion of laboratory changes over time explains the general distinction between variation and disease progression, although sweat testing has its own collection requirements.
For a valid repeat, follow the center’s instructions, maintain normal hydration, and avoid lotions or creams on the collection site. Do not fast, overdrink water, or stop prescribed medicines unless instructed; disclose all medicines, especially CFTR modulators. If the first sample was QNS, the repeat may simply be the first interpretable test—not a confirmation of any earlier diagnostic category.
Kur është e përshtatshme vlerësimi gjenetik i CFTR?
CFTR genetic evaluation is appropriate when sweat chloride remains intermediate, newborn screening is abnormal, family history is relevant, or characteristic symptoms persist despite a low result. Testing may need to extend beyond a common-variant panel to sequencing and deletion/duplication analysis. A negative limited panel cannot exclude all clinically relevant CFTR variants.
Finding 2 variants is not automatically equivalent to finding 2 CF-causing variants. Classification matters, and the variants usually need to be on opposite gene copies—in trans—to support the recessive diagnostic explanation. Parental testing can help establish phase; 2 variants on the same copy, in cis, leave the other copy unresolved.
A variant of uncertain significance cannot be promoted to a disease-causing finding simply because sweat chloride is 41 mmol/L. Specialists combine curated variant evidence, the phenotype, family testing, and sometimes functional assessment. Genetic counseling should explain what the result establishes, what it leaves unanswered, and whether relatives or a reproductive partner need targeted evaluation.
Kantesti is an AI blood test interpretation platform, not a CFTR variant-classification laboratory. Our shpjegim i teknologjisë AI describes how laboratory information is organized, but 1 unresolved genetic finding requires qualified interpretation rather than an automated disease label. When I review accompanying chemistry, I treat the genetic report as a separate evidence source with its own method, coverage, and limitations.
Cilat teste shtesë mund të sqarojnë një rezultat jo përfundimtar?
Specialist CFTR functional tests can help when sweat chloride and genetics remain inconclusive. Nasal potential difference assesses ion transport in nasal epithelium, while intestinal current measurement assesses transport in intestinal tissue. These tests require validated protocols at experienced reference centers; they are not routine blood tests or interchangeable screening tools.
The 2017 consensus recommends that nasal potential difference and intestinal current measurement be performed in validated reference centers when needed for diagnosis (Farrell et al., 2017). Availability varies internationally, and 1 abnormal functional measurement must be interpreted using the center’s protocol and clinical context. Referral is often more sensible than asking a general laboratory to improvise an unfamiliar assay.
Organ-specific tests answer different questions. Fecal elastase below 200 µg/g can suggest pancreatic exocrine insufficiency, but a watery sample may dilute the measurement and a normal result does not exclude pancreatic-sufficient CF. Our udhëzues interpretimi i elastazës në feçe explains those limitations; pancreatic status is evidence about organ function, not a substitute for establishing CFTR-related diagnosis.
Fat malabsorption may also justify stool-fat assessment, with collection and dietary requirements determined by the laboratory. Adult fecal fat above about 7 g/day on an appropriate standardized intake suggests steatorrhea, but the cause may be pancreatic, intestinal, or biliary. Our fecal fat result guide helps separate documenting malabsorption from naming its cause.
A mund të ndikojnë kushtet ose ilaçet e tjera në klorurin e djersës?
Technical problems and some non-CF conditions can produce elevated or intermediate sweat chloride, while medicines can affect sweat production or CFTR function. Severe malnutrition, untreated hypothyroidism, and adrenal insufficiency are among reported non-CF associations. These possibilities require a clinically directed assessment; they should not become an excuse to dismiss a valid result of 60 mmol/L or higher.
Adrenal insufficiency deserves consideration when fatigue, weight loss, low blood pressure, pigmentation changes, or abnormal electrolytes accompany the diagnostic question. A sweat value of 48 mmol/L alone does not justify a cortisol workup, but the combined pattern may. Our guide to adrenal insufficiency warning signs explains when symptoms make that alternative urgent.
Malnutrition can be a confounder and also a consequence of an underlying disorder, so correcting nutrition does not automatically resolve the CF question. A child with 43 mmol/L and chronic diarrhea may need evaluation for celiac disease or another malabsorption cause as well as CFTR assessment. Our explanation of IgA-related celiac testing pitfalls is relevant when negative celiac antibodies conflict with a suggestive history.
CFTR modulators can lower sweat chloride because they improve channel function; a treated value below 30 mmol/L does not erase an established CF diagnosis. Drugs that reduce sweating, such as topiramate in some patients, can make adequate collection harder without providing a reliable prediction of chloride concentration. Give the center a complete medication list, and never stop treatment just to produce an untreated number.
Çfarë duhet të bëjnë familjet ndërsa diagnoza është e pasigurt?
While a borderline result is being clarified, keep specialist follow-up, monitor relevant symptoms, and avoid starting CF-specific treatment without an indication. A sweat chloride value of 30–59 mmol/L does not justify routine pancreatic enzymes, antibiotics, high-dose vitamins, or extra salt on its own. Supportive care should address demonstrated problems rather than a provisional label.
Bring the original sweat report, newborn-screening record if applicable, genetic report, medication list, and growth measurements to the appointment. Recording 2–3 concrete observations—such as stool frequency, weight trend, or repeated chest illnesses—is usually more useful than an exhaustive diary. Ask who will arrange the repeat test and who will explain a result that remains intermediate.
Nutrition testing should be driven by symptoms and growth, not by the sweat number alone. Iron deficiency can accompany restricted intake or malabsorption, but a ferritin result does not confirm CF; iron treatment also needs an appropriate indication. Our complete iron studies guide explains how to distinguish low stores from inflammation-related changes when a clinician requests that assessment.
Routine chemistry can help assess complications: low chloride and bicarbonate elevation may accompany salt depletion, while low albumin needs a separate nutritional, hepatic, or protein-loss explanation. Our udhëzues interpretimi i proteinave të serumit provides that context. Seek urgent care for breathing difficulty, marked lethargy, repeated vomiting, or substantially reduced urination—do not wait 1–2 months for the planned sweat retest.
Si duhet shpjeguar dhe dokumentuar rezultati?
A useful sweat chloride explanation records the exact value, units, collection quality, clinical context, and next diagnostic step. As of October 8, 2026, this article uses the 2017 CF diagnostic consensus and the 2024 CRMS/CFSPID management guideline—not a newly invented 2026 cutoff. The central distinction remains unchanged: intermediate is not confirmed CF.
For a result of 42 mmol/L, a clear clinical note might say: intermediate quantitative sweat chloride, adequate sample, CF diagnosis unresolved, repeat at an experienced center and review CFTR testing. That wording is more useful than possible CF without a plan. If the repeat is below 30 mmol/L but symptoms remain concerning, the note should explain why investigation is continuing.
Kantesti is an AI lab test interpretation service that can help explain accompanying blood chemistry, but cannot confirm cystic fibrosis from sweat chloride or genetics. At Kantesti, the safe boundary is to distinguish report explanation from specialist diagnosis; our medical advisory responsibilities describe the role of clinical oversight. A value of 60 mmol/L or higher should trigger a clinical pathway, not an AI-generated treatment prescription.
As Thomas Klein, MD, my practical recommendation is to ask 3 questions: was the specimen valid, does the clinical story fit, and what evidence will resolve the uncertainty? The related Zenodo publications below address general laboratory interpretation, not sweat chloride diagnostic validation. The CF-specific external references are the sources supporting the thresholds, confirmation strategy, and follow-up recommendations in this article.
Pyetje të Shpeshta
A do flori i klorurit të djersës do të thotë fibrozë cistike?
Një rezultat kufitar i klorurit të djersës prej 30–59 mmol/L nuk diagnostikon vetë fibrozën cistike. Intervali përputhet me njerëz me CF, kushte të tjera të lidhura me CFTR dhe pa çrregullim CFTR. Testimi i përsëritur sasior në një qendër me përvojë, rishikimi i simptomave dhe ekzaminimi, dhe ndonjëherë vlerësimi i zgjatur i CFTR janë të përshtatshëm. Edhe 2 rezultate të ndërmjetme kërkojnë interpretim shtesë sesa diagnozë automatike.
Çfarë është një rezultat pozitiv në testin e klorurit të djersës?
Një përqendrim sasior i klorurit të djersës prej 60 mmol/L ose më i lartë është në intervalin diagnostikues pozitiv dhe mbështet fibrozën cistike me tipare klinike përputhëse, ekzaminim të të porsalindurit, ose histori familjare. Mostra duhet të plotësojë kërkesat e mbledhjes dhe analizës. Konfirmimi nga specialistë zakonisht përfshin testim të përsëritur në një datë të ndarë ose një metodë diagnostike të pavarur. Një ekran pozitiv i përçueshmërisë së djersës nuk është i ndërkambyeshëm me një rezultat pozitiv sasior të klorurit.
A rezultati i kloridit të djersës prej 35 është normal tek një i rritur?
Një rezultat i klorurit të djersës prej 35 mmol/L është ndërmjetës në një të rritur sipas konsensusit diagnostikues të Fondacionit të Fibrozës Cistike të vitit 2017. Kategoritë aktuale janë nën 30 mmol/L, 30–59 mmol/L dhe të paktën 60 mmol/L për të gjitha moshat. Disa diapazone më të vjetra laboratorike përdornin 40 mmol/L si kufirin ndërmjetës pas foshnjërisë. Prandaj, një rezultat prej 35 mmol/L te një i rritur duhet të shqyrtohet në kontekstin klinik në vend që të hidhet poshtë duke përdorur një interval të vjetëruar.
Sa shpejt duhet përsëritur një test i ndërmjetëm i djersës?
Një rezultat i ndërmjetëm i klorurit të djersës prej 30–59 mmol/L në përgjithësi kërkon testime të përsëritura kuantitative brenda 1–2 muajve në një qendër me përvojë, të akredituar siç duhet. Foshnjat simptomatike, rritja e dobët, ose shqetësimet e rëndësishme respiratore ose pankreatike kërkojnë vlerësim më të hershëm nga specialistë. Fëmijët të cilët janë caktuar posaçërisht CRMS/CFSPID ndjekin një plan më afatgjatë që përfshin testime të përsëritura të djersës në moshën 6 muajshe dhe çdo vit deri në të paktën moshën 8 vjeç. Testimi i përsëritur diagnostikues dhe plani i vazhdueshëm i mbikëqyrjes shërbejnë qëllimeve të ndryshme.
A mund të paraqitet fibrozë cistike me klorur të djersës nën 30?
Fibroza cistike mund të ndodhë ndonjëherë me klorur uji poshtë 30 mmol/L, veçanërisht kur varianta të caktuara CFTR ruajnë funksionin e kanalit të djersës. Një rezultat i ulët e bën CF më pak të mundshëm, por nuk e përjashton plotësisht atë kur simptomat ose gjenetika janë sugjeruese. Bronkiektazia e vazhdueshme, pankreatiti i përsëritur ose malabsorbimi i pashpjegueshëm mund të justifikojnë vlerësim të mëtejshëm nga specialistë. Duhet të konfirmohet gjithashtu një mostër e mjaftueshme dhe metoda kuantitative e saktë.
A mos shpjegon një mutacion CFTR testin kufitar të djersës?
Një variant i identifikuar i CFTR që shkakton CF nuk e vërteton vetë fibrozën cistike ose nuk shpjegon plotësisht një rezultat të klorurit të djersës prej 30–59 mmol/L. Një panel i kufizuar mund të humbasë një variant tjetër, dhe simptomat klinike mund të kenë një shkak tjetër. Sekuencimi i zgjatur, analiza e fshirjes/dyfishimit dhe këshillimi gjenetik mund të jenë të përshtatshme kur dyshimi mbetet. Nëse gjenden 2 variante, klasifikimi i tyre dhe nëse ato janë në kopje të kundërta të gjeneve gjithashtu kanë rëndësi.
Çfarë do të thotë "sasia nuk është e mjaftueshme" në një test djersë?
Sasia e pamjaftueshme, ose QNS, do të thotë se është mbledhur shumë pak djersë për të dhënë një rezultat diagnostikues të besueshëm. Sasi minimale të zakonshme janë 15 µL për mbledhjen Macroduct ose 75 mg për mbledhjen me garzë ose letër filtruese. QNS nuk është një test negativ i klorurit të djersës dhe nuk mund të përjashtojë fibrozën cistike. Nevojitet mbledhje e përsëritur, dhe faqet e veçanta të mbledhjes nuk duhet të bashkohen për të arritur minimumin.
Merrni sot analizë të analizave të gjakut me AI
Bashkohuni me mbi 2 milionë përdorues në mbarë botën që i besojnë Kantesti për analizë të menjëhershme dhe të saktë të analizave laboratorike. Ngarkoni rezultatet e analizave të gjakut dhe merrni interpretim gjithëpërfshirës të biomarkerëve të 15,000+ brenda sekondash.
📚 Publikime kërkimore të cituara
Klein, T., Mitchell, S., & Weber, H. (2026). Testi i Urobilinogjenit në Urinë: Udhëzues i plotë për Analizën e Urinës 2026. Kantesti Kërkim Mjekësor me AI.
Klein, T., Mitchell, S., & Weber, H. (2026). Udhëzues për Studimet e Hekurit: TIBC, Ngopja e Hekurit dhe Kapaciteti Lidhës. Kantesti Kërkim Mjekësor me AI.
📖 Referenca të jashtme mjekësore
Green DM et al. (2024). Cystic Fibrosis Foundation Evidence-Based Guideline for the Management of CRMS/CFSPID. Pediatrics.
LeGrys VA et al. (2007). Diagnostic Sweat Testing: The Cystic Fibrosis Foundation Guidelines. Gazeta e Pediatrisë.
⚕️ Mohim përgjegjësie mjekësore
Ky artikull është vetëm për qëllime edukative dhe nuk përbën këshilla mjekësore. Gjithmonë konsultohuni me një ofrues të kualifikuar të kujdesit shëndetësor për vendimet e diagnozës dhe trajtimit.
Sinjalet e Besimit E-E-A-T
Përvoja
Rishikim klinik i udhëhequr nga mjeku i flukseve të punës për interpretimin e analizave.
Ekspertizë
Fokus i mjekësisë laboratorike mbi mënyrën se si sillen biomarkerët në kontekstin klinik.
Autoritariteti
Shkruar nga Dr. Thomas Klein me rishikim nga Dr. Sarah Mitchell dhe Prof. Dr. Hans Weber.
Besueshmëria
Interpretim i bazuar në prova, me rrugë të qarta për ndjekje për të reduktuar alarmin.