Skilgreind svitalausnarklukurstig milli 30–59 mmol/L staðfestir ekki cystic fibrosis. Það þýðir að niðurstöðu þarf að fylgja eftir: venjulega með endurteknum prófum á reyndri miðstöð, yfirferð einkenna og nýbura-skimunar, og stundum CFTR erfðafræðilegu eða hagnýtu mati.


- Lág svitalausnarklukur: Minna en 30 mmol/L gerir cystic fibrosis ólíklegri, en útilokar hana ekki algjörlega þegar einkenni eða erfðafræði eru sterklega til sýnis.
- Millistig svitalausnarklukur: Gildi 30–59 mmol/L eru óljós — ekki staðfest cystic fibrosis greining og ekki sjálfkrafa arfberalíníustig.
- Hækkuð svitalausnarklukur: Gild niðurstaða 60 mmol/L eða hærri styður cystic fibrosis í viðeigandi klínískum aðstæðum og þarf staðfestingu sérfræðinga.
- Endurtekt: Millistig niðurstaða krefst almennt annarrar svitalausnarklukurprófunar innan 1–2 mánaða, með fyrri mati fyrir einkennabörn eða áhyggjuefni.
- Öll aldursskeið: Núverandi greiningarmörk Cystic Fibrosis Foundation nota minna en 30, 30–59, og að minnsta kosti 60 mmol/L fyrir ungbörn, börn og fullorðna.
- Gæði sýnis: Ófullnægjandi svitastýni er ekki hægt að tilkynna sem áreiðanlega neikvæða niðurstöðu; aðskilin söfnunarsvæði ætti ekki að sameina.
- CFTR mat: Einkennandi millistiganið úrslit, grunur um sjúkdóm eða óeðlilegt nýburaskimun getur réttlætt röðun, greiningu á eyðingu/tvöföldun og erfðaráðgjöf.
- AI takmarkanir: Svitaklórmælingar mæla svita, ekki blóð. AI túlkun á meðfylgjandi rannsóknarniðurstöðum getur ekki staðfest eða útilokað cystískir blaðrur.
Hvað þýða lág, millistig, og hækkuð niðurstöður?
Svitaklórmælingar undir 30 mmol/L gera cystískir blaðrur ólíklegri; 30–59 mmol/L er millistig; og 60 mmol/L eða hærra styður cystískir blaðrur í réttu klínísku samhengi. Á mörkum niðurstaða er ástæða til að rannsaka – ekki greining, alvarleikastig eða ástæða til að hefja meðferð á eigin spýtur.
Samþykki Cystic Fibrosis Foundation frá 2017 beitir þessum 3 þröskuldum yfir aldurshópa, frekar en að nota hærri millistigabakanda fyrir eldri börn og fullorðna (Farrell o.fl., 2017). Sum eldri skýrslur lýsa enn 40–59 mmol/L sem á mörkum eftir ungbarnaeinkenni; niðurstaða 35 mmol/L ætti ekki að hunsa einfaldlega vegna þess að úrelt viðmiðunarbil kallar það eðlilegt.
Niðurstaða 59 mmol/L og ein 60 mmol/L falla í mismunandi flokka, en líffræði breytist ekki skyndilega á milli þessara talna. Gæði sýnis, einkenni, skimunarsaga og endurteknar mælingar ákvarða hversu örugglega flokkinn er hægt að nota. Okkar skýring á fráviksmerkingum rannsóknarstofu útskýrir af hverju merkt tala er ekki greining sjálf.
Ég er Thomas Klein, MD, aðal læknir hjá Kantesti, og klínísk nálgun mín er að aðgreina mælinguna frá greiningunni áður en fjallað er um hvorttveggja. Kantesti er AI blóðprófgreiningartæki; svitaklóri er sérstakt sérfræðipróf, ekki blóðlíkamamerki. Okkar stofnun og klíníska umboð útskýra þann mun, sem skiptir máli sérstaklega þegar einhver hleður inn blönduðri rannsóknarskýrslu.
Hvað mælir svitalausnarklukurprófið raunverulega?
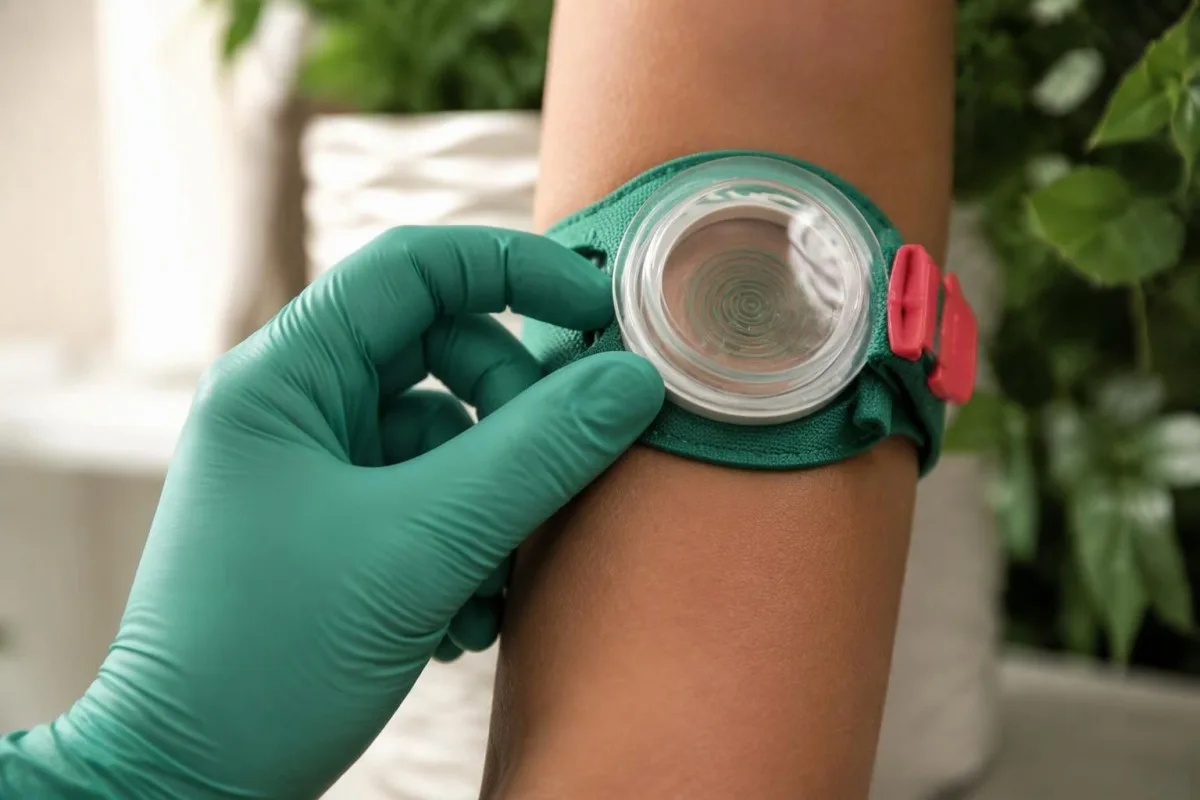
Svitaklórt próf mælir klórþéttni í svita eftir að pilocarpine örvar lítið svæði til söfnunar. Það metur eina afleiðingu CFTR rásarstarfsemi: hversu áhrifarík svitakirtill endurupptekur klór áður en sviti kemst á yfirborðið. Greiningarniðurstaðan er gefin upp í mmol/L, ekki sem magn svita sem framleiddur er.
The sweat gland first produces fluid, and its duct then reabsorbs salt. Reduced CFTR function can leave more chloride in the final sweat, producing values of 60 mmol/L or higher in many people with cystic fibrosis. This is a functional clue, but it does not directly measure lung damage, pancreatic function, or the number of genetic variants present.
Sweat chloride and serum chloride describe different compartments. A person can have elevated sweat chloride while the chloride concentration in a metabolic panel is normal—or low after substantial salt loss. Our discussion of serum chloride and fluids concerns blood chemistry; its reference intervals cannot be substituted for the 30–59 mmol/L sweat interval.
The units can also look different without representing different thresholds: for chloride, 1 mmol/L equals 1 mEq/L because chloride has a single electrical charge. Sweat conductivity is another matter—it reflects multiple ions, often expressed as sodium chloride equivalents. A conductivity result must not be interpreted using diagnostic sweat chloride thresholds, even when the report looks reassuringly numerical.
Af hverju staðfestir millistig niðurstaða ekki cystic fibrosis?
An intermediate sweat chloride result does not confirm cystic fibrosis because 30–59 mmol/L overlaps several clinical situations. These include some people with cystic fibrosis, people with other CFTR-associated conditions, and people without a CFTR disorder. The same value can therefore lead to different conclusions depending on the evidence around it.
For an illustrative comparison, consider a thriving infant with 38 mmol/L after newborn screening and an adult with 38 mmol/L plus recurrent pancreatitis and bronchiectasis. Neither number independently proves cystic fibrosis, but the second history raises different diagnostic questions. This is why I would not attach a single percentage probability to every borderline sweat chloride test without knowing the referral context.
Persistent intermediate results on 2 separate occasions can still occur in cystic fibrosis, and the 2017 consensus recommends considering extended CFTR analysis or specialized functional testing in that setting (Farrell et al., 2017). Conversely, 2 intermediate measurements do not automatically convert uncertainty into a confirmed diagnosis. Repetition establishes persistence; it does not explain the cause by itself.
Borderline is also not another word for carrier. A person with 1 identified CF-causing variant may be a carrier, but the initial genetic panel might have missed another variant, or the symptoms may have another explanation. Our discussion of borderline stool test follow-up illustrates the broader distinction between an indeterminate measurement and a named disease; the follow-up tests themselves are different.
Hvað krefst jákvæð svitalausnarklukur niðurstaða næst?
A properly collected sweat chloride result of at least 60 mmol/L supports a cystic fibrosis diagnosis when there is compatible newborn screening, a relevant family history, or characteristic clinical features. Specialist assessment should follow promptly. Confirmation usually uses repeat testing on a separate date or an independent diagnostic method, such as appropriate CFTR analysis.
A report saying sweat chloride test positive deserves more than a telephone message reading only the flag. Ask for the actual concentration, the collection method, whether the sample was sufficient, and the plan for confirmation. A measured chloride of 72 mmol/L is meaningful evidence; a positive conductivity screening result is not an interchangeable diagnostic finding.
The distinction between a category and a concentration matters at both ends of the scale. Chloride concentrations above roughly 160 mmol/L are outside the expected physiological range for sweat and should trigger immediate laboratory review rather than assumptions about unusually severe disease. The collection and analytical record may be more informative than another decimal place on the report.
Positive-range sweat chloride is not, by itself, an emergency severity score. A clinically stable child with 68 mmol/L needs a timely CF specialist pathway; a child with dehydration or breathing difficulty needs urgent care regardless of the sweat value. Our guide to eigindlegar og megindlegar niðurstöður explains why the measured number should accompany the positive label.
Getur lág niðurstaða útilokað cystic fibrosis?
Sweat chloride below 30 mmol/L makes cystic fibrosis less likely, but cannot absolutely exclude it when symptoms or CFTR findings are strongly suggestive. A low result is most reassuring when the sample was valid, the person has no characteristic symptoms, and the screening or family-history concern has been adequately addressed.
Certain CFTR variants preserve enough sweat-duct function to produce lower chloride concentrations despite clinically relevant disease. The 2017 consensus therefore allows further evaluation when a value below 30 mmol/L conflicts with genotype or evolving clinical features (Farrell et al., 2017). A normal newborn screen also does not eliminate every possible CF diagnosis in a child who later develops suggestive symptoms.
Age does not create a separate low-result exception: a value of 27 mmol/L has the same diagnostic category in a toddler and an adult. What changes is the history available to interpret it—growth trajectory in a young child, for example, versus years of recurrent pancreatitis or unexplained bronchiectasis in an adult. The referral question should travel with the laboratory result.
A child with 24 mmol/L, persistent greasy stools, and faltering growth still needs an explanation for the symptoms, even if cystic fibrosis becomes less likely. The next step may include pancreatic, gastrointestinal, or nutritional assessment rather than simply repeating every test. Our guidance on takmarkanir á túlkun AI fyrir börn explains why pediatric decisions require age-specific clinical oversight.
Hvernig eru millistig niðurstöður meðhöndlaðar eftir nýbura-skimun?
An infant with an abnormal newborn screen and intermediate sweat chloride needs assessment through a CF specialist pathway, but may not have cystic fibrosis. Some clinically well infants receive the designation CRMS/CFSPID, meaning the screening and diagnostic findings remain inconclusive. This designation has specific criteria; it should not be applied to every borderline result.
CRMS/CFSPID generally applies after positive newborn screening when sweat chloride is below 30 mmol/L with 2 CFTR variants, at least 1 of uncertain consequence, or when chloride is 30–59 mmol/L with no more than 1 CF-causing variant. The infant should not have clinical features establishing CF. A symptomatic child or an adult with borderline chloride needs a different diagnostic framing.
The 2024 Cystic Fibrosis Foundation guideline recommends repeat sweat chloride at 6 months and annually through at least age 8 for children with CRMS/CFSPID (Green et al., 2024). Fewer than 10% are reclassified as CF in the evidence summarized by that guideline, although individual risk varies. That estimate describes a defined screened population—not all children with intermediate chloride.
For screen-positive newborns, diagnostic sweat testing is generally arranged after 10 days of age and ideally by 4 weeks, when the infant is over 2 kg and at least 36 weeks corrected gestational age. Feeding, stool pattern, and weight gain help determine urgency. Our explanation of pediatric growth assessment addresses broader growth questions; a borderline sweat result does not itself justify growth-hormone testing.
Hvað þýðir landamæra svitalausnarklukur hjá fullorðnum?
Sweat chloride levels 30–59 mmol/L are intermediate in adults, just as they are in children. Persistent intermediate results deserve particular attention when there is unexplained bronchiectasis, recurrent pancreatitis, chronic sinus disease with other suggestive features, or obstructive infertility. Adult diagnosis is possible; age alone does not exclude cystic fibrosis.
Imagine an illustrative 34-year-old with chloride of 44 mmol/L, repeated pancreatitis, and otherwise normal routine blood chemistry. The normal metabolic panel does not settle the CFTR question, because it measures neither sweat-duct transport nor pancreatic duct function. A specialist might pursue extended genetics and pancreatic assessment while also checking more common causes of recurrent pancreatitis.
Bronchiectasis has several possible causes, and 1 intermediate sweat result should not end that investigation. Depending on the history, clinicians may evaluate immune deficiency, aspiration, ciliary disorders, and other inherited respiratory conditions. Our guide to alfa-1 antitrypsin prófun discusses a different inherited lung-risk pathway; it is complementary only when the clinical pattern supports testing.
Male infertility can occasionally be the first clue to CFTR-associated disease, especially when congenital absence of the vas deferens causes obstruction. A sperm count of 0 is not enough to establish that anatomy or a CF diagnosis, and hormonal explanations require different evaluation. Our semen analysis interpretation guide explains why reproductive assessment must accompany—not be replaced by—CFTR testing.
Gætu söfnunarvandamál gert niðurstöðuna villandi?
Collection problems can make sweat chloride results unreliable, and insufficient sweat is not a negative test. Evaporation, contamination, incorrect handling, and inadequate sample volume can interfere with interpretation. Before drawing conclusions from a borderline result, confirm that the laboratory performed quantitative chloride analysis on an acceptable sample.
Common minimum quantities are 75 mg for gauze or filter-paper collection and 15 µL for a Macroduct collection system; collection generally lasts no more than 30 minutes. Samples from separate sites should not be pooled to reach the minimum. The Cystic Fibrosis Foundation sweat-testing guidance describes these collection safeguards because an apparently precise number cannot rescue an inadequate specimen (LeGrys et al., 2007).
A report marked QNS—quantity not sufficient—means no reliable diagnostic concentration was obtained. If one arm yields an acceptable sample and the other does not, the center should explain which result is valid; the unsuccessful site is not a second negative measurement. Likewise, conflicting bilateral values should prompt a quality review rather than an improvised average that hides disagreement.
Copied reports introduce another avoidable problem: 35 mmol/L can become 85 mmol/L through transcription or image-reading error. Our PDF afskriftar eftirlitslisti is useful for verifying numbers against the original report, not for validating the sweat procedure. Kantesti’s klínískir staðlar og takmarkanir should also be distinguished from accreditation of the laboratory that collected and measured the sweat.
Hvenær skal prófað endurtekið á viðurkenndri miðstöð?
An intermediate sweat chloride result generally warrants repeat quantitative testing within 1–2 months at an accredited CF center or an appropriately accredited laboratory experienced in sweat testing. Earlier specialist assessment is appropriate for symptomatic infants, poor growth, recurrent pancreatitis, or significant respiratory concerns. Persistent uncertainty should not be managed through repeated low-quality collections.
The right center depends on your country: CF-center accreditation and laboratory accreditation are related but not identical. Ask whether the laboratory regularly performs pediatric and adult sweat chloride testing, monitors insufficient-sample rates, and uses quantitative chloride rather than conductivity alone. For a result of 46 mmol/L, an experienced collection team may be more useful than choosing a laboratory solely for convenience.
Repeat tests can cross categories because of biological and analytical variation. Values of 29 and 33 mmol/L on separate dates deserve context; they do not prove that CFTR function suddenly deteriorated. Our discussion of laboratory changes over time explains the general distinction between variation and disease progression, although sweat testing has its own collection requirements.
For a valid repeat, follow the center’s instructions, maintain normal hydration, and avoid lotions or creams on the collection site. Do not fast, overdrink water, or stop prescribed medicines unless instructed; disclose all medicines, especially CFTR modulators. If the first sample was QNS, the repeat may simply be the first interpretable test—not a confirmation of any earlier diagnostic category.
Hvenær er CFTR erfðafræðilegt mat viðeigandi?
CFTR genetic evaluation is appropriate when sweat chloride remains intermediate, newborn screening is abnormal, family history is relevant, or characteristic symptoms persist despite a low result. Testing may need to extend beyond a common-variant panel to sequencing and deletion/duplication analysis. A negative limited panel cannot exclude all clinically relevant CFTR variants.
Finding 2 variants is not automatically equivalent to finding 2 CF-causing variants. Classification matters, and the variants usually need to be on opposite gene copies—in trans—to support the recessive diagnostic explanation. Parental testing can help establish phase; 2 variants on the same copy, in cis, leave the other copy unresolved.
A variant of uncertain significance cannot be promoted to a disease-causing finding simply because sweat chloride is 41 mmol/L. Specialists combine curated variant evidence, the phenotype, family testing, and sometimes functional assessment. Genetic counseling should explain what the result establishes, what it leaves unanswered, and whether relatives or a reproductive partner need targeted evaluation.
Kantesti is an AI blood test interpretation platform, not a CFTR variant-classification laboratory. Our AI tækni útskýring describes how laboratory information is organized, but 1 unresolved genetic finding requires qualified interpretation rather than an automated disease label. When I review accompanying chemistry, I treat the genetic report as a separate evidence source with its own method, coverage, and limitations.
Hvaða viðbótarpróf geta skýrt óljósa niðurstöðu?
Specialist CFTR functional tests can help when sweat chloride and genetics remain inconclusive. Nasal potential difference assesses ion transport in nasal epithelium, while intestinal current measurement assesses transport in intestinal tissue. These tests require validated protocols at experienced reference centers; they are not routine blood tests or interchangeable screening tools.
The 2017 consensus recommends that nasal potential difference and intestinal current measurement be performed in validated reference centers when needed for diagnosis (Farrell et al., 2017). Availability varies internationally, and 1 abnormal functional measurement must be interpreted using the center’s protocol and clinical context. Referral is often more sensible than asking a general laboratory to improvise an unfamiliar assay.
Organ-specific tests answer different questions. Fecal elastase below 200 µg/g can suggest pancreatic exocrine insufficiency, but a watery sample may dilute the measurement and a normal result does not exclude pancreatic-sufficient CF. Our leiðbeiningar um túlkun á hægðaróni explains those limitations; pancreatic status is evidence about organ function, not a substitute for establishing CFTR-related diagnosis.
Fat malabsorption may also justify stool-fat assessment, with collection and dietary requirements determined by the laboratory. Adult fecal fat above about 7 g/day on an appropriate standardized intake suggests steatorrhea, but the cause may be pancreatic, intestinal, or biliary. Our fecal fat result guide helps separate documenting malabsorption from naming its cause.
Getur aðrir sjúkdómar eða lyf haft áhrif á svitalausnarklukur?
Technical problems and some non-CF conditions can produce elevated or intermediate sweat chloride, while medicines can affect sweat production or CFTR function. Severe malnutrition, untreated hypothyroidism, and adrenal insufficiency are among reported non-CF associations. These possibilities require a clinically directed assessment; they should not become an excuse to dismiss a valid result of 60 mmol/L or higher.
Adrenal insufficiency deserves consideration when fatigue, weight loss, low blood pressure, pigmentation changes, or abnormal electrolytes accompany the diagnostic question. A sweat value of 48 mmol/L alone does not justify a cortisol workup, but the combined pattern may. Our guide to adrenal insufficiency warning signs explains when symptoms make that alternative urgent.
Malnutrition can be a confounder and also a consequence of an underlying disorder, so correcting nutrition does not automatically resolve the CF question. A child with 43 mmol/L and chronic diarrhea may need evaluation for celiac disease or another malabsorption cause as well as CFTR assessment. Our explanation of IgA-related celiac testing pitfalls is relevant when negative celiac antibodies conflict with a suggestive history.
CFTR modulators can lower sweat chloride because they improve channel function; a treated value below 30 mmol/L does not erase an established CF diagnosis. Drugs that reduce sweating, such as topiramate in some patients, can make adequate collection harder without providing a reliable prediction of chloride concentration. Give the center a complete medication list, and never stop treatment just to produce an untreated number.
Hvað ættu fjölskyldur að gera meðan greining er óviss?
While a borderline result is being clarified, keep specialist follow-up, monitor relevant symptoms, and avoid starting CF-specific treatment without an indication. A sweat chloride value of 30–59 mmol/L does not justify routine pancreatic enzymes, antibiotics, high-dose vitamins, or extra salt on its own. Supportive care should address demonstrated problems rather than a provisional label.
Bring the original sweat report, newborn-screening record if applicable, genetic report, medication list, and growth measurements to the appointment. Recording 2–3 concrete observations—such as stool frequency, weight trend, or repeated chest illnesses—is usually more useful than an exhaustive diary. Ask who will arrange the repeat test and who will explain a result that remains intermediate.
Nutrition testing should be driven by symptoms and growth, not by the sweat number alone. Iron deficiency can accompany restricted intake or malabsorption, but a ferritin result does not confirm CF; iron treatment also needs an appropriate indication. Our complete iron studies guide explains how to distinguish low stores from inflammation-related changes when a clinician requests that assessment.
Routine chemistry can help assess complications: low chloride and bicarbonate elevation may accompany salt depletion, while low albumin needs a separate nutritional, hepatic, or protein-loss explanation. Our leiðbeiningar um greiningu á sermisprótínum provides that context. Seek urgent care for breathing difficulty, marked lethargy, repeated vomiting, or substantially reduced urination—do not wait 1–2 months for the planned sweat retest.
Hvernig ætti að útskýra og skjalfesta niðurstöðuna?
A useful sweat chloride explanation records the exact value, units, collection quality, clinical context, and next diagnostic step. As of October 8, 2026, this article uses the 2017 CF diagnostic consensus and the 2024 CRMS/CFSPID management guideline—not a newly invented 2026 cutoff. The central distinction remains unchanged: intermediate is not confirmed CF.
For a result of 42 mmol/L, a clear clinical note might say: intermediate quantitative sweat chloride, adequate sample, CF diagnosis unresolved, repeat at an experienced center and review CFTR testing. That wording is more useful than possible CF without a plan. If the repeat is below 30 mmol/L but symptoms remain concerning, the note should explain why investigation is continuing.
Kantesti is an AI lab test interpretation service that can help explain accompanying blood chemistry, but cannot confirm cystic fibrosis from sweat chloride or genetics. At Kantesti, the safe boundary is to distinguish report explanation from specialist diagnosis; our medical advisory responsibilities describe the role of clinical oversight. A value of 60 mmol/L or higher should trigger a clinical pathway, not an AI-generated treatment prescription.
As Thomas Klein, MD, my practical recommendation is to ask 3 questions: was the specimen valid, does the clinical story fit, and what evidence will resolve the uncertainty? The related Zenodo publications below address general laboratory interpretation, not sweat chloride diagnostic validation. The CF-specific external references are the sources supporting the thresholds, confirmation strategy, and follow-up recommendations in this article.
Algengar spurningar
Þýðir grenjandi svitalykt þroskaþroska?
Niðurstaða úr svitalindarsölti sem er á mörkum (30–59 mmól/L) útilokar ekki ein og sér cystal firbræðing. Bilinu skarast við fólk með CF, aðrar CFTR-tengdar sjúkdóma og enga CFTR-röskun. Endurtekin magnbundin próf á reyndu miðstöð, yfirferð á einkennum og skimun, og stundum víðtækari CFTR-mat eru viðeigandi. Jafnvel 2 milliliða niðurstöður krefjast viðbótarútskýringa fremur en sjálfkrafa greiningar.
Hvað þýðir jákvæð svitalaugaprófsniðurstaða?
Mælt klórþéttni í svita sem er 60 mmól/L eða hærri er á jákvæðu greiningarsviði og styður cystic fibrosis með samhæfðum klínískum einkennum, nýburaskimun eða fjölskyldusögu. Sýnið verður að uppfylla kröfur um söfnun og greiningu. Sérfræðingastaðfesting felur venjulega í sér endurteknar prófanir á öðrum degi eða sjálfstæð greiningaraðferð. Jákvæð svitaleiðnimæling er ekki skiptanleg við jákvæða mælda klórþéttni.
Er 35 í svitaklórríðingu eðlilegt hjá fullorðnum?
Svitklóríðgildi sem nemur 35 mmól/L er millistig í fullorðnum samkvæmt samþykkt Cystic Fibrosis Foundation frá 2017. Núverandi flokkar eru undir 30 mmól/L, 30–59 mmól/L og að minnsta kosti 60 mmól/L fyrir allar aldir. Sum eldri rannsóknarstofuviðmið notuðu 40 mmól/L sem millistigsmörk eftir unglingsár. Því ætti að meta fullorðinsgildi sem nemur 35 mmól/L í klínísku samhengi frekar en að líta framhjá því með úreltu viðmiði.
Hversu fljótt á að endurtaka svitaþolspróf?
Miðlungs niðurstaða úr svitaklópræðingum milli 30–59 mmol/L kallar almennt á endurteknar magnbundnar prófanir innan 1–2 mánaða á sérfræðingamiðstöð sem hefur tilskilin leyfi og reynslu. Ungbörn með einkenni, lélegur vöxtur eða verulegar áhyggjur af öndunar- eða brisstarfsemi réttlæta fyrri mat sérfræðings. Börn sem sérstaklega eru skilgreind sem CRMS/CFSPID fylgja lengra prófunaráætlun sem felur í sér endurteknar svitaprófanir 6 mánaða og árlega allt að minnsta kosti 8 ára aldri. Endurteknar prófanir í greiningarskyni og áframhaldandi eftirlit þjóna mismunandi tilgangi.
Getur cystic fibrosis komið fram við svitaklórsgildi undir 30?
Cystic fibrosis getur stundum komið fyrir með svitalyklóríðmælingu undir 30 mmol/L, sérstaklega þegar ákveðnar CFTR-afbrigði varðveita virkni svitastúta. Lág niðurstaða gerir CF ólíklegri en útilokar hana ekki alveg þegar einkenni eða erfðafræði benda sterkt til þess. Einkennandi berkjubólga, endurtekin brisbólga eða óútskýrð vanfrásog getur réttlætt frekari sérfræðingamat. Næginlegt sýnishorn og rétt magnbundin aðferð verða einnig að vera staðfest.
Skýrir ein CFTR-mútaun komið á óljóst svitalpróf?
Eitt greint CF-valda CFTR-afbrigði einangrað stofnar ekki cystic fibrosis né útskýrir að fullu svitalyktunarmælingu frá 30–59 mmol/L. Takmarkaður spjaldi getur misst annað afbrigði, og klínísk einkenni geta haft aðra orsök. Framlengd röðun, greining á eyðingu/tvöföldun og erfðaráðgjöf geta verið viðeigandi þegar grunur er enn til staðar. Ef 2 afbrigði finnast, skiptir flokkun þeirra og hvort þau séu á mótlægum genaafritum einnig máli.
Hvað þýðir „magn ekki nægilegt“ á svita prófi?
Ófullnægjandi magn, eða QNS, þýðir að of lítið sviti var safnað til að fá áreiðanlega greiningarniðurstöðu. Algeng lágmarks magn eru 15 µL fyrir Macroduct söfnun eða 75 mg fyrir svamp- eða síupappírssöfnun. QNS er ekki neikvætt svitaklóprófun og getur ekki útilokað cystalækni. Endurtekin söfnun er nauðsynleg, og ekki má sameina aðskildar söfnunarstaði til að ná lágmarki.
Fáðu AI-knúna greiningu á blóðprufum í dag
Vertu með yfir 2 milljónir notenda um allan heim sem treysta Kantesti fyrir tafarlausa og nákvæma greiningu á blóðprufum. Hladdu upp niðurstöðum blóðrannsókna þinna og fáðu yfirgripsmikla túlkun á 15,000+ lífmerkjum á sekúndum.
📚 Tilvísuð rannsóknarútgáfa
Klein, T., Mitchell, S., & Weber, H. (2026). Þvagþéttniþvagefni í þvagprófi: Leiðarvísir um heildarþvaggreining 2026. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). Leiðbeiningar um járnrannsóknir: TIBC, járnmettun og bindingargeta. Kantesti AI Medical Research.
📖 Ytri læknisfræðilegar heimildir
Green DM et al. (2024). Cystic Fibrosis Foundation Evidence-Based Guideline for the Management of CRMS/CFSPID. Barnalækningar.
LeGrys VA et al. (2007). Diagnostic Sweat Testing: The Cystic Fibrosis Foundation Guidelines. Tímarit fyrir börn.
⚕️ Fyrirvari vegna læknisfræðilegra mála
Þessi grein er eingöngu til fræðslu og felur ekki í sér læknisráðgjöf. Leitaðu alltaf til hæfs heilbrigðisstarfsmanns vegna ákvarðana um greiningu og meðferð.
E-E-A-T traustmerki
Reynsla
Læknastýrð klínísk yfirferð á vinnuferlum við túlkun rannsóknarniðurstaðna.
Sérþekking
Áhersla á rannsóknarstofulækningar: hvernig lífmarkarar hegða sér í klínísku samhengi.
Yfirvald
Skrifað af Dr. Thomas Klein með yfirferð Dr. Sarah Mitchell og próf. Dr. Hans Weber.
Traustleiki
Rökstudd túlkun byggð á gögnum með skýrum eftirfylgnileiðum til að draga úr ávörun.