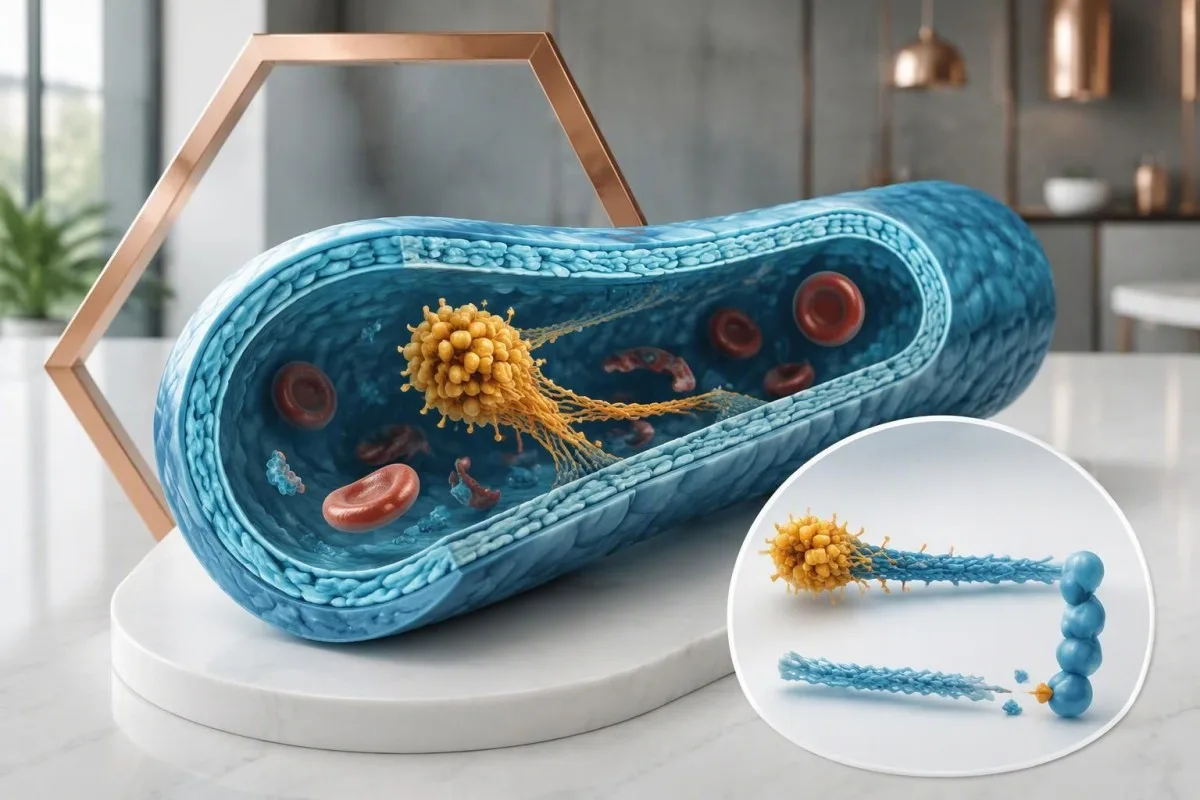
ADAMTS13 aktivitāte zem 10% spēcīgi atbalsta TTP, ja kopā ir zems trombocītu skaits un sarkano asins šūnu iznīcināšana, taču izolēts rezultāts nenozīmē akūtu epizodi. Aizdomas par TTP prasa neatliekamu izvērtēšanu un ārstēšanas lēmumu pieņemšanu, negaidot laboratorijas rezultātu.


- Smags deficīts nozīmē ADAMTS13 aktivitāti zem 10%; tas spēcīgi atbalsta TTP saderīgā klīniskā aina.
- Neatliekama izvērtēšana ir prioritāte, kad trombocitopēnija un mikroangiopātiskā hemolītiskā anēmija liecina par TTP, pat pirms ADAMTS13 rezultātu saņemšanas.
- Aktivitāte mēra fermenta darbību; 5% aktivitāte nenozīmē 5% iespējamību saslimt ar TTP.
- Inhibitoru testēšana nosaka funkcionālu traucējumu ar ADAMTS13, savukārt antivielu testēšana var noteikt saistošas antivielas, kas neinhibē laboratorijas reakciju.
- Paraugu ņemšana pirms ārstēšanas ir vēlama, jo plazmas infūzija vai apmaiņa var paaugstināt aktivitāti un samazināt nosakāmās antivielas vai inhibitoru līmeni.
- Robežvērtību aktivitāte apmēram 10–20% prasa speciālistu interpretāciju; tas pats par sevi nevar droši atrisināt spēcīgi aizdomīgu prezentāciju.
- Klīniskā remisija var pastāvēt līdzās aktivitātei zem 10%; zems uzraudzības rezultāts signalizē par recidīva risku, nevis automātiski pierāda akūtu recidīvu.
- AI interpretācija var palīdzēt izskaidrot pārskatus, bet nekad nedrīkst aizkavēt neatliekamo palīdzību vai aizstāt hematologa ārstēšanas lēmumus.
Vai zema ADAMTS13 aktivitāte automātiski nozīmē TTP?
Zema ADAMTS13 aktivitāte nenozīmē automātiski akūtu TTP epizodi. aktivitāte zem 10% spēcīgi atbalsta trombotisko trombocitopēnisko purpuru, ja pacientam ir arī trombocitopēnija un mikroangiopātiskā hemolītiskā anēmija; aizdomas par TTP prasa neatliekamu novērtēšanu, negaidot apstiprinājumu.
2020. gada ISTH diagnostikas vadlīnijas identificē ADAMTS13 aktivitāte zem 10% kā TTP galveno laboratorisko atradumu, interpretējot to kopā ar prezentāciju un paraugu ņemšanas laiku (Zheng et al., 2020). Personai ar aktivitāti 4%, krītošām trombocītām un fragmentētām sarkanajām šūnām nepieciešama ļoti atšķirīga reakcija nekā personai ar tādu pašu aktivitāti remisijas periodā.
Apsveriet ilustratīvu pacientu ar trombocītu skaitu ir WBC, hemoglobīna līmeni 8,7 g/dL un jaunu apjukumu: šāda kombinācija prasa tūlītēju hospitalizāciju, nevis rutīnas atkārtotu vizīti. Šistocītu interpretācijas ceļvedis izskaidro, kāpēc fragmentētās šūnas piešķir steidzamību, lai gan to neesamība agrīnā slaidā nedroši neizslēdz TTP.
Kantesti ir AI asins analīžu analizators kas var palīdzēt izskaidrot, kāpēc aktivitāte zem 10% ir svarīga kopā ar trombocītu un hemolīzes rezultātiem, taču tā nevar noteikt, vai esat drošībā mājās. Mana pieeja kā Thomas Klein, MD, ir nekavējoties atdalīt divus jautājumus: vai tas liecina par smagu fermentu deficītu un vai ir pierādījumi par pašreiz notiekošu ārkārtas situāciju?
Ko dara ADAMTS13 un kāpēc 10% ir svarīgs?
ADAMTS13 sagriež neparasti lielus von Willebrand faktora multimērus mazākās formās, ierobežojot neatbilstošu trombocītu pielipšanu mazos asinsvados. Aktivitāte zem 10% nozīmē šīs funkcijas smagu zudumu; tas nav slimības varbūtības procentuālais novērtējums vai trombocītu skaita mērījums.
Bez pietiekami daudz strādājoša enzīma lieli von Willebrand faktora multimēri var veidot trombocītu agregātus mikrovaskulāros kanālos, patērējot cirkulējošos trombocītus un traumējot sarkanās šūnas, kas iziet cauri sašaurinātajiem kanāliem. Tas izskaidro acīmredzami pretrunīgo kombināciju ar trombu izraisītu orgānu bojājumu un zemu trombocītu skaitu; aktivitāte 3% apraksta fermentu darbību, nevis koagulācijas daudzumu visā ķermenī.
The 10% slieksnis nāk no klīniskām liecībām, kas atšķir smagu ADAMTS13 deficītu no daudzām citām trombotiskām mikroangiopātijām, nevis no asas bioloģiskās atslēgšanās starp 9% un 11%. Tuvāk šai robežai ir jāpievērš uzmanība analīžu variācijai, ārstēšanas ietekmei un klīniskajam modelim; hematologs var pieprasīt apstiprinājumu, izmantojot citu metodi, ja rezultāts un prezentācija nesakrīt.
Daudzas laboratorijas ziņo par pieaugušo atsauces intervāliem aptuveni ap 50–150%, but the actual interval is assay-specific and may differ substantially. Do not confuse TTP with von Willebrand disease: the von Willebrand disease testing guide describes a predominantly bleeding disorder involving the protein that ADAMTS13 normally processes, rather than the same enzyme deficiency.
Kādus pavadošos rezultātus padara TTP biežāku?
Thrombocytopenia plus microangiopathic hemolytic anemia is the central laboratory pattern that raises suspicion for TTP. Supporting findings include schistocytes, increased LDH and indirect bilirubin, reduced haptoglobin, and organ injury; clinicians do not require the classic five-feature presentation before acting.
Platelets are often markedly reduced, sometimes below 30 × 10⁹/L, but a higher count does not exclude evolving TTP. Hemoglobin can also lag behind the process early on, so the direction of change matters; a fall from 145 to 42 × 10⁹/L over a short interval deserves attention even before the familiar textbook pattern is complete.
An LDH of 900 IU/L may support hemolysis or organ injury, but it cannot identify TTP on its own because LDH comes from several tissues. The LDH result interpretation guide explains that limitation; clinicians pair LDH with bilirubin fractions, reticulocytes, the smear, and other evidence rather than treating one elevated enzyme as a diagnosis.
Haptoglobin below a laboratory's detection limit supports intravascular hemolysis, although liver disease can also lower it and an inflammatory response can partially mask the expected reduction. The low haptoglobin guide covers those exceptions; an activity of 6% becomes much more persuasive when several independent markers point toward the same microvascular process.
Kad jāmeklē neatliekamā palīdzība?
Suspected TTP is a medical emergency, and clinicians should not wait for ADAMTS13 results before initiating the appropriate urgent pathway. New confusion, weakness, seizures, chest pain, breathlessness, or severe illness alongside low platelets or suspected hemolysis requires immediate emergency assessment.
A new activity result below 10% in someone being investigated for thrombocytopenia or hemolysis needs immediate contact with the treating team, even if symptoms seem modest. If that team cannot be reached promptly, emergency assessment is safer than waiting for a routine appointment; someone already under a documented remission-monitoring plan should follow that team's specific instructions.
Chest discomfort in suspected TTP may reflect cardiac microvascular injury, and it can occur without the usual coronary risk profile. Our chest pain laboratory guide explains why troponin and ECG assessment belong in urgent care, but neither a reassuring initial ECG nor an activity result above 10% after plasma treatment should independently end the evaluation.
Emergency teams usually collect a CBC, smear, hemolysis markers, kidney tests, coagulation studies, and a pretreatment ADAMTS13 sample while arranging hematology input. The practical rule is simple: if obtaining that sample would delay lifesaving treatment, treatment comes first; a send-out test that takes 24 hours or several days cannot serve as permission to wait.
Kā atšķiras aktivitātes, inhibitoru un antivielu testi?
ADAMTS13 activity measures enzyme function, inhibitor testing measures functional neutralization, and antibody testing detects immune binding to ADAMTS13. These are related but different questions; activity of 5%, a negative inhibitor assay, and a positive antibody result can be a biologically coherent combination.
An activity assay asks how efficiently the sample cleaves a defined substrate under laboratory conditions, usually reporting the result as a percentage of a reference preparation. An activity of 7% therefore means markedly impaired measured function; it does not reveal whether the cause is an autoantibody, an inherited deficiency, or another explanation without additional investigation.
A functional inhibitor assay typically mixes patient plasma with a source of normal ADAMTS13 and checks for loss of activity after incubation. Laboratories may report inhibitor titers in Bethesda units per milliliter, but a result such as 1 BU/mL must be interpreted using that laboratory's method and positivity threshold; there is no universal antibody-to-inhibitor conversion.
An anti-ADAMTS13 antibody assay, commonly an IgG binding assay, can detect antibodies that accelerate enzyme clearance without strongly neutralizing the substrate reaction in vitro. Our pozitīva antivielu rezultātu rokasgrāmata explains this broader distinction; a negative inhibitor result does not rule out immune TTP when activity is below 10% and other evidence supports it.
Vai plazmas terapija var mainīt ADAMTS13 testu?
Plasma infusion and plasma exchange can raise measured ADAMTS13 activity because donor plasma supplies the enzyme. Exchange can also remove or dilute inhibitors and antibodies, so a result obtained after treatment may underestimate the severity of the original deficiency or obscure its immune cause.
Whenever feasible, clinicians collect the ADAMTS13 sample before the first plasma infusion or exchange, ideally before other relevant treatment begins. The 2020 ISTH diagnostic guideline explicitly emphasizes pretreatment sampling (Zheng et al., 2020); the instruction is not to postpone care, but to obtain a useful sample while the urgent treatment pathway is already being organized.
For example, a pretreatment activity of 2% and a post-exchange activity of 18% can describe the same patient rather than two contradictory diagnoses. The later value reflects the mixture of disease biology and treatment effect; ask the hospital laboratory whether an earlier retained plasma aliquot exists before assuming that the initial diagnostic opportunity has been lost.
There is no safe universal instruction to stop plasma therapy and wait a fixed number of days simply to produce a cleaner result. The post-transfusion A1c guide illustrates a different treatment-related testing problem, but the mechanisms are not interchangeable: for ADAMTS13, record the collection time and all preceding plasma or enzyme-replacement treatment, including even 1 prior infusion.
Vai analīzes metode vai parauga kvalitāte var jūs maldināt?
ADAMTS13 results can be affected by assay design, specimen handling, and method-specific interference. A surprising result near 10% deserves discussion with the laboratory, especially if the sample was collected after treatment or the measured activity does not fit the rest of the clinical picture.
Common methods measure cleavage of a von Willebrand factor-derived substrate; some use fluorescence, while others detect cleavage products through different readouts. Bilirubin, hemoglobin, or other sample constituents can interfere with particular systems, but the direction and magnitude are method-dependent; do not assume that every visibly altered sample produces a falsely low ADAMTS13 activity of 8%.
Testing laboratories commonly request citrāta plazmā, with processing, freezing, and transport instructions specific to the assay. Our high hemolysis index guide explains why collection-related sample damage differs from hemolysis occurring inside the patient; that distinction matters because TTP itself can produce hemolysis even when the laboratory specimen has been collected correctly.
Kantesti ir AI asins analīžu rezultātu platforma that can help readers identify the reported percentage, reference interval, and collection date, but it cannot inspect an assay's raw signal or validate an unexpected 9% result. My practical question is whether the laboratory recommends confirmation on a retained pretreatment sample or another assay—not whether the patient should wait untreated for perfect certainty.
Ko citu var izraisīt samazināta ADAMTS13 aktivitāte?
Sepsis, advanced liver disease, and several systemic illnesses can cause reduced ADAMTS13 activity without classic TTP. Reductions above 20% are generally less specific, while results of 10–20% form an interpretive gray zone; severe deficiency still demands careful specialist evaluation rather than automatic attribution to another illness.
Vērtība 35% in a critically ill patient with sepsis and abnormal coagulation tests is not equivalent to 3% in someone with otherwise unexplained thrombocytopenia and hemolysis. Clinical reasoning also considers disseminated intravascular coagulation, medication-associated microangiopathy, severe hypertension, and complement-mediated disease; occasionally overlapping conditions make the initial classification genuinely difficult.
Pregnancy and the postpartum period require particular care because TTP, HELLP syndrome, and complement-mediated microangiopathy can share several findings. The HELLP ārkārtas laboratorijas ceļvedis describes the obstetric pattern, but activity below 10% should not be dismissed as a normal pregnancy-related change; maternal and hematology teams often need to evaluate the situation together.
Marked kidney dysfunction may shift attention toward another microangiopathy, but it does not exclude TTP, particularly when pretreatment activity is severely deficient. Our urgent low eGFR guide discusses kidney warning signs; a creatinine of 3 mg/dL is a clue about organ involvement, not a stand-alone rule for deciding which microangiopathy is present.
Kā PLASMIC rādītājs palīdz pirms rezultātu saņemšanas?
The PLASMIC score estimates the likelihood of severe ADAMTS13 deficiency in adults with suspected thrombotic microangiopathy. Scores of 6–7 indicate high probability, 5 is intermediate, and 0–4 is low probability; the score supports urgent reasoning but does not diagnose TTP or replace clinical judgment.
The score assigns 1 point each for platelets below 30 × 10⁹/L, evidence of hemolysis, no active cancer, no transplant history, MCV below 90 fL, INR below 1.5, and creatinine below 2 mg/dL. Bendapudi and colleagues developed and externally validated this approach in adults with thrombotic microangiopathies, rather than in people with an isolated mildly low platelet count (Bendapudi et al., 2017).
Its hemolysis component can be met by a reticulocyte count above 2.5%, undetectable haptoglobin, or indirect bilirubin above 2 mg/dL. A relatively normal INR fits the TTP pattern because routine coagulation tests do not measure the same process; the normal coagulation test limitations guide explains why reassuring clotting times cannot exclude microvascular platelet aggregation.
Scores become less dependable when applied outside their validated context, including children and some pregnancy, cancer, transplant, or complex critical-care presentations. A score of 4 must not overrule a compelling specialist assessment, just as a score of 7 is not proof; clinicians use the estimate to inform immediate action while obtaining the actual pretreatment activity result.
Vai smaga deficīta gadījumā nozīmē imūno vai iedzimto TTP?
Severe ADAMTS13 deficiency can result from immune TTP or congenital TTP. Immune disease involves autoantibodies; congenital disease usually involves pathogenic variants in both copies of the ADAMTS13 gene, and a negative inhibitor assay alone cannot reliably distinguish these two mechanisms.
A person with activity of 1% and convincing anti-ADAMTS13 antibodies usually has evidence favoring immune TTP, although the full report and timing still matter. Conversely, negative antibodies obtained after plasma exchange or immunosuppression are weaker evidence against an immune mechanism; clinicians may review pretreatment testing and repeat selected investigations once interpretation is less confounded.
Congenital TTP can present in childhood, but some people first become symptomatic during pregnancy or another physiological stress in adulthood. Persistent activity below 10%, repeatedly negative immune studies, and a compatible history may prompt genetic testing; a family history can help, but its absence does not exclude an autosomal recessive condition in which both parents are unaffected carriers.
Finding 1 ADAMTS13 variant does not automatically establish congenital TTP, because variant classification and the second gene copy matter. Kantesti's asins analīžu biomarķieru ceļvedis helps distinguish functional laboratory measurements from genetic findings; treatment choice ultimately depends on establishing the mechanism, not simply renaming every antibody-negative low result as inherited disease.
Kā ADAMTS13 rezultāti ietekmē steidzamu ārstēšanu?
Suspected immune TTP is generally treated urgently with plasma exchange and corticosteroids, with specialist decisions about caplacizumab and immune-directed therapy. Confirmed congenital TTP instead requires ADAMTS13 replacement; activity below 10% helps establish the mechanism but is not a reason to postpone initial lifesaving care.
Plasma exchange addresses 2 problems in immune TTP: it provides functional enzyme and removes circulating pathogenic factors, while corticosteroids and often rituximab target the immune process. Caplacizumab blocks the von Willebrand factor–platelet interaction rather than correcting enzyme deficiency, so a rising platelet count during treatment does not necessarily mean ADAMTS13 activity has recovered.
In the HERCULES trial, the composite of TTP-related death, recurrence, or major thromboembolic events during treatment occurred in 12% of caplacizumab recipients versus 49% of placebo recipients, alongside standard care (Scully et al., 2019). Those figures describe a trial outcome, not an individual's prognosis; caplacizumab also increases bleeding risk, so prescribing and duration require specialist oversight.
Congenital TTP may be treated with plasma-based replacement or recombinant ADAMTS13 where available and appropriate; immunosuppression does not repair an inherited enzyme defect. Our koagulācijas analīžu ceļvedis explains why routine clotting times cannot measure this replacement response; platelet transfusion is generally avoided in TTP unless a compelling indication, such as life-threatening bleeding, changes the balance.
Ko nozīmē zema aktivitāte pēc TTP ārstēšanas?
Low ADAMTS13 activity during remission indicates ongoing deficiency and increased relapse risk, but it does not automatically mean an acute clinical relapse. A person can have activity below 10% with a normal platelet count and no active hemolysis; that still needs prompt hematology follow-up.
Clinical recovery is assessed through platelet recovery, resolution of hemolysis, and organ status, not activity alone. For example, platelets of 210 × 10⁹/L with stable hemoglobin and activity of 7% differ from platelets of 24 × 10⁹/L with renewed hemolysis; neither result should be interpreted without knowing whether this is initial diagnosis, treatment response, or remission surveillance.
Some follow-up frameworks describe an ADAMTS13 relapse as a fall below 20% after prior enzyme recovery, even without an acute clinical episode. That biochemical warning can lead to closer monitoring or preemptive immune-directed treatment in selected patients; our post-hospital laboratory changes guide explains why the treatment timeline belongs beside each result.
Monitoring may occur every 1–3 months in parts of follow-up, with different intervals according to recovery, previous relapses, pregnancy plans, and local practice. Kantesti can help organize reported trends through the medication safety trend workflow, but new neurological symptoms, chest pain, or falling platelets require direct clinical assessment rather than waiting for the next scheduled upload.
Kā Kantesti var palīdzēt, ne kavējot neatliekamo aprūpi?
Kantesti can help explain an ADAMTS13 report, but it cannot diagnose or exclude acute TTP remotely. The useful workflow is to review the percentage, accompanying CBC and hemolysis results, and treatment timing after arranging urgent care when the presentation suggests TTP—not before.
Kantesti ir ar AI balstīts asins analīzes rīks that supports patient understanding of laboratory terminology, including the difference between activity below 10% and a positive inhibitor result. As an organization, we explain our scope on the Par mums lapā; reader understanding is the goal, not an automated declaration that a potentially dangerous result is harmless.
The safest report review checks 4 items before discussing a trend: patient identity, collection date, units or percentage, and treatment received before collection. Our technical and clinical standards describe the evaluation framework, but no benchmark can substitute for checking the original laboratory document or knowing whether a sample followed plasma exchange.
A PDF or photo can omit an inhibitor comment, a specimen warning, or the fact that activity was measured after 2 exchanges; those omissions can change the interpretation substantially. The AI tehnoloģiju ceļvedis explains the report-processing approach, while my editorial priority as Thomas Klein, MD, remains straightforward: an explanation must never become a reason to delay emergency hematology care.
Pētījumu publikācijas, pierādījumu ierobežojumi un avotu pārbaudes
TTP decisions should be grounded in specialist guidelines and directly relevant clinical studies, not unrelated laboratory education publications. As of October 8, 2026, this article uses the verified 2020 ISTH diagnostic guideline, the 2017 PLASMIC study, and the 2019 HERCULES trial for its principal clinical claims.
The 3 external medical references listed below address different questions: diagnosis and pretreatment sampling, estimating severe deficiency before results return, and caplacizumab outcomes during treatment. Their publication dates are stated explicitly; the date of this article does not imply that a new 2026 guideline exists, and local hematology protocols may incorporate additional evidence or country-specific access arrangements.
The 2 Figshare DOI resources listed separately are broader educational materials, not evidence validating an ADAMTS13 cutoff or TTP treatment. Their associated articles cover digestive symptom interpretation un hormonal health questions; a DOI identifies a deposited resource but does not by itself demonstrate peer review, clinical relevance, or independent validation.
ResearchGate and Academia.edu links below are explicitly 2 discovery searches, not verified copies or endorsements of those deposits; publication dates are shown as unknown rather than invented. Kantesti's medicīnas konsultatīvā padome provides information about physician expertise, but that organizational page should not be interpreted as documentation that any named physician personally reviewed this individual article.
Bieži uzdotie jautājumi
Vai ADAMTS13 aktivitāte zem 10 procentiem nozīmē, ka man noteikti ir TTP?
ADAMTS13 aktivitāte zem 10% stingri atbalsta TTP, ja trombocitopēnija un mikroangiopātiskā hemolītiskā anēmija rodas kopā. Tas automātiski neapstiprina akūtu epizodi, jo smags deficīts var saglabāties remisijas laikā vai rasties iedzimtā TTP gadījumā bez pašreizējiem simptomiem. Svarīgs ir paraugu savākšanas laiks, iepriekšēja ārstēšana, inhibitoru un antivielu rezultāti un klīniskie atklājumi. Jauna aizdomas par TTP gadījumu prasa neatliekamu izvērtēšanu, negaidot apstiprinājumu.
Vai TTP var būt pie ADAMTS13 aktivitātes virs 10%?
ADAMTS13 aktivitātes rezultāts virs 10% droši neizslēdz TTP, ja paraugs iegūts pēc plazmas infūzijas vai apmaiņas. Pirmsapstrādes rezultāti 10–20% ir interpretācijas pelēkā zona, kas var prasīt atkārtotu vai alternatīvas metodes testēšanu. Uzticams pirmsapstrādes rezultāts virs 20% parasti novirza novērtējumu uz citiem trombotiskās mikroangiopātijas cēloņiem. Spēcīgas klīniskās aizdomas joprojām prasa steidzamu speciālista novērtējumu, kamēr tiek izmeklētas neatbilstības.
Kāda ir atšķirība starp ADAMTS13 inhibitoru un antivielu?
ADAMTS13 inhibitor tests nosaka fermenta funkcionālo neitralizāciju, savukārt antivielu tests nosaka imūno saistīšanos ar ADAMTS13. Aktivitāte tiek uzrādīta atsevišķi, parasti kā procentos, un rezultāts 5% norāda uz nopietni traucētu izmērīto fermenta funkciju. Dažas antivielas veicina fermenta izvadīšanu, nerada pozitīvu funkcionālo inhibitoru testu. Tāpēc negatīvs inhibitoru tests pats par sevi neizslēdz imūno TTP.
Vai ADAMTS13 tests jāveic pirms plazmas apmaiņas?
ADAMTS13 testu ideālā gadījumā vajadzētu veikt pirms pirmās plazmas infūzijas vai plazmas apmaiņas, jo donoru plazma satur funkcionālu enzīmu. Apmaiņa var arī noņemt vai atšķaidīt inhibitorus un antivielas, padarot vēlāku rezultātu mazāk reprezentatīvu sākotnējai slimībai. Ārstēšanas beigu aktivitāte 18% var sekot pēc ārstēšanas sākuma aktivitātes zem 10%. Paraugu ņemšana nedrīkst aizkavēt neatliekamo ārstēšanu, ja ir spēcīgas aizdomas par TTP.
Vai ADAMTS13 aktivitāte 30% ir avārijas situācija?
ADAMTS13 aktivitāte 30% apmērā daudzās laboratorijās ir samazināta, bet nav tā smagā deficīta zem 10% līmeņa, kas stingri norāda uz TTP. Cipars viens pats nenosaka, vai pastāv ārkārtas situācija. Zems trombocītu skaits, aktīva hemolīze, apmulsums, sāpes krūtīs vai cits orgānu bojājums joprojām prasa steidzamu izvērtēšanu, tostarp citu mikroangiopātiju izmeklēšanu. Stabila persona bez šiem atradumiem prasa interpretāciju, izmantojot laboratorijas intervālu un klīnisko vēsturi, nevis automātisku ārkārtas situācijas marķēšanu.
Vai ADAMTS13 var palikt zems, pat ja manas trombocītu skaits ir normāls?
ADAMTS13 aktivitāte var saglabāties zem 10% TTP remisijas laikā pat tad, ja trombocīti ir normāli un hemolīze ir beigusies. Šis modelis norāda uz pastāvīgu enzīmu deficītu un var liecināt par palielinātu recidīvu risku, nevis automātiski pierādīt pašreizēju akūtu recidīvu. Dažās uzraudzības sistēmās pēc iepriekšējas atveseļošanās tiek izmantota aktivitāte zem 20% kā bioķīmisks recidīvu brīdinājums. Hematologam vajadzētu izlemt, vai ir piemērota ciešāka uzraudzība vai preventīva ārstēšana.
Cik ilgi jāgaida ADAMTS13 rezultāti, un vai ārstēšanu var atlikt?
ADAMTS13 rezultātu iegūšanas laiks atšķiras atkarībā no slimnīcas un testa, sākot no ātras vietējās testēšanas līdz nosūtītu paraugu rezultātiem, kas aizņem vairākas dienas. Rezultāts, kas sagaidāms 24–72 stundu laikā, nav iemesls ārstēšanas atlikšanai, ja ir spēcīgas aizdomas par TTP. Neatliekamās palīdzības komandas, plānojot speciālista aprūpi, izmanto klīnisko ainu, rutīnas laboratorijas atradumus un dažreiz PLASMIC rādītāju. Vēlamā secība ir savlaicīga paraugu ņemšana pirms ārstēšanas, ja tas ir iespējams, kam seko steidzami lēmumi par ārstēšanu, negaidot rezultātu.
Iegūstiet AI vadītu asins analīžu analīzi jau šodien
Pievienojieties vairāk nekā 2 miljoniem lietotāju visā pasaulē, kuri uzticas Kantesti tūlītējai, precīzai laboratorijas analīžu interpretācijai. Augšupielādējiet savas asins analīzes rezultātus un dažu sekunžu laikā saņemiet visaptverošu 15,000+ biomarķieru interpretāciju.
📚 Atsauces pētniecības publikācijas
Kleins, T., Mičels, S., un Vēbers, H. (2026). Caureja pēc badošanās, melni plankumi izkārnījumos un kuņģa-zarnu trakta ceļvedis 2026. gadam. Kantesti AI Medicīnas pētījumi.
Kleins, T., Mičels, S., un Vēbers, H. (2026). Sieviešu veselības ceļvedis: ovulācija, menopauze un hormonālie simptomi. Kantesti AI Medicīnas pētījumi.
📖 Ārējās medicīniskās atsauces
Zheng XL et al. (2020). ISTH vadlīnijas trombotiskās trombocitopēniskās purpuras diagnosticēšanai. Journal of Thrombosis and Haemostasis.
Bendapudi PK et al. (2017). Derivation and external validation of the PLASMIC score for rapid assessment of adults with thrombotic microangiopathies: a cohort study. The Lancet Haematology.
Scully M et al. (2019). Caplacizumab Treatment for Acquired Thrombotic Thrombocytopenic Purpura. New England Journal of Medicine.
⚕️ Medicīniskā atruna
Šis raksts ir paredzēts tikai izglītojošiem nolūkiem un nav medicīnisks padoms. Vienmēr konsultējieties ar kvalificētu veselības aprūpes speciālistu, lai pieņemtu lēmumus par diagnostiku un ārstēšanu.
E-E-A-T uzticēšanās signāli
Pieredze
Ārstu vadīta klīniskā laboratorijas interpretācijas darbplūsmu pārskatīšana.
Ekspertīze
Laboratorijas medicīnas fokuss uz to, kā biomarķieri uzvedas klīniskā kontekstā.
Autoritāte
Sagatavojis Dr. Thomas Klein, pārskatījusi Dr. Sarah Mitchell un prof. Dr. Hans Weber.
Uzticamība
Uz pierādījumiem balstīta interpretācija ar skaidriem turpmākās rīcības ceļiem, lai mazinātu trauksmi.