
Gaucher disease is diagnosed by demonstrating deficient glucocerebrosidase activity, usually in leukocytes, with GBA1 analysis providing genetic confirmation. A low dried blood spot screen needs follow-up; carrier status and an elevated lyso-Gb1 result are not interchangeable with a diagnosis.

핵심 요점
- Dried blood spot screening identifies possible enzyme deficiency; 1 abnormal screening result does not establish Gaucher disease.
- Confirmatory enzyme testing usually measures glucocerebrosidase in leukocytes; activity below approximately 10–15% of mean normal activity is characteristic, subject to the laboratory's validated method.
- GBA1 confirmation identifies disease-causing variants in both gene copies; 2 variants must be on opposite copies to establish a biallelic genotype.
- Carrier status usually means 1 disease-causing GBA1 variant, not Gaucher disease; enzyme activity overlaps between carriers and noncarriers.
- Lyso-Gb1 supports diagnosis and monitoring, but a published 12 ng/mL research cutoff is not a universal threshold across laboratories.
- Uncertain variants require specialist interpretation; 2 variants of uncertain significance do not establish Gaucher disease by themselves.
- Family planning involves a 25% affected-child probability per pregnancy when both parents carry a disease-causing variant in the same recessive gene.
- Disease severity cannot be calculated from a single enzyme percentage, GBA1 result or lyso-Gb1 measurement.
What confirms Gaucher disease after a screening result?
Gaucher disease is confirmed by deficient glucocerebrosidase activity in an appropriate diagnostic specimen, supported by GBA1 testing. An abnormal dried blood spot usually leads to leukocyte enzyme testing and analysis of both GBA1 copies; symptoms help assess disease involvement but are not required for an early diagnosis.

The diagnostic pathway has 3 distinct questions: did screening identify a possible deficiency, does a reliable cellular assay confirm it, and what genetic changes explain it? Treating these questions separately prevents a screening flag, a carrier finding or an uncertain variant from becoming an unsupported lifelong diagnosis.
Kantesti is an AI blood test analyzer that helps explain report terminology without replacing specialist confirmation of inherited enzyme deficiencies. Our 회사 소개 describes the organization behind these explanations; for this condition, we distinguish 2 tasks—understanding a report and establishing the diagnosis.
A molecular result identifying 2 pathogenic or likely pathogenic GBA1 variants on opposite gene copies can establish a genetic diagnosis, even before symptoms develop. However, pairing the genetic result with a validated enzyme assay is especially valuable after screening, because disagreement can reveal a specimen problem, incomplete testing or incorrect variant interpretation.
Dardis et al. (2022), in the International Working Group of Gaucher Disease laboratory guidance, distinguish screening from diagnostic enzyme measurement and molecular analysis. A practical first step is to obtain the complete report—not just the word 'positive'—including specimen type, activity, reference interval and whether a second-tier test was performed.
Why can a dried blood spot screen show low activity?
Low glucocerebrosidase activity on a dried blood spot can reflect Gaucher disease or a collection, transport or analytical problem. The result identifies someone who needs follow-up; it does not reliably distinguish an affected person from a carrier using 1 screening measurement.

A dried blood spot contains a mixture of cellular elements rather than a standardized preparation of isolated leukocytes. Because the screening signal depends partly on specimen composition, hematocrit and leukocyte abundance can influence activity; the diagnostic laboratory therefore interprets 1 low result alongside collection quality and its own screening algorithm.
Heat, moisture and inadequate drying can reduce enzyme activity before the specimen reaches the laboratory. If several lysosomal enzymes are unexpectedly low on the same card, deterioration becomes more plausible than several separate disorders; comparing 2 or more assay signals can therefore provide useful quality-control information without proving the cause.
For example, imagine a screening card exposed to prolonged humid transport that returns low activity, followed by normal leukocyte testing from a correctly handled specimen. That hypothetical pair of results supports a screening artifact, not a recovered enzyme deficiency; our sample quality guide explains the broader principle that handling errors affect different assays differently.
Newborn screening programs do not all include Gaucher disease, and second-tier protocols differ between jurisdictions. Ask 3 questions: was this population screening or testing prompted by symptoms, was lyso-Gb1 measured, and was GBA1 analysis already performed? Those answers determine whether the next appointment should focus on confirmation, genetics or both.
How does confirmatory glucocerebrosidase testing work?
Confirmatory Gaucher disease enzyme testing usually measures acid beta-glucosidase, also called glucocerebrosidase, in leukocytes. Cultured skin fibroblasts provide another diagnostic specimen when needed; the laboratory uses an assay designed to measure the relevant lysosomal enzyme rather than interpreting a routine chemistry panel.

Glucocerebrosidase normally helps break down glucosylceramide inside lysosomes. Diagnostic assays measure the conversion of a laboratory substrate under controlled conditions; laboratories may report activity in nmol/hour/mg protein or another validated unit, so 2 reports with different denominators cannot be compared by their printed numbers alone.
Leukocyte separation and specimen stability matter because the diagnostic assay depends on viable enzyme activity, not merely the presence of DNA. Ask the receiving laboratory which collection tube, shipping conditions and arrival window it requires; a rule used for 1 hospital's routine tests may be inappropriate for a specialist metabolic laboratory.
Fasting is generally unnecessary for isolated enzyme and DNA testing, although additional tests ordered at the same visit may have separate requirements. Our G6PD enzyme testing explanation illustrates why cell type and assay context matter, but G6PD is a different enzyme with different inheritance and retesting considerations.
A diagnostic laboratory may use a control enzyme or other checks to determine whether the specimen is suitable. When the report says 'insufficient,' 'degraded' or 'repeat required,' the correct interpretation is that 1 test has not answered the question—not that the patient has a borderline form of Gaucher disease.
How low must glucocerebrosidase activity be?
Activity below approximately 10–15% of mean normal glucocerebrosidase activity is characteristic of Gaucher disease in diagnostic cellular assays. The laboratory's affected range and assay validation govern interpretation; there is no single activity value in nmol/hour/mg that applies to every method.

The 10–15% description refers to a proportion of mean normal activity, not necessarily a proportion of the lower reference limit. That distinction matters: dividing a patient's result by the wrong reference number can create a misleading percentage, especially when the laboratory reports a broad interval instead of a control mean.
For a hypothetical assay with mean normal activity of 20 nmol/hour/mg protein, a result of 2 nmol/hour/mg represents 10% of that mean. This arithmetic explains the percentage; it does not establish a transferable cutoff, because another laboratory may use a different substrate, preparation, calibration or normalization method.
Carrier enzyme activity overlaps with activity in people without a disease-causing variant, so an intermediate value cannot reliably establish or exclude carrier status. The distinction between 정성 및 정량 결과 is useful here: 'low' summarizes a measurement but does not explain its diagnostic reliability.
Residual activity is not a disease-severity calculator. A person with 5% activity is not necessarily more clinically affected than someone with 8%; substrate-based assays do not reproduce every aspect of enzyme function in tissues, and genotype, age, organ involvement and treatment history all contribute to the clinical picture.
| 수준 | 범위 | 의미 |
|---|---|---|
| Within the laboratory's normal interval | Method-specific activity units | Usually argues against classic GBA1-related enzyme deficiency when specimen quality is satisfactory. |
| Intermediate or borderline activity | Below normal but outside a clear affected range | Needs laboratory review; cannot reliably classify carrier status. |
| Markedly deficient diagnostic activity | Often below approximately 10–15% of mean normal | Supports Gaucher disease in a validated cellular assay; correlate with GBA1 findings. |
| Unsuitable specimen | No interpretable diagnostic threshold | Requires repeat collection; specimen failure is not evidence of severe disease. |
Where does lyso-Gb1 fit in Gaucher diagnosis?
Lyso-Gb1, also called glucosylsphingosine, is a biomarker that supports Gaucher diagnosis and helps monitor disease activity and treatment response. It complements enzyme and GBA1 testing; a single concentration does not independently identify the genotype, clinical subtype or need for treatment.

Rolfs et al. (2013), in PLOS ONE, reported excellent diagnostic discrimination using a 12 ng/mL cutoff in a selected non-Jewish Caucasian cohort. That finding supports the biomarker's usefulness, but the cohort, assay and study design matter; it should not be converted into a universal screening threshold for every newborn or laboratory.
Plasma and dried blood spot lyso-Gb1 results are not automatically interchangeable, and laboratories may report ng/mL or nmol/L. A hypothetical plasma result of 60 ng/mL against that laboratory's upper limit of 6 ng/mL is 10 times the upper limit; the comparison should use the same specimen type and method.
Lyso-Gb1 is not lyso-Gb3: the latter is associated with Fabry disease and reflects a different lipid pathway. Kantesti's educational explanations keep these names separate because confusing the 2 can send follow-up in the wrong direction; our Fabry testing pathway explains the corresponding enzyme and gene tests.
A substantial lyso-Gb1 elevation strengthens concern when diagnostic enzyme activity is deficient, whereas a discordant biomarker result prompts review rather than automatic dismissal. For follow-up, compare at least 2 measurements using a consistent method and interpret the trend with platelet count, organ assessment, skeletal findings and treatment timing.
What do GBA1 genetic test results actually establish?
GBA1 genetic test results establish which variants were detected and whether they support a disease-causing genotype. Gaucher disease is autosomal recessive: 2 pathogenic or likely pathogenic variants on opposite gene copies support a genetic diagnosis, while one detected variant usually indicates carrier status or incomplete testing.

The report should state the exact variant, its classification, zygosity and the test's technical limitations. A variant of uncertain significance, or VUS, is not a confirmed disease-causing finding; detecting 2 VUS does not establish Gaucher disease without additional evidence, even when the report uses alarming language such as 'potentially relevant.'
Kantesti is an AI blood test interpretation platform that can help explain the difference between 1 detected variant and a confirmed biallelic result. Our 바이오마커 용어 가이드 supports report reading, but AI explanation does not substitute for a clinical laboratory's variant classification or a genetic counselor's assessment.
Two variants can sit together on the same gene copy, called 'in cis,' leaving the other copy unaffected. Variants on opposite copies are 'in trans'; parental testing can help establish this phase, so the phrase '2 variants found' must not be treated as synonymous with 'both copies affected.'
A negative limited mutation panel is different from negative comprehensive analysis. If a panel examines only selected variants, its 1 negative result leaves untested regions and structural changes unresolved; ask whether sequencing, deletion/duplication analysis and methods capable of detecting recombinant alleles were included before interpreting the result as exclusion.
Why is a GBA1 carrier result not Gaucher disease?
A GBA1 carrier usually has one disease-causing variant and does not have Gaucher disease. Carrier status mainly changes reproductive counseling, while certain heterozygous GBA1 variants also increase Parkinson disease risk; neither issue turns 1 carrier finding into a diagnosis of a lysosomal storage disorder.
When both parents carry a disease-causing variant in GBA1, each pregnancy has a 25% probability of an affected child, a 50% probability of a carrier child and a 25% probability of a child who inherits neither familial variant. These probabilities reset with every pregnancy; previous outcomes do not change the next calculation.
Carrier interpretation depends on the gene's inheritance and the test's limitations. Our SMA carrier result guide shows how hidden risk can depend on gene-copy arrangement, while Fragile X carrier interpretation uses a different mechanism; neither algorithm should be imported into GBA1 counseling.
Sidransky et al. (2009), in the New England Journal of Medicine, found an overall odds ratio of 5.43 for the association between GBA mutations and Parkinson disease in a multicenter case-control study. An odds ratio is not a lifetime probability: most carriers do not inevitably develop Parkinson disease, and individual risk varies by variant and other factors.
Symptoms still deserve assessment in someone labeled a carrier. If a hypothetical person has 1 detected pathogenic variant plus clearly deficient leukocyte activity, clinicians should look for an undetected second allele or another explanation rather than assuming that carrier status alone accounts for the findings.
Why does GBA1 testing need a specialist laboratory?
GBA1 testing is technically challenging because the nearby GBAP1 pseudogene has approximately 96% sequence similarity to GBA1. A suitable assay must distinguish the functional gene from the pseudogene and address recombinant or structural alleles that a limited test may miss or misassign.
Short DNA reads can map ambiguously when 2 regions are highly similar, and gene–pseudogene recombination can produce complex alleles. This is why 'sequencing performed' is not enough information: the laboratory should explain whether its method is validated for the GBA1 locus and how it handles difficult regions.
Variant names also changed with the protein numbering convention. The older N370S name corresponds to p.Asn409Ser, and L444P corresponds to p.Leu483Pro; the 39-amino-acid difference can make the same variant appear to be 2 different findings when comparing an older family report with a newer result.
Not every GBA1-associated Parkinson risk variant causes Gaucher disease on its own. For example, p.Glu365Lys, historically E326K, requires careful classification rather than automatic counting as 1 Gaucher-causing allele; our genetic result interpretation guide explains why a variant's significance must be matched to the condition under investigation.
Consumer genotyping and unvalidated raw-data interpretation should not confirm or exclude Gaucher disease. If a report lists only 1 common variant, request clinical confirmation and ask about the second allele; if it lists a complex allele, ask whether the changes are in cis and whether parental testing could clarify them.
What if enzyme, lyso-Gb1 and DNA results disagree?
Discordant Gaucher results require specimen review, method review and specialist interpretation before a final diagnosis. Low enzyme activity with 1 detected variant, or elevated lyso-Gb1 with apparently normal activity, can reflect incomplete genetic testing, analytical limitations or a less common biological explanation.

A hypothetical combination of deficient leukocyte activity, elevated lyso-Gb1 and 1 pathogenic GBA1 variant strongly justifies a search for the missing allele. The next investigation may involve deletion/duplication assessment, recombinant-allele analysis or another validated method; repeating the same limited panel does not necessarily add useful information.
Rare saposin C deficiency, related to PSAP, can produce a Gaucher-like biochemical and clinical picture despite relatively preserved activity in some artificial-substrate assays. This is a specialist differential diagnosis, not a reason to distrust every normal enzyme test; it becomes relevant when 2 or more independent findings remain unexplained.
Allogeneic stem-cell transplantation can alter leukocyte enzyme activity and the source of DNA in circulating cells, so the laboratory needs that history. Recent transfusions should also be disclosed, although their impact depends on product and assay; 방문 간 결과를 비교하는 것 requires more than assuming every numerical change reflects disease.
Kantesti AI cannot resolve gene phase, laboratory contamination or donor-cell chimerism from a report alone. Our AI 설명 안전 가이드 separates readable explanations from diagnostic verification; carry all 3 reports—enzyme, genetics and biomarker—to the same specialist review instead of interpreting each in isolation.
Which blood counts and symptoms raise suspicion?
Unexplained spleen enlargement, thrombocytopenia, anemia and skeletal symptoms can prompt Gaucher testing, but none confirms the disease. The combination matters more than 1 isolated abnormality, and clinicians must consider hematological, hepatic and other causes alongside a lysosomal storage disorder.
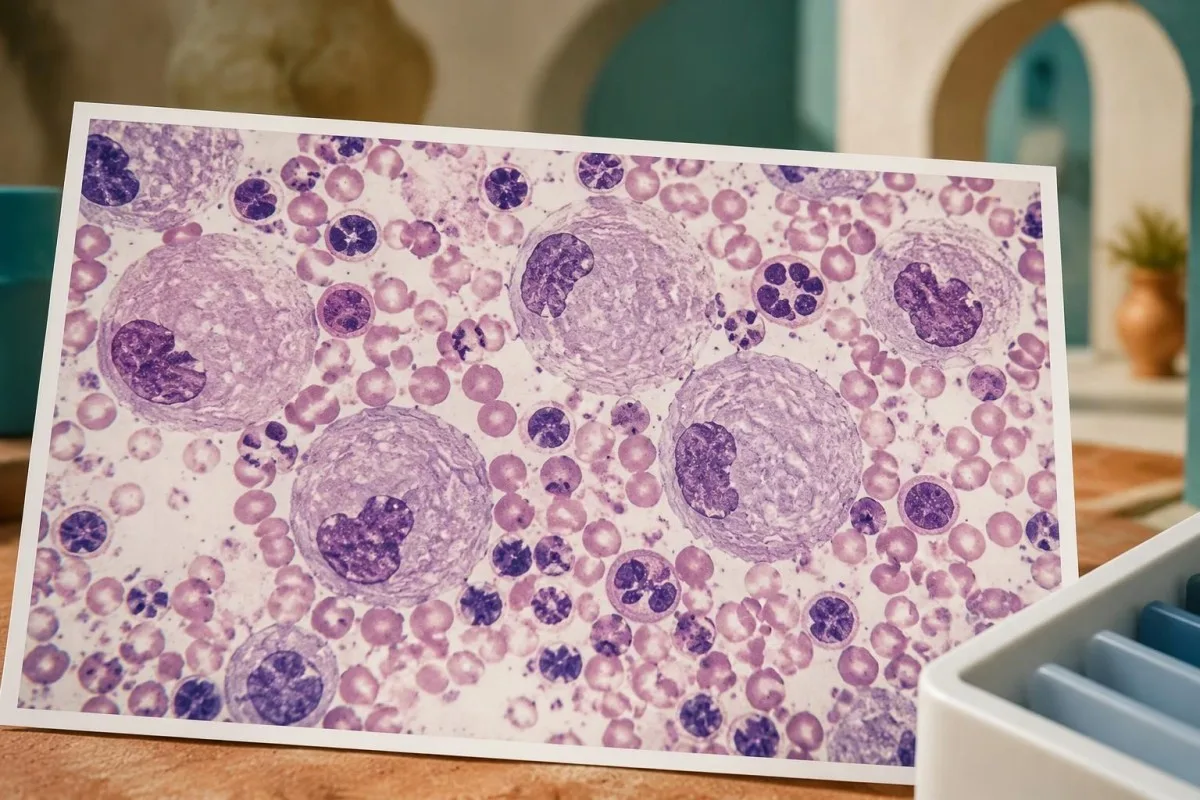
For example, a hypothetical adult with platelets of 85 × 10^9/L, hemoglobin of 10.4 g/dL and an enlarged spleen deserves an explanation for the combined pattern. Those numbers do not diagnose Gaucher disease; they justify assessment for sequestration, marrow disorders, liver disease and other causes rather than attributing everything to iron deficiency.
A low automated platelet count should first be checked for clumping when the clinical context suggests an artifact. Our 혈소판 응집 설명 describes this common alternative; confirming 1 truly low count prevents a false laboratory abnormality from driving an unnecessary rare-disease workup.
Bone marrow examination is not routinely required to diagnose Gaucher disease when enzyme and genetic testing are available. Gaucher-like or 'pseudo-Gaucher' cells can occur in other conditions, including disorders with high cell turnover; our marrow diagnosis guide explains why cellular appearance and disease-specific confirmation answer different questions.
A normal CBC does not exclude early or mild Gaucher disease, particularly when 2 familial pathogenic variants are known. Conversely, a marrow report mentioning storage-like cells should lead to biochemical confirmation rather than immediate labeling; ask which alternative causes were considered and whether the enzyme specimen was collected before any treatment.
Can these tests identify Gaucher type and severity?
Enzyme and GBA1 tests establish the biochemical and genetic basis of Gaucher disease, but clinical assessment determines subtype and organ involvement. The conventional classification uses types 1, 2 and 3, with primary neurological involvement distinguishing neuronopathic forms; these categories do not replace an individualized assessment.
Type 1 lacks the primary neuronopathic pattern of types 2 and 3, although people with type 1 or heterozygous GBA1 variants can still have other neurological conditions. The distinction is clinically specific; a future Parkinson risk association is not equivalent to classifying someone as having neuronopathic Gaucher disease.
The p.Asn409Ser variant is strongly associated with non-neuronopathic disease when present in a Gaucher genotype, but genotype does not precisely predict skeletal burden or treatment timing. A hypothetical pair of siblings with the same 2 variants can still differ in spleen size, platelet count, bone involvement and age at recognition.
Skeletal assessment may require imaging because routine calcium or alkaline phosphatase results can miss Gaucher-related bone involvement. Our bone health laboratory guide explains what general bone tests can and cannot show; a normal result on 1 chemistry panel is not a substitute for indicated imaging.
Neurological assessment focuses on symptoms, examination and age-appropriate specialist evaluation, including eye movement abnormalities when relevant. Our neurofilament interpretation guide explains why a nonspecific neuronal-injury marker cannot determine Gaucher subtype; neither that marker nor 1 lyso-Gb1 concentration provides a stand-alone classification.
Who should have family testing after confirmation?
After Gaucher disease is confirmed, genetic counseling can identify relatives who need targeted testing and explain reproductive probabilities. Testing for the family's 2 established variants is often more informative than repeating a broad screening panel, particularly when the original report clearly documents their phase and classification.
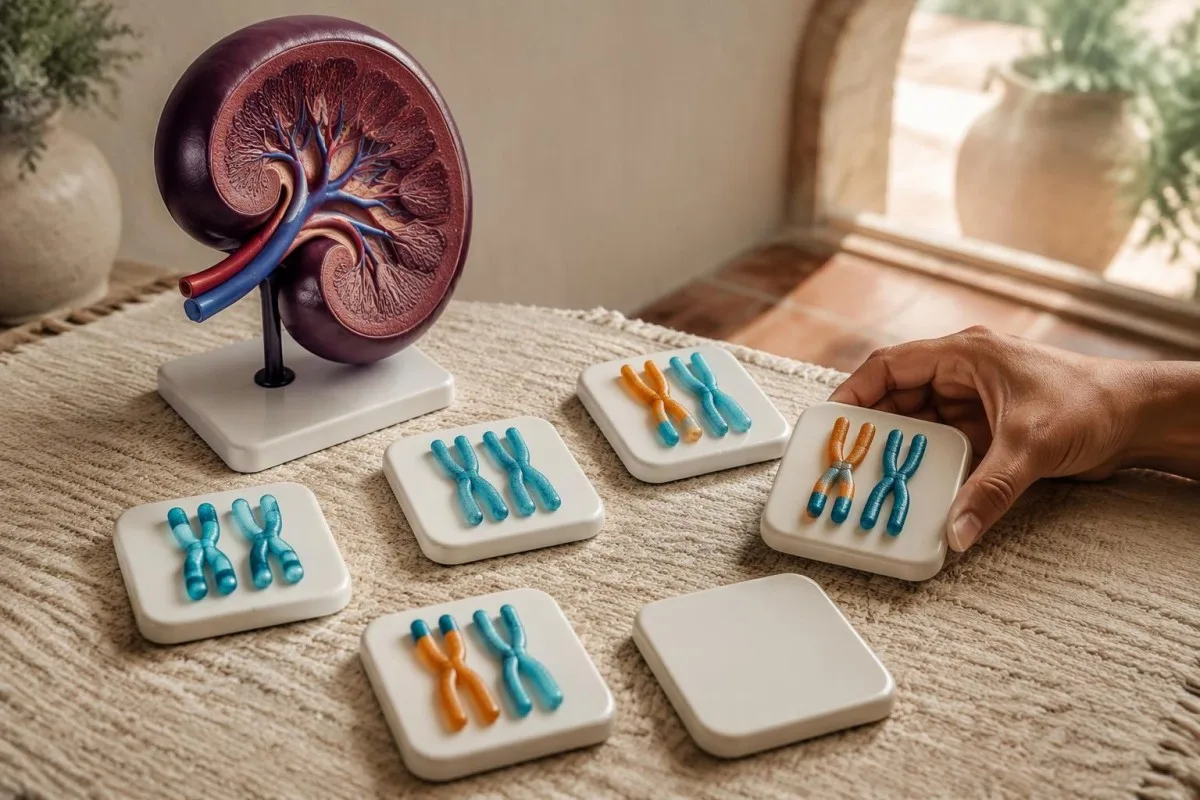
Full siblings of an affected person generally have the familiar 25% affected, 50% carrier and 25% noncarrier probabilities when both parents are carriers. These are pretest probabilities, not predictions about a particular sibling; an apparently well relative may still need testing because symptom severity and age at presentation vary.
Partner testing helps estimate reproductive risk, but the scope of the assay matters. A negative panel testing only several common variants leaves more residual uncertainty than a validated comprehensive assay; ask the counselor to explain both the detected result and the remaining risk rather than treating 1 negative screen as a guarantee.
Testing minors raises 2 different questions: could identifying disease change their childhood care, and is the request solely to establish future reproductive carrier status? Diagnostic testing for a potentially affected child can have immediate value, while carrier-only testing may warrant a different consent discussion based on local practice and family circumstances.
Share the original clinical laboratory report, including exact variant names and specimen details, rather than a rewritten family summary. Our secure result sharing guide explains practical consent considerations; each adult relative should control access to their own results, even when 1 family member coordinates appointments.
What happens after Gaucher disease is confirmed?
A confirmed diagnosis leads to specialist assessment, baseline measurements and a decision about treatment or surveillance. Enzyme replacement or substrate reduction therapy is considered according to clinical involvement, not simply because 1 enzyme result is low or lyso-Gb1 exceeds a reference limit.

Baseline assessment commonly includes CBC, liver-related tests, spleen and liver measurements, skeletal evaluation and a disease-specific biomarker. Establishing these findings before treatment makes later changes interpretable; 2 lyso-Gb1 results without information about method, treatment timing and organ status provide a much weaker follow-up picture.
Chitotriosidase and CCL18 may support monitoring, but they are not substitutes for diagnostic enzyme testing. A common 24-base-pair CHIT1 duplication can eliminate chitotriosidase activity when present on both copies, so an undetectable chitotriosidase result can reflect inherited marker deficiency rather than an absence of Gaucher disease.
Kantesti's trend tools can help organize routine results, but they do not establish whether specialized Gaucher testing is analytically comparable or whether treatment should change. Genetic information deserves particular care; our 개인정보 보호 및 데이터 지침은 explains data handling, and patients should avoid including relatives' identifiable reports without consent.
Children need age-specific interpretation, growth assessment and pediatric metabolic oversight rather than adult reference ranges applied mechanically. Our 소아 AI 안전 지침 describes that boundary; seek urgent care for uncontrolled bleeding, severe new abdominal pain or acute neurological change instead of waiting for a second routine monitoring result.
Which evidence supports the pathway, and what can AI explain?
The diagnostic pathway is supported by specialist laboratory guidance, biomarker research and clinical genetic evidence—not by AI output alone. The 3 directly relevant medical references below address laboratory confirmation, lyso-Gb1 and GBA-associated Parkinson risk; our separate publications provide background on routine laboratory interpretation.

Kantesti is an AI-powered blood test analysis tool that helps translate report language into questions for a clinician, rather than verifying a rare-disease diagnosis. Our 임상 검사 방법 정보는 explains broader oversight; performance on routine panels does not establish diagnostic accuracy for GBA1 phase, rare alleles or specialized enzyme assays.
Dardis et al. (2022) provide the central laboratory framework, while Rolfs et al. (2013) provide evidence for lyso-Gb1 as a diagnostic and follow-up biomarker. Their findings answer 2 different questions: how to establish enzyme deficiency and how to measure an associated biochemical signal; neither supports interpreting a carrier screen as affected status.
Our publication on coagulation test interpretation is relevant background when a confirmed patient is being assessed for bleeding, but it is not a Gaucher diagnostic study. The associated Zenodo DOI below documents that educational publication, not independent validation of a Gaucher test or a treatment threshold.
함께 제공되는 혈청 단백질 해석 가이드 explains routine protein measurements that may accompany broader assessment; albumin and globulins do not confirm this disorder. Both of the 2 Zenodo references are included transparently as related educational publications, separate from the directly relevant medical evidence.
자주 묻는 질문
비정상적인 건조 혈액 반점 검사 후 고셔병은 어떻게 진단하나요?
An abnormal dried blood spot is usually followed by confirmatory glucocerebrosidase activity testing in leukocytes and GBA1 analysis. Diagnostic cellular activity below approximately 10–15% of mean normal is characteristic, although interpretation depends on the laboratory's method and specimen quality. Two pathogenic or likely pathogenic GBA1 variants on opposite gene copies support genetic confirmation. Lyso-Gb1 adds biochemical evidence but does not replace those tests.
글루코세레브로시다아제 활성이 낮으면 고셔병이 있다는 뜻인가요?
0 글루코세레브로시다아제 활성이 낮다고 해서 항상 고셔병을 의미하는 것은 아니며, 특히 건조혈반 선별검사 결과인 경우에는 더욱 그렇습니다. 검체 채취의 질, 운송 조건 및 검체 구성은 선별검사 활도에 영향을 미칠 수 있습니다. 검증된 백혈구 또는 섬유아세포 분석에서 활성이 현저히 결핍된 결과는 선별검사에서 활성이 낮게 나온 측정값 1건보다 진단 근거로 훨씬 강합니다. 경계성 결과 또는 서로 일치하지 않는 결과는 검사실 검토와 GBA1 검사 결과와의 상관 평가가 필요합니다.
Can a GBA1 carrier have Gaucher disease?
A person with only 1 disease-causing GBA1 variant is usually a carrier, not someone with Gaucher disease. If symptoms and confirmatory enzyme testing strongly suggest disease, clinicians should investigate whether a second variant was missed or another explanation exists. Enzyme activity alone cannot reliably identify carriers because carrier and noncarrier ranges overlap. Certain heterozygous GBA1 variants also increase Parkinson disease risk, but that association is not a diagnosis of either Parkinson disease or Gaucher disease.
What lyso-Gb1 level confirms Gaucher disease?
No single lyso-Gb1 concentration universally confirms Gaucher disease across all laboratories and specimen types. Rolfs et al. (2013) reported excellent discrimination with a 12 ng/mL cutoff in a selected research cohort, but that threshold is assay- and population-dependent. Interpret the result using the reporting laboratory's interval and whether the specimen was plasma or a dried blood spot. Confirmation relies on diagnostic enzyme testing and appropriate genetic evidence.
Do two GBA1 variants prove Gaucher disease?
Two detected GBA1 variants do not automatically prove Gaucher disease. Both must be disease-causing or likely disease-causing, and they must affect opposite gene copies rather than lie together on 1 copy. Two variants of uncertain significance do not establish the diagnosis by themselves. Parental testing, assay review and confirmatory enzyme activity can help resolve uncertain results.
Is a bone marrow biopsy needed to diagnose Gaucher disease?
Bone marrow biopsy is not routinely needed when diagnostic enzyme and GBA1 testing are available. Gaucher-like cells can occur in other disorders, so their appearance is not sufficiently specific to confirm the diagnosis alone. Clinicians may still recommend marrow examination for a separate hematological question, such as unexplained abnormalities affecting 2 or more cell lines. If storage-like cells are reported, disease-specific biochemical testing remains necessary.
Should relatives be tested if Gaucher disease is confirmed?
Relatives may benefit from targeted testing after the family's disease-causing GBA1 variants are established. When both parents are carriers, each full sibling has a pretest probability of 25% affected, 50% carrier and 25% inheriting neither familial variant. Genetic counseling explains which relatives need testing, what a negative result leaves unresolved and how results affect reproductive planning. Testing an apparently well sibling can still be useful because Gaucher disease severity and age at recognition vary.
혈액검사 결과 보는법
검사실 보고서를 업로드하면 Kantesti의 AI가 몇 초 안에 각 바이오마커를 쉬운 말로 설명합니다. 전 세계 200만 명 이상이 사용하고 있습니다.
참고 자료
- Klein, T., Mitchell, S., & Weber, H. (2026). aPTT 정상 범위: D-Dimer, Protein C 혈액 응고 안내서. Kantesti AI 의학 연구. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). 혈청 단백질 안내서: 글로불린, 알부민 및 A/G 비율 혈액검사. Kantesti AI 의학 연구. DOI
- Dardis A et al. (2022). Patient centered guidelines for the laboratory diagnosis of Gaucher disease type 1. Orphanet Journal of Rare Diseases.
- Rolfs A et al. (2013). Glucosylsphingosine is a highly sensitive and specific biomarker for primary diagnostic and follow-up monitoring in Gaucher disease in a non-Jewish, Caucasian cohort of Gaucher disease patients. PLOS ONE. DOI
- Sidransky E et al. (2009). Multicenter analysis of glucocerebrosidase mutations in Parkinson's disease. New England Journal of Medicine. DOI 퍼브메드
- 200만+분석한 검사
- 127+국가
- 100+언어
의료진 소개


E-E-A-T 신뢰 신호
경험
의사가 주도하는 검사 해석 워크플로 임상 검토.
전문적 지식
임상 맥락에서 바이오마커가 어떻게 거동하는지에 대한 검사실 의학 중심.
권위
Thomas Klein 박사의 의학적 검토를 거쳤으며, Sarah Mitchell 박사와 Hans Weber 교수의 기여가 있었습니다.
신뢰성
경고를 줄이기 위한 명확한 후속 경로가 포함된 근거 기반 해석.





의학적 면책 조항
이 글은 교육 목적만을 위한 것이며 의학적 조언을 구성하지 않습니다. 진단 및 치료 결정에는 항상 자격을 갖춘 의료 전문가와 상담하세요.
게시됨 · 편집팀에 문의
Kantesti Ltd 발행, 잉글랜드 및 웨일스에 등록된 회사, 회사 번호. 17090423, 런던, 영국.
