
Clozapine monitoring uses absolute neutrophil count (ANC) to detect dangerous neutropenia; low results can prompt extra testing, specialist review or a clinician-directed treatment interruption. Schedules vary by country and treatment stage. Fever, sore throat or sudden illness needs urgent assessment—even after a reassuring result. Do not change clozapine yourself.

要点
- ANC units: 1.0 × 10⁹/L equals 1,000 cells/µL; check the units before comparing results with treatment thresholds.
- US general thresholds: ANC of 1,000–1,499 cells/µL can allow continued treatment with increased monitoring; 500–999 cells/µL usually triggers a clinician-directed interruption when clozapine-induced neutropenia is suspected.
- Severe neutropenia: ANC below 500 cells/µL requires urgent clinical management, usually treatment interruption and hematology involvement.
- Duffy-null counts: A documented Duffy-null-associated neutrophil count can justify a different treatment pathway; ancestry alone does not establish eligibility.
- US schedule: Prescribing-information monitoring generally starts weekly for 6 months, then every 2 weeks for 6 months, then monthly.
- Administrative changes: The FDA removed the US clozapine REMS on June 13, 2025; this removed registry requirements, not the clinical need for ANC monitoring.
- International schedules: Traditional UK pathways use weekly testing for 18 weeks, fortnightly testing until 1 year, then every 4 weeks; revised European recommendations can permit longer intervals in eligible stable patients.
- 緊急症状: Fever of 38.0°C or higher, new sore throat, mouth sores, shaking chills or sudden marked illness warrants urgent same-day assessment. Confusion, breathing difficulty or collapse requires emergency help.
What does clozapine monitoring actually decide?
Clozapine monitoring uses ANC results to help clinicians decide whether treatment can continue, needs closer surveillance or must be interrupted. An ANC below 500 cells/µL is a serious safety finding, but decisions at higher counts depend on the country's protocol, previous results and the patient's documented baseline.

An ANC result is not a stand-alone prescription instruction: a count of 1,200 cells/µL may permit continued treatment in one pathway but trigger a different response in another. The prescriber must identify the correct protocol before interpreting the number; applying a US threshold to a UK monitoring-service alert can create an avoidable medication-supply problem.
Kantesti is an AI blood test analyzer that can explain an ANC of 1.2 × 10⁹/L as 1,200 cells/µL, but our interpretation cannot authorize clozapine dispensing or replace the prescribing team. Our 会社情報は、より広範な医療AIのミッション、認証、および製品の範囲を説明しています。実用的な約束はシンプルです。迅速な解釈であっても、慎重な解釈であるべきです。 identifies the organization providing that educational service, rather than a clozapine monitoring registry.
A falling count deserves attention even before it crosses a treatment threshold: a hypothetical decline from 4,000 to 1,700 cells/µL differs from a long-standing baseline near 1,700. Our guide to ALCの低下と好中球の低下は複合細胞減少症と呼ばれ、薬剤、ウイルスによる骨髄抑制、自己免疫疾患、または骨髄疾患に続く可能性があります。好中球数が少ない場合の発熱は、この組み合わせにおける緊急の要素です。 explains ordinary variation, but clozapine users should obtain medication-specific advice rather than follow a general retesting timetable.
How do you read ANC units and calculate the count?
ANC measures the absolute number of neutrophils, not their percentage among white cells. The conversion is exact: 1.0 × 10⁹/L equals 1,000 cells/µL. A laboratory's reference interval and a clozapine treatment threshold answer different questions, so a flagged result does not automatically mean treatment must stop.
Most modern laboratories report ANC directly, usually as neutrophils, absolute neutrophils or NEUT#. If calculation is necessary, multiply the total WBC by the neutrophil fraction, including bands when separately reported; for example, 4,000 cells/µL × 0.40 gives an ANC of 1,600 cells/µL, not 40 cells/µL.
A hypothetical WBC of 6,000 cells/µL with neutrophils at 15% produces an ANC of 900 cells/µL despite a total WBC that may sit within the laboratory's reference interval. That discrepancy explains why the neutrophil reference-range guide distinguishes the absolute count from the differential percentage.
Decimal formatting can cause dangerous misunderstandings: 0.8 × 10⁹/L means 800 cells/µL, whereas 8.0 × 10⁹/L means 8,000 cells/µL. Compare the original report, collection date and units—not a cropped screenshot or a manually entered number—and ask the laboratory or monitoring team to resolve any ambiguity before the result is used for prescribing.
| レベル | 範囲 | 意味 |
|---|---|---|
| Above the conventional neutropenia cutoff | ≥1.5 × 10⁹/L; ≥1,500 cells/µL | Usually outside the conventional adult neutropenia definition; this is not a universal laboratory reference interval or dispensing rule. |
| 軽度の好中球減少 | 1.0–1.499 × 10⁹/L; 1,000–1,499 cells/µL | Requires interpretation against baseline, symptoms and the applicable clozapine pathway. |
| 中等度の好中球減少 | 0.5–0.999 × 10⁹/L; 500–999 cells/µL | Often requires urgent prescriber review; treatment actions differ for general and documented Duffy-null pathways. |
| 重度の好中球減少 | <0.5 × 10⁹/L; <500 cells/µL | High-risk finding requiring urgent clinical management, usually hematology involvement and clinician-directed interruption. |
Which ANC results change treatment in the US pathway?
The US general-population pathway usually permits clozapine initiation at ANC ≥1,500 cells/µL. During treatment, ANC of 1,000–1,499 cells/µL can allow continuation with intensified monitoring; 500–999 cells/µL generally requires interruption when clozapine-induced neutropenia is suspected. These are clinician actions, not instructions for patients to adjust medication.
For mild neutropenia, the US prescribing-information approach commonly increases ANC checks to 3 times weekly until recovery to at least 1,500 cells/µL. Correll et al. (2022), in CNS Drugs, reproduce these management pathways and emphasize that clozapine's substantial psychiatric benefits must be considered alongside hematological risk rather than treating every low result identically.
For ANC of 500–999 cells/µL in the general pathway, clinicians usually arrange hematology input and daily testing initially, with treatment resumption considered after recovery according to the label. A repeat sample can clarify an unexpected result, but a symptomatic patient or a rapidly falling count should not wait 24 hours merely to obtain a more convenient number.
A count below 500 cells/µL enters the severe-neutropenia pathway, where any later rechallenge requires an explicit specialist risk–benefit decision. Total WBC or CRP cannot substitute for ANC; our explanation of WBCとCRPの不一致 shows why apparently reassuring results elsewhere in the panel do not cancel a low neutrophil count.
| レベル | 範囲 | 意味 |
|---|---|---|
| US general-pathway initiation threshold | ANC ≥1,500 cells/µL | Usually eligible for initiation from a hematological perspective, subject to the full prescribing assessment. |
| Mild neutropenia during treatment | ANC 1,000–1,499 cells/µL | Treatment can often continue under prescriber direction with ANC monitoring 3 times weekly. |
| Moderate neutropenia during treatment | ANC 500–999 cells/µL | Usually interrupt if clozapine-induced neutropenia is suspected; obtain hematology advice and intensified monitoring. |
| Severe neutropenia during treatment | ANC <500 cells/µL | Interrupt under urgent clinical management; any future rechallenge needs specialist justification. |
How does a Duffy-null-associated count change decisions?
Documented Duffy-null-associated neutrophil counts can justify lower clozapine ANC thresholds because a stable lower circulating count does not necessarily indicate impaired immunity. US prescribing information has historically called this the benign ethnic neutropenia, or BEN, pathway; its usual initiation threshold is ANC ≥1,000 cells/µL with at least 2 baseline measurements.

Under the US documented BEN pathway, an ANC of 500–999 cells/µL may permit continued clozapine with hematology consultation and monitoring 3 times weekly. This differs from the general pathway at the same number; the distinction must already be established clinically, not inferred after an alarming result simply to avoid an interruption.
Ancestry is not a diagnostic test for Duffy-null status, and 2 people with similar ancestry may have different baseline ANC patterns. Our Duffy-null count explanation discusses phenotype or genotype evidence, historical counts and assessment for other causes; genetic testing is not universally required, but a clinician-documented explanation is needed for an alternative treatment pathway.
A hypothetical stable baseline of 1,200 cells/µL does not make a new fall to 450 cells/µL harmless: that result meets the severe-neutropenia threshold even in the US BEN pathway. Fever, recurrent unusual infections, anemia or low platelets also weakens the assumption that a low ANC is an isolated constitutional finding and warrants a broader assessment.
How large is clozapine neutropenia risk over time?
Clozapine neutropenia risk is concentrated early in treatment, especially during the first 18 weeks to 6 months, but it does not disappear later. Correll et al. (2022) describe agranulocytosis as affecting approximately 1% of treated patients; estimates vary across populations, monitoring systems and definitions, so this is not an individual prediction.
Approximately 1% means roughly 1 in 100 treated people in that broad estimate, not a 1% risk every month and not a 1% risk after every dose. Mild neutropenia is more frequent than agranulocytosis, and studies that combine the two outcomes can make the risk of life-threatening neutrophil depletion appear larger than it actually is.
Early intensive testing reflects the concentration of events during the first 6 months, rather than an assumption that each additional tablet causes predictable cumulative marrow damage. Severe clozapine-associated neutropenia is not reliably prevented by choosing a low dose alone, and a previously normal count cannot guarantee that the next count will remain normal.
After 2 years of stable treatment, the absolute risk is generally much lower than during initiation, which helps explain proposals for less frequent routine testing. Late neutropenia still needs investigation for medication effects, illness and marrow disease; our guide to よくある感染症の検査 explains why symptoms and other cell lines can reveal risks that an ANC-only schedule misses.
What is the US clozapine monitoring schedule after REMS?
The US prescribing-information ANC schedule generally remains weekly for 6 months, every 2 weeks for the next 6 months, then monthly. The FDA removed the clozapine REMS on June 13, 2025, ending its enrollment and ANC-reporting requirements; that administrative change did not remove the clinical recommendation to monitor neutrophils.

The FDA's 2025 clozapine REMS removal communication separates access restrictions from safe prescribing: prescribers, pharmacies and patients no longer need to participate in that federal registry. A pharmacy no longer needs the former REMS dispensing authorization, but the prescriber may still require a recent ANC and a local service may still use an electronic safety workflow.
For a hypothetical patient completing 6 months without a concerning ANC event, the usual label pathway moves from weekly to every-2-week monitoring rather than immediately to monthly testing. Neutropenia, a treatment interruption or a relevant medication change can alter that plan; ask which event starts the next monitoring period instead of counting months independently.
Kantesti can help explain a trend across 3 dated ANC reports, but our platform does not determine the next legally or clinically acceptable dispensing date. Our 薬剤安全性トレンドガイド explains why the original collection dates and the prescribing team's schedule must remain attached to any AI-generated summary.
Why can UK monitoring services use a different schedule?
Traditional UK clozapine monitoring pathways use weekly testing for 18 weeks, every 2 weeks until 1 year, then every 4 weeks. UK dispensing has also depended on product-linked monitoring-service clearance; revised recommendations and local implementation can change the pathway, so the patient's own service must confirm the schedule and action thresholds.

An older UK pathway may classify ANC of 1.5–2.0 × 10⁹/L as amber and below 1.5 × 10⁹/L as red in patients without an approved lower-baseline pathway. Those thresholds are not interchangeable with the US continuation algorithm, and legacy UK systems may also consider total WBC; the relevant service must state which rules it currently applies.
Every 4 weeks means every 28 days, not simply once in each calendar month, so a missed appointment can affect a supply window even when the previous result was satisfactory. A useful baseline testing plan should include who books the sample, who receives it and who contacts the patient if the monitoring service cannot release medication.
Administrative alerts can arise from an overdue sample, an unprocessed sample or a genuinely low count—3 different problems with different solutions. Contact the prescribing team and pharmacy promptly if supply is threatened; do not stretch doses, borrow tablets or assume that a policy change in another country has automatically changed your own monitoring-service rules.
What changed in revised European ANC recommendations?
Revised European recommendations allow less frequent ANC testing in eligible stable patients: weekly for 18 weeks, monthly through the first year, every 12 weeks after 1 year and annually after 2 years. These longer intervals depend on the specified absence of neutropenia and the locally implemented product information; they are not a universal schedule.

The European Medicines Agency's 2025 communication on revised routine blood count monitoring shifts the principal hematological measure toward ANC rather than combined WBC and ANC surveillance. The revised approach generally uses baseline ANC of at least 1,500 cells/µL, or at least 1,000 cells/µL in an established BEN pathway, while lowering some treatment-interruption thresholds compared with older European systems.
In the revised European approach, ANC below 1,000 cells/µL generally triggers stopping treatment in the standard pathway, whereas below 500 cells/µL is the corresponding threshold for an established BEN pathway. Results above those stopping thresholds can still require intensified surveillance; a hypothetical count of 1,100 cells/µL is not a reason to ignore a new downward trend.
Country authorization, the particular product information and service implementation can differ, even when patients have each taken clozapine for 2 years. Our guide to blood-test timing and changes explains why historical stability matters; obtain written confirmation before assuming that an annual European schedule applies to a UK, US or other national pathway.
What should happen after an unexpected low ANC?
An unexpected low ANC needs prompt prescriber review, confirmation when appropriate and assessment for causes other than clozapine. In the US label pathway, an initial ANC below 1,500 cells/µL is generally confirmed within 24 hours, but severe neutropenia or infection symptoms require immediate management rather than waiting for a routine repeat.
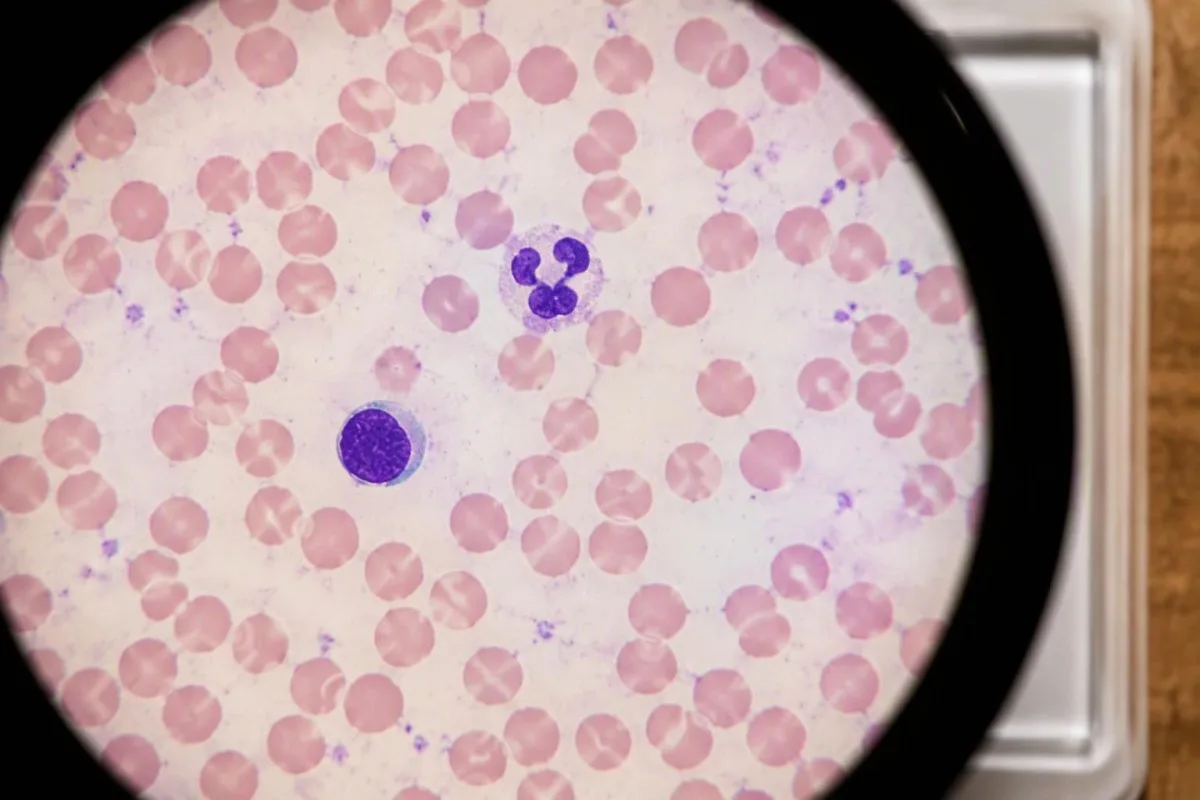
Recent viral illness, other medicines, autoimmune disease and nutritional deficiency can all lower ANC; a count of 900 cells/µL establishes neutropenia but does not establish its cause. Clinicians review the timing of drug exposure and may examine hemoglobin, platelets and a cell sample slide; concurrent abnormalities can justify evaluation for possible marrow disorders.
Kantesti is an AI blood test interpretation platform that can place an ANC of 0.9 × 10⁹/L beside platelet and hemoglobin trends, while leaving causation and medication decisions to clinicians. Our broader 血液学マーカーガイド explains why a normal red-cell result does not erase an isolated neutrophil problem.
Sampling time and temporary physiological variation can affect a borderline result, but there is no safe rule that an afternoon repeat will always normalize an ANC of 1,400 cells/µL. If a clinician requests a repeat at a consistent time, follow that plan without delaying necessary care; exercise, supplements or deliberate timing changes should not be used to manipulate a treatment-clearance result.
Which infection symptoms require urgent assessment?
During clozapine treatment, fever of 38.0°C or higher, new sore throat, mouth sores, shaking chills or sudden marked illness warrants urgent same-day clinical assessment. A known ANC below 500 cells/µL makes possible infection especially urgent. Confusion, breathing difficulty, fainting or rapidly worsening illness requires emergency help, regardless of the last count.

Formal febrile-neutropenia definitions often use a single temperature of at least 38.3°C or at least 38.0°C sustained for 1 hour, together with severe or impending severe neutropenia. Those definitions support clinical classification—not a home instruction to wait an hour; tell the urgent-care team that you take clozapine and provide your last ANC if available.
An ANC of 2,000 cells/µL measured 7 days ago cannot exclude a new fall today, and severe neutropenia can weaken usual local signs such as redness or discharge. Assessment may include an urgent CBC with differential, cultures and examination; our procalcitonin interpretation guide explains why a low infection biomarker cannot independently rule out an early serious infection.
New fever may also signal pneumonia, myocarditis or another illness that raises clozapine concentrations, creating 2 linked safety questions: immune protection and medication toxicity. Call the prescribing team's urgent number immediately for advice about the next dose; if you cannot reach them promptly while significantly unwell, seek urgent care rather than waiting for an app interpretation or routine appointment.
How do other medicines, smoking and illness affect monitoring?
Other medicines can increase neutropenia risk or change clozapine concentrations, and those are different problems requiring different tests. ANC is measured in cells/µL, whereas clozapine concentration is commonly measured in ng/mL; a normal ANC does not exclude excessive drug exposure, and a therapeutic concentration does not exclude neutropenia.

Carbamazepine is generally avoided with clozapine because of marrow-suppression risk and clinically relevant interactions; concurrent valproate has also been associated with neutropenia in observational studies. A hypothetical ANC decline from 2,600 to 1,300 cells/µL after adding another medicine warrants a complete medication review, not a conclusion that clozapine is necessarily the sole cause; valproate level interpretation addresses the separate issue of drug exposure.
Stopping combustible smoking can raise clozapine concentrations because smoke components—not nicotine itself—induce CYP1A2 metabolism. A person who stops smoking during a 3-day hospital admission may therefore need prescriber-directed concentration monitoring and dose review; our nicotine test explanation clarifies why cotinine alone does not measure the smoke-related enzyme effect.
Kantesti can explain why an ANC of 2,100 cells/µL and a clozapine level of 900 ng/mL describe different risks, but we cannot select a safer dose. Fever, major caffeine changes and interacting medicines such as ciprofloxacin can alter exposure; report new excessive sedation, confusion or muscle jerks promptly, even if the neutrophil result is reassuring.
What happens after missed tests or a treatment break?
A missed ANC appointment can create a supply problem, while a clozapine treatment break can create a separate restarting hazard. After more than 48 hours without clozapine, many protocols require supervised re-titration beginning at 12.5 mg once or twice daily rather than immediate return to the previous dose; exact instructions depend on the prescribing information.

Tolerance to clozapine's blood-pressure effects can be lost quickly, so restarting a previous 300 mg daily regimen after a break may cause profound hypotension or collapse. US prescribing information also specifies reduced restart doses for shorter interruptions; patients should contact the prescribing team after missed doses rather than using a remembered 48-hour rule to decide what to take.
A treatment break does not always reset ANC surveillance to the beginning, because monitoring rules depend on interruption duration and the reason treatment stopped. In the US normal-ANC pathway, interruptions of 30 days or longer generally return patients to initiation-style monitoring; national monitoring services may use different interruption rules, especially after an abnormal count.
After a hypothetical 5-day admission, confirm the last dose, current prescription, latest ANC and who will supervise the next dose before leaving hospital. Our explanation of 退院後の結果について helps organize altered laboratory values, but it cannot reconcile prescriptions or authorize restarting after neutropenia.
What does ANC monitoring miss about clozapine safety?
ANC monitoring does not detect clozapine-related myocarditis, constipation, metabolic complications or excessive drug concentrations. Some initiation protocols add weekly troponin and CRP during the first 4 weeks, while ongoing care assesses bowel function, weight, glucose and lipids. A satisfactory ANC therefore confirms only one part of medication safety.
New chest pain, breathlessness or persistent unexplained tachycardia during the first 4 weeks needs prompt clinical assessment rather than reassurance from a normal ANC. Troponin and CRP can support a myocarditis investigation, but thresholds and screening practices vary; our myocarditis testing explanation describes why laboratory results must be interpreted with symptoms and cardiac evaluation.
Clozapine-related bowel slowing can become dangerous even when stool is still passing, and severe abdominal pain, distension or vomiting requires urgent assessment. Record bowel frequency and stool consistency rather than asking only whether constipation is present; the 便の形状に関するガイド provides a shared description, while a change lasting 48 hours should prompt contact according to the patient's bowel-management plan.
Correll et al. (2022) describe a clozapine plasma reference range of approximately 350–600 ng/mL for many treatment-response decisions, while emphasizing individual variation and adverse effects. That range is not an ANC target or a universal safe-dose boundary; concentration samples usually need defined timing relative to the last dose, whereas routine ANC collection generally does not require a trough sample.
How should you prepare for your next clozapine review?
Bring the latest ANC, its units, earlier counts and a complete medication list to every clozapine review. Ask which national and service-specific pathway applies, what happens below its thresholds and whom to contact urgently. Keeping at least 3 dated results available helps distinguish a stable baseline from a new decline.
For a hypothetical sequence of 2,400, 1,900 and 1,400 cells/µL, useful questions concern the trend, recent illness, interacting medicines and the required next sample—not simply whether the latest value is red. Also ask who receives results outside office hours and whether the pharmacy needs monitoring-service clearance; these practical details can prevent an avoidable treatment gap.
Kantesti is an AI biomarker interpretation platform that helps translate an ANC of 1.4 × 10⁹/L into an understandable count and a list of clinician questions. Our 技術的・臨床的監督 describes the boundaries of interpretation; it does not establish that an automated answer is a validated clozapine prescribing decision or a substitute for hematology advice.
Kantesti's educational workflow should preserve 3 essentials: the source result, the applicable clinical protocol and the human decision-maker. Our 責任あるAIの原則 explain why urgent symptoms take priority over automated analysis, while our プライバシーとデータに関する情報を確認し、 explains considerations when sharing sensitive psychiatric and laboratory records.
研究出版物とエビデンスの適用範囲
The 2 Kantesti publications listed in the research publication section concern digestive symptoms and women's health, not clozapine ANC thresholds or monitoring schedules. Their Figshare DOIs identify those publications but do not establish peer review or provide evidence for clozapine decisions; the directly relevant medical and regulatory sources are listed separately below.
よくある質問
クロザピンの投与を継続できないANCの低値はどの程度ですか?
The ANC threshold for continuing clozapine depends on the country and the patient's documented baseline pathway. In the US general pathway, ANC of 1,000–1,499 cells/µL can allow continuation with increased monitoring, while 500–999 cells/µL usually requires interruption when clozapine-induced neutropenia is suspected. A documented BEN or Duffy-null-associated pathway can permit continuation at 500–999 cells/µL under specialist supervision. ANC below 500 cells/µL requires urgent clinical management; patients should obtain immediate prescriber instructions rather than change treatment themselves.
クロザピンのREMSが廃止された後も、ANC(絶対好中球数)の血液検査は必要ですか?
はい、米国のクロザピンREMSが廃止されても、ANCモニタリングの臨床上の推奨はなくなっていません。FDAは2025年6月13日に登録制度を廃止し、登録、報告、調剤承認の要件を終了しました。処方情報に記載された検査スケジュールは、通常、最初の6か月は毎週、次の6か月は2週間ごと、その後は毎月のままです。好中球減少症、投与中断、その他関連する臨床的変化があった場合、処方医が追加検査を求めることがあります。.
Why is my clozapine blood test schedule different from someone else's?
Clozapine blood test schedules differ because national product information, monitoring services, treatment duration and previous ANC events are not identical. Traditional UK pathways use weekly testing for 18 weeks, fortnightly testing until 1 year and testing every 4 weeks thereafter. Revised European recommendations can permit every-12-week testing after 1 year and annual testing after 2 years in eligible stable patients, subject to local implementation. Ask your own prescribing service to confirm the applicable schedule before changing any appointment.
Can clozapine cause neutropenia after years of normal results?
Clozapine-associated neutropenia can occur after years of normal results, although risk is much higher during early treatment. The first 18 weeks to 6 months account for a major concentration of severe events. A new low count after 2 years still needs assessment for clozapine, other medicines, infection and marrow or autoimmune conditions. A previously reassuring ANC does not remove the need for urgent assessment when fever or sudden illness develops.
What should I do if I have a fever while taking clozapine?
A fever of 38.0°C or higher while taking clozapine warrants urgent same-day clinical assessment, especially with sore throat, mouth sores, shaking chills or marked weakness. Tell the clinician that you take clozapine and provide your most recent ANC if available. A known ANC below 500 cells/µL makes possible infection especially urgent, and confusion, breathing difficulty or collapse requires emergency help. Obtain immediate prescribing advice about the next dose rather than waiting for the next routine test or changing medication independently.
Can I restart my usual clozapine dose after missing two days?
You should not restart your usual clozapine dose after a treatment break without instructions from the prescribing team. After more than 48 hours without treatment, many protocols require re-titration beginning at 12.5 mg once or twice daily because tolerance to blood-pressure effects can be lost. Some prescribing information also requires reduced doses after shorter interruptions. Contact the team promptly, since the correct restart plan and ANC schedule depend on the exact duration and reason for the break.
Does a normal white blood cell count mean my clozapine ANC is safe?
A normal total white blood cell count does not guarantee that the ANC is satisfactory for clozapine treatment. For example, a WBC of 6,000 cells/µL with 15% neutrophils produces an ANC of 900 cells/µL. Treatment decisions require the absolute neutrophil count, the applicable protocol and the clinical context rather than the WBC alone. A normal ANC also cannot exclude myocarditis, severe bowel slowing or excessive clozapine concentrations.
血液検査結果の見方を確認しましょう
検査報告書をアップロードすると、KantestiのAIが数秒で各バイオマーカーを平易な言葉で説明します。世界中で200万人以上が利用しています。.
参考文献
- Klein, T., Mitchell, S., & Weber, H. (2026). 断食後の下痢、便中の黒い粒子、消化器ガイド2026。. Kantesti AI医学研究。. 掲載日
- Klein, T., Mitchell, S., & Weber, H. (2026). 女性の健康ガイド:排卵、更年期、ホルモン関連症状。. Kantesti AI医学研究。. 掲載日
- Correll CU et al. (2022). A Guideline and Checklist for Initiating and Managing Clozapine Treatment in Patients with Treatment-Resistant Schizophrenia. CNS Drugs. 掲載日
- US Food and Drug Administration (2025). FDA removes risk evaluation and mitigation strategy (REMS) program for the antipsychotic drug Clozapine. FDA Drug Safety and Availability.
- European Medicines Agency (2025). Clozapine: revised recommendations for routine blood count monitoring. Direct healthcare professional communication.
- 200万以上分析対象の検査
- 127+国
- 100+言語
医療チームについて


E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
Thomas Klein医師による医学的レビュー。Sarah Mitchell医師およびHans Weber教授の協力。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.






医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
公開 · 編集チームにお問い合わせください
Kantesti Ltdが発行。イングランドおよびウェールズで登録、会社番号. 17090423, 、英国ロンドン。.
