Listeria can cause brief diarrhea or a serious bloodstream infection. Fever, pregnancy, immune suppression, and neurological symptoms determine which response is safest—not food exposure alone.

Punti chiave
- Intestinal illness usually begins within 24 hours of exposure and lasts 1–3 days; persistent fever or worsening illness needs reassessment.
- Urgent fever assessment is appropriate during pregnancy or immune suppression, especially with a temperature of 38.0°C or higher and a plausible food exposure.
- Pregnancy testing threshold in ACOG guidance is fever above 38.1°C with compatible symptoms after implicated food exposure and no other explanation; this is not a reason to delay care at 38.0°C.
- Sintomi di emergenza include confusion, stiff neck with fever, seizures, breathing difficulty, or rapidly worsening weakness; seek emergency care without waiting for a laboratory report.
- Listeria incubation period differs by syndrome: intestinal symptoms often begin within 24 hours, while invasive illness can appear days to weeks later.
- Blood cultures help diagnose suspected invasive listeriosis; a CBC, CRP, or ordinary stool panel cannot reliably exclude it.
- Exposure without symptoms generally warrants neither testing nor preventive antibiotics, including during pregnancy; monitor for symptoms over the following 2 months.
- limiti dell’interpretazione con IA mean our platform can explain existing laboratory results but cannot arrange cultures, identify the organism from routine biomarkers, or rule out listeriosis.
Which listeria symptoms need urgent evaluation?
Listeria symptoms need urgent evaluation when fever accompanies pregnancy, weakened immunity, or signs of invasive illness. Contact maternity care or your treating team promptly for a temperature of 38.0°C or higher; confusion, stiff neck with fever, seizures, or breathing difficulty require emergency care.
Brief diarrhea in an otherwise healthy adult is different from fever with chills, muscle aches, or unusual drowsiness in someone at increased risk. Listeria causes 2 broad syndromes—intestinal illness and invasive disease—and the same food exposure does not produce the same urgency in every person.
A temperature reading below 38.0°C does not make a rapidly deteriorating person safe, especially after fever-reducing medication or during immune suppression. The reason we worry about fever combined with confusion is that together they can suggest bloodstream or central nervous system involvement, rather than uncomplicated gastroenteritis.
For example, a hypothetical pregnant person with a temperature of 38.2°C and new aches after eating recalled food needs prompt clinical assessment, not an online testing purchase. A healthy adult with 2 loose stools, no fever, and normal hydration may instead need observation, provided no warning signs develop.
Kantesti è un Analizzatore di analisi del sangue AI that helps explain existing laboratory findings, but neither a normal CBC nor a 60-second interpretation excludes invasive listeriosis. Our organizzazione e finalità describe our role; urgent symptoms require a clinician who can examine you and arrange appropriate samples.
How does intestinal illness differ from invasive listeriosis?
Intestinal listeriosis primarily causes diarrhea and vomiting, whereas invasive listeriosis spreads beyond the intestine and can cause bloodstream infection or meningitis. Intestinal symptoms commonly start within 24 hours and last 1–3 days; invasive illness may occur without any preceding diarrhea.

Watery diarrhea, nausea, abdominal cramps, and sometimes fever can fit intestinal illness, but these symptoms cannot identify Listeria among foodborne causes. A 24-hour onset also overlaps with other illnesses; our explanation of norovirus recovery and testing illustrates why symptom timing alone rarely names the organism.
Invasive disease more often produces fever, chills, muscle aches, marked fatigue, or neurological changes such as imbalance and confusion. Someone who develops fever 10 days after a food exposure may have no bowel symptoms at all, so the absence of diarrhea should not close the diagnostic discussion.
A hypothetical healthy 34-year-old whose vomiting stops after 18 hours and who can drink normally has a different risk profile from a 74-year-old with new fever and unsteadiness. Age, immune suppression, and pregnancy shift concern toward invasive disease even when the gastrointestinal symptoms initially seem mild.
Recovery should move in the right direction over 1–3 days, not alternate between improvement and worsening systemic symptoms. Diarrhea continuing beyond that window, recurrent fever, reduced urination, or severe abdominal pain deserves reassessment; clinicians may investigate another pathogen or a noninfectious cause rather than assume persistent Listeria.
What is the listeria incubation period?
The listeria incubation period ranges from hours for intestinal illness to days or weeks for invasive disease. Public-health guidance describes invasive symptoms as usually beginning within 2 weeks, but pregnancy-associated illness can present considerably later; exposure follow-up commonly extends for 2 months.

Goulet et al. examined 37 invasive cases with reasonably defined exposures and reported median incubation periods of 2 days for bacteremia, 9 days for central nervous system disease, and 27.5 days for pregnancy-associated illness (Goulet et al., 2013). These were small, selected groups—not precise countdowns for an individual exposure.
The pregnancy-associated range in that study was 17–67 days, which helps explain why a food eaten several weeks earlier can remain relevant. The practical question is not simply whether symptoms began yesterday; clinicians need the date of exposure, the date symptoms started, and the type of illness suspected.
A hypothetical fever starting 6 hours after a particular meal does not prove that meal caused invasive listeriosis. Earlier meals, viral infections, urinary infections, and other causes remain possible; our digestive symptom timing guide explains why timing should narrow possibilities rather than establish a diagnosis.
Monitoring for 2 months after implicated exposure means remaining alert to new compatible symptoms, not measuring your temperature every hour while well. Keep a brief dated note of the food and recall details; repeated eating of the same product makes a single incubation calculation especially unreliable.
Why do listeria symptoms in pregnancy need faster assessment?
Listeria symptoms in pregnancy can be mild in the pregnant person while posing serious risks to the fetus or newborn. Fever, muscle aches, or unusual fatigue after implicated food exposure warrant prompt maternity advice; reduced fetal movement, contractions, or fluid leakage require urgent obstetric assessment.

Pregnant people are approximately 10 times more likely to develop listeriosis than the general population, according to CDC risk information. Listeria can cross the placenta, so apparently modest maternal illness can accompany miscarriage, stillbirth, premature delivery, or neonatal infection; symptom intensity is not a dependable measure of fetal safety.
ACOG Committee Opinion No. 614 recommends simultaneous testing and treatment for an exposed pregnant patient with fever above 38.1°C, compatible symptoms, and no other identified cause (ACOG, 2014). That threshold defines a management pathway—not a biological boundary—and a reading of 38.0°C with concerning symptoms should still prompt a call.
A hypothetical person at 28 weeks with aches, a temperature of 38.2°C, and a recalled-food exposure may need blood cultures and obstetric assessment before results return. Routine antenatal antibody tests answer different questions; our toxoplasma results in pregnancy explain one example of this distinction.
Reduced movement should be assessed according to your maternity unit's instructions, regardless of whether you have a fever or can identify an exposure. A fetal fibronectin result concerns preterm-birth assessment; it neither detects Listeria nor replaces evaluation of new contractions or fluid leakage.
Who is at higher risk of invasive listeriosis?
Adults aged 65 years or older, pregnant people, newborns, and people with weakened immunity have increased risk of invasive listeriosis. Transplant medicines, chemotherapy, some immune-suppressing treatments, and conditions such as advanced HIV can lower the threshold for assessing fever or otherwise unexplained illness.
Listeria can survive inside host cells, which makes cell-mediated immune defenses particularly relevant. A normal total white-cell count does not demonstrate normal protection against this organism; an adult aged 68 taking transplant medicines may be vulnerable even when a routine CBC carries no abnormal flags.
Medication exposure needs to be specific: the drug, dose, recent changes, and reason for treatment all help clinicians interpret risk. Someone receiving tacrolimus should not stop it after a food recall; our guida al monitoraggio del tacrolimus explains why treatment changes need transplant-team supervision rather than a single laboratory reading.
Known chemotherapy-related neutropenia creates a separate emergency pathway: commonly used fever definitions include 38.3°C once or 38.0°C sustained for 1 hour. Follow your oncology team's instructions immediately, and do not wait an hour if you feel unwell; broad assessment is needed, not testing for Listeria alone.
Kantesti AI can explain an absolute neutrophil count such as 0.4 × 10⁹/L, but it cannot determine the cause of accompanying fever or whether immune function is otherwise adequate. Our guide to test per infezioni frequenti separates blood-cell counts from wider immune assessment.
Which warning signs require emergency care now?
Confusion, seizures, stiff neck with fever, severe headache with altered awareness, breathing difficulty, or rapid deterioration require emergency assessment. These signs can indicate meningitis, sepsis, or another serious condition; you do not need a temperature above 38.1°C or a confirmed food exposure before seeking help.
Listeria meningitis may cause headache, neck stiffness, confusion, loss of balance, or seizures, but not everyone develops the full pattern. A hypothetical 72-year-old with fever and new difficulty walking needs urgent assessment even without neck stiffness; waiting for all the classic symptoms can delay appropriate treatment.
Sepsis can present with very low blood pressure, reduced urine output, mottled appearance, or unusual drowsiness, sometimes without a high fever. A lactate above 2 mmol/L can add concern in the appropriate setting, but our lactate result interpretation explains why sampling conditions and noninfectious causes also matter.
A baby younger than 3 months with a temperature of 38.0°C or higher needs urgent medical assessment, whether or not Listeria is suspected. Poor feeding, abnormal sleepiness, breathing changes, or a low temperature can also signal serious neonatal illness; maternal exposure history should be shared but must not delay care.
Hospital teams may check platelets, clotting, kidney function, and lactate when systemic illness is severe; none identifies Listeria on its own. Our sepsis-related clotting patterns explain one complication, but do not wait for even 1 abnormal laboratory result when emergency symptoms are present.
Does recalled food exposure alone require testing?
Eating food recalled for Listeria generally does not require testing or preventive antibiotics when you remain well, including during pregnancy. The CDC exposure-management framework and ACOG guidance instead support symptom awareness, with reassessment if compatible illness develops within the next 2 months.

A recall identifies a potentially contaminated product; it does not establish that every package contained Listeria or that every person who ate it became infected. Three separate questions matter: whether your product matches the recall, whether you actually ate it, and whether you have developed compatible symptoms.
There is no validated blood-test schedule at 24 hours, 7 days, or 2 weeks that reliably screens a well person after exposure. Blood cultures sample what is happening in the bloodstream at collection, so a negative culture obtained without illness would not guarantee that invasive disease cannot develop later.
Save the product name, batch details, exposure date, and recall notice before discarding the food as instructed; these are more useful than repeated routine panels. Our guida sul tempismo dei test del sangue explains why results from different dates cannot be treated as interchangeable snapshots.
A hypothetical pregnant person who ate recalled food 3 days ago but feels entirely well usually does not need antibiotics or cultures solely for that event. New fever, aches, diarrhea, or obstetric symptoms changes the decision; if you already had symptoms that resolved, describe that history rather than classify yourself as never symptomatic.
How is listeria diagnosed, and when are blood cultures appropriate?
Invasive listeriosis is diagnosed by identifying Listeria monocytogenes from a normally sterile site, commonly blood or cerebrospinal fluid. Blood cultures are appropriate when compatible systemic illness raises suspicion, especially in pregnancy, older age, or immune suppression—not simply because a recalled food was eaten.

Blood cultures are generally collected before antibiotics when this can be done without delaying urgent treatment; hospitals commonly collect 2 sets for adult bloodstream-infection assessment. Appropriate sample volume and aseptic collection improve usefulness, but pregnancy, children, and difficult access may require an adapted collection plan.
Suspected meningitis may require lumbar puncture for cerebrospinal fluid culture and other tests, provided the procedure is clinically safe. A 1-time negative blood culture does not exclude central nervous system disease, particularly after antibiotics; the team must interpret the specimen source, collection timing, and clinical presentation together.
Standard meningitis molecular panels can include Listeria, whereas other panels do not; a negative result only addresses the organisms and specimen covered by that assay. Our typhoid culture and timing guide discusses a parallel problem: nonspecific blood findings and antibody screens are not substitutes for suitable microbiology.
ACOG's exposed-pregnancy pathway recommends blood cultures when fever above 38.1°C accompanies compatible illness without another cause (ACOG, 2014). A culture that identifies Listeria needs prompt clinician review and treatment planning; incubation and organism identification take time, so the initial decision may need to precede confirmation.
What if you have mild symptoms but no fever?
Mild, afebrile symptoms after implicated exposure need individualized assessment in high-risk people, but do not automatically require antibiotics. CDC's framework allows observation or blood cultures in selected higher-risk patients; worsening symptoms or a new temperature of 38.0°C or higher should trigger prompt reassessment.
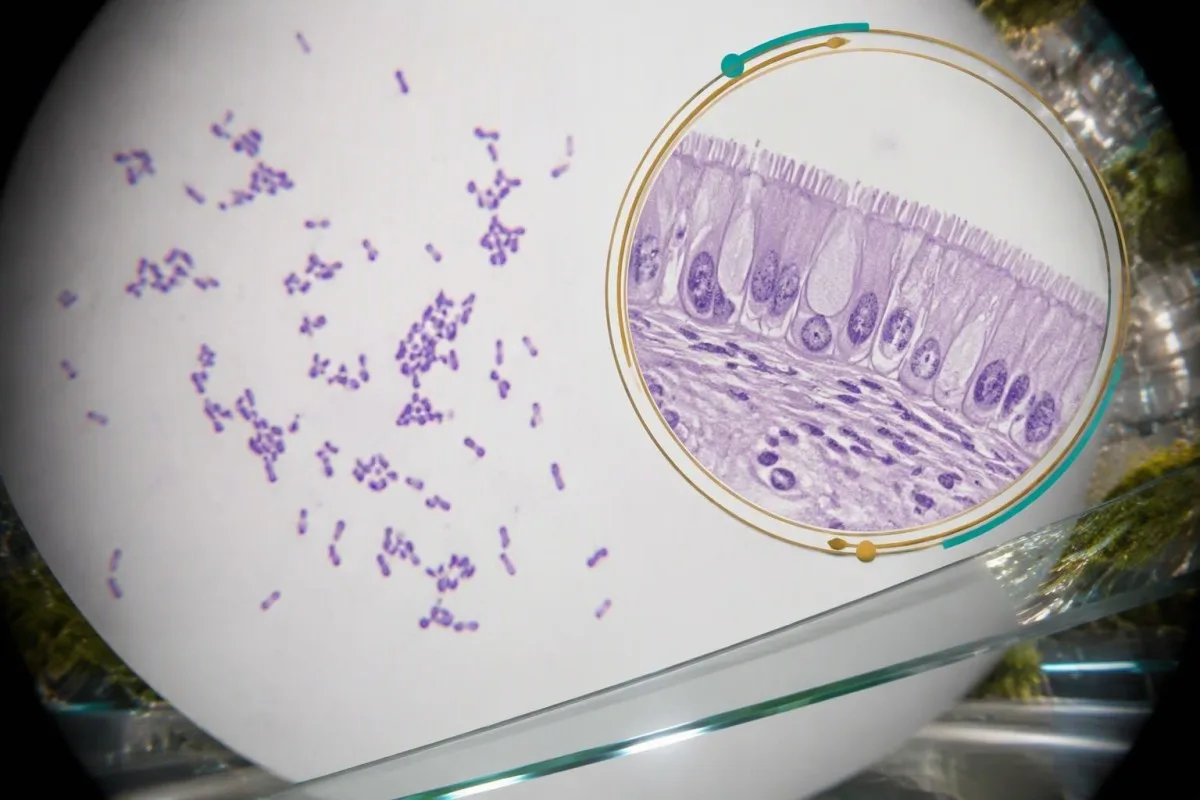
An exposed pregnant person with mild nausea or diarrhea but no fever should contact maternity care for advice rather than assume either infection or complete safety. The evidence for treating this afebrile group is limited; clinicians may reasonably choose different approaches after considering 2 factors—exposure credibility and the symptom pattern.
Ordinary stool cultures and common gastrointestinal PCR panels are not reliable screening tools for invasive listeriosis; many do not test for Listeria at all. A stool result naming another pathogen can explain diarrhea, but it does not necessarily explain persistent systemic symptoms in a high-risk person 1 week later.
A positive stool finding also does not automatically establish invasive disease, because intestinal carriage and systemic infection are different questions. Our guide to Campylobacter stool PCR results explains why detecting an organism, deciding whether it caused illness, and choosing treatment are 3 separate steps.
A hypothetical transplant recipient with 2 days of mild diarrhea, no fever, and a clear recall match may be advised to have cultures or closer observation. Persistent diarrhea also raises medication effects, dehydration, and other pathogens; seek earlier advice if drinking becomes difficult or urine output falls.
How is invasive listeriosis treated?
Invasive listeriosis usually requires hospital-directed antibiotics, most often intravenous ampicillin or another appropriate Listeria-active regimen. Treatment depends on the infection site, pregnancy, kidney function, and allergy history; uncomplicated bloodstream infection often needs at least about 14 days, while meningitis usually requires a longer course.

Listeria is not reliably treated by cephalosporins, so ceftriaxone alone is inadequate when Listeria meningitis is a concern. Empirical meningitis regimens add appropriate Listeria coverage for relevant risk groups; antibiotic choice should not be inferred from a generic 'bacterial infection' label or a single CRP result.
A typical adult meningitis regimen may use ampicillin 2 g intravenously every 4 hours when kidney function permits, but doses require clinician adjustment. This is not a home-treatment instruction: the site of illness, body size, renal function, and complications determine both dosing and how long treatment continues.
Gentamicin is sometimes added, although the benefit of combination treatment is uncertain and practice varies; kidney and hearing toxicity matter. Our gentamicin level monitoring explains why a trough above the local target can require intervention rather than simply completing the original dosing schedule.
A serious penicillin allergy can change treatment, with trimethoprim-sulfamethoxazole among possible alternatives under specialist supervision; pregnancy adds further considerations. Tell the team whether the reaction involved hives, breathing problems, or a delayed rash, even if it occurred 20 years ago; our guida alla rivalutazione dell’allergia alla penicillina explains why the details matter.
Can CBC, CRP, or procalcitonin rule out Listeria?
A CBC, CRP, or procalcitonin result cannot confirm or exclude listeriosis. These tests help assess inflammation, immune-cell patterns, and illness severity, but a normal white-cell count or CRP below 5 mg/L must not override concerning symptoms in pregnancy or immune suppression.

Many adult laboratories use a white-cell reference interval near 4.0–11.0 × 10⁹/L, but local ranges, pregnancy, and medicines alter interpretation. A value inside that interval does not demonstrate the absence of bacteremia; our confronto WBC e CRP explains why these markers can disagree during evolving illness.
A hypothetical pregnant person with WBC 10.8 × 10⁹/L, CRP 4 mg/L, fever of 38.3°C, and a credible exposure still needs clinical assessment. CRP can lag behind symptom onset, while pregnancy itself can raise white-cell counts; neither direction supplies a Listeria-specific answer.
Procalcitonin below 0.1 ng/mL is often considered low, depending on the assay, but there is no validated low cutoff that safely excludes invasive listeriosis. Our procalcitonin thresholds and trends explain why early infection, localized disease, and clinical context limit standalone reassurance.
Kantesti è un Piattaforma di interpretazione esami del sangue AI that can explain patterns such as CRP 45 mg/L alongside creatinine and CBC findings, without identifying the responsible bacterium. Our technical and clinical safeguards distinguish interpretation support from microbiological diagnosis; antibiotics and cultures must follow clinical assessment.
What does a preliminary or negative culture report mean?
A preliminary culture report describes an incomplete laboratory process, while a negative result only reflects the samples and conditions tested. 'No growth at 24 hours' is not the same as a final negative report; previous antibiotics and inadequate collection can reduce the chance of detecting Listeria.

A report of 'Gram-positive rods' means the laboratory has described bacterial shape and staining, not confirmed Listeria species. Some organisms with this appearance may represent contamination, but clinicians must not dismiss the finding automatically in a pregnant or immunocompromised person with fever of 38.2°C.
Many laboratories finalize routine negative blood cultures after approximately 5 days, although systems and special protocols vary. The exact wording matters: 'pending,' 'no growth to date,' and 'final no growth' describe different stages, and an organism detected early still needs identification and susceptibility work where appropriate.
A hypothetical patient whose cultures were collected 2 hours after the first antibiotic dose may have a negative result despite genuine bacterial illness. Persistent neurological symptoms, ongoing fever, or obstetric concerns may therefore justify further investigation; repeat cultures should answer a clinical question rather than follow an automatic calendar.
Kantesti can help explain report terminology, but it cannot turn 'no growth at 24 hours' into an exclusion of invasive listeriosis. Our guida alla tecnologia di interpretazione con IA describes how report information is processed; incomplete source data remains incomplete, regardless of how clearly the explanation is written.
What follow-up and food precautions are useful?
After assessment, follow-up should track symptoms and the clinician's plan—not rely on repeated screening while well. After implicated food exposure, remain alert for compatible illness for 2 months; during recovery from confirmed listeriosis, recurrent fever, new neurological symptoms, or obstetric changes need prompt reassessment.

Listeria can grow at refrigerator temperatures, so refrigeration does not make a recalled ready-to-eat product safe. Keep the refrigerator at 4°C or colder, follow storage limits, and clean surfaces that contacted the implicated food; discarding only the visibly spoiled part is not an adequate response.
Higher-risk people should choose pasteurized dairy products and follow local advice about chilled ready-to-eat foods; some chilled foods require reheating rather than simply confirming pasteurization. Where reheating is recommended, reaching 74°C or steaming hot throughout reduces risk, but recalled products should be discarded according to recall instructions rather than salvaged.
A hypothetical person discharged after invasive illness may have improving symptoms while CRP remains above 5 mg/L; conversely, new fever matters even if a previous result was falling. Our laboratory changes after hospital discharge explains why symptoms, sample dates, and treatment timing should be reviewed together.
Kantesti è un servizio di interpretazione dei test del laboratorio di IA that can organize existing results from 2 or more dates, but recovery decisions remain with your treating team. Before sharing reports, review our indicazioni sulla privacy e sui dati; result uploads should never delay reporting recurrent fever or new neurological symptoms.
Research, evidence limits, and your care checklist
Listeria decisions depend on clinical presentation, risk group, and suitable microbiology—not an exposure history or inflammation marker alone. Prepare 4 details for your consultation: food and recall information, exposure dates, symptom and temperature history, and pregnancy or immune-suppression status.
Goulet et al. (2013) provide useful incubation estimates, but their 37 invasive cases with defined exposures cannot predict an individual's exact symptom-onset date. ACOG's 2014 pregnancy guidance offers a practical exposure-management pathway; its fever threshold supports clinical decisions rather than proving that lower temperatures are harmless.
The MONALISA prospective cohort describes the clinical features and prognostic factors of invasive listeriosis (Charlier et al., 2017), not the likelihood of infection after 1 serving of recalled food. Hospitalized, confirmed cases are a selected population, so their outcomes should not be presented as the risk faced by every exposed, well person.
The 2 DOI-linked laboratory-education publications below concern other diagnostic topics and are not evidence for Listeria incubation, pregnancy management, or antibiotic selection. A DOI identifies a publication record; it does not by itself establish peer review, clinical validity, or relevance to the decision you need to make.
Our Kantesti medical content team separates clinical evidence from interpretation support under our standard di contenuto medico. Before ending a consultation, ask 3 questions: which results are pending, who will review them, and which symptoms mean you should seek help before the planned follow-up.
Domande frequenti
Quali sono i primi sintomi della listeriosi?
I primi sintomi della listeriosi possono essere diarrea e vomito che iniziano entro 24 ore, oppure febbre, dolori e stanchezza che compaiono giorni o settimane dopo in caso di malattia invasiva. La malattia intestinale dura comunemente da 1 a 3 giorni, ma la listeriosi invasiva può manifestarsi senza diarrea. La gravidanza, l’età pari o superiore a 65 anni e un sistema immunitario indebolito aumentano il rischio di sintomi sistemici. Confusione, convulsioni o rigidità del collo con febbre richiedono una valutazione d’emergenza.
Quali sono i sintomi della listeriosi in gravidanza?
I sintomi della listeriosi in gravidanza spesso includono febbre, dolori muscolari e stanchezza insolita, a volte con diarrea o senza sintomi gastrointestinali evidenti. Una temperatura pari o superiore a 38.0°C associata a un quadro compatibile dovrebbe indurre a contattare il servizio di maternità, soprattutto dopo l’esposizione ad alimenti implicati. Le linee guida ACOG indicano una febbre superiore a 38.1°C associata a sintomi compatibili e senza altre cause come criterio per eseguire test e avviare il trattamento nelle pazienti in gravidanza esposte. Una riduzione dei movimenti fetali, le contrazioni o la perdita di liquido richiedono una valutazione ostetrica urgente, indipendentemente dalla temperatura.
Quanto tempo dopo aver mangiato cibo contaminato compaiono i sintomi della listeriosi?
I sintomi intestinali da Listeria spesso iniziano entro 24 ore, mentre i sintomi invasivi di solito iniziano entro 2 settimane, ma possono comparire più tardi. Un piccolo studio sul periodo di incubazione ha riportato mediane di 2 giorni per la batteriemia, 9 giorni per la malattia del sistema nervoso centrale e 27.5 giorni per la malattia associata alla gravidanza. Queste cifre descrivono gruppi selezionati e non forniscono un conto alla rovescia esatto per un singolo individuo. Le indicazioni sull’esposizione raccomandano comunemente di prestare attenzione a eventuali sintomi compatibili per 2 mesi.
Dovrei fare il test per la Listeria dopo aver mangiato un alimento ritirato dal mercato?
In genere, dopo l’esposizione a un alimento richiamato, non sono raccomandati test né antibiotici preventivi se si sta bene, anche durante la gravidanza. Nei 2 mesi successivi, monitorare l’eventuale comparsa di sintomi compatibili e conservare il prodotto e i dettagli dell’esposizione. Nuova febbre, dolori, diarrea o sintomi ostetrici possono modificare la valutazione, soprattutto nelle persone a maggior rischio. Non esiste un programma di esami del sangue di routine convalidato a 24 ore o a 7 giorni che garantisca di non sviluppare la listeriosi in seguito.
Come viene diagnosticata la Listeria?
La listeriosi invasiva viene diagnosticata identificando Listeria monocytogenes in un sito normalmente sterile, come il sangue o il liquido cerebrospinale. Nei pazienti adulti con sospetta infezione del flusso sanguigno, i medici prelevano comunemente 2 set di emocolture, adattando la procedura alle circostanze cliniche. L’emocromo (CBC), la CRP, i test anticorpali e i comuni esami delle feci non possono confermare o escludere in modo affidabile la listeriosi invasiva. Quando possibile, i campioni per le colture dovrebbero essere raccolti prima di somministrare antibiotici, senza ritardare il trattamento urgente.
Gli esami del sangue normali possono escludere la listeriosi?
0 Esami del sangue di routine nella norma non possono escludere la listeriosi. Una conta dei globuli bianchi compresa nell’intervallo tipico per gli adulti di 4,0–11,0 × 10⁹/L o una CRP inferiore a 5 mg/L possono essere riscontrate anche in presenza di una malattia clinicamente preoccupante. La gravidanza, i farmaci immunosoppressori e un prelievo precoce possono rendere questi risultati particolarmente difficili da interpretare. Sintomi compatibili e fattori di rischio determinano se siano necessari una visita, esami colturali o un trattamento urgente.
La listeriosi può guarire senza antibiotici?
Mild intestinal listeriosis in an otherwise healthy person often resolves within 1–3 days without antibiotics. Invasive listeriosis requires clinician-directed antibiotic treatment and frequently hospital care. Pregnancy, weakened immunity, persistent fever, or neurological changes make self-management unsafe even if diarrhea seems mild. A temperature of 38.0°C or higher in a higher-risk person warrants prompt advice rather than waiting for the intestinal recovery window to pass.
Scopri come leggere le analisi del sangue
Carica il tuo referto di laboratorio e l'IA di Kantesti spiega ogni biomarcatore in un linguaggio semplice in pochi secondi. Utilizzata da oltre 2 milioni di persone in tutto il mondo.
Riferimenti
- Klein, T., Mitchell, S., & Weber, H. (2026). Esame del sangue per il virus Nipah: guida alla diagnosi e alla diagnosi precoce 2026. Ricerca medica sull'IA di Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Guida al gruppo sanguigno B negativo, all’esame del sangue LDH e alla conta dei reticolociti. Ricerca medica sull'IA di Kantesti. DOI
- American College of Obstetricians and Gynecologists (2014). Committee Opinion No. 614: Management of Pregnant Women With Presumptive Exposure to Listeria monocytogenes. Obstetrics & Gynecology.
- Goulet V et al. (2013). What is the incubation period for listeriosis? BMC Infectious Diseases. DOI
- Charlier C et al. (2017). Clinical features and prognostic factors of listeriosis: the MONALISA national prospective cohort study. The Lancet Infectious Diseases. DOI
- 2 milioni+Esami analizzati
- 127+Paesi
- 100+Lingue
Informazioni sul team medico


Segnali di fiducia E-E-A-T
Esperienza
Revisione clinica guidata da un medico dei flussi di lavoro di interpretazione degli esami.
Competenza
Focus sulla medicina di laboratorio su come i biomarcatori si comportano nel contesto clinico.
autorevolezza
Revisione medica a cura del dott. Thomas Klein, con il contributo della dott.ssa Sarah Mitchell e del prof. Hans Weber.
Affidabilità
Interpretazione basata su evidenze, con percorsi di follow-up chiari per ridurre l’allarme.






Avvertenza medica
Questo articolo ha solo scopo educativo e non costituisce consulenza medica. Consulta sempre un operatore sanitario qualificato per decisioni su diagnosi e trattamento.
Pubblicato · Contatta il team editoriale
Pubblicato da Kantesti Ltd, registrata in Inghilterra e Galles, numero di società. 17090423, Londra, Regno Unito.
