لیستریا میتواند باعث اسهال کوتاهمدت یا عفونت جدی جریان خون شود. تب، بارداری، سرکوب ایمنی و علائم عصبی تعیین میکنند کدام اقدام ایمنتر است—نه صرفاً قرار گرفتن در معرض غذا.

نکات کلیدی
- بیماری رودهای معمولاً ظرف ۲۴ ساعت پس از مواجهه آغاز میشود و ۱ تا ۳ روز ادامه مییابد؛ تب مداوم یا تشدید بیماری نیازمند ارزیابی مجدد است.
- ارزیابی فوری تب در دوران بارداری یا سرکوب ایمنی مناسب است، بهویژه با دمای ۳۸٫۰°C یا بالاتر و مواجهه محتمل با غذا.
- آستانه آزمایش در بارداری در راهنمای ACOG، تب بالاتر از ۳۸٫۱°C همراه با علائم سازگار پس از مواجهه با غذای مشکوک و بدون توضیح دیگری است؛ این دلیلی برای بهتعویقانداختن مراقبت در دمای ۳۸٫۰°C نیست.
- علائم اورژانسی شامل گیجی، سفتی گردن همراه با تب، تشنج، دشواری تنفس یا ضعف با تشدید سریع است؛ بدون انتظار برای گزارش آزمایشگاهی به اورژانس مراجعه کنید.
- دوره نهفتگی لیستریا بسته به سندرم متفاوت است: علائم رودهای اغلب ظرف ۲۴ ساعت آغاز میشوند، درحالیکه بیماری تهاجمی ممکن است روزها تا هفتهها بعد بروز کند.
- کشت خون به تشخیص لیستریوز تهاجمیِ مشکوک کمک میکند؛ CBC، CRP یا پنل معمول آزمایش مدفوع نمیتواند آن را با اطمینان رد کند.
- مواجهه بدون علامت معمولاً نه آزمایش لازم دارد و نه آنتیبیوتیک پیشگیرانه، حتی در دوران بارداری؛ طی ۲ ماه آینده علائم را زیر نظر بگیرید.
- محدودیتهای تفسیر با هوش مصنوعی یعنی پلتفرم ما میتواند نتایج آزمایشگاهی موجود را تفسیر کند، اما نمیتواند کشت تجویز کند، عامل بیماریزا را از نشانگرهای زیستی معمول شناسایی کند یا لیستریوز را رد کند.
کدام علائم لیستریا نیاز به ارزیابی فوری دارند؟
بروز علائم لیستریا در صورت همراهی تب با بارداری، ضعف ایمنی یا نشانههای بیماری تهاجمی، نیازمند ارزیابی فوری است. در صورت رسیدن دما به ۳۸٫۰°C یا بالاتر، فوراً با مراقبتهای بارداری یا تیم درمان خود تماس بگیرید؛ گیجی، سفتی گردن همراه با تب، تشنج یا دشواری تنفس نیازمند مراقبت اورژانسی است.
اسهال کوتاهمدت در یک بزرگسالِ سالم با تب همراه با لرز، درد عضلانی یا خوابآلودگی غیرعادی در فردی با خطر بیشتر تفاوت دارد. لیستریا دو سندرم کلی ایجاد میکند—بیماری رودهای و بیماری تهاجمی—و مواجهه یکسان با غذا برای همه افراد به یک اندازه فوریت ندارد.
پایینتر بودن دمای ثبتشده از ۳۸٫۰°C به این معنا نیست که حال فردی که بهسرعت رو به وخامت است خوب است، بهویژه پس از مصرف داروی تببر یا در دوره سرکوب ایمنی. علت نگرانی از تب همراه با گیجی این است که این دو با هم میتوانند نشاندهنده درگیری جریان خون یا دستگاه عصبی مرکزی باشند، نه گاستروانتریت بدون عارضه.
برای مثال، یک فرد باردار فرضی با دمای ۳۸٫۲°C و دردهای تازه پس از خوردن غذای فراخوانشده، به ارزیابی بالینی فوری نیاز دارد، نه خرید آنلاین آزمایش. یک بزرگسال سالم با ۲ بار مدفوع شل، بدون تب و با آبرسانی طبیعی، ممکن است بهجای آن فقط نیازمند زیر نظر گرفتن باشد، بهشرط آنکه علائم هشدار بروز نکنند.
کانتستی یک آنالایزر آزمایش خون هوش مصنوعی که به توضیح یافتههای آزمایشگاهی موجود کمک میکند، اما نه CBC طبیعی و نه تفسیر ۶۰ثانیهای نمیتواند لیستریوز تهاجمی را رد کند. ما سازمان و هدف نقش ما را توصیف میکنند؛ علائم فوری نیازمند پزشکی هستند که بتواند شما را معاینه کند و نمونههای مناسب را بگیرد.
بیماری رودهای چه تفاوتی با لیستریوز تهاجمی دارد؟
لیستریوز رودهای عمدتاً باعث اسهال و استفراغ میشود، درحالیکه لیستریوز تهاجمی از روده فراتر میرود و میتواند باعث عفونت جریان خون یا مننژیت شود. علائم رودهای معمولاً ظرف ۲۴ ساعت آغاز میشوند و ۱–۳ روز ادامه مییابند؛ بیماری تهاجمی ممکن است بدون هیچ اسهال قبلی بروز کند.

اسهال آبکی، تهوع، گرفتگی شکم و گاهی تب میتوانند با بیماری رودهای سازگار باشند، اما این علائم نمیتوانند لیستریا را از میان عوامل بیماریزای منتقله از غذا شناسایی کنند. آغاز علائم پس از ۲۴ ساعت نیز با بیماریهای دیگر همپوشانی دارد؛ توضیح ما درباره بهبودی و آزمایش نوروویروس نشان میدهد چرا زمانبندی علائم بهتنهایی بهندرت عامل بیماریزا را مشخص میکند.
بیماری تهاجمی بیشتر با تب، لرز، درد عضلانی، خستگی شدید یا تغییرات عصبی مانند عدم تعادل و گیجی بروز میکند. ممکن است فردی که ۱۰ روز پس از مواجهه با غذا دچار تب میشود، اصلاً علائم گوارشی نداشته باشد؛ بنابراین نبود اسهال نباید بحث تشخیصی را خاتمه دهد.
یک فرد سالم و فرضی ۳۴ساله که استفراغش پس از ۱۸ ساعت متوقف میشود و میتواند بهطور طبیعی مایعات بنوشد، با یک فرد ۷۴ساله که دچار تب تازه و بیثباتی در راهرفتن شده، نمایه خطر متفاوتی دارد. سن، سرکوب ایمنی و بارداری، حتی زمانی که علائم گوارشی در ابتدا خفیف به نظر میرسند، نگرانی از بیماری تهاجمی را افزایش میدهند.
روند بهبودی باید طی ۱–۳ روز رو به بهبود باشد، نه اینکه با علائم سیستمیکِ رو به وخامت متناوب شود. ادامه اسهال بیش از این بازه، تب عودکننده، کاهش ادرار یا درد شدید شکم نیازمند ارزیابی مجدد است؛ پزشکان ممکن است بهجای فرض تداوم لیستریا، عامل بیماریزای دیگری یا علتی غیرعفونی را بررسی کنند.
دوره نهفتگی لیستریا چقدر است؟
دوره کمون لیستریا برای بیماری رودهای از چند ساعت تا چند روز یا چند هفته برای بیماری تهاجمی متغیر است. راهنمای بهداشت عمومی میگوید علائم تهاجمی معمولاً طی ۲ هفته آغاز میشوند، اما بیماری مرتبط با بارداری میتواند بسیار دیرتر بروز کند؛ پیگیری مواجهه معمولاً تا ۲ ماه ادامه مییابد.

Goulet et al. examined 37 invasive cases with reasonably defined exposures and reported median incubation periods of 2 days for bacteremia, 9 days for central nervous system disease, and 27.5 days for pregnancy-associated illness (Goulet et al., 2013). These were small, selected groups—not precise countdowns for an individual exposure.
The pregnancy-associated range in that study was 17–67 days, which helps explain why a food eaten several weeks earlier can remain relevant. The practical question is not simply whether symptoms began yesterday; clinicians need the date of exposure, the date symptoms started, and the type of illness suspected.
A hypothetical fever starting 6 hours after a particular meal does not prove that meal caused invasive listeriosis. Earlier meals, viral infections, urinary infections, and other causes remain possible; our digestive symptom timing guide explains why timing should narrow possibilities rather than establish a diagnosis.
Monitoring for 2 months after implicated exposure means remaining alert to new compatible symptoms, not measuring your temperature every hour while well. Keep a brief dated note of the food and recall details; repeated eating of the same product makes a single incubation calculation especially unreliable.
چرا علائم لیستریا در بارداری نیاز به ارزیابی سریعتری دارند؟
Listeria symptoms in pregnancy can be mild in the pregnant person while posing serious risks to the fetus or newborn. Fever, muscle aches, or unusual fatigue after implicated food exposure warrant prompt maternity advice; reduced fetal movement, contractions, or fluid leakage require urgent obstetric assessment.

Pregnant people are approximately 10 times more likely to develop listeriosis than the general population, according to CDC risk information. Listeria can cross the placenta, so apparently modest maternal illness can accompany miscarriage, stillbirth, premature delivery, or neonatal infection; symptom intensity is not a dependable measure of fetal safety.
ACOG Committee Opinion No. 614 recommends simultaneous testing and treatment for an exposed pregnant patient with fever above 38.1°C, compatible symptoms, and no other identified cause (ACOG, 2014). That threshold defines a management pathway—not a biological boundary—and a reading of 38.0°C with concerning symptoms should still prompt a call.
A hypothetical person at 28 weeks with aches, a temperature of 38.2°C, and a recalled-food exposure may need blood cultures and obstetric assessment before results return. Routine antenatal antibody tests answer different questions; our toxoplasma results in pregnancy explain one example of this distinction.
Reduced movement should be assessed according to your maternity unit's instructions, regardless of whether you have a fever or can identify an exposure. A fetal fibronectin result concerns preterm-birth assessment; it neither detects Listeria nor replaces evaluation of new contractions or fluid leakage.
چه کسانی در معرض خطر بیشتر لیستریوز تهاجمی هستند؟
Adults aged 65 years or older, pregnant people, newborns, and people with weakened immunity have increased risk of invasive listeriosis. Transplant medicines, chemotherapy, some immune-suppressing treatments, and conditions such as advanced HIV can lower the threshold for assessing fever or otherwise unexplained illness.
Listeria can survive inside host cells, which makes cell-mediated immune defenses particularly relevant. A normal total white-cell count does not demonstrate normal protection against this organism; an adult aged 68 taking transplant medicines may be vulnerable even when a routine CBC carries no abnormal flags.
Medication exposure needs to be specific: the drug, dose, recent changes, and reason for treatment all help clinicians interpret risk. Someone receiving tacrolimus should not stop it after a food recall; our راهنمای پایش تاکرولیموس explains why treatment changes need transplant-team supervision rather than a single laboratory reading.
Known chemotherapy-related neutropenia creates a separate emergency pathway: commonly used fever definitions include 38.3°C once or 38.0°C sustained for 1 hour. Follow your oncology team's instructions immediately, and do not wait an hour if you feel unwell; broad assessment is needed, not testing for Listeria alone.
Kantesti AI can explain an absolute neutrophil count such as 0.4 × 10⁹/L, but it cannot determine the cause of accompanying fever or whether immune function is otherwise adequate. Our guide to آزمایش عفونت های مکرر separates blood-cell counts from wider immune assessment.
کدام علائم هشدار نیازمند مراقبت اورژانسی در حال حاضر هستند؟
Confusion, seizures, stiff neck with fever, severe headache with altered awareness, breathing difficulty, or rapid deterioration require emergency assessment. These signs can indicate meningitis, sepsis, or another serious condition; you do not need a temperature above 38.1°C or a confirmed food exposure before seeking help.
Listeria meningitis may cause headache, neck stiffness, confusion, loss of balance, or seizures, but not everyone develops the full pattern. A hypothetical 72-year-old with fever and new difficulty walking needs urgent assessment even without neck stiffness; waiting for all the classic symptoms can delay appropriate treatment.
Sepsis can present with very low blood pressure, reduced urine output, mottled appearance, or unusual drowsiness, sometimes without a high fever. A lactate above 2 mmol/L can add concern in the appropriate setting, but our lactate result interpretation explains why sampling conditions and noninfectious causes also matter.
A baby younger than 3 months with a temperature of 38.0°C or higher needs urgent medical assessment, whether or not Listeria is suspected. Poor feeding, abnormal sleepiness, breathing changes, or a low temperature can also signal serious neonatal illness; maternal exposure history should be shared but must not delay care.
Hospital teams may check platelets, clotting, kidney function, and lactate when systemic illness is severe; none identifies Listeria on its own. Our sepsis-related clotting patterns explain one complication, but do not wait for even 1 abnormal laboratory result when emergency symptoms are present.
آیا صرفاً قرار گرفتن در معرض غذای فراخوانشده نیازمند آزمایش است؟
Eating food recalled for Listeria generally does not require testing or preventive antibiotics when you remain well, including during pregnancy. The CDC exposure-management framework and ACOG guidance instead support symptom awareness, with reassessment if compatible illness develops within the next 2 months.

A recall identifies a potentially contaminated product; it does not establish that every package contained Listeria or that every person who ate it became infected. Three separate questions matter: whether your product matches the recall, whether you actually ate it, and whether you have developed compatible symptoms.
There is no validated blood-test schedule at 24 hours, 7 days, or 2 weeks that reliably screens a well person after exposure. Blood cultures sample what is happening in the bloodstream at collection, so a negative culture obtained without illness would not guarantee that invasive disease cannot develop later.
Save the product name, batch details, exposure date, and recall notice before discarding the food as instructed; these are more useful than repeated routine panels. Our راهنمای زمانبندی آزمایش خون explains why results from different dates cannot be treated as interchangeable snapshots.
A hypothetical pregnant person who ate recalled food 3 days ago but feels entirely well usually does not need antibiotics or cultures solely for that event. New fever, aches, diarrhea, or obstetric symptoms changes the decision; if you already had symptoms that resolved, describe that history rather than classify yourself as never symptomatic.
لیستریا چگونه تشخیص داده میشود و چه زمانی کشت خون مناسب است؟
Invasive listeriosis is diagnosed by identifying Listeria monocytogenes from a normally sterile site, commonly blood or cerebrospinal fluid. Blood cultures are appropriate when compatible systemic illness raises suspicion, especially in pregnancy, older age, or immune suppression—not simply because a recalled food was eaten.

Blood cultures are generally collected before antibiotics when this can be done without delaying urgent treatment; hospitals commonly collect 2 sets for adult bloodstream-infection assessment. Appropriate sample volume and aseptic collection improve usefulness, but pregnancy, children, and difficult access may require an adapted collection plan.
Suspected meningitis may require lumbar puncture for cerebrospinal fluid culture and other tests, provided the procedure is clinically safe. A 1-time negative blood culture does not exclude central nervous system disease, particularly after antibiotics; the team must interpret the specimen source, collection timing, and clinical presentation together.
Standard meningitis molecular panels can include Listeria, whereas other panels do not; a negative result only addresses the organisms and specimen covered by that assay. Our typhoid culture and timing guide discusses a parallel problem: nonspecific blood findings and antibody screens are not substitutes for suitable microbiology.
ACOG's exposed-pregnancy pathway recommends blood cultures when fever above 38.1°C accompanies compatible illness without another cause (ACOG, 2014). A culture that identifies Listeria needs prompt clinician review and treatment planning; incubation and organism identification take time, so the initial decision may need to precede confirmation.
اگر علائم خفیف دارید اما تب ندارید، چه باید کرد؟
Mild, afebrile symptoms after implicated exposure need individualized assessment in high-risk people, but do not automatically require antibiotics. CDC's framework allows observation or blood cultures in selected higher-risk patients; worsening symptoms or a new temperature of 38.0°C or higher should trigger prompt reassessment.
An exposed pregnant person with mild nausea or diarrhea but no fever should contact maternity care for advice rather than assume either infection or complete safety. The evidence for treating this afebrile group is limited; clinicians may reasonably choose different approaches after considering 2 factors—exposure credibility and the symptom pattern.
Ordinary stool cultures and common gastrointestinal PCR panels are not reliable screening tools for invasive listeriosis; many do not test for Listeria at all. A stool result naming another pathogen can explain diarrhea, but it does not necessarily explain persistent systemic symptoms in a high-risk person 1 week later.
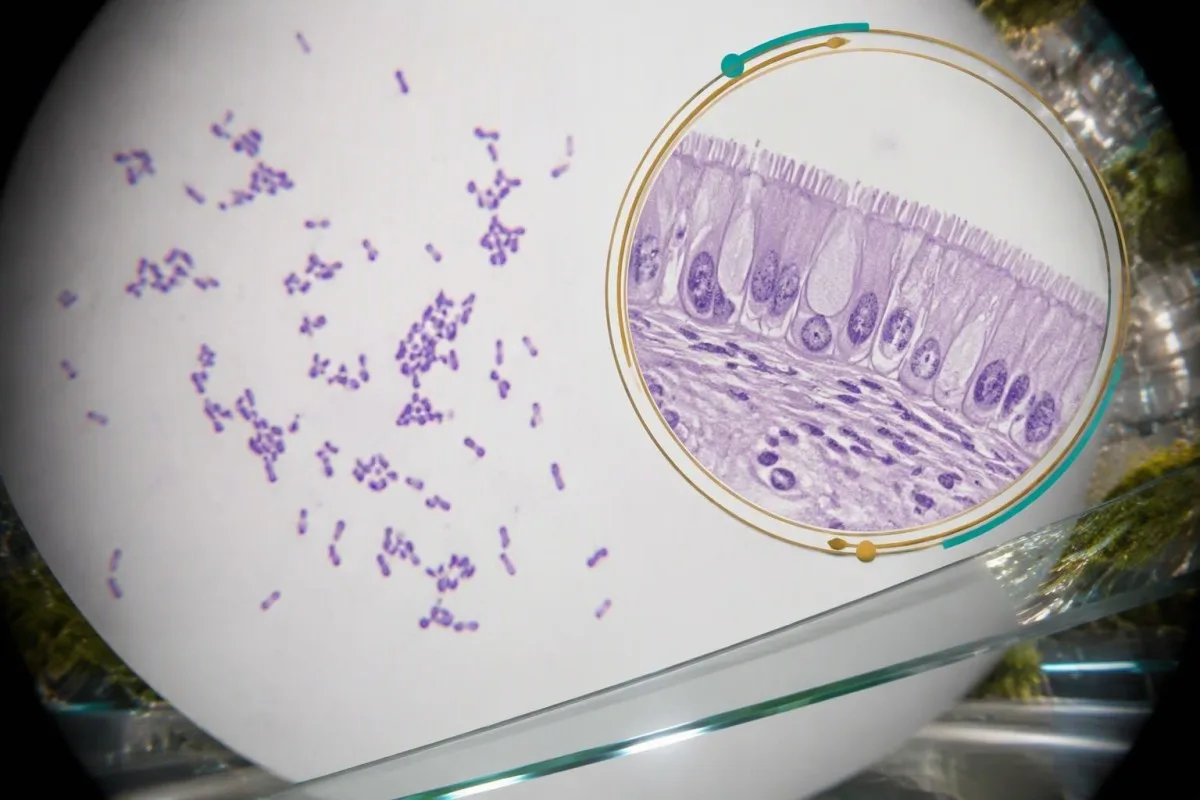
A positive stool finding also does not automatically establish invasive disease, because intestinal carriage and systemic infection are different questions. Our guide to Campylobacter stool PCR results explains why detecting an organism, deciding whether it caused illness, and choosing treatment are 3 separate steps.
A hypothetical transplant recipient with 2 days of mild diarrhea, no fever, and a clear recall match may be advised to have cultures or closer observation. Persistent diarrhea also raises medication effects, dehydration, and other pathogens; seek earlier advice if drinking becomes difficult or urine output falls.
لیستریوز تهاجمی چگونه درمان میشود؟
Invasive listeriosis usually requires hospital-directed antibiotics, most often intravenous ampicillin or another appropriate Listeria-active regimen. Treatment depends on the infection site, pregnancy, kidney function, and allergy history; uncomplicated bloodstream infection often needs at least about 14 days, while meningitis usually requires a longer course.

Listeria is not reliably treated by cephalosporins, so ceftriaxone alone is inadequate when Listeria meningitis is a concern. Empirical meningitis regimens add appropriate Listeria coverage for relevant risk groups; antibiotic choice should not be inferred from a generic 'bacterial infection' label or a single CRP result.
A typical adult meningitis regimen may use ampicillin 2 g intravenously every 4 hours when kidney function permits, but doses require clinician adjustment. This is not a home-treatment instruction: the site of illness, body size, renal function, and complications determine both dosing and how long treatment continues.
Gentamicin is sometimes added, although the benefit of combination treatment is uncertain and practice varies; kidney and hearing toxicity matter. Our gentamicin level monitoring explains why a trough above the local target can require intervention rather than simply completing the original dosing schedule.
A serious penicillin allergy can change treatment, with trimethoprim-sulfamethoxazole among possible alternatives under specialist supervision; pregnancy adds further considerations. Tell the team whether the reaction involved hives, breathing problems, or a delayed rash, even if it occurred 20 years ago; our ارزیابی مجدد حساسیت به پنیسیلین explains why the details matter.
آیا CBC، CRP یا پروکلسیتونین میتوانند لیستریا را رد کنند؟
A CBC, CRP, or procalcitonin result cannot confirm or exclude listeriosis. These tests help assess inflammation, immune-cell patterns, and illness severity, but a normal white-cell count or CRP below 5 mg/L must not override concerning symptoms in pregnancy or immune suppression.

Many adult laboratories use a white-cell reference interval near 4.0–11.0 × 10⁹/L, but local ranges, pregnancy, and medicines alter interpretation. A value inside that interval does not demonstrate the absence of bacteremia; our مقایسه WBC و CRP ما explains why these markers can disagree during evolving illness.
A hypothetical pregnant person with WBC 10.8 × 10⁹/L, CRP 4 mg/L, fever of 38.3°C, and a credible exposure still needs clinical assessment. CRP can lag behind symptom onset, while pregnancy itself can raise white-cell counts; neither direction supplies a Listeria-specific answer.
Procalcitonin below 0.1 ng/mL is often considered low, depending on the assay, but there is no validated low cutoff that safely excludes invasive listeriosis. Our procalcitonin thresholds and trends explain why early infection, localized disease, and clinical context limit standalone reassurance.
کانتستی یک پلتفرم تفسیر آزمایش خون AI that can explain patterns such as CRP 45 mg/L alongside creatinine and CBC findings, without identifying the responsible bacterium. Our technical and clinical safeguards distinguish interpretation support from microbiological diagnosis; antibiotics and cultures must follow clinical assessment.
گزارش اولیه یا منفی کشت به چه معناست؟
A preliminary culture report describes an incomplete laboratory process, while a negative result only reflects the samples and conditions tested. 'No growth at 24 hours' is not the same as a final negative report; previous antibiotics and inadequate collection can reduce the chance of detecting Listeria.

A report of 'Gram-positive rods' means the laboratory has described bacterial shape and staining, not confirmed Listeria species. Some organisms with this appearance may represent contamination, but clinicians must not dismiss the finding automatically in a pregnant or immunocompromised person with fever of 38.2°C.
Many laboratories finalize routine negative blood cultures after approximately 5 days, although systems and special protocols vary. The exact wording matters: 'pending,' 'no growth to date,' and 'final no growth' describe different stages, and an organism detected early still needs identification and susceptibility work where appropriate.
A hypothetical patient whose cultures were collected 2 hours after the first antibiotic dose may have a negative result despite genuine bacterial illness. Persistent neurological symptoms, ongoing fever, or obstetric concerns may therefore justify further investigation; repeat cultures should answer a clinical question rather than follow an automatic calendar.
Kantesti can help explain report terminology, but it cannot turn 'no growth at 24 hours' into an exclusion of invasive listeriosis. Our فناوری تفسیر AI describes how report information is processed; incomplete source data remains incomplete, regardless of how clearly the explanation is written.
چه پیگیریها و احتیاطهای غذایی مفید هستند؟
After assessment, follow-up should track symptoms and the clinician's plan—not rely on repeated screening while well. After implicated food exposure, remain alert for compatible illness for 2 months; during recovery from confirmed listeriosis, recurrent fever, new neurological symptoms, or obstetric changes need prompt reassessment.

Listeria can grow at refrigerator temperatures, so refrigeration does not make a recalled ready-to-eat product safe. Keep the refrigerator at 4°C or colder, follow storage limits, and clean surfaces that contacted the implicated food; discarding only the visibly spoiled part is not an adequate response.
Higher-risk people should choose pasteurized dairy products and follow local advice about chilled ready-to-eat foods; some chilled foods require reheating rather than simply confirming pasteurization. Where reheating is recommended, reaching 74°C or steaming hot throughout reduces risk, but recalled products should be discarded according to recall instructions rather than salvaged.
A hypothetical person discharged after invasive illness may have improving symptoms while CRP remains above 5 mg/L; conversely, new fever matters even if a previous result was falling. Our laboratory changes after hospital discharge explains why symptoms, sample dates, and treatment timing should be reviewed together.
کانتستی یک سرویس تفسیر آزمایشهای آزمایشگاه AI منتشر میشوند that can organize existing results from 2 or more dates, but recovery decisions remain with your treating team. Before sharing reports, review our راهنمای حریم خصوصی و دادهها; result uploads should never delay reporting recurrent fever or new neurological symptoms.
پژوهش، محدودیتهای شواهد و فهرست بررسی مراقبت شما
Listeria decisions depend on clinical presentation, risk group, and suitable microbiology—not an exposure history or inflammation marker alone. Prepare 4 details for your consultation: food and recall information, exposure dates, symptom and temperature history, and pregnancy or immune-suppression status.
Goulet et al. (2013) provide useful incubation estimates, but their 37 invasive cases with defined exposures cannot predict an individual's exact symptom-onset date. ACOG's 2014 pregnancy guidance offers a practical exposure-management pathway; its fever threshold supports clinical decisions rather than proving that lower temperatures are harmless.
The MONALISA prospective cohort describes the clinical features and prognostic factors of invasive listeriosis (Charlier et al., 2017), not the likelihood of infection after 1 serving of recalled food. Hospitalized, confirmed cases are a selected population, so their outcomes should not be presented as the risk faced by every exposed, well person.
The 2 DOI-linked laboratory-education publications below concern other diagnostic topics and are not evidence for Listeria incubation, pregnancy management, or antibiotic selection. A DOI identifies a publication record; it does not by itself establish peer review, clinical validity, or relevance to the decision you need to make.
Our Kantesti medical content team separates clinical evidence from interpretation support under our استانداردهای محتوای پزشکی. Before ending a consultation, ask 3 questions: which results are pending, who will review them, and which symptoms mean you should seek help before the planned follow-up.
سوالات متداول
نخستین علائم لیستریا چیست؟
نخستین علائم لیستریا ممکن است اسهال و استفراغی باشد که ظرف ۲۴ ساعت آغاز میشود، یا تب، درد بدن و خستگی که چند روز تا چند هفته بعد در بیماری تهاجمی ظاهر میشوند. بیماری رودهای معمولاً ۱ تا ۳ روز طول میکشد، اما لیستریوز تهاجمی میتواند بدون اسهال رخ دهد. بارداری، سن ۶۵ سال یا بیشتر و ضعف سیستم ایمنی، نگرانی درباره علائم سیستمیک را افزایش میدهند. گیجی، تشنج یا سفتی گردن همراه با تب، نیازمند ارزیابی اورژانسی است.
علائم لیستریا در دوران بارداری چیست؟
علائم لیستریا در بارداری اغلب شامل تب، دردهای عضلانی و خستگی غیرمعمول است و گاهی با اسهال یا بدون علائم گوارشی بارز همراه میشود. دمای 38.0°C یا بالاتر همراه با بیماری سازگار با لیستریا باید موجب دریافت راهنمایی از مرکز مراقبت بارداری شود، بهویژه پس از مصرف غذای مشکوک. دستورالعمل ACOG تب بالاتر از 38.1°C همراه با علائم سازگار و بدون علت دیگر را در زنان بارداری که در معرض آلودگی قرار گرفتهاند، محرکی برای آزمایش و درمان میداند. کاهش حرکات جنین، انقباضات یا نشت مایع، صرفنظر از دمای بدن، نیازمند ارزیابی فوری مامایی است.
علائم لیستریوز چه مدت پس از خوردن غذای آلوده ظاهر میشوند؟
علائم رودهای لیستریا اغلب ظرف 24 ساعت آغاز میشوند، در حالی که علائم تهاجمی معمولاً ظرف 2 هفته شروع میشوند، اما ممکن است دیرتر ظاهر شوند. یک مطالعه کوچک درباره دوره نهفتگی، میانههای 2 روز برای باکتریمی، 9 روز برای بیماری دستگاه عصبی مرکزی و 27.5 روز برای بیماری مرتبط با بارداری را گزارش کرد. این ارقام گروههای منتخب را توصیف میکنند و شمارش معکوس دقیقی برای یک فرد ارائه نمیدهند. توصیههای مربوط به مواجهه معمولاً گوشبهزنگماندن برای علائم سازگار را به مدت 2 ماه پیشنهاد میکنند.
آیا پس از خوردن غذای فراخوانشده باید برای لیستریا آزمایش بدهم؟
در صورت مواجهه با غذای فراخوانشده، اگر حالتان خوب است، معمولاً انجام آزمایش و مصرف آنتیبیوتیک پیشگیرانه توصیه نمیشود؛ این موضوع در دوران بارداری نیز صدق میکند. طی ۲ ماه آینده مراقب بروز علائم سازگار باشید و اطلاعات مربوط به محصول و مواجهه را نگه دارید. تب جدید، بدندرد، اسهال یا علائم مامایی میتوانند ارزیابی را تغییر دهند، بهویژه در فردی که در معرض خطر بیشتری است. هیچ برنامه آزمایش خون معمولِ تأییدشدهای در ۲۴ ساعت یا ۷ روز وجود ندارد که تضمین کند بعداً به لیستریوز مبتلا نخواهید شد.
لیستریا چگونه تشخیص داده میشود؟
لیستریوز تهاجمی با شناسایی Listeria monocytogenes از یک محل که در حالت طبیعی استریل است، مانند خون یا مایع مغزینخاعی، تشخیص داده میشود. پزشکان معمولاً در بزرگسالان با عفونت مشکوک جریان خون، با توجه به شرایط بالینی، ۲ مجموعه کشت خون میگیرند. CBC، CRP، آزمایشهای آنتیبادی و پنلهای معمول مدفوع نمیتوانند لیستریوز تهاجمی را بهطور قابلاعتماد تأیید یا رد کنند. در صورت امکان، نمونههای کشت باید پیش از آنتیبیوتیکها گرفته شوند، بیآنکه درمان فوری به تأخیر بیفتد.
آیا آزمایشهای معمول خون میتوانند ابتلا به لیستریا را رد کنند؟
آزمایشهای معمول خون نمیتوانند لیستریوز را رد کنند. شمارش گلبولهای سفید در محدوده معمول بزرگسالان، یعنی ۴٫۰ تا ۱۱٫۰ × ۱۰⁹/L، یا CRP کمتر از ۵ mg/L ممکن است با وجود بیماریای که از نظر بالینی نگرانکننده است، مشاهده شود. بارداری، داروهای سرکوبکننده ایمنی و نمونهگیری زودهنگام میتوانند تفسیر این نتایج را بهویژه دشوار کنند. علائم سازگار و عوامل خطر تعیین میکنند که آیا معاینه، کشت یا درمان فوری لازم است.
آیا لیستریا بدون آنتیبیوتیک از بین میرود؟
لیستریوز رودهای خفیف در فردی که از سایر جهات سالم است، اغلب طی ۱–۳ روز و بدون آنتیبیوتیک برطرف میشود. لیستریوز تهاجمی به درمان آنتیبیوتیکی تحت نظر پزشک و اغلب مراقبت بیمارستانی نیاز دارد. بارداری، ضعف سیستم ایمنی، تب مداوم یا تغییرات عصبی باعث میشوند خودمراقبتی ایمن نباشد، حتی اگر اسهال خفیف به نظر برسد. دمای ۳۸٫۰°C یا بالاتر در فردی با خطر بیشتر، نیازمند دریافت سریع توصیه پزشکی است و نباید منتظر گذشت دوره بهبودی رودهای ماند.
چگونه نتایج آزمایش خون را بخوانیم
گزارش آزمایشگاهی خود را بارگذاری کنید تا هوش مصنوعی Kantesti ظرف چند ثانیه هر زیستنشانگر را به زبان ساده توضیح دهد. بیش از 2 میلیون نفر در سراسر جهان از آن استفاده کردهاند.
منابع
- Klein, T., Mitchell, S., & Weber, H. (2026). آزمایش خون ویروس نیپا: راهنمای تشخیص و شناسایی زودهنگام ۲۰۲۶. پژوهش پزشکی هوش مصنوعی Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). راهنمای گروه خونی B منفی، آزمایش خون LDH و شمارش رتیکولوسیت. پژوهش پزشکی هوش مصنوعی Kantesti. DOI
- American College of Obstetricians and Gynecologists (2014). Committee Opinion No. 614: Management of Pregnant Women With Presumptive Exposure to Listeria monocytogenes. Obstetrics & Gynecology.
- Goulet V et al. (2013). What is the incubation period for listeriosis? BMC Infectious Diseases. DOI
- Charlier C et al. (2017). Clinical features and prognostic factors of listeriosis: the MONALISA national prospective cohort study. The Lancet Infectious Diseases. DOI
- ۲ میلیون+آزمایشهای تجزیهوتحلیلشده
- 127+کشورها
- 100+زبانها
درباره تیم پزشکی


سیگنالهای اعتماد E-E-A-T
تجربه
بازبینی بالینی مبتنی بر نظر پزشک از فرایندهای تفسیر آزمایشگاه.
تخصص
تمرکز بر پزشکی آزمایشگاهی و اینکه نشانگرهای زیستی در زمینه بالینی چگونه رفتار میکنند.
اقتدارگرایی
با بازبینی پزشکی دکتر توماس کلاین، با مشارکت دکتر سارا میچل و پروفسور دکتر هانس وبر.
قابل اعتماد بودن
تفسیر مبتنی بر شواهد با مسیرهای پیگیری روشن برای کاهش هشدارها.






سلب مسئولیت پزشکی
این مقاله فقط برای اهداف آموزشی است و توصیه پزشکی محسوب نمیشود. برای تصمیمهای مربوط به تشخیص و درمان، همیشه با یک ارائهدهنده مراقبتهای بهداشتی واجد شرایط مشورت کنید.
منتشر شد · با تیم تحریریه تماس بگیرید
منتشرشده توسط Kantesti Ltd، ثبتشده در انگلستان و ولز، شماره شرکت. 17090423, ، لندن، بریتانیا.
