A pozitív széklet-PCR-eredmény nem jelenti automatikusan azt, hogy gyógyszerre van szüksége. A kezelésről szóló döntés a tartós tünetektől, az alternatív magyarázatoktól, valamint a kórokozó kiirtása és a közérzet javulása közötti bizonytalan összefüggéstől függ.

Főbb tanulságok
- Pozitív PCR Dientamoeba fragilis genetikai anyagát mutatja ki; 1 pozitív eredmény nem bizonyítja, hogy a kórokozó okozta az emésztőrendszeri tüneteket.
- Nincsenek tünetek általában azt jelenti, hogy nincs szükség kezelésre, még akkor sem, ha a székletvizsgálat Dientamoeba fragilis jelenlétét mutatja ki.
- Tartós hasmenés A 14 napja vagy annál hosszabb ideje fennálló panaszok újraértékelést igényelnek, de az időtartam önmagában nem bizonyítja, hogy a Dientamoeba fragilis a felelős.
- A kezeléssel kapcsolatos bizonyítékok között szerepel egy 96 gyermeket bevonó randomizált vizsgálat, amelyben a metronidazol klinikai eredményei nem voltak jobbak a placebóénál.
- Paromomicin orvos által választott lehetőség; a CDC felnőttekre vonatkozó útmutatója napi 25–35 mg/kg-os adagot sorol fel, 3 részletben, 7 napon át.
- Kalprotektin az 50 µg/g alatti érték gyakori felnőtt laboratóriumi referenciaérték, nem olyan vizsgálati küszöb, amely megerősíti vagy kizárja a tüneteket okozó Dientamoeba fragilis-fertőzést.
- Figyelmeztető jelek mint például a véres széklet, az erős hasi fájdalom, a kiszáradás vagy a nem szándékos fogyás, a pozitív PCR-en túlmutató kivizsgálást tesznek szükségessé.
- Utánkövetés a tüneteket és a vizsgálati eredményeket egyaránt értékelnie kell; a kórokozó eltűnése és a tünetek megszűnése két különböző kimenetel.
Kezelni kell a Dientamoeba fragilis pozitív eredményét?
A Dientamoeba fragilis pozitív széklet-PCR-eredmény nem teszi automatikusan szükségessé a kezelést. A tünetmentes embereknek általában nincs szükségük gyógyszerre; az orvosok mérlegelhetik a kezelést, ha az emésztőrendszeri tünetek tartósan fennállnak, a kórokozó szerepe valószínűsíthető, és az egyéb lehetséges magyarázatokat is megvizsgálták.
A kimutatás és az okozati szerep két külön kérdés. A székletvizsgálati panel pontosan azonosíthat egy kórokozót anélkül, hogy megállapítaná, miért van valakinek hasi fájdalma vagy hasmenése, ezért egy pozitív eredmény értelmezendő lelet, nem pedig a kezelés megkezdését kiváltó ok; a kórokozó lehet véletlen lelet, közrejátszhat a tünetekben, vagy nem függhet össze a jelenlegi betegséggel.
A A CDC klinikai ellátásra vonatkozó útmutatója szerint a tünetmentes Dientamoeba fragilis-kimutatás általában nem igényel kezelést, és a gyógyszeres kezelés egyes tünetes embereknél segíthet, ha ez az egyetlen kimutatott kórokozó (CDC, 2024). Ha csak egy kórokozót találnak, az valószínűbbé teszi, hogy ez magyarázza a tüneteket, de nem zárja ki a cöliákiát, a gyógyszerek mellékhatásait vagy a funkcionális bélbetegséget.
Például képzeljünk el egy felnőttet, akinek egy háztartásban terjedő gyomor-bélhurut után 2 napja laza a széklete, és a vizsgálati panel Dientamoeba fragilist mutat ki. Ha a tünetek már enyhülnek, és a folyadékbevitel megfelelő, ésszerűbb lehet a megfigyelés, mint azonnal olyan antimikrobiális szert adni, amely maga is hányingert vagy hasmenést okozhat.
Az Kantesti egy AI-vérvizsgálat-elemző, amely magyarázatot adhat a kísérő laboratóriumi leletekre, de széklet-PCR alapján nem tudja megállapítani, hogy ez a kórokozó okozta-e a tüneteit. Ezt a korlátot a szervezetünkre vonatkozó tájékoztatónkban; ismertetjük; a klinikai döntés több tényezőtől függ, nem csupán egy laboratóriumi eredménytől.
Mit mutat ki valójában a Dientamoeba fragilis székletvizsgálat?
A Dientamoeba fragilis széklet-PCR a beküldött mintában található kórokozó genetikai anyagát mutatja ki. Nem állapítja meg közvetlenül, hogy a kórokozó életképes-e, okozott-e szövetkárosodást, vagy kiváltotta-e a tüneteket, és nincs olyan általánosan validált PCR-küszöbérték, amely meghatározná, szükséges-e a kezelés.
A Dientamoeba fragilis bélben élő egysejtű, nem féreg. A neve félrevezető lehet: az egysejtűeknek a trichomonasokkal rokon csoportjába tartozik, nem a közönséges amőbák közé, és mikroszkóp alatt a trofozoitákban gyakran 1 vagy 2 sejtmag látható; a név szereplése a leleten nem jelenti azt, hogy a szervezetben invazív fertőzés áll fenn.
A legtöbb klinikai leletben kimutatható/nem mutatható ki, szerepel, nem pedig klinikailag validált súlyossági skála. Ha a laboratórium ciklusküszöbértéket ad meg, az alacsonyabb érték általában több célanyag jelenlétére utal az adott vizsgálati módszerben, de a kivonás, a széklet állaga és az alkalmazott platformok közötti különbségek miatt egyetlen szám sem használható általános kezelési küszöbértékként; a mi kvalitatív és kvantitatív eredményekről szóló útmutatónk elmagyarázza a jelentésbeli különbséget.
PCR- és mikroszkópos vizsgálati eredményeink eltérhetnek egymástól anélkül, hogy bármelyik értelmetlen lenne. PCR is generally more sensitive, whereas microscopy depends on preservation, staining, and expertise; traditional parasite microscopy may require specimens collected on 3 separate days because organism shedding and visibility vary, while a validated molecular assay may use a single specimen.
Check the actual panel contents before assuming other infections were excluded. A negative result for 5 listed pathogens says nothing about an organism the panel never tested, and some gastrointestinal panels do not include Dientamoeba fragilis at all; ask whether your result came from a targeted assay or a broader panel.
Mikor valószínűbb, hogy a pozitív PCR véletlen hordozást jelez?
Incidental carriage is more likely when the person has no symptoms, symptoms have already resolved, or another explanation fits better. A repeated positive result can demonstrate ongoing detection, but 2 positive samples still do not establish that Dientamoeba fragilis is causing illness.
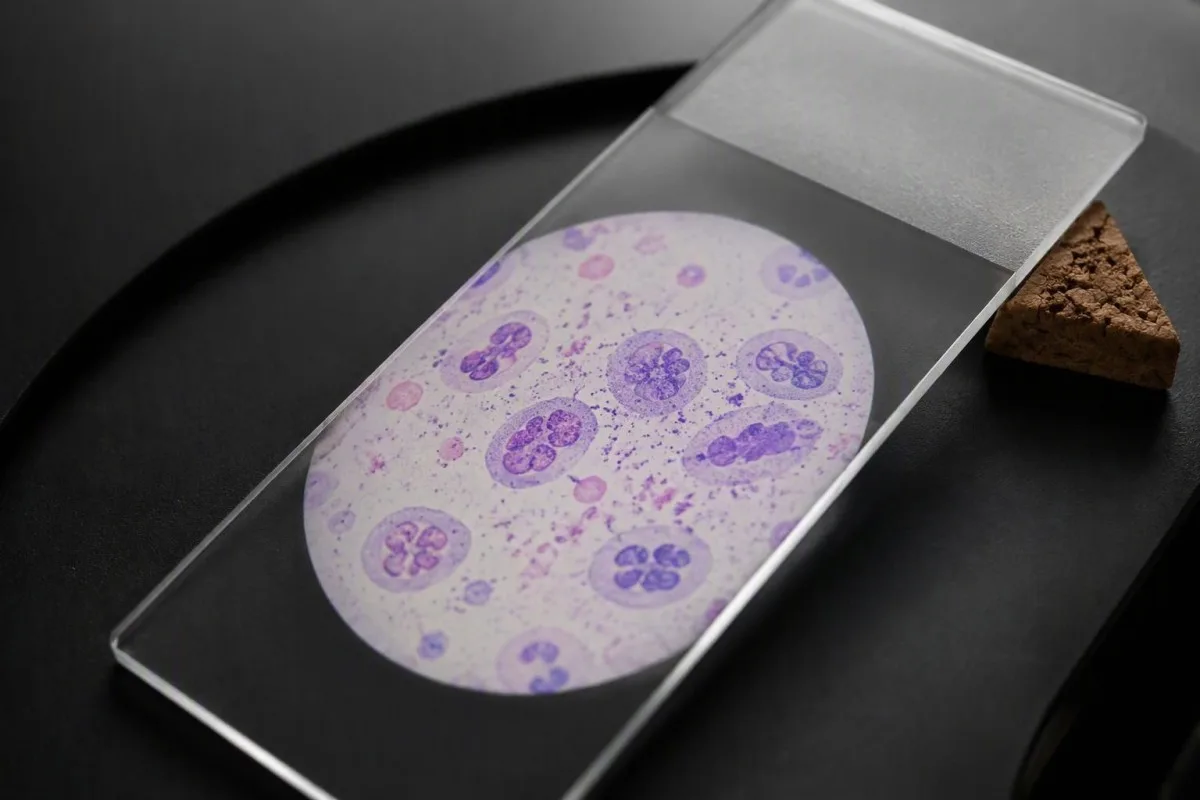
Asymptomatic detection is real, not automatically a laboratory error. Sensitive PCR testing finds organisms that older methods missed, including in people who feel well; because prevalence differs substantially between settings, age groups, and assays, a single percentage from 1 population should not be used to estimate your personal likelihood of illness.
A timing of symptoms can weaken an apparent association. A hypothetical person with 5 years of alternating constipation and diarrhea who receives a first positive stool PCR has not necessarily acquired a new explanation for those longstanding symptoms; the test cannot date acquisition or show whether the organism was present before symptoms started.
A positive commercial microbiome report is not equivalent to a clinical diagnosis. Relative abundance, proprietary risk scores, and organisms reported outside validated pathogen testing may not have established treatment implications; before acting on 1 highlighted finding, review our discussion of mikrobiomvizsgálatok korlátairól szóló ismertetőnk.
Egy asymptomatic household contact is not automatically a treatment candidate. Screening and treating every family member after 1 positive result can create avoidable medication exposure; contact testing is more reasonably discussed when several people have persistent compatible symptoms, or when a specialist or local public-health team identifies a specific reason.
Mely Dientamoeba fragilis okozta tünetek lehetnek relevánsak?
Reported Dientamoeba fragilis symptoms include loose stools, abdominal discomfort, bloating, and sometimes nausea or reduced appetite. None is specific to this organism, so clinicians assess the symptom pattern, duration, and functional impact rather than assuming that 1 positive PCR explains everything.
Stool consistency is often more useful than the word diarrhea. On the 7-category Bristol Stool Chart, types 6 and 7 describe mushy and watery stools; recording those types alongside frequency helps distinguish persistent loose stools from frequent but formed bowel movements, as explained in our székletállag-útmutatónk.
A 7-day symptom diary can clarify whether the illness is continuous or meal-related. Record bowel frequency, stool type, nighttime waking, abdominal discomfort, medicines, and missed activities; a pattern that repeatedly follows a particular food may suggest malabsorption or intolerance, although dietary associations alone do not diagnose either condition.
Stool color does not identify Dientamoeba fragilis. Yellow stools can accompany rapid transit, dietary changes, or fat malabsorption, and 1 unusual bowel movement is not a parasite-specific sign; our explanation of yellow stool causes helps separate color changes from more informative accompanying features.
For example, a hypothetical adult with 4 loose stools daily for 6 weeks, stable weight, and no other pathogen detected has a more plausible treatment discussion than someone whose brief illness has ended. Even then, the assessment should consider medication effects, celiac disease, and inflammatory or functional conditions before assigning causation.
Mely tüneteket nem szabad a Dientamoeba fragilisnek tulajdonítani?
Blood in stool, substantial dehydration, severe or localized abdominal pain, persistent fever, and unintentional weight loss need assessment beyond a positive Dientamoeba fragilis result. These findings can signal another condition, and clinicians should not allow 1 detected organism to delay appropriate investigation.
Seek urgent medical help for severe pain, collapse, confusion, or inability to keep fluids down. A temperature around 38°C or higher combined with significant illness deserves prompt advice, although age, immune status, and other symptoms matter more than a single cutoff; emergency symptoms should not wait for a repeat parasite test.
Látható red blood or black, tarry stool is not a typical finding to dismiss as uncomplicated dientamoebiasis. Iron tablets and some foods can change stool color, but 1 episode accompanied by dizziness, weakness, or significant pain warrants prompt assessment; our székletben észlelhető vérre vonatkozó figyelmeztető jeleink explain why appearance and accompanying symptoms matter.
Diarrhea that wakes someone from sleep and progressive weight loss broaden the differential diagnosis. Unintentional loss of more than 5% of body weight over 6–12 months is a commonly used clinical warning threshold, but smaller losses can still matter in children, frail adults, or someone losing weight rapidly.
Reduced urine output can indicate kiszáradás, especially when accompanied by thirst, dizziness, or dry mouth. Do not wait for a precise number of hours if the person appears unwell; infants, older adults, pregnant people, and those with kidney disease need a lower threshold for clinical advice than a healthy adult with 1 mild loose stool.
Mi a teendő, ha a székletpanel egy másik kórokozót is kimutat?
When another pathogen is detected, clinicians compare its established disease pattern with the symptoms before prioritizing Dientamoeba fragilis treatment. A panel with 2 positive targets may reflect coinfection, persistent shedding, or incidental carriage; it does not automatically justify treating both organisms.
Giardia has a better-established relationship with persistent diarrhea and malabsorption than Dientamoeba fragilis. If both are detected in a hypothetical person with 3 weeks of loose, greasy stools after untreated-water exposure, a clinician may prioritize Giardia-directed care; our Giardia treatment and recovery guide explains the different evidence base.
Campylobacter detection does not automatically require antibiotics either, despite its established role in gastroenteritis. Severity, illness duration, and vulnerability determine the decision, so 2 detected organisms still require 2 separate clinical judgments; compare our discussion of Campylobacter antibiotic decisions rather than assuming all stool positives follow one rule.
Legutóbbi antibiotic exposure changes the assessment because it raises concern for antibiotic-associated diarrhea and C. difficile. A positive screening assay with a negative toxin result creates another detection-versus-disease problem, particularly when someone does not have at least 3 unformed stools in 24 hours; our diszkordáns C. difficile-eredményekről guide describes that distinction.
A negative panel is not a complete gastrointestinal evaluation. Even a panel covering 20 organisms cannot identify bile acid diarrhea, microscopic colitis, celiac disease, or every travel-related infection; the test menu, exposure history, and symptom duration determine whether additional microbiology or a noninfectious workup makes more sense.
A Dientamoeba fragilis kezelése megbízhatóan enyhíti a tüneteket?
Dientamoeba fragilis treatment does not reliably produce symptom improvement, and the evidence is mixed. A randomized, placebo-controlled trial involving 96 children found that metronidazole did not improve clinical outcomes more than placebo, even though treatment initially increased organism eradication.
Röser et al. reported the trial in Clinical Infectious Diseases in 2014. Children aged 3–12 years received a 10-day course of metronidazole or placebo, and the study did not establish a clinical benefit from metronidazole; that result argues against routine treatment of every symptomatic child with a positive test.
The trial does not prove that all treatments are ineffective in every patient. It evaluated 1 medication in a particular pediatric population, so its findings cannot automatically be extended to paromomycin, every adult presentation, or unusual clinical circumstances; uncertainty should narrow claims rather than be converted into either universal treatment or universal dismissal.
Before-and-after improvement is weaker evidence than a randomized comparison. Over a 2-week period, symptoms may improve naturally, fluctuate, or respond to changes in diet and other medicines; an uncontrolled report of feeling better after treatment cannot reliably separate those explanations from a specific effect on Dientamoeba fragilis.
At Kantesti, we distinguish organism eradication, symptom recovery, and study design as 3 separate issues when explaining this uncertainty. Our digestive symptom research guide provides broader context, but it is not direct evidence that antimicrobial treatment improves outcomes in Dientamoeba-positive patients.
Milyen gyógyszereket alkalmazhatnak az orvosok, és mik a korlátaik?
Clinicians may use paromomycin or metronidazole for selected symptomatic patients, but medication choice does not resolve uncertainty about causation. CDC adult guidance lists paromomycin at 25–35 mg/kg/day in 3 divided doses for 7 days; this is prescribing information, not an instruction to self-treat.
Paromomycin mainly acts within the intestinal lumen. A retrospective adult study by van Hellemond et al. in 2012 found better eradication with paromomycin than some alternatives, but the nonrandomized design cannot establish superior symptom relief; its findings support a medication discussion, not a guaranteed cure for abdominal discomfort.
A CDC adult metronidazole regimen is 500–750 mg orally 3 times daily for 10 days (CDC, 2024). Nausea, altered taste, medication interactions, and occasional neurologic adverse effects matter; pediatric dosing differs, and pregnancy, breastfeeding, liver disease, or other medical conditions require a prescriber to assess the specific choice.
Medication reconciliation should happen before prescribing. Metronidazole can increase warfarin's anticoagulant effect, so a person taking warfarin may need an individualized INR monitoring plan rather than merely a routine 10-day prescription; our guide to antibiotikumok és INR változások explains the mechanism and monitoring considerations.
A penicillin allergy label does not automatically prohibit either of these medicines because they are not penicillins. However, any previous reaction to the proposed drug itself needs review, and 1 vague historical allergy label should not substitute for a full medication history; our allergy label reassessment guide explains that separate issue.
Mikor vizsgálják ki az orvosok a tünetek más okait, mielőtt gyógyszert írnak fel?
Clinicians often investigate other causes before prescribing when symptoms are longstanding, atypical, associated with warning signs, or poorly explained by the stool result. Diarrhea lasting 4 weeks or longer is commonly classified as chronic, making a structured noninfectious assessment particularly useful.
Medication effects are a high-yield starting point. Metformin, magnesium-containing products, laxatives, and some antibiotics can cause loose stools; if a hypothetical person develops diarrhea 1 week after a dose increase, that timeline may be more informative than incidental parasite detection, although prescribed medicines should not be stopped without advice.
A fecal calprotectin below 50 µg/g is a common adult laboratory reference threshold, while values above roughly 250 µg/g may strengthen concern for intestinal inflammation in an appropriate clinical pathway. These are not universal diagnostic boundaries: age, infection, NSAID use, and laboratory methods affect interpretation, as discussed in our borderline calprotectin follow-up alapján.
Celiac screening commonly combines tissue transglutaminase IgA with total IgA. Reducing gluten before testing can make results falsely reassuring, and IgA deficiency changes which antibody tests are appropriate; if gluten has already been removed for several weeks, our gluten challenge planning guide explains why clinicians individualize the next step.
A normal initial workup does not make every alternative disappear. In someone with 6 months of watery diarrhea, clinicians may consider bile acid diarrhea or microscopic colitis; the latter can require colon examination with tissue sampling even when the bowel looks normal, while an IBS diagnosis depends on a compatible pattern and appropriate exclusion of warning features.
A vérvizsgálatok kimutathatják, hogy a Dientamoeba fragilis okozza-e a betegséget?
Routine blood tests cannot establish that Dientamoeba fragilis caused digestive symptoms. They can identify consequences or competing explanations, such as dehydration, anemia, inflammation, or nutrient deficiency; no validated CBC, CRP, or eosinophil cutoff confirms symptomatic disease from this organism.
CBC and ferritin can reveal an alternative reason for fatigue. In otherwise healthy adults, ferritin below 15 µg/L strongly supports depleted iron stores, although inflammation can raise ferritin and obscure deficiency; fatigue with low iron should not automatically be attributed to 1 stool finding, as our alacsony ferritin tüneti útmutatónk magyaráz.
For example, imagine an adult with ferritin 9 µg/L and hemoglobin 108 g/L alongside a positive stool PCR. Those hypothetical results warrant investigation of iron deficiency and its cause, not an assumption that treating the protozoan will correct the anemia; our vasanyagcsere-vizsgálatok értelmezési útmutatóinkat shows why multiple markers matter.
Eosinophilia is not a reliable marker of Dientamoeba fragilis disease. An eosinophil count above 0.5 × 10^9/L is commonly considered elevated, but allergies, medicines, and some helminth infections are more typical explanations; a positive Dientamoeba test should not stop clinicians from investigating substantial or persistent eosinophilia separately.
Kantesti is an AI blood test interpretation platform that explains CBC, ferritin, CRP, and kidney-function results without treating them as proof of parasite causation. A CRP of 3 mg/L may fall within a laboratory's standard reference interval, yet normal inflammatory markers do not exclude celiac disease, microscopic colitis, or other explanations for persistent diarrhea.
Miben különböznek a kezelési döntések gyermekek és veszélyeztetett felnőttek esetében?
Children, pregnant people, frail adults, and immunocompromised patients need individualized assessment rather than an automatic response to positive PCR. In children, growth, hydration, and symptom severity matter especially; the randomized metronidazole trial in 96 children supports caution about routine prescribing.
Growth faltering should prompt a broader pediatric evaluation. A hypothetical child with 6 weeks of loose stools and a falling growth trajectory needs assessment of intake, celiac disease, inflammation, and other causes; Dientamoeba fragilis detection may be relevant, but it should not become the only explanation considered.
Children can become dehydrated more quickly than healthy adults, particularly when vomiting accompanies diarrhea. Oral rehydration solution prepared exactly as directed is preferable to guessing electrolyte amounts, and 1 clearly unwell child with reduced urine, unusual drowsiness, or inability to drink needs prompt advice rather than waiting for a medication trial.
Pregnancy changes medication selection, not the meaning of PCR. A positive result still does not establish causation, while gestational stage, symptom burden, and drug-specific safety information influence prescribing; a person who is 10 weeks pregnant should discuss treatment with the maternity or prescribing team rather than using another household member's medication.
Immunosuppression lowers the threshold for evaluating other opportunistic causes, but it does not make this organism automatically responsible. Kantesti AI does not replace pediatric or specialist assessment; our discussion of gyermekek mesterséges intelligencia általi értelmezése explains why adult reference ranges and 1 abnormal result can be misleading.
Meg kell ismételni a székletvizsgálatot a kezelés után?
Repeat testing is not automatically necessary after symptoms resolve, and a test-of-cure plan should be agreed with the treating clinician. Persistent symptoms require reassessment; 1 repeat positive PCR does not by itself justify another course, and a negative result does not explain ongoing symptoms.
Testing immediately after treatment can be difficult to interpret. PCR detects genetic material rather than directly measuring living organisms, and there is no universal Dientamoeba-specific interval that makes every result definitive; instead of choosing an arbitrary day 3 test, ask what question the repeat test is intended to answer.
A positive repeat result may reflect persistence, reacquisition, or assay-related timing considerations. Those possibilities have different implications, so before prescribing course 2 a clinician should review adherence, the original symptom pattern, household exposures, and whether the first course changed anything that mattered to the patient.
A negative PCR with ongoing bloating shifts attention toward other explanations rather than proving treatment failure. Selected patients with risk factors may warrant a breath-test discussion, but bloating alone should not trigger indiscriminate SIBO testing; our breath test preparation guide explains why protocol and pretest probability matter.
Define success before treatment starts. For a hypothetical adult, improvement from 5 watery stools per day to 1–2 formed stools is a meaningful outcome, whereas an unchanged symptom diary with a negative PCR is laboratory clearance without demonstrated symptom benefit; documenting both prevents repeated medication from becoming the default response.
Milyen gyakorlati lépések segíthetnek a háztartás szükségtelen kezelésbe vonása nélkül?
Handwashing, careful bathroom hygiene, safe food handling, and clear follow-up records are reasonable steps after a positive result. The exact transmission routes of Dientamoeba fragilis remain incompletely resolved, so 1 positive household test does not justify promises that a particular cleaning routine will prevent recurrence.

Wash hands with soap and water after toilet use and before preparing food. Scrubbing for about 20 seconds is a standard general hygiene recommendation, not a Dientamoeba-specific eradication method; gloves do not replace handwashing, and bathrooms should be cleaned using ordinary product instructions rather than improvised chemical mixtures.
The proposed connection with pinworm transmission is not settled. Nighttime anal itching may justify a separate assessment, sometimes involving a morning tape test on 3 occasions, but a positive Dientamoeba PCR alone is not a reason to give everyone a deworming medicine or assume pinworms are present.
Kantesti is an AI-powered blood test analysis tool that can help explain accompanying laboratory results while stool-management decisions remain with the clinician. Keep the symptom diary, medicine list, and test dates together as 3 distinct records; our mintainterpretációs munkafolyamatokat describe educational workflows rather than evidence that our service treats intestinal parasites.
A shared household record should respect consent and minimize unnecessary identifiers. If 2 family members have symptoms, each person's clinical assessment and treatment decision remain separate; our adatvédelmi és adatkezelési gyakorlata explain how we approach information handling, but your clinician's secure communication channel should be used for prescribing and urgent advice.
Mit kérdezzen meg orvosától, és mely kutatások támasztják alá a döntést?
Ask whether Dientamoeba fragilis plausibly explains your symptoms, which alternatives need checking, and what benefit would justify treatment. The most useful evidence separates symptom outcomes from organism eradication; a 10-day treatment course and a negative follow-up test are not, by themselves, proof of clinical benefit.

Bring 4 items to the appointment: the full stool report, a medication list, a symptom timeline, and any relevant accompanying laboratory results. Ask what would change the decision—another pathogen, celiac antibodies, a concerning calprotectin result, or spontaneous improvement—and agree on when to return if symptoms persist or warning signs develop.
A 7-day diary can make observation an active plan rather than doing nothing. Maintain fluids and tolerated foods; oral rehydration solution can help replace diarrheal losses, but restrictive diets, herbal parasite cleanses, and supplements have no established role in eradicating Dientamoeba fragilis and should not delay investigation of persistent symptoms.
A 3 external sources below have different evidentiary roles: CDC provides clinical prescribing guidance, Röser et al. provide randomized pediatric symptom-outcome evidence, and van Hellemond et al. provide retrospective adult eradication data. Kantesti applies orvosi tartalmi szabványok that distinguish these study designs instead of presenting them as equally strong proof.
A 2 Figshare publications listed below are general educational resources, not trials of Dientamoeba fragilis treatment; the women's health guide does not provide direct evidence for this decision. A DOI establishes a persistent identifier, not clinical validation, and our technical and clinical methodology should likewise not be mistaken for proof that AI can establish the cause of digestive symptoms.
Gyakran feltett kérdések
A Dientamoeba fragilisra pozitív PCR azt jelenti, hogy antibiotikumra van szükségem?
A Dientamoeba fragilis pozitív PCR-lelet nem jelenti automatikusan azt, hogy antimikrobiális kezelésre van szüksége. A tünetmentes embereknek általában nincs szükségük gyógyszeres kezelésre, és 1 pozitív székletvizsgálati eredmény nem bizonyítja, hogy mi okozta az emésztőrendszeri tüneteket. A klinikusok mérlegelhetik a kezelést, ha a tünetek tartósan fennállnak, más lehetséges okokat is megvizsgáltak, és a kórokozó szerepe valószínűnek tűnik. Az erős fájdalom, a kiszáradás vagy a véres széklet a PCR-leleten túlmutató kivizsgálást tesz szükségessé.
0 Elmúlhat a Dientamoeba fragilis kezelés nélkül?
0 A Dientamoeba fragilis kimutatása kezelés nélkül is negatívvá válhat, és az emésztőrendszeri tünetek a kórokozó kiürülésétől függetlenül is megszűnhetnek. A 7 napos tünetnapló segíthet dokumentálni a javulást, ha a megfigyelés megfelelő megközelítés. Sem a spontán gyógyulás, sem egy későbbi negatív PCR-vizsgálat nem bizonyítja, hogy a kórokozó okozta az eredeti betegséget. A tartós vagy súlyosbodó tünetek újraértékelést indokolnak a határozatlan ideig tartó várakozás helyett.
Mi a legjobb kezelés a Dientamoeba fragilis ellen?
Nincs minden Dientamoeba fragilis-pozitív beteg esetében egységesen elfogadott, legjobb tünetenyhítő kezelés. A CDC felnőttekre vonatkozó útmutatója 25–35 mg/kg/nap paromomicint sorol fel 3 részletben, 7 napon át, de a metronidazol is szóba jöhet. A retrospektív bizonyítékok a paromomicint részesítik előnyben a kórokozó kiirtására, de a kórokozó kiirtása nem jelenti ugyanazt, mint a tünetek javulása. A gyógyszert felíró orvosnak az életkor, a terhesség, az egészségi állapot és a gyógyszerkölcsönhatások figyelembevételével egyénileg kell megválasztania a kezelést.
Miért vannak még mindig tüneteim a Dientamoeba fragilis kezelése után?
A Dientamoeba fragilis kezelése után fennálló tünetek azt jelenthetik, hogy a kórokozó nem a fő kiváltó ok volt, más betegség áll fenn, vagy a kezelés nem szüntette meg a kimutathatóságot. A negatív PCR nem zárja ki a cöliákiát, a gyógyszer okozta hasmenést, a mikroszkópos vastagbélgyulladást vagy a funkcionális bélbetegséget. A 4 hétig vagy tovább tartó hasmenés rendszerint indokolja a krónikus hasmenés strukturált kivizsgálását. Újabb gyógyszeres kúrát az ismételt kivizsgálás után kell alkalmazni, nem pusztán azért felírni, mert a tünetek továbbra is fennállnak.
Kezelni kell a Dientamoeba fragilis fertőzést gyermekeknél?
A Dientamoeba fragilis fertőzött gyermekeket nem szabad automatikusan kezelni pozitív széklet-PCR-lelet alapján. Egy 96, 3–12 éves gyermeket vizsgáló randomizált tanulmányban a 10 napos metronidazol-kezelés nem eredményezett jobb klinikai kimenetelt, mint a placebo. Gyermekeknél a kezelési döntés során figyelembe kell venni a tartós tüneteket, a hidratáltságot, a növekedést, az alternatív diagnózisokat és az adott gyógyszer biztonságosságát. A növekedés elmaradása vagy az, ha a gyermek egyértelműen rossz állapotban van, klinikai vizsgálatot tesz szükségessé, a parazita eredményétől függetlenül.
Vizsgálatnak vagy kezelésnek kell alávetni a családtagjaimat, ha az eredményem pozitív?
Egyetlen, Dientamoeba fragilisra pozitív háztartástag miatt nem indokolt automatikusan minden kontakt tesztelése vagy kezelése. Tünetmentes kimutatás esetén általában nincs szükség kezelésre, míg 2 vagy több, tartósan fennálló, összeegyeztethető tüneteket mutató személy esetén indokolt lehet a háztartás tagjainak megbeszélése a kezelőorvossal. A körülbelül 20 másodpercig tartó, szappannal és vízzel végzett kézmosás ésszerű általános higiénés intézkedés, de nem bizonyított garancia a Dientamoeba kiújulása ellen. A cérnagiliszta-fertőzés vizsgálata külön döntés kérdése, nem pedig a pozitív PCR automatikus következménye.
Érthető magyarázatot kaphat a vérvizsgálat eredményekről
Töltse fel laborleletét, és az Kantesti AI másodpercek alatt közérthetően elmagyarázza az egyes biomarkereket. Világszerte több mint 2 millió ember használja.
Referenciák
- Klein, T., Mitchell, S., & Weber, H. (2026). Hasmenés böjt után, fekete pöttyök a székletben és GI-útmutató, 2026. Kantesti AI orvosi kutatás. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Női egészségügyi útmutató: ovuláció, menopauza és hormonális tünetek. Kantesti AI orvosi kutatás. DOI
- Betegségellenőrzési és Megelőzési Központok (2024). Clinical Care of Dientamoeba fragilis. CDC Clinical Guidance.
- Röser D et al. (2014). Metronidazole Therapy for Treating Dientamoebiasis in Children Is Not Associated With Better Clinical Outcomes: A Randomized, Double-Blinded and Placebo-Controlled Clinical Trial. Clinical Infectious Diseases. DOI
- van Hellemond JJ et al. (2012). Is paromomycin the drug of choice for eradication of Dientamoeba fragilis in adults? International Journal for Parasitology: Drugs and Drug Resistance.
- 2 hónapos kortólElemzett vizsgálatok
- 127+Országok
- 100+Nyelvek
Az orvosi csapatról


E-E-A-T bizalmi jelzések
Tapasztalat
Orvosok által vezetett klinikai áttekintés a laboratóriumi értelmezési munkafolyamatokról.
Szakértelem
Laboratóriumi medicina fókusz: hogyan viselkednek a biomarkerek klinikai környezetben.
Tekintélyesség
Orvosi lektor: Dr. Thomas Klein, közreműködött Dr. Sarah Mitchell és Prof. Dr. Hans Weber.
Megbízhatóság
Bizonyítékokon alapuló értelmezés, világos követési útvonalakkal a riadalom csökkentésére.






Orvosi nyilatkozat
A cikk kizárólag oktatási célokat szolgál, és nem minősül orvosi tanácsadásnak. A diagnózisra és a kezelési döntésekre vonatkozóan mindig konzultáljon szakképzett egészségügyi szolgáltatóval.
Közzétéve · Kapcsolat a szerkesztőséggel
Kiadó: Kantesti Ltd, bejegyezve Angliában és Walesben, cégjegyzékszám:. 17090423, London, Egyesült Királyság.
