A positive stool PCR does not automatically mean you need medication. Treatment decisions depend on persistent symptoms, alternative explanations, and the uncertain relationship between clearing the organism and feeling better.

Najważniejsze wnioski
- Pozytywny PCR detects Dientamoeba fragilis genetic material; 1 positive result does not establish that the organism caused your digestive symptoms.
- Brak objawów usually means no treatment is needed, even when a stool test detects Dientamoeba fragilis.
- Persistent diarrhea lasting 14 days or longer deserves reassessment, but duration alone does not prove that Dientamoeba fragilis is responsible.
- Treatment evidence includes a randomized trial of 96 children in which metronidazole did not improve clinical outcomes more than placebo.
- Paromomycin is a clinician-selected option; CDC adult guidance lists 25–35 mg/kg/day in 3 divided doses for 7 days.
- Kalprotektyna below 50 µg/g is a common adult laboratory reference threshold, not a test that confirms or excludes symptomatic Dientamoeba fragilis.
- Warning signs such as blood in stool, severe abdominal pain, dehydration, or unintentional weight loss require assessment beyond the positive PCR.
- Kontynuacja / obserwacja should measure symptoms as well as test results; organism clearance and symptom recovery are 2 different outcomes.
Does a Dientamoeba fragilis positive result need treatment?
A dientamoeba fragilis positive stool PCR does not automatically require treatment. People without symptoms usually do not need medication; clinicians may consider treatment when digestive symptoms persist, the organism is plausibly relevant, and other explanations have been assessed.
Detection and causation are separate questions. A stool panel can identify an organism accurately without establishing why someone has abdominal pain or diarrhea, so 1 positive result is a finding to interpret rather than a prescription trigger; the organism may be incidental, contributory, or unrelated to the current illness.
Ten CDC clinical care guidance says asymptomatic Dientamoeba fragilis detection generally does not require treatment and that medication may help some symptomatic people when it is the only organism found (CDC, 2024). Finding only 1 organism strengthens a possible explanation, but it still does not exclude celiac disease, medication effects, or a functional bowel disorder.
For example, consider a hypothetical adult with 2 days of loose stools after a household stomach bug whose panel detects Dientamoeba fragilis. If symptoms are already settling and hydration is adequate, observation may be more sensible than immediately adding an antimicrobial that can itself cause nausea or diarrhea.
Kantesti is an AI blood test analyzer that can explain accompanying laboratory findings, but it cannot determine from a stool PCR whether this organism caused your symptoms. We explain that boundary through our organizational information; the clinical decision depends on more than 1 laboratory result.
What does a Dientamoeba fragilis stool test actually detect?
A Dientamoeba fragilis stool PCR detects genetic material from the organism in the submitted sample. It does not directly establish organism viability, tissue damage, or symptom causation, and there is no validated universal PCR cutoff that determines whether treatment is necessary.
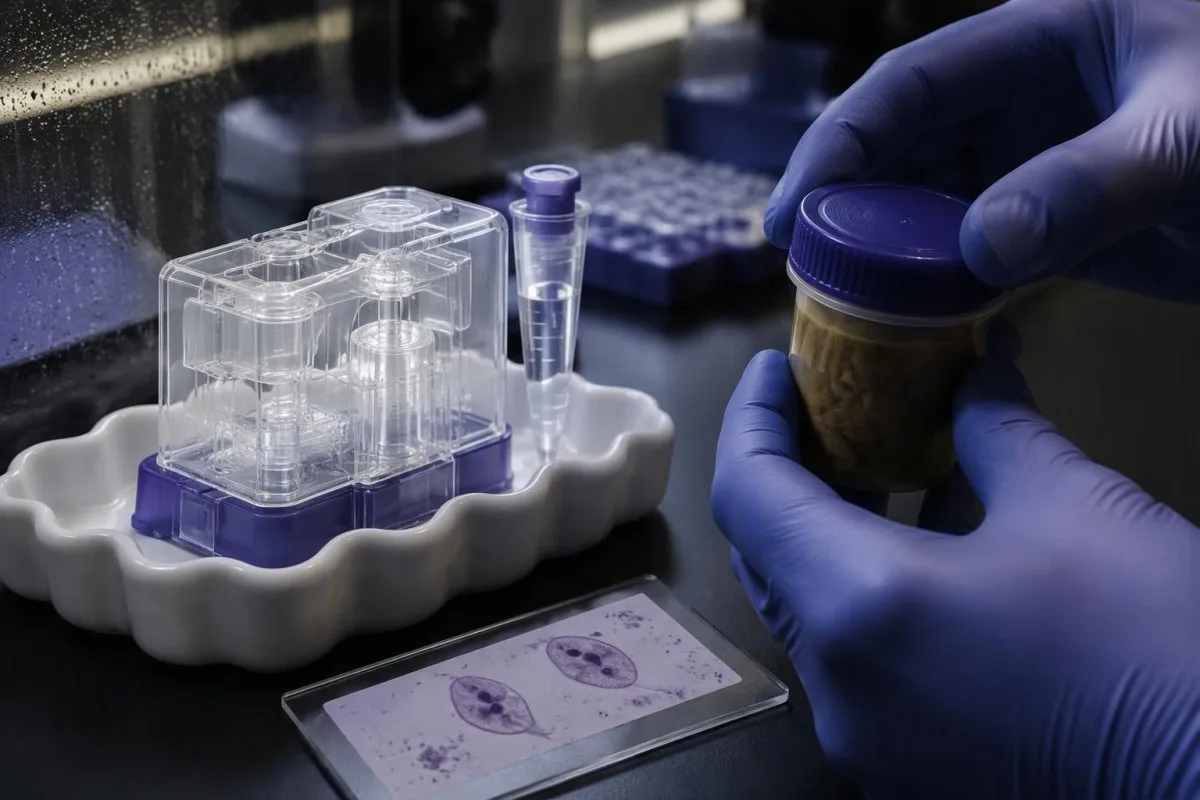
Dientamoeba fragilis is an intestinal protozoan, not a worm. Its name can be misleading: it belongs to a group related to trichomonads rather than ordinary amoebae, and microscopic trophozoites commonly have 1 or 2 nuclei; seeing the name on a report does not imply an invasive infection throughout the body.
Most clinical reports use detected/not detected, rather than a clinically validated severity scale. If a laboratory supplies a cycle threshold, a lower value usually indicates more target material within that assay, but differences in extraction, stool consistency, and platforms prevent a number from functioning as a universal treatment threshold; our przewodnik po wynikach jakościowych i ilościowych wyjaśnia rozróżnienie w raportowaniu.
PCR and microscopy can disagree without either result being meaningless. PCR is generally more sensitive, whereas microscopy depends on preservation, staining, and expertise; traditional parasite microscopy may require specimens collected on 3 separate days because organism shedding and visibility vary, while a validated molecular assay may use a single specimen.
Check the actual panel contents before assuming other infections were excluded. A negative result for 5 listed pathogens says nothing about an organism the panel never tested, and some gastrointestinal panels do not include Dientamoeba fragilis at all; ask whether your result came from a targeted assay or a broader panel.
When is positive PCR more likely to be incidental carriage?
Incidental carriage is more likely when the person has no symptoms, symptoms have already resolved, or another explanation fits better. A repeated positive result can demonstrate ongoing detection, but 2 positive samples still do not establish that Dientamoeba fragilis is causing illness.
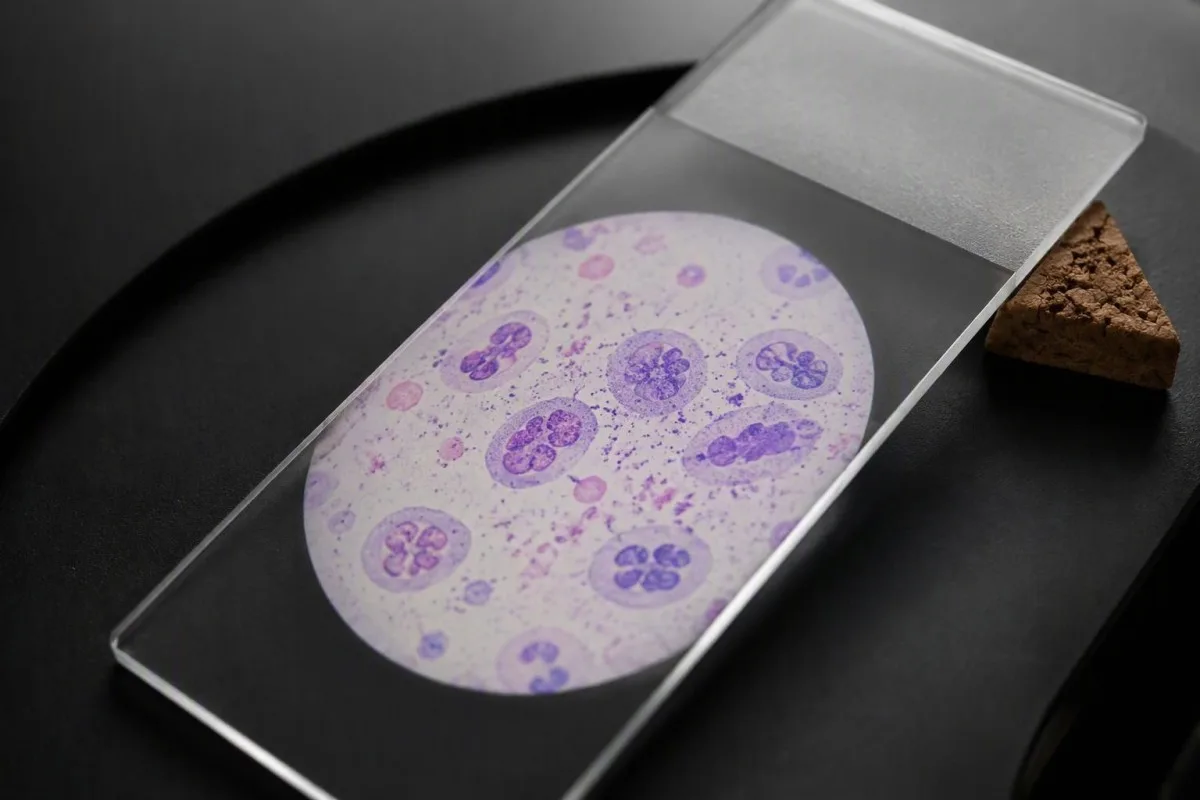
Asymptomatic detection is real, not automatically a laboratory error. Sensitive PCR testing finds organisms that older methods missed, including in people who feel well; because prevalence differs substantially between settings, age groups, and assays, a single percentage from 1 population should not be used to estimate your personal likelihood of illness.
Ten timing of symptoms can weaken an apparent association. A hypothetical person with 5 years of alternating constipation and diarrhea who receives a first positive stool PCR has not necessarily acquired a new explanation for those longstanding symptoms; the test cannot date acquisition or show whether the organism was present before symptoms started.
A positive commercial microbiome report is not equivalent to a clinical diagnosis. Relative abundance, proprietary risk scores, and organisms reported outside validated pathogen testing may not have established treatment implications; before acting on 1 highlighted finding, review our discussion of ograniczeń badań mikrobiomu.
Jakiś asymptomatic household contact is not automatically a treatment candidate. Screening and treating every family member after 1 positive result can create avoidable medication exposure; contact testing is more reasonably discussed when several people have persistent compatible symptoms, or when a specialist or local public-health team identifies a specific reason.
Which Dientamoeba fragilis symptoms could be relevant?
Reported Dientamoeba fragilis symptoms include loose stools, abdominal discomfort, bloating, and sometimes nausea or reduced appetite. None is specific to this organism, so clinicians assess the symptom pattern, duration, and functional impact rather than assuming that 1 positive PCR explains everything.
Stool consistency is often more useful than the word diarrhea. On the 7-category Bristol Stool Chart, types 6 and 7 describe mushy and watery stools; recording those types alongside frequency helps distinguish persistent loose stools from frequent but formed bowel movements, as explained in our poradnik dotyczący konsystencji stolca.
A 7-day symptom diary can clarify whether the illness is continuous or meal-related. Record bowel frequency, stool type, nighttime waking, abdominal discomfort, medicines, and missed activities; a pattern that repeatedly follows a particular food may suggest malabsorption or intolerance, although dietary associations alone do not diagnose either condition.
Stool color does not identify Dientamoeba fragilis. Yellow stools can accompany rapid transit, dietary changes, or fat malabsorption, and 1 unusual bowel movement is not a parasite-specific sign; our explanation of yellow stool causes helps separate color changes from more informative accompanying features.
For example, a hypothetical adult with 4 loose stools daily for 6 weeks, stable weight, and no other pathogen detected has a more plausible treatment discussion than someone whose brief illness has ended. Even then, the assessment should consider medication effects, celiac disease, and inflammatory or functional conditions before assigning causation.
Which symptoms should not be blamed on Dientamoeba fragilis?
Blood in stool, substantial dehydration, severe or localized abdominal pain, persistent fever, and unintentional weight loss need assessment beyond a positive Dientamoeba fragilis result. These findings can signal another condition, and clinicians should not allow 1 detected organism to delay appropriate investigation.
Seek urgent medical help for severe pain, collapse, confusion, or inability to keep fluids down. A temperature around 38°C or higher combined with significant illness deserves prompt advice, although age, immune status, and other symptoms matter more than a single cutoff; emergency symptoms should not wait for a repeat parasite test.
Widoczne red blood or black, tarry stool is not a typical finding to dismiss as uncomplicated dientamoebiasis. Iron tablets and some foods can change stool color, but 1 episode accompanied by dizziness, weakness, or significant pain warrants prompt assessment; our objawy alarmowe związane z krwią w stolcu explain why appearance and accompanying symptoms matter.
Diarrhea that wakes someone from sleep and progressive weight loss broaden the differential diagnosis. Unintentional loss of more than 5% of body weight over 6–12 months is a commonly used clinical warning threshold, but smaller losses can still matter in children, frail adults, or someone losing weight rapidly.
Reduced urine output can indicate odwodnienie, especially when accompanied by thirst, dizziness, or dry mouth. Do not wait for a precise number of hours if the person appears unwell; infants, older adults, pregnant people, and those with kidney disease need a lower threshold for clinical advice than a healthy adult with 1 mild loose stool.
What if the stool panel detects another pathogen too?
When another pathogen is detected, clinicians compare its established disease pattern with the symptoms before prioritizing Dientamoeba fragilis treatment. A panel with 2 positive targets may reflect coinfection, persistent shedding, or incidental carriage; it does not automatically justify treating both organisms.
Giardia has a better-established relationship with persistent diarrhea and malabsorption than Dientamoeba fragilis. If both are detected in a hypothetical person with 3 weeks of loose, greasy stools after untreated-water exposure, a clinician may prioritize Giardia-directed care; our Giardia treatment and recovery guide explains the different evidence base.
Campylobacter detection does not automatically require antibiotics either, despite its established role in gastroenteritis. Severity, illness duration, and vulnerability determine the decision, so 2 detected organisms still require 2 separate clinical judgments; compare our discussion of Campylobacter antibiotic decisions rather than assuming all stool positives follow one rule.
Niedawne antibiotic exposure changes the assessment because it raises concern for antibiotic-associated diarrhea and C. difficile. A positive screening assay with a negative toxin result creates another detection-versus-disease problem, particularly when someone does not have at least 3 unformed stools in 24 hours; our rozbieżnych wynikach badań w kierunku C. difficile guide describes that distinction.
A negative panel is not a complete gastrointestinal evaluation. Even a panel covering 20 organisms cannot identify bile acid diarrhea, microscopic colitis, celiac disease, or every travel-related infection; the test menu, exposure history, and symptom duration determine whether additional microbiology or a noninfectious workup makes more sense.
Does Dientamoeba fragilis treatment reliably improve symptoms?
Dientamoeba fragilis treatment does not reliably produce symptom improvement, and the evidence is mixed. A randomized, placebo-controlled trial involving 96 children found that metronidazole did not improve clinical outcomes more than placebo, even though treatment initially increased organism eradication.
Röser et al. reported the trial in Clinical Infectious Diseases in 2014. Children aged 3–12 years received a 10-day course of metronidazole or placebo, and the study did not establish a clinical benefit from metronidazole; that result argues against routine treatment of every symptomatic child with a positive test.
The trial does not prove that all treatments are ineffective in every patient. It evaluated 1 medication in a particular pediatric population, so its findings cannot automatically be extended to paromomycin, every adult presentation, or unusual clinical circumstances; uncertainty should narrow claims rather than be converted into either universal treatment or universal dismissal.
Before-and-after improvement is weaker evidence than a randomized comparison. Over a 2-week period, symptoms may improve naturally, fluctuate, or respond to changes in diet and other medicines; an uncontrolled report of feeling better after treatment cannot reliably separate those explanations from a specific effect on Dientamoeba fragilis.
Na Kantesti, we distinguish organism eradication, symptom recovery, and study design as 3 separate issues when explaining this uncertainty. Our digestive symptom research guide provides broader context, but it is not direct evidence that antimicrobial treatment improves outcomes in Dientamoeba-positive patients.
Which medicines may clinicians use, and what are the limits?
Clinicians may use paromomycin or metronidazole for selected symptomatic patients, but medication choice does not resolve uncertainty about causation. CDC adult guidance lists paromomycin at 25–35 mg/kg/day in 3 divided doses for 7 days; this is prescribing information, not an instruction to self-treat.
Paromomycin mainly acts within the intestinal lumen. A retrospective adult study by van Hellemond et al. in 2012 found better eradication with paromomycin than some alternatives, but the nonrandomized design cannot establish superior symptom relief; its findings support a medication discussion, not a guaranteed cure for abdominal discomfort.
Ten CDC adult metronidazole regimen is 500–750 mg orally 3 times daily for 10 days (CDC, 2024). Nausea, altered taste, medication interactions, and occasional neurologic adverse effects matter; pediatric dosing differs, and pregnancy, breastfeeding, liver disease, or other medical conditions require a prescriber to assess the specific choice.
Medication reconciliation should happen before prescribing. Metronidazole can increase warfarin's anticoagulant effect, so a person taking warfarin may need an individualized INR monitoring plan rather than merely a routine 10-day prescription; our guide to antybiotyki i zmiany INR explains the mechanism and monitoring considerations.
A penicillin allergy label does not automatically prohibit either of these medicines because they are not penicillins. However, any previous reaction to the proposed drug itself needs review, and 1 vague historical allergy label should not substitute for a full medication history; our allergy label reassessment guide explains that separate issue.
When do clinicians investigate other causes before prescribing?
Clinicians often investigate other causes before prescribing when symptoms are longstanding, atypical, associated with warning signs, or poorly explained by the stool result. Diarrhea lasting 4 weeks or longer is commonly classified as chronic, making a structured noninfectious assessment particularly useful.
Medication effects are a high-yield starting point. Metformin, magnesium-containing products, laxatives, and some antibiotics can cause loose stools; if a hypothetical person develops diarrhea 1 week after a dose increase, that timeline may be more informative than incidental parasite detection, although prescribed medicines should not be stopped without advice.
A fecal calprotectin below 50 µg/g is a common adult laboratory reference threshold, while values above roughly 250 µg/g may strengthen concern for intestinal inflammation in an appropriate clinical pathway. These are not universal diagnostic boundaries: age, infection, NSAID use, and laboratory methods affect interpretation, as discussed in our borderline calprotectin follow-up .
Celiac screening commonly combines tissue transglutaminase IgA with total IgA. Reducing gluten before testing can make results falsely reassuring, and IgA deficiency changes which antibody tests are appropriate; if gluten has already been removed for several weeks, our gluten challenge planning guide explains why clinicians individualize the next step.
A normal initial workup does not make every alternative disappear. In someone with 6 months of watery diarrhea, clinicians may consider bile acid diarrhea or microscopic colitis; the latter can require colon examination with tissue sampling even when the bowel looks normal, while an IBS diagnosis depends on a compatible pattern and appropriate exclusion of warning features.
Can blood tests show whether Dientamoeba fragilis is causing illness?
Routine blood tests cannot establish that Dientamoeba fragilis caused digestive symptoms. They can identify consequences or competing explanations, such as dehydration, anemia, inflammation, or nutrient deficiency; no validated CBC, CRP, or eosinophil cutoff confirms symptomatic disease from this organism.
CBC and ferritin can reveal an alternative reason for fatigue. In otherwise healthy adults, ferritin below 15 µg/L strongly supports depleted iron stores, although inflammation can raise ferritin and obscure deficiency; fatigue with low iron should not automatically be attributed to 1 stool finding, as our przewodnik po objawach niskiego ferrytyny .
For example, imagine an adult with ferritin 9 µg/L and hemoglobin 108 g/L alongside a positive stool PCR. Those hypothetical results warrant investigation of iron deficiency and its cause, not an assumption that treating the protozoan will correct the anemia; our przewodnik po interpretacji badań żelaza shows why multiple markers matter.
Eosinophilia is not a reliable marker of Dientamoeba fragilis disease. An eosinophil count above 0.5 × 10^9/L is commonly considered elevated, but allergies, medicines, and some helminth infections are more typical explanations; a positive Dientamoeba test should not stop clinicians from investigating substantial or persistent eosinophilia separately.
Kantesti is an AI blood test interpretation platform that explains CBC, ferritin, CRP, and kidney-function results without treating them as proof of parasite causation. A CRP of 3 mg/L may fall within a laboratory's standard reference interval, yet normal inflammatory markers do not exclude celiac disease, microscopic colitis, or other explanations for persistent diarrhea.
How do treatment decisions differ for children and vulnerable adults?
Children, pregnant people, frail adults, and immunocompromised patients need individualized assessment rather than an automatic response to positive PCR. In children, growth, hydration, and symptom severity matter especially; the randomized metronidazole trial in 96 children supports caution about routine prescribing.
Growth faltering should prompt a broader pediatric evaluation. A hypothetical child with 6 weeks of loose stools and a falling growth trajectory needs assessment of intake, celiac disease, inflammation, and other causes; Dientamoeba fragilis detection may be relevant, but it should not become the only explanation considered.
Children can become dehydrated more quickly than healthy adults, particularly when vomiting accompanies diarrhea. Oral rehydration solution prepared exactly as directed is preferable to guessing electrolyte amounts, and 1 clearly unwell child with reduced urine, unusual drowsiness, or inability to drink needs prompt advice rather than waiting for a medication trial.
Pregnancy changes medication selection, not the meaning of PCR. A positive result still does not establish causation, while gestational stage, symptom burden, and drug-specific safety information influence prescribing; a person who is 10 weeks pregnant should discuss treatment with the maternity or prescribing team rather than using another household member's medication.
Immunosuppression lowers the threshold for evaluating other opportunistic causes, but it does not make this organism automatically responsible. Kantesti AI does not replace pediatric or specialist assessment; our discussion of Interpretacja AI dla dzieci explains why adult reference ranges and 1 abnormal result can be misleading.
Should you repeat the stool test after treatment?
Repeat testing is not automatically necessary after symptoms resolve, and a test-of-cure plan should be agreed with the treating clinician. Persistent symptoms require reassessment; 1 repeat positive PCR does not by itself justify another course, and a negative result does not explain ongoing symptoms.
Testing immediately after treatment can be difficult to interpret. PCR detects genetic material rather than directly measuring living organisms, and there is no universal Dientamoeba-specific interval that makes every result definitive; instead of choosing an arbitrary day 3 test, ask what question the repeat test is intended to answer.
A positive repeat result may reflect persistence, reacquisition, or assay-related timing considerations. Those possibilities have different implications, so before prescribing course 2 a clinician should review adherence, the original symptom pattern, household exposures, and whether the first course changed anything that mattered to the patient.
A negative PCR with ongoing bloating shifts attention toward other explanations rather than proving treatment failure. Selected patients with risk factors may warrant a breath-test discussion, but bloating alone should not trigger indiscriminate SIBO testing; our breath test preparation guide explains why protocol and pretest probability matter.
Define success before treatment starts. For a hypothetical adult, improvement from 5 watery stools per day to 1–2 formed stools is a meaningful outcome, whereas an unchanged symptom diary with a negative PCR is laboratory clearance without demonstrated symptom benefit; documenting both prevents repeated medication from becoming the default response.
What practical steps help without unnecessary household treatment?
Handwashing, careful bathroom hygiene, safe food handling, and clear follow-up records are reasonable steps after a positive result. The exact transmission routes of Dientamoeba fragilis remain incompletely resolved, so 1 positive household test does not justify promises that a particular cleaning routine will prevent recurrence.

Wash hands with soap and water after toilet use and before preparing food. Scrubbing for about 20 seconds is a standard general hygiene recommendation, not a Dientamoeba-specific eradication method; gloves do not replace handwashing, and bathrooms should be cleaned using ordinary product instructions rather than improvised chemical mixtures.
The proposed connection with pinworm transmission is not settled. Nighttime anal itching may justify a separate assessment, sometimes involving a morning tape test on 3 occasions, but a positive Dientamoeba PCR alone is not a reason to give everyone a deworming medicine or assume pinworms are present.
Kantesti is an AI-powered blood test analysis tool that can help explain accompanying laboratory results while stool-management decisions remain with the clinician. Keep the symptom diary, medicine list, and test dates together as 3 distinct records; our przykładowe procedury interpretacji describe educational workflows rather than evidence that our service treats intestinal parasites.
A shared household record should respect consent and minimize unnecessary identifiers. If 2 family members have symptoms, each person's clinical assessment and treatment decision remain separate; our polityka prywatności i zasady przetwarzania danych explain how we approach information handling, but your clinician's secure communication channel should be used for prescribing and urgent advice.
What should you ask your clinician, and which research supports the decision?
Ask whether Dientamoeba fragilis plausibly explains your symptoms, which alternatives need checking, and what benefit would justify treatment. The most useful evidence separates symptom outcomes from organism eradication; a 10-day treatment course and a negative follow-up test are not, by themselves, proof of clinical benefit.

Bring 4 items to the appointment: the full stool report, a medication list, a symptom timeline, and any relevant accompanying laboratory results. Ask what would change the decision—another pathogen, celiac antibodies, a concerning calprotectin result, or spontaneous improvement—and agree on when to return if symptoms persist or warning signs develop.
A 7-day diary can make observation an active plan rather than doing nothing. Maintain fluids and tolerated foods; oral rehydration solution can help replace diarrheal losses, but restrictive diets, herbal parasite cleanses, and supplements have no established role in eradicating Dientamoeba fragilis and should not delay investigation of persistent symptoms.
Ten 3 external sources below have different evidentiary roles: CDC provides clinical prescribing guidance, Röser et al. provide randomized pediatric symptom-outcome evidence, and van Hellemond et al. provide retrospective adult eradication data. Kantesti applies standardy treści medycznych that distinguish these study designs instead of presenting them as equally strong proof.
Ten 2 Figshare publications listed below are general educational resources, not trials of Dientamoeba fragilis treatment; the women's health guide does not provide direct evidence for this decision. A DOI establishes a persistent identifier, not clinical validation, and our technical and clinical methodology should likewise not be mistaken for proof that AI can establish the cause of digestive symptoms.
Często zadawane pytania
Czy dodatni wynik testu PCR w kierunku Dientamoeba fragilis oznacza, że potrzebuję antybiotyków?
Dodatni wynik badania PCR w kierunku Dientamoeba fragilis nie oznacza automatycznie konieczności leczenia przeciwdrobnoustrojowego. Osoby bez objawów na ogół nie potrzebują leków, a 1 dodatni wynik badania kału nie pozwala ustalić, co było przyczyną objawów ze strony układu pokarmowego. Lekarze mogą rozważyć leczenie, gdy objawy utrzymują się, oceniono inne możliwe przyczyny i wydaje się prawdopodobne, że ten drobnoustrój ma związek z objawami. Silny ból, odwodnienie lub krew w stolcu wymagają oceny wykraczającej poza wynik badania PCR.
Czy Dientamoeba fragilis może ustąpić bez leczenia?
0 Wykrywalność Dientamoeba fragilis może stać się ujemna bez leczenia, a objawy ze strony układu pokarmowego mogą ustąpić również niezależnie od wyeliminowania drobnoustroju. Prowadzenie dziennika objawów przez 7 dni może pomóc udokumentować poprawę, gdy obserwacja jest właściwym postępowaniem. Ani samoistny powrót do zdrowia, ani późniejszy ujemny wynik PCR nie dowodzą, że drobnoustrój wywołał pierwotną chorobę. Utrzymujące się lub nasilające objawy powinny skłonić do ponownej oceny, a nie do bezterminowego czekania.
Jakie jest najlepsze leczenie zakażenia Dientamoeba fragilis?
Nie ma powszechnie ustalonej najlepszej metody łagodzenia objawów u każdego pacjenta z dodatnim wynikiem badania w kierunku Dientamoeba fragilis. Wytyczne CDC dla dorosłych wymieniają paromomycynę w dawce 25–35 mg/kg/dobę, podawanej w 3 dawkach podzielonych przez 7 dni; inną opcją jest metronidazol. Dane retrospektywne przemawiają za paromomycyną pod względem eradykacji drobnoustroju, ale eradykacja nie jest równoznaczna z ustąpieniem objawów. Osoba przepisująca lek musi indywidualnie dobrać go, uwzględniając wiek, ciążę, schorzenia i interakcje z lekami.
0 Dlaczego po leczeniu zakażenia Dientamoeba fragilis nadal występują u mnie objawy?
Utrzymywanie się objawów po leczeniu zakażenia Dientamoeba fragilis może oznaczać, że ten drobnoustrój nie był główną przyczyną, występuje inna choroba albo leczenie nie wyeliminowało wykrywalności patogenu. Ujemny wynik PCR nie wyklucza celiakii, biegunki związanej ze stosowaniem leków, mikroskopowego zapalenia jelita grubego ani czynnościowego zaburzenia jelit. Biegunka trwająca 4 tygodnie lub dłużej zazwyczaj wymaga przeprowadzenia ustrukturyzowanej diagnostyki przewlekłej biegunki. Kolejną kurację lekami należy zastosować dopiero po ponownej ocenie, a nie przepisywać wyłącznie dlatego, że objawy się utrzymują.
Czy dzieci z Dientamoeba fragilis powinny być leczone?
Dzieci z zakażeniem Dientamoeba fragilis nie powinny być automatycznie leczone na podstawie dodatniego wyniku PCR z próbki kału. W randomizowanym badaniu z udziałem 96 dzieci w wieku 3–12 lat nie stwierdzono lepszych wyników klinicznych po 10-dniowym kursie metronidazolu niż po placebo. Podejmując decyzje dotyczące dzieci, należy uwzględnić utrzymujące się objawy, nawodnienie, wzrastanie, alternatywne rozpoznania oraz bezpieczeństwo konkretnego leku. Zahamowanie wzrastania lub wyraźnie zły stan dziecka wymagają oceny klinicznej niezależnie od wyniku badania w kierunku pasożyta.
Czy moja rodzina powinna zostać przebadana lub leczona, jeśli mój wynik jest dodatni?
Pojedynczy domownik z dodatnim wynikiem badania w kierunku Dientamoeba fragilis nie uzasadnia automatycznie badania ani leczenia wszystkich osób z kontaktu. Bezobjawowe wykrycie zwykle nie wymaga leczenia, natomiast 2 lub więcej osób z utrzymującymi się zgodnymi objawami może uzasadniać omówienie sytuacji domowników z lekarzem. Mycie rąk wodą z mydłem przez około 20 sekund to rozsądny ogólny środek higieny, ale nie daje sprawdzonej gwarancji zapobieżenia nawrotowi zakażenia Dientamoeba. Ocena w kierunku owsicy to odrębna decyzja, a nie automatyczna konsekwencja dodatniego wyniku PCR.
Dowiedz się, jak czytać wyniki badań krwi
Prześlij wynik badania laboratoryjnego, a sztuczna inteligencja Kantesti w kilka sekund objaśni prostym językiem każdy biomarker. Z narzędzia korzysta ponad 2 miliony osób na całym świecie.
Odniesienia
- Klein, T., Mitchell, S. i Weber, H. (2026). Biegunka po poście, czarne drobinki w stolcu i poradnik gastroenterologiczny 2026. Badania medyczne z wykorzystaniem sztucznej inteligencji Kantesti. DOI
- Klein, T., Mitchell, S. i Weber, H. (2026). Przewodnik po zdrowiu kobiet: owulacja, menopauza i objawy hormonalne. Badania medyczne z wykorzystaniem sztucznej inteligencji Kantesti. DOI
- Centers for Disease Control and Prevention (2024). Clinical Care of Dientamoeba fragilis. CDC Clinical Guidance.
- Röser D et al. (2014). Metronidazole Therapy for Treating Dientamoebiasis in Children Is Not Associated With Better Clinical Outcomes: A Randomized, Double-Blinded and Placebo-Controlled Clinical Trial. Clinical Infectious Diseases. DOI
- van Hellemond JJ et al. (2012). Is paromomycin the drug of choice for eradication of Dientamoeba fragilis in adults? International Journal for Parasitology: Drugs and Drug Resistance.
- 2 mln+Analizowane badania
- 127+Kraje
- 100+Języki
O zespole medycznym


Sygnały zaufania E-E-A-T
Doświadczenie
Kliniczna weryfikacja procesów interpretacji przez lekarza.
Ekspertyza
Medycyna laboratoryjna skupiona na tym, jak zachowują się biomarkery w kontekście klinicznym.
Autorytatywność
Recenzja medyczna: dr Thomas Klein, przy współpracy dr Sarah Mitchell i prof. dr. Hansa Webera.
Solidność
Interpretacja oparta na dowodach, z jasnymi ścieżkami dalszego postępowania, aby ograniczyć alarm.






Zastrzeżenie medyczne
Ten artykuł ma wyłącznie charakter edukacyjny i nie stanowi porady medycznej. Zawsze konsultuj decyzje dotyczące diagnozy i leczenia z wykwalifikowanym pracownikiem ochrony zdrowia.
Opublikowano · Skontaktuj się z zespołem redakcyjnym
Opublikowano przez Kantesti Ltd, zarejestrowaną w Anglii i Walii, numer firmy. 17090423, Londyn, Wielka Brytania.
