A positive stool PCR does not automatically mean you need medication. Treatment decisions depend on persistent symptoms, alternative explanations, and the uncertain relationship between clearing the organism and feeling better.

Prìomh phuingean
- PCR dearbhach detects Dientamoeba fragilis genetic material; 1 positive result does not establish that the organism caused your digestive symptoms.
- Gun chomharran usually means no treatment is needed, even when a stool test detects Dientamoeba fragilis.
- Persistent diarrhea lasting 14 days or longer deserves reassessment, but duration alone does not prove that Dientamoeba fragilis is responsible.
- Treatment evidence includes a randomized trial of 96 children in which metronidazole did not improve clinical outcomes more than placebo.
- Paromomycin is a clinician-selected option; CDC adult guidance lists 25–35 mg/kg/day in 3 divided doses for 7 days.
- Calprotectin below 50 µg/g is a common adult laboratory reference threshold, not a test that confirms or excludes symptomatic Dientamoeba fragilis.
- Warning signs such as blood in stool, severe abdominal pain, dehydration, or unintentional weight loss require assessment beyond the positive PCR.
- Leantainn suas should measure symptoms as well as test results; organism clearance and symptom recovery are 2 different outcomes.
Does a Dientamoeba fragilis positive result need treatment?
A dientamoeba fragilis positive stool PCR does not automatically require treatment. People without symptoms usually do not need medication; clinicians may consider treatment when digestive symptoms persist, the organism is plausibly relevant, and other explanations have been assessed.
Detection and causation are separate questions. A stool panel can identify an organism accurately without establishing why someone has abdominal pain or diarrhea, so 1 positive result is a finding to interpret rather than a prescription trigger; the organism may be incidental, contributory, or unrelated to the current illness.
An CDC clinical care guidance says asymptomatic Dientamoeba fragilis detection generally does not require treatment and that medication may help some symptomatic people when it is the only organism found (CDC, 2024). Finding only 1 organism strengthens a possible explanation, but it still does not exclude celiac disease, medication effects, or a functional bowel disorder.
For example, consider a hypothetical adult with 2 days of loose stools after a household stomach bug whose panel detects Dientamoeba fragilis. If symptoms are already settling and hydration is adequate, observation may be more sensible than immediately adding an antimicrobial that can itself cause nausea or diarrhea.
Kantesti is an AI blood test analyzer that can explain accompanying laboratory findings, but it cannot determine from a stool PCR whether this organism caused your symptoms. We explain that boundary through our organizational information; the clinical decision depends on more than 1 laboratory result.
What does a Dientamoeba fragilis stool test actually detect?
A Dientamoeba fragilis stool PCR detects genetic material from the organism in the submitted sample. It does not directly establish organism viability, tissue damage, or symptom causation, and there is no validated universal PCR cutoff that determines whether treatment is necessary.
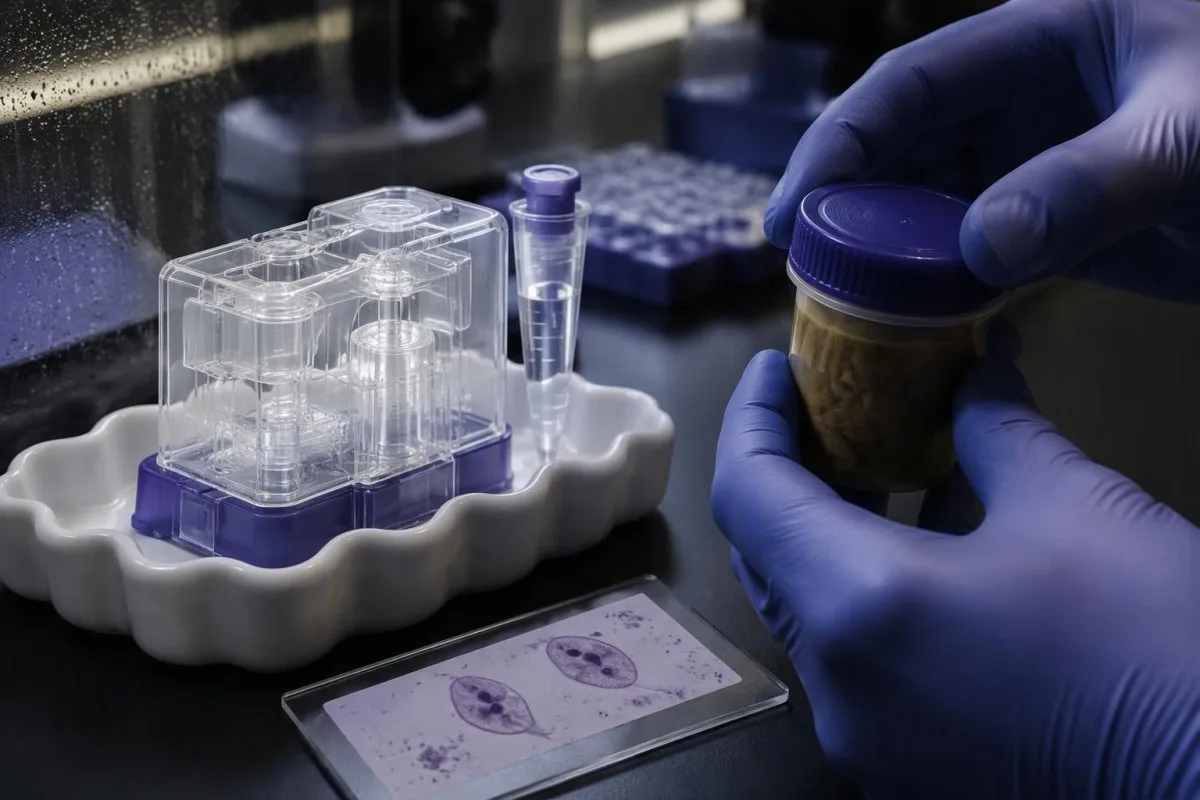
Dientamoeba fragilis is an intestinal protozoan, not a worm. Its name can be misleading: it belongs to a group related to trichomonads rather than ordinary amoebae, and microscopic trophozoites commonly have 1 or 2 nuclei; seeing the name on a report does not imply an invasive infection throughout the body.
Most clinical reports use detected/not detected, rather than a clinically validated severity scale. If a laboratory supplies a cycle threshold, a lower value usually indicates more target material within that assay, but differences in extraction, stool consistency, and platforms prevent a number from functioning as a universal treatment threshold; our stiùireadh air toraidhean càileachdail is cainneachdail tha am foillseachadh a' mìneachadh an eadar-dhealachaidh a thaobh aithris.
PCR and microscopy can disagree without either result being meaningless. PCR is generally more sensitive, whereas microscopy depends on preservation, staining, and expertise; traditional parasite microscopy may require specimens collected on 3 separate days because organism shedding and visibility vary, while a validated molecular assay may use a single specimen.
Check the actual panel contents before assuming other infections were excluded. A negative result for 5 listed pathogens says nothing about an organism the panel never tested, and some gastrointestinal panels do not include Dientamoeba fragilis at all; ask whether your result came from a targeted assay or a broader panel.
When is positive PCR more likely to be incidental carriage?
Incidental carriage is more likely when the person has no symptoms, symptoms have already resolved, or another explanation fits better. A repeated positive result can demonstrate ongoing detection, but 2 positive samples still do not establish that Dientamoeba fragilis is causing illness.
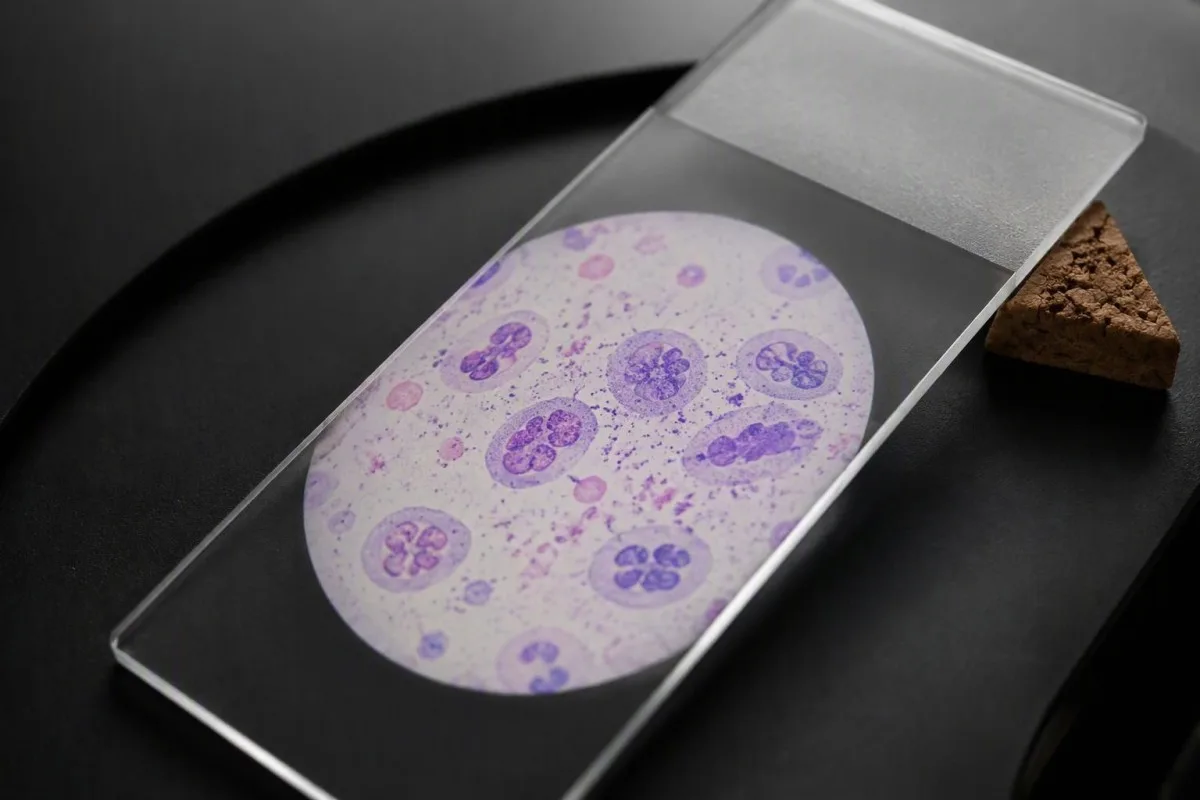
Asymptomatic detection is real, not automatically a laboratory error. Sensitive PCR testing finds organisms that older methods missed, including in people who feel well; because prevalence differs substantially between settings, age groups, and assays, a single percentage from 1 population should not be used to estimate your personal likelihood of illness.
An timing of symptoms can weaken an apparent association. A hypothetical person with 5 years of alternating constipation and diarrhea who receives a first positive stool PCR has not necessarily acquired a new explanation for those longstanding symptoms; the test cannot date acquisition or show whether the organism was present before symptoms started.
A positive commercial microbiome report is not equivalent to a clinical diagnosis. Relative abundance, proprietary risk scores, and organisms reported outside validated pathogen testing may not have established treatment implications; before acting on 1 highlighted finding, review our discussion of chuingealachaidhean deuchainn meanbh-bhitheòim.
An asymptomatic household contact is not automatically a treatment candidate. Screening and treating every family member after 1 positive result can create avoidable medication exposure; contact testing is more reasonably discussed when several people have persistent compatible symptoms, or when a specialist or local public-health team identifies a specific reason.
Which Dientamoeba fragilis symptoms could be relevant?
Reported Dientamoeba fragilis symptoms include loose stools, abdominal discomfort, bloating, and sometimes nausea or reduced appetite. None is specific to this organism, so clinicians assess the symptom pattern, duration, and functional impact rather than assuming that 1 positive PCR explains everything.
Stool consistency is often more useful than the word diarrhea. On the 7-category Bristol Stool Chart, types 6 and 7 describe mushy and watery stools; recording those types alongside frequency helps distinguish persistent loose stools from frequent but formed bowel movements, as explained in our stiùireadh againn air cunbhalachd an stòil.
A 7-day symptom diary can clarify whether the illness is continuous or meal-related. Record bowel frequency, stool type, nighttime waking, abdominal discomfort, medicines, and missed activities; a pattern that repeatedly follows a particular food may suggest malabsorption or intolerance, although dietary associations alone do not diagnose either condition.
Stool color does not identify Dientamoeba fragilis. Yellow stools can accompany rapid transit, dietary changes, or fat malabsorption, and 1 unusual bowel movement is not a parasite-specific sign; our explanation of yellow stool causes helps separate color changes from more informative accompanying features.
For example, a hypothetical adult with 4 loose stools daily for 6 weeks, stable weight, and no other pathogen detected has a more plausible treatment discussion than someone whose brief illness has ended. Even then, the assessment should consider medication effects, celiac disease, and inflammatory or functional conditions before assigning causation.
Which symptoms should not be blamed on Dientamoeba fragilis?
Blood in stool, substantial dehydration, severe or localized abdominal pain, persistent fever, and unintentional weight loss need assessment beyond a positive Dientamoeba fragilis result. These findings can signal another condition, and clinicians should not allow 1 detected organism to delay appropriate investigation.
Seek urgent medical help for severe pain, collapse, confusion, or inability to keep fluids down. A temperature around 38°C or higher combined with significant illness deserves prompt advice, although age, immune status, and other symptoms matter more than a single cutoff; emergency symptoms should not wait for a repeat parasite test.
Fhaicsinneach red blood or black, tarry stool is not a typical finding to dismiss as uncomplicated dientamoebiasis. Iron tablets and some foods can change stool color, but 1 episode accompanied by dizziness, weakness, or significant pain warrants prompt assessment; our soidhnichean rabhaidh mu fhuil anns an stòl explain why appearance and accompanying symptoms matter.
Diarrhea that wakes someone from sleep and progressive weight loss broaden the differential diagnosis. Unintentional loss of more than 5% of body weight over 6–12 months is a commonly used clinical warning threshold, but smaller losses can still matter in children, frail adults, or someone losing weight rapidly.
Reduced urine output can indicate dìth uisge, especially when accompanied by thirst, dizziness, or dry mouth. Do not wait for a precise number of hours if the person appears unwell; infants, older adults, pregnant people, and those with kidney disease need a lower threshold for clinical advice than a healthy adult with 1 mild loose stool.
What if the stool panel detects another pathogen too?
When another pathogen is detected, clinicians compare its established disease pattern with the symptoms before prioritizing Dientamoeba fragilis treatment. A panel with 2 positive targets may reflect coinfection, persistent shedding, or incidental carriage; it does not automatically justify treating both organisms.
Giardia has a better-established relationship with persistent diarrhea and malabsorption than Dientamoeba fragilis. If both are detected in a hypothetical person with 3 weeks of loose, greasy stools after untreated-water exposure, a clinician may prioritize Giardia-directed care; our Giardia treatment and recovery guide explains the different evidence base.
Campylobacter detection does not automatically require antibiotics either, despite its established role in gastroenteritis. Severity, illness duration, and vulnerability determine the decision, so 2 detected organisms still require 2 separate clinical judgments; compare our discussion of Campylobacter antibiotic decisions rather than assuming all stool positives follow one rule.
O chionn ghoirid antibiotic exposure changes the assessment because it raises concern for antibiotic-associated diarrhea and C. difficile. A positive screening assay with a negative toxin result creates another detection-versus-disease problem, particularly when someone does not have at least 3 unformed stools in 24 hours; our toraidhean C. difficile nach eil a’ co-thaobhadh guide describes that distinction.
A negative panel is not a complete gastrointestinal evaluation. Even a panel covering 20 organisms cannot identify bile acid diarrhea, microscopic colitis, celiac disease, or every travel-related infection; the test menu, exposure history, and symptom duration determine whether additional microbiology or a noninfectious workup makes more sense.
Does Dientamoeba fragilis treatment reliably improve symptoms?
Dientamoeba fragilis treatment does not reliably produce symptom improvement, and the evidence is mixed. A randomized, placebo-controlled trial involving 96 children found that metronidazole did not improve clinical outcomes more than placebo, even though treatment initially increased organism eradication.
Röser et al. reported the trial in Clinical Infectious Diseases in 2014. Children aged 3–12 years received a 10-day course of metronidazole or placebo, and the study did not establish a clinical benefit from metronidazole; that result argues against routine treatment of every symptomatic child with a positive test.
The trial does not prove that all treatments are ineffective in every patient. It evaluated 1 medication in a particular pediatric population, so its findings cannot automatically be extended to paromomycin, every adult presentation, or unusual clinical circumstances; uncertainty should narrow claims rather than be converted into either universal treatment or universal dismissal.
Before-and-after improvement is weaker evidence than a randomized comparison. Over a 2-week period, symptoms may improve naturally, fluctuate, or respond to changes in diet and other medicines; an uncontrolled report of feeling better after treatment cannot reliably separate those explanations from a specific effect on Dientamoeba fragilis.
Aig Kantesti, we distinguish organism eradication, symptom recovery, and study design as 3 separate issues when explaining this uncertainty. Our digestive symptom research guide provides broader context, but it is not direct evidence that antimicrobial treatment improves outcomes in Dientamoeba-positive patients.
Which medicines may clinicians use, and what are the limits?
Clinicians may use paromomycin or metronidazole for selected symptomatic patients, but medication choice does not resolve uncertainty about causation. CDC adult guidance lists paromomycin at 25–35 mg/kg/day in 3 divided doses for 7 days; this is prescribing information, not an instruction to self-treat.
Paromomycin mainly acts within the intestinal lumen. A retrospective adult study by van Hellemond et al. in 2012 found better eradication with paromomycin than some alternatives, but the nonrandomized design cannot establish superior symptom relief; its findings support a medication discussion, not a guaranteed cure for abdominal discomfort.
An CDC adult metronidazole regimen is 500–750 mg orally 3 times daily for 10 days (CDC, 2024). Nausea, altered taste, medication interactions, and occasional neurologic adverse effects matter; pediatric dosing differs, and pregnancy, breastfeeding, liver disease, or other medical conditions require a prescriber to assess the specific choice.
Medication reconciliation should happen before prescribing. Metronidazole can increase warfarin's anticoagulant effect, so a person taking warfarin may need an individualized INR monitoring plan rather than merely a routine 10-day prescription; our guide to atharrachaidhean ann an antibiotics agus INR explains the mechanism and monitoring considerations.
A penicillin allergy label does not automatically prohibit either of these medicines because they are not penicillins. However, any previous reaction to the proposed drug itself needs review, and 1 vague historical allergy label should not substitute for a full medication history; our allergy label reassessment guide explains that separate issue.
When do clinicians investigate other causes before prescribing?
Clinicians often investigate other causes before prescribing when symptoms are longstanding, atypical, associated with warning signs, or poorly explained by the stool result. Diarrhea lasting 4 weeks or longer is commonly classified as chronic, making a structured noninfectious assessment particularly useful.
Medication effects are a high-yield starting point. Metformin, magnesium-containing products, laxatives, and some antibiotics can cause loose stools; if a hypothetical person develops diarrhea 1 week after a dose increase, that timeline may be more informative than incidental parasite detection, although prescribed medicines should not be stopped without advice.
A fecal calprotectin below 50 µg/g is a common adult laboratory reference threshold, while values above roughly 250 µg/g may strengthen concern for intestinal inflammation in an appropriate clinical pathway. These are not universal diagnostic boundaries: age, infection, NSAID use, and laboratory methods affect interpretation, as discussed in our borderline calprotectin follow-up a’ stiùireadh.
Celiac screening commonly combines tissue transglutaminase IgA with total IgA. Reducing gluten before testing can make results falsely reassuring, and IgA deficiency changes which antibody tests are appropriate; if gluten has already been removed for several weeks, our gluten challenge planning guide explains why clinicians individualize the next step.
A normal initial workup does not make every alternative disappear. In someone with 6 months of watery diarrhea, clinicians may consider bile acid diarrhea or microscopic colitis; the latter can require colon examination with tissue sampling even when the bowel looks normal, while an IBS diagnosis depends on a compatible pattern and appropriate exclusion of warning features.
Can blood tests show whether Dientamoeba fragilis is causing illness?
Routine blood tests cannot establish that Dientamoeba fragilis caused digestive symptoms. They can identify consequences or competing explanations, such as dehydration, anemia, inflammation, or nutrient deficiency; no validated CBC, CRP, or eosinophil cutoff confirms symptomatic disease from this organism.
CBC and ferritin can reveal an alternative reason for fatigue. In otherwise healthy adults, ferritin below 15 µg/L strongly supports depleted iron stores, although inflammation can raise ferritin and obscure deficiency; fatigue with low iron should not automatically be attributed to 1 stool finding, as our stiùireadh comharraidhean ferritin ìosal a’ mìneachadh.
For example, imagine an adult with ferritin 9 µg/L and hemoglobin 108 g/L alongside a positive stool PCR. Those hypothetical results warrant investigation of iron deficiency and its cause, not an assumption that treating the protozoan will correct the anemia; our stiùireadh mìneachaidh air sgrùdaidhean iarainn shows why multiple markers matter.
Eosinophilia is not a reliable marker of Dientamoeba fragilis disease. An eosinophil count above 0.5 × 10^9/L is commonly considered elevated, but allergies, medicines, and some helminth infections are more typical explanations; a positive Dientamoeba test should not stop clinicians from investigating substantial or persistent eosinophilia separately.
Kantesti is an AI blood test interpretation platform that explains CBC, ferritin, CRP, and kidney-function results without treating them as proof of parasite causation. A CRP of 3 mg/L may fall within a laboratory's standard reference interval, yet normal inflammatory markers do not exclude celiac disease, microscopic colitis, or other explanations for persistent diarrhea.
How do treatment decisions differ for children and vulnerable adults?
Children, pregnant people, frail adults, and immunocompromised patients need individualized assessment rather than an automatic response to positive PCR. In children, growth, hydration, and symptom severity matter especially; the randomized metronidazole trial in 96 children supports caution about routine prescribing.
Growth faltering should prompt a broader pediatric evaluation. A hypothetical child with 6 weeks of loose stools and a falling growth trajectory needs assessment of intake, celiac disease, inflammation, and other causes; Dientamoeba fragilis detection may be relevant, but it should not become the only explanation considered.
Children can become dehydrated more quickly than healthy adults, particularly when vomiting accompanies diarrhea. Oral rehydration solution prepared exactly as directed is preferable to guessing electrolyte amounts, and 1 clearly unwell child with reduced urine, unusual drowsiness, or inability to drink needs prompt advice rather than waiting for a medication trial.
Pregnancy changes medication selection, not the meaning of PCR. A positive result still does not establish causation, while gestational stage, symptom burden, and drug-specific safety information influence prescribing; a person who is 10 weeks pregnant should discuss treatment with the maternity or prescribing team rather than using another household member's medication.
Immunosuppression lowers the threshold for evaluating other opportunistic causes, but it does not make this organism automatically responsible. Kantesti AI does not replace pediatric or specialist assessment; our discussion of mìneachadh AI airson clann explains why adult reference ranges and 1 abnormal result can be misleading.
Should you repeat the stool test after treatment?
Repeat testing is not automatically necessary after symptoms resolve, and a test-of-cure plan should be agreed with the treating clinician. Persistent symptoms require reassessment; 1 repeat positive PCR does not by itself justify another course, and a negative result does not explain ongoing symptoms.
Testing immediately after treatment can be difficult to interpret. PCR detects genetic material rather than directly measuring living organisms, and there is no universal Dientamoeba-specific interval that makes every result definitive; instead of choosing an arbitrary day 3 test, ask what question the repeat test is intended to answer.
A positive repeat result may reflect persistence, reacquisition, or assay-related timing considerations. Those possibilities have different implications, so before prescribing course 2 a clinician should review adherence, the original symptom pattern, household exposures, and whether the first course changed anything that mattered to the patient.
A negative PCR with ongoing bloating shifts attention toward other explanations rather than proving treatment failure. Selected patients with risk factors may warrant a breath-test discussion, but bloating alone should not trigger indiscriminate SIBO testing; our breath test preparation guide explains why protocol and pretest probability matter.
Define success before treatment starts. For a hypothetical adult, improvement from 5 watery stools per day to 1–2 formed stools is a meaningful outcome, whereas an unchanged symptom diary with a negative PCR is laboratory clearance without demonstrated symptom benefit; documenting both prevents repeated medication from becoming the default response.
What practical steps help without unnecessary household treatment?
Handwashing, careful bathroom hygiene, safe food handling, and clear follow-up records are reasonable steps after a positive result. The exact transmission routes of Dientamoeba fragilis remain incompletely resolved, so 1 positive household test does not justify promises that a particular cleaning routine will prevent recurrence.

Wash hands with soap and water after toilet use and before preparing food. Scrubbing for about 20 seconds is a standard general hygiene recommendation, not a Dientamoeba-specific eradication method; gloves do not replace handwashing, and bathrooms should be cleaned using ordinary product instructions rather than improvised chemical mixtures.
The proposed connection with pinworm transmission is not settled. Nighttime anal itching may justify a separate assessment, sometimes involving a morning tape test on 3 occasions, but a positive Dientamoeba PCR alone is not a reason to give everyone a deworming medicine or assume pinworms are present.
Kantesti is an AI-powered blood test analysis tool that can help explain accompanying laboratory results while stool-management decisions remain with the clinician. Keep the symptom diary, medicine list, and test dates together as 3 distinct records; our eisimpleir de shruth-obrach mìneachaidh describe educational workflows rather than evidence that our service treats intestinal parasites.
A shared household record should respect consent and minimize unnecessary identifiers. If 2 family members have symptoms, each person's clinical assessment and treatment decision remain separate; our prìobhaideachd agus cleachdaidhean dàta explain how we approach information handling, but your clinician's secure communication channel should be used for prescribing and urgent advice.
What should you ask your clinician, and which research supports the decision?
Ask whether Dientamoeba fragilis plausibly explains your symptoms, which alternatives need checking, and what benefit would justify treatment. The most useful evidence separates symptom outcomes from organism eradication; a 10-day treatment course and a negative follow-up test are not, by themselves, proof of clinical benefit.

Bring 4 items to the appointment: the full stool report, a medication list, a symptom timeline, and any relevant accompanying laboratory results. Ask what would change the decision—another pathogen, celiac antibodies, a concerning calprotectin result, or spontaneous improvement—and agree on when to return if symptoms persist or warning signs develop.
A 7-day diary can make observation an active plan rather than doing nothing. Maintain fluids and tolerated foods; oral rehydration solution can help replace diarrheal losses, but restrictive diets, herbal parasite cleanses, and supplements have no established role in eradicating Dientamoeba fragilis and should not delay investigation of persistent symptoms.
An 3 external sources below have different evidentiary roles: CDC provides clinical prescribing guidance, Röser et al. provide randomized pediatric symptom-outcome evidence, and van Hellemond et al. provide retrospective adult eradication data. Kantesti applies inbhean susbaint mheidigeach that distinguish these study designs instead of presenting them as equally strong proof.
An 2 Figshare publications listed below are general educational resources, not trials of Dientamoeba fragilis treatment; the women's health guide does not provide direct evidence for this decision. A DOI establishes a persistent identifier, not clinical validation, and our technical and clinical methodology should likewise not be mistaken for proof that AI can establish the cause of digestive symptoms.
Ceistean cumanta
A bheil PCR dearbhach airson Dientamoeba fragilis a’ ciallachadh gu bheil feum agam air antibiotaicean?
Chan eil toradh PCR dearbhach airson Dientamoeba fragilis a’ ciallachadh gu fèin-obrachail gu bheil feum agad air làimhseachadh mì-mhicrobialach. Mar as trice, chan fheum daoine aig nach eil comharraidhean cungaidh-leigheis, agus chan urrainn do 1 toradh dearbhach bho shampall stòil a-mhàin adhbhar nan comharraidhean cnàmhaidh a stèidheachadh. Faodaidh luchd-clionaigeach beachdachadh air làimhseachadh ma mhaireas na comharraidhean, ma chaidh adhbharan eile a mheasadh, agus ma tha coltas reusanta ann gu bheil an dìosganach buntainneach. Feumar measadh a dhèanamh air pian mòr, dìth-uisgeachaidh no fuil anns an stòl a bharrachd air toradh na PCR.
An urrainn do Dientamoeba fragilis falbh às aonais leigheis?
0. Faodaidh lorg Dientamoeba fragilis fàs àicheil gun làimhseachadh, agus faodaidh na comharraidhean cnàmhaidh fàs nas fheàrr cuideachd gu neo-eisimeileach bho bhith a’ cur às don fhàs-bheairt. Faodaidh leabhar-latha chomharran thar 7 làithean cuideachadh le bhith a’ clàradh leasachaidh nuair a tha e iomchaidh sùil a chumail air an t-suidheachadh. Chan eil faighinn seachad air gu nàdarra no PCR àicheil nas fhaide air adhart a’ dearbhadh gur e am fàs-bheairt a dh’adhbhraich an tinneas tùsail. Bu chòir ath-mheasadh a dhèanamh air comharraidhean a mhaireas no a dh’fhàsas nas miosa, seach feitheamh gun chrìoch.
Dè an làimhseachadh as fheàrr airson Dientamoeba fragilis?
Chan eil leigheas as fheàrr air a dhearbhadh gu h-uile-choitcheann airson faochadh a thoirt do chomharran anns gach euslainteach aig a bheil Dientamoeba fragilis dearbhach. Tha stiùireadh an CDC do dh’inbhich a’ moladh paromomycin aig 25–35 mg/kg/latha ann an 3 dòsan roinnte fad 7 làithean, agus tha metronidazole na roghainn eile. Tha fianais ath-sheallach a’ fàbharachadh paromomycin airson cur às don fhàs-bheairt, ach chan eil cur às don fhàs-bheairt an aon rud ri leasachadh nan comharran. Feumaidh an neach-òrdachaidh an roghainn a dhèanamh fa leth a rèir aois, torrachas, tinneasan meidigeach agus eadar-obrachaidhean le cungaidhean.
Carson a tha comharraidhean agam fhathast às dèidh làimhseachadh airson Dientamoeba fragilis?
Dh’fhaodadh comharraidhean leantainneach an dèidh làimhseachadh Dientamoeba fragilis a bhith a’ ciallachadh nach b’ e am fàs-bheairt prìomh adhbhar nan comharraidhean, gu bheil suidheachadh eile ann, no nach do ghlan an làimhseachadh an galar. Chan eil toradh PCR àicheil a’ dùnadh a-mach galar celiac, a’ bhuinneach a tha co-cheangailte ri cungaidhean-leigheis, colitis mhicroscopach, no eas-òrdugh gnìomhachail a’ bhroinn. Mar as trice, feumar measadh eagraichte air a’ bhuinneach leantainneach ma mhaireas i 4 seachdainean no nas fhaide. Bu chòir cùrsa eile de chungaidh-leigheis a leantainn às dèidh ath-mheasaidh, seach a bhith ga òrdachadh dìreach air sgàth ’s gu bheil na comharraidhean a’ leantainn.
Should children with Dientamoeba fragilis be treated?
Children with Dientamoeba fragilis should not be treated automatically on the basis of a positive stool PCR. A randomized trial of 96 children aged 3–12 years found no better clinical outcomes with a 10-day metronidazole course than with placebo. Pediatric decisions should consider persistent symptoms, hydration, growth, alternative diagnoses, and drug-specific safety. Growth faltering or a clearly unwell child needs clinical assessment regardless of the parasite result.
Should my family be tested or treated if my result is positive?
A single Dientamoeba fragilis-positive household member does not automatically justify testing or treating every contact. Asymptomatic detection generally does not require treatment, while 2 or more people with persistent compatible symptoms may justify a household discussion with a clinician. Soap-and-water handwashing for about 20 seconds is reasonable general hygiene, but it is not a proven guarantee against Dientamoeba recurrence. Pinworm assessment is a separate decision rather than an automatic consequence of positive PCR.
Faigh mìneachadh air na toraidhean deuchainn fala agad
Luchdaich suas aithisg an obair-lann agad agus mìnichidh AI Kantesti gach bith-chomharradh ann an cànan soilleir taobh a-staigh diogan. Air a chleachdadh le còrr is 2 mhillean neach air feadh an t-saoghail.
Tùsan
- Klein, T., Mitchell, S., & Weber, H. (2026). Buinneach an dèidh Fastadh, Speicean Dubha anns an Stòl agus Iùl GI 2026. Rannsachadh Meidigeach AI Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Iùl Slàinte nam Ban: Ubhachadh, Menopause agus Comharraidhean Hormonail. Rannsachadh Meidigeach AI Kantesti. DOI
- Ionadan airson Smachd agus Bacadh Galaran (2024). Clinical Care of Dientamoeba fragilis. CDC Clinical Guidance.
- Röser D et al. (2014). Metronidazole Therapy for Treating Dientamoebiasis in Children Is Not Associated With Better Clinical Outcomes: A Randomized, Double-Blinded and Placebo-Controlled Clinical Trial. Galaran Clionaigeach Gabhaltach. DOI
- van Hellemond JJ et al. (2012). Is paromomycin the drug of choice for eradication of Dientamoeba fragilis in adults? International Journal for Parasitology: Drugs and Drug Resistance.
- 2M+Deuchainnean air an sgrùdadh
- 127+Dùthchannan
- 100+Cànanan
Mu dheidhinn an sgioba mheidigeach


Comharran earbsa E-E-A-T
Eòlas
Lèirmheas clionaigeach air a stiùireadh le lighiche air sruthan-obrach mìneachaidh obair-lann.
Eòlas
Fòcas air leigheas obair-lann air mar a bhios bith-chomharraidhean (biomarkers) a’ giùlan ann an co-theacsa clionaigeach.
Ùghdarrasachd
Ath-sgrùdadh meidigeach leis an Dr Thomas Klein, le tabhartasan bhon Dr Sarah Mitchell agus an t-Oll. Dr Hans Weber.
Earbsachd
Mìneachadh stèidhichte air fianais le slighean leanmhainn soilleir gus dragh a lughdachadh.






Àicheadh meidigeach
Tha an artaigil seo dìreach airson adhbharan foghlaim agus chan eil e a’ dèanamh comhairle mheidigeach. Cuir fios an-còmhnaidh gu solaraiche cùram slàinte teisteanasach airson co-dhùnaidhean breithneachaidh is leigheis.
Foillsichte · Cuir fios chun sgioba dheasachaidh
Foillsichte le Kantesti Ltd, clàraichte ann an Sasainn agus sa Chuimrigh, àireamh companaidh. 17090423, Lunnainn, an Rìoghachd Aonaichte.
