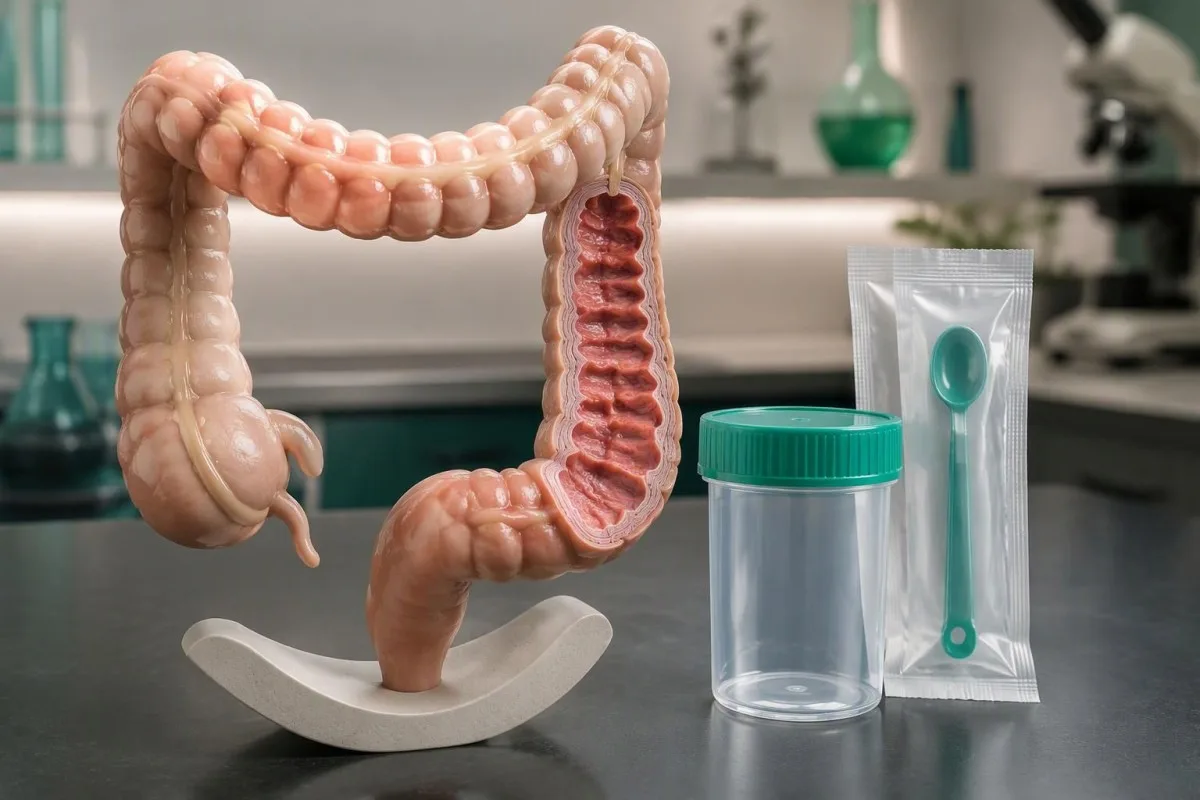
Do mhòr-chuid dhaoine, chan fhiach deuchainn microbiome caolainn a cheannach gus IBS a dhearbhadh no stuthan cur-ris a thaghadh. Tha e a 'toirt cunntas air DNA microbial ann an aon sampall feces, ach chan urrainn dha sgòr caolainn fallain uile-choitcheann a stèidheachadh no ro-innse gu earbsach dè an làimhseachadh a chuidicheas.


- Luach clionaigeach an crochadh air an atharraich toradh cùram; chan eil tomhas-lìn aig a bheil gabhail ris gu farsaing aig cunntas-sluaigh microbiome luchd-cleachdaidh airson IBS.
- Coimeas tomhas a 'tomhas roinn de shreathan air an seòrsachadh: 10% chan eil e a 'ciallachadh 10% de na bacteria beò gu lèir air feadh do shlighe cnàmhaidh.
- Modhan sreathachaidh eadar-dhealaichte: tha sgrùdadh 16S a 'cuimseachadh air gine comharra bacterial, fhad' sa tha sgrùdadh shotgun a 'samplachadh DNA nas fharsainge.
- Sgòran measgachadh an crochadh air an obair-obrach cunntais agus obair-lann; chan e tomhas meidigeach àbhaisteach a th' ann an sgòr de 70/100.
- Dearbhadh IBS mar as trice a 'cleachdadh pian bhoilg ath-chuairteachaidh a' cuibheasachadh co-dhiù 1 latha san t-seachdain anns na 3 mìosan roimhe seo, còmhla ri slatan-tomhais clionaigeach eile.
- Calprotectin fecal fo-ìsle nas 50 µg/g mar as trice air a mheas mar ìosal ann an inbhich, ach tha raointean obair-lann agus comharran rabhaidh fhathast cudromach.
- Elastase an stòil fo-ìsle 100 µg/g a’ toirt taic do dhroch obair pancreatic exocrine nuair a thèid a thomhas ann an sampall freagarrach; faodaidh sampallan uisgeach toraidhean a tha a’ coimhead nas ìsle a thoirt gu buil.
- Taghadh cur-ris chan urrainn gu earbsach lean an gnàthas bacterial a-mhàin; tha comharran, dearbhadh air tinneasan, buaidhean cungaidh-leigheis agus dìth air a nochdadh nas fheàrr mar phuingean tòiseachaidh.
Cuin a tha deuchainn microbiome caolainn airidh air pàigheadh?
A deuchainn microbiome gut is fhiach airgead a phàigheadh mar iongnadh no eacarsaich rannsachaidh, ach mar as trice chan ann mar inneal dearbhaidh no taghaidh làimhseachaidh. Air 6 Dàmhair 2026, tha an eadar-dhealachadh a ghabhas dìon eadar a’ toirt cunntas air 1 sampall stòl agus a’ nochdadh gu bheil gnìomh air an aithisg aige a’ leasachadh slàinte.
Chan eil aithisgean sreathachaidh luchd-cleachdaidh a’ dearbhadh IBS gu earbsach, ag aithneachadh adhbhar bloating, no a’ taghadh probiotic pearsanta. Tha an aithris aonta eadar-nàiseanta air deuchainn microbiome a’ toirt cunntas air cnapan-starra mòra gu cleachdadh clionaigeach cunbhalach, a’ gabhail a-steach gnàthachadh agus feum clionaigeach air a nochdadh (Porcari et al., 2025); chan eil a bhith a’ lorg eadar-dhealachaidhean eadar buidhnean an aon rud ri bhith a’ dearbhadh 1 neach fa-leth.
tha Kantesti na inneal-anailisidh fala AI, chan e seirbheis sreathachaidh stòil. Is mise Thomas Klein, Oifigear Meidigeach an Àrd, agus is e mo chomhairle 3 ceistean a sgaradh: dè a chaidh a thomhas, ciamar a tha e ath-riochdachail, agus an atharraicheadh am freagairt cùram? Ar cùl-fhiosrachadh companaidh a’ mìneachadh ar fòcas air deuchainn fala.
Faodaidh pasgan teòiridheach £180 a thighinn gu bhith na cheannach mòran nas motha ma tha an aithisg a’ moladh cur-ris mìosail £60 agus deuchainn a-rithist gach 3 mìosan. Tha na figearan sin a’ sealltainn duilgheadas buidseit, chan e meas prìs margaidh: tha a’ chosgais bhrìoghmhor a’ toirt a-steach a h-uile càil a bhios an aithisg thùsail gad chreidsinn ri cheannach.
Faodaidh neach inbheach asymptomatic a tha a’ còrdadh ris a’ bhith-eòlas gabhail ris gu reusanta ris an sin neo-chinnt. Feumaidh cuideigin le 6 seachdainean de bhuinneach leantainneach còmhradh eadar-dhealaichte: measadh meidigeach, deuchainn amas, agus plana nach eil an urra ri bhith a’ leasachadh sgòr sunnd dìon-fearainn.
Dè dìreach a tha deuchainn microbiome feces a 'tomhas?
A deuchainn microbiome stòl mar as trice a’ tomhas DNA microbial air fhaighinn air ais bho shampall stòl beag. Tha an dà phrìomh dhòigh-seachain—sreathachaidh gine RNA ribosomal 16S agus sreathachaidh metagenomic shotgun—eadar-dhealaichte anns na as urrainn dhaibh aithneachadh, ach chan eil gin dhiubh sin a’ tomhas gu dìreach gach beò-bheairt a tha beò no a ghnìomhachd air feadh a’ ghalair.
sreathachaidh 16S a’ tadhail air gine comharra a thathas a’ cleachdadh gus bacteria a chlasachadh agus, le dòighean freagarrach, archaea. Bidh diofar roinnean caochlaideach agus prìomhairean a’ faighinn air ais diofar bhuidhnean; chan eil dearbh-aithne ìre gnè a’ stèidheachadh dè an gnè no an sìol a tha an làthair, agus chan urrainn do dhìol-slàinte air sìol-shònraichte leantainn gu fèin-ghluasadach bho 1 ainm gnè.
sreathachaidh Shotgun a’ sampaileadh DNA nas fharsainge agus is urrainn dha ginean microbial a chomharrachadh, uaireannan le rùn gnè nas fheàrr. Ach, chan eil a bhith a’ lorg 1 gine co-cheangailte ri slighe metabolic a’ sealltainn gu bheil an t-slighe gnìomhach, gu bheil an toradh aige a’ ruighinn do phrìomh chorp, no gum biodh atharrachadh air a’ chomharran a’ leasachadh.
Tha stòl a’ riochdachadh stuth a tha a’ fàgail an colon, chan e liosta iomlan den innidh bheag no de bhuidhnean a tha a’ greimeachadh air mucus innidh. Mar sin, faodaidh sampall air a chruinneachadh air 1 mhadainn a bhith brosnachail gu teicnigeach fhad ‘s a tha e a’ seachnadh an àite anatomical a tha buntainneach don cheist clionaigeach—gu sònraichte nuair a tha cuideigin a’ faighneachd mu chomharran innidh bheag.
Faodaidh aithisg a bhith a’ measgachadh bhuidhnean a chaidh a lorg, tomhasan tuairmseach agus gnìomhan ro-innse mar gum biodh iad nan tomhasan co-ionann. Chan eil iad. An stiùireadh againn gu toraidhean càileachdail agus cainneachdail a’ mìneachadh carson a tha aithneachadh rudeigin agus tomhas an tomhas aige a’ freagairt air 2 cheist eadar-dhealaichte.
Dè tha ceudadan àireamhachd bacterial a 'ciallachadh dha-rìribh?
Coimeas tomhas tha e na chuibhreann den organism de na sreathan a tha air an gabhail a-steach ann an àireamhachadh obair-lann, chan e cunntas iomlan de bacteria beò. Ma tha 20 de 100 leughaidhean air an clàradh buinteach do aon bhuidheann, is e 20% an cunntas a thathas ag aithris; tha an t-ainmiche a’ dearbhadh dè tha an ceudad sin a’ ciallachadh.
Faodaidh ceudad a dhol sìos gun an gnìomh fhèin a’ lughdachadh. Ann an eisimpleir sìmplidh, tha 20 leughaidhean co-cheangailte am measg 100 leughaidhean iomlan a’ toirt 20%, fhad ‘s a tha 20 am measg 200 a’ toirt 10%; dh’ fhaodadh an dàrna toradh nochdadh leudachadh air buidhnean eile seach dìth a’ chiad fheadhainn.
Absolute microbial load requires additional measurement, such as calibrated quantitative PCR, flow cytometry or a validated spike-in approach. Even then, stool water content and the reporting denominator matter: copies per gram of wet stool and copies per gram of dry stool are 2 different quantities.
A report stating that an organism is absent usually means it was not detected above that workflow’s threshold. If an organism has a true read fraction of 0.01% and only 1,000 relevant reads are sampled, missing it is unsurprising; non-detection should not trigger a diagnosis of bacterial deficiency.
The same reasoning applies when percentages distract from absolute blood-cell counts, as explained in our count versus percentage guide. For microbiome reports, ask 2 practical questions: what entered the denominator, and were unclassified reads excluded?
A bheil sgòr nas àirde de dhiofar microbiome a 'ciallachadh slàinte nas fheàrr?
A higher microbiome diversity score does not automatically mean better digestive health. Diversity summarizes features such as richness and evenness; it does not identify whether organisms are helpful, harmful or clinically relevant, and a proprietary 0–100 score has no universal medical interpretation.
Richness counts detected categories, while evenness describes how balanced their proportions are. A sample with 100 detected species dominated by 1 species may have high richness but low evenness; sequencing depth and the taxonomic level chosen can change both calculations.
The Shannon index combines richness and evenness. Using natural logarithms, 2 equally abundant categories produce approximately 0.69 and 4 produce approximately 1.39; these are mathematical examples, not healthy-gut thresholds, and values calculated at genus level should not be compared directly with species-level values.
Bowel transit complicates the interpretation because stool consistency is associated with microbiome composition. Recording stool form for 7 days can reveal whether a score is being compared across very different bowel states; the Clàr stòl Bristol provides a practical vocabulary.
A reference cohort also shapes the result: a percentile against 500 self-selected customers is not equivalent to a percentile against a carefully characterized population. Ask whether the comparator matches your age, geography, medications and bowel habits before treating an 18th-percentile result as a problem.
Carson a dh'fhaodas dà sholaraiche microbiome toraidhean eadar-dhealaichte a thoirt seachad?
Two providers can give different results from the same stool because their collection, DNA extraction, sequencing and computational workflows differ. At least 4 layers can change a report before clinical interpretation begins; disagreement does not necessarily mean that either laboratory mixed up the specimen.
DNA extraction is a major source of variation because bacterial cell walls differ in how easily they break open. Costea and colleagues demonstrated why fecal sample processing needs standardization (Costea et al., 2017); insufficient mechanical disruption can under-represent some organisms even when 2 laboratories sequence equal amounts of extracted DNA.
Transport introduces another variable: an unstabilized sample spending 48 hours at room temperature is not equivalent to a sample immediately placed in a validated preservative. The correct handling conditions are kit-specific; refrigeration is not automatically appropriate when a collection system was designed and validated for ambient shipping.
Reference databases and software versions can reassign the same sequence. One provider may report a species while another reports only its genus, and 2 health scores may use different proprietary weighting systems; apparently conflicting recommendations can arise from the scoring rules rather than the underlying biology.
A specimen problem can undermine interpretation even when the instrument works correctly, a principle illustrated by our stiùireadh eadar-theachd sampall. If comparing results, document collection time, preservative, recent medicines and the pipeline version—not just the final percentage.
Ciamar a bu chòir dhut cruinneas deuchainn microbiome caolainn a bhith a' breithneachadh?
Gut microbiome test accuracy has 3 separate meanings: analytical validity, clinical validity and clinical utility. A laboratory may accurately detect microbial DNA without accurately diagnosing a condition or proving that its recommended treatment improves outcomes; a single percentage labelled accuracy cannot resolve those distinctions.
Analytical validity asks whether the workflow measures what it claims to measure. Useful evidence includes known-composition microbial controls, extraction blanks, contamination controls, detection limits and duplicate precision; processing 1 sample twice is helpful, but it does not test every source of variation from home collection onward.
Clinical validity asks whether a result distinguishes people with and without a defined condition in relevant populations. An algorithm evaluated in 200 people already known to have severe disease may perform differently in 200 primary-care patients with overlapping symptoms; spectrum and selection bias matter.
Clinical utility asks whether using the report improves a patient outcome compared with appropriate usual care. Porcari et al. (2025) distinguish research promise from readiness for routine application; a prettier report or a change in 1 bacterial percentage is not itself evidence of less pain or better nutrition.
Ar duilleag inbhean clionaigeach concerns blood-result interpretation and should not be read as validation of consumer stool sequencing. For any health report, the accuracy assessment checklist helps separate technical performance from claims that require patient-outcome studies.
An urrainn do aithisg microbiome IBS a dhearbhadh no brùthadh a mhìneachadh?
A consumer microbiome report cannot diagnose irritable bowel syndrome, and no bacterial abundance cutoff reliably establishes IBS in routine practice. Commonly used Rome IV criteria include abdominal pain averaging at least 1 day weekly in the previous 3 months, with symptom onset at least 6 months earlier.
Rome IV also requires pain associated with at least 2 of 3 features: defecation, changed stool frequency, or changed stool form. These criteria support a positive clinical diagnosis, but warning signs and alternative explanations still require assessment; painless bloating alone does not meet the IBS pain criterion.
The ACG guideline supports a positive diagnostic strategy rather than endless exclusion testing, with celiac testing and inflammatory-marker assessment in appropriate patients with diarrhea symptoms (Lacy et al., 2021). A microbiome score is not one of those diagnostic criteria, even if a report associates 1 organism with IBS.
Consider a hypothetical 34-year-old with bloating, loose stools and low iron stores: celiac disease deserves consideration before a recommendation to remove gluten. Testing commonly includes tissue transglutaminase IgA and total IgA, because low IgA can mislead an IgA-based result.
Kantesti AI should not turn an unvalidated stool score into an IBS diagnosis or a claim of small-intestinal bacterial overgrowth. Anyone already avoiding gluten should discuss testing preparation rather than improvise a challenge; our stiùireadh ullachaidh deuchainn celiac explains why duration and intake affect interpretation.
Dè na deuchainnean clionaigeach feces a fhreagras air barrachd cheistean feumail?
Clinical stool diagnostics investigate defined problems, such as intestinal inflammation, pancreatic enzyme output, pathogens or occult bleeding. They are different from microbiome profiling; fecal calprotectin, for example, is commonly reported in µg/g with assay-specific interpretation, whereas a bacterial diversity score has no comparable universal diagnostic threshold.
Calprotectin fecal reflects intestinal neutrophil activity, not microbiome diversity. Many adult laboratories use below 50 µg/g as a low result, but infection, NSAID exposure and other conditions can raise it; our calprotectin and lactoferrin comparison explains their overlapping clinical roles.
An intermediate calprotectin result often needs context and sometimes a repeat after about 2–6 weeks, depending on the local pathway. Persistent symptoms or alarm features may justify earlier investigation, so our borderline calprotectin guide should not be used to postpone assessment.
Fecal elastase estimates pancreatic exocrine output: above 200 µg/g is generally reassuring, 100–200 µg/g is indeterminate, and below 100 µg/g supports insufficiency in an appropriate specimen. The stool elastase interpretation guide explains why dilution and pretest probability matter.
A provider may bundle 1 clinically established assay with several exploratory scores in the same package. That does not validate the entire package: judge each component separately, and remember that normal calprotectin does not exclude every bowel disorder or replace colorectal-cancer evaluation when indicated.
An urrainn do shreath luchd-cleachdaidh fallas caolainn a riaghladh gu earbsach?
Consumer microbiome sequencing cannot reliably rule out a gut infection unless the specific pathogen claim has been clinically validated. Targeted stool PCR, antigen assays, toxin testing and culture answer different questions; 3 or more new unformed stools in 24 hours may prompt assessment for C. difficile in the right clinical setting.
C. difficile testing needs symptoms and risk context because detecting a toxin gene can identify colonization as well as illness. Recent antibiotics, healthcare exposure and laxative use influence the decision; 1 positive molecular result does not automatically establish toxin-mediated disease or justify treatment.
Travel-associated diarrhea may require targeted testing for Giardia or other pathogens based on exposure and symptom duration. A report that simply lists an organism among hundreds lacks the same clinical meaning as a validated diagnostic assay, and 1 negative consumer profile cannot safely exclude it.
H. pylori stool antigen testing is an example of a directed assay with established uses. Proton pump inhibitors generally need to be withheld for 2 weeks and antibiotics or bismuth for 4 weeks before testing when clinically safe; prescribed medicines should not be stopped without advice.
Acid-suppressing medicines can also affect symptoms, microbiome composition and other laboratory results. Our PPI and gastrin guide illustrates why medication history belongs in the interpretation rather than being reduced to 1 report note about an altered bacterial community.
Dè na comharran a bu chòir a bhith aig prìomhachas thairis air deuchainn microbiome?
Visible blood, black tarry stool, unexplained weight loss, anemia, persistent nighttime diarrhea or severe abdominal pain should take priority over a consumer microbiome test. A reassuring bacterial score provides no safety clearance; heavy bleeding, fainting, severe dehydration or rapidly worsening pain warrants urgent assessment.
A normal microbiome report cannot exclude colorectal cancer, inflammatory bowel disease or a clinically significant source of bleeding. Even 1 episode of black tarry stool needs assessment when gastrointestinal bleeding is plausible; our stool bleeding urgency guide distinguishes color changes from concerning patterns.
A positive FIT detects human hemoglobin in stool and requires follow-up through the relevant diagnostic pathway; repeating a microbiome kit does not answer why it is positive. The positive FIT next steps explain why a screening or symptomatic result cannot be dismissed by an unrelated score.
Risk depends on age, family history and symptom trajectory, not just a single duration cutoff. A hypothetical 62-year-old with 8 weeks of new bowel-habit change and weight loss needs prompt clinical review even if a consumer report rates diversity as excellent.
Severe diarrhea can cause kidney and electrolyte complications before its cause is known. Fewer trips to urinate, dizziness on standing or inability to keep fluids down for several hours should shift attention toward hydration and medical assessment—not toward whether 1 bacterial genus appears unusually abundant.
An urrainn do thoraidhean microbiome probiotics no stuthan cur-ris pearsanaichte a thaghadh?
A microbiome report alone cannot reliably select a personalized probiotic, prebiotic or vitamin regimen. A low bacterial percentage is not a diagnosed deficiency, and benefits depend on the indication, exact formulation and sometimes strain; 1 genus name does not establish which supplement will help.
The ACG guideline suggests against probiotics for global IBS symptoms because the evidence is very uncertain, while supporting soluble fiber (Lacy et al., 2021). That recommendation does not prove that every probiotic is ineffective; it means that confidence in routinely recommending 1 product for IBS remains limited.
A cautious soluble-fiber trial may start with about 3–5 g of psyllium daily and increase gradually according to tolerance and product instructions. Take it with adequate fluid—often at least 250 mL per dose—and seek advice for swallowing difficulty or obstruction risk; adding several fermentable products at once makes symptom attribution harder.
Vitamin or mineral needs require dietary and clinical assessment, not a microbial vitamin-production prediction. In the United States, the adult zinc upper intake level is 40 mg/day from all sources; sustained excess can cause copper deficiency, as our high zinc safety guide a’ mìneachadh.
Kantesti is an AI blood test interpretation platform that helps place measured blood results in context; microbial genes cannot establish serum B12, iron stores or magnesium status. Our evidence-based food choices can support dietary variety, but 1 restrictive plan is not appropriate for every digestive condition.
Ciamar a bheir cruinneachadh, ath-dheuchainn agus prìobhaideachd buaidh air luach?
Collection quality, repeat-test consistency and data handling affect whether a microbiome purchase is useful. Follow the specific kit instructions, keep a record of relevant exposures, and avoid treating a change between 2 samples as proof of improvement when collection conditions or analytical methods also changed.
Recent antibiotics, bowel preparation, acute diarrhea and major dietary changes can alter the sample’s context. There is no universal evidence-based waiting interval—such as exactly 4 weeks—that makes every microbiome test representative again; document dates and discuss the question rather than stopping a necessary treatment to improve a score.
Repeated samples are easier to interpret when provider, kit, handling and bowel state remain comparable. Keeping a 7-day record of symptoms, stool form, diet changes and medicines may be more useful than purchasing a repeat immediately; our stiùireadh comharraidhean cnàmhaidh explains common contextual clues.
Privacy questions should cover both the physical specimen and the digital data. Ask 4 things before paying: how long each is retained, whether secondary research use is optional, whether third-party sharing occurs, and whether deletion covers raw sequencing files as well as the account.
Shotgun sequencing can capture human DNA alongside microbial DNA, so human-read filtering and retention policies deserve scrutiny. A GDPR-aligned statement alone does not answer every processing question; request the actual consent terms, hosting arrangements and cross-border safeguards before sending 1 specimen that may generate extensive data.
Dè a bu chòir dhut a dhèanamh ma tha aithisg microbiome agad mu thràth?
If you already have a microbiome report, separate established clinical assays from exploratory scores and prioritize symptoms over bacterial rankings. Write down 3 items before making changes: the problem you want to improve, the evidence for the proposed intervention, and the outcome that would justify continuing it.
The first step is to inventory the report rather than accept its overall traffic-light rating. A package containing calprotectin in µg/g, bacterial relative abundance in percent and a wellness score out of 100 contains 3 different types of information; each needs its own interpretation and evidence.
Choose 1 measurable outcome for a reasonable trial: weekly pain days, stool frequency, urgency episodes or the ability to tolerate a food. A hypothetical 4-week intervention that improves symptoms without changing a diversity score may still be useful; the reverse pattern does not establish patient benefit.
Kantesti is an AI-powered blood test analysis tool, not a substitute for a digestive diagnosis. Our mìneachadh teicneòlas AI describes how blood-result interpretation works; ferritin, a CBC or electrolytes may answer specific clinical questions, but there is no validated blood panel that reveals your ideal bacterial balance.
My practical recommendation, as Thomas Klein, is to bring the original report and a 7-day symptom record to the clinician rather than a shopping list of recommended supplements. Do not add antibiotics, antifungals or restrictive diets solely because 1 organism was flagged; agree on what would trigger reassessment or specialist referral.
Foillseachaidhean rannsachaidh agus crìochan eadar-mhìneachaidh AI
Research on AI blood-result interpretation does not validate consumer microbiome diagnosis or personalized supplement selection. The 2 company-supplied Figshare records below concern blood-test workflows; neither title establishes that stool-sequencing recommendations improve digestive symptoms, detect IBS or identify an individual’s optimal probiotic.
Kantesti’s supplied technical benchmark is described as evaluating 100,000 synthetic test cases. Synthetic-case performance can examine defined technical behavior, but it is not equivalent to diagnostic accuracy in consecutive real patients; independent reproduction, representative clinical data and patient outcomes require separate evaluation.
The supplied hantavirus report describes engineering validation and deployment across 50,000 interpreted blood-test reports. Deployment volume does not by itself establish sensitivity, specificity or outcome benefit, and a triage workflow for 1 infectious condition cannot be generalized to microbiome profiling without new evidence.
The formal citations below use n.d. because publication dates were not supplied; their linked records should be checked for authorship, version and review status. ResearchGate and Academia.edu links are DOI search routes, not claims that 2 verified copies exist there, and repository availability should not be mistaken for journal peer review.
Clinical accountability remains separate from publication count or sample volume. Our bòrd comhairleachaidh meidigeach page describes medical governance; the decision standard remains whether a particular test answers the patient’s question, with limitations explained before purchase rather than after 1 unexpected result.
Ceistean Bitheanta
0 A bheil luach ann an deuchainnean meanbh-bhitheam a’ ghut?
0 Mar as trice chan fhiach deuchainnean meanbh-bhitheòim na caolain a cheannach airson IBS a dhearbhadh no leasachaidhean pearsanaichte a thaghadh. Faodaidh iad cunntas a thoirt air DNA meanbh-fhàs-bheairtean ann an 1 sampall stòil, ach sa chumantas chan eil stairsnich breithneachaidh stèidhichte no feum dearbhte ann an taghadh leigheis aig sgòran luchd-cleachdaidh. Beachdaich air cosgais iomlan a’ phasgain, nan deuchainnean ath-aithris agus nam bathar a thathar a’ moladh mus ceannaich thu e. Tha e nas fheàrr dèiligeadh ri comharraidhean leantainneach tro mheasadh clionaigeach agus deuchainnean cuimsichte a fhreagras ceist shònraichte.
Dè cho ceart ’s a tha deuchainn air meanbh-bhitheam a’ chaolain?
Tha cruinneas deuchainn micribhioma na caorach an crochadh air 3 ceistean air leth: a bheil an obair-lann a' tomhas DNA miocrobaidh ceart, a bheil an toradh a' ro-innse staid clionaigeach, agus a bheil gnìomh air a leasachadh thoraidhean. Faodaidh cruinneachadh, toirt air falbh DNA, doimhneachd sreathachaidh agus stòran-dàta iomraidh atharrachadh air an àireamh a chaidh aithris. Chan eil toradh a ghabhas ath-riochdachadh gu teicnigeach a' toirt seachad dearbhadh earbsach gu fèin-obrachail. Faighnich airson dearbhadh air an tagradh sònraichte seach gabhail ri aon sa cheud cruinneas iomlan.
An urrainn do dheuchainn mhicro-bhioma an caill a bhith a' breithneachadh air IBS?
Chan urrainn deuchainn air meanbh-bheò-eòlas caolain luchd-cleachdaidh IBS a dhearbhadh a’ cleachdadh ìre bacterial stèidhichte. Tha na slatan-tomhais Rome IV a thathas a’ cleachdadh gu cumanta a’ toirt a-steach pian bhoilg ath-chuairteach air cuibheasach co-dhiù 1 latha san t-seachdain anns na 3 mìosan roimhe seo, toiseach comharran co-dhiù 6 mìosan roimhe seo, agus atharrachaidhean caolain co-cheangailte. Bidh luchd-clionaigeach cuideachd a’ measadh chomharran rabhaidh agus a’ beachdachadh air deuchainnean targaid, a’ toirt a-steach deuchainn celiac ann an euslaintich iomchaidh le a’ bhuinneach. Chan eil pròifileadh meanbh-bheò-eòlais a’ dol an àite a’ mheasaidh sin.
Dè an sgòr àbhaisteach airson measgachadh microbiome?
Chan eil sgòr àbhaisteach uile-choitcheann aig microbiome airson euslainteach fa leth. Chan eil sgòr seilbhe de 70/100 ach cudromach taobh a-staigh cunntas an t-solaraiche agus an sluagh iomraidh, chan ann mar bhreithneachadh àbhaisteach. Tha beairteas, cothromachd, doimhneachd sreathachaidh agus an ìre a thaobh gnèithean a’ toirt buaidh air tomhais iomadachd. Chan eil iomadachd nas àirde gu fèin-ghluasadach nas fheàrr, agus chan eil sgòr ìosal leis fhèin a’ gealltainn stuthan cur-ris no cungaidh-leigheis.
A bheil deuchainn microbiome mar an ceudna ri deuchainn stòil bhon dotair agam?
Tha pròifileadh an microbiome eadar-dhealaichte bho dheuchainn clionaigeach stòil airson suidheachadh sònraichte. Bidh calprotectin fecal gu tric a’ cleachdadh nas ìsle na 50 µg/g mar thoradh ìosal inbheach, fhad ‘s a bhios elastase fecal nas ìsle na 100 µg/g a’ toirt taic do dhroch ghnìomhachd pancreatic ann an sampall iomchaidh. Bidh modhan pathogen targaid agus FIT a’ sgrùdadh cheistean sònraichte eile. Faodaidh pasgan malairteach a bhith a’ toirt a-steach modhan stèidhichte agus sgòran rannsachaidh, mar sin feumar gach co-phàirt a mheasadh air leth.
An urrainn do thoraidhean mo mhicribiome innse dhomh dè am probiotic a ghabhas mi?
Chan eil toraidhean an microbiome ag aithneachadh gu earbsach an probiotic as coltaiche a chuidicheas neach. Chan eil lorg air ìre ìosal de 1 ghineas bacterial a’ stèidheachadh dìth no a’ sealltainn gum bi slugadh organaich co-cheangailte a’ leasachadh comharraidhean. Tha fianais probiotic an urra ris an comharra, an cruthachadh agus uaireannan an strain sònraichte. Airson IBS, tha stiùireadh ACG 2021 a’ moladh an aghaidh probiotics airson comharraidhean cruinneil leis gu bheil an fianais taice glè mì-chinnteach.
Faigh Mion-sgrùdadh Deuchainn Fala le Cumhachd AI an-diugh
Thig còmhla ri còrr is 2 mhillean neach air feadh an t-saoghail a tha a’ earbsa Kantesti airson mion-sgrùdadh sa bhad, ceart air deuchainnean obair-lann. Luchdaich suas na toraidhean deuchainn fala agad agus faigh mìneachadh coileanta air biomarcair 15,000+ ann an diogan.
📚 Foillseachaidhean Rannsachaidh le Iomraidhean
Klein, T., Mitchell, S., & Weber, H. (2026). Taic Co-dhùnaidh Clionaigeach Le Taic AI Ioma-chànanach airson Triàsadh Hantavirus Tràth: Dealbhadh, Dheimhinneachadh Innleadaireachd, agus Cur an sàs san t-Saoghal Fìor thairis air 50,000 Aithisg deuchainn fala eadar-theangaichte. Rannsachadh Leigheis AI Kantesti.
Klein, T., Mitchell, S., & Weber, H. (2026). Sgrùdadh Teicnigeach fèin-ghluasadach stèidhichte air Rubric a chaidh a chlàradh ro-làimh de Inneal Mìneachaidh Deuchainn Fala Kantesti air 100,000 cùis deuchainn fuadain. Rannsachadh Leigheis AI Kantesti.
📖 Iomraidhean Meidigeach Taobh a-muigh
Porcari S et al. (2025). International consensus statement on microbiome testing in clinical practice. The Lancet Gastroenterology & Hepatology.
Costea PI et al. (2017). Towards standards in human fecal sample processing. Nature Biotechnology.
⚕️ Àicheadh Meidigeach
Tha an artaigil seo dìreach airson adhbharan foghlaim agus chan eil e a’ dèanamh comhairle mheidigeach. Cuir fios an-còmhnaidh gu solaraiche cùram slàinte teisteanasach airson co-dhùnaidhean breithneachaidh is leigheis.
Comharran earbsa E-E-A-T
Eòlas
Lèirmheas clionaigeach air a stiùireadh le lighiche air sruthan-obrach mìneachaidh obair-lann.
Eòlas
Fòcas air leigheas obair-lann air mar a bhios bith-chomharraidhean (biomarkers) a’ giùlan ann an co-theacsa clionaigeach.
Ùghdarrasachd
Air a sgrìobhadh le Dr. Thomas Klein le ath-sgrùdadh le Dr. Sarah Mitchell agus Prof. Dr. Hans Weber.
Earbsachd
Mìneachadh stèidhichte air fianais le slighean leanmhainn soilleir gus dragh a lughdachadh.