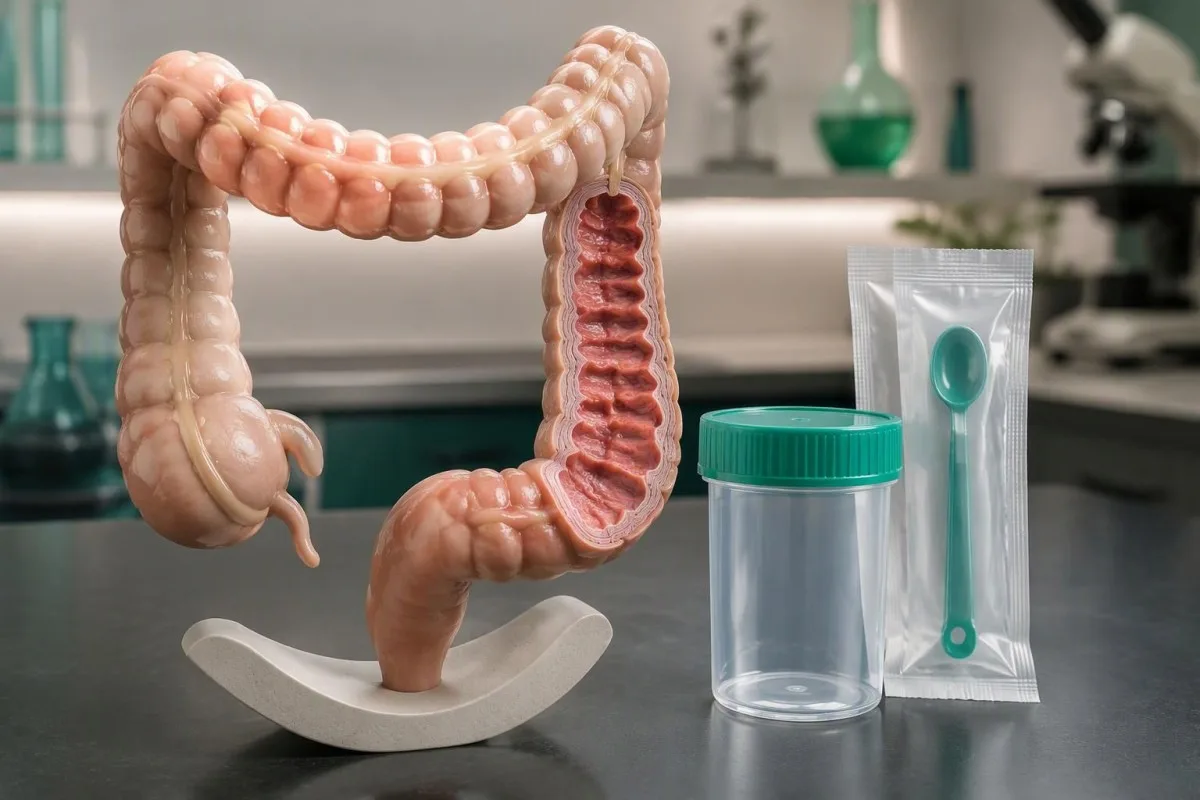
လူအများစုအတွက်၊ IBS ကို စစ်ဆေးရန် သို့မဟုတ် ဖြည့်စွက်စာများ ရွေးချယ်ရန် အူလမ်း microbome စစ်ဆေးမှုသည် ဝယ်ယူရန် တန်ဖိုးမရှိပါ။ ၎င်းသည် မစင်နမူနာတစ်ခုတွင် microbial DNA ကို ဖော်ပြသည်၊ သို့သော် ကမ္ဘာလုံးဆိုင်ရာ ကျန်းမာသော အူတွင်းရမှတ်ကို မတည်ထောင်နိုင် သို့မဟုတ် မည်သည့်ကုသမှုက ကူညီမည်ကို ယုံကြည်စိတ်ချစွာ မခန့်မှန်းနိုင်ပါ။.


- ဆေးဘက်ဆိုင်ရာ တန်ဖိုး ရလဒ်တစ်ခုက စောင့်ရှောက်မှုကို ပြောင်းလဲစေမလားအပေါ် မူတည်ပါသည်။ စားသုံးသူ microbiome ပရိုဖိုင်လ်များသည် IBS အတွက် ကမ္ဘာလုံးဆိုင်ရာ အသိအမှတ်ပြုထားသော ရောဂါရှာဖွေရေး ကန့်သတ်ချက် မရှိပါ။.
- ဆွေမျိုးပမာဏ ပုံစံခွဲထားသော sequencing များ၏ ရှယ်ယာကို တိုင်းတာသည်- 10% သည် သင့် အစာခြေလမ်းကြောင်းတလျှောက်ရှိ ဘက်တီးရီးယားအားလုံး၏ 10% ကို မဆိုလိုပါ။.
- Sequencing နည်းလမ်းများ ကွဲပြားသည်- 16S ပရိုဖိုင်သည် ဘက်တီးရီးယား marker gene ကို ရည်ရွယ်သည်၊ shotgun sequencing သည် DNA ကို ပိုမိုကျယ်ပြန့်စွာ နမူနာယူသည်။.
- စုံလင်မှု ရမှတ်များ တွက်ချက်မှုနှင့် ဓာတ်ခွဲခန်း လုပ်ငန်းစဉ်ပေါ် မူတည်သည်- 70/100 ရမှတ်သည် စံသတ်မှတ်ထားသော ဆေးဘက်ဆိုင်ရာ တိုင်းတာမှု မဟုတ်ပါ။.
- IBS ရောဂါရှာဖွေရေး ပုံမှန်အားဖြင့် လွန်ခဲ့သော 3 လအတွင်း ပျမ်းမျှ အနည်းဆုံး တစ်ပတ်လျှင် 1 ရက်ရှိသော ပြန်ဖြစ်သော ဝမ်းဗိုက်နာကျင်မှုကို အခြားဆေးဘက်ဆိုင်ရာ စံနှုန်းများနှင့်အတူ အသုံးပြုသည်။.
- Fecal calprotectin အောက်ပိုင်း 50 µg/g သည် လူကြီးများတွင် နိမ့်ကျသည်ဟု မှတ်ယူလေ့ရှိသော်လည်း ဓာတ်ခွဲခန်း အကွာအဝေးနှင့် သတိပေးသည့် လက္ခဏာများကမူ အရေးကြီးပါသည်။.
- Stool elastase အောက်ပိုင်း 100 µg/g သည် ပန်ကရိယ endocrine ချို့ယွင်းမှုကို ထောက်ကူပေးသည်၊ သင့်လျော်သောနမူနာဖြင့် တိုင်းတာသောအခါတွင်ဖြစ်သည်၊ ရေကဲ့သို့သောနမူနာများသည် မှားယွင်းစွာ နိမ့်ကျသော ရလဒ်များကို ပေးနိုင်သည်။.
- ဖြည့်စွက်စာ ရွေးချယ်မှု ဘက်တီးရီးယား အဆင့်သတ်မှတ်ချက်ကို တစ်ခုတည်းဖြင့် ယုံကြည်စိတ်ချစွာ လိုက်နာနိုင်မည် မဟုတ်ပါ၊ လက္ခဏာများ၊ သတ်မှတ်ထားသော ရောဂါများ၊ ဆေးဝါး အကျိုးသက်ရောက်မှုများနှင့် ပြသထားသော ချို့ယွင်းချက်များသည် ပိုကောင်းသော အစပျိုးမှတ်များဖြစ်သည်။.
အူလမ်း microbiome စစ်ဆေးမှုကို မည်သည့်အခါတွင် ပေးချေသင့်သနည်း။
A အူလမ်းကြောင်း မိုက်ခရိုဘယோம் စစ်ဆေးမှု သိချင်စိတ် သို့မဟုတ် သုတေသန လေ့ကျင့်ခန်း အနေဖြင့် ပေးရကျိုးနပ်နိုင်သော်လည်း၊ ရောဂါရှာဖွေရေး သို့မဟုတ် ကုသမှု ရွေးချယ်ရေး ကိရိယာ အနေဖြင့် မဟုတ်ပါ။ အောက်တိုဘာ 5, 2026 နေ့အထိ၊ တရားမျှတသော ကွဲပြားမှုမှာ မစင်နမူနာ 1 ခုကို ဖော်ပြခြင်းနှင့် ၎င်း၏ အစီရင်ခံစာအပေါ် အရေးယူဆောင်ရွက်ခြင်းက ကျန်းမာရေးကို တိုးတက်စေကြောင်း ပြသခြင်းတို့ကြား ကွဲပြားပါသည်။.
စားသုံးသူ အစီအစဉ်ခွဲများ အစီရင်ခံစာများသည် IBS ကို ယုံကြည်စိတ်ချစွာ ရောဂါရှာဖွေရန်၊ ဝမ်းဗိုက်တင်းခြင်း၏ အကြောင်းရင်းကို ဖော်ထုတ်ရန် သို့မဟုတ် ကိုယ်ပိုင် probiotic ကို ရွေးချယ်ရန် မယုံကြည်စိတ်ချပါ။ မိုက်ခရိုဘယோம் စစ်ဆေးမှုဆိုင်ရာ နိုင်ငံတကာ သဘောတူညီချက် ကြေညာချက်သည် ပုံမှန်ဆေးဘက်ဆိုင်ရာ အသုံးချမှုအတွက် အဓိက အတားအဆီးများဖြစ်သည့် စံနမူနာနှင့် သက်သေပြထားသော ဆေးဘက်ဆိုင်ရာ အသုံးဝင်မှု (Porcari et al., 2025) တို့အပါအဝင်၊ အုပ်စုများအကြား ကွဲပြားမှုများကို သိရှိခြင်းသည် လူတစ်ဦးကို ရောဂါရှာဖွေခြင်းနှင့် တူညီခြင်းမရှိပါ။.
Kantesti သည် AI သွေးစစ်ခွဲခြမ်းစိတ်ခွဲစက်ဖြစ်သည်၊ မစင်-အစီအစဉ်ခွဲခြင်းဝန်ဆောင်မှု မဟုတ်ပါ။ ကျွန်ုပ် Thomas Klein၊ အဓိက ဆေးဘက်ဆိုင်ရာ အရာရှိဖြစ်ပြီး၊ ကျွန်ုပ်၏ အကြံပြုချက်မှာ မေးခွန်း 3 ခုကို ခွဲခြားရန်ဖြစ်သည်- ဘာကို တိုင်းတာခဲ့သလဲ၊ မည်မျှ ပြန်လုပ်နိုင်သလဲ၊ နှင့် အဖြေသည် ပြုစုစောင့်ရှောက်မှုကို ပြောင်းလဲစေမည်လား။ ကျွန်ုပ်တို့၏ ကုမ္ပဏီအကြောင်းအရာ သွေးစစ်အာရုံစိုက်မှုကို ရှင်းပြသည်။.
တစ်ခုမှန်းဆထားသည့် £180 ကိရိယာသည် လစဉ် £60 ဖြည့်စွက်စာများနှင့် 3 လတစ်ကြိမ် ထပ်ခါတလဲလဲ စစ်ဆေးရန် အစီရင်ခံစာက အကြံပြုပါက ပိုမိုကြီးမားသော ဝယ်ယူမှုတစ်ခု ဖြစ်လာနိုင်သည်။ ထိုကိန်းဂဏန်းများသည် ဘတ်ဂျက်ပြဿနာကို ညွှန်ပြသည်၊ မ market ဈေးနှုန်းခန့်မှန်းချက်ကို မဟုတ်ပါ။ အဓိပ္ပါယ်ရှိသော ကုန်ကျစရိတ်တွင် အစောပိုင်း အစီရင်ခံစာက သင့်အား ဝယ်ယူရန် လှုံ့ဆော်ခဲ့သည့် အရာအားလုံး ပါဝင်သည်။.
ဇီဝဗေဒကို နှစ်သက်သော လက္ခဏာမပြသော လူကြီးတစ်ဦးသည် ယင်းမရေရာမှုကို လက်ခံနိုင်သည်၊ ဆည်းကပ်နိုင်သည်။ 6 ပတ်ကြာ အဆက်မပြတ် ဝမ်းပျက်ဝမ်းလျှောဖြစ်သောသူသည် ကွဲပြားသော ဆွေးနွေးမှုတစ်ခု လိုအပ်သည်- ဆေးဘက်ဆိုင်ရာ အကဲဖြတ်မှု၊ ရည်ရွယ်ထားသော စစ်ဆေးမှုနှင့် ကျန်းမာရေး အဆင့်ကို တိုးတက်စေရန် မမှီခိုသော အစီအစဉ်တစ်ခု။.
မစင် microbiome စစ်ဆေးမှုသည် အမှန်တကယ် မည်သည့်အရာကို တိုင်းတာသနည်း။
A မစင် မိုက်ခရိုဘယோம் စစ်ဆေးမှု မစင်နမူနာ အနည်းငယ်မှ ပြန်လည်ရရှိသော အဏုဇီဝ DNA ကို တိုင်းတာလေ့ရှိသည်။ အဓိက ချဉ်းကပ်နည်းနှစ်ခု—16S ရီဘိုဆိုမယ့် RNA မျိုးဗီဇ အစီအစဉ်ခွဲခြင်းနှင့် ရှော့ဂန်း မက်တာဂျီနိုမစ် အစီအစဉ်ခွဲခြင်း—၎င်းတို့ မည်သည့်အရာကို ဖော်ထုတ်နိုင်သည် အပေါ်တွင် ကွဲပြားသော်လည်း၊ မည်သည့်အရာကမျှ အသက်ရှင်နေသော သတ္တဝါတိုင်း သို့မဟုတ် အူလမ်းကြောင်းတစ်လျှောက်လုံး ၎င်း၏ လှုပ်ရှားမှုကို တိုက်ရိုက် မတိုင်းတာပါ။.
16S အစီစဉ်ခွဲခြင်း ဘက်တီးရီးယားနှင့် သင့်လျော်သော နည်းလမ်းများဖြင့်၊ အာကေးယာများကို အမျိုးအစားခွဲရန် အသုံးပြုသော မှတ်သားကိရိယာ မျိုးဗီဇကို ပစ်မှတ်ထားသည်။ ကွဲပြားသော အတက်အဆင်း ဒေသများနှင့် ပရိုင်မာများသည် ကွဲပြားသော သတ္တဝါများကို ပြန်လည်ရရှိသည်၊ မျိုးရင်းအဆင့် ဖော်ထုတ်မှုသည် မည်သည့် မျိုးစိတ် သို့မဟုတ် ပင်စည်ကို ရှိသည်ကို မသတ်မှတ်နိုင်ပါ၊ နှင့် ပင်စည်-အထူး ကုသမှု တောင်းဆိုမှုများသည် 1 မျိုးရင်း အမည်မှ အလိုအလျောက် လိုက်နာနိုင်မည် မဟုတ်ပါ။.
ရှော့ဂန်း အစီစဉ်ခွဲခြင်း DNA ကို ပိုမိုကျယ်ပြန့်စွာ နမူနာယူပြီး အဏုဇီဝ မျိုးဗီဇများကို ဖော်ထုတ်နိုင်သည်၊ တစ်ခါတစ်ရံ ပိုကောင်းသော မျိုးစိတ် အကွာအဝေးဖြင့်။ သို့သော်လည်း၊ ဇီဝပြောင်းလဲမှု လမ်းကြောင်းနှင့် ဆက်စပ်နေသော 1 မျိုးဗီဇကို ရှာဖွေခြင်းသည် လမ်းကြောင်းသည် တက်ကြွနေကြောင်း၊ ၎င်း၏ ထုတ်ကုန်သည် သင့်တစ်ရှူးများသို့ ရောက်ရှိကြောင်း၊ သို့မဟုတ် ၎င်းကို ပြောင်းလဲခြင်းက လက္ခဏာများကို တိုးတက်စေမည်ကို မပြပါ။.
မစင်သည် အူသိမ်၏ မစင်ဖြစ်သည်၊ အူသိမ်၏ မစင် သို့မဟုတ် အူသိမ် mucus ကို ကပ်နေသော သတ္တဝါများ၏ မစင်မဟုတ်ပါ။ ထို့ကြောင့် တစ်နေ့ မနက်တွင် စုဆောင်းထားသော နမူနာသည် နည်းပညာအရ အချက်အလက်ပြည့်စုံသော်လည်း ဆေးဘက်ဆိုင်ရာ မေးခွန်းနှင့် သက်ဆိုင်သော ရုပ်ပိုင်းဆိုင်ရာ တည်နေရာကို လွဲချော်စေနိုင်သည်။.
အစီရင်ခံစာသည် ဖော်ထုတ်ထားသော သတ္တဝါများ၊ ခန့်မှန်းထားသော အချိုးအစားများနှင့် ခန့်မှန်းထားသော လုပ်ဆောင်ချက်များကို တူညီသော တိုင်းတာမှုများကဲ့သို့ ပေါင်းစပ်နိုင်သည်။ ၎င်းတို့သည် မဟုတ်ပါ။ ကျွန်ုပ်တို့၏ လမ်းညွှန်ချက် qualitative နှင့် quantitative ရလဒ်များ တစ်စုံတစ်ရာကို ဖော်ထုတ်ခြင်းနှင့် ၎င်း၏ပမာဏကို တိုင်းတာခြင်းတို့သည် မေးခွန်း 2 ခုကို ဖြေရှင်းပေးကြောင်း ရှင်းပြသည်။.
ဘက်တီးရီးယား ပမာဏ ရာခိုင်နှုန်းများသည် အမှန်တကယ် အဘယ်အရာကို ဆိုလိုသနည်း။
ဆွေမျိုးပမာဏ သည် ဓာတ်ခွဲခန်း၏ တွက်ချက်မှုတွင် ပါဝင်သော အစီစဉ်ခွဲများ၏ သတ္တဝါ၏ အချိုးအစားဖြစ်သည်၊ အသက်ရှင်နေသော ဘက်တီးရီးယားအရေအတွက် မဟုတ်ပါ။ အကယ်၍ ၁၀၀ စီစဉ်ခွဲများအနက် ၂၀ သည် အုပ်စုတစ်စုနှင့် သက်ဆိုင်ပါက၊ ၎င်း၏ အစီရင်ခံစာ အကျယ်အဝန်းမှာ 20% ဖြစ်သည်၊ အောက်ခြေက ထိုရာခိုင်နှုန်းက မည်သို့အဓိပ္ပါယ်ရှိသည်ကို ဆုံးဖြတ်သည်။.
တစ်စုံတစ်ရာ ပမာဏနည်းပါးခြင်းမရှိဘဲ ရာခိုင်နှုန်း ကျဆင်းနိုင်သည်။ ရိုးရှင်းသော ဥပမာတွင်၊ ၁၀၀ စုစုပေါင်း အစီစဉ်ခွဲများအနက် ၂၀ သည် 20% ကို ပေးသည်၊ အခြား ၂၀၀ အနက် ၂၀ သည် 10% ကို ပေးသည်၊ ဒုတိယ ရလဒ်သည် ပထမတစ်ခု၏ လျော့နည်းမှုကို ထင်ဟပ်စေနိုင်သည်။.
Absolute microbial load requires additional measurement, such as calibrated quantitative PCR, flow cytometry or a validated spike-in approach. Even then, stool water content and the reporting denominator matter: copies per gram of wet stool and copies per gram of dry stool are 2 different quantities.
A report stating that an organism is absent usually means it was not detected above that workflow’s threshold. If an organism has a true read fraction of 0.01% and only 1,000 relevant reads are sampled, missing it is unsurprising; non-detection should not trigger a diagnosis of bacterial deficiency.
The same reasoning applies when percentages distract from absolute blood-cell counts, as explained in our count versus percentage guide. For microbiome reports, ask 2 practical questions: what entered the denominator, and were unclassified reads excluded?
microbiome စုံလင်မှု မြင့်မားခြင်းသည် ကောင်းမွန်သော ကျန်းမာရေးကို ဆိုလိုသလော။
A higher microbiome diversity score does not automatically mean better digestive health. Diversity summarizes features such as richness and evenness; it does not identify whether organisms are helpful, harmful or clinically relevant, and a proprietary 0–100 score has no universal medical interpretation.
Richness counts detected categories, while evenness describes how balanced their proportions are. A sample with 100 detected species dominated by 1 species may have high richness but low evenness; sequencing depth and the taxonomic level chosen can change both calculations.
The Shannon index combines richness and evenness. Using natural logarithms, 2 equally abundant categories produce approximately 0.69 and 4 produce approximately 1.39; these are mathematical examples, not healthy-gut thresholds, and values calculated at genus level should not be compared directly with species-level values.
Bowel transit complicates the interpretation because stool consistency is associated with microbiome composition. Recording stool form for 7 days can reveal whether a score is being compared across very different bowel states; the Bristol ဝမ်းဇယား (Bristol stool chart) provides a practical vocabulary.
A reference cohort also shapes the result: a percentile against 500 self-selected customers is not equivalent to a percentile against a carefully characterized population. Ask whether the comparator matches your age, geography, medications and bowel habits before treating an 18th-percentile result as a problem.
အဘယ်ကြောင့် microbiome ပေးသူ နှစ်ဦးသည် မတူညီသော ရလဒ်များကို ပေးနိုင်သနည်း။
Two providers can give different results from the same stool because their collection, DNA extraction, sequencing and computational workflows differ. At least 4 layers can change a report before clinical interpretation begins; disagreement does not necessarily mean that either laboratory mixed up the specimen.
DNA extraction is a major source of variation because bacterial cell walls differ in how easily they break open. Costea and colleagues demonstrated why fecal sample processing needs standardization (Costea et al., 2017); insufficient mechanical disruption can under-represent some organisms even when 2 laboratories sequence equal amounts of extracted DNA.
Transport introduces another variable: an unstabilized sample spending 48 hours at room temperature is not equivalent to a sample immediately placed in a validated preservative. The correct handling conditions are kit-specific; refrigeration is not automatically appropriate when a collection system was designed and validated for ambient shipping.
Reference databases and software versions can reassign the same sequence. One provider may report a species while another reports only its genus, and 2 health scores may use different proprietary weighting systems; apparently conflicting recommendations can arise from the scoring rules rather than the underlying biology.
A specimen problem can undermine interpretation even when the instrument works correctly, a principle illustrated by our နမူနာ အနှောင့်အယှက် လမ်းညွှန်. If comparing results, document collection time, preservative, recent medicines and the pipeline version—not just the final percentage.
အူလမ်း microbiome စစ်ဆေးမှု၏ တိကျမှုကို မည်သို့ စီရင်သင့်သနည်း။
Gut microbiome test accuracy has 3 separate meanings: analytical validity, clinical validity and clinical utility. A laboratory may accurately detect microbial DNA without accurately diagnosing a condition or proving that its recommended treatment improves outcomes; a single percentage labelled accuracy cannot resolve those distinctions.
Analytical validity asks whether the workflow measures what it claims to measure. Useful evidence includes known-composition microbial controls, extraction blanks, contamination controls, detection limits and duplicate precision; processing 1 sample twice is helpful, but it does not test every source of variation from home collection onward.
Clinical validity asks whether a result distinguishes people with and without a defined condition in relevant populations. An algorithm evaluated in 200 people already known to have severe disease may perform differently in 200 primary-care patients with overlapping symptoms; spectrum and selection bias matter.
Clinical utility asks whether using the report improves a patient outcome compared with appropriate usual care. Porcari et al. (2025) distinguish research promise from readiness for routine application; a prettier report or a change in 1 bacterial percentage is not itself evidence of less pain or better nutrition.
ကျွန်တော်တို့ရဲ့ clinical standards စာမျက်နှာတွင် ဒီလိုပုံစံဖြင့် စီမံထားသည်။ concerns blood-result interpretation and should not be read as validation of consumer stool sequencing. For any health report, the accuracy assessment checklist helps separate technical performance from claims that require patient-outcome studies.
microbiome အစီရင်ခံစာသည် IBS ကို စစ်ဆေးနိုင်ပါသလား သို့မဟုတ် ဝမ်းလေထခြင်းကို ရှင်းပြနိုင်ပါသလား။
A consumer microbiome report cannot diagnose irritable bowel syndrome, and no bacterial abundance cutoff reliably establishes IBS in routine practice. Commonly used Rome IV criteria include abdominal pain averaging at least 1 day weekly in the previous 3 months, with symptom onset at least 6 months earlier.
Rome IV also requires pain associated with at least 2 of 3 features: defecation, changed stool frequency, or changed stool form. These criteria support a positive clinical diagnosis, but warning signs and alternative explanations still require assessment; painless bloating alone does not meet the IBS pain criterion.
The ACG guideline supports a positive diagnostic strategy rather than endless exclusion testing, with celiac testing and inflammatory-marker assessment in appropriate patients with diarrhea symptoms (Lacy et al., 2021). A microbiome score is not one of those diagnostic criteria, even if a report associates 1 organism with IBS.
Consider a hypothetical 34-year-old with bloating, loose stools and low iron stores: celiac disease deserves consideration before a recommendation to remove gluten. Testing commonly includes tissue transglutaminase IgA and total IgA, because low IgA can mislead an IgA-based result.
Kantesti AI should not turn an unvalidated stool score into an IBS diagnosis or a claim of small-intestinal bacterial overgrowth. Anyone already avoiding gluten should discuss testing preparation rather than improvise a challenge; our celiac စစ်ဆေးမှု ပြင်ဆင်မှု လမ်းညွှန် explains why duration and intake affect interpretation.
မည်သည့်ဆေးဘက်ဆိုင်ရာ မစင် စစ်ဆေးမှုများသည် ပိုမိုအသုံးဝင်သော မေးခွန်းများကို ဖြေကြားပေးသနည်း။
Clinical stool diagnostics investigate defined problems, such as intestinal inflammation, pancreatic enzyme output, pathogens or occult bleeding. They are different from microbiome profiling; fecal calprotectin, for example, is commonly reported in µg/g with assay-specific interpretation, whereas a bacterial diversity score has no comparable universal diagnostic threshold.
Fecal calprotectin reflects intestinal neutrophil activity, not microbiome diversity. Many adult laboratories use below 50 µg/g as a low result, but infection, NSAID exposure and other conditions can raise it; our calprotectin and lactoferrin comparison explains their overlapping clinical roles.
An intermediate calprotectin result often needs context and sometimes a repeat after about 2–6 weeks, depending on the local pathway. Persistent symptoms or alarm features may justify earlier investigation, so our borderline calprotectin guide should not be used to postpone assessment.
ဝမ်း elastase estimates pancreatic exocrine output: above 200 µg/g is generally reassuring, 100–200 µg/g is indeterminate, and below 100 µg/g supports insufficiency in an appropriate specimen. The stool elastase interpretation guide explains why dilution and pretest probability matter.
A provider may bundle 1 clinically established assay with several exploratory scores in the same package. That does not validate the entire package: judge each component separately, and remember that normal calprotectin does not exclude every bowel disorder or replace colorectal-cancer evaluation when indicated.
စားသုံးသူ sequencing သည် အူလမ်းပိုးဝင်ခြင်းကို ယုံကြည်စိတ်ချစွာ ပယ်ဖျက်နိုင်ပါသလား။
Consumer microbiome sequencing cannot reliably rule out a gut infection unless the specific pathogen claim has been clinically validated. Targeted stool PCR, antigen assays, toxin testing and culture answer different questions; 3 or more new unformed stools in 24 hours may prompt assessment for C. difficile in the right clinical setting.
C. difficile testing needs symptoms and risk context because detecting a toxin gene can identify colonization as well as illness. Recent antibiotics, healthcare exposure and laxative use influence the decision; 1 positive molecular result does not automatically establish toxin-mediated disease or justify treatment.
Travel-associated diarrhea may require targeted testing for Giardia or other pathogens based on exposure and symptom duration. A report that simply lists an organism among hundreds lacks the same clinical meaning as a validated diagnostic assay, and 1 negative consumer profile cannot safely exclude it.
H. pylori stool antigen testing is an example of a directed assay with established uses. Proton pump inhibitors generally need to be withheld for 2 weeks and antibiotics or bismuth for 4 weeks before testing when clinically safe; prescribed medicines should not be stopped without advice.
Acid-suppressing medicines can also affect symptoms, microbiome composition and other laboratory results. Our PPI and gastrin guide illustrates why medication history belongs in the interpretation rather than being reduced to 1 report note about an altered bacterial community.
မည်သည့်လက္ခဏာများသည် microbiome စစ်ဆေးခြင်းထက် ဦးစားပေးသင့်သနည်း။
Visible blood, black tarry stool, unexplained weight loss, anemia, persistent nighttime diarrhea or severe abdominal pain should take priority over a consumer microbiome test. A reassuring bacterial score provides no safety clearance; heavy bleeding, fainting, severe dehydration or rapidly worsening pain warrants urgent assessment.
A normal microbiome report cannot exclude colorectal cancer, inflammatory bowel disease or a clinically significant source of bleeding. Even 1 episode of black tarry stool needs assessment when gastrointestinal bleeding is plausible; our stool bleeding urgency guide distinguishes color changes from concerning patterns.
A positive FIT detects human hemoglobin in stool and requires follow-up through the relevant diagnostic pathway; repeating a microbiome kit does not answer why it is positive. The positive FIT next steps explain why a screening or symptomatic result cannot be dismissed by an unrelated score.
Risk depends on age, family history and symptom trajectory, not just a single duration cutoff. A hypothetical 62-year-old with 8 weeks of new bowel-habit change and weight loss needs prompt clinical review even if a consumer report rates diversity as excellent.
Severe diarrhea can cause kidney and electrolyte complications before its cause is known. Fewer trips to urinate, dizziness on standing or inability to keep fluids down for several hours should shift attention toward hydration and medical assessment—not toward whether 1 bacterial genus appears unusually abundant.
microbiome ရလဒ်များသည် ကိုယ်ပိုင် probiotics သို့မဟုတ် ဖြည့်စွက်စာများကို ရွေးချယ်နိုင်ပါသလား။
A microbiome report alone cannot reliably select a personalized probiotic, prebiotic or vitamin regimen. A low bacterial percentage is not a diagnosed deficiency, and benefits depend on the indication, exact formulation and sometimes strain; 1 genus name does not establish which supplement will help.
The ACG guideline suggests against probiotics for global IBS symptoms because the evidence is very uncertain, while supporting soluble fiber (Lacy et al., 2021). That recommendation does not prove that every probiotic is ineffective; it means that confidence in routinely recommending 1 product for IBS remains limited.
A cautious soluble-fiber trial may start with about 3–5 g of psyllium daily and increase gradually according to tolerance and product instructions. Take it with adequate fluid—often at least 250 mL per dose—and seek advice for swallowing difficulty or obstruction risk; adding several fermentable products at once makes symptom attribution harder.
Vitamin or mineral needs require dietary and clinical assessment, not a microbial vitamin-production prediction. In the United States, the adult zinc upper intake level is 40 mg/day from all sources; sustained excess can cause copper deficiency, as our high zinc safety guide က ရှင်းပြထားပါတယ်။.
Kantesti is an AI blood test interpretation platform that helps place measured blood results in context; microbial genes cannot establish serum B12, iron stores or magnesium status. Our evidence-based food choices can support dietary variety, but 1 restrictive plan is not appropriate for every digestive condition.
စုဆောင်းခြင်း၊ ထပ်ခါတလဲလဲ စစ်ဆေးခြင်းနှင့် ကိုယ်ရေးကိုယ်တာ က မည်သို့ တန်ဖိုးကို ထိခိုက်စေသနည်း။
Collection quality, repeat-test consistency and data handling affect whether a microbiome purchase is useful. Follow the specific kit instructions, keep a record of relevant exposures, and avoid treating a change between 2 samples as proof of improvement when collection conditions or analytical methods also changed.
Recent antibiotics, bowel preparation, acute diarrhea and major dietary changes can alter the sample’s context. There is no universal evidence-based waiting interval—such as exactly 4 weeks—that makes every microbiome test representative again; document dates and discuss the question rather than stopping a necessary treatment to improve a score.
Repeated samples are easier to interpret when provider, kit, handling and bowel state remain comparable. Keeping a 7-day record of symptoms, stool form, diet changes and medicines may be more useful than purchasing a repeat immediately; our အစာခြေ လက္ခဏာလမ်းညွှန် explains common contextual clues.
Privacy questions should cover both the physical specimen and the digital data. Ask 4 things before paying: how long each is retained, whether secondary research use is optional, whether third-party sharing occurs, and whether deletion covers raw sequencing files as well as the account.
Shotgun sequencing can capture human DNA alongside microbial DNA, so human-read filtering and retention policies deserve scrutiny. A GDPR-aligned statement alone does not answer every processing question; request the actual consent terms, hosting arrangements and cross-border safeguards before sending 1 specimen that may generate extensive data.
သင့်တွင် microbiome အစီရင်ခံစာတစ်ခု ရှိပြီးသားဖြစ်ပါက မည်သို့လုပ်သင့်သနည်း။
If you already have a microbiome report, separate established clinical assays from exploratory scores and prioritize symptoms over bacterial rankings. Write down 3 items before making changes: the problem you want to improve, the evidence for the proposed intervention, and the outcome that would justify continuing it.
The first step is to inventory the report rather than accept its overall traffic-light rating. A package containing calprotectin in µg/g, bacterial relative abundance in percent and a wellness score out of 100 contains 3 different types of information; each needs its own interpretation and evidence.
Choose 1 measurable outcome for a reasonable trial: weekly pain days, stool frequency, urgency episodes or the ability to tolerate a food. A hypothetical 4-week intervention that improves symptoms without changing a diversity score may still be useful; the reverse pattern does not establish patient benefit.
Kantesti is an AI-powered blood test analysis tool, not a substitute for a digestive diagnosis. Our AI தொழில்நுட்ப விளக்கம் describes how blood-result interpretation works; ferritin, a CBC or electrolytes may answer specific clinical questions, but there is no validated blood panel that reveals your ideal bacterial balance.
My practical recommendation, as Thomas Klein, is to bring the original report and a 7-day symptom record to the clinician rather than a shopping list of recommended supplements. Do not add antibiotics, antifungals or restrictive diets solely because 1 organism was flagged; agree on what would trigger reassessment or specialist referral.
သုတေသန ထုတ်ဝေမှုများနှင့် AI အနက်ဖွင့်ဆိုချက်များ၏ ကန့်သတ်ချက်များ
Research on AI blood-result interpretation does not validate consumer microbiome diagnosis or personalized supplement selection. The 2 company-supplied Figshare records below concern blood-test workflows; neither title establishes that stool-sequencing recommendations improve digestive symptoms, detect IBS or identify an individual’s optimal probiotic.
Kantesti’s supplied technical benchmark is described as evaluating 100,000 synthetic test cases. Synthetic-case performance can examine defined technical behavior, but it is not equivalent to diagnostic accuracy in consecutive real patients; independent reproduction, representative clinical data and patient outcomes require separate evaluation.
The supplied hantavirus report describes engineering validation and deployment across 50,000 interpreted blood-test reports. Deployment volume does not by itself establish sensitivity, specificity or outcome benefit, and a triage workflow for 1 infectious condition cannot be generalized to microbiome profiling without new evidence.
The formal citations below use n.d. because publication dates were not supplied; their linked records should be checked for authorship, version and review status. ResearchGate and Academia.edu links are DOI search routes, not claims that 2 verified copies exist there, and repository availability should not be mistaken for journal peer review.
Clinical accountability remains separate from publication count or sample volume. Our ဆေးဘက်ဆိုင်ရာအကြံပေးဘုတ်အဖွဲ့ page describes medical governance; the decision standard remains whether a particular test answers the patient’s question, with limitations explained before purchase rather than after 1 unexpected result.
အမေးများသောမေးခွန်းများ
အူလမ်းကြောင်း မိုက်ခရိုဘိုင်အိုမ် စစ်ဆေးမှုများက တန်ဖိုးရှိပါသလား?
IBS ရောဂါရှာဖွေရန် သို့မဟုတ် တစ်ဦးချင်းအတွက် သင့်လျော်သော ဖြည့်စွက်စာများကို ရွေးချယ်ရန် အူလမ်းကြောင်း မိုက်ခရိုဘိုင်အိုမစ် စစ်ဆေးမှုများကို ဝယ်ယူသင့်လေ့မရှိပါ။ ၎င်းတို့သည် ဝမ်းနမူနာ 1 ခုရှိ မိုက်ခရိုဘ်များ၏ DNA ကို ဖော်ပြပေးနိုင်သော်လည်း စားသုံးသူအတွက် ထုတ်ပေးသည့် အမှတ်ရလဒ်များတွင် ယေဘုယျအားဖြင့် သတ်မှတ်ထားသော ရောဂါရှာဖွေရေး အဆင့်သတ်မှတ်ချက်များနှင့် ကုသမှုရွေးချယ်ရာတွင် အသုံးဝင်ကြောင်း သက်သေပြထားမှု မရှိပါ။ မဝယ်ယူမီ ကိရိယာ၏ ကုန်ကျစရိတ်၊ ထပ်မံစစ်ဆေးမှုများနှင့် အကြံပြုထားသော ထုတ်ကုန်များအတွက် ကျသင့်ငွေ စုစုပေါင်းကို ထည့်သွင်းစဉ်းစားပါ။ ဆက်လက်ဖြစ်ပေါ်နေသော လက္ခဏာများကို သတ်မှတ်ထားသော မေးခွန်းတစ်ခုကို ဖြေဆိုပေးသည့် ဆေးဘက်ဆိုင်ရာ အကဲဖြတ်မှုနှင့် ပစ်မှတ်ထား စစ်ဆေးမှုများဖြင့် ကိုင်တွယ်ခြင်းက ပိုသင့်လျော်သည်။.
အူလမ်းကြောင်း မိုက်ခရိုဘိုင်အုမ်း စမ်းသပ်မှုက ဘယ်လောက်တိကျပါသလဲ။
အူလမ်းကြောင်း မိုက်ခရိုဘိုင်အုန်း စမ်းသပ်မှု၏ တိကျမှုသည် သီးခြားမေးခွန်း ၃ ခုအပေါ် မူတည်သည်—ဓာတ်ခွဲခန်းက မိုက်ခရိုဘ် DNA ကို မှန်ကန်စွာ တိုင်းတာခြင်း ရှိမရှိ၊ ရလဒ်က လက်တွေ့ရောဂါအခြေအနေကို ခန့်မှန်းနိုင်ခြင်း ရှိမရှိ၊ ထိုရလဒ်အပေါ် အခြေခံ၍ ဆောင်ရွက်ခြင်းက ကျန်းမာရေးရလဒ်များကို ပိုမိုကောင်းမွန်စေခြင်း ရှိမရှိတို့ ဖြစ်သည်။ နမူနာကောက်ယူပုံ၊ DNA ထုတ်ယူပုံ၊ စီကွင်းဆင့်အနက်နှင့် ကိုးကားဒေတာဘေ့စ်များသည် ဖော်ပြထားသော ပမာဏကို ပြောင်းလဲစေနိုင်သည်။ နည်းပညာအရ ထပ်တလဲလဲရရှိနိုင်သော ရလဒ်သည် ယုံကြည်စိတ်ချရသော ရောဂါရှာဖွေမှုကို အလိုအလျောက် ပေးစွမ်းခြင်း မရှိပါ။ တိကျမှုရာခိုင်နှုန်းတစ်ခုတည်းကို လက်ခံမည့်အစား သီးခြားအဆိုအတွက် အတည်ပြုချက်ကို တောင်းပါ။.
ဝမ်း stool microbiome စစ်ဆေးမှုဖြင့် IBS ကို စစ်ဆေးနိုင်ပါသလား။
IBS ကို တည်ထောင်ပြီးသား ဘက်တီးရီးယား ကန့်သတ်ချက်ဖြင့် စားသုံးသူ မစင် မိုက်ခရိုဘയോမ် စမ်းသပ်မှုကနေ ရောဂါမခွဲခြားနိုင်ပါ။ အသုံးများတဲ့ Rome IV စံနှုန်းတွေမှာ လွန်ခဲ့တဲ့ ၃ လအတွင်း ပျမ်းမျှ အနည်းဆုံး တစ်ပတ်ကို တစ်ရက် ဗိုက်နာခြင်း၊ ရောဂါလက္ခဏာ စတင်တာ အနည်းဆုံး ၆ လ စောခြင်း၊ နဲ့ ဆက်စပ်နေတဲ့ ဝမ်းသွားပုံပြောင်းလဲခြင်းတို့ ပါဝင်ပါတယ်။ ဆရာဝန်တွေက သတိပေးလက္ခဏာတွေကိုလည်း အကဲခတ်ပြီး၊ ဆီးချိုရောဂါ စမ်းသပ်ခြင်းအပါအဝင်၊ ဝမ်းလျှောတဲ့လူနာတွေမှာ သင့်လျော်တဲ့ စမ်းသပ်မှုတွေကို ထည့်သွင်းစဉ်းစားပါတယ်။ မိုက်ခရိုဘയോမ် ပရိုဖိုင်လင့်က အဲဒီအကဲခတ်မှုကို အစားမထိုးပါဘူး။.
ပုံမှန် မိုက်ခရိုဘಯோம் ကွဲပြားမှုရမှတ်ဆိုသည်မှာ အဘယ်နည်း။
တစ်ဦးချင်းစီ၏ မိုက်ခရိုဘယမ်၏ ကွဲပြားမှုအတွက် စကြဝဠာဆိုင်ရာ ပုံမှန်တန်ဖိုးမရှိပါ။ ပိုင်ဆိုင်ခွင့်ရအမှတ် 70/100 သည် စံသတ်မှတ်ထားသော ရောဂါခွဲခြားမှုအဖြစ် မဟုတ်ဘဲ ပေးသူ၏တွက်ချက်မှုနှင့် ရည်ညွှန်းလူဦးရေအတွင်း၌သာ အဓိပ္ပာယ်ရှိသည်။ ကြွယ်ဝမှု၊ ညီမျှမှု၊ sequencing depth နှင့် taxonomic level တို့သည် ကွဲပြားမှုတိုင်းတာမှုများကို ထိခိုက်စေသည်။ ပိုမိုများပြားသော ကွဲပြားမှုသည် အလိုအလျောက် ကောင်းသည်မဟုတ်၊ နိမ့်သော အမှတ်သည် ဖြည့်စွက်စာ သို့မဟုတ် ဆေးဝါးများကိုသာ မ justify နိုင်ပါ။.
ကျွန်တော့်ဆရာဝန်ဆီက ရတဲ့ မစင်စစ်ဆေးမှုနဲ့ မိုက်ခရိုဘယွန်စစ်ဆေးမှုက အတူတူပါပဲလား။
မိုက်ခရိုဘಯ serupa ၏ အကြောင်းအရာကို ဖော်ထုတ်ခြင်းသည် သတ်မှတ်ထားသော အခြေအနေအတွက် ဆေးခန်းမစင်စမ်းသပ်ခြင်းနှင့် မတူပါ။ မစင် calprotectin သည် အများအားဖြင့် အသက်ကြီးသူများအတွက် အနိမ့်ဆုံး 50 µg/g အောက်ကို အသုံးပြုပြီး၊ မစင် elastase သည် 100 µg/g အောက်သည် သင့်လျော်သော နမူနာတွင် ပန်ကရိယ exocrine ချို့ယွင်းမှုကို အထောက်အကူပြုပါသည်။ ရောဂါပိုး အတိအကျ စမ်းသပ်မှုများနှင့် FIT သည် အခြားသော အထူးမေးခွန်းများကို စုံစမ်းစစ်ဆေးသည်။ ကူးသန်းရောင်းဝယ်ရေး အထုပ်တွင် တည်ထောင်ပြီးသား စမ်းသပ်မှုများနှင့် စူးစမ်းလေ့လာရေး ရမှတ်များ ပါဝင်နိုင်သည်၊ ထို့ကြောင့် အစိတ်အပိုင်းတစ်ခုစီကို သီးခြားစီ အကဲဖြတ်ရမည်။.
ကျွန်ုပ်၏ မိုက်ခရိုဘယုန်း ရလဒ်များက ကျွန်ုပ် မည်သည့် ပရိုဘယိုတစ်ကို သောက်သင့်သည်ကို ပြောပြနိုင်သလား။
မိုက်ခရိုဘയോမ်ရလဒ်များသည် တစ်ဦးချင်းစီအတွက် အကောင်းဆုံးဖြစ်နိုင်သော ပရိုဘိုင်အိုတစ်ကို ယုံကြည်စိတ်ချရစွာ မဖော်ထုတ်နိုင်ပါ။ ဘက်တီးရီးယားမျိုးစိတ်တစ်ခု၏ နည်းပါးသော အချိုးအစားကို သိရှိခြင်းသည် မလုံလောက်ကြောင်း မပြသနိုင် သို့မဟုတ် ဆက်စပ်သော သက်ရှိသတ္တဝါကို မျိုချခြင်းက လက္ခဏာများကို တိုးတက်ကောင်းမွန်စေမည်ဟု မဖော်ပြနိုင်ပါ။ ပရိုဘိုင်အိုတစ်အထောက်အထားသည် အညွှန်း၊ ဖော်မြူလာနှင့် တစ်ခါတစ်ရံ တိကျသောမျိုးစိတ်ပေါ်တွင် မူတည်ပါသည်။ IBS အတွက်၊ 2021 ACG လမ်းညွှန်ချက်သည် အထောက်အထားများ အလွန်မရေရာသောကြောင့် အလုံးစုံ လက္ခဏာများအတွက် ပရိုဘိုင်အိုတစ်များကို ဆန့်ကျင်ရန် အကြံပြုထားသည်။.
AI ပါဝါသုံး သွေးစစ်ဆေးမှု ရလဒ်ကို ယနေ့ စတင် ခွဲခြမ်းစိတ်ဖြာပါ
Kantesti ကို အချိန်မီ၊ တိကျသော ဓာတ်ခွဲခန်း စစ်ဆေးမှု ရလဒ်ခွဲခြမ်းစိတ်ဖြာမှုအတွက် ယုံကြည်သည့် ကမ္ဘာတစ်ဝန်း အသုံးပြုသူ 2 သန်းကျော်နှင့် ပူးပေါင်းပါ။ သင့် သွေးစစ်ဆေးမှု ရလဒ်များကို တင်ပြီး စက္ကန့်ပိုင်းအတွင်း 15,000+ biomarker များ၏ ပြည့်စုံသော အဓိပ္ပာယ်ဖတ်ချက်ကို ရယူပါ။.
📚 ကိုးကားထားသော သုတေသန ထုတ်ဝေမှုများ
Klein, T., Mitchell, S., & Weber, H. (2026). ဘာသာစကားများစွာဖြင့် AI အကူအညီဖြင့် ဆေးပညာဆိုင်ရာ ဆုံးဖြတ်ချက်ပံ့ပိုးမှု- အစောပိုင်း Hantavirus ခွဲခြားခြင်း- ဒီဇိုင်း၊ အင်ဂျင်နီယာ- အတည်ပြုချက်၊ နှင့် လက်တွေ့-ကမ္ဘာ-တွင်-အကောင်-အထည်-ဖော်-မှု- 50,000-ကျော်-အနက်-ဖွင့်-ဆို-ထား-သော-သွေး-စစ်-အစီရင်ခံစာ-များ-တစ်-လျှောက်. Kantesti AI Medical Research.
Klein, T., Mitchell, S., & Weber, H. (2026). 100,000 Synthetic Test Cases များပေါ်တွင် Kantesti Blood-Test Interpretation Engine ကို အလိုအလျောက် နည်းပညာဆိုင်ရာ စံနှုန်းတင် (benchmark) ပြုလုပ်ခြင်း—Pre-Registered, Rubric-Based. Kantesti AI Medical Research.
📖 ပြင်ပ ဆေးဘက်ဆိုင်ရာ ကိုးကားချက်များ
Porcari S et al. (2025). International consensus statement on microbiome testing in clinical practice. The Lancet Gastroenterology & Hepatology.
Costea PI et al. (2017). Towards standards in human fecal sample processing. Nature Biotechnology.
⚕️ ဆေးဘက်ဆိုင်ရာ ရှင်းလင်းချက်
ဤဆောင်းပါးသည် ပညာရေးဆိုင်ရာ ရည်ရွယ်ချက်အတွက်သာ ဖြစ်ပြီး ဆေးဘက်ဆိုင်ရာ အကြံဉာဏ် မဟုတ်ပါ။ ရောဂါရှာဖွေခြင်းနှင့် ကုသမှု ဆုံးဖြတ်ချက်များအတွက် အရည်အချင်းပြည့်မီသော ကျန်းမာရေးစောင့်ရှောက်မှုပေးသူနှင့် အမြဲတမ်း တိုင်ပင်ပါ။.
E-E-A-T ယုံကြည်မှု အချက်ပြများ
အတွေ့အကြုံ
ဆရာဝန်ဦးဆောင်သည့် ဓာတ်ခွဲခန်း အဓိပ္ပာယ်ဖတ်ခြင်း လုပ်ငန်းစဉ်များကို ပြန်လည်သုံးသပ်ခြင်း။.
ကျွမ်းကျင်မှု
biomarker များသည် ဆေးဘက်ဆိုင်ရာ အခြေအနေတွင် မည်သို့ ပြုမူနေသည်ကို အာရုံစိုက်သည့် ဓာတ်ခွဲခန်း ဆေးပညာ။.
အခွင့်အာဏာရှိခြင်း
ဒေါက်တာ Thomas Klein မှ ရေးသားပြီး ဒေါက်တာ Sarah Mitchell နှင့် ပါမောက္ခ ဒေါက်တာ Hans Weber တို့က ပြန်လည်သုံးသပ်ထားသည်။.
ယုံကြည်စိတ်ချရမှု
စိတ်ပူစရာများကို လျော့ချရန်အတွက် ရှင်းလင်းသော နောက်ဆက်တွဲ လမ်းကြောင်းများပါဝင်သည့် သက်သေအထောက်အထားအခြေပြု အဓိပ္ပာယ်ဖတ်ချက်။.