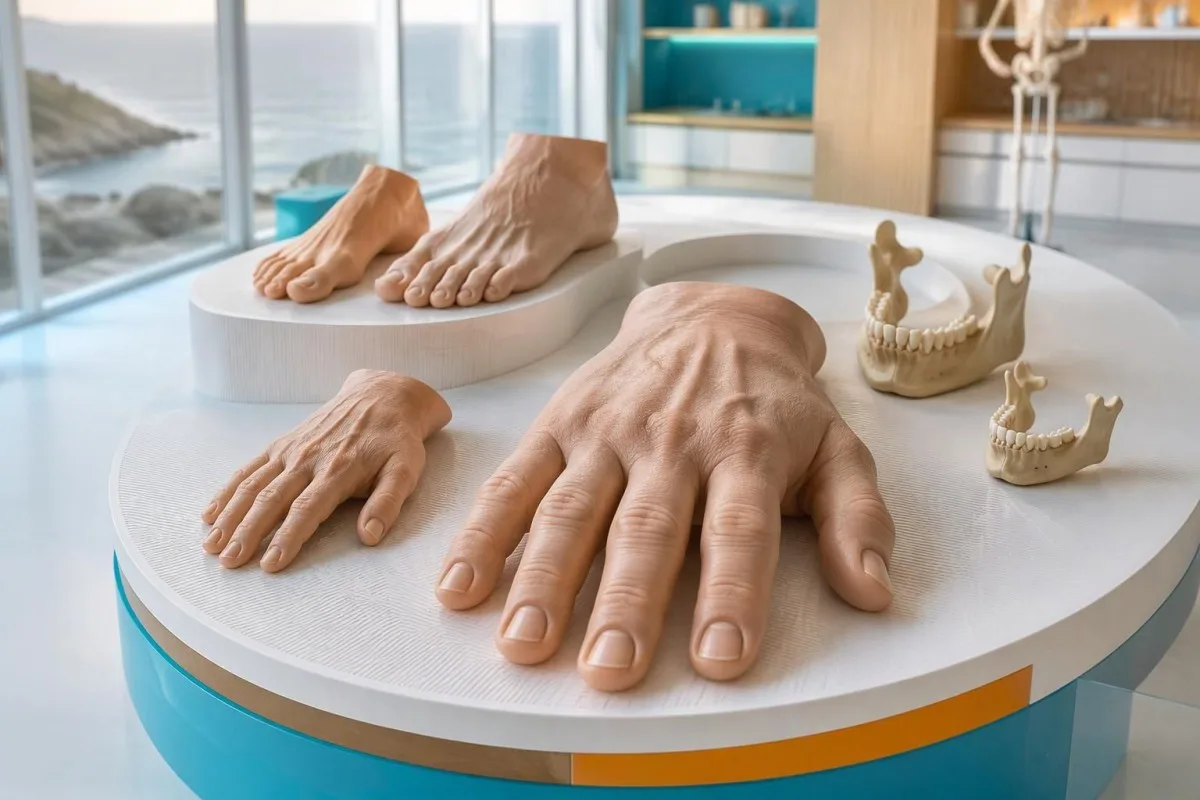
Progressively larger hands or feet, a changing jaw, wider tooth spacing, increased sweating and sleep apnea can suggest acromegaly—especially when several changes develop together. Symptoms cannot confirm it; clinical assessment and an age-adjusted IGF-1 blood test are needed.

اہم نکات
- ترقی matters more than an isolated symptom: increasing ring size plus a changing bite over several years deserves clinical review, even without dramatic facial changes.
- Hands and feet can become broader after adult height has stopped increasing; there is no validated number of ring or shoe sizes that diagnoses acromegaly.
- Facial changes may include a more prominent lower jaw, broader nose, thicker lips and new spaces between teeth; comparing 2 dated photographs can clarify the timeline.
- سلیپ ایپنیا alongside hand, foot or jaw enlargement strengthens the reason to check for growth hormone excess; snoring alone is not specific.
- IGF-1 is the usual first biochemical test, and its reference interval must match the person's age and the laboratory's assay.
- The 1.3× threshold comes from the 2024 acromegaly consensus: IGF-1 above 1.3 times the age-adjusted upper limit can confirm diagnosis when characteristic clinical features are present.
- گلوکوز سپریشن ٹیسٹنگ (Glucose suppression testing) sometimes resolves uncertainty: a clinician may use 75 g oral glucose and serial growth hormone measurements rather than relying on one random growth hormone result.
- ایمرجنسی علامات include a sudden severe headache with new visual problems, vomiting or reduced alertness; seek emergency care rather than waiting for a hormone appointment.
Which acromegaly symptoms deserve attention?
Acromegaly symptoms are concerning when hand, foot or facial enlargement progresses alongside changes such as sweating, snoring or a shifting bite. A single tight ring is usually nonspecific; 2 independent changes developing together provide a stronger reason for clinical evaluation, although no symptom checklist can establish the diagnosis.

Acromegaly results from excess growth hormone after the growth plates have closed. Growth hormone stimulates production of insulin-like growth factor 1, or IGF-1, which promotes enlargement of soft tissues and some bones; most cases arise from a noncancerous pituitary adenoma, not from a dietary problem.
Gradual change can be harder to recognize than a sudden symptom. Comparing your current appearance with photographs from 3–5 years earlier may reveal a changing brow, jaw or nose that daily mirror checks miss; that interval is a practical comparison window, not a required waiting period.
For example, imagine a 46-year-old whose wedding ring has been resized twice, whose shoes have become wider and whose dentist has documented a changing bite. Stable body weight makes simple weight gain a less complete explanation, but examination and hormone testing are still needed before calling this acromegaly.
Kantesti is an AI blood test analyzer that can help explain an IGF-1 report without treating a symptom list as a diagnosis. ہماری تنظیم اور مقصد explain our role: we support understanding of existing results, while a clinician evaluates physical changes and decides whether specialist testing is appropriate.
How acromegaly changes hands and ring size
Acromegaly can make adult hands broader and thicker, causing rings to stop fitting gradually rather than only during hot weather. Enlargement affecting both hands over time is more suggestive than swelling confined to 1 finger, particularly when shoe fit, facial shape or sweating also changes.

Ring size measures circumference, not the cause of enlargement. A change of 1 ring size can reflect weight gain, arthritis, fluid retention or different sizing systems; acromegaly becomes a consideration when the change is persistent and accompanied by thickening of the palms or other characteristic findings.
Temporary swelling behaves differently from progressive tissue enlargement. Checking whether the same ring fits in the morning and evening for 1 week can identify fluctuation, but this home observation cannot exclude acromegaly; avoid repeatedly forcing a tight ring over a swollen joint.
Thyroid-related fluid retention can resemble hand puffiness without reproducing the full acromegaly pattern. Our explanation of mild thyroid underactivity helps distinguish laboratory-defined thyroid changes from physical enlargement; a slightly abnormal TSH alone should not automatically explain a multi-year change in hand and jaw size.
A useful appointment record separates 2 observations: overall hand broadening and enlargement centered on particular joints. Bring approximate dates of ring resizing and note whether knuckle pain, morning stiffness or palm thickening came first; these details help a clinician distinguish tissue growth from joint disease or intermittent swelling.
When increasing shoe size is an early clue
Progressively wider or larger feet in adulthood can be an early sign of acromegaly, especially when hand size changes too. Replacing shoes 1 time is not diagnostic: brand differences, pregnancy-related foot changes, weight gain, bunions and falling arches can also alter fit without growth hormone excess.

Foot width sometimes changes before the stated shoe size does. If shoes bought 3 years apart have the same length but increasingly roomy toe boxes are necessary, record that detail; soft-tissue thickening and mechanical foot changes can coexist, so length alone is an incomplete measurement.
Acromegaly-related enlargement generally develops gradually and affects both feet. Sudden swelling of 1 leg or foot, particularly with calf discomfort or warmth, needs a different assessment; our guide to urgent one-sided leg swelling explains why that pattern should not be attributed to a slow hormonal disorder.
For a hypothetical 51-year-old, moving from the same manufacturer's size 8 to size 10 over several years would be more informative than comparing unrelated brands. The observation becomes more meaningful if a ring has also needed resizing, but there is no validated shoe-size increase that confirms acromegaly.
Bring 2 pairs of dated shoes or purchase records if available, rather than buying measuring equipment. A clinician can assess edema, arches, joints and soft tissues together; foot photographs should be taken in comparable positions because perspective can make a stable foot appear larger.
What jaw and tooth changes can reveal
Acromegaly facial changes can include a more prominent lower jaw, broader nose, thicker lips and wider spacing between teeth. A changing bite documented on 2 dental visits can be more useful than a subjective impression of looking different, because jaw growth and ordinary weight gain affect appearance differently.
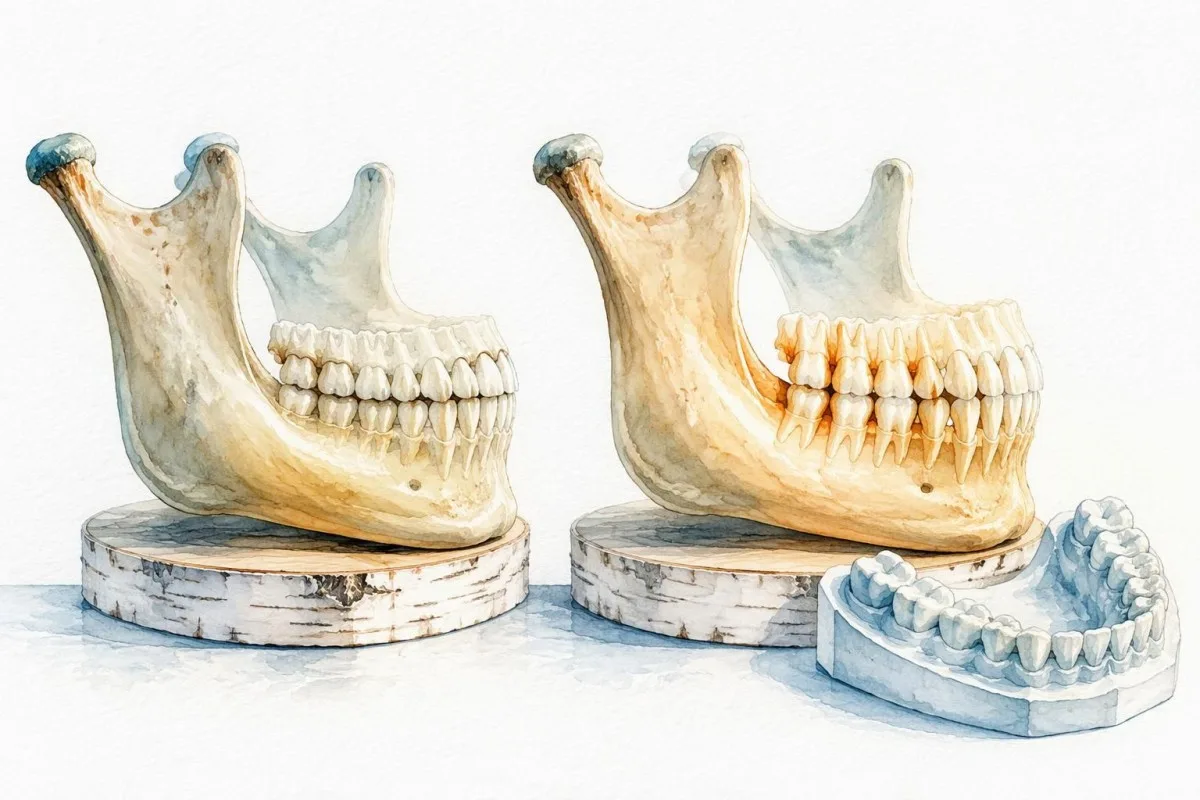
New tooth spacing does not necessarily mean the teeth themselves have enlarged. Enlargement of the jaw can change their positions relative to one another, while gum disease, missing teeth and orthodontic movement can also produce gaps; comparing dental records from 2 dates helps identify which process is more plausible.
Photographs are most useful when lighting, camera distance and head position are similar. Choose 1 older front-view photograph and 1 side view if possible; wide-angle phone lenses can exaggerate the nose and jaw, so apparent enlargement in a close selfie is not reliable evidence of hormone excess.
Bone disorders can also change skull or jaw shape, but usually require a different diagnostic pathway. Our explanation of Paget disease testing describes one alternative; an ALP result, whether normal or raised, cannot replace IGF-1 testing when the broader pattern suggests acromegaly.
Ask a dentist whether 2 findings are documented: a progressive bite change and new spacing not explained by gum or orthodontic disease. A dentist may recognize the physical pattern, but photographs, bite impressions and dental imaging cannot confirm acromegaly without an endocrine assessment.
Why sweating matters only in the wider pattern
Increased sweating and oily or thicker skin can accompany acromegaly, but sweating alone is a weak diagnostic clue. Persistent sweating becomes more relevant when it develops alongside at least 1 structural change, such as broader hands or a changing jaw; the combination guides evaluation rather than proving a hormonal cause.
A useful sweating history distinguishes persistent excess perspiration from brief episodes. Recording triggers and timing for 7 days can reveal links to exercise, medicines, meals or hot flashes; acromegaly does not have a distinctive sweat odor or a validated sweating frequency that separates it from other causes.
Episodic sweating with pounding headaches, palpitations and marked blood-pressure swings suggests a different endocrine question. Our guide to adrenal hormone warning patterns explains when metanephrine testing may be considered; that test and IGF-1 answer different questions, even when 2 conditions share sweating as a symptom.
Hot flashes can coincide with the age at which acromegaly becomes noticeable, creating an easy attribution error. The discussion of fluctuating menopause hormone results explains why 1 estradiol measurement is not a complete explanation for sweating, especially if ring fit and facial shape are also changing.
Skin tags are common and are not an acromegaly screening test. In a hypothetical 48-year-old with new sweating and several skin tags, we would distinguish metabolic or medication-related explanations from the much more specific observation of progressive hand and jaw enlargement; counting skin tags does not resolve that distinction.
How sleep apnea connects with tissue enlargement
Acromegaly can contribute to obstructive sleep apnea through enlargement of the tongue and other upper-airway tissues. Loud snoring, witnessed breathing pauses and daytime sleepiness warrant sleep evaluation; when these occur with progressive hand or jaw enlargement, an IGF-1 test may also be appropriate rather than assuming 1 diagnosis explains everything.
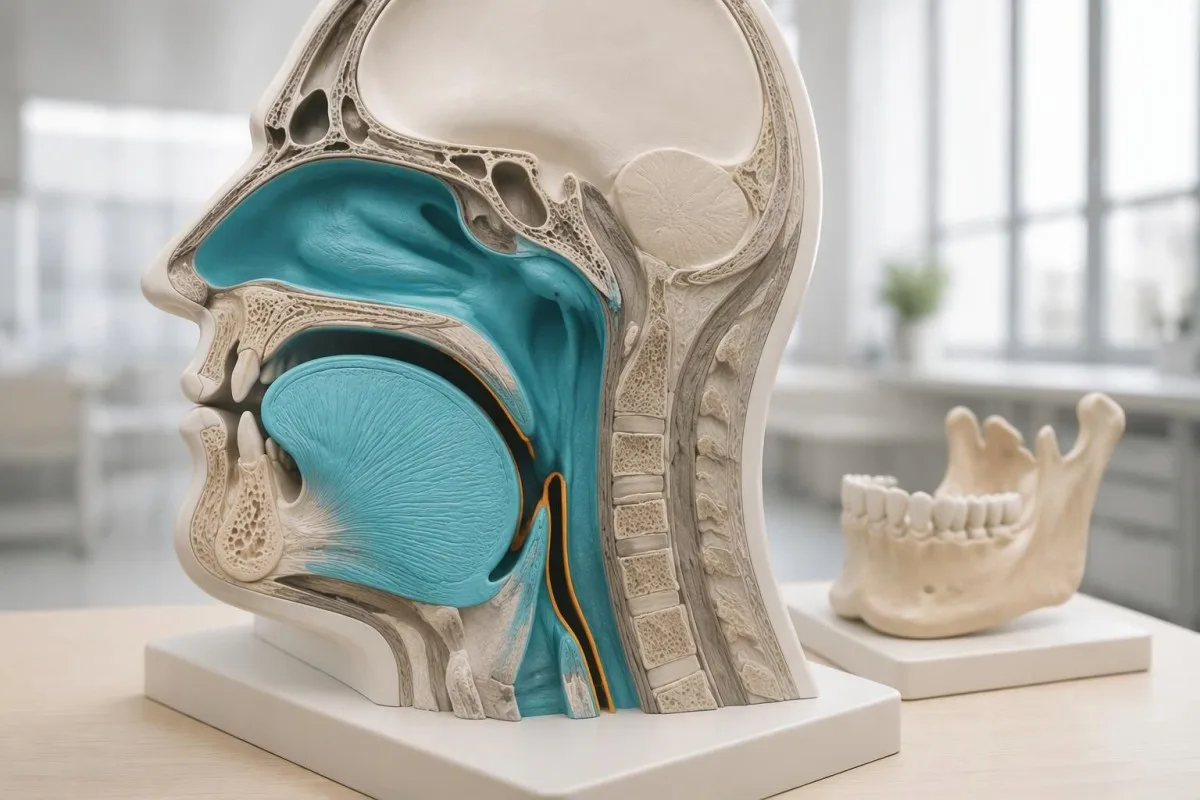
Obstructive sleep apnea is assessed using respiratory events during sleep, not facial appearance. An apnea–hypopnea index of at least 5 events/hour with relevant symptoms or comorbidities, or at least 15 events/hour regardless of symptoms, commonly supports adult diagnosis; neither threshold identifies the underlying cause as acromegaly.
Sleep studies answer a different question from a daytime sleepiness test. Our explanation of sleep-study test selection distinguishes overnight respiratory assessment from testing for narcolepsy; a normal or abnormal multiple sleep latency test does not assess growth hormone excess.
The Endocrine Society guideline recommends considering IGF-1 testing when several associated conditions occur together, including sleep apnea, diabetes, arthritis, carpal tunnel syndrome, excessive sweating and hypertension (Katznelson et al., 2014). Having 1 of these common conditions does not justify assuming acromegaly, but their coexistence can lower the threshold for discussing testing.
Treating hormone excess does not guarantee that sleep apnea disappears. If a person already uses positive-airway-pressure treatment, 1 improved night of sleep is not evidence that it can be stopped; residual airway anatomy and weight-related factors may persist, and any treatment change requires reassessment by the sleep team.
Hand numbness and joint pain: supporting clues
Carpal tunnel syndrome and joint discomfort can accompany acromegaly because tissue enlargement affects nerves, cartilage and joint mechanics. Numbness in the thumb, index and middle fingers is more consistent with median-nerve compression than numbness involving all 5 fingers equally, but the nerve pattern does not establish a hormonal cause.

Bilateral symptoms are useful context, not proof of acromegaly. Nighttime tingling in both hands plus 2 ring resizings and a changing bite deserves a different discussion from isolated tingling after repetitive wrist use; the associated structural changes explain why an endocrine cause might enter the differential.
The fingers involved help localize the problem before choosing tests. Our guide to median-nerve symptom patterns explains why little-finger numbness may point elsewhere; an abnormal nerve-conduction study can confirm nerve dysfunction without answering whether IGF-1 excess contributed.
Joint symptoms can outlast successful control of growth hormone excess. After years of altered cartilage and bone mechanics, correcting 1 hormone pathway does not necessarily reverse established degenerative changes; this is why early recognition matters even when pain has been labeled ordinary arthritis.
Kantesti can help organize an IGF-1 result alongside glucose or thyroid findings, but nerve symptoms still require clinical localization. For a hypothetical 55-year-old, distinguishing 2 problems—median-nerve compression and progressive tissue enlargement—avoids interpreting every abnormal laboratory value as the cause of hand numbness.
Other clues: glucose, blood pressure and hormone changes
Growth hormone excess can contribute to insulin resistance, high blood pressure and changes in other pituitary hormone functions. These findings are common outside acromegaly; concern rises when at least 2 metabolic or hormonal problems develop alongside progressive hand, foot or facial enlargement, rather than when a single routine result is abnormal.

Diabetes is a possible associated condition, not a diagnostic shortcut. An HbA1c of at least 6.5% or fasting plasma glucose of at least 126 mg/dL, equivalent to 7.0 mmol/L, meets commonly used diabetes thresholds when confirmation requirements are satisfied; neither value identifies growth hormone excess as the cause.
Thirst and blurred vision may therefore need evaluation independently of changes in appearance. Our guide to ہائی گلوکوز وارننگ کی علامات explains why a hypothetical glucose result of 280 mg/dL with symptoms deserves prompt clinical attention, even while a separate acromegaly assessment is being arranged.
Pituitary dysfunction can alter menstrual cycles, sexual function or fertility, but these symptoms have many causes. Our women's hormonal symptom guide discusses relevant alternatives; missing 2 periods alongside progressive jaw and hand changes deserves a broader review than assuming a single age-related explanation.
At Kantesti, we distinguish a complication marker from a disease-specific test: 1 abnormal HbA1c cannot substitute for age-adjusted IGF-1. Bring blood-pressure readings, medication names and the timing of hormonal symptoms, because a clinician may need to assess associated conditions and pituitary function in parallel.
What else can cause similar physical changes?
Weight gain, fluid retention, thyroid disease, arthritis and dental problems can resemble parts of the acromegaly pattern. The distinction depends on the distribution and progression of change: enlargement affecting hands, feet and jaw over several years is harder to explain with 1 localized joint or dental problem.
Weight gain often changes facial fullness without producing the same progressive mandibular prominence or dental spacing. In a hypothetical 50-year-old whose weight rose by 12 kg, tighter rings may have an ordinary explanation; a dentist-confirmed change in jaw relationship still deserves separate attention rather than dismissal.
Cushing syndrome can cause facial rounding, metabolic problems and muscle weakness, but its testing pathway differs from acromegaly. Our guide to cortisol screening and confirmation explains why 1 random cortisol result does not establish Cushing syndrome, just as a random growth hormone result does not establish acromegaly.
A pituitary problem can sometimes produce low free T4 without an appropriately elevated TSH. Our explanation of low T4 with normal TSH helps clarify why those 2 measurements must be interpreted together; a normal TSH alone is not a complete assessment of pituitary-related thyroid function.
Childhood growth and adult tissue enlargement should not be confused. Excess growth hormone before growth-plate closure can cause gigantism, whereas adult acromegaly does not usually increase height; a naturally large shoe size that has remained unchanged for 20 years is not equivalent to progressive adult enlargement.
Why IGF-1 is usually the first blood test
Age-adjusted IGF-1 is usually the first biochemical test when acromegaly is suspected because it reflects growth hormone activity more consistently than a single growth hormone measurement. The 2024 consensus states that characteristic clinical features plus IGF-1 above 1.3 times the age-adjusted upper limit can confirm the diagnosis (Giustina et al., 2024).

IGF-1 has no single normal adult range that applies to every age and assay. For example, if a hypothetical laboratory upper limit is 250 ng/mL and the result is 340 ng/mL, the result is 1.36 times that upper limit; using another laboratory's range could change the interpretation incorrectly.
A normal IGF-1 usually argues against acromegaly, but confounders can reduce its reliability. Poorly controlled diabetes, significant liver disease, undernutrition and oral estrogen can affect results; 1 normal measurement should be reviewed in context when physical features are compelling, rather than overridden or accepted automatically.
Kantesti is an AI blood test interpretation platform that can explain an IGF-1 value relative to the reference interval printed on the report. ہماری بائیو مارکر کی تشریح گائیڈ provides laboratory context, but identifying the assay, age range and clinical reason for testing remains part of clinician-led assessment.
Liver and nutritional status matter because IGF-1 production is closely linked to hepatic function and systemic health. Our سیرم پروٹین کی تشریح کا رہنما اصول explains relevant background markers; 1 albumin result cannot validate or invalidate IGF-1, but it may prompt a closer review of illness or nutrition.
| سطح | حد | اس کا مطلب |
|---|---|---|
| لیبارٹری وقفے کے اندر | At or below the age-adjusted upper limit | Usually argues against acromegaly; consider confounders if clinical suspicion remains strong. |
| حد سے کچھ زیادہ (بارڈر لائن) | >1.0–1.3× the age-adjusted upper limit | Requires clinical review; repeat testing and sometimes glucose suppression testing resolve uncertainty. |
| Above the consensus diagnostic threshold | >1.3× the age-adjusted upper limit | Can confirm acromegaly when characteristic clinical features are present; specialist interpretation is needed. |
When growth hormone suppression testing is useful
A glucose suppression test may help when IGF-1 results and clinical findings are equivocal. The test commonly uses 75 g oral glucose followed by serial growth hormone measurements; it assesses whether growth hormone suppresses appropriately, rather than treating one high random growth hormone value as diagnostic.

Growth hormone is released in pulses and can rise with sleep, exercise and physiological stress. That is why 1 random value, whether high or low, is unreliable for establishing or excluding acromegaly; an isolated result should not trigger a diagnosis based solely on a generic laboratory range.
Diagnostic cutoffs have changed with assay sensitivity. The Endocrine Society guideline used suppression below 1 ng/mL after glucose to exclude acromegaly in the appropriate testing context (Katznelson et al., 2014); specialist practice may use lower assay-dependent thresholds, including 0.4 ng/mL, rather than one universal cutoff.
For example, a hypothetical IGF-1 of 275 ng/mL against an upper limit of 250 ng/mL equals 1.10 times the upper limit. If growth hormone falls to 0.7 ng/mL, interpretation may differ by assay and clinical context; repeating IGF-1 and reviewing confounders is safer than selecting whichever cutoff gives a preferred answer.
Kantesti does not independently validate an acromegaly diagnosis or choose a glucose-test cutoff. Our کلینیکل میتھڈولوجی اور حدود explain why interpretation must remain tied to the source report; our separate guide to لیبارٹری میں معنی خیز تبدیلیاں explains why 2 results are not automatically comparable.
When to book a review—and when symptoms are urgent
Book a clinical review for unexplained progressive enlargement of hands, feet or jaw, especially when sweating, sleep apnea or a changing bite accompanies it. There is no minimum duration you must wait; a sudden severe headache with new visual symptoms is a separate emergency, not something to observe for 2 weeks.
A pituitary growth can affect nearby visual pathways, sometimes causing loss of peripheral vision. New difficulty noticing objects on either side, double vision or a substantial visual change warrants prompt assessment; involvement of 1 or both eyes does not reliably determine whether the cause is pituitary, retinal or neurological.
Sudden severe headache with vomiting, double vision, reduced alertness or visual loss can indicate pituitary apoplexy or another neurological emergency. Seek emergency care immediately rather than waiting for an IGF-1 result; even 1 abrupt neurological warning symptom can justify urgent assessment when severe or unexplained.
Pituitary adenomas are usually noncancerous, but noncancerous does not mean harmless when a growth produces excess hormones or presses on nearby structures. Our guide to neurological warning symptoms explains why progressive and sudden symptoms follow different routes; a 5-year appearance change and an abrupt visual deficit should not receive the same triage.
For gradual changes without emergency features, prepare 3 categories of evidence: appearance or sizing changes, associated symptoms and existing results. Ask whether an age-adjusted IGF-1 test and endocrine referral are appropriate; avoid arriving with a self-confirmed diagnosis or postponing care until every possible symptom appears.
What happens after an abnormal hormone result?
After biochemical confirmation or strong specialist-supported suspicion, pituitary MRI usually identifies the source and its relationship to surrounding structures. Imaging alone cannot confirm acromegaly: a pituitary finding may be incidental, and the 10 mm size boundary between microadenoma and macroadenoma describes size rather than hormone secretion.
A pituitary microadenoma measures less than 10 mm, while a macroadenoma measures at least 10 mm. A smaller growth can still secrete clinically significant growth hormone; conversely, a larger nonfunctioning growth may not cause acromegaly, so dimensions and biochemical activity answer different questions.
An endocrine team may assess prolactin, thyroid function, adrenal function and reproductive hormone pathways as well as IGF-1. Our guide to ہلکی پرولیکٹین میں اضافہ explains why 1 raised prolactin result can have several causes; it does not prove that a pituitary growth is secreting multiple hormones.
Visual-field testing may be needed when MRI shows proximity to the optic chiasm or when vision is affected. A reassuring ability to read a phone screen at 30 cm does not exclude peripheral field loss; formal testing assesses a different part of vision from everyday reading.
Kantesti AI cannot infer pituitary growth size from an IGF-1 concentration. If the pituitary MRI does not explain convincing biochemical findings, a specialist may review imaging quality, assay issues and rare alternative sources; a negative scan should not be converted into an unsupported claim that 1 hormone result was necessarily wrong.
Preparing your appointment and checking our sources
The most useful next step is a short timeline connecting physical changes, associated symptoms and existing laboratory results. Bring 2 dated photographs if available, ring or shoe history and the full IGF-1 report; these support a focused clinical discussion without turning home observations into a diagnostic score.

Write down when each change began and whether it has continued, fluctuated or stopped. A 1-page record is usually more useful than dozens of unlabeled photographs: include weight changes, dental observations, sleep-apnea treatment and medication or supplement use, especially prescribed hormones that could influence laboratory interpretation.
Kantesti is an AI-powered blood test analysis tool that can help explain an existing IGF-1 report and organize questions for your clinician. ہماری رہنمائی AI کی رپورٹ کی وضاحتوں کی جانچ describes source verification; an explanation cannot replace examination, and a normal metabolic panel does not mean IGF-1 was tested.
Protect identifying information when sharing laboratory reports or old photographs. Kantesti's رازداری اور ڈیٹا سے متعلق رہنمائی explains our data approach; use only the materials needed for the question, and obtain permission before sharing another person's results or images, even when comparing 2 family members.
The clinical recommendations here draw on the Endocrine Society's 2014 guideline and the 2024 diagnostic consensus, listed below. The 2 accompanying Figshare publications concern gastrointestinal and women's hormonal health; they are related educational resources, not evidence for acromegaly diagnosis, and a repository DOI does not by itself establish peer review.
اکثر پوچھے جانے والے سوالات
ایکرومیگالی کی ابتدائی علامات کیا ہیں؟
اکرومیگالی کی ابتدائی علامات میں انگوٹھیوں کا بتدریج زیادہ تنگ ہونا، جوتوں کا سائز بڑھنا، پسینہ زیادہ آنا، کارپل ٹنل کی نئی علامات اور دانتوں کے کاٹنے کے انداز میں تبدیلی شامل ہو سکتی ہے۔ تاریخ درج 2 تصاویر یا دانتوں کے ریکارڈ کا موازنہ کرنے سے ایسی تبدیلیاں سامنے آ سکتی ہیں جنہیں روزمرہ میں محسوس کرنا مشکل ہوتا ہے۔ انگوٹھی کے سائز میں کسی مخصوص اضافے یا علامات کی کسی خاص تعداد سے اکرومیگالی کی تصدیق نہیں ہوتی۔ غیر واضح طور پر بڑھتی ہوئی تبدیلیوں پر طبی معائنے اور عمر کے مطابق IGF-1 ٹیسٹ کروانا چاہیے۔
کیا انگوٹھی یا جوتے کا سائز بڑھنے کا مطلب ہے کہ مجھے اکرو میگالی ہے؟
انگوٹھی یا جوتے کا سائز بڑھنے کا بذاتِ خود یہ مطلب نہیں کہ آپ کو ایکرومیگالی ہے۔ وزن بڑھنا، جسم میں سیال جمع ہونا، گٹھیا، حمل کے دوران پاؤں میں تبدیلیاں اور جوتوں کے فرق سے بھی ان کی فٹنگ بدل سکتی ہے۔ جوتے کے سائز میں ایک نمبر اضافے کی تشخیصی اہمیت ثابت نہیں، لیکن جبڑے کی ساخت میں تبدیلی، پسینہ آنے یا نیند میں سانس رکنے کے ساتھ مسلسل بڑھتا ہوا سائز طبی معائنے کا تقاضا کرتا ہے۔ تشخیص کا انحصار طبی علامات اور ہارمونز کے مناسب ٹیسٹوں پر ہوتا ہے۔
کیا اکرو میگالی آپ کے چہرے میں تبدیلی لا سکتی ہے یا دانتوں کے درمیان خلا پیدا کر سکتی ہے؟
اکرومیگالی سے نچلا جبڑا زیادہ نمایاں ہو سکتا ہے اور جبڑے کے حجم میں تبدیلی کے ساتھ دانتوں کے درمیان فاصلہ بڑھ سکتا ہے۔ اس سے ناک بھی چوڑی اور ہونٹ موٹے ہو سکتے ہیں، لیکن مسوڑھوں کی بیماری، آرتھوڈونٹک علاج کے دوران دانتوں کی حرکت اور چہرے میں معمول کی تبدیلیوں سے بھی ملتی جلتی علامات پیدا ہو سکتی ہیں۔ دو تاریخوں کے دانتوں کے ریکارڈ کا موازنہ کرنے سے یہ طے کرنے میں مدد مل سکتی ہے کہ آیا دانتوں کی باہمی نشست یا ان کے درمیان فاصلہ بڑھا ہے۔ حیاتی کیمیائی جانچ کے بغیر چہرے کی تصاویر اور دانتوں کے معائنے کے نتائج سے اکرومیگالی کی تصدیق نہیں ہو سکتی۔
اکرومیگالی کی جانچ کے لیے کون سا خون کا ٹیسٹ کیا جاتا ہے؟
اکرومیگالی کا شبہ ہونے پر عموماً عمر کے مطابق ایڈجسٹ کیا گیا IGF-1 پہلا خون کا ٹیسٹ ہوتا ہے۔ 2024 کے اتفاقِ رائے کے مطابق، اگر مخصوص طبی علامات موجود ہوں تو عمر کے مطابق ایڈجسٹ شدہ بالائی حد سے 1.3 گنا زیادہ IGF-1 اکرومیگالی کی تصدیق کر سکتا ہے۔ سرحدی یا متضاد نتائج کی صورت میں دوبارہ ٹیسٹ اور معالج کی نگرانی میں گلوکوز سپریشن ٹیسٹ کی ضرورت پڑ سکتی ہے۔ نمو کے ہارمون کی ایک واحد بے ترتیب پیمائش تشخیص کے لیے قابلِ اعتماد متبادل نہیں ہے۔
کیا IGF-1 کا نتیجہ نارمل ہونے کے باوجود آپ کو ایکرومیگالی ہو سکتی ہے؟
عمر کے مطابق ایڈجسٹ کیا گیا، قابلِ اعتماد طریقے سے ناپا گیا نارمل IGF-1 عموماً غیر علاج شدہ ایکرومیگالی کے خلاف دلیل ہوتا ہے۔ تاہم، بے قابو ذیابیطس، جگر کی شدید بیماری، غذائیت کی کمی اور منہ سے لی جانے والی ایسٹروجن IGF-1 کو متاثر کر سکتی ہیں اور اس کی تشریح کو پیچیدہ بنا سکتی ہیں۔ اگر 1 نارمل نتیجے کے باوجود جسمانی تبدیلیاں برقرار رہیں تو معالج کو جانچ کے طریقۂ کار، حوالہ جاتی حد اور ممکنہ مداخلت کرنے والے عوامل کا جائزہ لینا چاہیے۔ دوبارہ ٹیسٹ یا ماہر سے معائنہ مناسب ہو سکتا ہے، بجائے اس کے کہ یہ فرض کر لیا جائے کہ علامات ہی تشخیص ثابت کرتی ہیں یا طبی تناظر کبھی اہمیت نہیں رکھتا۔
When should possible acromegaly symptoms be treated as an emergency?
Gradual hand, foot or facial enlargement usually calls for a scheduled clinical review rather than emergency care. A sudden severe headache with new visual loss, double vision, vomiting or reduced alertness needs emergency assessment because pituitary apoplexy and other neurological emergencies are possible. Do not wait 24 hours for a routine hormone result when these warning signs occur. New or progressive visual problems also deserve prompt clinical evaluation, even without obvious changes in appearance.
اپنے خون کے ٹیسٹ کے نتائج کی وضاحت حاصل کریں
اپنی لیب رپورٹ اپ لوڈ کریں اور Kantesti کا AI چند سیکنڈ میں ہر بائیومارکر کو آسان زبان میں سمجھائے گا۔ دنیا بھر میں 2 ملین سے زیادہ افراد استعمال کرتے ہیں۔.
حوالہ جات
- Klein, T., Mitchell, S., & Weber, H. (2026). روزہ رکھنے کے بعد اسہال، پاخانے میں سیاہ ذرات اور معدے و آنتوں کی رہنما معلومات 2026۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Klein, T., Mitchell, S., & Weber, H. (2026). خواتین کی صحت کی رہنما: بیضہ ریزی، سن یاس اور ہارمونل علامات۔. Kantesti AI طبی تحقیق۔. ڈی او آئی
- Katznelson L et al. (2014). Acromegaly: An Endocrine Society Clinical Practice Guideline. جرنل آف کلینیکل اینڈوکرائنولوجی اینڈ میٹابولزم۔. ڈی او آئی
- Giustina A et al. (2024). Consensus on criteria for acromegaly diagnosis and remission. Pituitary. ڈی او آئی
- 2M+تجزیہ کیے گئے ٹیسٹ
- 127+ممالک
- 100+زبانیں
طبی ٹیم کے بارے میں


E-E-A-T اعتماد کے اشارے
تجربہ
معالج کی قیادت میں لیب تشریح کے ورک فلو کا کلینیکل جائزہ۔.
مہارت
لیبارٹری میڈیسن کا فوکس یہ کہ بایومارکرز کلینیکل سیاق میں کیسے برتاؤ کرتے ہیں۔.
مستندیت
ڈاکٹر تھامس کلائن نے طبی جائزہ لیا، جبکہ ڈاکٹر سارہ مچل اور پروفیسر ڈاکٹر ہانس ویبر نے بھی تعاون کیا۔.
امانت داری
شواہد پر مبنی تشریح واضح فالو اپ راستوں کے ساتھ تاکہ گھبراہٹ کم ہو۔.





طبی دستبرداری
یہ مضمون صرف تعلیمی مقاصد کے لیے ہے اور طبی مشورہ نہیں ہے۔ تشخیص اور علاج کے فیصلوں کے لیے ہمیشہ کسی مستند صحت کے ماہر سے رجوع کریں۔.
شائع ہوا۔ · ادارتی ٹیم سے رابطہ کریں
Kantesti Ltd کی جانب سے شائع کردہ، انگلینڈ اور ویلز میں رجسٹرڈ، کمپنی نمبر. 17090423, ، لندن، برطانیہ۔.
