Autoimmune encephalitis diagnosis combines the symptom pattern, spinal fluid testing, MRI and EEG while excluding infections and other causes. Blood antibodies alone cannot confirm it, and negative antibodies do not always exclude it; sudden confusion, a first seizure or reduced consciousness needs emergency assessment.

Punts essencials
- Diagnòstic requires a compatible clinical syndrome and supporting investigations—not one positive antibody result.
- Lo moment d’aparicion dels simptòmas matters: established possible autoimmune encephalitis criteria emphasize progression over less than 3 months.
- Avaluacion d’emergéncia is needed for sudden confusion, a first seizure, reduced consciousness, breathing changes or rapidly worsening behavior.
- Seizure duration of 5 minutes or repeated seizures without recovery requires an immediate emergency response.
- Paired antibody testing usually means testing both cerebrospinal fluid and serum; the most informative specimen differs by antibody.
- Anti-NMDA receptor antibodies should include CSF IgG against GluN1; one study found serum antibodies absent in 14.4% of confirmed cases.
- Normal MRI or CSF does not individually exclude autoimmune encephalitis, especially early in the illness or in certain antibody syndromes.
- Anticòs negatius require reassessment of the syndrome, test panel and objective evidence—not automatic exclusion or automatic treatment.
- Prochaines etapas may include hospital monitoring, infection treatment, specialist-directed immunotherapy and antibody-guided cancer screening.
What establishes an autoimmune encephalitis diagnosis?
Autoimmune encephalitis diagnosis is established by matching a rapidly developing neurological syndrome with CSF, MRI, EEG and antibody findings while reasonably excluding other causes. The usual starting framework considers progression over less than 3 months, rather than a blood antibody result in isolation.
The 2016 framework separates possible, probable and syndrome-specific definite diagnoses; these categories are not interchangeable measures of severity. Possible autoimmune encephalitis requires subacute memory problems, altered mental status or psychiatric symptoms, plus at least 1 qualifying finding—new focal signs, unexplained seizures, CSF pleocytosis or suggestive MRI—and reasonable exclusion of alternatives (Graus et al., 2016).
Each investigation answers a different question: MRI examines brain structure, EEG measures electrical activity, CSF assesses the central nervous system environment, and antibodies may identify a mechanism. Agreement across 2 o mai independent types of evidence is more persuasive than repeating the same blood panel, but there is no universal score that converts their results into a diagnosis.
Kantesti es un Analizador de tèst de sang d'IA for explaining uploaded blood reports, not a service that diagnoses encephalitis or interprets MRI, EEG or spinal fluid. Our scope is described through our UK organization; even 1 new episode of confusion or seizure needs clinical assessment rather than an online interpretation.
Which symptoms require emergency assessment?
Sudden confusion, a first seizure, reduced consciousness or rapidly worsening behavior requires emergency assessment, whether or not autoimmune encephalitis is the cause. A seizure lasting 5 minutas, repeated seizures without recovery, breathing difficulty or new one-sided weakness warrants calling the local emergency number immediately.
Behavioral change becomes a medical emergency when it accompanies disorientation, inability to recognize familiar people, unusual repetitive movements, severe sleep disruption or inability to remain safe. Fever with headache, neck stiffness or confusion also raises concern for an infection; 1 episode of collapse or markedly reduced responsiveness is enough to seek emergency care rather than waiting for fever.
Stroke, low glucose, poisoning and infectious encephalitis can resemble an autoimmune presentation during the first d’oras. New facial droop, arm weakness, speech difficulty or sudden visual loss should trigger the same urgent response described in our stroke warning signs, even if an antibody panel has already been ordered.
During a convulsive seizure, protect the person from nearby hazards, cushion the head and time the event; do not restrain them or put anything in their mouth. After movements stop, use the recovery position if they are breathing normally, and tell emergency responders whether the event reached 5 minutas, whether recovery occurred and which medicines or substances were recently taken.
What clinical pattern makes autoimmune encephalitis more likely?
A new combination of memory loss, seizures, psychiatric symptoms, speech changes or movement abnormalities developing over days to weeks raises suspicion more than any isolated symptom. The less-than-3-mes diagnostic window captures a subacute change from baseline; it is not a rule that symptoms must continue for 3 months before testing.

A familiar lifelong concentration difficulty differs from a sudden inability to form memories or follow a conversation. The distinction between lifelong attention symptoms and an abrupt change matters because 2 setmanas of new disorientation, seizures and declining speech cannot safely be explained by an old psychiatric or developmental diagnosis alone.
Different antibody syndromes have different clues: anti-NMDA receptor encephalitis may combine psychiatric change, speech dysfunction, seizures, abnormal movements and autonomic instability. LGI1-associated disease can produce very brief, frequent face-and-arm events and memory impairment, sometimes with sodium below 135 mmol/L; these events can precede obvious cognitive decline and may not have a clear scalp EEG correlate.
Family observations often establish the timeline when the affected person cannot describe it accurately. Bring 3 concrete examples—such as forgetting a conversation within minutes, a new unexplained seizure and a sudden inability to use familiar objects—and list the dates, sleep changes and medication changes; symptom order helps clinicians distinguish encephalitis from delirium, medication effects and primary psychiatric illness.
Which blood tests and alternative causes are checked first?
Initial autoimmune encephalitis tests include urgent checks for reversible metabolic, toxic and infectious causes, alongside neurological investigations. Glucose, sodium, calcium, magnesium, kidney and liver results help identify mimics; a glucose below 54 mg/dL, o 3.0 mmol/L, can itself cause serious neurological symptoms.

Low glucose deserves immediate treatment, not attribution to an autoimmune antibody result. Our explanation of las causas d'un glucèmia bas covers medication and illness effects; in this setting, clinicians also investigate sodium disturbances, oxygenation, carbon dioxide retention and drug exposure because 1 reversible abnormality may explain the presentation or coexist with brain inflammation.
Sodium interpretation depends on glucose and the speed of change, not merely whether the laboratory flags a result. A sodium of 128 mmol/L with substantial hyperglycemia has a different physiological interpretation from 128 mmol/L with normal glucose; glucose-adjusted sodium interpretation helps explain the distinction, but correction and treatment require the clinical team.
Normal blood inflammatory markers do not rule out inflammation confined mainly to the nervous system, and high markers do not identify its cause. Kantesti cannot establish autoimmune encephalitis from a CBC or CRP result; clinicians may add thyroid studies, toxicology, ammonia or exposure-specific infection tests while arranging CSF testing, often within the first 24 oras when feasible.
What does autoimmune encephalitis spinal fluid testing show?
Autoimmune encephalitis spinal fluid testing looks for inflammatory evidence, neuronal antibodies and infections in cerebrospinal fluid, usually obtained by lumbar puncture. A CSF white-cell count above 5 cells/µL meets the pleocytosis threshold used in established diagnostic criteria, but neither an elevated count nor a normal count settles the diagnosis alone.
The CSF request commonly includes cell count, protein, glucose with a contemporaneous serum glucose, oligoclonal bands, an IgG index and appropriate microbial tests. Many laboratories call 2 o mai CSF-restricted bands positive, although thresholds differ; l’interpretacion de las bendas oligoclonalas del LCR explains why these bands support nervous-system immune activity without specifically proving encephalitis or multiple sclerosis.
Protein interpretation needs age and sample quality: an adult result of 60 mg/dL may be mildly elevated under one laboratory's range but less striking under an age-adjusted interval. A traumatic puncture can introduce circulating cells and protein into the specimen; a markedly low CSF glucose ratio redirects attention toward infections, malignant involvement or other causes rather than being a signature autoimmune finding.
Lumbar puncture is performed after checking procedural safety, including anticoagulants, platelet status and whether examination findings require imaging first. Tell the team about the last dose of cada anticoagulant and any previous spinal procedure; collecting enough material for both routine and specialist testing reduces the chance of needing 2 punctures simply because the antibody request was added late.
| Nivèl | Interval | Significacion |
|---|---|---|
| Globuls blancs del LCR de l'adult | Usually 0–5 cells/µL | More than 5 cells/µL supports pleocytosis, but infections and other inflammatory disorders can produce the same finding. |
| Proteïna del LCR de l'adult | Often approximately 15–45 mg/dL | Reference limits vary substantially by laboratory and age; elevation is not specific for autoimmune encephalitis. |
| CSF-to-serum glucose ratio | Often approximately 0.6 | A ratio below about 0.4 warrants investigation for other causes; interpret with sampling time and serum glucose. |
| CSF IgG index | Upper limit often approximately 0.7 | Use the reporting laboratory's interval and paired serum measurements; an elevated index suggests intrathecal immune activity, not a specific diagnosis. |
Why blood antibody results alone cannot confirm the diagnosis
A positive blood neuronal antibody result cannot confirm autoimmune encephalitis without a matching clinical syndrome and appropriate supporting evidence. Testing 2 specimen types—serum and CSF—usually improves interpretation because antibody sensitivity, specificity and clinical relevance differ between the circulation and the central nervous system.
The antibody's name, immunoglobulin class, assay method and specimen matter more than the word positive. For anti-NMDA receptor encephalitis, the relevant finding is IgG against GluN1, whereas low-level serum GAD65 antibodies may reflect diabetes-associated autoimmunity rather than brain disease; our GAD65 result interpretation explica perqué 1 threshold cannot be transferred between assays.
Unexpected serum-only positives may require confirmation with a different method, particularly when the neurological picture does not fit. Some antibodies, including LGI1, can be more readily detected in serum, so negative CSF is not a universal veto; interpretacion d’un resultat d’anticòrs positiu explains the distinction between detecting an immune marker and demonstrating that it caused the current illness.
Kantesti es un plataforma d’interpretacion d’analisi de sang d’AI that can explain a report's wording without converting 1 serum result into an encephalitis diagnosis. A positive ANA, complement abnormality or thyroid antibody answers a different clinical question from a neuronal antibody panel; our systemic autoimmune marker guide helps keep those categories separate.
How is the anti NMDA receptor antibody test interpreted?
The anti NMDA receptor antibody test is most informative when CSF is examined for IgG against the GluN1 receptor subunit. In a retrospective study of 250 affected patients, CSF antibodies were detected in all participants, while serum antibodies were detected in 214, giving serum sensitivity of 85.6% within that cohort.
The difference in that cohort means 36 of 250 patients—14.4%—had negative serum results despite positive CSF testing (Gresa-Arribas et al., 2014). These figures explain why blood testing alone can miss anti-NMDA receptor encephalitis; they do not guarantee 100% sensitivity for every laboratory, disease stage or testing method used in routine practice.
The established probable anti-NMDA receptor syndrome uses rapid onset of at least 4 de 6 symptom groups, an abnormal EEG or inflammatory CSF finding, and reasonable exclusion of alternatives. The groups cover behavior or cognition, speech, seizures, movement abnormalities, reduced consciousness and autonomic dysfunction or hypoventilation; a separate pathway permits 3 groups when a systemic teratoma is present (Graus et al., 2016).
Antibody titres are not a simple recovery score, and persistence after improvement does not automatically indicate active relapse. Repeat testing should answer a specific specialist question rather than chase a negative result; Kantesti's metodologia e dels limits clinic describe why performance claims for blood-report explanation must not be applied to this 1 specialized neurological diagnostic pathway.
What can MRI show, and can the scan be normal?
Brain MRI can support autoimmune encephalitis by showing compatible changes, especially in the medial temporal lobes, but a normal scan does not exclude the condition. Bilateral medial temporal T2/FLAIR abnormalities are central to the established definite autoimmune limbic encephalitis criteria, which assess ambedós temporal lobes rather than any isolated bright area.
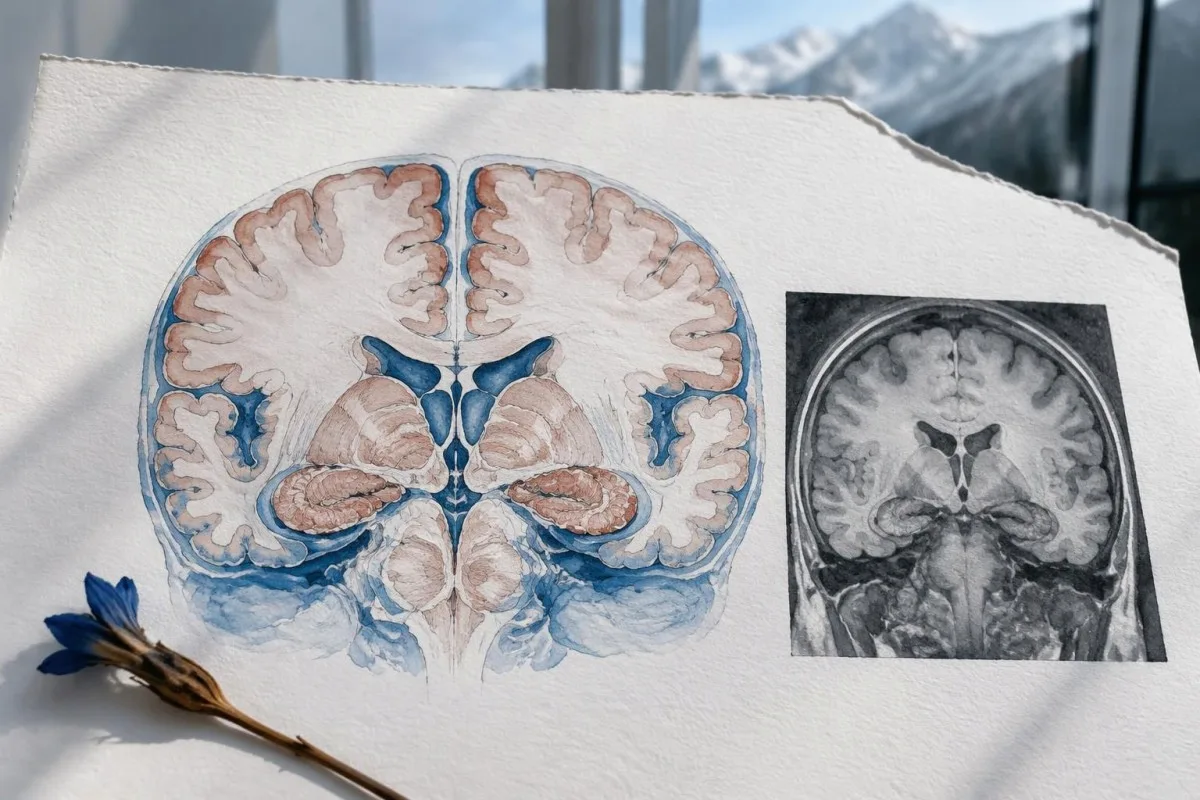
MRI findings must be interpreted against seizure timing, because recent seizures can themselves cause temporary signal abnormalities. A scan obtained 1 jorn after prolonged seizures may look different from a later scan; unilateral temporal changes also require consideration of herpes simplex encephalitis, structural disease and other causes, so the radiology phrase possible encephalitis is not a final diagnosis.
The imaging pattern may suggest a related inflammatory disorder rather than a classic neuronal-antibody syndrome. Extensive white-matter changes or cortical findings can prompt evaluation for demyelinating conditions, including MOG-associated disease; the distinction changes which antibody assay and specimen are most useful, and 1 broad autoimmune panel may not cover both pathways adequately.
A persistently normal initial MRI does not end the workup when the examination, EEG or CSF remains concerning. Neurologists may arrange repeat imaging or selected additional studies, while focal or progressive findings also require assessment for structural brain warning signs; timing depends on deterioration and the diagnostic question, not a fixed 7-day repeat rule.
How does EEG contribute to autoimmune encephalitis tests?
EEG detects seizures, nonconvulsive seizure activity and abnormal brain rhythms that MRI cannot measure. A routine EEG often records approximately 20–30 minutas, so a negative short recording may miss intermittent seizures; persistent unexplained reduced responsiveness can justify continuous EEG monitoring rather than another brief test.

Generalized or focal slowing supports brain dysfunction but does not identify its cause; sedatives, metabolic illness and infections can produce similar changes. Extreme delta brush can support anti-NMDA receptor encephalitis in the right context, but it is not required, and the absence of that 1 pattern does not meaningfully exclude the syndrome.
Continuous EEG is particularly useful when apparent sleep, agitation or repetitive movements could actually represent nonconvulsive seizures. Monitoring may extend for 24 hours or longer depending on the clinical course; seizure medicines are assessed alongside kidney function and interactions, while levetiracetam level interpretation explains why a drug concentration does not measure the severity of encephalitis.
A scalp EEG can miss some brief focal events, including events suspected to be faciobrachial dystonic seizures, so a family video may add useful information if recording it does not delay care. Record duration and recovery for each event, and do not change treatment based on a laboratory range alone; lacosamide monitoring principles address a different question from whether the underlying illness is autoimmune.
Can autoimmune encephalitis be diagnosed with negative antibodies?
Negative antibodies do not always exclude autoimmune encephalitis, because panels are incomplete and some clinically supported cases remain antibody-negative. However, probable antibody-negative disease requires stronger objective evidence than symptoms alone; the established adult framework requires at least 2 de 3 specified categories of supporting findings after other criteria are met.
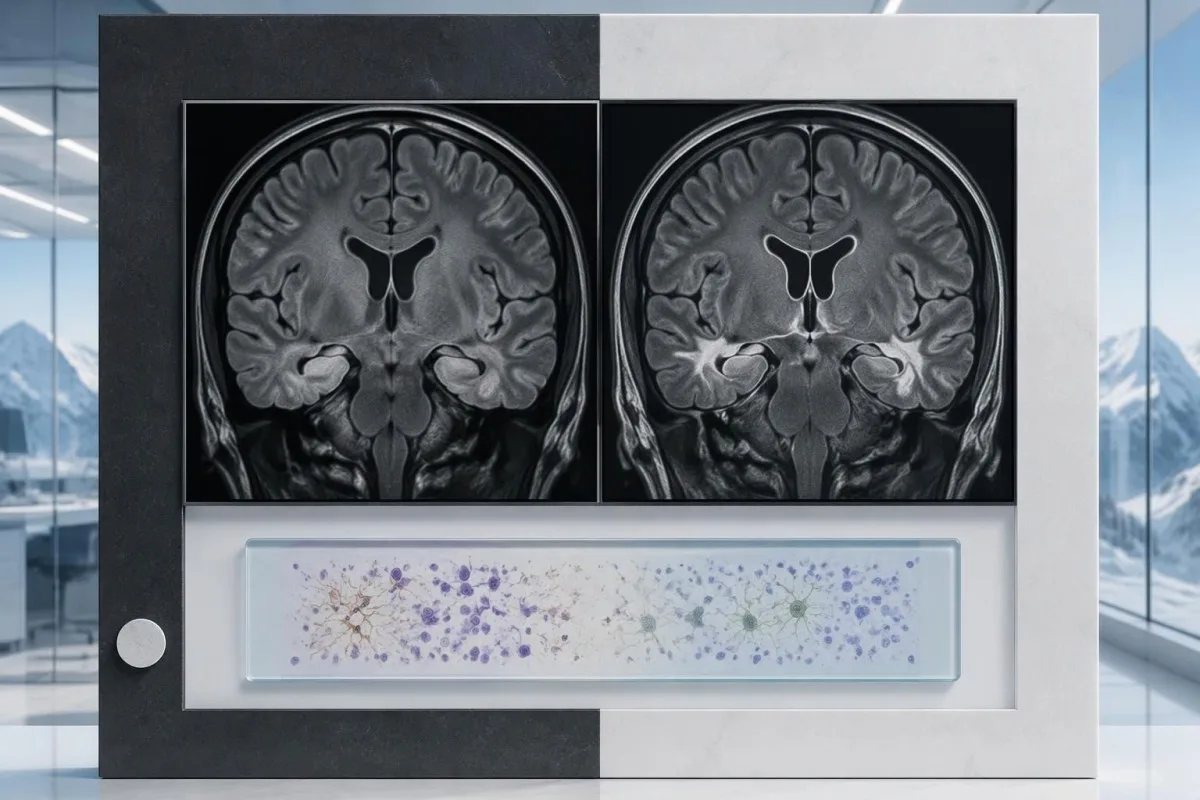
Lo 3 supporting categories are suggestive MRI abnormalities, inflammatory CSF findings, and brain tissue evidence of inflammatory infiltrates that excludes another disorder. Multiple CSF abnormalities still count as 1 category, not several independent categories; brain tissue examination is uncommon and not a routine step taken simply to satisfy criteria (Graus et al., 2016).
Before accepting an antibody-negative label, clinicians check whether both serum and CSF were tested, which antibodies were included and whether treatment preceded collection. A 2-specimen negative panel is more informative than a negative serum screen alone, but it still requires review for infectious, toxic, seizure-related, malignant and other inflammatory explanations; pediatric presentations need an age-appropriate specialist framework.
New injury biomarkers cannot replace this reasoning: an elevated neurofilament light chain result can indicate neuronal injury without identifying an autoimmune cause. Our neurofilament test limitations explain that distinction; if MRI, CSF and EEG are all unrevealing, 3 negative investigation types should trigger careful diagnostic reassessment rather than indefinite immune treatment based only on nonspecific symptoms.
Why might clinicians investigate an underlying cancer?
Some autoimmune encephalitis syndromes are associated with an underlying cancer, so screening is tailored to the antibody, syndrome, age and individual risk. A negative first screening study does not always end surveillance; selected higher-risk paraneoplastic presentations may need repeat screening over the next 2 ans, depending on specialist guidance.
Anti-NMDA receptor encephalitis can be associated with a teratoma, especially an ovarian teratoma, but many affected people have no detectable tumor. Pelvic ultrasound or MRI may therefore be appropriate for some patients, while 1 normal routine tumor-marker blood test cannot substitute for the imaging strategy; the investigation is about identifying a possible trigger, not proving that every encephalitis case is cancer-related.
Antibodies against intracellular targets can suggest a different disease mechanism and a stronger paraneoplastic concern than many surface-antibody syndromes. Our anti-Hu follow-up guide explains why a compatible anti-Hu result can prompt chest-focused investigation, yet even 1 positive anti-Hu report needs clinical and laboratory confirmation before it is treated as evidence of a particular cancer.
The screening plan should name the suspected association, initial imaging modality and trigger for repeat investigation rather than defaulting to indiscriminate scans. Best-practice recommendations discuss CT, targeted imaging and selected whole-body FDG-PET according to context (Abboud et al., 2021); balancing the chance of a missed trigger against incidental findings is part of deciding whether 1 additional study will meaningfully change care.
What happens while antibody results are pending?
Hospital teams may start treatment before antibody results return when the syndrome and initial investigations strongly support autoimmune encephalitis. The immediate priorities are stabilizing breathing and seizures, investigating infection and collecting appropriate specimens; antibody panels may take days to several weeks, depending on referral laboratory arrangements.

Suspected herpes simplex encephalitis requires prompt antiviral treatment while investigations continue; it should not be dismissed because the autoimmune explanation seems plausible. If an early CSF HSV PCR is negative but suspicion remains high, specialists may repeat it after approximately 3–7 jorns, considering symptom timing and imaging rather than allowing 1 negative early sample to end infection assessment.
First-line immune treatments commonly include corticosteroids, intravenous immunoglobulin or plasma exchange, sometimes in combination; selection depends on severity, likely mechanism and contraindications. Abboud et al. (2021) advise not waiting for antibody confirmation when autoimmune encephalitis is strongly suspected after appropriate infection evaluation, but this is not a mandate to give 1 empiric treatment course to everyone with unexplained brain fog.
Samples are ideally collected before immune treatment when doing so does not dangerously delay care, because intravenous immunoglobulin and plasma exchange can complicate later antibody interpretation. Steroid planning may also require exposure-based parasite assessment; our Strongyloides screening considerations explain why past residence or travel can matter even years later, particularly before substantial immunosuppression.
How do clinicians reconcile conflicting results?
Conflicting results are resolved by checking the syndrome, specimen, assay and timing—not by counting positive tests. A CSF antibody that fits the neurological picture may outweigh a negative serum result, whereas 1 low-level serum positive in an incompatible presentation may require confirmation rather than treatment.

Consider a clearly hypothetical 23-year-old who develops confusion, reduced speech, seizures and abnormal movements over 12 jorns. MRI is normal, EEG shows diffuse slowing, CSF has 18 white cells/µL, and CSF GluN1 IgG is confirmed despite negative serum testing; after appropriate exclusion of alternatives, these findings can support anti-NMDA receptor encephalitis without requiring an abnormal MRI.
Now consider a hypothetical 47-year-old amb 2 ans of stable concentration difficulty, no seizures or new neurological deficits, and a low-level serum GAD65 result obtained through a broad panel. That pattern does not automatically meet autoimmune encephalitis criteria; reviewing diabetes-related autoimmunity, assay units and other explanations is more defensible than treating the word positive as evidence of a new inflammatory brain illness.
Kantesti es un Outil d’analisi de sang amb IA that can help explain laboratory terminology without adjudicating these 2 neurological cases. Our limitas d’una IA responsabla are relevant here: bring the original report, specimen type, method, collection date and treatment dates to neurology, because a summary that omits those details can make conflicting results appear falsely equivalent.
Follow-up, evidence and research publications
The next step after assessment is a documented plan for neurological follow-up, seizure safety, recovery monitoring and any required cancer surveillance. Before discharge, clarify 3 things: the working diagnosis, which results remain pending and which changes require immediate emergency reassessment; improvement alone does not validate every original diagnostic assumption.

Recovery assessment includes memory, speech, sleep, behavior and daily function—not antibody titres alone. Ask whether repeat MRI, EEG or CSF will answer a specific clinical question, and obtain written advice about driving and seizure precautions; 1 new seizure, renewed disorientation or worsening consciousness needs urgent reassessment, even when previous routine blood results were reassuring.
Kantesti's broader laboratory publications address different clinical questions and are not evidence for diagnosing encephalitis. The linked iron panel education e d’interpretacion de l’analisi d’orina correspond to the 2 Zenodo DOI references below; neither publication validates neuronal antibody testing, MRI interpretation, EEG interpretation or an autoimmune encephalitis treatment pathway.
The directly relevant evidence for this article comes from 3 peer-reviewed sources: the Graus diagnostic framework, the Gresa-Arribas paired-antibody study and the Abboud acute-management recommendations. Our nòrmas de contengut medical separate educational information from individual diagnosis; request a named clinical contact for pending results so an important send-out test does not arrive without a follow-up plan.
Preguntes més freqüents
Quins tèsts son necessaris per diagnosticar una encefaliti autoimmunitària?
0 Lo diagnostic d'encefaliti autoimmunitària combina generalament l'avaloracion neurologica, l'IRM cerebral, l'EEG e la poncion lombara amb l'analisi dels anticòrs dins lo LCR e lo sèrum. Los critèris establits per una malautiá possibla meton l'accent sus una evolucion en mens de 3 meses e almens 1 resultat neurologic, de LCR o d'IRM que complís los critèris, amb l'exclusion rasonabla d'autras causas. Lo glucòsi, los electròlits e los tèsts d'infeccion ajudan a identificar de condicions que pòdon imitar una encefaliti. Cap de tèst unic permet de confirmar o d'exclure la malautiá dins totes los cases.
Un tèst sanguin pòt confirmar una encefaliti autoimmuna ?
0 Un resultat d’anticòrs sanguins a el sol pòt pas confirmar una encefaliti autoimmunitària, perque sa significacion depend de l’anticòs, de l’assaig e del sindròma clinic. Los clinicians considèran generalament 2 tipes de mòstra, lo sèrum e lo LCR, quitament se la mòstra preferida varia segon l’anticòs. Per l’encefaliti del receptor anti-NMDA, los IgG del LCR contra GluN1 son particularament importants. Un resultat positiu inesperat sonque dins lo sèrum pòt necessitar una confirmacion abans d’èsser considerat clinicament pertinent.
Una encefalitis autoimmuna pòt aver d'anticòrs negatius ?
L’encefaliti autoimmunitària pòt se manifestar amb tèsts d’anticòrs negatius, mas lo diagnostic deu èsser sostengut per d’elements clinics e d’investigacion objectius. Lo quadre establit per als adults amb anticòrs negatius probables inclutz almens 2 de 3 categorias d’elements de sosten: IRM suggestiva, LCS inflamatori o trobalhas qualificativas sul teissut cerebral, amb d’autres critèris necessaris. Mantunas mesuras anormalas del LCS comptan totjorn coma una sola categoria. Los resultats negatius exigisson tanben de verificar lo panèl, los tipes d’ensag e los diagnostics alternatius.
Los tèsts del liquid cefalorraquidian son melhor que los tèsts de sang per l’encefaliti anti-NMDA receptor?
0 Les tests del LCR són més sensibles que les proves sèriques per detectar els anticossos anti-receptor NMDA en una cohort retrospectiva de referència. Gresa-Arribas et al. (2014) van detectar anticossos al LCR de tots els 250 participants afectats, però al sèrum de 214, és a dir, 85.6%. Això va deixar un 14.4% de participants amb sèrum negatiu malgrat tenir un LCR positiu. L’anticòs en qüestió és IgG contra GluN1, i el resultat encara ha de concordar amb la presentació clínica.
0 Pòdon l’IRM e l’EEG èsser normals en una encefaliti autoimuna ?
0 A normala IRM exclutz pas una encefaliti autoimmunitària, e un EEG cort pòt mancar de crises intermittentas. Un EEG de rutina registra comunament aproximativament 20–30 minutas d’activitat, mentre que lo monitoratge contunh pòt durar 24 oras o mai quand es indicat. Lo ralentiment de l’EEG sosten una disfoncion cerebrala, mas identifica pas una causa autoimmunitària. D’investigacions persistentament normalas devon incitar a una reavaloracion atenta, pas a una exclusion automatica ni a un tractament immunitari automatic.
0 Quins simptòmas d’encefaliti autoimmunitària vòlon dire que devi anar al servici d’urgéncia ?
0 Sobda confusion, una primièra crisi epileptica, una diminucion de la consciéncia, de cambiaments de la respiracion o un comportament perilhós que s’agreuja rapidament necessitan una avaloracion d’urgéncia. Apelatz lo numèro d’urgéncia local per una crisi epileptica que dura 5 minutas o per de crisis repetidas sens retorn a l’estat normal. Una flaquesa novèla d’un costat del còrs o una dificultat per parlar requerisson tanben de suènhs immediats, perque un AVC e d’autras urgéncias pòdon imitar una encefalita. Esperetz pas lo resultat d’un anticòs e vos basetz pas sus una interpretacion de laboratòri en linha per decidir se aqueles simptòmas son urgents.
Do doctors wait for antibody results before treating autoimmune encephalitis?
Clinicians may begin specialist-directed treatment before antibody results return when the clinical syndrome and initial investigations strongly support autoimmune encephalitis. Send-out antibody results can take days to several weeks, so waiting is not always safe. Immediate care includes seizure and breathing support, infection assessment and antiviral treatment when infectious encephalitis is suspected. First-line immune treatment may involve 1 or more of corticosteroids, intravenous immunoglobulin and plasma exchange, selected for the individual situation.
Fasètz-vos explicar los resultats analisi de sang
Telecargatz vòstre compte rendut de laboratòri e l’IA de Kantesti explica cada biomarcador en lenga simpla en qualques segondas. Utilizat per mai de 2 milions de personas dins lo mond.
Referéncias
- Klein, T., Mitchell, S., & Weber, H. (2026). Test d’urobilinogen en urina : Guia completa d’urinalisi 2026. Recèrca medicala per IA de Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Guida dels bilançs del fèrre: TIBC, saturacion del fèrre e capacitat de ligam. Recèrca medicala per IA de Kantesti. DOI
- Graus F et al. (2016). A clinical approach to diagnosis of autoimmune encephalitis. The Lancet Neurology. DOI PubMed
- Gresa-Arribas N et al. (2014). Antibody titres at diagnosis and during follow-up of anti-NMDA receptor encephalitis: a retrospective study. The Lancet Neurology. DOI PubMed
- Abboud H et al. (2021). Autoimmune encephalitis: proposed best practice recommendations for diagnosis and acute management. Journal of Neurology, Neurosurgery & Psychiatry. DOI PubMed
- 2M+Tèsts analisats
- 127+Païses
- 100+Lengas
A prepaus de l’equipa medicala


Senhals de confiança E-E-A-T
Experiéncia
Revisión clinica menada pel metge de las practicas d’interpretacion de las analisis.
Expertisa
Fòcus sus la medicina de laboratòri sus cossí los biomarcadors se comportan dins un contèxte clinic.
Autoritat
Revisat medicalament pel Dr Thomas Klein, amb de contribucions de la Dr Sarah Mitchell e del Prof. Dr Hans Weber.
Fisança
Interpretacion basada sus d’evidéncias amb de camins de seguiment clars per reduzir l’alarmisme.





Avís medical
Aqueste article es solament per tòcas educatius e constituís pas de conselh medical. Consultatz totjorn un professional de la sant qualificat per las decisions de diagnostica e de tractament.
Publicat · Contactar l’equipa editoriala
Publicat per Kantesti Ltd, enregistrada en Anglatèrra e País de Galas, n° d’entrepresa. 17090423, Londres, Reialme Unit.
