
Sudden balance loss, vision changes, facial drooping, arm weakness, or speech difficulty can signal a stroke. Call your local emergency number immediately—even if symptoms disappear or routine bloodwork is normal; neither improvement nor normal laboratory results makes waiting safe.

要点
- BE-FAST means Balance, Eyes, Face, Arms, Speech, and Time; one sudden warning sign can justify an emergency call.
- Emergency numbers include 999 or 112 in the UK and 911 in the US; use your local emergency service elsewhere.
- Disappearing symptoms may represent a transient ischemic attack, or TIA, and still require urgent assessment.
- 正常な血液検査 cannot exclude either an ischemic stroke or a stroke caused by bleeding.
- Last known well means the last time the person was definitely at their usual neurological baseline—not when someone discovered the symptoms.
- Treatment windows commonly include intravenous thrombolysis within 4.5 hours for eligible patients; selected patients may receive thrombectomy up to 24 hours.
- Women’s warning signs include the same BE-FAST symptoms as men’s; pregnancy or postpartum status changes the clinical context, not the need for emergency action.
- 待たない for a laboratory report, an AI interpretation, a second episode, or improvement before calling for help.
Which stroke symptoms need an emergency call?
Sudden stroke symptoms require an immediate emergency call: new balance loss, vision loss or double vision, facial drooping, arm weakness, or speech difficulty. Use BE-FAST, but do not wait for all 6 signs; symptoms that disappear and normal routine bloodwork do not exclude stroke.
A stroke occurs when a brain artery becomes blocked or a brain vessel ruptures; these 2 mechanisms require different treatments. The symptoms cannot reliably distinguish them at home, which is why taking aspirin or trying to lower blood pressure yourself can be unsafe before professional assessment.
The practical clue is a sudden change from the person’s usual function, not whether they look seriously ill. Someone may remain awake, walk into a room, or describe only 1 weak hand while still having a disabling stroke; pain and loss of consciousness are not required.
For example, imagine a person speaking normally at 10:12 who develops garbled speech at 10:14 while eating breakfast. Call immediately and report both times; do not spend another 10 minutes checking facial symmetry, searching symptoms online, or arranging a routine blood test.
Kantesti is an AI blood test analyzer for understanding laboratory reports, not an emergency stroke diagnostic service. Our 組織および臨床スコープ should be understood alongside this limit: even an interpretation delivered in approximately 60 seconds must never delay an emergency call.
What do the six BE-FAST stroke signs mean?
BE-FAST stroke signs cover Balance, Eyes, Face, Arms, Speech, and Time to call emergency services. The 6-part mnemonic adds sudden imbalance and visual changes to FAST, helping people recognize strokes that do not begin with obvious facial drooping or arm weakness.
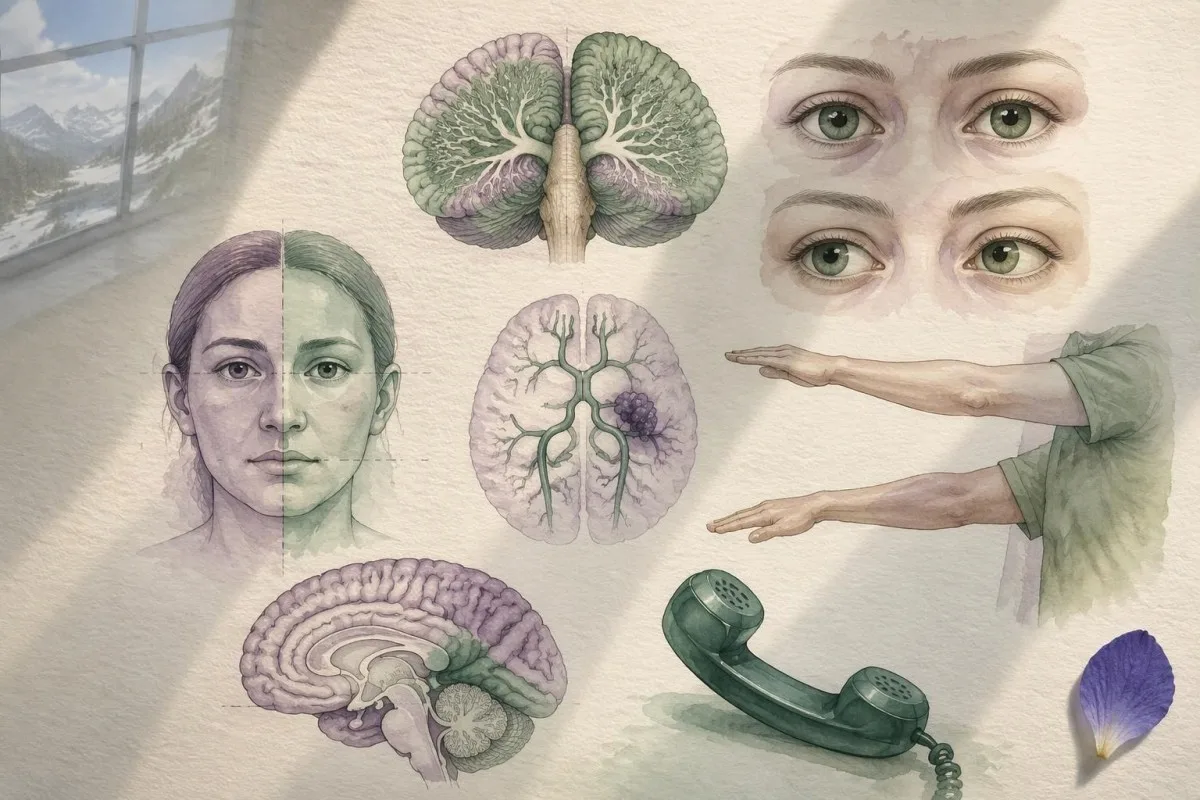
Balance means sudden unsteadiness, loss of coordination, or difficulty standing or walking; Eyes means sudden vision loss, double vision, or missing part of the visual field. Either can occur without the other 3 physical FAST features, so a normal smile does not make these symptoms safe to dismiss.
Face means a new uneven smile or facial droop; Arms means new weakness, drift, or numbness, especially on 1 side. Speech includes slurring, wrong words, inability to understand a simple sentence, or inability to produce words—not just an unfamiliar accent or someone speaking quietly.
Time means call now, not finish the checklist first. In a retrospective study of 736 ischemic strokes, FAST missed 14.1%; adding balance and visual symptoms reduced the missed proportion to 4.4% (Aroor et al., 2017), but those single-center results do not establish a universal home-screening accuracy.
A person with only hand symptoms still needs attention to timing and function. Our guide to finger-specific numbness patterns explains a common peripheral cause, but sudden loss of dexterity in 1 hand must not be assumed to be carpal tunnel syndrome without assessment.
When can sudden dizziness or imbalance signal stroke?
Sudden severe imbalance can signal a posterior circulation stroke, particularly when accompanied by double vision, speech changes, weakness, or inability to walk. These strokes involve structures such as the cerebellum and brainstem, so the 3 physical FAST checks may all appear normal.
Not every dizzy spell is a stroke; inner-ear disorders and faintness are common alternatives. The concerning combination is a new, persistent balance disturbance plus loss of a previously easy function—for example, being unable to take 2 unsupported steps or suddenly needing furniture to remain upright.
A positional trigger does not automatically prove an inner-ear cause, and nausea does not rule out stroke. If a person develops abrupt vertigo with 1 new neurological feature, such as double vision or slurred speech, call emergency services rather than testing repeated head movements at home.
The HINTS examination is a clinician-performed assessment used in a specific acute vestibular syndrome, not a 3-step self-test for every dizzy patient. Incorrect technique or use in the wrong setting can falsely reassure; an online demonstration cannot substitute for trained examination and appropriate imaging.
Orthostatic symptoms usually have a different pattern, often linked to standing and recurring over time. Our standing-related dizziness guide explains that distinction, but even someone with established POTS needs emergency assessment for 1 sudden, unfamiliar neurological deficit.
Which sudden vision changes count as stroke warnings?
Sudden vision loss, new double vision, or loss of one side of the visual field can be stroke symptoms. A problem affecting just 1 eye can also represent interrupted retinal circulation, which requires emergency assessment even when facial movement, arm strength, and speech seem normal.

Visual-field loss is different from blurred vision: a person may miss everything to the left or right despite both eyes being open. For example, they might see only 1 half of a plate or repeatedly bump into objects on the same side, without realizing that vision—not attention—is the problem.
New double vision can reflect impaired eye alignment from brainstem dysfunction, especially when paired with imbalance or speech changes. Tell the dispatcher whether the symptom involves 1 eye, both eyes, or a missing side of the scene, but do not delay the call to perform a detailed eye examination.
A brief, painless blackout in 1 eye can be a retinal TIA rather than an ordinary eye complaint. The fact that sight returns after several minutes is not evidence that circulation is safe; the episode may require brain, vessel, and cardiac assessment in addition to an eye examination.
Routine eye screening answers a different question from sudden visual loss. Our explanation of pressure and visual-field testing describes longer-term assessment, but an abrupt change over seconds or minutes should not wait for an optician appointment scheduled 1 week later.
Do early signs of stroke appear before the main event?
Early signs of stroke are often the stroke itself, not a predictable warning phase lasting days. Some people have a preceding TIA, but there is no reliable 24-hour symptom sequence; sudden loss of speech, strength, vision, or coordination deserves action at its first appearance.

Last known well is the last time someone was definitely at their usual neurological baseline. If a person went to sleep normally at 22:30 and woke with weakness at 06:30, both times matter; reporting 06:30 as the definite onset would incorrectly shorten the possible duration.
Wake-up symptoms are still an emergency, even when several hours may have passed. Some patients with unknown onset can receive treatment selected by imaging, so assuming that the usual 4.5-hour intravenous treatment window has already closed may wrongly prevent access to useful care.
A sudden severe headache reaching maximum intensity within about 1 minute is a thunderclap headache and warrants emergency assessment, particularly with vomiting, neck stiffness, or neurological changes. Many ischemic strokes cause no headache, so its absence must not become a reason to wait.
The speed of change helps distinguish some neurological patterns, but it cannot establish a diagnosis alone. Our 進行性筋力低下の警告サイン discuss a different emergency pattern; weakness evolving over 2 days and weakness appearing in seconds both need appropriate clinical evaluation.
Are stroke symptoms in women different?
Stroke symptoms in women usually include the same BE-FAST warning signs as in men. Some observational reports describe more accompanying confusion, headache, nausea, or generalized symptoms, but there is no separate reliable 6-sign checklist for women, and these nonspecific features cannot diagnose stroke alone.

A useful distinction is between a focal deficit and an accompanying symptom: inability to use 1 arm is more localizing than fatigue alone. If a woman has sudden nausea plus double vision and inability to walk, the neurological combination—not whether the symptoms sound stereotypically female—should drive the emergency call.
Pregnancy and the postpartum period change the possible causes of headache and neurological symptoms, including hypertensive complications and cerebral venous thrombosis. Tell emergency clinicians the pregnancy stage or delivery date; a new severe headache with 1 focal deficit should not be attributed to exhaustion or migraine without assessment.
Normal or previously reassuring pregnancy bloodwork cannot exclude a neurological emergency. Our explanation of HELLPの緊急時にみられる検査所見に関する addresses one obstetric complication, but neither a normal platelet count nor normal liver enzymes excludes all causes of postpartum headache or stroke.
Consider a hypothetical woman 10 days after delivery who develops abrupt word-finding difficulty and a headache unlike her usual migraines. The safe action is an emergency call with the delivery date and last known well—not waiting for a repeat CBC, checking whether the headache improves, or asking an app to classify symptoms.
Why do disappearing symptoms still suggest a TIA?
Stroke-like symptoms that disappear may represent a TIA or a stroke with improving deficits, and both need urgent assessment. A modern TIA diagnosis concerns transient ischemia without acute infarction, not simply symptoms lasting under 24 hours; only professional evaluation can make that distinction.
Amin et al. (2023), in an American Heart Association scientific statement, reported 90-day stroke-risk estimates after TIA as high as 17.8%, with almost half of those strokes occurring within 2 days. Those figures describe particular study populations, not an individual prediction; prompt assessment and prevention can change the risk.
If weakness resolves while an ambulance is coming, do not cancel because the person now feels normal. Record when symptoms started, when they stopped, which side was affected, and whether any episode recurred; even 1 brief focal event may identify an unstable arterial or cardiac source.
Risk scores such as ABCD2 cannot safely replace vessel imaging, cardiac assessment, and clinical judgment. A low score may overlook important causes, while a normal examination after 10 minutes of resolved symptoms documents recovery rather than proving that the original event was harmless.
At Kantesti, we separate long-term laboratory risk review from assessment of a new neurological event. Our family-history stroke testing guide is relevant after urgent care, but a preventive panel next week is not a substitute for assessment of 1 suspected TIA today.
Can normal routine bloodwork rule out stroke?
Normal routine bloodwork cannot rule out stroke or TIA. A CBC, metabolic panel, lipid panel, or coagulation panel measures selected cellular, chemical, or clotting properties; none shows whether 1 brain artery is blocked, whether brain tissue is injured, or whether bleeding has occurred inside the skull.

An INR of 1.0 and a normal aPTT do not prove that no clot exists. These tests assess aspects of coagulation under laboratory conditions, not the presence of an arterial obstruction; our guide to 正常な凝固検査の限界 explains why reassuring values can coexist with clinically important clotting.
A normal cholesterol result answers a risk-factor question, not an emergency diagnostic question. For example, an LDL cholesterol of 85 mg/dL does not exclude an embolus from atrial fibrillation or an artery problem; our metabolic panel versus cholesterol guide also clarifies which tests a routine panel actually contains.
Kantesti is an AI blood test interpretation platform that explains reported laboratory findings without using normal values to exclude stroke. A hypothetical platelet count of 240 × 10⁹/L, glucose of 98 mg/dL, and creatinine of 0.9 mg/dL can all coexist with a new cerebral artery blockage.
A panel from 2 days ago has an additional limitation: it describes the time of collection, not current neurological function. Emergency teams may repeat selected tests for treatment safety, but a person should call for help based on sudden symptoms rather than wait for a new sample or compare old reference ranges.
What should you do while emergency help is coming?
Call emergency services, report suspected stroke, and note the last known well time. Use 999 or 112 in the UK, 911 in the US, or your local emergency number; do not drive yourself, and do not wait for laboratory results before requesting help.
Keep the person safely supported and follow the dispatcher’s positioning instructions rather than making them walk to prove they are better. Do not offer food, drink, or tablets because stroke can impair swallowing; if consciousness or breathing changes, tell the dispatcher immediately and follow their resuscitation guidance.
Do not start aspirin, take an extra anticoagulant dose, or use extra blood-pressure medication on your own. The 2 major stroke mechanisms need different approaches, and sudden blood-pressure reduction can be harmful in some situations; clinicians may give aspirin for suspected TIA under a local pathway, but that is not a universal home-treatment instruction.
Gather medication names and the time of the last anticoagulant dose, especially for warfarin, apixaban, rivaroxaban, dabigatran, or edoxaban. Our INR結果の説明 helps clarify warfarin monitoring, but a normal INR does not reliably establish the absence of a direct oral anticoagulant’s effect.
For example, if symptoms began at 14:05 and a prescribed anticoagulant was taken at 08:00, communicate both exact times. Unlocking the door and having the medication list ready can help responders; finding an old report, charging a phone for an upload, or arranging private transport must not postpone the call.
Which emergency tests actually assess suspected stroke?
Suspected stroke is assessed with neurological examination, urgent brain imaging, and selected supporting tests—not routine bloodwork alone. A rapid glucose check identifies a treatable mimic; CT commonly checks for intracranial bleeding, while CT angiography or MRI may answer additional questions about arteries and brain tissue.
An early noncontrast CT may look normal during an ischemic stroke, so a reassuring initial scan is not always the end of assessment. MRI with diffusion-weighted imaging can detect many early infarcts, but early false-negative studies occur, particularly in posterior circulation events; persistent symptoms still need clinical reconciliation.
Low glucose can cause confusion, weakness, or speech difficulty, sometimes resembling a stroke. A glucose below 70 mg/dL, or 3.9 mmol/L, is hypoglycemia; below 54 mg/dL, or 3.0 mmol/L, is clinically significant hypoglycemia, and our low-glucose causes guide explains common medication and illness-related causes.
A severe metabolic disturbance can also complicate examination, but finding one does not automatically exclude simultaneous stroke. Our glucose-adjusted sodium explanation describes why marked hyperglycemia changes sodium interpretation; neither calculation should delay emergency assessment of 1 new focal deficit.
Kantesti AI can explain laboratory terminology after collection, but it cannot perform a neurological examination or interpret an evolving emergency as a safe exclusion of stroke. Powers et al. (2019) state that only glucose must precede intravenous thrombolysis in all patients; additional laboratory results may be needed when specific medication, bleeding, or coagulation concerns exist.
Why must treatment not wait for routine test results?
Stroke treatment is time-sensitive because threatened brain tissue may become permanently injured while testing is delayed. Established treatment pathways include intravenous thrombolysis within 4.5 hours for eligible patients and thrombectomy up to 24 hours in selected patients; those limits are eligibility windows, not safe periods for waiting.

Thrombolysis uses medication to dissolve an eligible clot; thrombectomy uses a catheter-based device to remove selected artery blockages. The 2019 AHA/ASA guideline describes imaging-selected thrombectomy between 6 and 24 hours for certain patients (Powers et al., 2019), but anatomy, imaging findings, baseline function, and specialist judgment determine eligibility.
Blood pressure and medication exposure affect treatment safety without becoming reasons to stay home. An established pre-thrombolysis blood-pressure threshold is below 185/110 mmHg, and hospital teams can manage elevated readings; patients should not attempt to meet that threshold using extra tablets before transport.
Coagulation results matter when a specific safety concern is present, but they do not diagnose the blockage itself. A platelet count below 100 × 10⁹/L or warfarin-associated INR above 1.7 can affect standard intravenous thrombolysis eligibility; our clotting assay interpretation guide explains why different assays answer different questions.
Imagine someone first assessed 3 hours after definite symptom onset who waits another 90 minutes for a nonessential routine panel before reaching a stroke team. That delay may consume a conventional treatment window, although eligibility is never decided by time alone; the safer sequence is emergency assessment first, with necessary tests performed in parallel.
Can migraine, seizures, or brain biomarkers distinguish stroke?
Migraine, seizures, low glucose, and some vestibular disorders can mimic stroke, but they cannot be reliably distinguished at home. No routine report containing 1 neurological biomarker establishes that a sudden deficit is harmless; examination, symptom timing, and appropriate imaging remain central to assessment.
Migraine aura often spreads gradually across several minutes, whereas stroke often causes an abrupt loss of function, but the patterns overlap. A first aura, an unfamiliar aura, or a sudden negative symptom such as losing 1 side of vision should not be self-diagnosed as migraine just because headache is present.
A seizure can be followed by temporary weakness, sometimes called Todd paralysis, and a stroke can itself trigger a seizure. Reporting witnessed shaking or a 1-minute episode of unresponsiveness helps clinicians, but it does not make subsequent weakness safe to observe without urgent assessment.
Neurofilament light chain reflects neuronal injury in multiple conditions rather than functioning as a rapid stroke exclusion test. Our NfL result interpretation guide explains this nonspecificity; a single result, whether high or low, cannot replace assessment of 1 newly impaired neurological function.
Some GFAP-based testing pathways address selected traumatic brain injuries, not universal stroke screening. Our GFAP and head-injury guide discusses that separate use; even where research examines stroke biomarkers, assay timing, thresholds, and performance vary, so 1 normal value must not reassure a symptomatic person.
How can blood tests help after the emergency assessment?
Blood tests help identify and monitor some stroke risk factors after urgent diagnosis, including diabetes and atherogenic cholesterol patterns. They do not replace blood-pressure measurement, cardiac rhythm assessment, or vascular imaging, and 1 reassuring panel does not guarantee that a person will not have another event.

A hypothetical follow-up panel with LDL cholesterol of 142 mg/dL and HbA1c of 7.2% identifies modifiable concerns, not the exact cause of the event. Our ApoB treatment-decision guide explains particle-related risk assessment; treatment targets depend on the diagnosed stroke mechanism, comorbidities, and the clinician’s prevention plan.
Hypertension needs direct measurement because a chemistry panel does not measure arterial pressure. Our secondary hypertension testing guide explains selected laboratory investigations, but 2 normal electrolyte results do not exclude common primary hypertension or replace repeated blood-pressure readings.
Atrial fibrillation may require ECG monitoring because 1 short recording can miss intermittent episodes. Similarly, broad inherited thrombophilia testing is not automatically useful after every arterial stroke; the history, age, imaging pattern, and suspected mechanism determine which additional investigations could change treatment.
Kantesti can support clinician-directed comparison of follow-up laboratory reports, but medication changes belong within the prescribed care plan. Whole-food eating patterns, smoking cessation, activity adapted to recovery, and consistent medication use address longer-term risk; none can reverse a new sudden deficit or justify waiting 1 more day for emergency assessment.
Research publications, evidence, and laboratory interpretation limits
The stroke evidence cited here supports emergency recognition and assessment; our 2 listed repository publications address general laboratory interpretation, not stroke diagnosis. Readers can review our validation methods and limits without treating technical evaluation as proof that an AI tool can exclude an acute neurological emergency.

Our listed kidney-function interpretation guide explains BUN and creatinine in their own clinical context. Its Zenodo DOI identifies a repository publication; a creatinine of 0.9 mg/dL, for example, describes a laboratory finding and cannot establish that cerebral circulation is intact.
関連資料の urinalysis interpretation publication addresses urine findings rather than acute brain assessment. These 2 repository references are included for transparency about related educational material, not as external stroke guidelines, peer-reviewed stroke trials, or evidence that urine testing can distinguish TIA from stroke.
Kantesti is an AI-powered blood test analysis tool whose educational role must remain separate from emergency triage and definitive diagnosis. Our 医療コンテンツ基準 explain the editorial framework; the 3 external medical references below address BE-FAST, suspected TIA, and established acute ischemic stroke management.
Clinical follow-up may involve sharing reports with a treating team, but that should happen after emergency needs are addressed. Our プライバシーとデータの取り扱い describe report handling; permission to review 1 family member’s laboratory report does not authorize access to another’s, and no upload should postpone an emergency call.
よくある質問
脳卒中の初期警告サインにはどのようなものがありますか?
脳卒中の初期警告サインは、多くの場合、突然の平衡感覚の喪失、視覚の変化、顔のゆがみ、腕の脱力、または会話の困難です。BE-FASTはこれらを、救急サービスに連絡する時間を含む6つの確認項目にまとめています。脳卒中を起こすのに、すべての兆候が現れる必要はなく、頭痛や意識消失が必要なわけでもありません。新たな神経学的異常が突然現れたら、直ちに電話し、最後に正常だった時刻を伝えてください。.
脳卒中の症状は数分後に消えることがありますか?
TIAや症状が改善する脳卒中では、脳卒中の症状が数分後に消えることがありますが、症状が消えたからといって安全だとは限りません。米国心臓協会の2023年のTIAに関する声明では、一部の集団における90日以内の脳卒中リスクは最大17.8%と推定され、その約半数が2日以内に発生すると報告されています。これらの推定値は個人の予測ではなく、迅速な治療によってリスクを減らせる可能性があります。言葉、筋力、視力が正常に戻った場合でも、緊急の診察を受けてください。.
通常の血液検査で脳卒中を否定できますか?
通常の定期血液検査では、脳動脈、頭蓋内出血、または損傷した脳組織を直接確認できないため、脳卒中を除外することはできません。血小板数が240 × 10⁹/Lであったり、INRが1.0であったりしても、虚血性脳卒中を発症していることがあります。緊急評価では、神経学的検査、脳画像検査、および必要に応じた補助検査が行われます。助けを求める前に、検査結果やAIの解釈を待たないでください。.
突然のめまいは脳卒中の兆候ですか?
突然のめまいは、特に重度の平衡障害、複視、言語の変化、または新たな筋力低下を伴う場合、脳卒中の症状である可能性があります。後方循環系の脳卒中では、FASTの3つの身体的チェック項目である顔(Face)、腕(Arms)、言語(Speech)が一見正常なことがあります。めまいの発作の多くは脳卒中以外が原因ですが、通常どおり歩けない場合や新たな局所神経症状がある場合は、緊急の評価が必要です。HINTSは訓練を受けた臨床医が行う診察であり、自宅でのスクリーニング検査として信頼できるものではありません。.
女性では脳卒中の症状が異なりますか?
女性にも一般的に、男性と同じBE-FASTの脳卒中警告サインが現れますが、頭痛、吐き気、混乱を伴うことがあります。女性向けの、別個の信頼できる脳卒中6サインチェックリストはありません。妊娠中または産後であることは、考えられる原因を増やすため、特に新たな重度の頭痛や局所的な神経脱落症状がある場合は、救急医療従事者に伝えてください。突然の神経学的変化を、評価を受けずにストレス、片頭痛、疲労のせいだと決めつけてはいけません。.
脳卒中を起こしていると思ったら、アスピリンを服用すべきですか?
脳卒中が疑われる場合、救急医療の専門家から服用するよう明確に指示されない限り、自己判断でアスピリンを服用しないでください。脳卒中の主な2つのメカニズムである動脈閉塞と頭蓋内出血では、必要な処置が異なり、出血がある場合はアスピリンが有害となる可能性があります。医療従事者は、地域の診療手順に従い、TIAが疑われる場合に直ちにアスピリンを処方することがありますが、これはすべての人に共通する自宅での指示ではありません。まず救急サービスに連絡し、嚥下の安全性と治療の指示が確認されるまで、食べ物、飲み物、錠剤を口にしないでください。.
How long do you have to get treatment for a stroke?
Eligible patients commonly receive intravenous thrombolysis within 4.5 hours of known onset, while selected patients may receive thrombectomy up to 24 hours based on imaging and other criteria. Some patients with unknown onset or wake-up stroke can also qualify for imaging-selected treatment. These windows are not safe waiting periods, and earlier assessment generally preserves more treatment options. Call immediately even if the onset time is uncertain or several hours have passed.
血液検査結果の見方を確認しましょう
検査報告書をアップロードすると、KantestiのAIが数秒で各バイオマーカーを平易な言葉で説明します。世界中で200万人以上が利用しています。.
参考文献
- Klein, T., Mitchell, S., & Weber, H. (2026). BUN/クレアチニン比の説明:腎機能検査ガイド。. Kantesti AI医学研究。. 掲載日
- Klein, T., Mitchell, S., & Weber, H. (2026). 尿中ウロビリノーゲン検査:完全尿検査ガイド2026。. Kantesti AI医学研究。. 掲載日
- Aroor S et al. (2017). BE-FAST (Balance, Eyes, Face, Arm, Speech, Time): Reducing the Proportion of Strokes Missed Using the FAST Mnemonic. Stroke. 掲載日
- Amin HP et al. (2023). Diagnosis, Workup, Risk Reduction of Transient Ischemic Attack in the Emergency Department Setting: A Scientific Statement From the American Heart Association. Stroke. 掲載日
- Powers WJ et al. (2019). Guidelines for the Early Management of Patients With Acute Ischemic Stroke: 2019 Update to the 2018 Guidelines for the Early Management of Acute Ischemic Stroke: A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association. Stroke. 掲載日
- 200万以上分析対象の検査
- 127+国
- 100+言語
医療チームについて


E-E-A-T 信頼性シグナル
経験
医師主導による、検査結果解釈ワークフローの臨床レビュー。.
専門知識
臨床的な文脈においてバイオマーカーがどのように振る舞うかに焦点を当てた検査医学。.
権威
Thomas Klein医師による医学的レビュー。Sarah Mitchell医師およびHans Weber教授の協力。.
信頼性
アラームを減らすための明確なフォローアップ経路を備えた、エビデンスに基づく解釈。.




医療免責事項
この記事は教育目的のみを対象としており、医療助言を構成するものではありません。診断や治療の判断を行う際は、必ず有資格の医療提供者にご相談ください。.
公開 · 編集チームにお問い合わせください
Kantesti Ltdが発行。イングランドおよびウェールズで登録、会社番号. 17090423, 、英国ロンドン。.
