
Sudden balance loss, vision changes, facial drooping, arm weakness, or speech difficulty can signal a stroke. Call your local emergency number immediately—even if symptoms disappear or routine bloodwork is normal; neither improvement nor normal laboratory results makes waiting safe.

Βασικά συμπεράσματα
- BE-FAST means Balance, Eyes, Face, Arms, Speech, and Time; one sudden warning sign can justify an emergency call.
- Emergency numbers include 999 or 112 in the UK and 911 in the US; use your local emergency service elsewhere.
- Disappearing symptoms may represent a transient ischemic attack, or TIA, and still require urgent assessment.
- Φυσιολογικές αιματολογικές εξετάσεις cannot exclude either an ischemic stroke or a stroke caused by bleeding.
- Last known well means the last time the person was definitely at their usual neurological baseline—not when someone discovered the symptoms.
- Treatment windows commonly include intravenous thrombolysis within 4.5 hours for eligible patients; selected patients may receive thrombectomy up to 24 hours.
- Women’s warning signs include the same BE-FAST symptoms as men’s; pregnancy or postpartum status changes the clinical context, not the need for emergency action.
- Μην περιμένετε for a laboratory report, an AI interpretation, a second episode, or improvement before calling for help.
Which stroke symptoms need an emergency call?
Sudden stroke symptoms require an immediate emergency call: new balance loss, vision loss or double vision, facial drooping, arm weakness, or speech difficulty. Use BE-FAST, but do not wait for all 6 signs; symptoms that disappear and normal routine bloodwork do not exclude stroke.
A stroke occurs when a brain artery becomes blocked or a brain vessel ruptures; these 2 mechanisms require different treatments. The symptoms cannot reliably distinguish them at home, which is why taking aspirin or trying to lower blood pressure yourself can be unsafe before professional assessment.
The practical clue is a sudden change from the person’s usual function, not whether they look seriously ill. Someone may remain awake, walk into a room, or describe only 1 weak hand while still having a disabling stroke; pain and loss of consciousness are not required.
For example, imagine a person speaking normally at 10:12 who develops garbled speech at 10:14 while eating breakfast. Call immediately and report both times; do not spend another 10 minutes checking facial symmetry, searching symptoms online, or arranging a routine blood test.
Kantesti is an AI blood test analyzer for understanding laboratory reports, not an emergency stroke diagnostic service. Our οργανισμός και το κλινικό μας πεδίο εφαρμογής should be understood alongside this limit: even an interpretation delivered in approximately 60 seconds must never delay an emergency call.
What do the six BE-FAST stroke signs mean?
BE-FAST stroke signs cover Balance, Eyes, Face, Arms, Speech, and Time to call emergency services. The 6-part mnemonic adds sudden imbalance and visual changes to FAST, helping people recognize strokes that do not begin with obvious facial drooping or arm weakness.
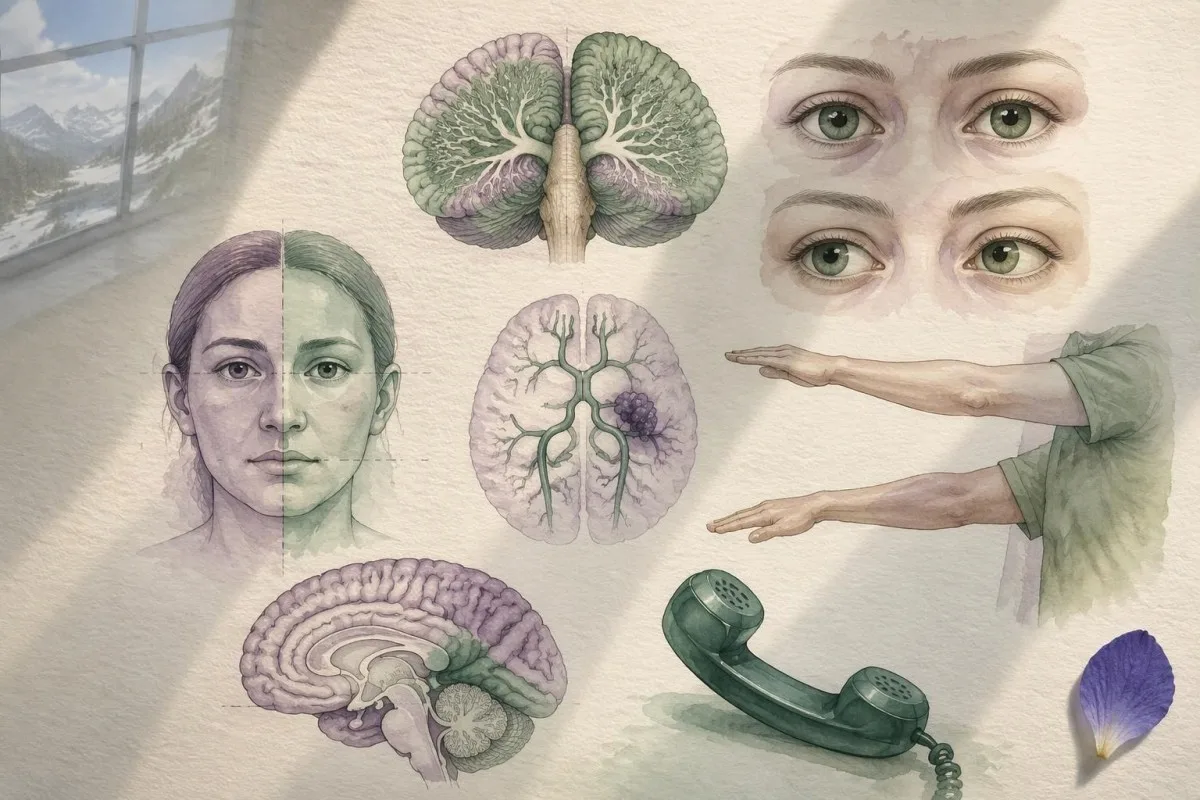
Balance means sudden unsteadiness, loss of coordination, or difficulty standing or walking; Eyes means sudden vision loss, double vision, or missing part of the visual field. Either can occur without the other 3 physical FAST features, so a normal smile does not make these symptoms safe to dismiss.
Face means a new uneven smile or facial droop; Arms means new weakness, drift, or numbness, especially on 1 side. Speech includes slurring, wrong words, inability to understand a simple sentence, or inability to produce words—not just an unfamiliar accent or someone speaking quietly.
Time means call now, not finish the checklist first. In a retrospective study of 736 ischemic strokes, FAST missed 14.1%; adding balance and visual symptoms reduced the missed proportion to 4.4% (Aroor et al., 2017), but those single-center results do not establish a universal home-screening accuracy.
A person with only hand symptoms still needs attention to timing and function. Our guide to finger-specific numbness patterns explains a common peripheral cause, but sudden loss of dexterity in 1 hand must not be assumed to be carpal tunnel syndrome without assessment.
When can sudden dizziness or imbalance signal stroke?
Sudden severe imbalance can signal a posterior circulation stroke, particularly when accompanied by double vision, speech changes, weakness, or inability to walk. These strokes involve structures such as the cerebellum and brainstem, so the 3 physical FAST checks may all appear normal.
Not every dizzy spell is a stroke; inner-ear disorders and faintness are common alternatives. The concerning combination is a new, persistent balance disturbance plus loss of a previously easy function—for example, being unable to take 2 unsupported steps or suddenly needing furniture to remain upright.
A positional trigger does not automatically prove an inner-ear cause, and nausea does not rule out stroke. If a person develops abrupt vertigo with 1 new neurological feature, such as double vision or slurred speech, call emergency services rather than testing repeated head movements at home.
The HINTS examination is a clinician-performed assessment used in a specific acute vestibular syndrome, not a 3-step self-test for every dizzy patient. Incorrect technique or use in the wrong setting can falsely reassure; an online demonstration cannot substitute for trained examination and appropriate imaging.
Orthostatic symptoms usually have a different pattern, often linked to standing and recurring over time. Our standing-related dizziness guide explains that distinction, but even someone with established POTS needs emergency assessment for 1 sudden, unfamiliar neurological deficit.
Which sudden vision changes count as stroke warnings?
Sudden vision loss, new double vision, or loss of one side of the visual field can be stroke symptoms. A problem affecting just 1 eye can also represent interrupted retinal circulation, which requires emergency assessment even when facial movement, arm strength, and speech seem normal.

Visual-field loss is different from blurred vision: a person may miss everything to the left or right despite both eyes being open. For example, they might see only 1 half of a plate or repeatedly bump into objects on the same side, without realizing that vision—not attention—is the problem.
New double vision can reflect impaired eye alignment from brainstem dysfunction, especially when paired with imbalance or speech changes. Tell the dispatcher whether the symptom involves 1 eye, both eyes, or a missing side of the scene, but do not delay the call to perform a detailed eye examination.
A brief, painless blackout in 1 eye can be a retinal TIA rather than an ordinary eye complaint. The fact that sight returns after several minutes is not evidence that circulation is safe; the episode may require brain, vessel, and cardiac assessment in addition to an eye examination.
Routine eye screening answers a different question from sudden visual loss. Our explanation of pressure and visual-field testing describes longer-term assessment, but an abrupt change over seconds or minutes should not wait for an optician appointment scheduled 1 week later.
Do early signs of stroke appear before the main event?
Early signs of stroke are often the stroke itself, not a predictable warning phase lasting days. Some people have a preceding TIA, but there is no reliable 24-hour symptom sequence; sudden loss of speech, strength, vision, or coordination deserves action at its first appearance.

Last known well is the last time someone was definitely at their usual neurological baseline. If a person went to sleep normally at 22:30 and woke with weakness at 06:30, both times matter; reporting 06:30 as the definite onset would incorrectly shorten the possible duration.
Wake-up symptoms are still an emergency, even when several hours may have passed. Some patients with unknown onset can receive treatment selected by imaging, so assuming that the usual 4.5-hour intravenous treatment window has already closed may wrongly prevent access to useful care.
A sudden severe headache reaching maximum intensity within about 1 minute is a thunderclap headache and warrants emergency assessment, particularly with vomiting, neck stiffness, or neurological changes. Many ischemic strokes cause no headache, so its absence must not become a reason to wait.
The speed of change helps distinguish some neurological patterns, but it cannot establish a diagnosis alone. Our προειδοποιητικά σημεία προοδευτικής αδυναμίας discuss a different emergency pattern; weakness evolving over 2 days and weakness appearing in seconds both need appropriate clinical evaluation.
Are stroke symptoms in women different?
Stroke symptoms in women usually include the same BE-FAST warning signs as in men. Some observational reports describe more accompanying confusion, headache, nausea, or generalized symptoms, but there is no separate reliable 6-sign checklist for women, and these nonspecific features cannot diagnose stroke alone.

A useful distinction is between a focal deficit and an accompanying symptom: inability to use 1 arm is more localizing than fatigue alone. If a woman has sudden nausea plus double vision and inability to walk, the neurological combination—not whether the symptoms sound stereotypically female—should drive the emergency call.
Pregnancy and the postpartum period change the possible causes of headache and neurological symptoms, including hypertensive complications and cerebral venous thrombosis. Tell emergency clinicians the pregnancy stage or delivery date; a new severe headache with 1 focal deficit should not be attributed to exhaustion or migraine without assessment.
Normal or previously reassuring pregnancy bloodwork cannot exclude a neurological emergency. Our explanation of οδηγός μας για τις εργαστηριακές εικόνες επειγόντων περιστατικών HELLP addresses one obstetric complication, but neither a normal platelet count nor normal liver enzymes excludes all causes of postpartum headache or stroke.
Consider a hypothetical woman 10 days after delivery who develops abrupt word-finding difficulty and a headache unlike her usual migraines. The safe action is an emergency call with the delivery date and last known well—not waiting for a repeat CBC, checking whether the headache improves, or asking an app to classify symptoms.
Why do disappearing symptoms still suggest a TIA?
Stroke-like symptoms that disappear may represent a TIA or a stroke with improving deficits, and both need urgent assessment. A modern TIA diagnosis concerns transient ischemia without acute infarction, not simply symptoms lasting under 24 hours; only professional evaluation can make that distinction.
Amin et al. (2023), in an American Heart Association scientific statement, reported 90-day stroke-risk estimates after TIA as high as 17.8%, with almost half of those strokes occurring within 2 days. Those figures describe particular study populations, not an individual prediction; prompt assessment and prevention can change the risk.
If weakness resolves while an ambulance is coming, do not cancel because the person now feels normal. Record when symptoms started, when they stopped, which side was affected, and whether any episode recurred; even 1 brief focal event may identify an unstable arterial or cardiac source.
Risk scores such as ABCD2 cannot safely replace vessel imaging, cardiac assessment, and clinical judgment. A low score may overlook important causes, while a normal examination after 10 minutes of resolved symptoms documents recovery rather than proving that the original event was harmless.
At Kantesti, we separate long-term laboratory risk review from assessment of a new neurological event. Our family-history stroke testing guide is relevant after urgent care, but a preventive panel next week is not a substitute for assessment of 1 suspected TIA today.
Can normal routine bloodwork rule out stroke?
Normal routine bloodwork cannot rule out stroke or TIA. A CBC, metabolic panel, lipid panel, or coagulation panel measures selected cellular, chemical, or clotting properties; none shows whether 1 brain artery is blocked, whether brain tissue is injured, or whether bleeding has occurred inside the skull.

An INR of 1.0 and a normal aPTT do not prove that no clot exists. These tests assess aspects of coagulation under laboratory conditions, not the presence of an arterial obstruction; our guide to τα όρια φυσιολογικών εξετάσεων πήξης explains why reassuring values can coexist with clinically important clotting.
A normal cholesterol result answers a risk-factor question, not an emergency diagnostic question. For example, an LDL cholesterol of 85 mg/dL does not exclude an embolus from atrial fibrillation or an artery problem; our metabolic panel versus cholesterol guide also clarifies which tests a routine panel actually contains.
Kantesti is an AI blood test interpretation platform that explains reported laboratory findings without using normal values to exclude stroke. A hypothetical platelet count of 240 × 10⁹/L, glucose of 98 mg/dL, and creatinine of 0.9 mg/dL can all coexist with a new cerebral artery blockage.
A panel from 2 days ago has an additional limitation: it describes the time of collection, not current neurological function. Emergency teams may repeat selected tests for treatment safety, but a person should call for help based on sudden symptoms rather than wait for a new sample or compare old reference ranges.
What should you do while emergency help is coming?
Call emergency services, report suspected stroke, and note the last known well time. Use 999 or 112 in the UK, 911 in the US, or your local emergency number; do not drive yourself, and do not wait for laboratory results before requesting help.
Keep the person safely supported and follow the dispatcher’s positioning instructions rather than making them walk to prove they are better. Do not offer food, drink, or tablets because stroke can impair swallowing; if consciousness or breathing changes, tell the dispatcher immediately and follow their resuscitation guidance.
Do not start aspirin, take an extra anticoagulant dose, or use extra blood-pressure medication on your own. The 2 major stroke mechanisms need different approaches, and sudden blood-pressure reduction can be harmful in some situations; clinicians may give aspirin for suspected TIA under a local pathway, but that is not a universal home-treatment instruction.
Gather medication names and the time of the last anticoagulant dose, especially for warfarin, apixaban, rivaroxaban, dabigatran, or edoxaban. Our επεξήγηση των αποτελεσμάτων INR helps clarify warfarin monitoring, but a normal INR does not reliably establish the absence of a direct oral anticoagulant’s effect.
For example, if symptoms began at 14:05 and a prescribed anticoagulant was taken at 08:00, communicate both exact times. Unlocking the door and having the medication list ready can help responders; finding an old report, charging a phone for an upload, or arranging private transport must not postpone the call.
Which emergency tests actually assess suspected stroke?
Suspected stroke is assessed with neurological examination, urgent brain imaging, and selected supporting tests—not routine bloodwork alone. A rapid glucose check identifies a treatable mimic; CT commonly checks for intracranial bleeding, while CT angiography or MRI may answer additional questions about arteries and brain tissue.
An early noncontrast CT may look normal during an ischemic stroke, so a reassuring initial scan is not always the end of assessment. MRI with diffusion-weighted imaging can detect many early infarcts, but early false-negative studies occur, particularly in posterior circulation events; persistent symptoms still need clinical reconciliation.
Low glucose can cause confusion, weakness, or speech difficulty, sometimes resembling a stroke. A glucose below 70 mg/dL, or 3.9 mmol/L, is hypoglycemia; below 54 mg/dL, or 3.0 mmol/L, is clinically significant hypoglycemia, and our low-glucose causes guide explains common medication and illness-related causes.
A severe metabolic disturbance can also complicate examination, but finding one does not automatically exclude simultaneous stroke. Our glucose-adjusted sodium explanation describes why marked hyperglycemia changes sodium interpretation; neither calculation should delay emergency assessment of 1 new focal deficit.
Kantesti AI can explain laboratory terminology after collection, but it cannot perform a neurological examination or interpret an evolving emergency as a safe exclusion of stroke. Powers et al. (2019) state that only glucose must precede intravenous thrombolysis in all patients; additional laboratory results may be needed when specific medication, bleeding, or coagulation concerns exist.
Why must treatment not wait for routine test results?
Stroke treatment is time-sensitive because threatened brain tissue may become permanently injured while testing is delayed. Established treatment pathways include intravenous thrombolysis within 4.5 hours for eligible patients and thrombectomy up to 24 hours in selected patients; those limits are eligibility windows, not safe periods for waiting.

Thrombolysis uses medication to dissolve an eligible clot; thrombectomy uses a catheter-based device to remove selected artery blockages. The 2019 AHA/ASA guideline describes imaging-selected thrombectomy between 6 and 24 hours for certain patients (Powers et al., 2019), but anatomy, imaging findings, baseline function, and specialist judgment determine eligibility.
Blood pressure and medication exposure affect treatment safety without becoming reasons to stay home. An established pre-thrombolysis blood-pressure threshold is below 185/110 mmHg, and hospital teams can manage elevated readings; patients should not attempt to meet that threshold using extra tablets before transport.
Coagulation results matter when a specific safety concern is present, but they do not diagnose the blockage itself. A platelet count below 100 × 10⁹/L or warfarin-associated INR above 1.7 can affect standard intravenous thrombolysis eligibility; our clotting assay interpretation guide explains why different assays answer different questions.
Imagine someone first assessed 3 hours after definite symptom onset who waits another 90 minutes for a nonessential routine panel before reaching a stroke team. That delay may consume a conventional treatment window, although eligibility is never decided by time alone; the safer sequence is emergency assessment first, with necessary tests performed in parallel.
Can migraine, seizures, or brain biomarkers distinguish stroke?
Migraine, seizures, low glucose, and some vestibular disorders can mimic stroke, but they cannot be reliably distinguished at home. No routine report containing 1 neurological biomarker establishes that a sudden deficit is harmless; examination, symptom timing, and appropriate imaging remain central to assessment.
Migraine aura often spreads gradually across several minutes, whereas stroke often causes an abrupt loss of function, but the patterns overlap. A first aura, an unfamiliar aura, or a sudden negative symptom such as losing 1 side of vision should not be self-diagnosed as migraine just because headache is present.
A seizure can be followed by temporary weakness, sometimes called Todd paralysis, and a stroke can itself trigger a seizure. Reporting witnessed shaking or a 1-minute episode of unresponsiveness helps clinicians, but it does not make subsequent weakness safe to observe without urgent assessment.
Neurofilament light chain reflects neuronal injury in multiple conditions rather than functioning as a rapid stroke exclusion test. Our NfL result interpretation guide explains this nonspecificity; a single result, whether high or low, cannot replace assessment of 1 newly impaired neurological function.
Some GFAP-based testing pathways address selected traumatic brain injuries, not universal stroke screening. Our GFAP and head-injury guide discusses that separate use; even where research examines stroke biomarkers, assay timing, thresholds, and performance vary, so 1 normal value must not reassure a symptomatic person.
How can blood tests help after the emergency assessment?
Blood tests help identify and monitor some stroke risk factors after urgent diagnosis, including diabetes and atherogenic cholesterol patterns. They do not replace blood-pressure measurement, cardiac rhythm assessment, or vascular imaging, and 1 reassuring panel does not guarantee that a person will not have another event.

A hypothetical follow-up panel with LDL cholesterol of 142 mg/dL and HbA1c of 7.2% identifies modifiable concerns, not the exact cause of the event. Our ApoB treatment-decision guide explains particle-related risk assessment; treatment targets depend on the diagnosed stroke mechanism, comorbidities, and the clinician’s prevention plan.
Hypertension needs direct measurement because a chemistry panel does not measure arterial pressure. Our secondary hypertension testing guide explains selected laboratory investigations, but 2 normal electrolyte results do not exclude common primary hypertension or replace repeated blood-pressure readings.
Atrial fibrillation may require ECG monitoring because 1 short recording can miss intermittent episodes. Similarly, broad inherited thrombophilia testing is not automatically useful after every arterial stroke; the history, age, imaging pattern, and suspected mechanism determine which additional investigations could change treatment.
Kantesti can support clinician-directed comparison of follow-up laboratory reports, but medication changes belong within the prescribed care plan. Whole-food eating patterns, smoking cessation, activity adapted to recovery, and consistent medication use address longer-term risk; none can reverse a new sudden deficit or justify waiting 1 more day for emergency assessment.
Research publications, evidence, and laboratory interpretation limits
The stroke evidence cited here supports emergency recognition and assessment; our 2 listed repository publications address general laboratory interpretation, not stroke diagnosis. Readers can review our validation methods and limits without treating technical evaluation as proof that an AI tool can exclude an acute neurological emergency.

Our listed kidney-function interpretation guide explains BUN and creatinine in their own clinical context. Its Zenodo DOI identifies a repository publication; a creatinine of 0.9 mg/dL, for example, describes a laboratory finding and cannot establish that cerebral circulation is intact.
Το συνοδευτικό urinalysis interpretation publication addresses urine findings rather than acute brain assessment. These 2 repository references are included for transparency about related educational material, not as external stroke guidelines, peer-reviewed stroke trials, or evidence that urine testing can distinguish TIA from stroke.
Kantesti is an AI-powered blood test analysis tool whose educational role must remain separate from emergency triage and definitive diagnosis. Our πρότυπα ιατρικού περιεχομένου explain the editorial framework; the 3 external medical references below address BE-FAST, suspected TIA, and established acute ischemic stroke management.
Clinical follow-up may involve sharing reports with a treating team, but that should happen after emergency needs are addressed. Our το απόρρητο και τα δεδομένα describe report handling; permission to review 1 family member’s laboratory report does not authorize access to another’s, and no upload should postpone an emergency call.
Συχνές ερωτήσεις
Ποια είναι τα πρώτα προειδοποιητικά σημάδια ενός εγκεφαλικού επεισοδίου;
Τα πρώτα προειδοποιητικά σημάδια εγκεφαλικού επεισοδίου είναι συχνά η αιφνίδια απώλεια ισορροπίας, οι αλλαγές στην όραση, η πτώση του προσώπου, η αδυναμία στο χέρι ή η δυσκολία στην ομιλία. Το BE-FAST τα οργανώνει σε 6 ερωτήματα, συμπεριλαμβανομένου του χρόνου κλήσης των υπηρεσιών έκτακτης ανάγκης. Δεν χρειάζεται να εμφανίζει κάποιος όλα τα σημάδια, πονοκέφαλο ή απώλεια συνείδησης για να υποστεί εγκεφαλικό επεισόδιο. Καλέστε αμέσως για οποιοδήποτε νέο, αιφνίδιο νευρολογικό έλλειμμα και αναφέρετε την τελευταία ώρα που ήταν γνωστό ότι το άτομο βρισκόταν στη συνήθη κατάστασή του.
0 Μπορούν τα συμπτώματα εγκεφαλικού επεισοδίου να υποχωρήσουν μετά από λίγα λεπτά;
Τα συμπτώματα του εγκεφαλικού μπορεί να εξαφανιστούν μετά από λίγα λεπτά λόγω παροδικού ισχαιμικού επεισοδίου (TIA) ή εγκεφαλικού που βρίσκεται σε ύφεση, αλλά η εξαφάνισή τους δεν σημαίνει ότι δεν υπάρχει κίνδυνος. Η δήλωση της American Heart Association του 2023 για το TIA αναφέρει εκτιμήσεις κινδύνου εγκεφαλικού εντός 90 ημερών έως και 17.8% σε ορισμένους πληθυσμούς, με σχεδόν τα μισά περιστατικά να συμβαίνουν εντός 2 ημερών. Αυτές οι εκτιμήσεις δεν αποτελούν πρόβλεψη για ένα συγκεκριμένο άτομο και η άμεση θεραπεία μπορεί να μειώσει τον κίνδυνο. Ζητήστε επείγουσα αξιολόγηση ακόμη και αν η ομιλία, η δύναμη ή η όραση επανέλθουν στο φυσιολογικό.
Μπορούν οι συνήθεις αιματολογικές εξετάσεις να αποκλείσουν ένα εγκεφαλικό επεισόδιο;
Οι συνήθεις αιματολογικές εξετάσεις δεν μπορούν να αποκλείσουν εγκεφαλικό επεισόδιο, επειδή δεν απεικονίζουν άμεσα τις αρτηρίες του εγκεφάλου, την ενδοκράνια αιμορραγία ή τον τραυματισμένο εγκεφαλικό ιστό. Ένας αριθμός αιμοπεταλίων 240 × 10⁹/L ή ένα INR 1.0 μπορεί να συνυπάρχει με ισχαιμικό εγκεφαλικό επεισόδιο. Η επείγουσα αξιολόγηση βασίζεται στη νευρολογική εξέταση, στην απεικόνιση του εγκεφάλου και σε επιλεγμένες υποστηρικτικές εξετάσεις. Μην περιμένετε τα αποτελέσματα εργαστηριακών εξετάσεων ή την ερμηνεία της ΤΝ πριν καλέσετε για βοήθεια.
Είναι η ξαφνική ζάλη ένδειξη εγκεφαλικού επεισοδίου;
Η ξαφνική ζάλη μπορεί να είναι σύμπτωμα εγκεφαλικού επεισοδίου, ιδιαίτερα όταν συνοδεύεται από σοβαρή αστάθεια, διπλωπία, αλλαγές στην ομιλία ή νέα αδυναμία. Τα εγκεφαλικά επεισόδια της οπίσθιας κυκλοφορίας μπορεί να αφήσουν τους 3 σωματικούς ελέγχους FAST—Πρόσωπο, Χέρια και Ομιλία—φαινομενικά φυσιολογικούς. Πολλά επεισόδια ζάλης έχουν αιτίες που δεν σχετίζονται με εγκεφαλικό επεισόδιο, αλλά η αδυναμία φυσιολογικής βάδισης ή ένα νέο εστιακό έλλειμμα απαιτεί επείγουσα αξιολόγηση. Το HINTS είναι εξέταση που διενεργείται από εκπαιδευμένο κλινικό ιατρό και δεν αποτελεί αξιόπιστη μέθοδο αυτοελέγχου στο σπίτι.
Διαφέρουν τα συμπτώματα του εγκεφαλικού επεισοδίου στις γυναίκες;
Οι γυναίκες έχουν γενικά τα ίδια προειδοποιητικά σημάδια εγκεφαλικού επεισοδίου BE-FAST με τους άνδρες, αν και μπορεί να συνοδεύονται από πονοκέφαλο, ναυτία ή σύγχυση. Δεν υπάρχει ξεχωριστός αξιόπιστος κατάλογος 6 σημείων εγκεφαλικού επεισοδίου για τις γυναίκες. Η εγκυμοσύνη ή η περίοδος μετά τον τοκετό προσθέτει πιθανές αιτίες και θα πρέπει να αναφέρεται στους επαγγελματίες υγείας των επειγόντων περιστατικών, ιδιαίτερα όταν εμφανίζεται νέος έντονος πονοκέφαλος ή εστιακό νευρολογικό έλλειμμα. Οι αιφνίδιες νευρολογικές μεταβολές δεν θα πρέπει να αποδίδονται στο στρες, στην ημικρανία ή στην εξάντληση χωρίς αξιολόγηση.
Πρέπει να πάρω ασπιρίνη αν νομίζω ότι παθαίνω εγκεφαλικό;
Μην ξεκινήσετε να παίρνετε ασπιρίνη με δική σας πρωτοβουλία σε περίπτωση υποψίας εγκεφαλικού επεισοδίου, εκτός αν ένας επαγγελματίας των υπηρεσιών έκτακτης ανάγκης σάς δώσει ρητά οδηγίες να την πάρετε. Οι δύο κύριοι μηχανισμοί του εγκεφαλικού επεισοδίου — η αρτηριακή απόφραξη και η ενδοκράνια αιμορραγία — απαιτούν διαφορετική αντιμετώπιση, ενώ η ασπιρίνη μπορεί να είναι επιβλαβής όταν υπάρχει αιμορραγία. Οι κλινικοί γιατροί μπορεί να συνταγογραφήσουν άμεσα ασπιρίνη σε περίπτωση υποψίας παροδικού ισχαιμικού επεισοδίου (TIA), στο πλαίσιο ενός τοπικού κλινικού πρωτοκόλλου, αλλά αυτό δεν αποτελεί καθολική οδηγία για το σπίτι. Καλέστε πρώτα τις υπηρεσίες έκτακτης ανάγκης και αποφύγετε φαγητό, ποτό ή δισκία μέχρι να διευκρινιστούν η ασφάλεια της κατάποσης και οι οδηγίες θεραπείας.
How long do you have to get treatment for a stroke?
Eligible patients commonly receive intravenous thrombolysis within 4.5 hours of known onset, while selected patients may receive thrombectomy up to 24 hours based on imaging and other criteria. Some patients with unknown onset or wake-up stroke can also qualify for imaging-selected treatment. These windows are not safe waiting periods, and earlier assessment generally preserves more treatment options. Call immediately even if the onset time is uncertain or several hours have passed.
Δείτε πώς να διαβάσετε εξετάσεις αίματος
Ανεβάστε την εργαστηριακή σας αναφορά και η τεχνητή νοημοσύνη της Kantesti εξηγεί κάθε βιοδείκτη με απλή γλώσσα μέσα σε λίγα δευτερόλεπτα. Την έχουν χρησιμοποιήσει περισσότεροι από 2 εκατομμύρια άνθρωποι παγκοσμίως.
Αναφορές
- Klein, T., Mitchell, S., & Weber, H. (2026). Λόγος BUN/Κρεατινίνης Επεξήγηση: Οδηγός Εξέτασης Νεφρικής Λειτουργίας. Ιατρική έρευνα της τεχνητής νοημοσύνης Kantesti. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Ουροχολινογόνο στα Ούρα: Οδηγός Πλήρους Ανάλυσης Ούρων 2026. Ιατρική έρευνα της τεχνητής νοημοσύνης Kantesti. DOI
- Aroor S et al. (2017). BE-FAST (Balance, Eyes, Face, Arm, Speech, Time): Reducing the Proportion of Strokes Missed Using the FAST Mnemonic. Stroke. DOI
- Amin HP et al. (2023). Diagnosis, Workup, Risk Reduction of Transient Ischemic Attack in the Emergency Department Setting: A Scientific Statement From the American Heart Association. Stroke. DOI
- Powers WJ et al. (2019). Guidelines for the Early Management of Patients With Acute Ischemic Stroke: 2019 Update to the 2018 Guidelines for the Early Management of Acute Ischemic Stroke: A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association. Stroke. DOI
- 2+ εκατομμύριαΕξετάσεις που αναλύθηκαν
- 127+χωρών
- 100+Γλώσσες
Σχετικά με την ιατρική ομάδα


Σήματα εμπιστοσύνης E-E-A-T
Εμπειρία
Κλινική ανασκόπηση από ιατρό για τις ροές εργασίας ερμηνείας εργαστηριακών αποτελεσμάτων.
Πραγματογνωμοσύνη
Εστίαση στην εργαστηριακή ιατρική στο πώς συμπεριφέρονται οι βιοδείκτες στο κλινικό πλαίσιο.
Αυθεντικότητα
Ιατρική αξιολόγηση από τον Δρ. Thomas Klein, με συνεισφορές από τη Δρ. Sarah Mitchell και τον Καθ. Δρ. Hans Weber.
Αξιοπιστία
Ερμηνεία βασισμένη σε τεκμηριωμένα δεδομένα με σαφείς οδούς παρακολούθησης για τη μείωση του συναγερμού.




Ιατρική αποποίηση ευθύνης
Αυτό το άρθρο προορίζεται μόνο για εκπαιδευτικούς σκοπούς και δεν αποτελεί ιατρική συμβουλή. Συμβουλεύεστε πάντα έναν κατάλληλο επαγγελματία υγείας για αποφάσεις σχετικά με τη διάγνωση και τη θεραπεία.
Δημοσιεύθηκε · Επικοινωνήστε με τη συντακτική ομάδα
Εκδίδεται από την Kantesti Ltd, εγγεγραμμένη στην Αγγλία και την Ουαλία, αριθμός εταιρείας. 17090423, Λονδίνο, Ηνωμένο Βασίλειο.
