Positive means the fusion was detected; negative means it was not detected by that particular assay. The clinical meaning changes substantially between diagnosis and treatment monitoring.


- BCR-ABL1 positive meaning: The assay detected the fusion associated with chronic myeloid leukemia and some acute lymphoblastic leukemias; the result alone does not distinguish these diagnoses.
- BCR-ABL1 negative meaning: No covered fusion was detected in the tested specimen. A negative result does not exclude every leukemia or every rare BCR-ABL1 transcript.
- International Scale: BCR-ABL1 PCR percentages describe a standardized transcript ratio, not the percentage of your body or cellular elements affected.
- Major molecular response: BCR-ABL1 of 0.1% IS or lower meets the usual MMR threshold for appropriately monitored CML.
- Deep molecular response: MR4 corresponds to 0.01% IS or lower; MR4.5 corresponds to 0.0032% IS or lower, with adequate assay sensitivity.
- Undetectable results: A negative PCR result cannot establish MR4.5 unless the specimen contains enough reference-gene material to support that sensitivity.
- Treatment milestones: The 2020 European LeukemiaNet framework uses 10%, 1% and 0.1% IS at 3, 6 and 12 months as optimal-response thresholds, interpreted with the full clinical picture.
- Stopping treatment: One undetectable result is not permission to stop a tyrosine kinase inhibitor. Selected patients need sustained deep response and a specialist-supervised monitoring plan.
What positive and negative BCR-ABL1 results actually mean
Positive BCR-ABL1 test results mean the laboratory detected the BCR::ABL1 fusion in your specimen. Negative results mean the assay did not detect the fusion it was designed to find. Before treatment, a positive result supports a fusion-associated leukemia diagnosis; during treatment, it measures residual disease. Undetectable does not necessarily mean cure.
The reason for testing changes the interpretation more than the word positive does. Consider two hypothetical patients: a 52-year-old being investigated for persistent leukocytosis and a 52-year-old already receiving treatment for CML. The first needs diagnostic classification; the second needs comparison with previous molecular measurements and the treatment timeline.
A qualitative result answers whether a target was detected, while a quantitative result measures its amount within an assay-defined framework. A report stating detected without a percentage may be appropriate for initial transcript identification but insufficient for routine response assessment. Our explanation of qualitativen und quantitativen Tests helps separate these two reporting formats.
Interpretation starts with three details: indication, assay coverage and specimen quality. I'm Thomas Klein, MD, Chief Medical Officer at Kantesti, and those are the details I would check before discussing a reassuring or concerning number. Kantesti is an AI blood test analyzer that helps explain laboratory report terminology; our Organisation und unser klinischer Fokus do not replace specialist molecular hematology interpretation.
What the BCR::ABL1 fusion says about the underlying biology
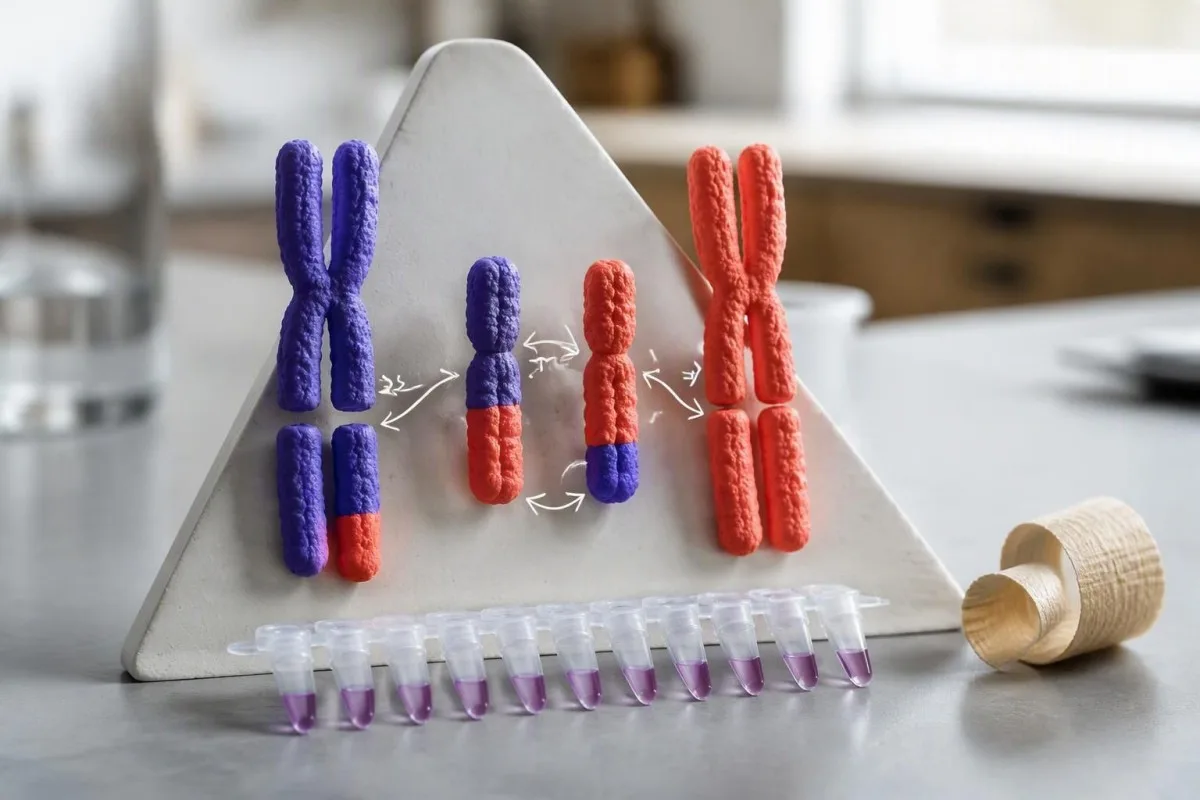
BCR::ABL1 joins material from the BCR gene on chromosome 22 with the ABL1 gene on chromosome 9. The resulting fusion protein has abnormal tyrosine kinase activity. This usually arises through an acquired rearrangement called t(9;22), although variant or cryptic rearrangements can produce the same fusion without a textbook chromosome appearance.
The Philadelphia chromosome is the altered chromosome 22 traditionally associated with this rearrangement. A karyotype examines chromosome structure, whereas PCR commonly detects the fusion's RNA transcript after conversion to complementary DNA. These are related findings, not interchangeable measurements: chromosome appearance and transcript abundance answer different questions.
BCR::ABL1 is usually an acquired change in a hematopoietic cell clone, not an inherited finding present throughout the body. A parent with BCR::ABL1-positive CML does not automatically need their children tested for that fusion. This differs from an inherited thrombophilia result, as explained in our Factor V Leiden interpretation.
A fusion's biological importance does not tell us its quantity from a yes-or-no report. One clearly positive diagnostic specimen may establish a crucial treatment target, but it cannot tell you whether the disease is chronic-phase CML or a BCR::ABL1-positive acute leukemia. Morphology, immunophenotyping, chromosome findings and clinical history establish that distinction together.
How PCR, FISH and chromosome testing differ at diagnosis
PCR detects fusion transcripts, FISH detects a fusion-associated DNA signal pattern, and karyotyping examines chromosomes in dividing cells. Initial diagnosis often requires more than one method because each has different strengths. A PCR percentage, a FISH-positive cell percentage and a Philadelphia-positive metaphase percentage must not be treated as the same measurement.
Diagnostic BCR::ABL1 testing identifies the molecular target but does not independently establish cell lineage or disease phase. The European LeukemiaNet laboratory recommendations describe complementary roles for cytogenetics, molecular assays and transcript identification at presentation (Cross et al., 2023). An apparently straightforward positive result can therefore still require marrow assessment and additional chromosome analysis.
Flow cytometry answers a different diagnostic question from BCR::ABL1 PCR: which cellular population is present and what characteristics it expresses. A 20% blast finding, for example, must be interpreted with disease-specific classification criteria rather than converted into a PCR response category. Our discussion of PNH-Durchflusszytometrie illustrates why cell-based and molecular measurements should remain separate.
A peripheral smear can strengthen suspicion but cannot substitute for fusion testing. Basophilia, immature granulocytes or unusual cellular morphology may prompt targeted investigation, while findings such as teardrop cells on smears broaden the differential diagnosis. Ask whether the report's percentage describes transcripts, interphase nuclei or metaphases—those three denominators are fundamentally different.
Why p210, p190 and atypical transcripts change interpretation
The transcript name identifies which BCR::ABL1 RNA junction the assay detected and determines how future monitoring should be performed. Most CML cases express e13a2 or e14a2 transcripts, commonly called p210. The e1a2 transcript, commonly called p190, is frequent in BCR::ABL1-positive ALL but is not exclusive to that diagnosis.
Approximately 2% of CML patients have atypical transcripts that may not be reliably measured by routine p210 assays. Cross et al. (2023) recommend identifying the transcript at diagnosis so that monitoring targets the actual fusion. A negative standard assay is much less reassuring if the original positive transcript was never documented or falls outside that assay's coverage.
Atypical transcript monitoring may require a personalized assay and response measurements referenced to the patient's own baseline rather than standard IS thresholds. A p190 ratio should not automatically be compared with p210 CML milestones such as 0.1% IS. The laboratory must specify whether its particular result has validated International Scale calibration for that transcript.
The precise target name matters more than the abbreviation on a report header. At Kantesti, our explanatory approach distinguishes BCR::ABL1 fusion detection from other ABL1-related molecular tests; our Leitfaden zur Biomarker-Terminologie provides broader context. Keep the original transcript report alongside follow-up results, especially when moving between two hospitals or molecular laboratories.
What a negative BCR-ABL1 test means before diagnosis
A negative diagnostic BCR::ABL1 result means the tested specimen did not contain a detectable covered fusion; it does not mean all leukemia has been excluded. The result argues against conventional BCR::ABL1-positive CML when assay coverage and specimen quality are appropriate. Persistent clinical suspicion may require complementary testing rather than simple reassurance.
A technically inadequate specimen is not equivalent to a genuine negative result. Degraded RNA, insufficient cellular material, inhibition or failed reference-gene amplification can make a result uninterpretable. If a report contains both not detected and a specimen-adequacy warning, those two statements must be read together rather than allowing the reassuring phrase to override the limitation.
BCR::ABL1-negative disorders can still cause major abnormalities on a complete blood count. Other myeloid neoplasms, acute leukemias and marrow-failure conditions need different investigations; a negative fusion result does not settle those possibilities. Our Leitfaden zu CBC-Mustern bei aplastischer Anämie explain one separate marrow-failure pathway without implying that BCR::ABL1 is a general screening test.
Discordant results deserve laboratory discussion before diagnostic labels are changed. A fusion-positive FISH result with a negative routine p210 PCR may suggest an uncovered transcript or another technical issue, while an isolated extremely low PCR signal may require confirmation. The practical question is not which of two tests wins, but whether both methods examined the same target in suitable material.
How to read a BCR-ABL1 PCR International Scale percentage
A BCR-ABL1 PCR International Scale percentage is a calibrated ratio of BCR::ABL1 transcripts to a reference gene, expressed against a standardized historical baseline. It is not the percentage of leukemic cells in your body. The IS baseline of 100% is a reference convention, not a claim that every cellular element is affected.
The International Scale links laboratory measurements to the standardized baseline used in early CML treatment studies. A laboratory applies an established calibration method, such as a validated conversion factor or calibrated assay system, to its measured transcript ratio. Values above 100% IS can occur and do not imply more than 100% of a patient's cells are leukemic.
BCR::ABL1 of 1% IS is ten times higher than 0.1% IS, despite a difference of only 0.9 percentage points. The measurement's denominator is reference-gene expression, not a conventional cell count. Our explanation of counts versus percentages highlights a related denominator problem, although CBC percentages and molecular transcript ratios are distinct measurements.
Reports that omit IS should not automatically be interpreted using IS milestones. A raw BCR::ABL1/ABL1 ratio of 0.08% might or might not correspond to 0.08% IS, depending on assay calibration and transcript coverage. Ask the laboratory whether the displayed value is already standardized; applying a conversion twice is just as misleading as not applying it at all.
Kantesti is an AI blood test interpretation platform that helps distinguish report units, including whether a molecular percentage is explicitly marked IS. A low displayed number is not enough to establish a response category if calibration or sample sensitivity is missing. The safest comparison retains the transcript name, laboratory, reference gene and date alongside each percentage.
What MMR, MR4 and MR4.5 thresholds mean
Major molecular response, or MMR, means BCR::ABL1 is 0.1% IS or lower in standard CML monitoring. MR4 means 0.01% IS or lower; MR4.5 means 0.0032% IS or lower. These categories describe progressively deeper molecular responses, provided the assay and specimen support the claimed measurement sensitivity.
The MR labels describe logarithmic reductions from the standardized IS baseline, not reductions from every patient's personal diagnostic value. A fall from 100% to 0.1% IS is a 1,000-fold reduction and corresponds to MR3 or MMR. A patient who starts at 35% IS should not substitute 35% for the standardized baseline when assigning MR4.
A low positive result can still represent excellent disease control. BCR::ABL1 of 0.006% IS meets MR4 numerically while remaining detectable, so positive does not automatically mean treatment failure. Conversely, the categories in the table are response descriptors—not emergency severity levels—and must be interpreted with treatment duration and serial results.
Molecular response and nonspecific cellular-turnover markers answer different questions. An isolated rise in LDH and cellular turnover cannot replace BCR::ABL1 monitoring or assign an MR category. For an undetectable result, request the reference-gene transcript count or the laboratory's validated sensitivity statement before calling it MR4.5 or MR5.
How treatment timing changes the meaning of a PCR result
A BCR::ABL1 percentage must be interpreted against time since treatment began, previous results and treatment interruptions. The 2020 European LeukemiaNet framework defines optimal responses as no more than 10% IS at 3 months, 1% at 6 months and 0.1% at 12 months. A single value is not a complete treatment assessment.
The 3-, 6- and 12-month milestones are decision frameworks rather than automatic instructions to change medication. Hochhaus et al. (2020) specify that a value above 10% IS at 3 months requires confirmation within 1–3 months before meeting that framework's failure definition. Subsequent specialist decisions also consider the pace of decline, drug tolerance, comorbidities and treatment goals.
The same 0.2% IS result can have different implications at 6 months and after years of stable MMR. At 6 months it is below the 1% optimal-response threshold in the 2020 framework; after a long period below 0.1%, it may represent loss of MMR and warrant closer investigation. Our Vergleich serieller Ergebnisse emphasizes keeping dates and clinical events attached to measurements.
Medication interruptions can explain a slower molecular decline without proving biological resistance. In a hypothetical patient with 0.8% IS at 6 months, a documented 3-week interruption for intolerance would matter to the interpretation. Bring the actual start date, missed-dose history and interruption dates—not just the laboratory's high flag—to your hematology appointment.
Why an undetectable BCR-ABL1 result does not prove cure
Undetectable BCR::ABL1 means no target was detected within that specimen's demonstrated sensitivity; it does not prove that every fusion-positive cell has disappeared. Residual cells can remain below the assay's detection limit. A report can therefore be negative while the patient still needs medication, molecular monitoring or both.
The depth of an undetectable response depends on how much usable reference-gene material was examined. With ABL1 as the reference gene, commonly used criteria require at least 10,000 ABL1 transcripts to support undetectable MR4, 32,000 for MR4.5 and 100,000 for MR5, subject to the laboratory's validated workflow (Cross et al., 2023). These counts assess measurement adequacy; they are not leukemic-cell counts.
Not detected with 8,000 ABL1 transcripts cannot automatically be assigned the same depth as not detected with 50,000. The second specimen may support a deeper response claim, while the first does not meet the usual ABL1 count requirement for MR4. Ask for the sensitivity achieved in this particular specimen, not simply the instrument's best advertised detection limit.
Undetectable is an assay statement in other fields too, but the treatment implications are disease-specific. Unser HIV viral-load explanation makes that measurement distinction clear without implying that HIV management rules apply to CML. For BCR::ABL1 monitoring, avoid interpreting a displayed 0.000% as mathematical proof of zero residual disease.
When a rising or newly detectable PCR result needs action
A rising BCR::ABL1 result needs interpretation of its absolute level, change from baseline and clinical setting—not panic over detectability alone. A change from 0.002% to 0.004% IS remains within MR4, whereas a change from 0.02% to 0.2% crosses the MMR threshold. Those situations deserve different follow-up.
Very low transcript measurements have more sampling variability because fewer target molecules are being counted. Detectable below the quantification limit means the target was found but its amount cannot be estimated with the laboratory's usual quantitative reliability. That wording is different from a reproducibly quantified result of 0.2% IS, even though both may appear positive.
Loss of MMR while taking treatment warrants review of adherence, interruptions, interactions and possible resistance. Kantesti AI explanations should preserve the distinction between a twofold low-level fluctuation and a tenfold rise crossing 0.1% IS; neither should be interpreted from a color flag alone. Our discussion of differences between laboratory visits provides general measurement context, not a substitute for molecular hematology rules.
BCR::ABL1 fusion quantification and ABL1 kinase-domain mutation testing are separate assays. The first tracks fusion transcript abundance; the second may investigate treatment resistance when clinically indicated. During supervised treatment-free remission, loss of MMR generally triggers prompt treatment restart rather than waiting for another routine test, while minor fluctuations on treatment may lead to repeat testing first.
How specimen handling and laboratory changes affect results
RNA quality, specimen cellularity, assay coverage and laboratory calibration can change how confidently BCR::ABL1 results are interpreted. Most routine CML molecular monitoring uses peripheral blood, often collected in an EDTA tube according to local instructions. Fasting is generally unnecessary for this assay, but correct collection and prompt processing still matter.
A molecular monitoring specimen must reach the laboratory within its validated transport and stability conditions. There is no universal 24-hour rule that can safely replace the receiving laboratory's instructions; tube type, temperature and transport time are method-dependent. Our first-draw preparation advice helps organize the appointment, but the molecular laboratory's requirements take priority.
Changing laboratories can introduce a measurement step that resembles a biological change. Two properly standardized laboratories aim for comparable IS values, yet extraction, amplification and low-level sampling differences remain relevant. If a first result from a new laboratory changes from 0.03% to 0.06% IS, the specialist should examine the previous trajectory and methodology before interpreting the twofold difference as resistance.
Digital PCR is not automatically an International Scale result just because it counts molecules differently. A digital assay still needs appropriate validation, transcript coverage and IS calibration before conventional response thresholds are applied. Keep one longitudinal record with the laboratory name, specimen type, reference gene and sensitivity; this becomes particularly useful after two or more changes of testing center.
Can treatment stop after repeated negative BCR-ABL1 tests?
Some carefully selected CML patients can attempt treatment-free remission after sustained deep molecular response, but repeated negative tests alone do not establish eligibility. A hematologist must confirm disease history, treatment duration, transcript monitorability and access to frequent sensitive PCR. Do not stop a tyrosine kinase inhibitor because one report says undetectable.
The 2020 European LeukemiaNet discontinuation framework includes first chronic phase, prolonged treatment and sustained deep response. Its minimum treatment duration is generally more than 5 years, or more than 4 years for a second-generation TKI, with more than 2 years of MR4 or deeper and additional eligibility conditions (Hochhaus et al., 2020). Local and newer specialist protocols may differ; these figures are not a self-assessment checklist.
Treatment-free remission is achievable for many selected patients, but molecular recurrence remains common. EURO-SKI reported molecular relapse-free survival of 61% at 6 months and 50% at 24 months after stopping treatment (Saussele et al., 2018). Those estimates apply to an eligible study population, not to every patient who obtains an undetectable result.
The 2020 ELN framework recommends monthly PCR for the first 6 months after stopping, every 2 months during months 6–12, and every 3 months afterward. Reliable access to testing and rapid reporting are part of the safety plan. Our medication trend tracking guidance supports organizing dates, but an app cannot authorize discontinuation or delay a restart decision.
Loss of MMR—BCR::ABL1 rising above 0.1% IS—is the usual molecular trigger to restart treatment during a supervised stopping attempt. Detectability below that threshold does not automatically end treatment-free remission, although it may prompt closer monitoring. The thing is, treatment-free remission means control without ongoing medication; it is not laboratory proof that no fusion-positive cells remain.
What to check on your report and ask your hematologist
Before interpreting a BCR::ABL1 report, check six items: testing purpose, transcript, specimen, IS status, sensitivity and the previous dated result. A newly positive diagnostic test needs prompt hematology follow-up; a monitoring result needs comparison with your treatment plan. Neither situation can be assessed safely from the percentage alone.
Three useful questions are: Is this result on the International Scale, what response depth does the specimen support, and has my response category changed? As Thomas Klein, MD, my practical recommendation is to bring the original transcript-identification report as well as the latest measurement. Our klinische Methodik und Einschränkungen explain why automated explanations should remain subordinate to the treating specialist's assessment.
Kantesti is an AI-powered blood test analysis tool that can help organize report terminology and dated laboratory trends, not diagnose leukemia or direct TKI changes. Molecular reports contain particularly sensitive information, including diagnosis-linked genetic findings. Review our Datenschutz und Datenverarbeitung before sharing a report, and retain the full sensitivity statement rather than uploading only one cropped number.
One new positive result without severe symptoms usually calls for prompt specialist contact rather than an emergency visit solely because of the molecular finding. Fever of 38°C or higher during anticancer treatment, severe breathlessness, chest pain, confusion or significant bleeding needs urgent assessment according to your team's instructions. Our report-sharing privacy checklist can help prepare a document, but do not wait for an AI explanation when urgent symptoms are present.
Research publications and the evidence behind these thresholds
The BCR::ABL1 interpretation in this article is grounded in CML clinical recommendations, molecular laboratory guidance and treatment-discontinuation evidence. As of October 17, 2026, the specifically cited sources are the 2020 ELN recommendations, 2023 ELN laboratory recommendations and 2018 EURO-SKI report. The date does not imply a newly issued 2026 guideline.
The three external references below directly support different parts of this article. Hochhaus et al. (2020) support response milestones and discontinuation conditions; Cross et al. (2023) support transcript coverage, calibration and specimen-sensitive response reporting. Saussele et al. (2018) provide prospective treatment-free-remission outcomes, which should not be confused with an assay's analytical detection limit.
The two Kantesti DOI publications are related laboratory education resources, not evidence validating BCR::ABL1 thresholds or TKI discontinuation. Unser Publikation zur RDW-Interpretation addresses red-cell indices, while our Veröffentlichung zum Nierenfunktionsverhältnis addresses renal laboratory interpretation. Such supporting laboratory information may matter during care, but neither resource measures the fusion.
The DOI entries use title-first APA-style citations because author and publication-date metadata were not supplied for verification. ResearchGate and Academia.edu links are clearly identified as searches, not claims of verified hosted copies or peer review. Our medizinische Inhaltsstandards provide the editorial context; an individual treatment decision still needs the patient's hematologist and current local protocol.
Häufig gestellte Fragen
Bedeutet ein positiver BCR-ABL1-Test, dass ich Leukämie habe?
Ein eindeutig positives BCR::ABL1-Ergebnis in einer geeigneten diagnostischen Probe spricht stark für eine Fusionsleukämie, meist CML oder BCR::ABL1-positive ALL. An der Fusion sind typischerweise die Chromosomen 9 und 22 beteiligt, doch anhand des Ergebnisses allein lassen sich weder die Zelllinie noch die Krankheitsphase bestimmen. Hämatologen interpretieren es zusammen mit der Morphologie, der Immunphänotypisierung und den Chromosomenbefunden. Ein unerwartet niedriger positiver Wert muss möglicherweise bestätigt und unter Berücksichtigung der Einschränkungen des Assays überprüft werden, bevor eine Diagnose gestellt wird.
Can a negative BCR-ABL1 test rule out leukemia?
A negative BCR::ABL1 test does not rule out every leukemia because many leukemias do not contain this fusion. It also cannot reliably exclude a fusion transcript that the assay does not cover; approximately 2% of CML patients have atypical transcripts. Adequate specimen quality and appropriate assay coverage make a negative result more informative. Persistent abnormal findings may require additional molecular testing, flow cytometry or marrow assessment.
What does 0.1% BCR-ABL1 on the International Scale mean?
BCR::ABL1 of 0.1% IS meets the usual major molecular response threshold in appropriately monitored CML. It represents a three-log, or 1,000-fold, reduction from the standardized IS baseline of 100%, not necessarily from that patient's original diagnostic value. The percentage is a calibrated transcript ratio rather than the percentage of leukemic cells. Its clinical significance depends on treatment duration, previous results and assay suitability.
Is undetectable BCR-ABL1 the same as being cured?
Undetectable BCR::ABL1 is not proof of cure because residual fusion-positive cells may remain below the specimen's detection limit. An undetectable MR4.5 claim commonly requires at least 32,000 ABL1 reference transcripts in an appropriately validated assay. A specimen with less usable material may support a shallower response even though both reports say not detected. Continue treatment and monitoring unless your hematologist provides a supervised alternative plan.
Can BCR-ABL1 become positive again after being negative?
BCR::ABL1 can become detectable again after an undetectable result because of low-level sampling variation, reduced treatment exposure or increasing residual disease. A change from undetectable to 0.004% IS may still represent MR4 if the assay supports that classification. A rise above 0.1% IS means loss of major molecular response and has greater clinical significance. Contact your hematology team, especially during treatment-free remission, rather than changing medication yourself.
Can I stop my CML medication after a negative PCR test?
One negative BCR::ABL1 PCR test is not enough to stop CML medication safely. Selected patients may attempt treatment-free remission after prolonged TKI therapy, sustained deep molecular response and confirmation of other eligibility conditions. The 2020 ELN framework generally requires more than 5 years of treatment, or more than 4 years for a second-generation TKI, and more than 2 years of deep response. Frequent PCR monitoring and prompt restart if MMR is lost are central to a supervised stopping plan.
How often should BCR-ABL1 PCR be checked during treatment?
BCR::ABL1 PCR is commonly measured about every 3 months during CML treatment, with more frequent testing when response is uncertain, treatment changes or transcript levels rise. Monitoring during treatment-free remission is more intensive: the 2020 ELN framework recommends monthly tests for the first 6 months after stopping. It then recommends testing every 2 months during months 6–12 and every 3 months afterward. Your hematologist may adjust the schedule to current local guidance and your individual situation.
Hol dir heute eine KI-gestützte Bluttest-Analyse
Schließe dich über 2 Millionen Nutzern weltweit an, die Kantesti für sofortige, genaue Laboranalysen vertrauen. Lade deine Blutwerte Ergebnisse hoch und erhalte in Sekunden eine umfassende Interpretation von 15,000+-Biomarkern.
📚 Referenzierte Forschungsveröffentlichungen
Klein, T., Mitchell, S., & Weber, H. (2026). RDW-Bluttest: Vollständiger Leitfaden zu RDW-CV, MCV und MCHC. Kantesti KI-Medizinische Forschung.
Klein, T., Mitchell, S., & Weber, H. (2026). Harnstoff-Kreatinin-Quotient erklärt: Leitfaden für Nierenfunktionstests. Kantesti KI-Medizinische Forschung.
📖 Externe medizinische Referenzen
Cross NCP et al. (2023). European LeukemiaNet laboratory recommendations for the diagnosis and management of chronic myeloid leukemia. Leukämie.
Saussele S et al. (2018). Discontinuation of tyrosine kinase inhibitor therapy in chronic myeloid leukaemia (EURO-SKI): a prespecified interim analysis of a prospective, multicentre, non-randomised, trial.
⚕️ Medizinischer Haftungsausschluss
Dieser Artikel dient nur zu Bildungszwecken und stellt keine medizinische Beratung dar. Wende dich für Diagnose- und Behandlungsentscheidungen immer an eine qualifizierte medizinische Fachkraft.
E-E-A-T Vertrauenssignale
Erfahrung
Ärztlich geleitete klinische Überprüfung von Labor-Interpretations-Workflows.
Sachverstand
Fokus der Labormedizin darauf, wie Biomarker sich im klinischen Kontext verhalten.
Autorität
Verfasst von Dr. Thomas Klein, überprüft von Dr. Sarah Mitchell und Prof. Dr. Hans Weber.
Vertrauenswürdigkeit
Evidenzbasierte Interpretation mit klaren nächsten Schritten zur Reduzierung von Alarm.