
Compare dated results, not just red flags. A useful timeline separates possible health changes from differences caused by sampling, laboratory methods, and everyday biology.

Key takeaways
- Comparable results need the same biomarker, compatible units, collection dates, and laboratory context; 2 differently named tests may not measure the same thing.
- Unit conversion can prevent false alarms: glucose of 90 mg/dL is approximately 5.0 mmol/L, not a different glucose level.
- Reference intervals commonly contain the central 95% of a defined reference population; an isolated flag does not establish a diagnosis.
- Percentage change equals 100 × (new result − previous result) ÷ previous result; a rise from 100 to 110 is 10%, but its significance depends on the test.
- Biological variation means there is no universal 10% or 20% cutoff that makes every changing blood result clinically meaningful.
- Kidney monitoring requires context: KDIGO advises evaluation of an eGFR change greater than 20% on a subsequent test in people with CKD.
- HbA1c timing reflects roughly 2–3 months of glucose exposure, so closely spaced repeat tests may not fully show a treatment response.
- Urgent results override trend tracking: potassium of 6.5 mmol/L or higher generally requires urgent clinical assessment, even without symptoms.
What is AI-powered analysis of blood test trends?
To compare blood test trends, arrange results by collection date, match the exact test and units, retain each laboratory’s reference interval, and record testing conditions. Then assess the size, speed, and persistence of a change with your clinician—because 2 different values do not automatically mean your health has changed.

AI-powered blood test analysis organizes reported measurements and explains possible relationships; it does not perform the laboratory assay or establish a diagnosis. Kantesti is an AI blood test analyzer that helps readers compare dated results while keeping the original report available for verification; details about our organization explain who provides the service.
A personal baseline is a pattern observed under reasonably comparable conditions, not a single ideal number. For a hypothetical adult whose hemoglobin has usually been 145–150 g/L, a new result of 121 g/L may deserve review even when that laboratory does not flag it, because the change and the person’s symptoms matter together.
Collection date is more informative than the date a PDF was downloaded or an explanation was generated. A report released on 12 October might describe a sample collected on 9 October; confusing those dates can make a medication change appear to precede a result that actually came first.
Start with the clinical question: are you monitoring treatment, checking a previously abnormal result, or investigating a new symptom? Our first-test preparation guide helps make the next measurement a useful comparison point; 3 well-contextualized results can be more informative than 12 poorly documented ones.
How AI prepares reports for a reliable comparison
A reliable comparison begins with verified extraction: the test name, value, unit, collection date, reference interval, and laboratory must survive the move from report to timeline. Before interpreting 2 reports together, check whether both measurements describe the same analyte and specimen type.

PDF and photo extraction can misread decimal points, inequality signs, or adjacent columns. Kantesti accepts these report formats, but readers should check consequential values against the source—for example, 0.8 and 8.0 mg/dL are not a small discrepancy, and an unreadable entry should remain unresolved rather than guessed.
Use 1 row per measurement, with columns for collection date and time, test name, numerical result, unit, laboratory interval, and relevant circumstances. Keep the original value beside any converted value; a separate note for medication changes prevents an otherwise tidy spreadsheet from erasing the information needed to explain a trend.
Qualitative results cannot be treated as numerical concentrations. A positive antibody screen, an antibody index of 2.1, and a titer of 1:160 may describe different reporting systems; our qualitative and quantitative guide explains why graphing them on one continuous scale can be misleading.
The analysis workflow should move through data preparation, related-marker comparison, clinical context, and evidence checking, with uncertainty visible at each stage. Our AI technology guide explains the general process; for serial interpretation, inspect at least 1 source report rather than relying entirely on a generated summary.
Check units and reference ranges before comparing values
Units must match before a numerical trend is calculated, and the reference interval belonging to each result must remain visible. Glucose of 90 mg/dL and glucose of 5.0 mmol/L are approximately equivalent; treating them as an 85-point fall would create a completely false trend.

Mass-to-molar conversion depends on the substance being measured, so there is no single conversion factor for an entire chemistry panel. Creatinine in mg/dL is multiplied by approximately 88.4 to obtain µmol/L; glucose in mg/dL is divided by approximately 18 to obtain mmol/L, and mixing these factors produces unusable results.
Reference intervals commonly describe the central 95% of a selected reference population, whereas treatment targets and diagnostic cutoffs answer different questions. Our out-of-range explanation distinguishes these concepts; a cholesterol result can be within a printed interval yet above an individual’s clinician-selected treatment goal.
A flag can change without the concentration changing when a laboratory updates its interval, assay, or age category. Hypothetically, ALT of 38 U/L would be unflagged against an upper limit of 45 U/L but flagged against 35 U/L; record both intervals rather than concluding that the second report shows worsening liver health.
Some measurements cannot be converted reliably using a fixed factor, including lipoprotein(a) mass and particle concentration. Likewise, total and free hormone concentrations are different measurements, and 1 assay’s antibody index may not be comparable with another manufacturer’s index even when the test names look similar.
| Level | Range | What it means |
|---|---|---|
| Glucose units | 90 mg/dL ≈ 5.0 mmol/L | Equivalent concentrations; divide mg/dL by approximately 18. |
| Creatinine units | 1.0 mg/dL ≈ 88.4 µmol/L | Equivalent concentrations; multiply mg/dL by approximately 88.4. |
| Hemoglobin units | 13.5 g/dL = 135 g/L | Equivalent concentrations; multiply g/dL by 10. |
| HbA1c reporting systems | 7.0% ≈ 53 mmol/mol | NGSP and IFCC reporting require a standardized conversion, not a simple decimal shift. |
| Ferritin units | 30 ng/mL = 30 µg/L | These units are numerically equivalent; clinical interpretation still requires context. |
Which testing conditions can change your results?
Meals, hydration, exercise, collection time, illness, supplements, and medication timing can change laboratory values without representing the same underlying process. For a fair comparison of 2 routine tests, document these conditions and follow the ordering clinician’s preparation instructions rather than creating your own fasting or medication rules.

Fasting requirements are test-specific, and many routine tests do not require fasting. When an 8–12-hour fast is prescribed, plain water is generally allowed unless instructed otherwise; our supplement and fasting guide explains why a supplement’s laboratory interference can matter separately from whether it contains calories.
A single demanding workout can temporarily affect AST, CK, creatinine, and other measurements, with duration varying by exercise intensity and the person. For a hypothetical runner with AST of 89 U/L after a marathon, muscle contribution is one explanation to consider alongside ALT, CK, symptoms, and a clinician-directed repeat—not a reason to dismiss the result.
Biotin interference can produce falsely high or falsely low immunoassay results, depending on the assay design. A 5 mg hair-and-nail supplement deserves disclosure, but there is no universal safe withholding period; ask the laboratory or clinician because dose, kidney function, and the specific testing method influence the necessary interval.
Hemolysis can falsely raise potassium, LDH, and AST because cellular contents enter the specimen after collection. A potassium result of 5.8 mmol/L with a hemolysis warning needs prompt clinical interpretation rather than casual averaging with an earlier result; our hemolysis redraw guide explains source checks and repeat testing.
How much change exceeds normal biological variation?
There is no universal percentage change that makes every blood test trend meaningful. A reference change value combines laboratory measurement imprecision with within-person biological variation; a 10% shift can matter for one biomarker and fall within expected variation for another.

Within-person biological variation describes natural fluctuation around an individual’s relatively stable level, while analytical variation describes imprecision in measurement. Fraser and Harris described how these components inform serial interpretation in Critical Reviews in Clinical Laboratory Sciences (1989); a population interval covering approximately 95% of reference results does not supply an individual change threshold.
For a simplified two-sided 95% reference change value, RCV = 1.96 × √2 × √(CVa² + CVi²), with both coefficients expressed consistently. In a hypothetical assay with analytical variation of 3% and within-person variation of 5%, the RCV is approximately 16.2%; a rise from 100 to 110 is 10% and does not exceed that illustrative threshold.
RCV is not a diagnosis or treatment rule, and the simplified formula assumes conditions that may not fit skewed distributions or acute illness. Some biomarkers need asymmetric, log-transformed limits; our between-visit change guide explains why neither exceeding 16.2% in this example nor staying below it guarantees clinical significance.
Repeated testing increases opportunities for incidental flags, especially when many biomarkers are examined together. If 20 independent tests each used a central 95% interval, the chance of at least one outside result would be approximately 64%; real tests are often correlated, but the example shows why broad panels should not turn every isolated flag into a disease claim.
Read related biomarkers together before interpreting a trend
Related biomarkers help explain a change, but a pattern still needs clinical confirmation. Falling hemoglobin with falling ferritin raises a different question from falling hemoglobin with stable iron stores; 2 measurements moving together can strengthen a hypothesis without proving its cause.
Ferritin can rise during an inflammatory response, so a rising value does not always indicate improved iron stores. A hypothetical ferritin increase from 18 to 75 µg/L during an acute illness needs interpretation alongside CRP, transferrin saturation, and the CBC; our iron studies guide explains why serum iron alone is an unstable substitute.
HbA1c reflects approximately 2–3 months of glucose exposure, but altered red-cell survival can distort its relationship with glucose. The American Diabetes Association’s Standards of Care (2024) recommend investigating substantial discordance between glucose and HbA1c; an HbA1c rise from 5.8% to 6.3% during iron deficiency should not automatically be attributed entirely to deteriorating glucose control.
Fructosamine reflects a shorter period, roughly 2–3 weeks, but protein turnover and albumin abnormalities can affect it. Our alternative glucose-marker explanation describes why switching markers requires a clinician’s judgment rather than choosing whichever result looks reassuring; neither test should be treated as an interchangeable numerical continuation of the other.
Calculated results can change when their inputs or equations change, even if the underlying physiology is similar. An eGFR fall from 82 to 74 mL/min/1.73 m² should be reviewed with creatinine, hydration, medication changes, and the reporting equation; check whether the laboratory changed methods before interpreting a small step in the graph as a new kidney problem.
Seven practical ways AI can support serial blood test review
AI can support organization, pattern review, and communication, but it cannot promise early diagnosis or better outcomes simply by drawing a trend line. Its 7 practical benefits are most useful when source data are checked and the next clinical decision remains with a qualified healthcare professional.

Early attention and personalized context are different from early diagnosis. Kantesti is an AI blood test interpretation platform that can help organize serial measurements around a person’s documented baseline; a persistent 3-test decline can generate a useful review question without proving that an otherwise hidden disease has been detected.
Comprehensive monitoring, clearer explanations, and longitudinal tracking are organizational benefits rather than diagnostic guarantees. Linking a creatinine result to the date a medication started is more useful than describing a 12% rise as automatically harmful; our medication trend workflow illustrates the role of timed comparisons.
Evidence checking and appointment preparation complete the benefit list, provided that explanations show their limits. A citation to a guideline is not proof that an AI correctly applied it to 1 individual, and a visually persuasive chart cannot resolve missing symptoms, incomplete medication information, or a mismatched assay.
1. Earlier attention to persistent changes
A pattern across 3 comparable measurements can justify a focused discussion before a dramatic abnormality appears. This is a reason to review the trend, not evidence that AI detects every condition earlier than conventional care.
2. Personalized context without invented targets
Two people with the same hemoglobin of 125 g/L can have different baselines, symptoms, and clinical needs. Personalization should explain those differences without declaring a private optimal range that overrides accepted clinical standards.
3. Monitoring related markers together
A 2-marker comparison such as creatinine with potassium can be more decision-relevant than either result alone after certain medication changes. The relationship helps prioritize questions, while the medication-specific monitoring plan determines action.
4. Clearer patient understanding
Explaining that glucose of 108 mg/dL is approximately 6.0 mmol/L can remove confusion created by different reporting conventions. Understanding units is a practical benefit that does not depend on a diagnostic prediction.
5. Longitudinal tracking with event annotations
A timeline becomes more useful when 1 treatment start, illness, or hospitalization is attached to the correct collection date. Event notes can explain apparent changes that an unannotated graph would misrepresent.
6. Scientific explanations with visible uncertainty
A 10% change should be explained using the relevant biomarker’s evidence and clinical setting, not a universal significance rule. Good analysis distinguishes a guideline threshold from an illustrative calculation or an uncertain association.
7. More focused clinician communication
A 1-page summary can preserve the question, baseline, recent results, and major confounders. The clinician can then check the original reports and decide whether observation, repeat testing, or investigation is appropriate.
Where blood test trends help screening and chronic care
Serial results are useful when they support an established screening or monitoring decision, particularly in diabetes, kidney disease, and treatment follow-up. Comparing 2 reports does not itself demonstrate that AI has saved a life; clinical benefit depends on appropriate testing, correct interpretation, and effective follow-up.
Preventive testing should follow age, symptoms, and risk, rather than an automatic schedule of increasingly broad panels. The ADA Standards of Care (2024) recommend repeating normal diabetes screening at least every 3 years, with earlier testing when risk changes; this is not a rule that every person needs all blood biomarkers checked at that interval.
Chronic kidney disease requires chronicity, not simply one low estimated filtration result. KDIGO’s 2024 guideline defines CKD through kidney abnormalities present for at least 3 months; an isolated eGFR of 58 mL/min/1.73 m² needs evaluation and context rather than an immediate conclusion that the person has established chronic disease.
For people with known CKD, KDIGO (2024) states that an eGFR change greater than 20% on a subsequent test exceeds expected variability and warrants evaluation. The guideline also identifies a reduction greater than 30% after starting a hemodynamically active therapy as a reason for evaluation; our SGLT2-related eGFR guide explains why an early dip is not automatically treatment failure.
Monitoring intervals must match the intervention, not the app’s processing speed. Lipids are often rechecked 4–12 weeks after starting or changing lipid-lowering treatment, whereas some kidney or electrolyte checks are needed much sooner; the prescribing clinician determines the timetable, and a trend tool should preserve that plan rather than replace it.
How athletes, older adults, and nutrient follow-up differ
Training, aging, and nutrient treatment change the context of serial measurements, so the same numerical movement can mean different things in different people. A ferritin increase of 20 µg/L after treatment is not interpreted the same way as an increase after a demanding race or during illness.

Athletic monitoring requires training notes, especially when interpreting iron status, muscle-associated enzymes, and creatinine. A ferritin of 18 µg/L in an endurance athlete deserves assessment of intake, losses, and other iron measurements—not an automatic supplement dose; our athlete ferritin discussion explains why training-phase comparisons can be deceptive.
Older adults need medication and muscle-mass context, because creatinine production can fall as muscle mass declines. A creatinine of 0.7 mg/dL is not proof of excellent filtration in a frail individual; clinicians may consider cystatin C or combined estimation when creatinine-based eGFR is less reliable and a decision depends on kidney function.
Iron treatment can temporarily increase RDW as newer cells coexist with an older, smaller-cell population. In a hypothetical follow-up after 3 weeks, rising hemoglobin with rising RDW may be compatible with recovery; our RDW after iron treatment guide explains why direction alone does not tell you whether every CBC component is improving.
Nutrient optimization should target an identified need, not a progressively higher serum number. A vitamin B12 rise from 180 to 900 pg/mL after supplementation confirms increased measured concentration but does not, by itself, prove symptom resolution or explain the original deficiency; document dose, route, timing, and the clinical reason for treatment.
Build a clinician-ready timeline and know when not to wait
A clinician-ready summary shows the baseline, recent values, relevant events, symptoms, and one clear question. Keep it to approximately 1 page when possible, but never let organizing a trend delay assessment of a critical laboratory result or a new emergency symptom.

Separate observation from interpretation when writing your summary. For example: creatinine rose from 0.9 to 1.2 mg/dL over 2 weeks after a medication change is an observation; the medication damaged my kidneys is an unconfirmed explanation, and the clinician needs hydration status, other drugs, symptoms, and repeat results to assess it.
A safe review workflow keeps the original reports accessible and shares only the information needed for care. Kantesti’s explanations can help formulate questions, but our secure result-sharing guide emphasizes consent and source access; bring at least the 2 reports supporting the change rather than a screenshot of the graph alone.
Potassium of 6.5 mmol/L or higher generally requires urgent clinical assessment, even if the person feels well. Hemolysis can cause a false elevation, but that possibility does not make it safe to wait for a routine appointment; seek immediate clinical advice, and use emergency services for palpitations, collapse, severe weakness, or other acute symptoms.
A rapid creatinine rise needs timely review, not a long-term wellness interpretation. An increase of at least 0.3 mg/dL within 48 hours, or to at least 1.5 times baseline within 7 days, meets standard laboratory criteria used for acute kidney injury assessment; reduced urine output, breathlessness, or significant illness increases urgency.
What user feedback can—and cannot—tell you about AI
User satisfaction is not evidence of diagnostic accuracy, and this guide does not present invented testimonials or patient outcomes. Judge an AI explanation by whether you can verify the original value, understand uncertainty, and identify an appropriate next step after comparing 2 or more reports.

A useful evaluation checks concrete tasks, not just whether the wording feels reassuring. Ask whether the tool preserved 1 decimal point correctly, retained a less-than sign, distinguished total from free measurements, and avoided diagnosing a condition from an isolated flag; these checks are more informative than a vague claim that users love the analysis.
Before uploading, review identifiers and consent, especially when reports belong to a family member. Our pre-upload privacy checklist covers practical precautions; a report can contain several identifiers beyond the patient’s name, including date of birth, address, accession number, and embedded document metadata.
Kantesti uses privacy-focused, GDPR-aligned data handling, but readers should review the actual policy rather than interpret that description as a guarantee of zero risk. Our privacy and data information explains the service’s approach; check retention, deletion, permitted processing, and sharing before uploading even 1 sensitive report.
Family trends require separate records and authorization, not a combined graph of relatives’ measurements. Comparing a parent’s LDL with a child’s LDL is not longitudinal tracking of 1 person, and sharing a relative’s health information should follow appropriate consent or legal authority rather than assuming a family relationship provides permission.
What better AI trend analysis should do next
Better trend analysis should make provenance, comparability, and uncertainty more visible, rather than promise more diagnoses from the same data. A useful future system would identify why 2 results may not be comparable before assigning clinical meaning to the line connecting them.
Method-aware comparison could help detect when a new assay or eGFR equation creates an artificial step in a timeline. An improvement worth seeking is an explicit warning that 1 result came from a different method, with the source of that information shown; without laboratory metadata, the system should admit that comparability is uncertain.
Uncertainty-aware displays could distinguish missing results, measurements below detection limits, and noncomparable tests without manufacturing values. A result reported as less than 3 should not become an exact value of 3 merely to complete a graph; the threshold and uncertainty should remain visible in both the explanation and exported timeline.
Kantesti is an AI-powered blood test analysis tool whose serial explanations should be judged by source fidelity and decision usefulness, not by how many patterns are described. Our AI source-checking guide helps readers inspect this distinction; discovering 10 correlations is not equivalent to establishing 10 clinically actionable findings.
Outcome evidence should test actual care decisions, including unnecessary repeat testing and false reassurance. A controlled study would need prespecified endpoints and comparison groups; a 60-second processing time measures workflow speed, not fewer complications, better diagnosis, or improved survival, and prospective evidence is needed before making those claims.
Frequently asked questions about AI and repeat blood tests
AI accuracy, repeat-testing frequency, and clinical safety are separate questions, and none has one universal percentage or schedule. For 2 serial reports, first confirm extraction and comparability; then use the clinician’s monitoring plan to decide whether the observed change requires action.
Extraction accuracy is not diagnostic accuracy, and a benchmark should state exactly what was tested. Kantesti’s validation and clinical standards provide the appropriate place to inspect methodology; performance on 1 dataset cannot establish a universal success rate across every laboratory, condition, language, and patient population.
Supported report content and clinical appropriateness are different, even when a tool can read a CBC, chemistry panel, lipid panel, or hormone result. A single explanation cannot safely ignore pregnancy, pediatric age ranges, transplant treatment, or symptoms; for example, 1 adult reference interval should not be applied automatically to a child’s result.
Repeat intervals depend on the marker and reason for testing, not how often a person wants a new graph. TSH is often checked around 6 weeks after a levothyroxine dose change because equilibration takes time; our thyroid testing schedule explains circumstances that can justify different timing.
The best next question is specific enough to guide care, rather than asking whether all results are good or bad. For a hypothetical 15% creatinine rise, ask whether the timing, medication change, hydration, and potassium result justify an earlier repeat; the answer may differ from what is appropriate for a 15% ferritin rise.
Conclusion: Your review plan and research publications
Use blood test trends to prepare a better clinical review, not to diagnose yourself. Before drawing a conclusion from 2 changing values, verify the source, units, laboratory method, testing conditions, and relevant symptoms; then agree on whether observation, repeat testing, or investigation is appropriate.
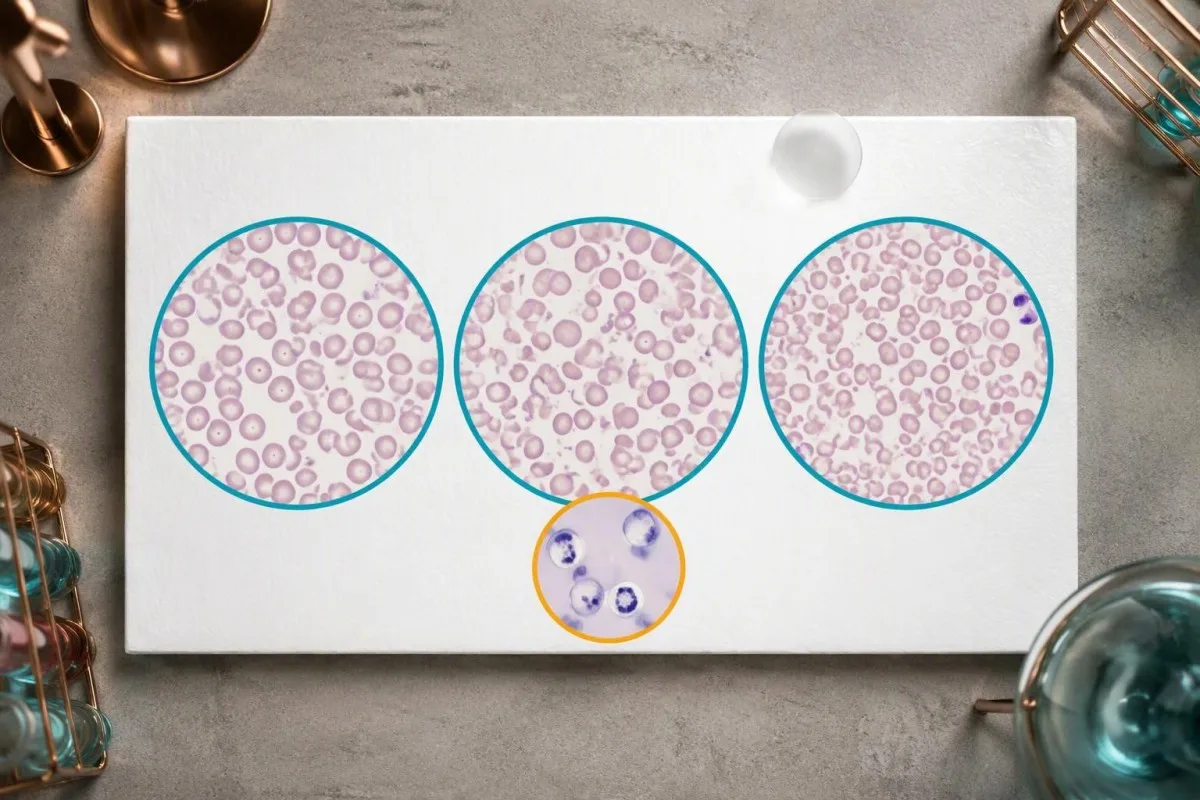
A practical review has 3 outputs: a verified timeline, a list of plausible confounders, and a clinician-agreed next step. Keep absolute values as well as percentage changes, because an improvement from a very abnormal result may still leave a problem requiring treatment or further investigation.
Responsibly used AI preserves uncertainty and human oversight, especially when results conflict or important history is missing. Our responsible AI principles explain these limits; if 1 result is critical or symptoms suggest an emergency, seek care rather than waiting for another upload or a more reassuring explanation.
Protein measurements add context but are not interchangeable trend markers: albumin, globulins, and the A/G ratio answer different questions. Our serum protein interpretation guide supports this distinction; a change in albumin from 40 to 32 g/L needs assessment of fluid status, protein loss, synthesis, and illness rather than a nutrition diagnosis alone.
The 2 Zenodo publications listed below are educational resources, not clinical trials proving the effectiveness of AI trend analysis. The serum-protein guide and complement/ANA guide provide related biomarker context; serial C3 or C4 values may be relevant in selected conditions, but repeating ANA titers alone generally does not provide a reliable disease-activity score.
Research publication context
The 2 DOI-linked guides should be read alongside the external clinical references, not instead of them. A repository DOI identifies a publication record; it does not by itself establish peer review, independent validation, diagnostic accuracy, or evidence of improved patient outcomes.
Frequently asked questions
How do I compare blood test results from different dates?
Compare the exact same biomarker using collection dates, compatible units, and the reference interval printed on each report. Record medication changes, illness, exercise, fasting, and laboratory differences before calculating a percentage change. For example, glucose of 90 mg/dL is approximately 5.0 mmol/L, so those values do not represent a meaningful fall. Ask your clinician whether the change is large enough, persistent enough, or symptom-associated enough to need further assessment.
How much change between blood tests is normal?
There is no universal normal percentage change for all blood tests because biological variation and assay imprecision differ by biomarker. A reference change value can help estimate whether a difference exceeds expected variation under appropriate conditions. In a hypothetical assay with analytical variation of 3% and within-person variation of 5%, a simplified two-sided 95% reference change value is approximately 16.2%. Exceeding that example threshold does not establish a diagnosis, and a smaller change can still matter in an urgent clinical setting.
Is AI blood test analysis accurate, and can it replace my doctor?
AI blood test analysis can help organize measurements and explain possible patterns, but its accuracy depends on source extraction, clinical context, and the specific task being evaluated. A single accuracy percentage cannot describe every biomarker, laboratory, or clinical decision. For example, reading 1 decimal point correctly is a different task from determining why a creatinine result changed. AI does not replace the clinician who considers symptoms, examines you, confirms findings, and selects treatment.
Can I compare results from two different laboratories?
Results from 2 laboratories may be comparable when they measure the same analyte with compatible units and sufficiently comparable methods. Keep both laboratories’ reference intervals, because a changed flag can result from a different interval rather than a changed concentration. Creatinine of 1.0 mg/dL is approximately 88.4 µmol/L, but unit conversion alone does not resolve every method difference. Antibody indices, some hormone assays, and lipoprotein(a) reporting require particular caution.
How often should I repeat blood tests to track a trend?
Repeat testing should follow the clinical question and the time needed for the biomarker to respond. HbA1c reflects roughly 2–3 months of glucose exposure, whereas some medication-related electrolyte checks are needed within days or weeks. TSH is often rechecked around 6 weeks after a levothyroxine dose change, although individual circumstances can alter the schedule. More frequent testing is not automatically safer and can create incidental findings or unnecessary treatment changes.
How can I protect my health data before uploading laboratory reports?
Review the service’s privacy policy, retention rules, deletion options, and processing permissions before uploading a laboratory report. Check at least the name, date of birth, address, and accession information, because identifiers can appear in several places within 1 PDF. Obtain appropriate consent or legal authority before uploading another person’s results. Removing visible identifiers can reduce exposure, but it does not guarantee complete anonymity or zero security risk.
Which changing blood test results should not wait for routine review?
A laboratory result marked critical or a result accompanied by severe new symptoms should receive prompt clinical assessment rather than routine trend tracking. Potassium of 6.5 mmol/L or higher generally requires urgent assessment, even when the person feels well. A creatinine increase of at least 0.3 mg/dL within 48 hours is another finding that warrants timely evaluation. Hemolysis or other sampling problems may explain an apparent abnormality, but a possible artifact is not a reason to delay clinical advice.
Get your blood test results explained
Upload your lab report and Kantesti's AI explains each biomarker in plain language within seconds. Used by more than 2 million people worldwide.
References
- Klein, T., Mitchell, S., & Weber, H. (2025). Serum Proteins Guide: Globulins, Albumin & A/G Ratio Blood Test. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2025). C3 C4 Complement Blood Test & ANA Titer Guide. Kantesti AI Medical Research. DOI
- Fraser CG, Harris EK. (1989). Generation and application of data on biological variation in clinical chemistry. Critical Reviews in Clinical Laboratory Sciences.
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group (2024). KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney International. DOI
- American Diabetes Association Professional Practice Committee (2024). 2. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes—2024. Diabetes Care. DOI
- 2M+Tests analysed
- 127+Countries
- 100+Languages
About the medical team


E-E-A-T Trust Signals
Experience
Physician-led clinical review of lab interpretation workflows.
Expertise
Laboratory medicine focus on how biomarkers behave in clinical context.
Authoritativeness
Medically reviewed by Dr. Thomas Klein, with contributions from Dr. Sarah Mitchell and Prof. Dr. Hans Weber.
Trustworthiness
Evidence-based interpretation with clear follow-up pathways to reduce alarm.




Medical disclaimer
This article is for educational purposes only and does not constitute medical advice. Always consult a qualified healthcare provider for diagnosis and treatment decisions.
Published · Updated · Contact the editorial team
Published by Kantesti Ltd, registered in England & Wales, company no. 17090423, London, United Kingdom.
