Genetic testing can confirm molecularly defined EDS subtypes, including classical and vascular EDS, but cannot routinely confirm hypermobile EDS. A negative panel and an uncertain variant answer different questions.

Viktiga slutsatser
- Detectable types: The 2017 EDS classification describes 13 subtypes; 12 have established molecular causes that appropriate genetic testing can investigate.
- Hypermobile EDS: No routinely accepted molecular test can confirm or exclude hEDS; diagnosis requires a clinical assessment.
- Classical EDS: COL5A1 and COL5A2 are the principal genes; selected COL1A1 variants can produce an overlapping classical phenotype.
- Vascular EDS: A pathogenic or likely pathogenic COL3A1 variant can confirm vEDS when interpreted with the clinical findings.
- Variant classification: Clinical laboratories use 5 categories, from pathogenic to benign; a VUS is not a positive diagnosis.
- Likely pathogenic: The ACMG/AMP framework uses greater than 90% certainty for this classification, not a 90% prediction of symptom severity.
- Recessive EDS: Confirmation usually requires 2 disease-causing variants affecting opposite copies of the relevant gene.
- Family risk: Many dominant EDS subtypes have a 50% transmission probability per pregnancy; recessive risks depend on both parents' results.
Which EDS types can a genetic test confirm?
Ehlers-Danlos genetic testing can confirm molecularly defined subtypes, but not routinely hypermobile EDS. The 2017 classification identifies 13 EDS subtypes, with established genetic causes for 12; confirmation requires an appropriately classified variant, the correct inheritance pattern, and compatible clinical findings.

A genetic test for Ehlers-Danlos syndrome examines DNA, not the amount of collagen circulating in your blood. Classical, vascular, kyphoscoliotic, and several rarer EDS forms can be investigated this way, but a panel containing 20 or 40 genes does not automatically cover every relevant variant type; the laboratory's methods matter as much as its gene list.
The international classification separates recognizable clinical patterns from their molecular causes (Malfait et al., 2017). Its 12 molecularly defined categories do not imply a universal 100% detection rate: a laboratory may omit a gene, miss a technically difficult region, or identify a change that cannot yet be classified confidently; our explanation of genetic result categories explores the same distinction in another inherited condition.
Kantesti is an AI blood test analyzer that helps explain routine laboratory findings, not a substitute for EDS molecular diagnosis. As an organization, Kantesti Ltd's clinical scope distinguishes educational interpretation from specialist assessment: neither 1 normal blood panel nor an AI-generated explanation can establish whether someone has an inherited connective-tissue disorder.
Which genes confirm classical and classical-like EDS?
Classical EDS usually involves COL5A1 or COL5A2, whereas TNXB-related classical-like EDS usually requires 2 disease-causing variants. Similar names do not mean identical inheritance, laboratory methods, or clinical findings; selected COL1A1 variants and AEBP1-related disease add further distinctions.
Classical EDS combines joint hypermobility with characteristic skin hyperextensibility and atrophic scarring, although expression varies within families. COL5A1 and COL5A2 encode components of type V collagen, and a heterozygous pathogenic or likely pathogenic variant can support confirmation; an arbitrary COL1A1 finding cannot, because different variants in that 1 gene cause substantially different connective-tissue phenotypes.
TNXB-related classical-like EDS often produces hyperextensibility and easy bruising without the typical atrophic scars of classical EDS. TNXB lies beside a highly similar pseudogene, TNXA, so the report should explain how the assay distinguishes them and detects deletions or rearrangements; some changes also involve neighboring CYP21A2, potentially linking connective-tissue findings with a separate endocrine condition.
AEBP1-related classical-like EDS, sometimes called classical-like EDS type 2, was characterized after the 2017 classification and is generally recessive. This is why a panel advertised as covering all EDS types needs its actual gene list checked; our guide to gene-specific family risk explains why a condition name alone cannot determine inheritance or the meaning of a negative result.
Can genetic testing confirm vascular EDS?
Vascular EDS is usually confirmed by a pathogenic or likely pathogenic COL3A1 variant. COL3A1 encodes type III collagen, and the combination of molecular evidence with a personal or family history of arterial or organ complications carries more diagnostic weight than a high joint-flexibility score.

Generalized joint hypermobility is not required for vascular EDS, so a Beighton score of 2/9 does not rule it out. Features prompting specialist consideration include arterial dissection or rupture, unexplained bowel perforation, spontaneous pneumothorax, and a compatible family history; isolated bruising or flexibility is much less specific and should not be treated as equivalent evidence.
A confirmed COL3A1 result can change vascular surveillance, procedural planning, pregnancy counseling, and testing for relatives. Different variant mechanisms can influence average patterns of disease, but they do not provide a reliable countdown to an individual's first complication; for a heterozygous dominant variant, the usual transmission probability is 50% per pregnancy, even when an affected parent has relatively few symptoms.
Sudden severe chest, abdominal, back, or head pain, collapse, or new neurological symptoms require emergency assessment—not waiting several weeks for a panel result. Call the local emergency number, such as 999 or 112 where applicable, and report known or suspected vascular EDS; our varningstecken på stroke som kräver akut vård explain why new speech, vision, balance, or limb changes need immediate action.
Which rarer EDS subtypes have established genetic causes?
The 9 other molecularly defined subtypes in the 2017 classification have distinct gene and inheritance requirements. A broad EDS panel can investigate them, but confirmation depends on variant mechanism—not simply finding any change in a gene associated with connective tissue.

Arthrochalasia EDS involves specific COL1A1 or COL1A2 changes affecting processing around exon 6, rather than every variant in either gene. Dermatosparaxis EDS involves biallelic ADAMTS2 variants, while cardiac-valvular EDS involves biallelic COL1A2 variants with an appropriate loss-of-function mechanism; these 3 diagnoses illustrate why gene name, variant location, and biological effect must be interpreted together.
Kyphoscoliotic EDS can involve 2 disease-causing variants in PLOD1 or FKBP14, with congenital hypotonia and early progressive spinal curvature providing useful clinical clues. Brittle cornea syndrome involves ZNF469 or PRDM5 and warrants careful ophthalmic assessment because corneal thinning changes management; a connective-tissue panel therefore needs to be matched to eye, skeletal, hearing, and muscle findings, not flexibility alone.
Spondylodysplastic EDS involves B4GALT7, B3GALT6, or SLC39A13, whereas musculocontractural EDS involves CHST14 or DSE; both groups usually follow recessive inheritance. Short stature, characteristic skeletal changes, or congenital contractures can direct testing more efficiently than adding dozens of unrelated genes, and 1 pathogenic variant in a recessive gene is ordinarily an incomplete explanation until the second allele is investigated.
Myopathic EDS involves COL12A1 and can follow dominant or recessive inheritance, while periodontal EDS involves heterozygous pathogenic variants in C1R or C1S. Severe early periodontal disease and lack of attached gingiva are particularly informative for the latter; unlike some metabolic conditions described in our enzyme and DNA results, most EDS diagnoses do not have a routine enzyme-screening shortcut.
Why does a negative panel not exclude hypermobile EDS?
A negative EDS panel does not exclude hypermobile EDS because hEDS lacks a routinely accepted diagnostic molecular test. The result means the laboratory did not identify reportable explanatory variants within its tested genes and methods—not that all inherited connective-tissue causes have been eliminated.

Most clinical EDS panels primarily investigate alternatives to hEDS, such as classical or vascular EDS and overlapping connective-tissue disorders. A hypothetical person with a Beighton score of 7/9, recurrent instability, and qualifying systemic findings could receive a negative 30-gene panel and still meet clinical hEDS criteria; the panel and the examination are answering different questions.
Research into hEDS genetics is active, but a candidate gene association is not the same as a validated test applicable to everyone with the condition. Before paying for a test described as hypermobile EDS genetic testing, ask for 3 things: the gene-disease evidence, the diagnostic validation, and the criteria used to decide whether a result confirms hEDS.
Neither orthostatic symptoms nor fatigue independently establishes hEDS, and neither symptom needs a positive genetic panel to deserve treatment. A person may need a separate standing or tilt-table assessment for suspected POTS; distinguishing 2 coexisting conditions avoids using one diagnosis as an explanation for every symptom or mistaking an association for proof of causation.
How is hEDS diagnosed when genetics cannot confirm it?
Hypermobile EDS is diagnosed through clinical criteria that assess generalized hypermobility, associated features, and exclusion of alternative explanations. Under the established 2017 adult criteria, the Beighton threshold is generally at least 5/9 through age 50 and at least 4/9 above age 50.
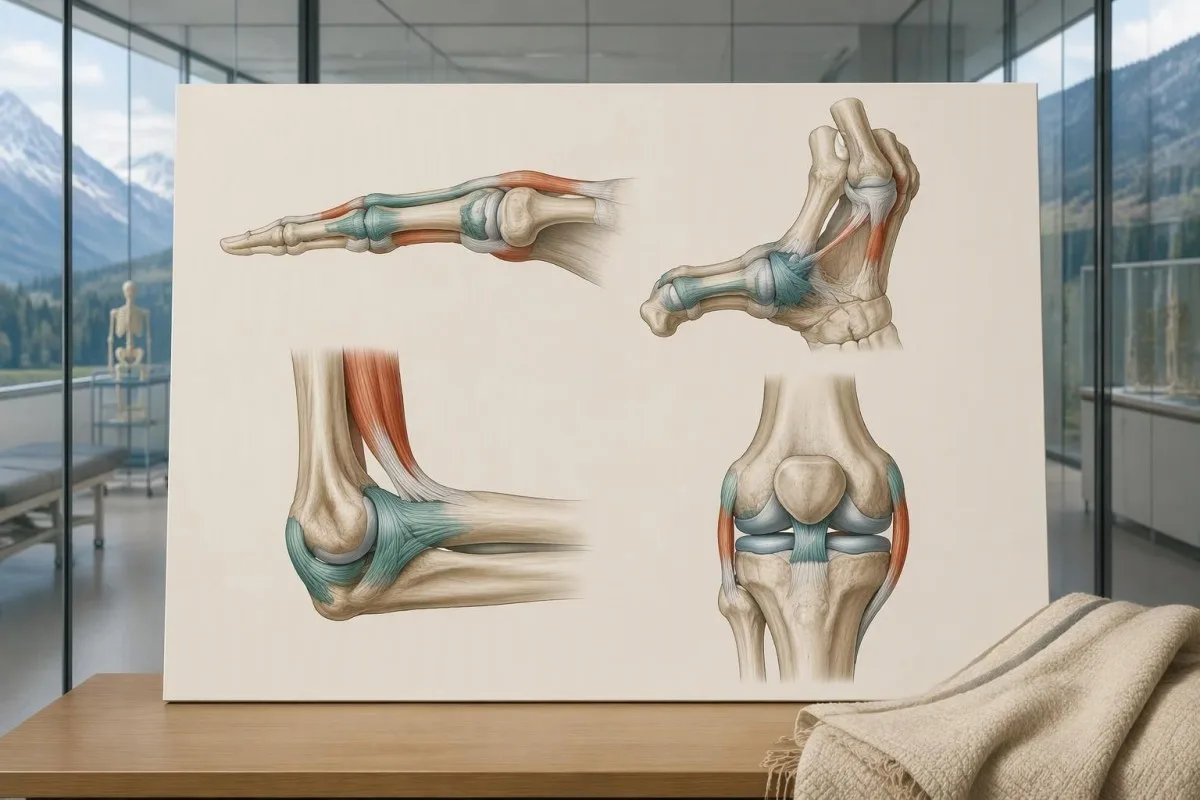
The 2017 criteria require all 3 major criteria, not just a high Beighton score. The second criterion requires at least 2 of 3 feature groups: systemic manifestations, a qualifying first-degree family history, or specified musculoskeletal complications; within the systemic group, at least 5 of 12 listed findings are required, so unrelated symptoms cannot simply be added together to reach a diagnosis.
Age and prior injury can alter measured flexibility, and historical hypermobility becomes relevant when someone is 1 point below the age-specific cutoff. The pediatric framework recommends a Beighton threshold of at least 6/9 for generalized joint hypermobility and reserves hEDS assessment for biological maturity (Tofts et al., 2023); childhood flexibility should not automatically become a lifelong adult diagnostic label.
Alternative explanations include other inherited connective-tissue disorders, neuromuscular conditions, and acquired rheumatologic disease; the exclusions depend on the person's findings rather than a mandatory universal blood-test package. An anti-RNP result, for example, belongs to an autoimmune connective-tissue assessment, not EDS DNA testing; clinicians may also diagnose a hypermobility spectrum disorder when symptoms are significant but all 3 hEDS criteria are not met.
Who needs an EDS panel rather than a targeted test?
An EDS panel is most useful when clinical findings suggest a molecularly defined subtype or several overlapping inherited disorders. When a family already has 1 known pathogenic variant, targeted testing for that exact variant is usually more informative than starting with a new broad panel.

Marked skin fragility, characteristic scars, congenital hip dislocation, progressive early scoliosis, unusual corneal findings, or arterial complications can justify clinical genetics assessment. A genetics service may select a broader heritable connective-tissue or aortopathy panel rather than an EDS-only panel when 2 or more diagnostic possibilities overlap; the aim is to investigate the phenotype, not to maximize the number of genes purchased.
Testing the most clearly affected relative first often makes later family testing easier to interpret. A negative targeted result for a known familial variant is fundamentally different from an unexplained negative panel in the first person tested; this distinction also appears in our explanation of informative negative genetic results, although the condition-specific screening recommendations are different.
Routine panel testing is not always helpful for isolated hypermobility without features of a molecularly defined disorder, because additional genes can generate additional VUS findings without clarifying the diagnosis. Some laboratories need specialized methods for particular variant classes, as illustrated by repeat-expansion testing methods; before ordering 1 panel, ask which plausible diagnoses its technical design can actually address.
What can an EDS panel miss technically?
An EDS panel can miss variants outside its coverage, certain deletions or rearrangements, and low-level mosaicism. Sequencing and deletion/duplication analysis are complementary methods, so a report stating that 99% of covered bases were read does not mean 99% of every possible EDS cause was excluded.

Small sequence changes are not the same as changes in gene copy number. Ask whether the assay includes deletion/duplication analysis, how poorly covered regions are completed, and whether complex loci such as TNXB receive validated additional testing; our copy-number interpretation guide shows why a reassuring number of copies can still leave unresolved questions in a different genetic setting.
Exome sequencing focuses mainly on protein-coding regions, while genome sequencing examines a broader DNA space; neither approach guarantees an explanation after 1 negative panel. Deep intronic variants, complex structural changes, mosaicism, and uncertain gene-disease relationships may require specialist analysis, and selected cases may benefit from RNA studies that investigate whether a suspected variant changes how a gene transcript is processed.
Kantesti is an AI blood test interpretation platform whose routine laboratory explanations do not validate an EDS panel's sequencing sensitivity. Our tekniska och kliniska standarder should not be interpreted as 100% accuracy for germline diagnosis; the molecular laboratory must provide its own assay validation, limitations, accredited reporting process, and variant-specific interpretation.
How do pathogenic variants differ from a VUS?
A pathogenic or likely pathogenic variant has enough evidence to support disease causation; a variant of uncertain significance does not. The ACMG/AMP framework uses 5 categories: pathogenic, likely pathogenic, uncertain significance, likely benign, and benign, with classification based on evidence rather than how unusual a DNA change looks.

Evidence can include population frequency, observations in affected families, segregation, well-validated functional studies, and the expected disease mechanism. A variant present in 1 person with hypermobility is not automatically causal, especially when that feature is common; Richards et al. (2015) specifically state that a VUS should not be used in clinical decision-making, preventing uncertain evidence from becoming a definitive diagnosis.
The ACMG/AMP definition of likely pathogenic corresponds to greater than 90% certainty that a variant is disease-causing. That percentage describes confidence in classification—not a 90% chance of arterial rupture, severe disability, or transmission—and even an established pathogenic variant must fit the gene, inheritance pattern, and clinical question before it can explain an individual's presentation.
A pathogenic classification also does not make every carrier's prognosis identical: penetrance and severity can vary with the gene, variant mechanism, and family context. Our explanation of variant effects and family risk illustrates this separation in another inherited disorder; for EDS, request the exact DNA and protein notation, laboratory classification, and report date rather than relying on a shortened portal label.
What should you do with an uncertain EDS variant?
An EDS VUS should trigger clarification, not an automatic EDS diagnosis or gene-specific treatment. The next steps are to review phenotype fit, check inheritance and assay limitations, and ask whether carefully selected family testing could provide evidence; testing 10 relatives without a clear question may add little.

Consider a clearly hypothetical adult whose panel finds 1 COL3A1 VUS and no pathogenic variants. The person does not have genetically confirmed vascular EDS on that basis, but a history of arterial dissection would still justify specialist evaluation; management follows the real clinical risk while the molecular uncertainty is investigated, rather than either ignoring the history or treating the VUS as proof.
For a recessive subtype, 2 variants must usually affect opposite gene copies, called being in trans, to explain the disorder. If both changes sit on the same copy, called being in cis, the other copy may remain functional; our discussion of recessive carrier result interpretation explains why parental testing can sometimes answer a specific phasing question rather than simply produce more results.
A VUS may later become benign, likely benign, likely pathogenic, or pathogenic as evidence changes, but there is no universal 6- or 12-month reclassification deadline. Ask who initiates reinterpretation, whether the laboratory contacts the ordering clinician, and how to update family findings; a new clinical event or informative relative's result can be more useful than repeatedly ordering the same unchanged panel.
What do positive and negative EDS panel results mean?
A positive EDS panel result can confirm a subtype only when classification, inheritance, and phenotype align. A negative result can lower the likelihood of adequately tested molecular diagnoses, but it neither confirms hEDS nor excludes it; 1 result must be interpreted against the reason testing was ordered.
A hypothetical heterozygous pathogenic COL5A1 finding in someone with characteristic scars and hyperextensible skin can support classical EDS. By contrast, 1 pathogenic ADAMTS2 variant in a person without a second explanatory allele usually indicates carrier status rather than confirmed dermatosparaxis EDS; a report can therefore contain a genuine pathogenic finding without that finding explaining the person's symptoms.
The meaning of a negative result changes with pretest probability. When the examination strongly suggests a rare molecular subtype, the next question is whether the assay covered the relevant gene and variant mechanisms; when findings are nonspecific, expanding from 30 to 300 genes may increase uncertain or incidental findings without making the answer more useful or making hEDS genetically testable.
Clinical genetics may recommend a targeted technical follow-up, a different diagnostic hypothesis, or later reanalysis rather than immediately repeating the same panel. The relationship between phenotype and molecular findings also matters in gene and biochemical confirmation, though EDS does not share that condition's biochemical tests; ask for a written explanation of what remains plausible after 1 negative result.
How do EDS results affect children and other relatives?
Family testing should follow the confirmed gene and inheritance pattern, not the broad EDS label. For many dominant subtypes, a heterozygous affected parent has a 50% transmission probability per pregnancy; when both parents carry a pathogenic variant for the same recessive subtype, the affected-child probability is usually 25%.

The standard recessive model gives a 25% chance of an affected child, a 50% chance of a carrier child, and a 25% chance of a child inheriting neither familial variant when both parents are carriers. Each pregnancy is a new event, not a running quota; partner testing must investigate the relevant gene sufficiently rather than checking only the variant carried by the first parent.
A negative family history does not exclude dominant EDS because a variant may arise de novo, relatives may have subtle findings, or family information may be incomplete. Testing children can be appropriate when a confirmed condition changes childhood care, particularly vascular EDS; this differs from some adult-onset predictive testing decisions, where timing and the child's future autonomy carry a different balance.
Hypermobile EDS can cluster in families, but no routine molecular result currently provides the same variant-specific cascade-testing pathway. Relatives should consent separately to testing and data sharing, and a family's 3 generations of history should distinguish documented diagnoses from suspected flexibility; our family consent and tracking guide explains why shared health information does not remove individual privacy or the need for personal assessment.
Can routine blood tests or AI interpretation diagnose EDS?
Routine blood tests and AI blood-test interpretation cannot diagnose EDS or classify a germline variant independently. A CBC, ferritin, thyroid panel, or coagulation screen may investigate symptoms and alternative explanations, but there is no routine collagen blood concentration with a diagnostic cutoff for the 13 EDS subtypes.

Kantesti is an AI-powered blood test analysis tool that can explain routine biomarker results alongside reported symptoms. For example, a hypothetical adult with ferritin of 9 ng/mL and hemoglobin of 13.0 g/dL may have depleted iron stores despite hemoglobin within their laboratory's reference interval; our guide to järnbrist före anemi explains why that finding deserves attention without becoming evidence for or against EDS.
Normal platelet counts, PT, and aPTT do not exclude connective-tissue fragility, and bruising can have more than 1 cause. Conversely, iron deficiency, thyroid dysfunction, or a bleeding disorder should not be dismissed simply because someone already has hEDS; our complete iron study interpretation addresses a treatable contributor to fatigue, not an inherited collagen diagnosis or a supplement-based cure.
An EDS genetic report contains sensitive information about both the individual and potentially their relatives, so it should not be treated as an ordinary screenshot for unrestricted sharing. Before sending even 1 report to an online service, check purpose, retention, deletion, and whether genetic-report analysis is supported; Kantesti AI's privacy information describes our data-handling approach, not authorization to replace a genetic counselor or molecular laboratory.
What should you bring to genetics, and which sources help?
Bring the complete genetic report, relevant medical records, and a structured family history to your genetics appointment. The 3 most useful questions are whether the result explains your phenotype, what the assay could have missed, and whether the finding changes your own or your relatives' care.
Record major complications with ages, documented diagnoses, and the exact relationship of affected relatives; a 3-generation pedigree can be more informative than an unverified statement that everyone is flexible. Include ophthalmology findings, relevant imaging, characteristic scarring, congenital orthopedic problems, and the full laboratory methods page, because a portal summary may omit gene coverage, deletion testing, or the distinction between a VUS and a pathogenic result.
Before leaving, ask who coordinates 1 next step and who will receive any amended report: the genetics service, the ordering clinician, or the molecular laboratory. Kantesti's standarder för medicinskt innehåll support clear separation of established evidence, hypothetical examples, and unresolved questions; this article's EDS recommendations draw on the international classification, ACMG/AMP interpretation guidance, and pediatric hypermobility framework cited below.
The 2 Zenodo publications listed in our research references cover urinalysis and iron studies, not EDS genetic-test validation. Our guide för tolkning av urinalys may help explain a separate urine report, but neither urine urobilinogen nor iron-binding capacity confirms an EDS subtype; these publications should not be read as evidence that our platform performs molecular EDS diagnosis.
Vanliga frågor
Kan ett genetiskt test diagnostisera Ehlers-Danlos syndrom?
A genetic test can confirm molecularly defined Ehlers-Danlos subtypes when it identifies an appropriately classified variant with the correct inheritance pattern and compatible clinical findings. The 2017 classification includes 13 subtypes, and 12 have established molecular causes that appropriate testing can investigate. Hypermobile EDS does not have a routinely accepted diagnostic molecular test. A panel's gene list, technical coverage, and variant interpretation determine what its result can establish.
Utesluter en negativ EDS-panel hypermobil EDS?
A negative EDS panel does not rule out hypermobile EDS because hEDS is diagnosed clinically rather than by a validated routine molecular test. A hypothetical negative 30-gene panel means no explanatory reportable variant was found within that assay's scope. The result can help evaluate other inherited disorders, but it cannot prove or disprove hEDS. The next step is a clinical assessment that considers hypermobility, associated features, and alternative diagnoses.
Betyder en COL3A1-variant att jag har vaskulärt EDS?
En COL3A1-variant stöder bekräftelse av vaskulärt EDS endast när den är patogen eller sannolikt patogen och tolkas tillsammans med de kliniska fynden. Kliniska laboratorier använder fem variantkategorier, och en COL3A1-variant av oklar betydelse innebär inte en bekräftad diagnos av vaskulärt EDS. Allvarliga, oförklarade komplikationer i artärer eller organ motiverar fortfarande specialistbedömning även när testresultaten är inkonklusiva. Plötslig, svår smärta, kollaps eller neurologiska symtom kräver akut vård i stället för att man väntar på omklassificering av varianten.
What does a VUS mean on an EDS genetic panel?
A variant of uncertain significance means available evidence cannot confidently establish whether that DNA change causes disease. The ACMG/AMP framework distinguishes VUS from likely pathogenic, which corresponds to greater than 90% certainty of disease causation. A VUS should not independently determine an EDS diagnosis, predictive testing, or gene-specific treatment. Clinical genetics may recommend targeted family studies or later reinterpretation while managing symptoms and risks on their own clinical merits.
Why were two variants found in an EDS gene?
Two variants may matter because several EDS subtypes follow recessive inheritance and usually require disease-causing changes in both gene copies. The laboratory must determine whether the 2 changes are pathogenic or likely pathogenic and whether they are in trans, affecting opposite copies. Two changes in cis, affecting the same copy, may not explain a recessive disorder. Finding one pathogenic variant and one VUS also does not automatically provide molecular confirmation.
Should my children be tested if I have EDS?
Children's testing depends on the confirmed subtype, whether a familial variant is known, and whether the result changes care during childhood. Many dominant EDS subtypes have a 50% transmission probability per pregnancy, making targeted testing useful when appropriate. When both parents carry variants for the same recessive subtype, the usual affected-child probability is 25% per pregnancy. Hypermobile EDS currently requires clinical evaluation rather than routine variant-specific family testing.
Can normal blood tests exclude Ehlers-Danlos syndrome?
Normal routine blood tests cannot exclude Ehlers-Danlos syndrome because standard panels do not measure the inherited structural changes responsible for EDS. A normal CBC, PT, or aPTT does not rule out connective-tissue fragility, and no routine collagen blood cutoff diagnoses the 13 classified subtypes. Blood tests can identify separate contributors to symptoms, such as iron deficiency or thyroid dysfunction. Molecularly defined EDS requires appropriate genetic interpretation, while hypermobile EDS requires clinical assessment.
Få dina blodprovsresultat förklarade
Ladda upp din laboratorierapport så förklarar Kantesti:s AI varje biomarkör på ett lättbegripligt språk inom några sekunder. Används av mer än 2 miljoner människor världen över.
Referenser
- Klein, T., Mitchell, S., & Weber, H. (2026). Urobilinogen i urintest: Komplett urinalysguide 2026. Kantesti AI Medicinsk forskning. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Guide till järnstatus: TIBC, järnmättnad och bindningskapacitet. Kantesti AI Medicinsk forskning. DOI
- Malfait F et al. (2017). The 2017 international classification of the Ehlers-Danlos syndromes. American Journal of Medical Genetics Part C: Seminars in Medical Genetics. DOI
- Richards S et al. (2015). Standarder och riktlinjer för tolkning av sekvensvarianter: en gemensam konsensusrekommendation från American College of Medical Genetics and Genomics och Association for Molecular Pathology. Genetics in Medicine. DOI PubMed
- Tofts LJ et al. (2023). Pediatric joint hypermobility: a diagnostic framework and narrative review. Orphanet Journal of Rare Diseases. DOI
- 2 miljoner+Analyserade tester
- 127+Länder
- 100+Språk
Om det medicinska teamet


E-E-A-T förtroendesignaler
Uppleva
Läkarledd klinisk granskning av arbetsflöden för laboratorietolkning.
Expertis
Laboratoriemedicinskt fokus på hur biomarkörer beter sig i kliniskt sammanhang.
Auktoritet
Medicinskt granskad av Dr. Thomas Klein, med bidrag från Dr. Sarah Mitchell och Prof. Dr. Hans Weber.
Trovärdighet
Evidensbaserad tolkning med tydliga uppföljningsspår för att minska larm.






Medicinsk friskrivning
Den här artikeln är endast avsedd för utbildningsändamål och utgör inte medicinsk rådgivning. Rådgör alltid med en behörig vårdgivare för beslut om diagnos och behandling.
Publicerad · Kontakta redaktionen
Publicerad av Kantesti Ltd, registrerat i England och Wales, företagsnr. 17090423, London, Storbritannien.
