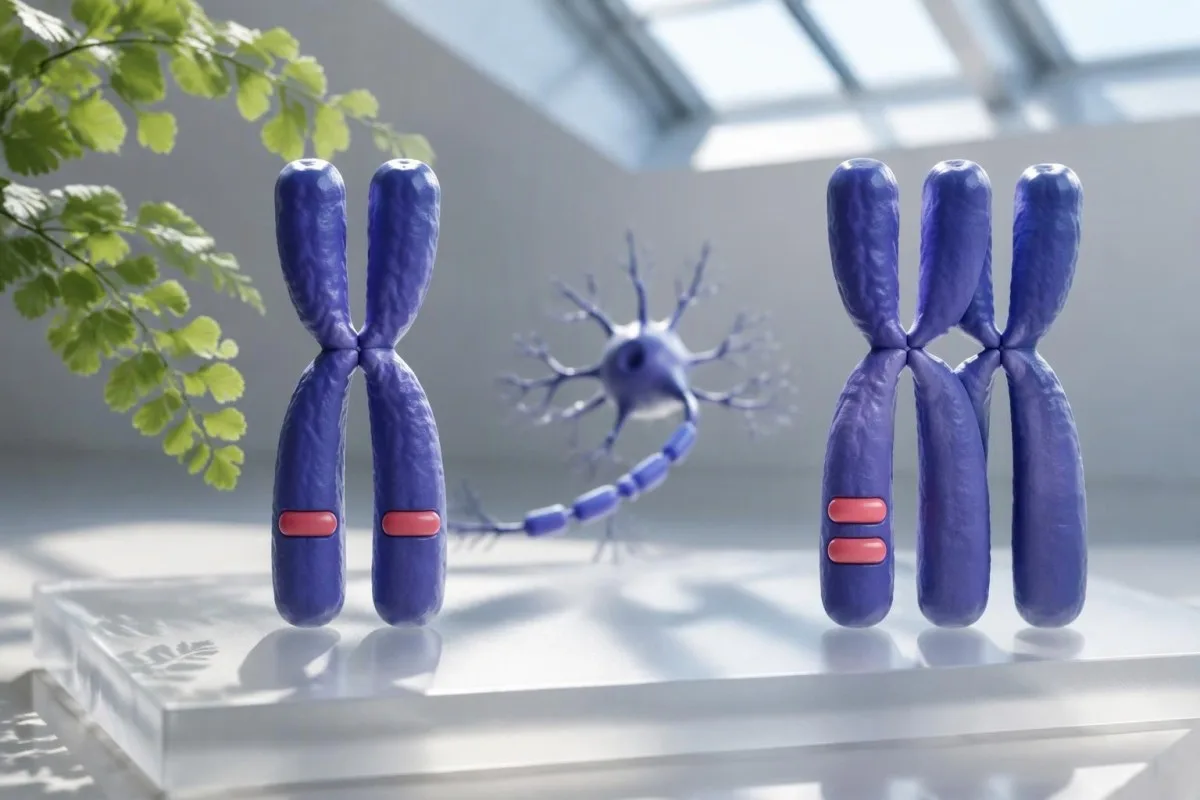
Two SMN1 copies usually mean a reduced chance of being a spinal muscular atrophy carrier—not zero risk. The remaining uncertainty depends on chromosome arrangement, linked variants, ancestry, and what the laboratory actually tested.

Idei principale
- Two SMN1 copies usually indicate reduced carrier risk, but copy-number testing cannot always distinguish a 1+1 arrangement from a silent-carrier 2+0 arrangement.
- Silent carrier means both SMN1 copies are on one chromosome 5, while the other chromosome has none; the person can pass on the chromosome without SMN1.
- Linked variants such as SMN1 c.*3+80T>G and c.*211_*212del can increase the estimated likelihood of a 2+0 arrangement, but they do not prove it.
- Residual risk varies by ancestry and assay: published European-ancestry estimates with two copies range from approximately 1:814 with linked variants absent to 1:12 with a linked variant present.
- Negative linked-variant testing lowers risk but cannot exclude every silent carrier or every disease-causing sequence variant within SMN1.
- Testarea partenerului is especially useful when one reproductive partner is a confirmed carrier, has increased silent-carrier risk, or has a relevant family history.
- Riscul de sarcină is approximately the first partner's carrier probability multiplied by the second partner's carrier probability multiplied by 1/4, under standard autosomal-recessive assumptions.
- Consiliere genetică helps distinguish a screening estimate from a confirmed genotype and can explain family testing, prenatal diagnosis, and reproductive options.
What do two SMN1 copies mean on SMA carrier screening?
Two SMN1 copies usually mean reduced SMA carrier risk, not a guarantee that you are not a carrier. Most people with this result have one copy on each chromosome 5, but some have both copies on one chromosome and none on the other—a 2+0 silent-carrier configuration.

SMN1 copy number is a DNA measurement, not a protein concentration or a routine blood-count result. A report stating “2 copies” usually describes the number of targeted SMN1 sequences detected; it does not necessarily establish that both copies are fully functional or located on separate chromosomes.
A reduced-risk result is different from a diagnostic result. Carrier screening estimates whether a generally unaffected person could pass on a disease-causing allele, whereas diagnosing SMA requires an appropriate clinical assessment and molecular investigation; the number 2 alone answers neither question completely.
The word “negative” can conceal different testing packages. One laboratory may report two copies without checking silent-carrier markers, while another adds linked-variant analysis and a residual-risk calculation; our explanation of rezultate calitative și cantitative helps distinguish the wording from the underlying measurement.
Kantesti is an AI blood test analyzer that explains laboratory terminology, but an SMN1 result is a specialized genetic test rather than an ordinary biomarker panel. Noastre prezentarea companiei explains our broader role; interpreting two copies for reproductive decisions still requires the original laboratory report and, when indicated, genetics expertise.
How can a person with two copies be an SMA silent carrier?
An SMA silent carrier has two SMN1 copies on one chromosome 5 and zero copies on the other: 2+0. Standard dosage testing can count the two copies without showing their chromosome assignment, making this arrangement look like the usual noncarrier 1+1 configuration.
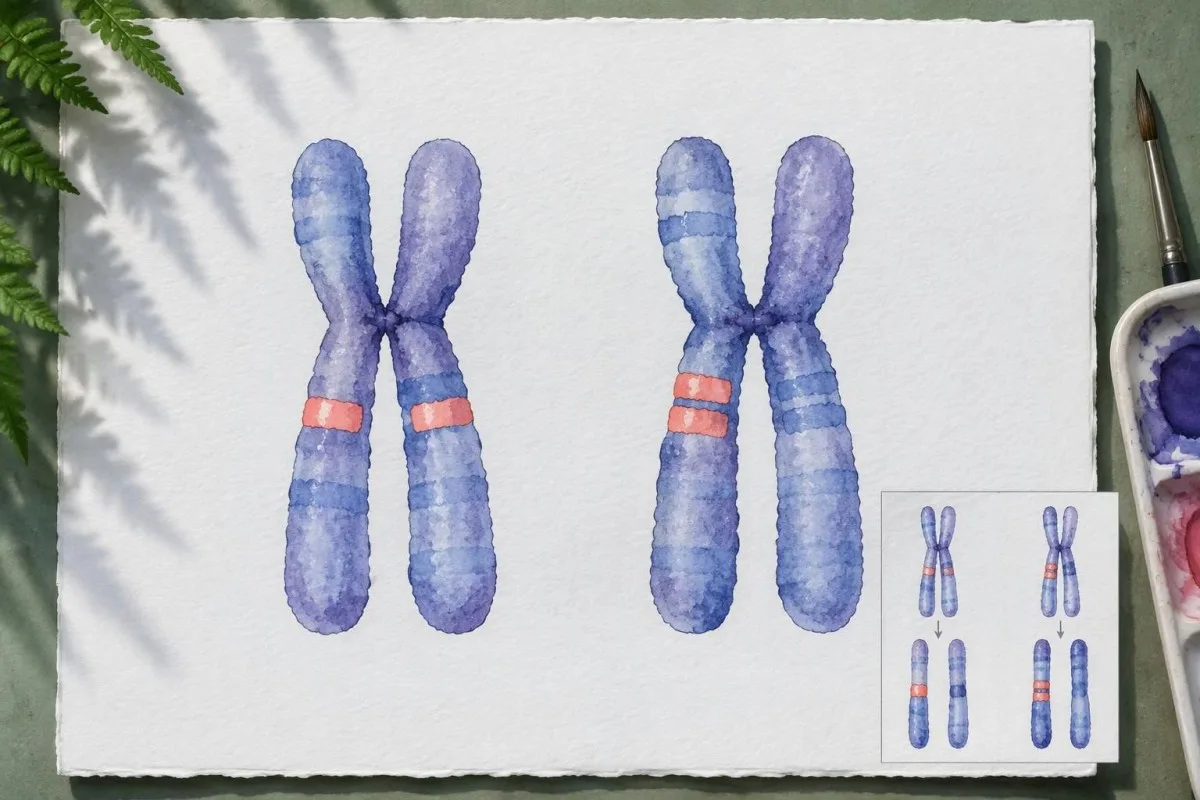
Chromosome arrangement is called phase. In a 1+1 arrangement, either chromosome passed to a child ordinarily contains an SMN1 copy; in a 2+0 arrangement, approximately half the person's eggs or sperm carry the chromosome with no SMN1, assuming standard segregation.
Silent does not mean early SMA or hidden symptoms. A 2+0 carrier generally has enough SMN1 function to remain unaffected; the clinical concern is reproductive transmission, not an expectation that the carrier will eventually develop the disease.
A clearly hypothetical example illustrates the counting problem. Person A has one SMN1 copy on each chromosome, while person B has two on the same chromosome; both receive a total-copy result of 2, yet only person B can ordinarily transmit a chromosome lacking SMN1.
Carrier-screening reports use different genetic measurements for different conditions. SMA testing emphasizes copy number and phase, while Fragile X screening results emphasize repeat size; a reassuring result for one condition cannot resolve the chromosome arrangement of another.
What does “SMN1 linked variant detected” actually mean?
“SMN1 linked variant detected” means the laboratory found a marker associated with SMN1 duplication on one chromosome. With two SMN1 copies, markers such as c.*3+80T>G sau c.*211_*212del can raise silent-carrier probability, but neither marker independently confirms a 2+0 genotype.

The commonly reported c.*3+80T>G marker may also appear under the older name g.27134T>G. These names can refer to the same linked marker using different sequence-reference conventions; ask the laboratory to confirm equivalence rather than assuming two differently named entries represent two separate findings.
A linked marker is not the same as a disease-causing SMN1 sequence variant. The asterisk in c.*3+80T>G places the change after the coding sequence; its screening value comes from association with duplication-bearing chromosomes, not from independently establishing loss of SMN1 function.
Marker performance depends on the population studied. Milligan et al. (2022), in Genes, recommend interpreting these variants alongside copy number and ancestry because a positive marker has substantially different predictive value across groups; two copies plus a positive marker should usually be described as increased carrier risk, not confirmed carrier status.
An absent marker does not prove a 1+1 arrangement. Some 2+0 chromosomes lack the tested marker, and some laboratories test only one of the two commonly discussed variants; the distinction between association and causation also matters when reading MEFV genetic findings.
What residual carrier risks are published for two SMN1 copies?
Residual carrier risk is the estimated chance of being an SMA carrier after a screening result. Milligan et al. (2022) summarize ancestry-dependent estimates for two SMN1 copies, with separate figures for copy-number-only testing and for linked variants reported absent or present; these are population estimates, not personal diagnoses.

For the review's European-ancestry category, two-copy residual risk is approximately 1:604 without marker information, 1:814 with markers absent, and 1:12 with a marker present. These correspond to about 0.17%, 0.12%, and 8.3%; the denominator shrinks when the estimated risk increases.
For the review's Black/African American category, the corresponding estimates are approximately 1:132, 1:375, and 1:39. The roughly 2.6% estimate associated with a positive marker is not interchangeable with the 8.3% European-category estimate, even though the laboratory wording may be identical.
For the review's broadly grouped Asian category, the estimates are approximately 1:719, 1:779, and 1:57; for its Hispanic category, they are approximately 1:641, 1:906, and 1:99. The categories combine heterogeneous populations, and the figures should not override a laboratory's assay-specific assessment or a relevant family history.
At Kantesti, we explain 1:12 as an estimated probability, not as proof that a particular person has a 2+0 arrangement. These SMA figures also should not be transferred to APOL1 genetic risk results, where the relationship between genotype, ancestry, and clinical outcome is fundamentally different.
Why does ancestry change the residual-risk estimate?
Ancestry changes residual-risk estimates because SMN1 duplication arrangements and their linked markers occur at different frequencies across studied populations. Broad ancestry labels are imperfect statistical categories; someone with mixed, unknown, or poorly represented ancestry may not have one defensible residual-risk denominator for a two-copy result.

Ancestry is not something a clinician can reliably infer from appearance. Applying the 1:39 or 1:12 marker-positive estimate simply from skin tone would misuse the evidence; self-reported ancestry, family information, and the laboratory's population definitions are more appropriate starting points.
A hypothetical person with mixed ancestry may receive a range rather than a single number. If two applicable published categories give marker-positive risks of 1:12 and 1:99, averaging the denominators does not produce a validated personal estimate because the underlying haplotype frequencies are not averaged that way.
Related reproductive partners need additional caution. The standard calculation that multiplies two independent carrier probabilities can underestimate shared-family risk when partners are biologically related; even two apparently reassuring copy-count results deserve individualized review if the family contains a confirmed SMA diagnosis.
Population-associated genetics should be separated from social labels. Discuția noastră despre Duffy-null neutrophil counts illustrates another situation where a specific inherited feature explains more than a broad racial category; for SMA, identifying the actual 1+1 or 2+0 arrangement is more informative than guessing from identity.
What can the laboratory method miss?
SMA screening can miss silent carriers, some disease-causing SMN1 sequence variants, and unusual structural arrangements, depending on the assay. Two copies measured by dosage testing do not automatically mean that sequencing, linked-marker analysis, or chromosome phasing was performed; each capability must be confirmed separately.
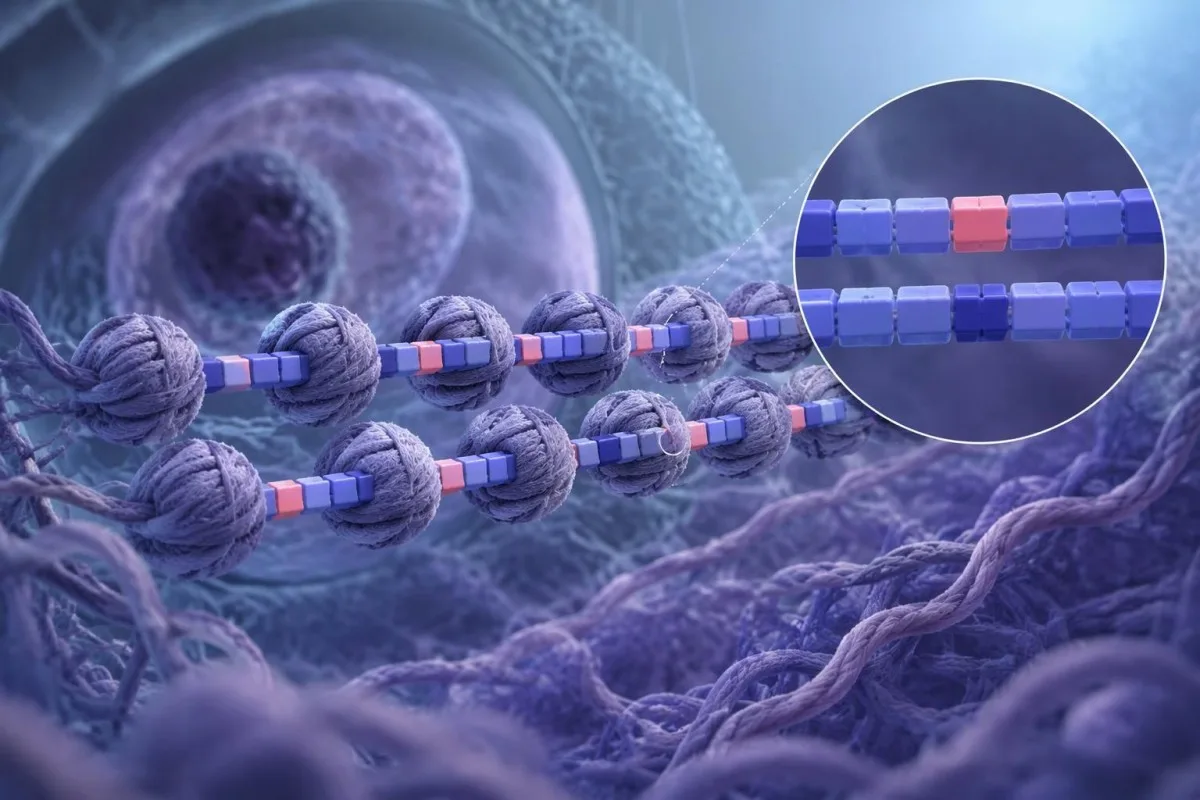
Many assays target SMN1 exon 7 because its deletion accounts for the large majority of SMA-associated genotypes. Other exons, complex rearrangements, or sequence variants may require additional methods; the fact that an assay detects two exon-7 copies does not establish complete coverage of both genes.
SMN1 and SMN2 are highly similar, which makes specialized assay design necessary. Laboratories may use quantitative PCR, digital PCR, MLPA, or validated sequencing-based approaches, but method names alone do not guarantee detection of a 2+0 arrangement or every clinically relevant sequence change.
Repeating an identical copy-number assay may reproduce the same uncertainty. If the first result is 2 copies without phase information, a second dosage result of 2 does not independently prove 1+1; the useful next question is whether a different analysis can resolve the specific blind spot.
Genetic tests should be judged by their intended measurement, not by whether they produce a precise-looking number. A repeat count in testarea genetică pentru boala Huntington answers a different question from SMN1 dosage, and even a highly accurate copy count can leave chromosome arrangement unresolved.
When do family history and SMN1 sequencing matter?
A confirmed SMA diagnosis in the family can justify genetics review even when screening reports two SMN1 copies and no linked variant. The most useful starting point is the affected relative's molecular report, because a family-specific deletion or sequence variant may require testing beyond routine carrier dosage.
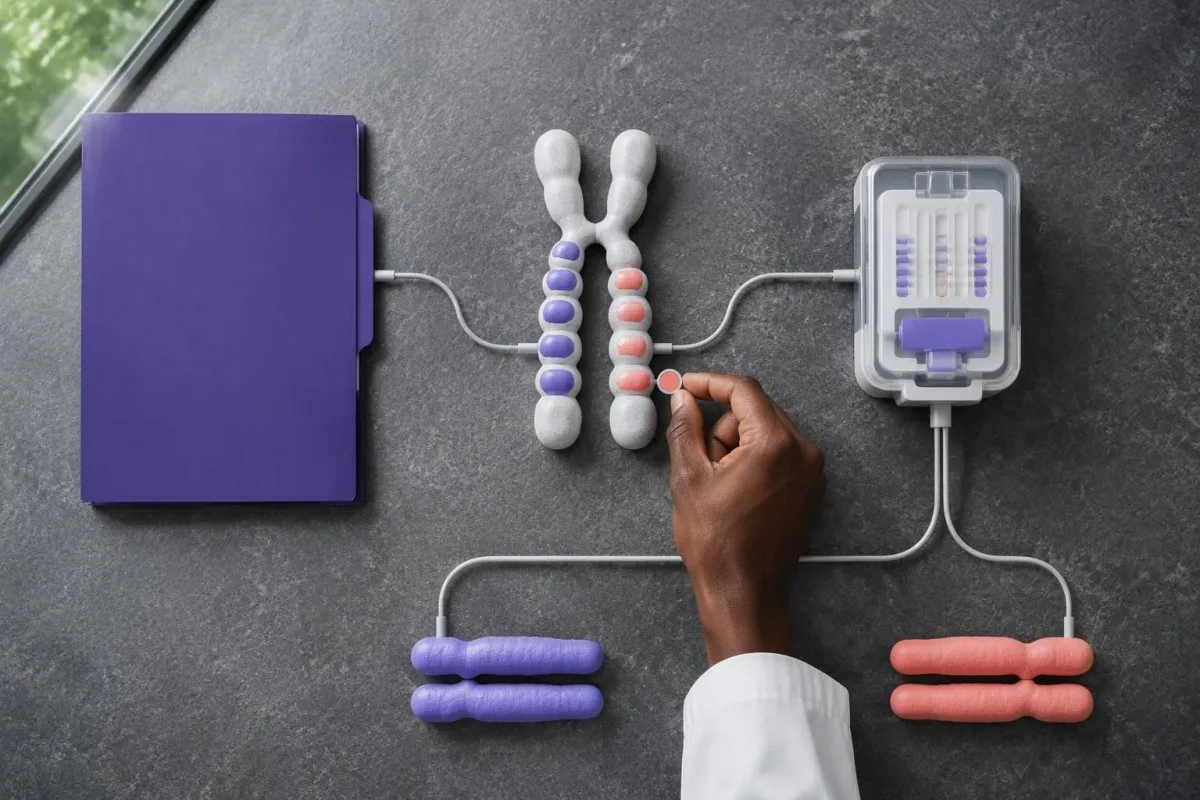
Approximately 2–5% of people with SMA have an SMN1 deletion on one chromosome and an intragenic pathogenic variant on the other, rather than the common biallelic exon-7 deletion pattern. This affected-person statistic explains a screening limitation; it is not the probability that someone with two copies is a carrier.
One disease-causing sequence variant can coexist with a total SMN1 copy count of 2. If one copy is functional and the other contains a pathogenic change, a person may be a carrier in a 1+1 arrangement rather than a silent 2+0 carrier; copy number alone cannot distinguish these mechanisms.
Testing an affected relative first can prevent unfocused follow-up. For example, if a hypothetical sibling's SMA report identifies a specific SMN1 sequence variant, targeted testing for that variant may be more informative than simply repeating a two-copy carrier screen.
Kantesti is an AI lab test interpretation service that helps explain report language, but it cannot sequence SMN1 or establish a 2+0 genotype from a document. Noastre validare clinică ale Kantesti should not be read as validation of genetic phasing; similarly, Fabry genetic interpretation depends on the exact inherited variant and condition-specific evidence.
When should a reproductive partner be tested?
Partner testing is particularly helpful when one person is a confirmed SMA carrier, has increased silent-carrier risk, or has a relevant family history. ACOG Committee Opinion No. 691 (2017) recommends offering SMA screening to people considering pregnancy or already pregnant and offering partner testing when carrier status is identified.

A two-copy, marker-positive result warrants a discussion, not an automatic assumption that both partners are carriers. Testing the reproductive partner can substantially clarify couple-level risk, especially if that partner has one SMN1 copy or a known pathogenic variant; counseling can proceed while testing is arranged.
Simultaneous screening can reduce delays during pregnancy. Gregg et al. (2021), in the ACMG practice resource, support an equitable offer of carrier screening and describe partner evaluation after an actionable finding; the appropriate test should match the implicated condition rather than relying on an unrelated panel's “negative” label.
A confirmed carrier's partner may need more than a basic copy count. The ACMG practice resource recommends full-gene analysis of the implicated gene for partner follow-up rather than a limited variant panel, while SMN1's technical complexity means sequencing, dosage, and silent-carrier analysis must be discussed with the laboratory.
Preconception testing offers more decision time than testing late in pregnancy. A couple planning conception in 3 months can ask about turnaround times and counseling access alongside other preparation, such as imunitatea la rubeolă înainte de concepție; immunity testing and SMA carrier screening answer separate questions.
How is the chance of an affected pregnancy calculated?
For standard autosomal-recessive SMA risk, multiply each reproductive partner's carrier probability by 1/4. Two confirmed carriers have an approximately 25% chance of an affected child in each pregnancy; when carrier status is uncertain, residual-risk estimates replace the confirmed-carrier probability of 1.

A hypothetical confirmed carrier and a partner with residual carrier risk of 1:814 have an estimated affected-pregnancy risk of 1:3,256. The calculation is 1 × 1/814 × 1/4, approximately 0.031%; this estimate inherits the assumptions and limitations of the partner's residual-risk figure.
A hypothetical confirmed carrier and a two-copy, marker-positive partner with estimated carrier risk of 1:12 have an affected-pregnancy estimate of 1:48. That is approximately 2.1%, not 25%, because the second person's carrier status remains uncertain; genetic counseling can discuss whether further testing might resolve that uncertainty.
Two uncertain results can still produce a useful estimate when the probabilities are appropriate and independent. Hypothetical risks of 1:12 and 1:39 yield 1:1,872 after multiplying by 1/4, approximately 0.053%; relatedness, a shared family variant, or unsuitable ancestry categories can make this simple calculation unreliable.
Kantesti's medical content team uses these calculations as educational examples, not individualized reproductive predictions. Inheritance arithmetic also appears in interpretare a screeningului hemoglobinei, but the relevant alleles and disease combinations differ; a healthy previous child does not change the 25% probability when both parents are confirmed SMA carriers.
What options help if a pregnancy may be at increased risk?
Genetic counseling can explain prenatal diagnosis, IVF with preimplantation genetic testing for monogenic disease, donor gametes, and conception without additional genetic testing. Chorionic villus sampling or amniocentesis can provide fetal material for targeted SMA diagnosis when the laboratory has an appropriate testing strategy; carrier screening alone does not diagnose the fetus.

Chorionic villus sampling is generally performed around 10–13 weeks, while amniocentesis is generally performed from 15 weeks onward. Local protocols and individual circumstances determine timing, procedural counseling, and which molecular analysis is suitable; arrange genetics input early rather than waiting for the next routine appointment.
Routine noninvasive prenatal screening does not rule out SMA. Common cell-free DNA screening targets selected chromosome conditions, and commercial single-gene screening is not equivalent to diagnostic testing; a low-risk result on a standard prenatal screen cannot resolve a parental 2+0 possibility.
Preimplantation genetic testing for monogenic disease requires a condition-specific laboratory plan. A hypothetical couple with one confirmed carrier and one unresolved two-copy result may need additional family or phase information before an IVF laboratory can design reliable testing; PGT-M is not simply a generic “SMA-negative embryo” checkbox.
Parental genetic results should remain distinct from other pregnancy laboratory findings. A screening pozitiv pentru anticorpi în sarcină concerns a different mechanism from recessive SMN1 inheritance; discussing both reports together can coordinate care, but one does not confirm or cancel the other.
Do SMN2 copies or normal health rule out SMA carrier status?
SMN2 copy number does not rule out SMA carrier status, and feeling well cannot exclude a 2+0 carrier arrangement. SMN1 is the principal gene assessed for carrier status; SMN2 is a related modifier gene whose copy number can influence disease severity after SMA is diagnosed, without determining an individual's outcome precisely.
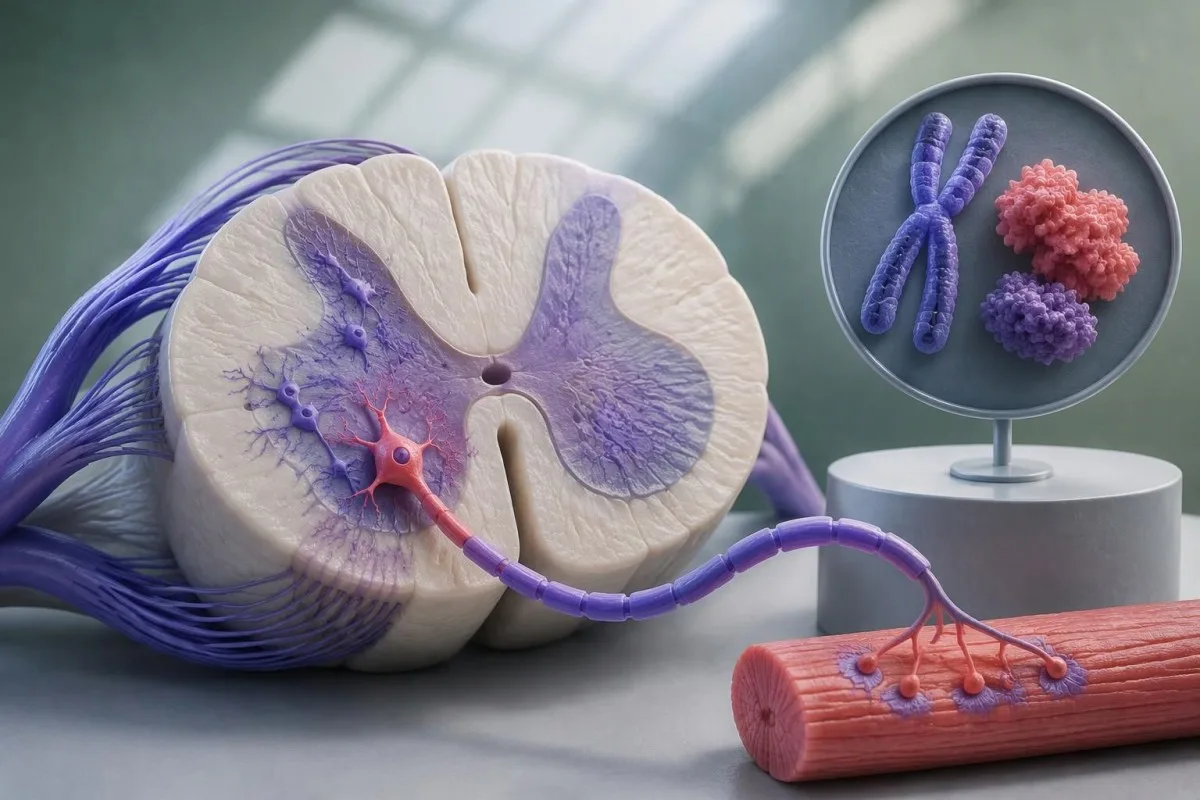
SMN2 usually produces much less full-length functional SMN protein than SMN1 because of altered RNA splicing. More SMN2 copies often correlate with a milder untreated phenotype, but someone with 3 or 4 SMN2 copies cannot use that number to exclude SMN1 carrier status or predict a future child's course.
SMA symptoms require a diagnostic pathway rather than reinterpretation of reproductive screening alone. Progressive weakness, reduced movement, feeding difficulty, or breathing problems in a child merit prompt assessment; a parent's previous two-copy result does not exclude an affected child because screening has recognized blind spots.
Many newborn SMA screens primarily identify homozygous SMN1 exon-7 deletion and can miss some less common genotypes. A negative newborn screen therefore does not exclude every form of SMA when clinical features are concerning; likewise, a carrier-screen result is not a substitute for evaluating symptoms.
AI explanations cannot safely replace pediatric examination or diagnostic genetic testing. Our guidance on Interpretarea AI la copii separates education from diagnosis; urgent breathing difficulty warrants immediate care regardless of whether a family report lists 1, 2, or 3 SMN1 copies.
Which details should you check on your SMN1 report?
Check the SMN1 copy count, exact linked-variant result, tested markers, assay limitations, residual-risk category, and any family-history caveat. These six details explain more than the headline “negative”; distinguish “not detected” from “not tested,” particularly when the report lists two SMN1 copies.
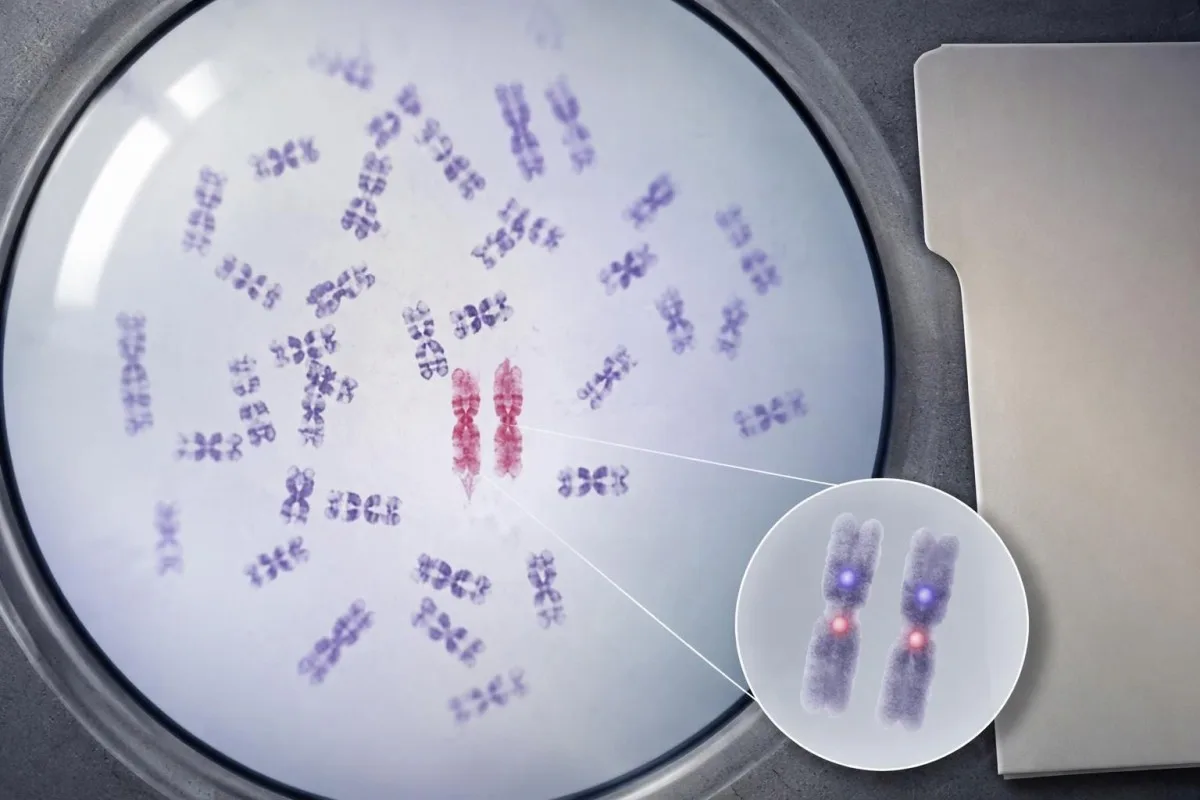
“Linked variant not detected” and “linked variant not assessed” are different results. With two copies, the first can support a lower estimate such as 1:814 in the published European category; the second leaves the copy-number-only estimate, approximately 1:604 in that category, unless the laboratory provides other evidence.
Keep the full report, including the interpretation page and method footnotes. A cropped screenshot showing only “SMN1: 2” removes information about sequencing coverage, markers, and ancestry assumptions; secure sharing through a family clinician workflow can help preserve the original document for review.
Useful laboratory questions are specific rather than general. Ask whether both c.*3+80T>G and c.*211_*212del were assessed, whether pathogenic sequence variants were evaluated, and whether family testing or a validated phasing method could distinguish 1+1 from 2+0 in your circumstances.
Kantesti does not determine chromosome phase from a PDF or reconstruct information missing from a genetic report. Noastre Ghid pentru tehnologia AI explains the broader interpretation workflow; for two SMN1 copies, the defensible output is an explanation of documented findings and remaining uncertainty, not an invented genotype.
How can AI help without overstating genetic certainty?
AI can help explain copy count, terminology, and questions for a genetics appointment, but it cannot confirm carrier phase or replace laboratory testing. A two-copy SMN1 result should remain linked to its original method and limitations; any educational interpretation must preserve the difference between estimated risk and proven carrier status.

Kantesti is an AI blood test interpretation platform whose educational role differs from a genetics laboratory's analytical role. For an SMN1 result of 2 copies, our explanation should not imply that a document upload establishes 1+1; our AI report safety guidance emphasizes checking claims against the source report.
Genetic reports can contain information relevant to more than one family member. Before sharing a two-copy result, remove unnecessary identifiers from relatives' attached records and obtain permission where appropriate; our genetic-report sharing precautions explain practical document-handling steps without implying that anonymization eliminates every privacy risk.
Privacy-focused handling does not make every form of disclosure risk-free. Genetic information may affect relatives and can have jurisdiction-dependent insurance or employment implications; our informații despre confidențialitate și date explains our handling approach, while a genetics professional can discuss questions specific to your country and family.
A useful appointment note can be only three lines long. Record “SMN1 copies: 2,” the exact linked-variant finding, and whether the reproductive partner has been tested; add the family-history question separately so that a reassuring automated summary does not accidentally bury the strongest reason for further assessment.
Which sources support the interpretation and next steps?
The SMA-specific evidence here comes from a 2022 testing-workflow review, ACOG's 2017 carrier-screening opinion, and ACMG's 2021 practice resource. The two additional publications listed below concern urinalysis and iron studies; they are separate educational resources, not evidence supporting SMN1 residual-risk estimates.
Milligan et al. (2022) provide the marker-dependent residual-risk estimates used in this article. Their table distinguishes copy-number-only results from two-copy results with duplication-associated variants absent or present; its population categories and assumptions should remain attached to any quoted number rather than being presented as universal reference intervals.
ACOG (2017) and Gregg et al. for ACMG (2021) support offering carrier screening and appropriate partner follow-up, but screening policy is not a personal genotype determination. When your report and a published 1:N estimate disagree, ask which assay, ancestry definition, family-history adjustment, or testing coverage explains the difference before choosing reproductive testing.
The two supplementary publications cannot answer a chromosome-phase question. Noastre urinalysis education resource addresses urine findings, while our iron studies education resource addresses iron measurements; neither publication validates SMA screening or estimates the likelihood of a 2+0 arrangement.
The practical next step is to preserve the report and clarify the uncertainty that would change a decision. For two SMN1 copies, that usually means checking marker coverage, family history, and partner results; our standarde de conținut medical require separating educational probabilities from confirmed diagnoses and avoiding unsupported reassurance.
Întrebări frecvente
Faptul că am două copii ale SMN1 înseamnă că nu sunt purtător al AME?
Două copii SMN1 înseamnă, de obicei, un risc redus de a fi purtător de AME, dar nu exclud statutul de purtător. Majoritatea oamenilor au o configurație 1+1, în timp ce un purtător silențios poate avea ambele copii pe un cromozom și niciuna pe celălalt — o configurație 2+0. Unele variante de secvență cauzatoare de boală pot, de asemenea, să nu fie detectate prin testarea bazată doar pe numărul de copii. Riscul dumneavoastră rezidual depinde de rezultatele markerilor asociați, de acoperirea testului, de ascendență și de istoricul familial.
Ce înseamnă două copii SMN1 cu o variantă asociată detectată?
Two SMN1 copies with a linked variant detected indicate increased likelihood of a silent-carrier arrangement, not confirmed carrier status. Common markers include c.*3+80T>G and c.*211_*212del. Published estimates summarized by Milligan et al. (2022) include approximately 1:12 for the European-ancestry category and 1:39 for the Black/African American category, but these population figures are not interchangeable. Genetic counseling and reproductive-partner testing can help clarify the practical implications.
Mai pot fi purtător asimptomatic dacă varianta asociată cu SMN1 este absentă?
Da, o persoană cu două copii SMN1 poate fi totuși un purtător silențios atunci când varianta asociată testată lipsește. Unele cromozomi 2+0 nu poartă markerul, iar laboratoarele pot diferi în privința markerilor pe care îi evaluează. Riscurile reziduale publicate în absența markerului includ aproximativ 1:814 pentru categoria de persoane cu ascendență europeană și 1:375 pentru categoria de persoane de culoare/afro-americane. Absența unui marker reduce riscul estimat, dar nu stabilește o configurație 1+1.
Ar trebui ca partenerul meu să fie testat dacă am două copii SMN1?
Partner testing is especially useful when a two-copy SMN1 result includes a linked variant, when SMA occurs in the family, or when the other partner is already a confirmed carrier. A two-copy, marker-negative result without relevant family history usually indicates lower risk, but screening can still be discussed during pregnancy planning. If one partner is a confirmed carrier, the other partner's assay should be reviewed for SMN1 dosage, sequence-variant coverage, and silent-carrier assessment. Two confirmed carriers have an approximately 25% affected-child risk in each pregnancy.
What is the baby's risk if one parent is an SMA carrier and the other has two copies?
When one parent is a confirmed SMA carrier, the estimated affected-pregnancy risk is the other parent's residual carrier risk multiplied by 1/4. For a hypothetical residual risk of 1:814, that produces approximately 1:3,256, or 0.031%. For a hypothetical residual risk of 1:12, it produces approximately 1:48, or 2.1%. These estimates require an appropriate residual-risk figure and may need adjustment for family history or biological relatedness.
Do SMN2 copies or a normal prenatal screen rule out SMA?
Neither SMN2 copy number nor a low-risk routine prenatal screen rules out SMA carrier status or an affected fetus. SMN2 is a disease-modifying gene, so a result of 3 or 4 copies does not establish whether SMN1 has a 1+1 or 2+0 arrangement. Standard cell-free DNA prenatal screening generally does not diagnose SMA. When a pregnancy has meaningful SMA risk, a genetics team can discuss condition-specific diagnostic testing using chorionic villus sampling or amniocentesis.
Aflați cum se citesc analizele de sânge
Încărcați buletinul de analize, iar AI-ul Kantesti explică fiecare biomarker în limbaj simplu, în câteva secunde. Folosit de peste 2 milioane de persoane din întreaga lume.
Referințe
- Klein, T., Mitchell, S., & Weber, H. (2026). Testul de urobilinogen în urină: Ghid complet de analiză de urină 2026. Kantesti AI Medical Research. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). Ghid privind studiile de fier: TIBC, saturația fierului și capacitatea de legare. Kantesti AI Medical Research. DOI
- Milligan JN et al. (2022). Recommendations for Interpreting and Reporting Silent Carrier and Disease-Modifying Variants in SMA Testing Workflows. Genes. DOI
- American College of Obstetricians and Gynecologists (2017). Committee Opinion No. 691: Carrier Screening for Genetic Conditions. Obstetrics & Gynecology. DOI
- Gregg AR et al. (2021). Screening for autosomal recessive and X-linked conditions during pregnancy and preconception: a practice resource of the American College of Medical Genetics and Genomics (ACMG). Genetics in Medicine. DOI
- 2M+Teste analizate
- 127+Țări
- 100+Limbi
Despre echipa medicală


Semnale de încredere E-E-A-T
Experienţă
Revizuire clinică condusă de medici a fluxurilor de lucru pentru interpretarea analizelor.
Expertiză
Focalizare pe medicina de laborator asupra modului în care biomarkerii se comportă în context clinic.
Autoritate
Revizuit medical de Dr. Thomas Klein, cu contribuții din partea Dr. Sarah Mitchell și Prof. Dr. Hans Weber.
Încredere
Interpretare bazată pe dovezi, cu căi clare de urmărire pentru a reduce alarmele.






Declinare a răspunderii medicale
Acest articol are doar scop educațional și nu constituie sfat medical. Consultă întotdeauna un furnizor calificat de servicii medicale pentru decizii privind diagnosticarea și tratamentul.
Publicat · Contactați echipa editorială
Publicat de Kantesti Ltd, înregistrată în Anglia și Țara Galilor, numărul companiei. 17090423, Londra, Regatul Unit.
