
A detected JAK2 variant can be a valuable clue, but the blood count, test method and clinical picture determine what happens next.

Belangrijkste punten
- Positief resultaat: A detected JAK2 variant supports a clonal blood-cell process, but it does not establish a particular diagnosis on its own.
- V617F: JAK2 V617F occurs in approximately 95% of polycythemia vera cases and in about half of essential thrombocythemia and primary myelofibrosis cases.
- Exon 12: A JAK2 exon 12 mutation is especially relevant when polycythemia vera is suspected and V617F is not detected.
- Negatief resultaat: A JAK2 mutation negative result does not exclude every myeloproliferative neoplasm; it only addresses variants covered by that assay.
- Allele burden: A 1% variant allele fraction describes approximately one mutant copy per 100 tested DNA copies, not necessarily 1% of cells.
- Blood counts: Persistently raised hemoglobin, hematocrit or platelets can guide the next stage of evaluation, but each has non-cancer causes.
- Vervolg: Ask for the exact variant, specimen, detection limit and whether exon 12, CALR or MPL testing is appropriate.
- Spoedklachten: Sudden stroke symptoms, chest pain or breathlessness require emergency assessment regardless of the JAK2 result.
What does a positive JAK2 mutation result mean?
A positive JAK2 mutation test result means the laboratory detected a specified genetic change in the tested sample. It supports the possibility of a myeloproliferative neoplasm, or MPN, but it does not identify the MPN subtype or prove that diagnostic criteria are met.

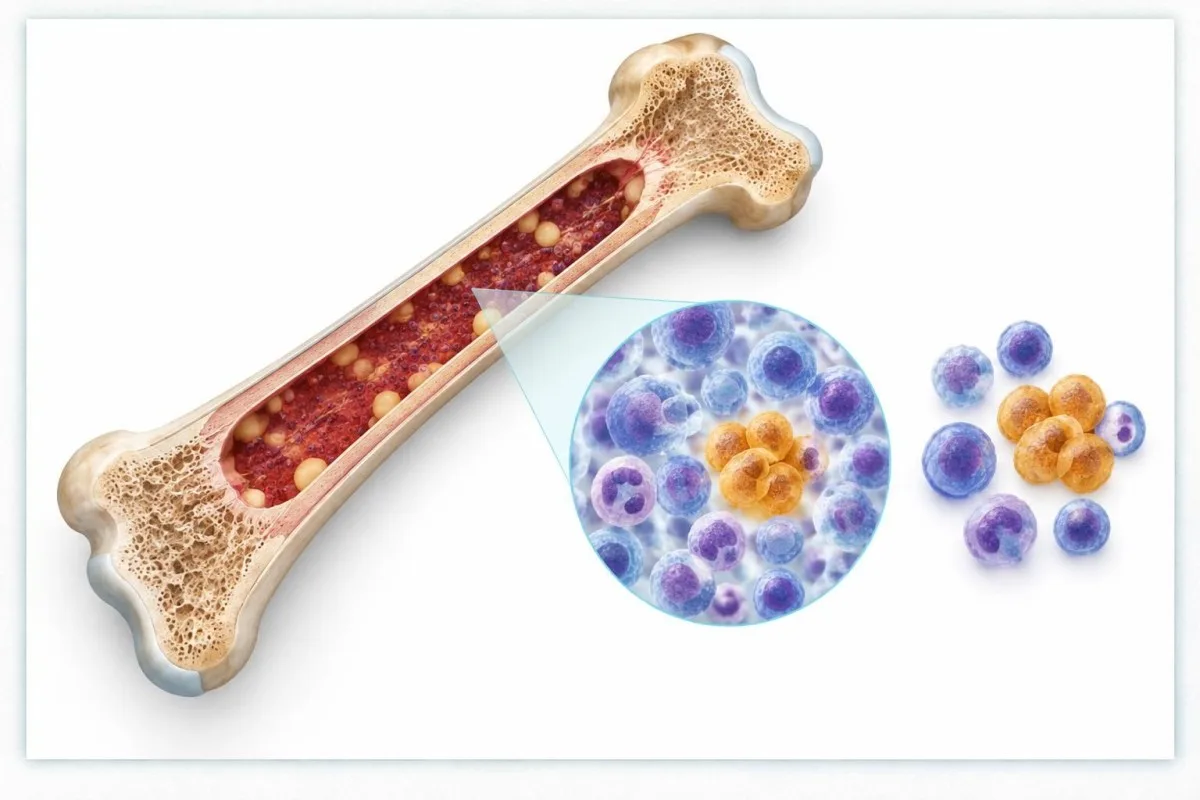
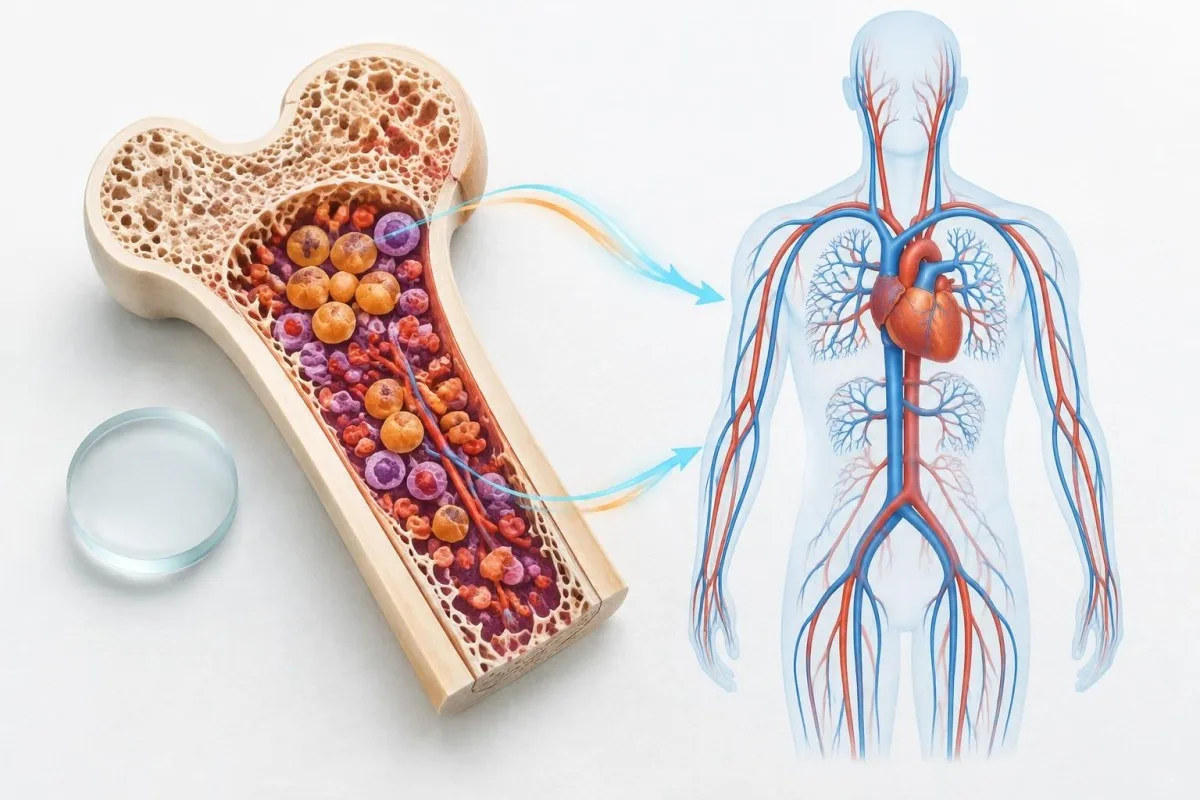
JAK2 helps transmit signals that regulate production of blood-cell lineages. An acquired activating variant can give a group of marrow cells a growth advantage; that group is called a clone.
The JAK2 V617F positive meaning depends on why testing was ordered. A persistent elevation in red cells suggests a different workup from isolated high platelets, even if the same variant is found.
Kantesti is an AI blood test analyzer that can help organize a JAK2 report alongside a complete blood count for discussion with a clinician. The biomarker-gids provides context for other measurements, but AI cannot diagnose an MPN or replace hematology review.
Which conditions are linked to JAK2 V617F?
JAK2 V617F is strongly associated with polycythemia vera, essential thrombocythemia and primary myelofibrosis. Its presence supports a clonal process, but all three conditions—and occasionally other myeloid disorders—can carry the same variant.
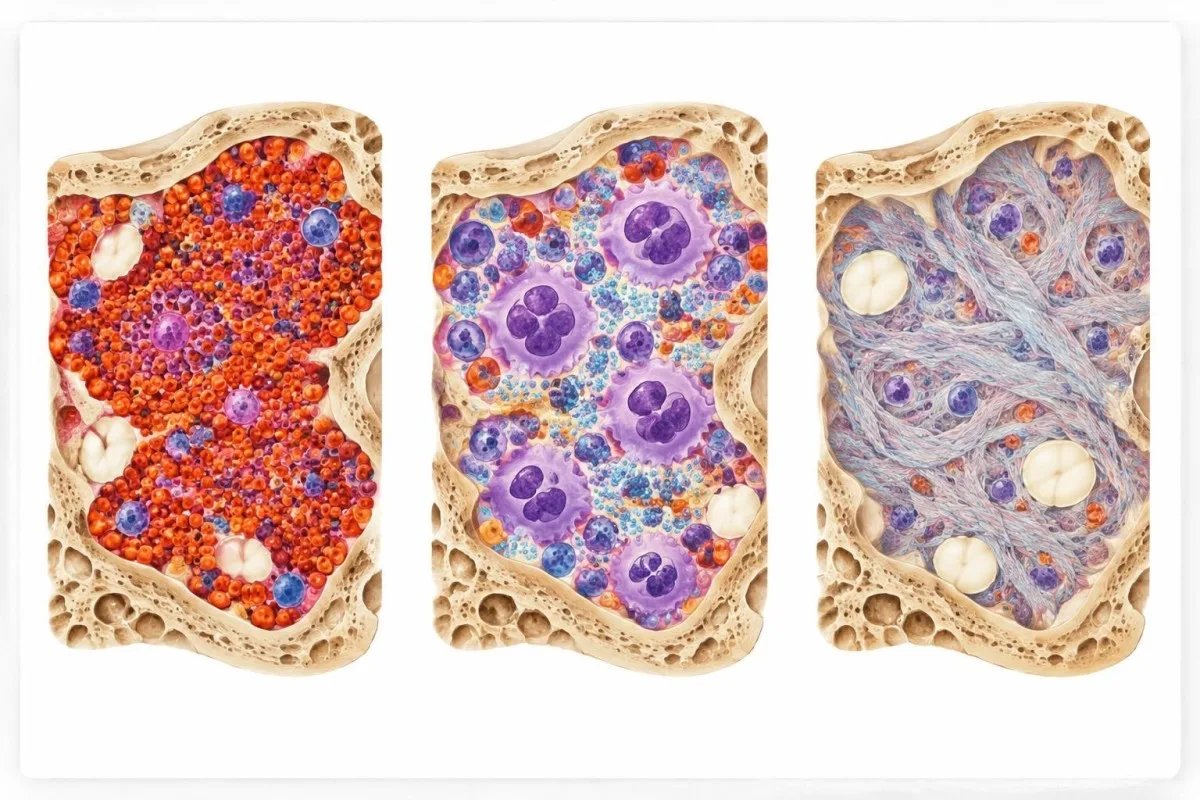
JAK2 V617F is present in approximately 95% of polycythemia vera cases and around 50–60% of essential thrombocythemia or primary myelofibrosis cases. These are approximate frequencies in diagnosed groups, not the chance that a person with a positive result has a particular disease.
Polycythemia vera predominantly involves increased red-cell production; essential thrombocythemia is characterized by persistent platelet elevation; and primary myelofibrosis has characteristic marrow changes that can progress to fibrosis. The diagnostic frameworks also distinguish early, or prefibrotic, myelofibrosis from essential thrombocythemia (Arber et al., 2022).
A clinician may consider BCR-ABL1 testing when the blood-count pattern raises the possibility of chronic myeloid leukemia. This is a different molecular test, not a substitute name for JAK2 testing.
What does a JAK2 exon 12 mutation mean?
A JAK2 exon 12 mutation is an acquired change in another part of the JAK2 gene, most closely associated with polycythemia vera when V617F is not detected. Exon 12 testing is particularly useful in a compatible erythrocytosis workup.
In the landmark report by Scott and colleagues, JAK2 exon 12 variants were identified in V617F-negative patients with polycythemia vera or related erythrocytosis (Scott et al., 2007). Exon 12 is a region containing several possible variants, rather than one single mutation.
A V617F-only report does not automatically cover exon 12. Ask whether exon 12 was included, performed as a reflex test after a negative V617F result, or requires a separate order.
Clinicians often pair molecular findings with an erythropoietin result. A low erythropoietin level can support polycythemia vera in the right setting, but it is not sufficient to diagnose it by itself.
Why does a positive result not establish an MPN diagnosis?
A positive JAK2 result does not establish an MPN diagnosis because the variant must be interpreted with blood counts, marrow findings when indicated, clinical history and applicable diagnostic criteria. A small JAK2-mutated clone can also be detected without an overt MPN.

The International Consensus Classification uses combinations of major and minor criteria rather than a JAK2 result alone (Arber et al., 2022). The specific criteria differ between polycythemia vera, essential thrombocythemia and primary myelofibrosis.
For example, a person may have a positive V617F result and a platelet count of 500 × 10⁹/L, but iron deficiency or inflammation may also contribute to the count. A hematologist assesses the whole pattern before assigning a diagnosis.
A myelodysplastic syndrome evaluation illustrates a related principle: molecular clues and the marrow examination answer different questions. Neither should be interpreted as an isolated verdict.
Which blood-count patterns guide the workup?
Persistent elevations in hemoglobin, hematocrit or platelets help clinicians decide which MPN criteria and alternative causes to investigate. A single abnormal complete blood count is a starting point, not a diagnosis.
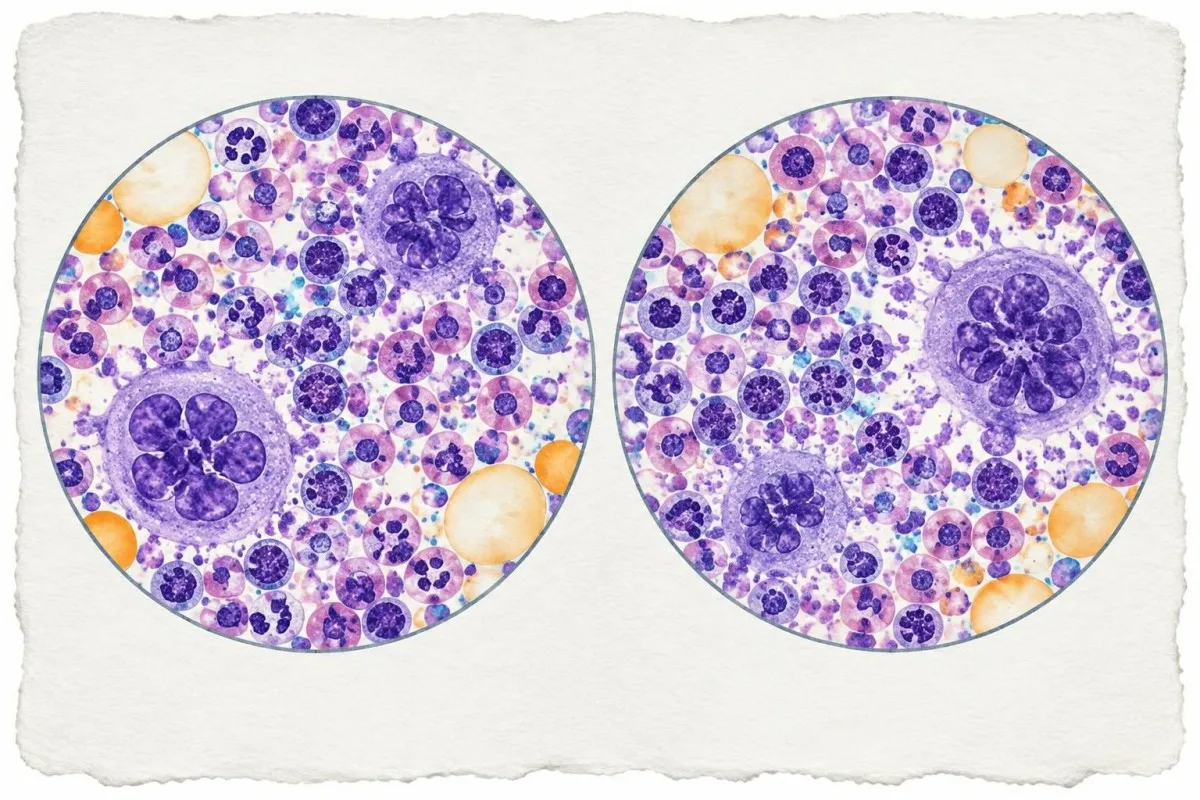
For polycythemia vera, one commonly used adult criterion is hemoglobin above 16,5 g/dL bij mannen of 16,0 g/dL bij vrouwen, of hematocriet boven 49% or 48%, respectively. These thresholds are diagnostic criteria used with other findings, not stand-alone treatment triggers.
For essential thrombocythemia, a sustained platelet count of at least 450 × 10⁹/L is one criterion. Infection, inflammation, iron deficiency and other conditions can also raise platelets, so the duration and associated findings matter.
Compare the values and units on your report with previous results. Our guide to hematocrit versus hemoglobin explains why the two measures can sometimes tell different stories.
What does a low JAK2 allele burden mean?
Een lage variant allele fraction, or VAF, means that a small proportion of JAK2 DNA copies in the tested sample carry the reported variant. A low VAF can occur in an early or small clone, but its clinical meaning depends on the assay and the rest of the evaluation.

A VAF of 1% means roughly 1 in 100 tested JAK2 copies carried the variant in that specimen. It does not automatically mean 1% of all cells are affected: cell mixture, gene-copy number and whether cells carry one or more variant copies can change the relationship.
For a simplified hypothetical example, if every relevant cell has two JAK2 copies and each affected cell has one variant copy, a 1% VAF could correspond to roughly 2% affected cells. Real clinical samples may not satisfy those assumptions.
Very small clones may represent klonale hematopoëse, a finding that can occur without an established blood cancer. A hematologist may review count trends and the original assay rather than label a low result benign or malignant from its percentage alone; see our guide to kwalitatieve en kwantitatieve resultaten.
How do detection limits affect JAK2 results?
A JAK2 assay detects variants only within its validated coverage and sensitivity. A result close to the laboratory’s detection or quantification limit may be less precise than a higher-level result, even when the finding is real.

De limit of detection is the lowest level at which an assay can reliably detect a variant under its validation conditions. The limit of quantification concerns reliable measurement of its amount; the two limits can differ.
Hypothetically, a laboratory with a 0.1% detection limit could detect a clone missed by an assay with a 1% limit. This comparison only applies if both assays cover the same variant and use suitable specimens.
Reports may say “detected below the quantifiable range,” give a percentage, or provide only a positive/negative answer. Kantesti can help organize those terms, but the laboratory’s own method notes remain the reference; our AI-technologiegids explains the platform’s general approach.
What does a JAK2 mutation negative result mean?
A JAK2 mutation negative result means no covered variant was detected above that test’s reporting limit. It does not exclude every MPN, every JAK2 variant or a clone below the assay’s sensitivity.

A negative V617F result is less supportive of polycythemia vera because about 95% of diagnosed cases carry V617F, but exon 12 variants account for many of the remaining cases. The next test depends on the clinical pattern and what the first assay actually covered.
Essential thrombocythemia and primary myelofibrosis can be associated with CALR of MPL variants instead of JAK2 V617F. Some patients have none of these three common driver variants detected, sometimes described as triple-negatief.
A report can be negative, indeterminate or technically unsuccessful; those are different outcomes. Ask the ordering team whether the specimen was adequate and whether genetic panel limitations affect the interpretation.
Which tests may follow a JAK2 result?
Follow-up testing can include repeat blood counts, a blood-film review, erythropoietin, iron studies, additional molecular tests and sometimes a bone marrow examination. The choice depends on whether the main finding involves red cells, platelets, white cells or unexplained symptoms.

When platelets remain at or above 450 × 10⁹/L, clinicians may assess iron status and inflammation as well as consider CALR and MPL testing. A raised platelet count is not specific for an MPN.
A marrow examination can distinguish patterns that a molecular result cannot, including essential thrombocythemia from prefibrotic primary myelofibrosis. The decision to perform one is individualized and depends on the diagnostic question.
A blood film may reveal immature cells or unusual shapes. Our guide to teardrop cells on a smear explains why such findings need context rather than automatic attribution to myelofibrosis.
Can iron deficiency or dehydration change the picture?
Iron deficiency can make red cells smaller and may obscure the degree of red-cell overproduction, while dehydration can make a blood count appear concentrated. Both can complicate the evaluation of suspected polycythemia vera.
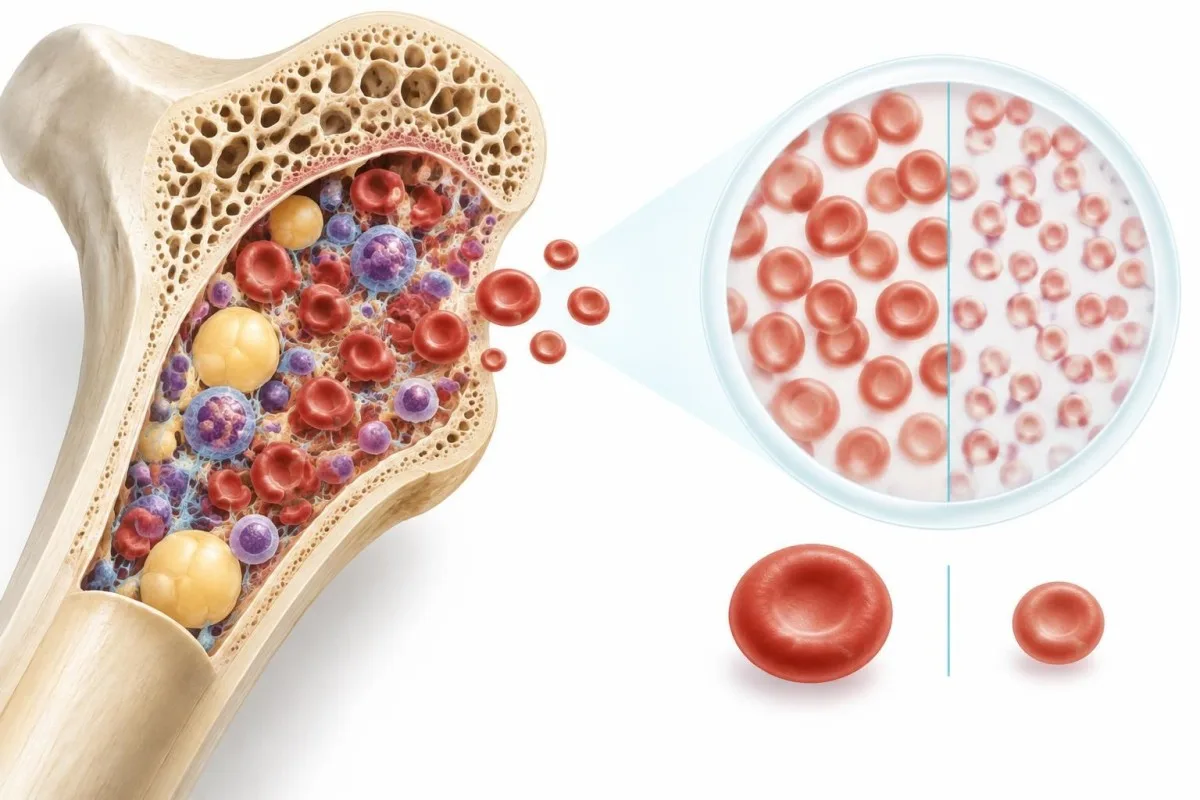
Low mean corpuscular volume, or MCV, can accompany iron deficiency. In a compatible clinical setting, a high red-cell count with small cells may deserve closer review even when hemoglobin is not strikingly elevated.
A hypothetically dehydrated patient may have a raised hematocrit because plasma volume is reduced, not because the body has produced excess red cells. A clinician can assess the history and decide when a repeat count is appropriate.
De handleiding voor ijzeronderzoek explains how ferritin, transferrin saturation and related measurements fit together. Do not start or stop iron solely because of a JAK2 result; ask the clinician managing the workup.
Is a JAK2 mutation inherited by family members?
JAK2 V617F and the exon 12 variants discussed in MPN testing are usually acquired, or somatic, changes in blood-forming cells rather than inherited variants present throughout the body. A positive result does not automatically mean children or siblings carry the same variant.
A family history of MPNs can still matter because inherited factors may affect susceptibility in some families. That is distinct from directly passing on the acquired V617F variant found in a blood-cell clone.
Blood-based testing alone can be difficult to use for determining whether some variants are inherited when a person has a myeloid disorder. If an inherited predisposition is suspected, a specialist can select appropriate testing and a suitable non-blood tissue source.
For contrast, our article on BRCA genetic results discusses inherited cancer-predisposition testing. It should not be treated as an interpretation guide for an acquired JAK2 result.
Does a positive JAK2 result mean a clot will occur?
A positive JAK2 result does not mean a blood clot will occur, although JAK2-associated MPNs can increase clotting risk. Risk assessment depends on the established diagnosis, prior clotting, age and other clinical factors—not the molecular result alone.
In polycythemia vera, clinicians commonly consider age over 60 jaar and a history of thrombosis when assessing risk. Other factors, including the blood count and cardiovascular risks, can influence individual management.
Do not begin aspirin, anticoagulants or phlebotomy solely because a JAK2 report is positive. These interventions have benefits and risks that require a diagnosis-specific plan.
New one-sided leg swelling can be a sign of deep vein thrombosis and needs prompt medical assessment. Sudden chest pain, severe breathlessness, facial droop, arm weakness or speech difficulty warrants emergency services.
When might repeat JAK2 testing be useful?
Repeat JAK2 testing may be useful when a result is near an assay’s limit, the sample was inadequate, the clinical picture changes or a specialist needs to clarify discordant findings. There is no universal retest interval for every positive or negative result.

Two VAF values from different laboratories may not be directly comparable if their methods, specimen types or reporting limits differ. A change from 0.2% to 0.3%, for example, may be hard to interpret without knowing measurement uncertainty.
For someone receiving MPN treatment, the clinician may request molecular monitoring for a specific reason; VAF should not be used alone to change medication or predict an individual outcome. Blood counts, symptoms and the treatment plan still matter.
Kantesti is an AI biomarker interpretation platform that can help readers organize dated results for review, but it cannot validate whether two JAK2 assays are interchangeable. Our gids voor tijdlijnen van bloedtesten covers practical comparison questions.
What should you discuss with your clinician next?
Bring the complete JAK2 report and recent blood counts to the ordering clinician, and ask whether a hematology referral is appropriate. The immediate next step depends on the variant, blood-count pattern, symptoms and reason for testing.

Ask four practical questions: Which variant was tested? Was the result qualitative or quantitative? What were the assay’s detection and quantification limits? Were exon 12, CALR or MPL variants included or tested separately?
Take prior complete blood counts, iron results, a medication list and any history of clotting or unusual bleeding. For example, a platelet count that has stayed above 450 × 10⁹/L across repeated tests tells a different story from a single raised count during an acute illness.
Kantesti can help organize a PDF or photo of laboratory results, but an AI explanation is not a diagnosis or a reason to delay specialist care. Read our medische validatie-informatie for the platform’s stated approach and limitations.
Veelgestelde vragen
Betekent JAK2 V617F-positief dat ik kanker heb?
Een positieve JAK2 V617F-uitslag bewijst op zichzelf niet dat u kanker hebt. Deze variant komt vaak voor bij myeloproliferatieve neoplasmata, waaronder bij ongeveer 95% van de gevallen van polycythaemia vera, maar kan ook worden aangetroffen in een kleine kloon van bloedcellen zonder dat er sprake is van een vastgestelde MPN. Een arts beoordeelt de uitslag in samenhang met het bloedbeeld, de symptomen en soms een beenmergonderzoek.
Can I have an MPN if my JAK2 test is negative?
Yes. A negative JAK2 result does not rule out all myeloproliferative neoplasms, and a V617F-only test does not rule out a JAK2 exon 12 mutation. Around half of essential thrombocythemia and primary myelofibrosis cases have JAK2 V617F; others may have CALR or MPL variants, or none of those three detected. Ask which variants your assay covered and whether further testing fits your blood-count pattern.
Is a JAK2 allele burden of 1% serious?
A JAK2 variant allele fraction of 1% means approximately 1 in 100 tested JAK2 DNA copies carried the variant in that sample. It does not by itself establish disease severity, predict an individual outcome or equal 1% affected cells. The detection method, blood counts, symptoms and whether an MPN diagnosis is established all matter. Discuss a low-level result with the ordering clinician rather than assuming it is harmless or dangerous.
What is the difference between JAK2 V617F and exon 12?
JAK2 V617F is a specific variant, whereas JAK2 exon 12 refers to a region where several different variants can occur. V617F is found in approximately 95% of polycythemia vera cases and also occurs in essential thrombocythemia and primary myelofibrosis. Exon 12 variants are particularly relevant to V617F-negative polycythemia vera. A V617F-only assay may not test exon 12.
Can a JAK2 mutation be passed to my children?
The JAK2 V617F and exon 12 changes detected during an MPN workup are usually acquired in blood-forming cells rather than inherited. A positive result therefore does not mean a child has inherited that same mutation. Some families have an increased predisposition to MPNs, so share a family history of blood disorders with your clinician. A genetics specialist can advise if inherited-risk testing is appropriate.
Should I start aspirin after a positive JAK2 test?
Do not start aspirin solely because of a positive JAK2 test. Treatment decisions depend on whether an MPN is diagnosed, the subtype, bleeding risk and factors such as age and previous thrombosis. For example, age over 60 years is one factor used in polycythemia vera risk assessment, but it is not an instruction to self-medicate. Ask your clinician for an individual plan.
Laat uw bloedwaarden begrijpen
Upload uw laboratoriumrapport en de AI van Kantesti legt elke biomarker binnen enkele seconden uit in begrijpelijke taal. Wereldwijd gebruikt door meer dan 2 miljoen mensen.
Referenties
- Klein, T., Mitchell, S., & Weber, H. (2026). AI Blood Test Analyzer: 2,5M tests geanalyseerd | Global Health Report 2026. Kantesti AI Medisch Onderzoek. DOI
- Klein, T., Mitchell, S., & Weber, H. (2026). RDW-bloedtest: complete gids voor RDW-CV, MCV en MCHC. Kantesti AI Medisch Onderzoek. DOI
- Arber DA et al. (2022). International Consensus Classification of Myeloid Neoplasms and Acute Leukemias: integrating morphologic, clinical, and genomic data. Blood. DOI
- Scott LM et al. (2007). JAK2 Exon 12 Mutations in Polycythemia Vera and Idiopathic Erythrocytosis. New England Journal of Medicine. DOI
- 2M+Geanalyseerde tests
- 127+Landen
- 100+Talen
Over het medische team


E-E-A-T Vertrouwenssignalen
Ervaring
Klinische beoordeling door artsen van lab-interpretatieworkflows.
Expertise
Laboratoriumgeneeskunde met focus op hoe biomarkers zich gedragen in een klinische context.
Gezag
Medisch beoordeeld door Dr. Thomas Klein, met bijdragen van Dr. Sarah Mitchell en Prof. Dr. Hans Weber.
Betrouwbaarheid
Evidence-based interpretatie met duidelijke vervolgstappen om onrust te verminderen.



Medische disclaimer
Dit artikel is uitsluitend bedoeld voor educatieve doeleinden en vormt geen medisch advies. Raadpleeg altijd een gekwalificeerde zorgverlener voor beslissingen over diagnose en behandeling.
Gepubliceerd · Neem contact op met het redactieteam
Uitgegeven door Kantesti Ltd, geregistreerd in Engeland en Wales, bedrijfsnr. 17090423, Londen, Verenigd Koninkrijk.
