
د JAK2 کشف شوی بدلون یوه ارزښتناکه نښه کېدای شي، خو د وینې شمېر، د ازموینې طریقه او کلینیکي انځور ټاکي چې ورپسې څه کېږي.

مهم ټکي
- مثبت پایله: د JAK2 کشف شوی بدلون د وینې د حجرو د کلوني بهیر ملاتړ کوي، خو په خپله کوم ځانګړی تشخیص نه ثابتوي.
- V617F: د JAK2 V617F بدلون د پولیسیتمیا ویرا په نږدې 95% پېښو کې او د ضروري ترومبوسایتمیا او لومړني مایلوفایبروسس په نږدې نیمایي پېښو کې لیدل کېږي.
- اېکسون 12: د JAK2 اېکسون 12 بدلون په ځانګړې توګه هغه مهال مهم دی چې د پولیسیتمیا ویرا شک وي او V617F ونه موندل شي.
- منفي پایله: د JAK2 د بدلون منفي پایله د مایلوپرولیفراټیف هره نیوپلازم نه ردوي؛ دا یوازې هغه بدلونونه ارزوي چې د ازموینې په پوښښ کې دي.
- د الیل بار: د 1% بدلونلرونکي الیل تناسب نږدې د هر 100 ازمویل شوو DNA کاپیو پر وړاندې یوه بدله کاپي ښيي، نه دا چې حتماً د حجرو 1% وي.
- د وینې شمېر: په دوامداره توګه د هیموګلوبین، هیماتوکریټ یا پلیټلېټونو لوړې کچې د ارزونې د بل پړاو لارښوونه کولی شي، خو هر یو یې د سرطان پرته نور لاملونه هم لري.
- تعقیب: د دقیق ډول، نمونې، د کشف حد او دا چې د اېکسون ۱۲، CALR یا MPL ازموینه مناسبه ده که نه، پوښتنه وکړئ.
- عاجلې نښې: د سکتې ناڅاپي نښې، د سینې درد یا ساه لنډي د JAK2 پایلې ته له پام پرته بیړنۍ ارزونه غواړي.
د JAK2 د بدلون مثبته پایله څه معنا لري؟
A د JAK2 د بدلون د ازموینې مثبته پایله یعنې لابراتوار په ازمویل شوې نمونه کې یو ټاکلی جنیټیک بدلون موندلی دی. دا د مایلوپرولیفراټیف نیوپلازم، یا MPN، د احتمال ملاتړ کوي، خو د MPN فرعي ډول نه ټاکي او نه ثابتوي چې د تشخیص معیارونه پوره شوي دي.

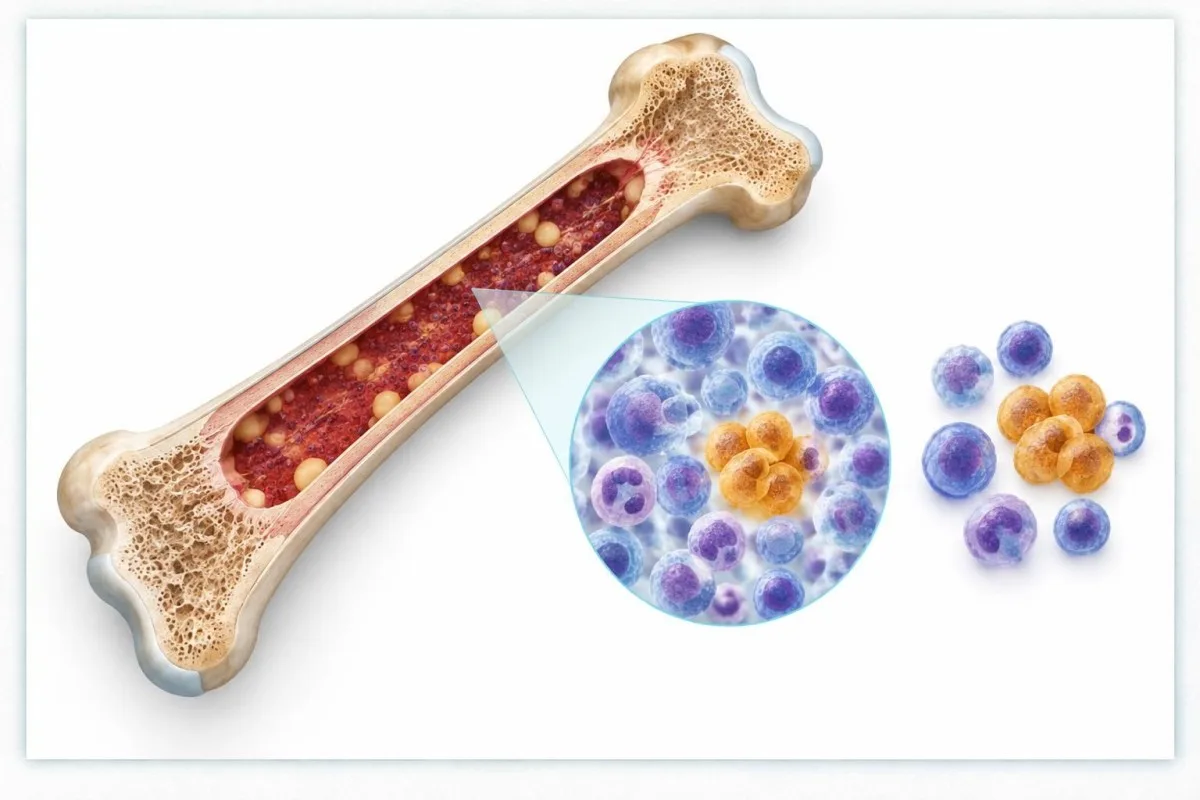
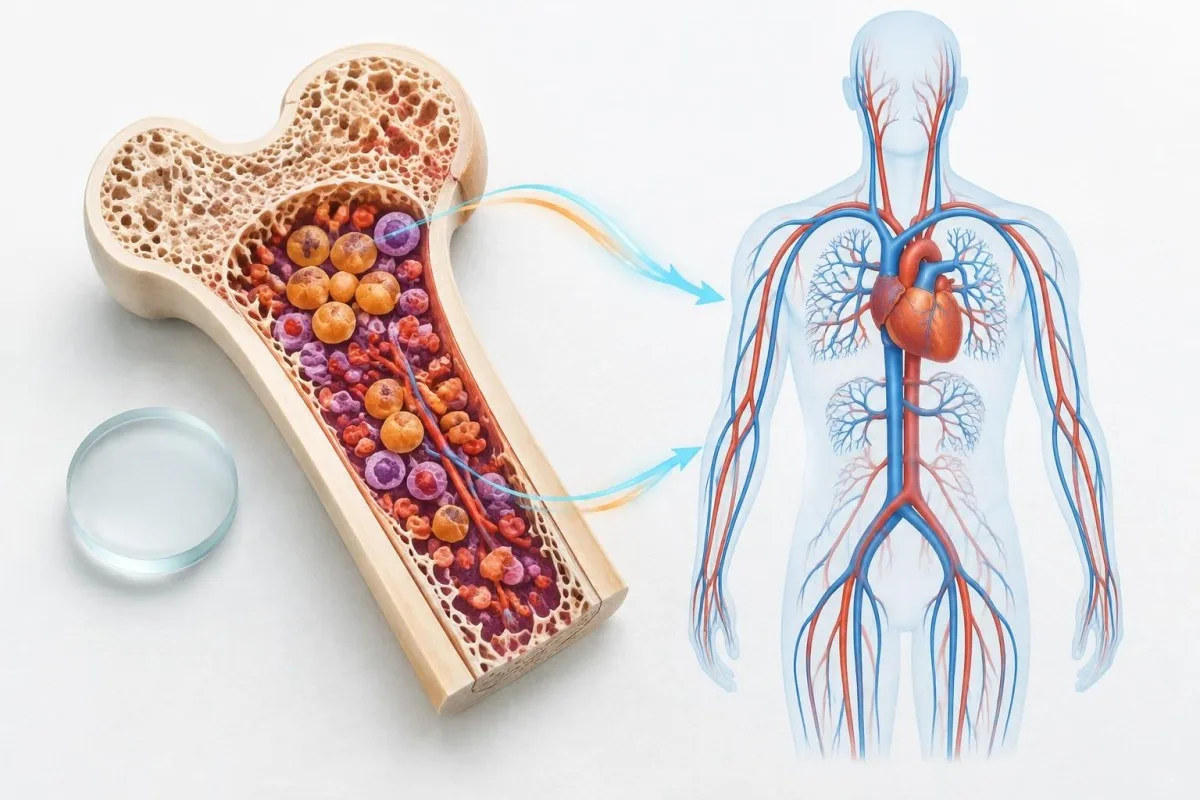
JAK2 د هغو نښو په لېږد کې مرسته کوي چې د وینې د حجرو د لړیو تولید تنظیموي. یو ترلاسه شوی فعالوونکی ډول کولای شي د هډوکي مغز د حجرو یوې ډلې ته د ودې ګټه ورکړي؛ هغې ډلې ته کلون.
د JAK2 V617F د مثبتې پایلې مانا په دې پورې اړه لري چې ازموینه ولې غوښتل شوې وه. د سرو حجرو دوامداره زیاتوالی له یوازې د پلیټلیټونو له لوړې کچې سره توپیر لرونکې ارزونه غواړي، ان که هماغه ډول وموندل شي.
Kantesti د وینې د ازموینو د تحلیل لپاره یو مصنوعي ځیرکتیايي وسیله ده چې له ډاکټر سره د بحث لپاره د JAK2 راپور د بشپړ وینې شمېرنې ترڅنګ تنظیمولو کې مرسته کولای شي. دغه د بایومارکر لارښود د نورو اندازو د پایلو د پوهېدو زمینه برابروي، خو مصنوعي ځیرکتیا د MPN تشخیص نه شي کولای او نه د وینې ناروغیو د متخصص ارزونه بدلولای شي.
له JAK2 V617F سره کومې ناروغۍ تړاو لري؟
JAK2 V617F له پولیسیتمیا ویرا، اساسي ترومبوسیتمیا او لومړني مایلوفایبروسیس سره قوي تړاو لري. د دې شتون د کلوني بهیر ملاتړ کوي، خو دا درې واړه حالتونه—او کله ناکله نور مایلوئید اختلالونه—همدا ډول لرلای شي.
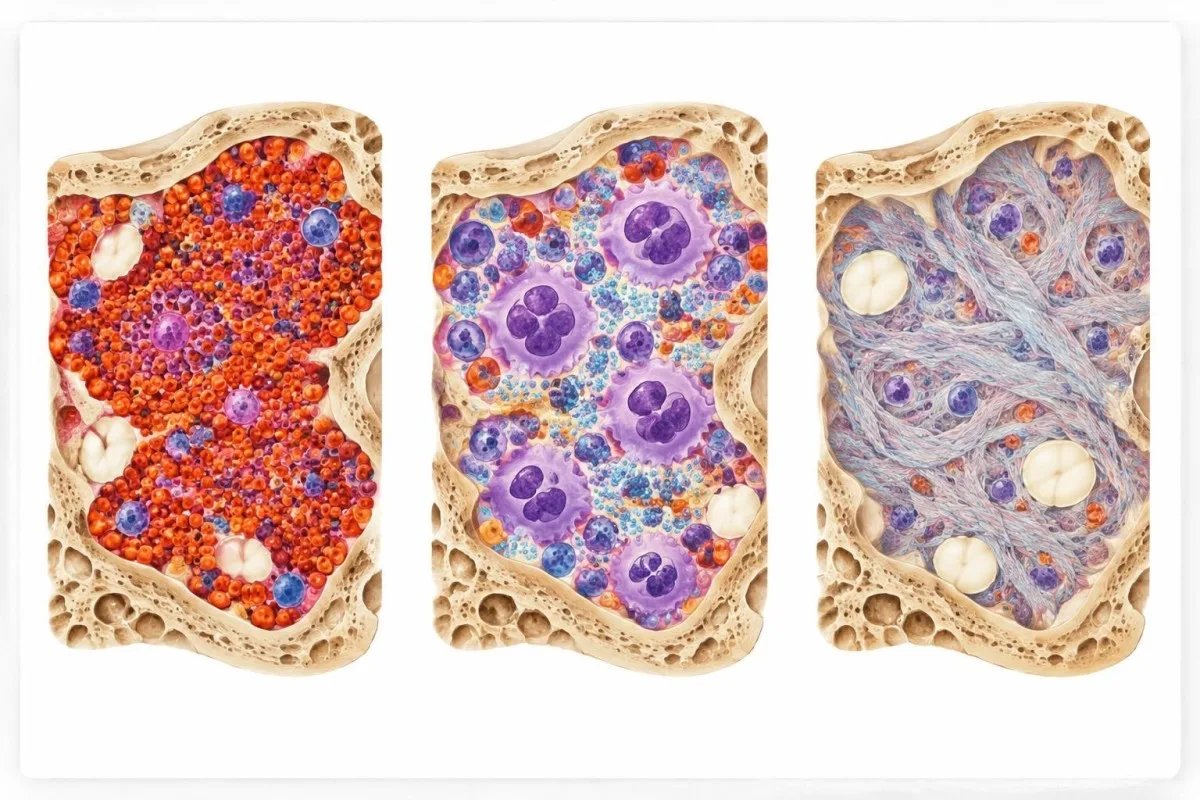
JAK2 V617F نږدې په 95% د پولیسیتمیا ویرا په پېښو او شاوخوا 50–60% د اساسي ترومبوسیتمیا یا لومړني مایلوفایبروسیس په پېښو کې شتون لري. دا په تشخیص شوو ډلو کې نږدې سلنې دي، نه دا چې د مثبتې پایلې لرونکی کس په کومه ځانګړې ناروغۍ اخته وي.
پلیسایتیمیا ویرا په عمده توګه د سرو حجرو له زیات تولید سره تړاو لري؛ اساسي ترومبوسایټیمیا د پلیټلېټونو د دوامدار زیاتوالي ځانګړتیا لري؛ او لومړنی مایلوفایبروسس د مغز ځانګړني بدلونونه لري چې فایبروسس ته پرمختګ کولی شي. تشخیصي چوکاټونه هم لومړنی، یا له فایبروسس څخه مخکې، مایلوفایبروسس له اساسي ترومبوسایټیمیا څخه جلا کوي (Arber et al., 2022).
یو کلینیشن ښايي په پام کې ونیسي د BCR-ABL1 ازموینه کله چې د وینې د شمېرې بڼه د مزمن میلوئید لېوکیمیا احتمال راپورته کړي. دا یوه بېله مالیکولي ازموینه ده، نه د JAK2 ازموینې بدیل نوم.
د JAK2 اېکسون 12 بدلون څه معنا لري؟
A د JAK2 د ۱۲م اېکسون جهش په JAK2 جین کې د بلې برخې یو ترلاسه شوی بدلون دی، چې له پلیسایتیمیا ویرا سره تر ټولو نږدې تړاو لري کله چې V617F ونه موندل شي. د اېکسون ۱۲ ازموینه د مناسبې اریتروسایتوز د ارزونې په بهیر کې په ځانګړې توګه ګټوره ده.
In the landmark report by Scott and colleagues, JAK2 exon 12 variants were identified in V617F-negative patients with polycythemia vera or related erythrocytosis (Scott et al., 2007). Exon 12 is a region containing several possible variants, rather than one single mutation.
A V617F-only report does not automatically cover exon 12. Ask whether exon 12 was included, performed as a reflex test after a negative V617F result, or requires a separate order.
Clinicians often pair molecular findings with an erythropoietin result. A low erythropoietin level can support polycythemia vera in the right setting, but it is not sufficient to diagnose it by itself.
ولې مثبته پایله د MPN تشخیص نه ثابتوي؟
A positive JAK2 result does not establish an MPN diagnosis because the variant must be interpreted with blood counts, marrow findings when indicated, clinical history and applicable diagnostic criteria. A small JAK2-mutated clone can also be detected without an overt MPN.

The International Consensus Classification uses combinations of major and minor criteria rather than a JAK2 result alone (Arber et al., 2022). The specific criteria differ between polycythemia vera, essential thrombocythemia and primary myelofibrosis.
For example, a person may have a positive V617F result and a platelet count of ۵۰۰ × ۱۰⁹/L, but iron deficiency or inflammation may also contribute to the count. A hematologist assesses the whole pattern before assigning a diagnosis.
A myelodysplastic syndrome evaluation illustrates a related principle: molecular clues and the marrow examination answer different questions. Neither should be interpreted as an isolated verdict.
د وینې د شمېر کومې بڼې د ارزونې لارښوونه کوي؟
Persistent elevations in hemoglobin, hematocrit or platelets help clinicians decide which MPN criteria and alternative causes to investigate. A single abnormal complete blood count is a starting point, not a diagnosis.
For polycythemia vera, one commonly used adult criterion is hemoglobin above په نارینه وو کې 16.5 g/dL یا په ښځو کې 16.0 g/dL, ، یا له 49% or 48%, respectively. These thresholds are diagnostic criteria used with other findings, not stand-alone treatment triggers.
For essential thrombocythemia, a sustained platelet count of at least 450 × 10⁹/L is one criterion. Infection, inflammation, iron deficiency and other conditions can also raise platelets, so the duration and associated findings matter.
Compare the values and units on your report with previous results. Our guide to hematocrit versus hemoglobin explains why the two measures can sometimes tell different stories.
د JAK2 د الیل ټیټ بار څه معنا لري؟
ټیټ variant allele fraction, or VAF, means that a small proportion of JAK2 DNA copies in the tested sample carry the reported variant. A low VAF can occur in an early or small clone, but its clinical meaning depends on the assay and the rest of the evaluation.

A VAF of 1% means roughly 1 in 100 tested JAK2 copies carried the variant in that specimen. It does not automatically mean 1% of all cells are affected: cell mixture, gene-copy number and whether cells carry one or more variant copies can change the relationship.
For a simplified hypothetical example, if every relevant cell has two JAK2 copies and each affected cell has one variant copy, a 1% VAF could correspond to roughly 2% affected cells. Real clinical samples may not satisfy those assumptions.
Very small clones may represent کلونل هیماتوپویزس, a finding that can occur without an established blood cancer. A hematologist may review count trends and the original assay rather than label a low result benign or malignant from its percentage alone; see our guide to کیفیتي او کمي پایلې.
د کشف حدونه د JAK2 پر پایلو څه اغېز کوي؟
A JAK2 assay detects variants only within its validated coverage and sensitivity. A result close to the laboratory’s detection or quantification limit may be less precise than a higher-level result, even when the finding is real.

د limit of detection is the lowest level at which an assay can reliably detect a variant under its validation conditions. The limit of quantification concerns reliable measurement of its amount; the two limits can differ.
Hypothetically, a laboratory with a 0.1% detection limit could detect a clone missed by an assay with a 1% limit. This comparison only applies if both assays cover the same variant and use suitable specimens.
Reports may say “detected below the quantifiable range,” give a percentage, or provide only a positive/negative answer. Kantesti can help organize those terms, but the laboratory’s own method notes remain the reference; our د AI ټکنالوژۍ لارښود explains the platform’s general approach.
د JAK2 د بدلون منفي پایله څه معنا لري؟
A JAK2 mutation negative result means no covered variant was detected above that test’s reporting limit. It does not exclude every MPN, every JAK2 variant or a clone below the assay’s sensitivity.

A negative V617F result is less supportive of polycythemia vera because about 95% of diagnosed cases carry V617F, but exon 12 variants account for many of the remaining cases. The next test depends on the clinical pattern and what the first assay actually covered.
Essential thrombocythemia and primary myelofibrosis can be associated with CALR یا MPL variants instead of JAK2 V617F. Some patients have none of these three common driver variants detected, sometimes described as درېګوني منفي وي.
A report can be negative, indeterminate or technically unsuccessful; those are different outcomes. Ask the ordering team whether the specimen was adequate and whether genetic panel limitations affect the interpretation.
د JAK2 د پایلې وروسته کومې ازموینې کېدای شي ترسره شي؟
Follow-up testing can include repeat blood counts, a blood-film review, erythropoietin, iron studies, additional molecular tests and sometimes a bone marrow examination. The choice depends on whether the main finding involves red cells, platelets, white cells or unexplained symptoms.

When platelets remain at or above 450 × 10⁹/L, clinicians may assess iron status and inflammation as well as consider CALR and MPL testing. A raised platelet count is not specific for an MPN.
A marrow examination can distinguish patterns that a molecular result cannot, including essential thrombocythemia from prefibrotic primary myelofibrosis. The decision to perform one is individualized and depends on the diagnostic question.
A blood film may reveal immature cells or unusual shapes. Our guide to teardrop cells on a smear explains why such findings need context rather than automatic attribution to myelofibrosis.
ایا د اوسپنې کمښت یا د بدن د اوبو کمښت انځور بدلولی شي؟
Iron deficiency can make red cells smaller and may obscure the degree of red-cell overproduction, while dehydration can make a blood count appear concentrated. Both can complicate the evaluation of suspected polycythemia vera.
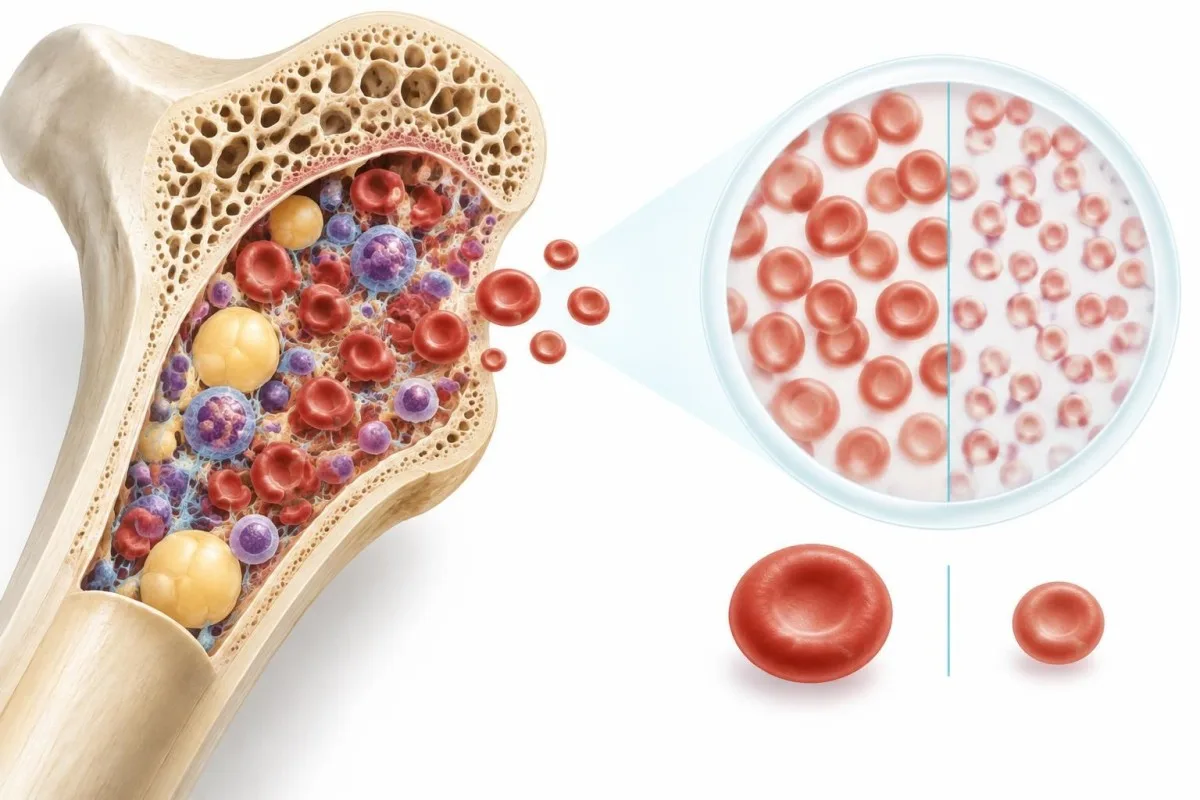
Low mean corpuscular volume, or ایم سي وي, can accompany iron deficiency. In a compatible clinical setting, a high red-cell count with small cells may deserve closer review even when hemoglobin is not strikingly elevated.
A hypothetically dehydrated patient may have a raised hematocrit because plasma volume is reduced, not because the body has produced excess red cells. A clinician can assess the history and decide when a repeat count is appropriate.
د د اوسپنې د مطالعاتو لارښود explains how ferritin, transferrin saturation and related measurements fit together. Do not start or stop iron solely because of a JAK2 result; ask the clinician managing the workup.
ایا د JAK2 بدلون د کورنۍ غړو ته په میراث رسېږي؟
JAK2 V617F and the exon 12 variants discussed in MPN testing are usually acquired, or somatic, changes in blood-forming cells rather than inherited variants present throughout the body. A positive result does not automatically mean children or siblings carry the same variant.
A family history of MPNs can still matter because inherited factors may affect susceptibility in some families. That is distinct from directly passing on the acquired V617F variant found in a blood-cell clone.
Blood-based testing alone can be difficult to use for determining whether some variants are inherited when a person has a myeloid disorder. If an inherited predisposition is suspected, a specialist can select appropriate testing and a suitable non-blood tissue source.
For contrast, our article on BRCA genetic results discusses inherited cancer-predisposition testing. It should not be treated as an interpretation guide for an acquired JAK2 result.
ایا د JAK2 مثبته پایله دا معنا لري چې د وینې لخته به رامنځته شي؟
A positive JAK2 result does not mean a blood clot will occur, although JAK2-associated MPNs can increase clotting risk. Risk assessment depends on the established diagnosis, prior clotting, age and other clinical factors—not the molecular result alone.
In polycythemia vera, clinicians commonly consider age over 60 کلونو and a history of thrombosis when assessing risk. Other factors, including the blood count and cardiovascular risks, can influence individual management.
Do not begin aspirin, anticoagulants or phlebotomy solely because a JAK2 report is positive. These interventions have benefits and risks that require a diagnosis-specific plan.
New one-sided leg swelling can be a sign of deep vein thrombosis and needs prompt medical assessment. Sudden chest pain, severe breathlessness, facial droop, arm weakness or speech difficulty warrants emergency services.
د JAK2 تکراري ازموینه کله ګټوره کېدای شي؟
Repeat JAK2 testing may be useful when a result is near an assay’s limit, the sample was inadequate, the clinical picture changes or a specialist needs to clarify discordant findings. There is no universal retest interval for every positive or negative result.

Two VAF values from different laboratories may not be directly comparable if their methods, specimen types or reporting limits differ. A change from 0.2% to 0.3%, for example, may be hard to interpret without knowing measurement uncertainty.
For someone receiving MPN treatment, the clinician may request molecular monitoring for a specific reason; VAF should not be used alone to change medication or predict an individual outcome. Blood counts, symptoms and the treatment plan still matter.
Kantesti is an AI biomarker interpretation platform that can help readers organize dated results for review, but it cannot validate whether two JAK2 assays are interchangeable. Our دليل توقيت اختبارات الدم covers practical comparison questions.
بل څه باید له خپل ډاکټر سره په اړه خبرې وکړئ؟
Bring the complete JAK2 report and recent blood counts to the ordering clinician, and ask whether a hematology referral is appropriate. The immediate next step depends on the variant, blood-count pattern, symptoms and reason for testing.

Ask four practical questions: Which variant was tested? Was the result qualitative or quantitative? What were the assay’s detection and quantification limits? Were exon 12, CALR or MPL variants included or tested separately?
Take prior complete blood counts, iron results, a medication list and any history of clotting or unusual bleeding. For example, a platelet count that has stayed above 450 × 10⁹/L across repeated tests tells a different story from a single raised count during an acute illness.
Kantesti can help organize a PDF or photo of laboratory results, but an AI explanation is not a diagnosis or a reason to delay specialist care. Read our د طبي تایید معلومات for the platform’s stated approach and limitations.
پرله پسې پوښتل شوي پوښتنې
ایا د JAK2 V617F مثبتې پایلې معنا دا ده چې سرطان لرم؟
د JAK2 V617F مثبته پایله په یوازې ځان دا نه ثابتوي چې تاسو سرطان لرئ. دا جنیټیک بدلون په مایلوپرولیفریټیف نیوپلازمونو کې عام دی، او د پولیسایتیمیا ورا د پېښو نږدې 95% کې موندل کېږي، خو د وینې د حجرو په یوه کوچني کلون کې هم د تثبیت شوي MPN له شتون پرته موندل کېدای شي. ډاکټر یې د وینې د حجرو شمېر، نښو او کله ناکله د هډوکي د مغز د معاینې ترڅنګ تفسیر کوي.
ایا د JAK2 ازموینه مې منفي وي، بیا هم MPN لرلای شم؟
هو. د JAK2 منفي پایله ټول مایلوپرولیفراټیف نیوپلازمونه نه ردوي، او یوازې د V617F ازموینه د JAK2 اېکسون 12 بدلون نه ردوي. د اساسي ترومبوسایتمیا او لومړني مایلوفایبروسیس شاوخوا نیمایي پېښې د JAK2 V617F بدلون لري؛ په نورو کې د CALR یا MPL ډولونه موندل کېدای شي، یا له دغو دریو څخه هېڅ یو ونه موندل شي. وپوښتئ چې ستاسو ازموینې کوم ډولونه پوښلي او ایا نورې ازموینې ستاسو د وینې د حجرو د شمېر له بڼې سره سمون لري.
ایا د JAK2 الیل بار ۱٪ جدي دی؟
د JAK2 د بدیل الیل ۱٪ سلنه په دې معنا ده چې په ازمویل شوې نمونه کې د JAK2 د DNA شاوخوا له هر ۱۰۰ کاپیو څخه یوې دا بدیل درلود. یوازې دا پایله د ناروغۍ شدت نه ښيي، د یوه کس پایله نه اټکلوي او نه هم دا معنا لري چې ۱٪ حجرې اغېزمنې دي. د کشف طریقه، د وینې د حجرو شمېر، نښې نښانې او دا چې د MPN تشخیص شوی که نه، ټول مهم دي. د ټیټې کچې پایله له هغه ډاکټر سره وڅېړئ چې ازموینه یې غوښتې وه، پر ځای د دې چې بېضرره یا خطرناکه یې وګڼئ.
د JAK2 V617F او اېکسون ۱۲ ترمنځ څه توپیر دی؟
JAK2 V617F یو ځانګړی واریانت دی، په داسې حال کې چې JAK2 اېکسون ۱۲ هغې سیمې ته اشاره کوي چېرې چې څو بېلابېل واریانتونه رامنځته کېدای شي. V617F د پولیسېتمیا ویرا په شاوخوا 95% پېښو کې موندل کېږي او په اساسي ترومبوسایتمیا او لومړني میلوفایبروسس کې هم رامنځته کېږي. د اېکسون ۱۲ واریانتونه په ځانګړې توګه د V617F-منفي پولیسېتمیا ویرا لپاره مهم دي. یوازې د V617F ازموینه ښايي اېکسون ۱۲ ونه ارزوي.
ایا د JAK2 بدلون خپلو ماشومانو ته لېږدولای شم؟
هغه بدلونونه چې د MPN د ارزونې پر مهال په JAK2 V617F او اېکسون ۱۲ کې موندل کېږي، معمولاً د وینې جوړوونکو حجرو کې ترلاسه شوي وي، نه دا چې په میراث کې لېږدېدلي وي. له همدې امله، مثبته پایله دا معنا نه لري چې ماشوم هماغه بدلون په میراث کې اخیستی دی. په ځینو کورنیو کې د MPNs پر وړاندې د استعداد کچه لوړه وي؛ نو د وینې د ناروغیو د کورنۍ مخینه له خپل ډاکټر سره شریکه کړئ. د جنیټیک متخصص مشوره درکولای شي چې ایا د موروثي خطر ازموینه مناسبه ده که نه.
ایا د JAK2 د مثبتې پایلې له ترلاسه کولو وروسته باید اسپرین پیل کړم؟
یوازې د JAK2 د مثبتې ازموینې له امله اسپرین مه پیلوئ. د درملنې پرېکړې پر دې پورې اړه لري چې ایا د MPN تشخیص شوی، فرعي ډول یې څه دی، د وینېبهېدنې خطر څومره دی، او عمر او د پخوانۍ ترومبوز پېښې په څېر عوامل څه دي. د بېلګې په توګه، تر ۶۰ کلونو پورته عمر د پولیسیتمیا ویرا د خطر په ارزونه کې یو له هغو عواملو څخه دی چې کارول کېږي، خو دا د خپلسري درملخوړلو لارښوونه نه ده. له خپل ډاکټر څخه د ځان لپاره د درملنې د پلان غوښتنه وکړئ.
د وینې ازموینې پایلې څنګه ولولئ
خپل لابراتواري راپور پورته کړئ، او د Kantesti AI به په څو ثانیو کې هر بایومارکر په ساده ژبه تشریح کړي. په ټوله نړۍ کې له 2 میلیونو څخه زیاتو کسانو ترې کار اخیستی.
ماخذونه
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د AI وینې د ازموینې شنونکی: 2.5M ازموینې تحلیل شوې | د نړیوال روغتیا راپور 2026. د Kantesti AI طبي څېړنه. د دفاع وزارت
- کلاین، ټي.، میچل، ایس.، او وېبر، ایچ. (۲۰۲۶). د RDW د وینې ازموینه: د RDW-CV، MCV او MCHC بشپړ لارښود. د Kantesti AI طبي څېړنه. د دفاع وزارت
- Arber DA et al. (2022). International Consensus Classification of Myeloid Neoplasms and Acute Leukemias: integrating morphologic, clinical, and genomic data. Blood. د دفاع وزارت
- Scott LM et al. (2007). JAK2 Exon 12 Mutations in Polycythemia Vera and Idiopathic Erythrocytosis. د نیو انګلنډ د طب ژورنال. د دفاع وزارت
- ۲ میلیونه+تحلیل شوې ازموینې
- 127+هېوادونه
- 100+ژبې
د طبي ټیم په اړه


د E-E-A-T باور نښې
تجربه
د ډاکټر تر مشرۍ لاندې کلینیکي بیاکتنه د لابراتواري تفسیر د کاري بهیرونو لپاره.
تخصص
د لابراتواري طب تمرکز پر دې چې بایومارکرونه په کلینیکي شرایطو کې څنګه چلند کوي.
واک ورکول
د ډاکټر توماس کلاین له خوا طبي بیاکتنه شوې، د ډاکټر سارا میچل او پروفیسور ډاکټر هانس وېبر په مرسته.
اعتبار
د شواهدو پر بنسټ تفسیر د روښانه تعقیبي لارو چارو سره، تر څو اندیښنه کمه شي.



طبي سلبِ مسئولیت
دا مقاله یوازې د زده کړې لپاره ده او طبي مشوره نه جوړوي. د تشخیص او درملنې د پرېکړو لپاره تل د وړ روغتیايي خدمت وړاندې کوونکي سره سلا وکړئ.
خپور شوی · له تحریري ټیم سره اړیکه ونیسئ
خپروونکی یې Kantesti Ltd دی، چې په انګلستان او وېلز کې ثبت شوی، د شرکت شمېره. 17090423, ، لندن، بریتانیا.
